Sardines — Vitamin D and B12
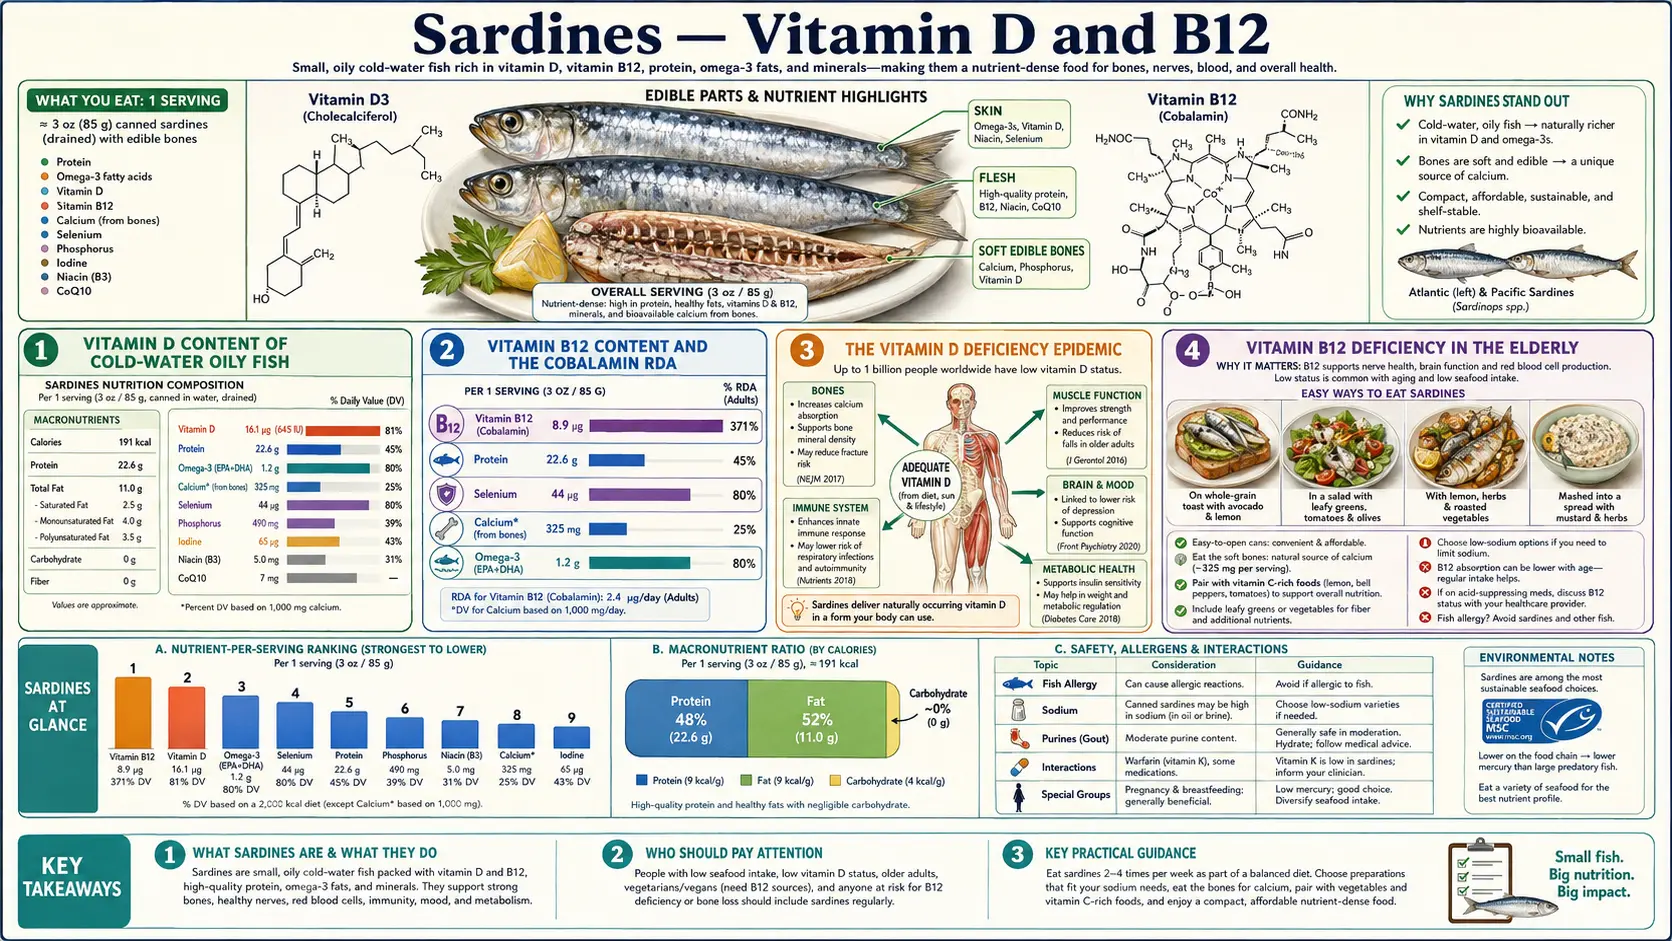
Vitamin D and Vitamin B12 are the two micronutrients most commonly inadequate in adult populations in the developed world. In US national survey data for 2011-2014, 5.0% of people aged 1 year and older were at risk of Vitamin D deficiency (serum 25-hydroxyvitamin D below 30 nmol/L, about 12 ng/mL) and 18.3% at risk of inadequacy (30-49 nmol/L). In large US and UK surveys, about 6% of people aged 60 and older are Vitamin B12 deficient and closer to 20% have marginal status in later life — with risk rising with age, metformin use, proton-pump-inhibitor use, atrophic gastritis, and vegan diet. The U.S. Department of Agriculture (USDA) lists canned sardines at 193 international units (IU) Vitamin D3 (cholecalciferol) and 8.94 micrograms Vitamin B12 (cobalamin) per 100 g — more than the adult B12 Recommended Dietary Allowance (RDA) of 2.4 micrograms. Practitioners describe two to three tins per week as a way to support B12 status and add to Vitamin D intake alongside seasonal sun exposure and supplements. This page covers the populations at highest risk, the laboratory monitoring strategy, and why food-source D3 and B12 from sardines is particularly valuable for the elderly and for patients on chronic gastric-acid-suppression therapy.
Table of Contents
- Vitamin D Content of Cold-Water Oily Fish
- Vitamin B12 Content and the Cobalamin Recommended Dietary Allowance
- The Vitamin D Deficiency Epidemic
- Vitamin B12 Deficiency in the Elderly
- Metformin and Proton Pump Inhibitor as B12-Depleting Drugs
- Laboratory Monitoring (25-OH-D, Methylmalonic Acid, Homocysteine)
- Supplement vs Food-Source Considerations
- The Vegan-to-Pescatarian Transition
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Vitamin D Content of Cold-Water Oily Fish
Cold-water oily fish synthesize Vitamin D3 (cholecalciferol) in their tissues from 7-dehydrocholesterol precursors. The fish do not need ultraviolet-B exposure for this synthesis the way humans do — the conversion occurs in their liver and is concentrated in fatty tissues. The biological function appears to be calcium regulation analogous to human Vitamin D physiology.
U.S. Department of Agriculture-listed Vitamin D content per 100 g for common fish:
- Wild salmon — 500-988 international units (the absolute leader; varies with species and season)
- Farmed salmon — 250-526 international units (lower due to feed composition; varies by producer)
- Mackerel — 360-643 international units
- Herring (kippered, pickled) — 200-450 international units
- Canned sardines (in oil) — 165-272 international units (varies by season and species)
- Canned tuna — 234 international units (albacore higher than skipjack)
- Cod — 36 international units (low; cod is a lean fish with most D in the liver, hence cod liver oil)
- Tilapia — 124 international units
- Cod liver oil (1 tsp) — 450-1,360 international units (and 2,500-5,000 international units Vitamin A, which is its own consideration)
USDA FoodData Central lists canned Atlantic sardines in oil (drained solids with bone) at 193 international units (4.8 micrograms) Vitamin D3 per 100 g, and gives the drained weight of a 3.75 oz can as 92 g; the amount varies with brand and season. The Institute of Medicine (IOM) Recommended Dietary Allowance for Vitamin D is 600 international units a day for ages 1-70 and 800 international units a day from age 71. Sardines alone are a meaningful but partial source. Many practitioners describe fall and winter supplementation of 1,000-2,000 international units/day Vitamin D3 for US adults living north of 35°N latitude, aiming for serum 25-OH-D in the 30-50 ng/mL range. Sardines and salmon contribute the food-source baseline that reduces the supplementation requirement.
Vitamin B12 Content and the Cobalamin Recommended Dietary Allowance
Vitamin B12 (cobalamin) is produced exclusively by bacteria. Animals acquire B12 either by consuming other animals (predators, carnivores), by consuming the bacteria themselves (ruminants harvesting B12 from fermentation in the rumen), or by consuming B12-rich animal tissues (organs, fish, eggs, dairy). Fish concentrate B12 in their liver, kidney, and muscle — sardines, being eaten whole with viscera in some preparations, are particularly B12 dense.
U.S. Department of Agriculture-listed Vitamin B12 content per 100 g:
- Beef liver — 70.6 µg braised, 83.1 µg pan-fried (2,900% Recommended Dietary Allowance)
- Clams (cooked) — 98.9 µg
- Oysters — 16-28 µg
- Wild salmon — 3.2 µg
- Canned sardines — 8.9 µg (370% Recommended Dietary Allowance in one 100 g serving)
- Canned tuna — 2.5 µg
- Beef (chuck roast) — 5.8 µg
- Eggs (one large) — 0.45 µg
- Milk (1 cup) — 1.1 µg
- Cheddar cheese (1 oz) — 0.2 µg
- Plant foods (any) — 0 µg (the strict zero is the key distinguishing feature)
USDA lists 8.94 µg of B12 per 100 g of drained canned sardines (a 3.75 oz can holds 92 g drained) — well above the adult Recommended Dietary Allowance of 2.4 µg. The body absorbs roughly 50% of the B12 in food (limited by intrinsic factor binding capacity).
For frequent sardine consumers, B12 deficiency from dietary inadequacy is essentially impossible — the limiting factor becomes absorption capacity, not intake. This is clinically meaningful because the populations at highest B12 risk (elderly, atrophic gastritis, proton pump inhibitor (PPI)/metformin users) suffer primarily from absorption failure rather than intake inadequacy, which is addressed in the next sections.
The Vitamin D Deficiency Epidemic
National Health and Nutrition Examination Survey (NHANES) data for 2011-2014 (16,180 people aged 1 year and older) found 5.0% at risk of Vitamin D deficiency (serum 25-hydroxyvitamin D below 30 nmol/L, about 12 ng/mL) and 18.3% at risk of inadequacy (30-49 nmol/L); the share at risk of deficiency was 17.5% among non-Hispanic Black people. The IOM set 20 ng/mL (50 nmol/L) as the level that meets the needs of at least 97.5% of the population, and concluded that the prevalence of Vitamin D inadequacy in North America has been overestimated. Many endocrinologists consider 30 ng/mL or higher optimal; by that threshold, 60-80% of US adults are reported to fall short. The deficit is greater in:
- Black and Hispanic populations (skin melanin reduces cutaneous synthesis)
- Northern latitude residents (insufficient ultraviolet-B during winter months)
- Indoor workers and sunscreen users
- Adults over 65 (cutaneous 7-dehydrocholesterol concentration declines with age, halving synthesis capacity)
- Obesity (Vitamin D sequesters in adipose tissue, reducing serum availability)
- Malabsorption (celiac, Crohn's, cystic fibrosis, post-bariatric surgery)
- Chronic kidney disease (reduced 1-alpha-hydroxylase activity)
- Veiled populations (limited skin exposure to ultraviolet-B)
The clinical consequences of long-term Vitamin D insufficiency include impaired calcium absorption (leading to secondary hyperparathyroidism and bone resorption), increased fall and fracture risk, increased susceptibility to upper respiratory infections, and (in observational but not all randomized data) increased risk of cardiovascular events, autoimmune disease, and certain cancers.
Practitioners commonly describe a three-pronged approach: dietary intake from oily fish (sardines, salmon, herring), seasonal sun exposure when possible (10-30 minutes midday spring/summer/fall on arms and legs without sunscreen), and targeted supplementation (1,000-2,000 international units/day Vitamin D3 for most adults; 4,000-5,000 international units/day for adults with documented severe deficiency, monitored by serum 25-OH-D every 3-6 months). Sardines contribute approximately 50-80 international units/day averaged across the week with 2-3 tins — not enough alone but a meaningful contribution to the food-source baseline.
The 2024 Endocrine Society clinical practice guideline suggests extra Vitamin D (above the Dietary Reference Intakes, without blood testing) for children and adolescents aged 1-18, adults aged 75 and older, pregnant people, and people with high-risk prediabetes. It suggests against Vitamin D above the current Dietary Reference Intakes (the IOM’s 600 international units a day up to age 70, 800 from age 71) to lower disease risk in healthy adults younger than 75, and against routine 25-OH-D blood testing, because no clinical trial evidence was found to support routine screening and there was no clear evidence defining the optimal blood level for disease prevention. The panel noted that the best doses for the groups it named remain unclear.
For more on Vitamin D testing, dosing, and the optimal range debate, see our Vitamin D3 page.
Vitamin B12 Deficiency in the Elderly
B12 deficiency prevalence rises with age. A 2009 review of large surveys in the United States and the United Kingdom reports:
- ~6% of people aged 60 and older are B12 deficient (plasma B12 below 148 pmol/L), with the share increasing with age
- Closer to 20% have marginal status (plasma B12 148-221 pmol/L) in later life
- ~40% of adults over 60 have biochemical evidence of B12 deficiency (elevated methylmalonic acid or homocysteine) even with apparently normal serum B12
The mechanism is not dietary inadequacy — elderly adults typically consume adequate dietary B12. The issue is absorption failure. B12 absorption requires:
- Adequate gastric acid to liberate B12 from food-protein binding
- Intrinsic factor produced by gastric parietal cells
- Intact ileum with cubilin-amnionless receptor complex for intrinsic factor (IF)-B12 complex uptake
Atrophic gastritis (loss of parietal cells, common in the elderly) reduces both gastric acid and intrinsic factor. Pernicious anemia (autoimmune destruction of parietal cells) eliminates intrinsic factor entirely. Ileal resection (Crohn's surgery, bariatric surgery with intestinal bypass) eliminates the absorption site.
The clinical consequences of unrecognized B12 deficiency are serious and partially irreversible: peripheral neuropathy (paresthesia, loss of vibratory sense, gait instability), megaloblastic anemia, cognitive impairment ranging from subtle to frank dementia, and subacute combined degeneration of the spinal cord. The cognitive impairment in particular is often misdiagnosed as Alzheimer's disease in elderly patients — one of the most rewarding diagnoses to make because it is reversible with B12 repletion if caught early.
Some practitioners describe screening serum B12 (and ideally methylmalonic acid) in all adults over 65, with the threshold for repletion set higher than standard laboratory cutoffs. The conservative threshold they use for considering B12 supplementation or sublingual B12 is serum B12 below 400 pg/mL or any elevation of methylmalonic acid (MMA) above 0.27 µmol/L.
Regular sardine consumption (2-3 tins per week) adds dietary B12 but does not bypass the absorption problem for patients with severe atrophic gastritis or pernicious anemia. Options described for those patients are sublingual B12 (1,000-2,000 µg/day), intranasal cyanocobalamin spray, or intramuscular methylcobalamin injections (1,000 µg monthly).
Metformin and Proton Pump Inhibitor as B12-Depleting Drugs
Two extremely common medications reliably produce B12 depletion over time:
- Metformin — the first-line oral diabetes medication, taken by approximately 90 million Americans. Metformin interferes with calcium-dependent B12-intrinsic factor uptake in the ileum. In a randomised placebo-controlled trial of 390 people with type 2 diabetes on insulin, 850 mg metformin three times a day for 4.3 years lowered B12 by 19% compared with placebo; B12 deficiency (below 150 pmol/L) was 7.2 percentage points more common than on placebo (one extra case for every 13.8 people treated over 4.3 years), and low B12 (150-220 pmol/L) 11.2 points more common. The current U.S. metformin label (section 5.2) reports that in 29-week clinical trials about 7% of patients whose B12 had been normal fell to subnormal levels, a drop that “appears to be rapidly reversible” when metformin is stopped or B12 is given, and it lists measuring blood counts (hematologic parameters) once a year and vitamin B12 every 2 to 3 years. Some practitioners start supplementation when serum B12 falls below 400 pg/mL.
- Proton pump inhibitors (PPIs) — omeprazole, esomeprazole, pantoprazole, lansoprazole, dexlansoprazole, rabeprazole. Proton pump inhibitors suppress gastric acid production, reducing the gastric-acid-dependent release of B12 from food protein. Long-term use (>2 years) is associated with B12 deficiency in observational studies. The deficiency risk increases with both dose and duration. In a case-control study in a California health-plan population, comparing 25,956 people newly diagnosed with B12 deficiency with 184,199 people without it, a 2-year-or-longer supply of proton pump inhibitors was linked to 65% higher odds of B12 deficiency (odds ratio 1.65) and a 2-year-or-longer supply of H2-blockers to 25% higher odds (odds ratio 1.25); more than 1.5 proton pump inhibitor pills a day was more strongly linked (odds ratio 1.95) than less than 0.75 pills a day (odds ratio 1.63).
Other B12-depleting medications include H2-blockers (famotidine, cimetidine — same mechanism as proton pump inhibitors but less potent; ranitidine was withdrawn from the US market at the U.S. Food and Drug Administration (FDA)’s request on April 1, 2020 over the contaminant N-nitrosodimethylamine (NDMA)), colchicine, neomycin, chloramphenicol, and nitrous oxide (a one-time exposure during anesthesia can precipitate frank B12 deficiency in patients with marginal status).
For patients on metformin or chronic proton pump inhibitor therapy, dietary sardine consumption provides high-dose B12 in a form that may partially bypass the absorption block (the high concentration in a single meal saturates intrinsic factor capacity and allows some passive diffusion in the ileum). Some practitioners describe three sardine tins per week plus 1,000 µg sublingual cyanocobalamin daily for high-risk patients. The metformin label lists blood counts once a year and vitamin B12 every 2 to 3 years.
Laboratory Monitoring (25-OH-D, Methylmalonic Acid, Homocysteine)
The relevant blood tests for monitoring sardines-as-a-strategy for D and B12 adequacy:
- Serum 25-hydroxyvitamin D (25-OH-D) — the standard Vitamin D status test. Insurance coverage is variable but the cash price is $30-60. Target range debated:
- <20 ng/mL: below the level (20 ng/mL) the IOM found meets the needs of at least 97.5% of people
- 20-30 ng/mL: labelled insufficiency by some groups
- 30-50 ng/mL: considered optimal by many practitioners; the 2024 Endocrine Society guideline found no clear evidence defining an optimal target level for disease prevention
- 50-80 ng/mL: high-normal, well-tolerated
- >100 ng/mL: potential toxicity
- Serum Vitamin B12 (cobalamin) — the standard screening test, with substantial limitations:
- <200 pg/mL: frank deficiency
- 200-400 pg/mL: marginal status, suggesting methylmalonic acid and homocysteine assessment
- >400 pg/mL: generally adequate
- The test does not distinguish between active methylcobalamin and inactive analogs; up to 30% of patients with biochemical deficiency have apparently normal serum B12
- Methylmalonic acid (MMA) — the most sensitive marker of functional B12 deficiency. B12 is required for the methylmalonyl-CoA mutase reaction; deficiency causes methylmalonic acid accumulation. Elevation above 0.27 µmol/L (or 270 nmol/L) is suspicious; above 0.40 µmol/L is highly specific for B12 deficiency.
- Homocysteine — elevated in both B12 deficiency and folate deficiency. Useful as a secondary marker but not specific to B12.
- Holotranscobalamin (active B12) — the fraction of serum B12 bound to transcobalamin II that is bioavailable to tissues. Newer test, not widely available; may eventually replace serum B12 as the screening test.
Practitioners who track a sardine-based dietary strategy describe a baseline panel of 25-OH-D, serum B12, methylmalonic acid, and homocysteine, repeated at 3-6 months to document the response. The 2024 Endocrine Society guideline suggests against routine 25-OH-D testing in people without an established reason for it.
Supplement vs Food-Source Considerations
For Vitamin D, food-source intake from sardines, salmon, and other oily fish is meaningful but typically insufficient alone for most adults living north of 35°N latitude. The realistic strategy combines food-source D3 (50-150 international units/day averaged) with seasonal sun exposure when possible and 1,000-2,000 international units/day supplemental D3 in fall/winter or year-round for indoor workers. Vitamin D3 (cholecalciferol) supplements are inexpensive ($5-10 for a year's supply), shelf-stable, and well-tolerated. There is no clear advantage of food-source over supplemental D3 from a biochemistry standpoint — both are converted to 25-OH-D in the liver and 1,25-(OH)2-D in the kidney through identical pathways.
For B12, the food-source vs supplement distinction is more nuanced. The intrinsic-factor-mediated absorption pathway has limited capacity (approximately 1.5-2 µg per meal). High-dose supplements (1,000-2,000 µg/day) saturate this pathway but also produce some passive diffusion across the intestinal wall (estimated 1% of the dose). For patients with intact gastrointestinal (GI) function, dietary B12 from fish, meat, eggs, and dairy is more than adequate. For patients with absorption failure (atrophic gastritis, pernicious anemia, proton pump inhibitor/metformin users, post-bariatric), high-dose oral or sublingual supplementation is necessary, and dietary B12 alone is not sufficient.
The form of supplemental B12 matters. Cyanocobalamin is the cheapest and most stable form but requires conversion to methylcobalamin or adenosylcobalamin in the body. Methylcobalamin and adenosylcobalamin (or "methyl-B12") are the active coenzyme forms and bypass the conversion step. Hydroxocobalamin (used clinically as an antidote for cyanide poisoning) is also effective. For most patients, generic cyanocobalamin is fine; patients with methylenetetrahydrofolate reductase (MTHFR) polymorphisms or those who prefer the active form can use methylcobalamin at modestly higher cost.
The Vegan-to-Pescatarian Transition
Long-term strict vegans (vegetable matter only, no dairy, eggs, or fish) reliably develop B12 deficiency if they do not supplement — usually within 3-5 years for adults, faster for children. In the European Prospective Investigation into Cancer and Nutrition (EPIC)-Oxford study of 689 British men, mean serum B12 was 281 pmol/L in meat-eaters, 182 pmol/L in vegetarians and 122 pmol/L in vegans; 52% of vegans, 7% of vegetarians and one meat-eater were classed as B12 deficient (below 118 pmol/L). Age and time on a vegetarian or vegan diet were not linked to serum B12 in that study.
Many vegans choose to remain vegan and supplement reliably with fortified plant milks (B12-fortified), nutritional yeast (B12-fortified), and explicit B12 supplements. This strategy works when followed consistently; the failure mode is intermittent supplementation that allows depletion of liver B12 stores over years.
Some long-term vegans choose to transition to a "pescatarian" pattern — including fish (and often eggs and dairy) while continuing to avoid land animals. The motivations vary (resolving B12 or omega-3 deficiency, addressing low-energy or cognitive symptoms, ethical evolution). For these patients, sardines are an ideal entry point:
- The smallest, least sentient marine organism in the human food chain
- Sustainable harvest with minimal environmental impact
- The most ethical-acceptable option for many people transitioning from strict veganism
- The highest single-food density of the two micronutrients (D and B12) most likely to be depleted
- The lowest toxin and contaminant burden
- Calcium-replete (addressing the calcium gap if dairy is also being avoided)
- Omega-3-replete (addressing the eicosapentaenoic acid (EPA)/docosahexaenoic acid (DHA) gap that alpha-linolenic acid (ALA) from flax and walnut does not adequately fill)
Practitioners describe a transition that begins with 1 tin per week while people judge tolerance, taste, and any psychological or ethical considerations, rising to 2-3 tins per week over 4-8 weeks, with serum B12, methylmalonic acid, and 25-OH-D checked before and 3-6 months after the transition. They report that most people see methylmalonic acid normalize and 25-OH-D rise meaningfully within 3 months.
Cautions
- Vitamin D toxicity — cannot occur from food-source D from sardines alone. A 2018 clinical review describes Vitamin D toxicity as usually caused by inadvertent or improper intake of extremely high doses of Vitamin D preparations, with serum 25-OH-D above 150 ng/mL (375 nmol/L) as its hallmark and severe high blood calcium (hypercalcemia) as its main feature; the same review notes that people with hypersensitivity to Vitamin D can develop symptom-free hypercalcemia even at doses recommended for the general population. Sardine consumption at any practical level is safe.
- Vitamin B12 toxicity — B12 has no established upper limit; the body excretes excess B12 in urine. The pink color of high-dose B12 supplement urine is harmless. Sardine consumption at any practical level is safe.
- Hidden Vitamin A in sardines — sardines do contain some Vitamin A (32 micrograms retinol activity equivalents (RAE) per 100 g, per USDA), much less than beef liver or cod liver oil. Not a teratogenicity concern at any reasonable intake level.
- B12-folate masking — high folate intake (often from folic-acid-fortified grains) can correct the megaloblastic anemia of B12 deficiency while allowing the neurological damage to progress unrecognized. For this reason, practitioners use methylmalonic acid or holotranscobalamin testing when B12 deficiency is suspected, regardless of folate or hemoglobin status.
- Drug interactions with sardine fortification of B12 — none. Sardine B12 follows the same absorption pathway as any food-source B12.
- The Vitamin D supplementation controversy — the VITAL trial and other large randomized controlled trials (RCTs) have not shown clear cardiovascular or cancer prevention benefit from Vitamin D supplementation in already-replete adults. The benefit appears confined to patients with documented insufficiency. The argument for sardine consumption is not "as much as possible" — it is to maintain the food-source baseline alongside testing and targeted supplementation.
Key Research Papers
- Holick MF (2007). Vitamin D deficiency. NEJM. — PubMed PMID: 17634462
- Allen LH (2009). How common is vitamin B-12 deficiency? American Journal of Clinical Nutrition. — PubMed PMID: 19116323
- Stabler SP (2013). Clinical practice. Vitamin B12 deficiency. NEJM. — PubMed PMID: 23301732
- de Jager J et al. (2010). Long term treatment with metformin in patients with type 2 diabetes and risk of vitamin B-12 deficiency: randomised placebo controlled trial. BMJ. — PubMed PMID: 20488910
- Lam JR et al. (2013). Proton pump inhibitor and histamine 2 receptor antagonist use and vitamin B12 deficiency. JAMA. — PubMed PMID: 24327038
- Manson JE et al. (2019). Vitamin D Supplements and Prevention of Cancer and Cardiovascular Disease (VITAL). NEJM. — PubMed PMID: 30415629
- Lips P (2007). Vitamin D physiology. Progress in Biophysics and Molecular Biology. — PubMed
- Pawlak R et al. (2013). How prevalent is vitamin B12 deficiency among vegetarians? Nutrition Reviews. — PubMed PMID: 23356638
- Wang H et al. (2013). Efficacy of vitamin B supplementation on cognition in elderly patients with cognitive-related diseases: meta-analysis. Journal of Geriatric Psychiatry and Neurology. — PubMed
- Carmel R (2011). Biomarkers of cobalamin (vitamin B-12) status in the epidemiologic setting. American Journal of Clinical Nutrition. — PubMed
- Smith AD et al. (2010). Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment. PLoS ONE. — PubMed
- Pittas AG et al. (2019). Vitamin D Supplementation and Prevention of Type 2 Diabetes (D2d). NEJM. — PubMed PMID: 31173679
- Ross AC et al. (2011). The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. Journal of Clinical Endocrinology and Metabolism. — PubMed PMID: 21118827
- Herrick KA et al. (2019). Vitamin D status in the United States, 2011-2014. American Journal of Clinical Nutrition. — PubMed PMID: 31076739
- Demay MB et al. (2024). Vitamin D for the Prevention of Disease: An Endocrine Society Clinical Practice Guideline. Journal of Clinical Endocrinology and Metabolism. — PubMed PMID: 38828931
- Gilsing AM et al. (2010). Serum concentrations of vitamin B12 and folate in British male omnivores, vegetarians and vegans: results from a cross-sectional analysis of the EPIC-Oxford cohort study. European Journal of Clinical Nutrition. — PubMed PMID: 20648045
- Marcinowska-Suchowierska E et al. (2018). Vitamin D Toxicity-A Clinical Perspective. Frontiers in Endocrinology. — PubMed PMID: 30294301
PubMed Topic Searches
Connections
- All Food
- Sardines Overview
- Sardines Benefits Hub
- Sardines — Calcium & Bones
- Sardines — Omega-3 Density
- Sardines — Low Mercury
- Vitamin D3
- Vitamin B12
- Folate (Vitamin B9)
- 25-Hydroxyvitamin D Test
- Vitamin B12 Test
- Methylmalonic Acid Test
- Homocysteine Test
- Anemia
- Peripheral Neuropathy
- Type 2 Diabetes (Metformin)
- Gastroesophageal Reflux Disease (Proton Pump Inhibitor Use)
- History
- Nutrients