Urinary Tract Infections
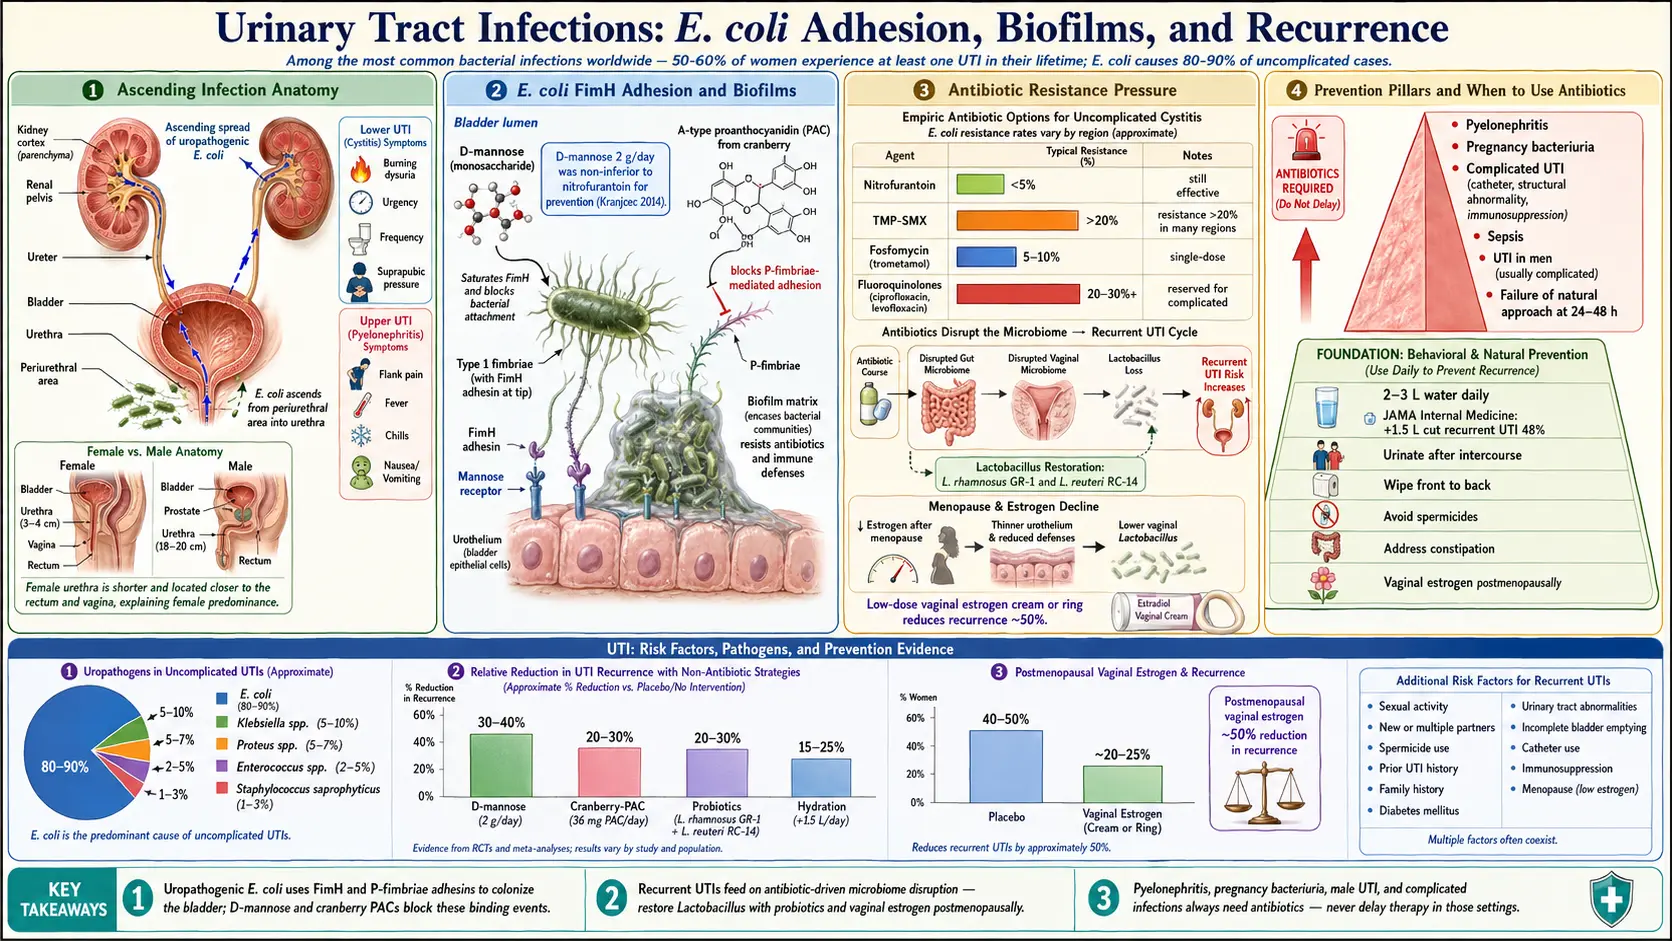
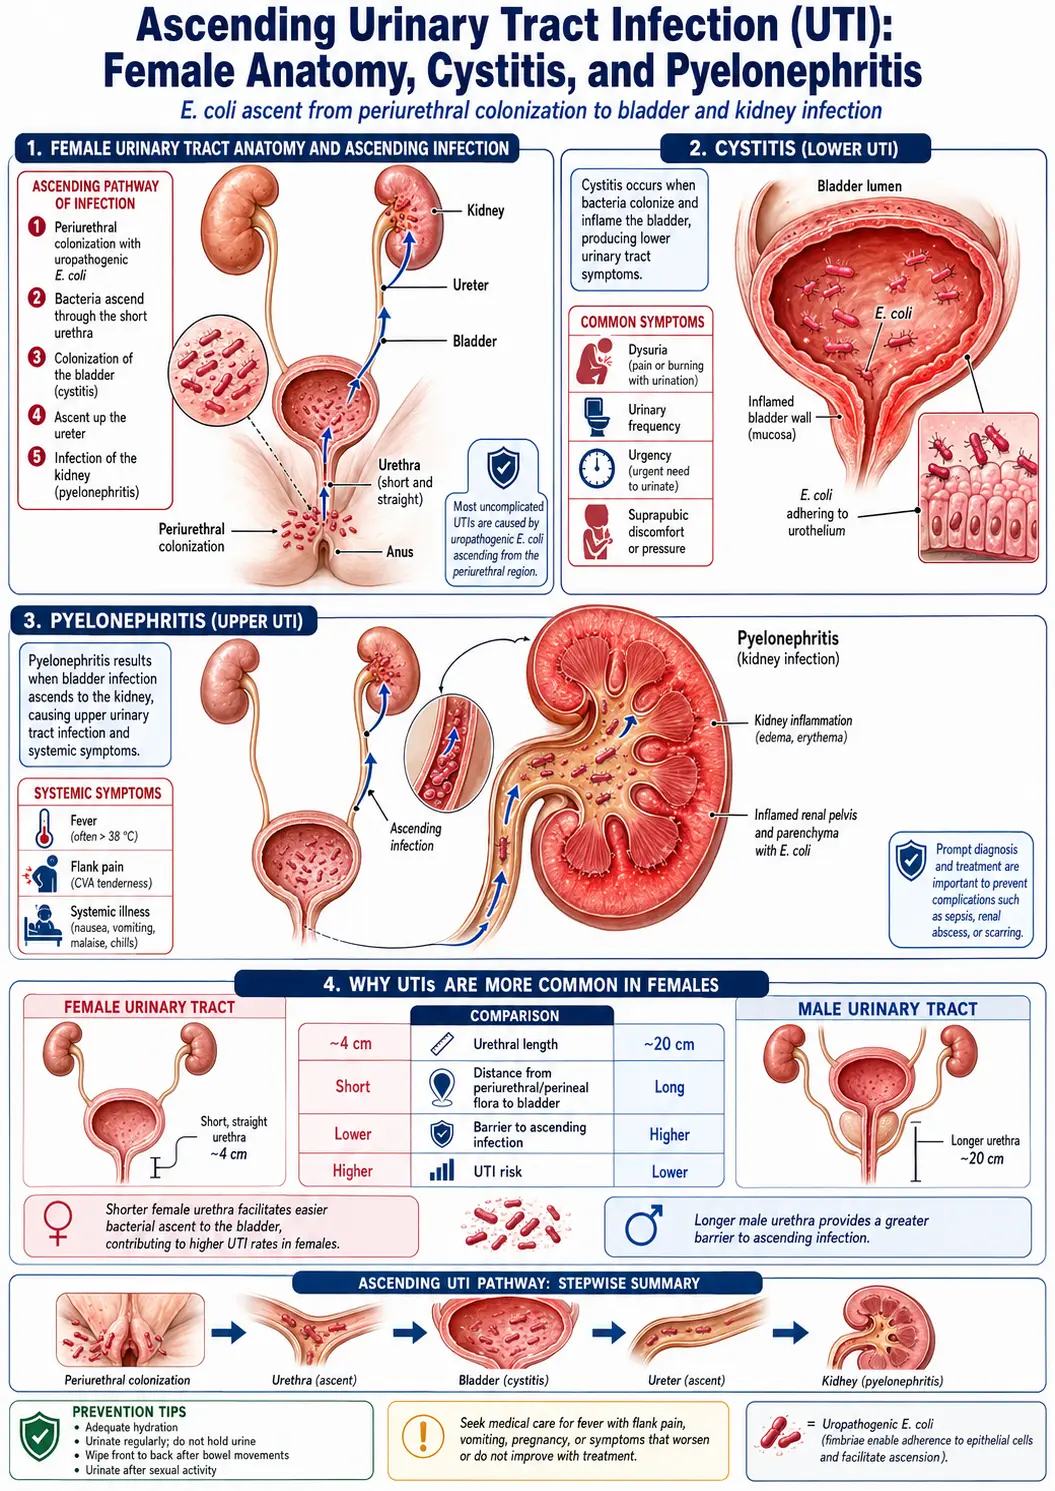
Table of Contents
- What Urinary Tract Infections Are
- Causes and Pathophysiology
- Risk Factors
- Symptoms
- Conventional Treatment and Antibiotic Resistance
- D-Mannose
- Cranberry and Proanthocyanidins (PACs)
- Herbal Antimicrobials
- Probiotics for Recurrent Urinary Tract Infections
- Hygiene Practices and Prevention
- Hydration and Urinary Health
- Estrogen and Postmenopausal Urinary Tract Infections
- When Antibiotics Are Necessary
- Cautions and Safety Considerations
- Key Research Papers
- Connections
- Featured Videos
What Urinary Tract Infections Are
A urinary tract infection (UTI) is an infection that occurs in any part of the urinary system, including the kidneys, ureters, bladder, and urethra. Urinary tract infections (UTIs) are among the most common bacterial infections worldwide, accounting for millions of healthcare visits each year. Women are disproportionately affected, with approximately 50-60% of women experiencing at least one urinary tract infection in their lifetime.
Types of Urinary Tract Infections
- Cystitis (bladder infection): The most common type, characterized by bladder inflammation, urgency, frequency, and discomfort. Most uncomplicated urinary tract infections fall into this category.
- Pyelonephritis (kidney infection): A more serious upper urinary tract infection that can involve fever, flank pain, nausea, and vomiting. Pyelonephritis requires prompt medical treatment to prevent complications such as sepsis or permanent kidney damage.
- Urethritis: Infection of the urethra, often associated with sexually transmitted organisms.
Causes and Pathophysiology
The vast majority of urinary tract infections are caused by Escherichia coli (E. coli), a bacterium that normally resides in the intestinal tract. E. coli accounts for approximately 80-90% of uncomplicated urinary tract infections. Other causative organisms include Klebsiella, Proteus, Enterococcus, and Staphylococcus saprophyticus.
Bacterial Biofilms
One of the reasons urinary tract infections frequently recur is the formation of bacterial biofilms. These are structured communities of bacteria that adhere to the bladder wall and encase themselves in a protective matrix. Biofilms are highly resistant to both antibiotics and immune defenses. Uropathogenic E. coli can also invade bladder epithelial cells and form intracellular bacterial communities that persist as reservoirs for future infections.
From a naturopathic perspective, addressing biofilm formation is a critical aspect of managing recurrent urinary tract infections. Agents such as N-acetylcysteine (NAC), lactoferrin, and certain enzymes may help disrupt biofilm structures.
Risk Factors
- Female anatomy: Women have a shorter urethra, placing the bladder closer to sources of bacteria from the rectum and vagina
- Sexual activity: Intercourse can introduce bacteria into the urinary tract. New sexual partners increase risk
- Menopause: Declining estrogen levels lead to changes in vaginal flora and thinning of urethral tissue, increasing susceptibility
- Catheter use: Indwelling urinary catheters are a major risk factor for hospital-acquired urinary tract infections
- Urinary retention: Incomplete bladder emptying allows bacteria to multiply
- Diabetes: Elevated blood sugar impairs immune function and promotes bacterial growth
- Spermicide use: Disrupts normal vaginal flora and increases urinary tract infection risk
- History of previous urinary tract infections: The strongest predictor of future urinary tract infections
- Constipation: Particularly in children, constipation can impair bladder emptying and promote bacterial colonization
- Immunosuppression: Any condition or medication that weakens immune defenses
Symptoms
Lower Urinary Tract Infection (Cystitis) Symptoms
- Burning or pain during urination (dysuria)
- Increased urinary frequency and urgency
- Cloudy, dark, or strong-smelling urine
- Blood in urine (hematuria)
- Pelvic pressure or lower abdominal discomfort
- Low-grade fever (sometimes)
Upper Urinary Tract Infection (Pyelonephritis) Symptoms
- High fever and chills
- Flank pain (pain in the side or back, below the ribs)
- Nausea and vomiting
- All symptoms of lower urinary tract infection may also be present
Conventional Treatment and Antibiotic Resistance
Conventional treatment for uncomplicated urinary tract infections typically involves a short course of antibiotics. Common first-line options include nitrofurantoin, trimethoprim-sulfamethoxazole (TMP-SMX), and fosfomycin. Fluoroquinolones are reserved for complicated infections due to their side-effect profile.
The Antibiotic Resistance Crisis
Antibiotic resistance in uropathogens is a growing global concern. Resistance rates to TMP-SMX exceed 20% in many regions, and multi-drug-resistant E. coli strains are increasingly common. Each course of antibiotics also disrupts the gut and vaginal microbiome, which paradoxically increases vulnerability to future urinary tract infections.
This cycle of recurrent infection and repeated antibiotic use underscores the importance of prevention-focused strategies and evidence-based natural alternatives that can reduce reliance on antibiotics without compromising patient safety.
D-Mannose
D-mannose is a naturally occurring simple sugar closely related to glucose. It is one of the most promising natural agents for urinary tract infection prevention and acute treatment support.
How D-Mannose Works
Uropathogenic E. coli use type 1 fimbriae (pili) tipped with FimH adhesins to attach to mannose receptors on bladder epithelial cells. D-mannose acts as a competitive inhibitor by saturating these bacterial adhesins, preventing E. coli from binding to the bladder wall. The bacteria are then flushed out during urination.
Clinical Evidence
A landmark randomized controlled trial published in the World Journal of Urology found that 2 grams of D-mannose daily was as effective as the antibiotic nitrofurantoin in preventing recurrent urinary tract infections over a six-month period, with significantly fewer side effects.
Dosage
- Prevention: 1-2 grams daily
- Acute infection support: 1.5-3 grams every 2-3 hours for 48-72 hours, then taper
- Available in powder or capsule form. Powder dissolved in water is generally preferred for faster absorption
Cranberry and Proanthocyanidins (PACs)
Cranberry has been used for urinary health for centuries. Its benefits come primarily from A-type proanthocyanidins (PACs), which prevent E. coli from adhering to bladder and kidney cells via a different mechanism than D-mannose, targeting P-fimbriae.
Choosing Effective Cranberry Products
- Not all cranberry products are equally effective. The key is PAC content
- 36 mg of PACs daily is a commonly studied dose, not an established minimum: the 2023 Cochrane review found no clear difference in urinary tract infection risk between low, moderate and high PAC doses, and a 2021 trial of 2 × 18.5 mg against 2 × 1 mg daily found a 24% reduction that was not statistically significant
- Cranberry capsules or concentrated extracts standardized to PAC content are more reliable than juice
- Cranberry juice cocktails contain excessive sugar and insufficient PACs
- Cranberry works best as a preventive strategy rather than treatment for active infection
Herbal Antimicrobials
Uva Ursi (Arctostaphylos uva-ursi)
Uva ursi, also known as bearberry, contains the active compound arbutin, which is converted to hydroquinone in the urinary tract. Hydroquinone has antimicrobial activity against common uropathogens. Uva ursi is most effective when urine pH is alkaline (above 7), so it is often taken with alkalinizing agents such as sodium bicarbonate. It is used short-term only (5-7 days) because of potential liver toxicity with prolonged use.
Oregano Oil
Oregano oil contains carvacrol and thymol, potent antimicrobial compounds active against E. coli and other uropathogens, including antibiotic-resistant strains. Emulsified oregano oil capsules (150-200 mg standardized to carvacrol content, taken 2-3 times daily with meals) may be used as part of a comprehensive protocol for acute urinary tract infection support. It does not replace antibiotics when they are medically indicated.
Garlic (Allium sativum)
Garlic contains allicin, a sulfur compound with broad-spectrum antimicrobial properties. Research has demonstrated activity against multi-drug-resistant uropathogens, including extended-spectrum beta-lactamase (ESBL)-producing E. coli. Fresh garlic or stabilized allicin supplements can be incorporated into an urinary tract infection prevention and treatment protocol.
Probiotics for Recurrent Urinary Tract Infections
The vaginal and urinary microbiome plays a crucial role in defense against urinary tract infections. A healthy vaginal flora dominated by Lactobacillus species creates an acidic environment (pH 3.5-4.5) that inhibits pathogenic bacterial growth.
Key Probiotic Strains
- Lactobacillus rhamnosus GR-1 and Lactobacillus reuteri RC-14: The most clinically studied strains for urogenital health. They colonize the vaginal tract and produce hydrogen peroxide, bacteriocins, and biosurfactants that inhibit uropathogens
- Lactobacillus crispatus: The dominant species in a healthy vaginal microbiome. Supplementation may help restore protective flora
Administration
- Oral probiotics containing GR-1 and RC-14 have been shown to migrate from the gut to the vaginal tract
- Vaginal probiotic suppositories offer direct colonization of the urogenital area
- Probiotics are especially important during and after antibiotic therapy to restore microbiome balance
Hygiene Practices and Prevention
- Wiping front to back after using the toilet keeps fecal bacteria away from the urethra
- Urinating after sexual intercourse flushes bacteria that may have been introduced
- Spermicides and diaphragms are linked to recurrent urinary tract infections in women prone to them
- Breathable cotton underwear and less time in tight-fitting clothing are common prevention habits
- Douching and scented feminine hygiene products disrupt vaginal flora
- Holding urine for prolonged periods leaves bacteria in the bladder longer; regular voiding flushes them out
- Constipation can contribute to incomplete bladder emptying and bacterial overgrowth
Hydration and Urinary Health
Adequate hydration is one of the simplest and most effective strategies for urinary tract infection prevention. Increased fluid intake promotes frequent urination, which physically flushes bacteria from the urinary tract before they can establish infection.
- A common hydration target is 2-3 liters of water daily, adjusted for activity level and climate
- A randomized controlled trial published in JAMA Internal Medicine found that women who increased water intake by 1.5 liters per day had 48% fewer recurrent urinary tract infections compared to the control group
- Herbal teas such as corn silk, marshmallow root, and parsley have traditional use as urinary demulcents and mild diuretics
- Common bladder irritants include caffeine, alcohol, carbonated beverages, and artificial sweeteners
Estrogen and Postmenopausal Urinary Tract Infections
Postmenopausal women experience a significant increase in urinary tract infection frequency due to declining estrogen levels. Estrogen plays a critical role in maintaining the health of the vaginal and urethral epithelium and supporting colonization by protective Lactobacillus species.
Vaginal Estrogen Therapy
Low-dose vaginal estrogen (cream, ring, or tablet) reduces recurrent urinary tract infections in postmenopausal women: in a 1993 randomized trial of 93 women, intravaginal estriol cream gave 0.5 infections per patient-year against 5.9 on placebo. Vaginal estrogen restores the vaginal epithelium, lowers vaginal pH, and promotes Lactobacillus recolonization. Vaginal estrogen therapy carries minimal systemic absorption and is generally considered safe even in women with contraindications to systemic hormone therapy.
Natural Alternatives
- Vaginal dehydroepiandrosterone (DHEA, prasterone): Converts locally to estrogen and testosterone, supporting vaginal tissue health
- Sea buckthorn oil: Contains omega-7 fatty acids that may improve mucosal membrane integrity
- Vitamin E suppositories: Can help maintain vaginal tissue moisture and elasticity
When Antibiotics Are Necessary
While natural approaches are valuable for prevention and support of mild urinary tract infections, antibiotics remain essential in certain situations:
- Pyelonephritis (kidney infection): Always requires antibiotic treatment to prevent serious complications
- Urinary tract infections during pregnancy: Even asymptomatic bacteriuria is treated to prevent preterm labor and pyelonephritis
- Complicated urinary tract infections: Infections in patients with structural abnormalities, catheters, or immunosuppression
- Sepsis or systemic infection: Medical emergency requiring immediate antibiotic therapy
- Symptoms worsening despite natural treatment after 24-48 hours
- Urinary tract infections in men: Generally considered complicated and typically warrant antibiotic treatment
Cautions and Safety Considerations
- Delayed treatment of a worsening urinary tract infection carries a real risk: untreated kidney infections can lead to sepsis, which is life-threatening
- Uva ursi: herbal practice limits it to one week at a time and excludes pregnancy and children
- Cranberry may interact with warfarin and other blood thinners
- D-mannose is generally very safe; because it is a sugar, high doses may affect blood sugar in people with diabetes
- Oregano oil can irritate the gastrointestinal tract; emulsified or enteric-coated formulations taken with food are the forms used to lessen this
- High-dose vitamin C (sometimes recommended to acidify urine) can increase oxalate levels and kidney stone risk in susceptible individuals
- Children, pregnant women, and people with weakened immune systems: in pregnancy even symptom-free bacteria in the urine are treated, because they are linked to kidney infection and preterm labor, and infections in people with weakened immune systems count as complicated. In any of these groups, high fever, chills, flank pain, vomiting or confusion are signs of kidney infection or sepsis that hospitals treat as urgent
- Self-diagnosis can be unreliable. Urinary tract infection symptoms can overlap with sexually transmitted infections, interstitial cystitis, or other conditions. Urinalysis and culture confirm diagnosis
An integrative approach that combines evidence-based natural prevention with appropriate use of conventional treatment when necessary offers the best outcomes for urinary tract health.
Key Research Papers
- Foxman B. Urinary tract infection syndromes: occurrence, recurrence, bacteriology, risk factors, and disease burden. Infectious Disease Clinics of North America. 2014;28(1):1-13. — doi:10.1016/j.idc.2013.09.003
- Hooton TM. Clinical practice. Uncomplicated urinary tract infection. New England Journal of Medicine. 2012;366(11):1028-1037. — PubMed PMID: 22417256
- Hooton TM, Vecchio M, Iroz A, et al. Effect of increased daily water intake in premenopausal women with recurrent urinary tract infections: a randomized clinical trial. JAMA Internal Medicine. 2018;178(11):1509-1515. — doi:10.1001/jamainternmed.2018.4204
- Kranjcec B, Papes D, Altarac S. D-mannose powder for prophylaxis of recurrent urinary tract infections in women: a randomized clinical trial. World Journal of Urology. 2014;32(1):79-84. — doi:10.1007/s00345-013-1091-6
- Gupta K, Hooton TM, Naber KG, et al. International clinical practice guidelines for the treatment of acute uncomplicated cystitis and pyelonephritis in women: a 2010 update by the Infectious Diseases Society of America and the European Society for Microbiology and Infectious Diseases. Clinical Infectious Diseases. 2011;52(5):e103-e120. doi:10.1093/cid/ciq257 — PubMed PMID: 21292654
- Jepson RG, Williams G, Craig JC. Cranberries for preventing urinary tract infections. Cochrane Database of Systematic Reviews. 2012;10:CD001321. doi:10.1002/14651858.CD001321.pub5 — PubMed PMID: 23076891
- Williams G, Hahn D, Stephens JH, Craig JC, Hodson EM. Cranberries for preventing urinary tract infections. Cochrane Database of Systematic Reviews. 2023;4(4):CD001321. doi:10.1002/14651858.CD001321.pub6 — PubMed PMID: 37068952
- Babar A, Moore L, Leblanc V, et al. High dose versus low dose standardized cranberry proanthocyanidin extract for the prevention of recurrent urinary tract infection in healthy women: a double-blind randomized controlled trial. BMC Urology. 2021;21(1):44. doi:10.1186/s12894-021-00811-w — PubMed PMID: 33757474
- Stamm WE, Norrby SR. Urinary tract infections: disease panorama and challenges. Journal of Infectious Diseases. 2001;183(Suppl 1):S1-S4. doi:10.1086/318850 — PubMed PMID: 11171002
- Flores-Mireles AL, Walker JN, Caparon M, Hultgren SJ. Urinary tract infections: epidemiology, mechanisms of infection and treatment options. Nature Reviews Microbiology. 2015;13(5):269-284. doi:10.1038/nrmicro3432 — PubMed PMID: 25853778
- Beerepoot MA, ter Riet G, Nys S, et al. Lactobacilli vs antibiotics to prevent urinary tract infections: a randomized, double-blind, noninferiority trial in postmenopausal women. Archives of Internal Medicine. 2012;172(9):704-712. doi:10.1001/archinternmed.2012.777 — PubMed PMID: 22782199
- Naber KG, Schito G, Botto H, et al. Surveillance study in Europe and Brazil on clinical aspects and antimicrobial resistance epidemiology in females with cystitis (ARESC): implications for empiric therapy. European Urology. 2008;54(5):1164-1175. doi:10.1016/j.eururo.2008.05.010 — PubMed PMID: 18511178
- Anger J, Lee U, Ackerman AL, et al. Recurrent Uncomplicated Urinary Tract Infections in Women: AUA/CUA/SUFU Guideline. Journal of Urology. 2019;202(2):282-289. doi:10.1097/JU.0000000000000296 — PubMed PMID: 31042112
- Raz R, Stamm WE. A controlled trial of intravaginal estriol in postmenopausal women with recurrent urinary tract infections. New England Journal of Medicine. 1993;329(11):753-756. — PubMed PMID: 8350884
Historical Background
Urinary tract infections have been recognized since ancient times, with descriptions of urinary symptoms found in Egyptian papyri. The bacterial cause of urinary tract infections was established in the late 19th century with the work of Theodor Escherich, who first described Escherichia coli in 1885. The development of sulfonamides in the 1930s and subsequent antibiotics revolutionized urinary tract infection treatment.
PubMed Topic Searches
- Clinical trials on urinary tract infection treatment — PubMed search
- D-mannose for UTI prevention — PubMed search
- Cranberry and proanthocyanidins for UTI — PubMed search
- Recurrent UTI prophylaxis in women — PubMed search
- Vaginal estrogen for postmenopausal UTI — PubMed search
- Probiotics (Lactobacillus) for UTI prevention — PubMed search
- Antibiotic resistance in E. coli UTI — PubMed search
- Increased hydration and UTI recurrence — PubMed search
Connections
- Urology
- Pyelonephritis (Kidney Infection)
- Interstitial Cystitis
- Probiotics
- E. Coli
- Vitamin C
- Kidney Stones
- Bladder Cancer
- Goldenseal
- Sepsis
- Oregano
- Garlic
- Urinalysis
- Diabetes
- Benign Prostatic Hyperplasia
- Prostate Conditions
- Artificial Sweeteners
- Irritable Bowel Syndrome
- Eucalyptus
- Andrographis
- Prostate Cancer
- Bacterial Vaginosis
- Yeast Infections
- Urinary Incontinence
- Herbs covered on this site that discuss this condition: Uva Ursi · Cat’s Whiskers / Java Tea (Orthosiphon aristatus) · Marsh Barbel (Hygrophila auriculata) · Olive Leaf (Olea europaea) · Saw Palmetto (Serenoa repens) · Barberry (Berberis vulgaris)
- Cranberry