Pyelonephritis (Kidney Infection)
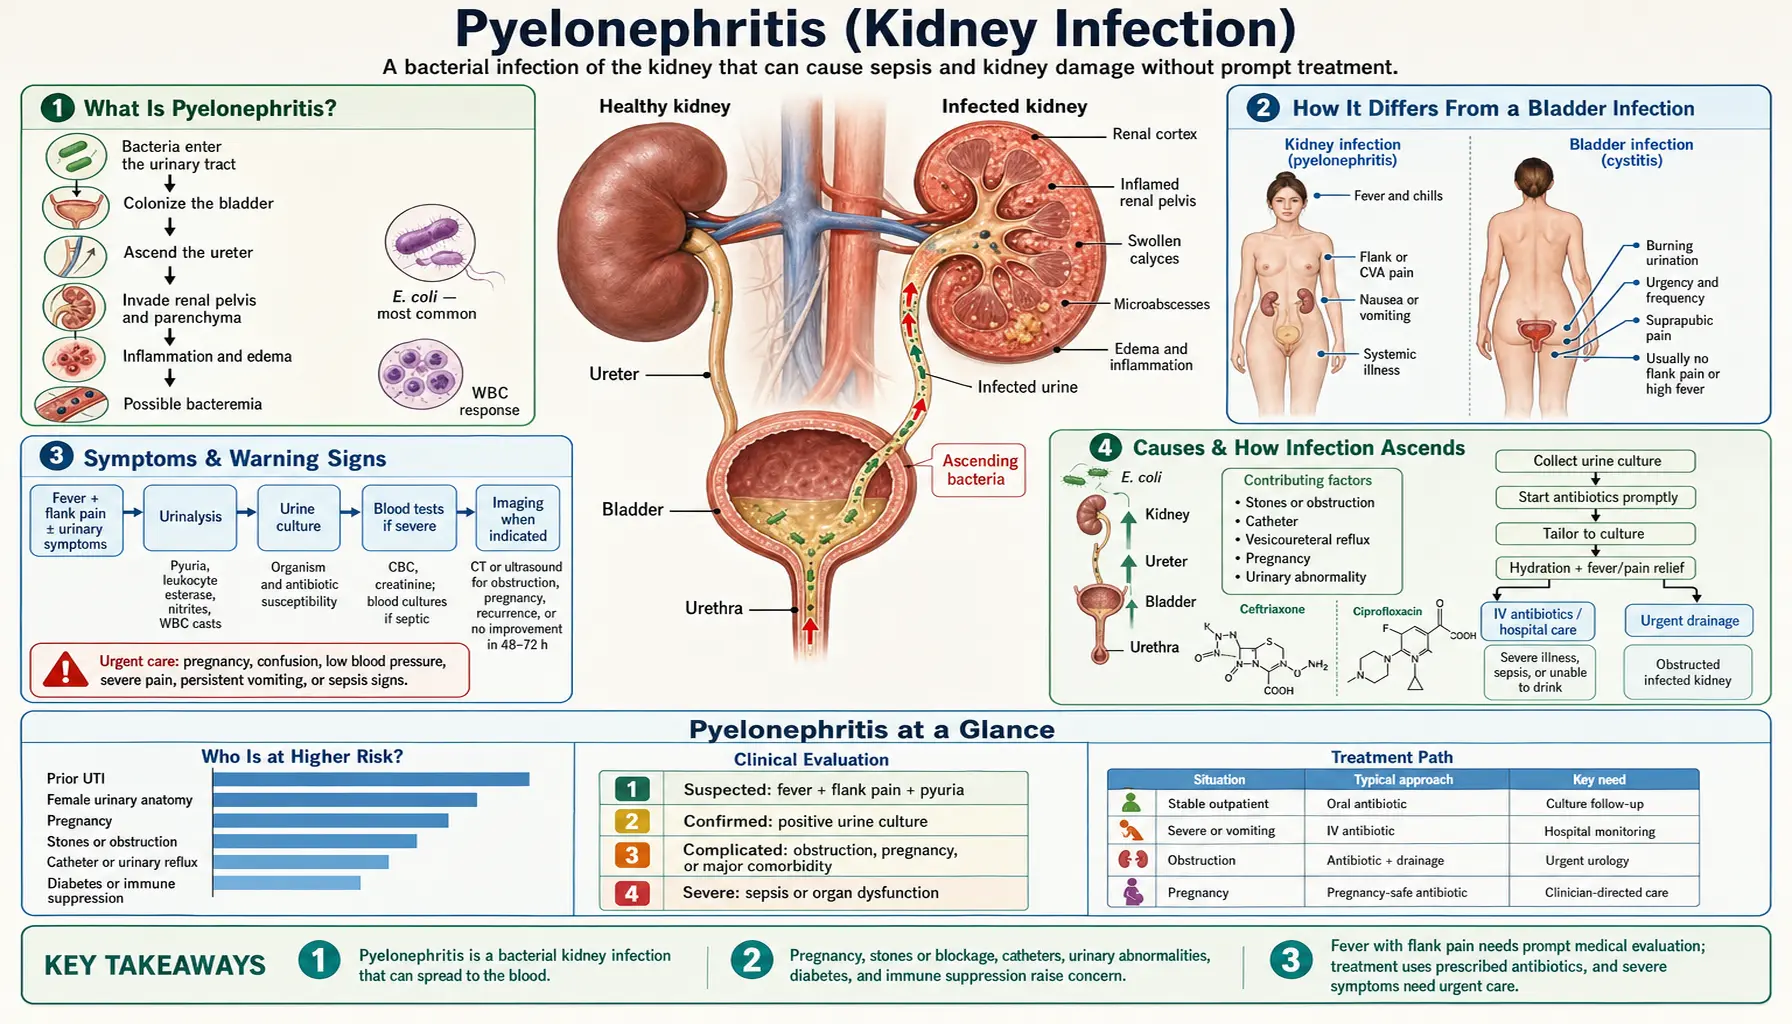
Pyelonephritis is a bacterial infection of the kidney — the most serious of the common urinary tract infections (UTIs). Most urinary tract infections are confined to the bladder, where they cause the familiar burning and urgency of cystitis. Pyelonephritis is what happens when those bacteria climb higher, past the bladder and up the ureters, until they reach the kidney itself. Because the kidney is a richly blood-supplied organ wired directly into the circulation, an infection here can spill bacteria into the bloodstream and set off sepsis. That is the whole reason a kidney infection is treated so much more urgently than a bladder infection: the classic combination of fever, flank pain, and nausea is the body's warning that a routine urinary tract infection (UTI) has become a systemic illness. The good news is that when it is caught early and treated with the right antibiotics, most people recover completely — and much of the danger comes from delay.
Table of Contents
How Pyelonephritis Is Defined
The name breaks down into its Greek roots: pyelo- (the renal pelvis, the funnel-shaped chamber where each kidney collects urine), nephro- (kidney), and -itis (inflammation). Put together, pyelonephritis means inflammation of the kidney and its collecting system caused by infection. In practice it refers to a bacterial infection that has taken hold in the substance of one or both kidneys rather than staying in the bladder below.
Doctors group urinary tract infections by where they sit. A lower urinary tract infection involves the bladder (cystitis) or urethra (urethritis) and is usually uncomfortable but low-risk. An upper urinary tract infection — pyelonephritis — involves the kidney and is a systemic infection that can become dangerous. The single feature that most often marks the difference is fever: a bladder infection typically does not cause one, while a kidney infection usually does.
By far the most common culprit is Escherichia coli (E. coli), the gut bacterium responsible for roughly 70–90% of uncomplicated cases. Kidney infection is also much more common in women than in men. In one large population-based analysis of a US health-plan population, acute pyelonephritis occurred in roughly 12–13 women per 10,000 per year as outpatients and about 3–4 per 10,000 requiring hospitalization; in men the rates were 2–3 per 10,000 as outpatients and 1–2 per 10,000 in hospital. In that study E. coli caused 80% of cases in women and 70% in men. Infections are described as uncomplicated when they occur in an otherwise-healthy, non-pregnant adult with a normal urinary tract, and complicated when there is an underlying problem — obstruction, a stone, a catheter, pregnancy, diabetes, a transplanted or single kidney, or a weakened immune system — that raises the risk of failure and complications.
How It Differs From a Bladder Infection
Because pyelonephritis and cystitis are two ends of the same disease process, they can be confusing to tell apart. The distinction matters enormously, though, because it changes how urgently and how aggressively the infection is treated. The table below summarizes the practical differences.
| Feature | Cystitis (bladder infection) | Pyelonephritis (kidney infection) |
|---|---|---|
| Location | Lower tract — the bladder | Upper tract — the kidney |
| Fever | Usually none | Common, often high (≥ 38 °C / 100.4 °F) with shaking chills |
| Pain | Burning on urination; pressure low in the pelvis | Flank or back pain, over the ribs at the side (costovertebral angle) |
| Whole-body illness | Feel basically well | Nausea, vomiting, exhaustion — genuinely sick |
| Risk level | Low; rarely serious | Can lead to bloodstream infection and sepsis |
| Typical treatment | Short oral antibiotic course, often started empirically | Longer course, urine culture guided, sometimes intravenous (IV) / hospital |
Clinicians treat a urinary infection that comes with a fever, back pain, or vomiting as a possible kidney infection until proven otherwise. Someone can have both sets of symptoms at once — the burning of cystitis and the fever and flank pain of pyelonephritis — because the kidney infection usually started as a bladder infection that climbed.
Symptoms & Warning Signs
Acute pyelonephritis often develops quickly, over a matter of hours to a day or two. Typical symptoms include:
- Fever and chills — frequently high (39–40 °C / 102–104 °F), sometimes with dramatic, teeth-chattering rigors.
- Flank or back pain — a deep ache or tenderness over one or both sides of the mid-back, where the kidneys sit. Tapping this area (the costovertebral angle) reproduces the pain.
- Nausea and vomiting — common enough that some people cannot keep fluids or pills down, which itself becomes a reason to be admitted for intravenous treatment.
- Feeling systemically unwell — profound fatigue, malaise, and sometimes confusion.
- Lower urinary symptoms — burning with urination, urgency, and frequency may be present (the leftover of the bladder infection that started it) or may be absent entirely.
- Changes in the urine — cloudy, strong-smelling, or bloody urine.
Older adults can present atypically. Instead of the classic fever-and-flank-pain picture, an elderly person with pyelonephritis may show up with new confusion, weakness, loss of appetite, or a fall — sometimes without much fever at all. In this group, new confusion, weakness or a fall can be the only sign of a kidney infection.
The symptoms that turn a kidney infection into an emergency — signs of sepsis and the inability to keep fluids down — are covered in Emergency Warning Signs below.
Causes & How Infection Ascends
The vast majority of kidney infections follow an ascending route. It usually unfolds in stages:
- Bacteria from the bowel — most often E. coli — colonize the skin and tissues around the urethral opening.
- They travel up the short urethra into the bladder, causing cystitis.
- From the bladder, they climb the ureters — the thin tubes that carry urine down from each kidney — and finally reach the renal pelvis and kidney tissue.
Several things make that climb easier. The bacteria that cause most kidney infections are uropathogenic strains equipped with hair-like appendages (P-fimbriae and other adhesins) that let them grip the lining of the urinary tract and resist being flushed out by the urine stream. Anything that lets urine pool or flow backward — a blockage, a stone, or urine refluxing from the bladder back up the ureters (vesicoureteral reflux) — hands these bacteria a ladder.
Women are far more susceptible for a simple anatomical reason: the female urethra is short and its opening sits close to the anus and vagina, so gut bacteria have a much shorter trip to the bladder. This is why the same infection that is common and usually mild in young women is comparatively rare in men and, when it does occur in a man, is more often treated as complicated.
Although E. coli dominates, other organisms cause a minority of cases: Klebsiella, Proteus (linked with stone formation and alkaline urine), Enterococcus, and — especially in catheterized or hospitalized patients — Pseudomonas and other resistant bacteria. Young, sexually active women occasionally grow Staphylococcus saprophyticus. Much less commonly, a kidney infection can arrive by the bloodstream rather than by climbing — for example, when Staphylococcus aureus in the blood seeds the kidney — but this hematogenous route is the exception, not the rule.
Risk Factors
Anything that increases bacterial exposure, slows urine flow, or weakens defenses raises the risk of pyelonephritis:
- Female anatomy — the single biggest factor, for the reasons described above.
- Sexual activity — intercourse can push bacteria toward the urethra; a new partner and spermicide use both raise risk.
- Pregnancy — hormonal changes relax and widen the ureters while the growing uterus presses on them, so urine drains more slowly. Untreated asymptomatic bacteriuria in pregnancy progresses to pyelonephritis in a substantial fraction of women, which is exactly why pregnant women are screened and treated for silent bacteria in the urine.
- Urinary obstruction — kidney stones, an enlarged prostate, tumors, or strictures block flow and let infection build behind the blockage. An infected, obstructed kidney is a surgical emergency.
- Vesicoureteral reflux — a valve problem, often present from childhood, that lets urine flow backward from the bladder toward the kidneys, carrying bacteria upstream.
- Catheters and instrumentation — indwelling urinary catheters and procedures on the urinary tract are a leading route in hospitalized patients.
- Diabetes — high blood sugar impairs immune defenses and puts glucose in the urine (food for bacteria), and diabetics are at markedly higher risk of severe complications such as emphysematous pyelonephritis.
- A weakened immune system — from immunosuppressive drugs, transplant, or illness.
- Incomplete bladder emptying — from a neurogenic bladder, spinal injury, or nerve disease, leaving residual urine for bacteria to grow in.
- Prior urinary tract infections and, in post-menopausal women, the drop in estrogen that thins protective tissues.
Diagnosis
Diagnosis rests on the clinical picture — fever plus flank pain plus urinary symptoms — confirmed by testing the urine.
- Urinalysis is the first test. It typically shows pyuria (white blood cells in the urine), a positive leukocyte esterase, nitrites (produced by common urinary bacteria), bacteria, and often blood. The finding most specific to kidney involvement is white-blood-cell casts — microscopic cylinders molded in the kidney tubules that point to infection in the kidney itself rather than just the bladder.
- Urine culture with antibiotic susceptibility testing is recommended for essentially all suspected pyelonephritis — unlike a simple bladder infection, which is often treated empirically without a culture. The culture confirms the organism and lets the doctor narrow (de-escalate) antibiotics to the most effective, narrowest choice once results return in a day or two.
- Blood tests — a complete blood count (often showing a high white-cell count), inflammatory markers, and kidney-function markers such as creatinine. In sicker patients, blood cultures and a lactate level help detect bloodstream infection and sepsis.
Imaging is not routine. A healthy adult who fits the classic picture and starts improving on antibiotics usually needs no scan. Imaging is reserved for situations where something more may be going on:
- No improvement (or worsening) after 48–72 hours of appropriate antibiotics — raising concern for an abscess or an obstructing stone.
- Suspected obstruction, a known stone, or recurrent infection.
- Diabetes, immune suppression, a transplant or single kidney, or infection in a man — groups where complications are more likely.
When imaging is needed, contrast-enhanced computed tomography (CT) is the most sensitive test for abscesses, obstruction, and gas-forming (emphysematous) infection. Ultrasound is radiation-free and is preferred in pregnancy and as a quick screen for a blocked, swollen kidney (hydronephrosis).
Treatment
Pyelonephritis is treated with antibiotics, and the central decision is whether a person can be managed at home with pills or needs to be in the hospital on an intravenous (IV) drip. That choice hinges on how sick they are, whether they can keep fluids and medicine down, and whether the infection is complicated.
Outpatient oral treatment
Someone who is not severely ill, is hemodynamically stable, can tolerate fluids and oral medication, is not pregnant, and has a reliable way to follow up can usually be treated at home. Where local resistance allows, first-line options include a fluoroquinolone — ciprofloxacin 500 mg twice daily for 7 days or levofloxacin 750 mg once daily for 5 days. Randomized trials support these shorter courses: a 7-day course of ciprofloxacin was found non-inferior to 14 days, and a 5-day, high-dose levofloxacin course performed comparably to longer regimens. If local E. coli resistance to fluoroquinolones exceeds about 10%, guidelines advise giving one long-acting initial parenteral dose (such as ceftriaxone or a consolidated aminoglycoside dose) before switching to oral therapy. Trimethoprim-sulfamethoxazole for 14 days is an option only when the cultured organism is known to be susceptible. Oral beta-lactams are generally less effective for kidney infection and are used as backups.
Hospital Treatment by Intravenous Drip
Admission for intravenous antibiotics is warranted for severe illness or sepsis, persistent vomiting, pregnancy, hemodynamic instability, a complicated urinary tract, uncertain ability to take medication reliably, or failure of outpatient therapy. Empiric intravenous choices include ceftriaxone, an intravenous fluoroquinolone, piperacillin-tazobactam, or — when extended-spectrum beta-lactamase (ESBL) organisms are likely — a carbapenem, sometimes with an aminoglycoside. Once a patient has been afebrile and clearly improving for about a day or two, treatment is switched to a targeted oral antibiotic guided by the culture, with a total course commonly running 7 to 14 days depending on the drug and severity.
The Infectious Diseases Society of America's 2025 guideline for complicated urinary tract infections, a group that includes kidney infections, suggests shorter courses for people who are improving on an effective antibiotic: 5–7 days of a fluoroquinolone or 7 days of another antibiotic, even when bacteria were also found in the blood. The panel kept a longer 10–14-day course for men with a feverish infection in whom a bacterial prostate infection is suspected. The same guideline suggests switching from the drip to tablets once the person is improving, able to take medicine by mouth, and an effective oral antibiotic is available, rather than finishing the course by drip.
Antibiotic resistance and source control
Resistance is a growing problem and shapes every treatment decision. Resistance of E. coli to trimethoprim-sulfamethoxazole and to fluoroquinolones has risen steadily, and fluoroquinolones now carry warnings about tendon rupture, aortic injury, and nervous-system and blood-sugar effects, so they are used more judiciously than in the past. ESBL-producing and even carbapenem-resistant organisms are increasingly encountered, which is why culture-guided therapy matters and why newer agents (for example, plazomicin) are held in reserve for multidrug-resistant infections. Finally, antibiotics cannot succeed alone when there is pus or a blockage: an abscess must be drained and an obstructing stone relieved. This source control is as important as the drug itself.
Newer drugs have been tested in hospital trials of complicated urinary infections that included kidney infections. In the 2024 CERTAIN-1 trial (661 adults), intravenous cefepime-taniborbactam, a combination built to work against bacteria that resist carbapenems, achieved combined cure of symptoms and bacteria in 70.6% of patients compared with 58.0% for meropenem; 42.2% of the analysed patients had acute pyelonephritis. In the 2022 ADAPT-PO trial (1,372 adults), tebipenem pivoxil hydrobromide taken by mouth matched intravenous ertapenem, with clinical cure in 93.1% and 93.6% of patients; a tablet that works against resistant strains could let some infections that now need a drip be treated by mouth.
Complications
Most people treated promptly recover fully. The complications below are what make early treatment matter:
- Sepsis and septic shock — the most feared acute complication. Bacteria entering the bloodstream trigger a body-wide inflammatory response that can drop blood pressure and shut down organs. This is a medical emergency.
- Kidney or perinephric abscess — a walled-off pocket of pus in or around the kidney. It is suspected when someone does not improve after 48–72 hours of antibiotics; it usually needs drainage.
- Emphysematous pyelonephritis — a rare, severe, gas-forming necrotizing infection that occurs overwhelmingly in people with diabetes. Historically it carried a high mortality; it is managed with aggressive antibiotics, drainage, and sometimes removal of the kidney, and its severity is graded by the extent of gas seen on computed tomography. In a series of 48 cases from Taiwan (Huang and Tseng, 2000), 96% of patients had diabetes and 18.8% died overall. Two of the five patients treated with antibiotics alone died (40%), while drainage through a catheter in the skin plus antibiotics succeeded in 66%; every patient whose gas stayed inside the kidney’s collecting system or tissue (classes 1 and 2) and who was treated with a drainage tube plus antibiotics survived.
- Papillary necrosis — death of the innermost kidney tissue, more likely with diabetes, obstruction, or heavy painkiller use.
- Acute kidney injury — a sudden drop in kidney function during severe infection.
- Kidney scarring and chronic damage — recurrent or reflux-associated infection can scar the kidney over time, contributing to high blood pressure and chronic kidney disease.
- Pregnancy complications — pyelonephritis in pregnancy raises the risk of preterm labor, maternal anemia, sepsis, and respiratory complications, which is why it is almost always treated in the hospital. In 546,092 pregnancies in Southern California (1993–2010), pyelonephritis occurred in 0.5%; those pregnancies more often had anemia (26.3% vs 11.4%), blood infection (1.9% vs 0.03%) and spontaneous preterm birth (10.3% vs 7.9%), and most of those preterm births came at 33–36 weeks.
Acute vs Chronic Pyelonephritis
Acute pyelonephritis is the sudden infection described throughout this article — it comes on fast, is treated with antibiotics, and in most healthy people resolves without lasting harm.
Chronic pyelonephritis is a different animal. It is a pattern of repeated or persistent kidney infection accompanied by progressive scarring, and it almost never occurs without an underlying structural problem driving it — most often vesicoureteral reflux (so-called reflux nephropathy, frequently rooted in childhood), long-standing obstruction, or stones. Over years, chronic pyelonephritis can leave the kidneys shrunken and scarred, cause hypertension, and erode kidney function toward chronic kidney disease. The key point is that treating chronic pyelonephritis means fixing the root cause — correcting reflux, relieving obstruction, removing stones — not simply repeating courses of antibiotics.
A rare and destructive chronic variant, xanthogranulomatous pyelonephritis, typically develops around a large staghorn stone with chronic obstruction (often from Proteus). It gradually replaces normal kidney tissue with lipid-laden inflammatory cells and usually requires surgical removal of the affected kidney.
Prevention
Preventing pyelonephritis largely means preventing bladder infections and treating them before they climb:
- Early treatment of bladder infections. Catching and treating cystitis early is the most direct way to stop it from ascending to the kidney.
- Fluids and not holding urine — drinking enough and emptying the bladder regularly flush it and help clear bacteria.
- Simple habits — urinating after intercourse and wiping front-to-back can reduce risk for women prone to urinary tract infections.
- Clearing obstruction. Removing or treating kidney stones and treating an enlarged prostate let urine drain freely.
- Screening for silent bacteria in the urine (asymptomatic bacteriuria) in pregnancy. Pregnancy is one of the few situations where treating bacteria in the urine of someone with no symptoms is clearly beneficial, because it prevents progression to pyelonephritis. Outside of pregnancy and certain urologic procedures, treating asymptomatic bacteria has not been shown to help and drives antibiotic resistance.
- Blood-sugar control. Good blood-sugar management lowers both the risk of infection and the risk of severe complications.
- Careful catheter use. Hospitals limit urinary catheters to patients who need them and remove them as early as possible, because catheter-associated infection is a leading route in the hospital.
- Recurrent urinary tract infections — prevention options used for repeated infections include behavioral measures, vaginal estrogen after menopause in selected women, and, in specific cases, preventive antibiotics.
Emergency Warning Signs
A bladder infection can usually wait for a routine clinic visit. A kidney infection — fever plus flank pain plus feeling genuinely ill — deserves same-day medical attention, and certain features make it an emergency. These are the signs that hospitals treat as urgent or emergency problems:
- A high fever with shaking chills together with back or side pain.
- Persistent vomiting so that you cannot keep down fluids or antibiotics.
- Signs of sepsis — new confusion or drowsiness, a racing heart, fast or shallow breathing, dizziness or fainting, very low or very high body temperature, or passing little or no urine. Suspected sepsis is a call-emergency-services situation.
- Severe or worsening flank pain, or blood in the urine with fever.
- Pregnancy with any fever or flank pain — this needs urgent evaluation and usually hospital admission.
- A single kidney, a kidney transplant, or a known blockage or stone on the affected side.
- No improvement after 48–72 hours of antibiotics — this can signal an abscess, an obstruction, or a resistant organism that needs a different approach.
The bottom line: burning and urgency alone can be handled routinely, but fever, back pain, vomiting, or feeling dangerously unwell mean the infection may have reached the kidney or the blood — and that is when hours matter.
Key Research Papers
- Johnson JR, Russo TA. Acute Pyelonephritis in Adults. New England Journal of Medicine. 2018;378(1):48-59. — doi:10.1056/NEJMcp1702758
- Gupta K, Hooton TM, Naber KG, et al. International Clinical Practice Guidelines for the Treatment of Acute Uncomplicated Cystitis and Pyelonephritis in Women: A 2010 Update by the Infectious Diseases Society of America and the European Society for Microbiology and Infectious Diseases. Clinical Infectious Diseases. 2011;52(5):e103-e120. — doi:10.1093/cid/ciq257
- Hooton TM. Uncomplicated Urinary Tract Infection. New England Journal of Medicine. 2012;366(11):1028-1037. — doi:10.1056/NEJMcp1104429
- Czaja CA, Scholes D, Hooton TM, Stamm WE. Population-Based Epidemiologic Analysis of Acute Pyelonephritis. Clinical Infectious Diseases. 2007;45(3):273-280. — doi:10.1086/519268
- Foxman B. Urinary Tract Infection Syndromes: Occurrence, Recurrence, Bacteriology, Risk Factors, and Disease Burden. Infectious Disease Clinics of North America. 2014;28(1):1-13. — doi:10.1016/j.idc.2013.09.003
- Foxman B. The epidemiology of urinary tract infection. Nature Reviews Urology. 2010;7(12):653-660. — doi:10.1038/nrurol.2010.190
- Talan DA, Stamm WE, Hooton TM, et al. Comparison of Ciprofloxacin (7 Days) and Trimethoprim-Sulfamethoxazole (14 Days) for Acute Uncomplicated Pyelonephritis in Women: A Randomized Trial. JAMA. 2000;283(12):1583-1590. — doi:10.1001/jama.283.12.1583
- Sandberg T, Skoog G, Hermansson AB, et al. Ciprofloxacin for 7 days versus 14 days in women with acute pyelonephritis: a randomised, open-label and double-blind, placebo-controlled, non-inferiority trial. The Lancet. 2012;380(9840):484-490. — doi:10.1016/S0140-6736(12)60608-4
- Peterson J, Kaul S, Khashab M, et al. A Double-Blind, Randomized Comparison of Levofloxacin 750 mg Once-Daily for Five Days With Ciprofloxacin 400/500 mg Twice-Daily for 10 Days for the Treatment of Complicated Urinary Tract Infections and Acute Pyelonephritis. Urology. 2008;71(1):17-22. — doi:10.1016/j.urology.2007.09.002
- Huang JJ, Tseng CC. Emphysematous Pyelonephritis: Clinicoradiological Classification, Management, Prognosis, and Pathogenesis. Archives of Internal Medicine. 2000;160(6):797-805. — doi:10.1001/archinte.160.6.797
- Hill JB, Sheffield JS, McIntire DD, Wendel GD. Acute Pyelonephritis in Pregnancy. Obstetrics & Gynecology. 2005;105(1):18-23. — doi:10.1097/01.AOG.0000149154.96285.a0
- Wing DA, Fassett MJ, Getahun D. Acute pyelonephritis in pregnancy: an 18-year retrospective analysis. American Journal of Obstetrics and Gynecology. 2014;210(3):219.e1-6. — PubMed PMID: 24100227
- Wagenlehner FME, Cloutier DJ, Komirenko AS, et al. Once-Daily Plazomicin for Complicated Urinary Tract Infections. New England Journal of Medicine. 2019;380(8):729-740. — doi:10.1056/NEJMoa1801467
- Trautner BW, Cortés-Penfield NW, Gupta K, et al. Clinical Practice Guidelines by Infectious Diseases Society of America (IDSA): 2025 Guidelines on Management and Treatment of Complicated Urinary Tract Infections—Duration of Antibiotics for Complicated UTI. Clinical Infectious Diseases. 2026;82(Suppl 3):i79-i88. — PubMed PMID: 41419448
- Trautner BW, Cortés-Penfield NW, Gupta K, et al. Clinical Practice Guidelines by Infectious Diseases Society of America: 2025 Guidelines on Management and Treatment of Complicated Urinary Tract Infections – Timing of Intravenous to Oral Antibiotics Transition for Complicated Urinary Tract Infections. Clinical Infectious Diseases. 2026;82(Suppl 3):i68-i78. — PubMed PMID: 41414903
- Wagenlehner FM, Gasink LB, McGovern PC, et al. Cefepime-Taniborbactam in Complicated Urinary Tract Infection. New England Journal of Medicine. 2024;390(7):611-622. — PubMed PMID: 38354140
- Eckburg PB, Muir L, Critchley IA, et al. Oral Tebipenem Pivoxil Hydrobromide in Complicated Urinary Tract Infection. New England Journal of Medicine. 2022;386(14):1327-1338. — PubMed PMID: 35388666
PubMed Topic Searches
These links open live PubMed searches for the listed keywords — results update as new studies are indexed.
- Acute pyelonephritis treatment — PubMed search
- Pyelonephritis antibiotic resistance — PubMed search
- Acute pyelonephritis in pregnancy — PubMed search
- Emphysematous pyelonephritis — PubMed search
- Chronic pyelonephritis & reflux nephropathy — PubMed search
- Pyelonephritis imaging (CT) — PubMed search
- Short-course antibiotics for pyelonephritis — PubMed search