⚠ Evidence warning: Clinical trials or other evidence do not support the claim that quercetin and luteolin work as mast-cell stabilizers that are particularly useful in mast cell activation syndrome. This page keeps it as a report of what people, websites or other media say.
Hives and Flushing

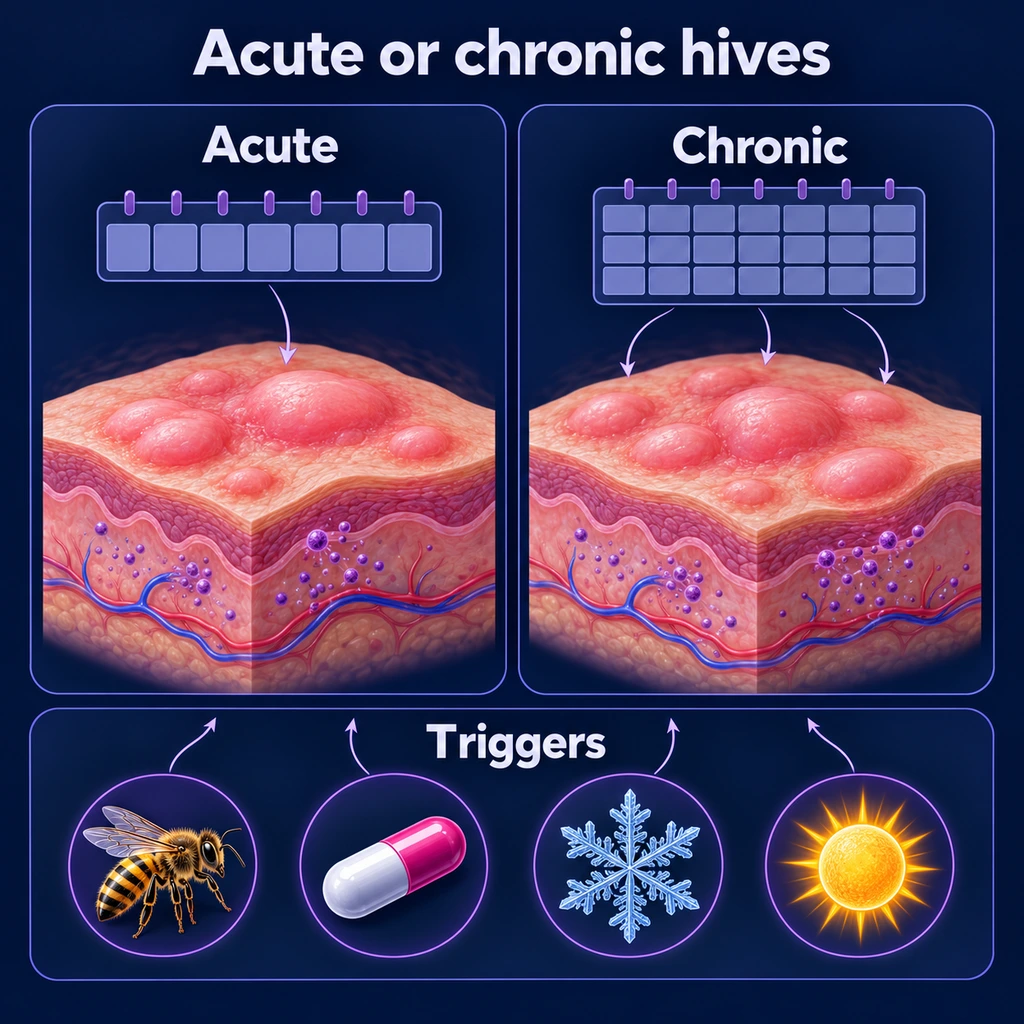
Table of Contents
Overview
Hives (urticaria) are raised, itchy, blanching wheals that come and go, typically resolving within 24 hours at any given site. Flushing is transient redness and warmth, usually of the face, neck, and upper chest. Both arise from the release of histamine and other vasoactive mediators from skin mast cells. They share triggers and pathways, and frequently co-occur. Most acute cases are self-limited and viral or allergic; chronic forms (lasting more than six weeks) are more often autoimmune, mast-cell-mediated, or driven by physical triggers, and require systematic evaluation.
Historical Background
Urticaria has been recognized since Hippocrates as "knidosis," from the Greek for nettle. The discovery of histamine in 1910 and immunoglobulin E in 1966 established the basic mechanism. Chronic spontaneous urticaria as an autoimmune disease was characterized in the 1990s. Mast cell activation syndrome was formalized as a distinct clinical entity in 2010, and alpha-gal syndrome was identified after lone-star-tick exposures in the U.S. Southeast in 2009.
Types of Hives and Flushing
- Acute urticaria — less than six weeks; usually viral, food, drug, or insect-sting triggered.
- Chronic spontaneous urticaria (CSU) — daily or near-daily hives for more than six weeks without an identifiable trigger; many cases are autoimmune (anti-IgE or anti-FcεRI antibodies).
- Chronic inducible urticaria — reproducibly triggered by physical stimuli: dermographism (pressure), cold, heat, exercise (cholinergic), water (aquagenic), pressure-delayed, or solar.
- Mast cell activation syndrome (MCAS) — episodic mediator release across multiple organ systems, with flushing, hives, gastrointestinal (GI) symptoms, brain fog, and sometimes anaphylaxis.
- Alpha-gal syndrome — delayed (3–6 hour) urticaria, gastrointestinal symptoms, or anaphylaxis after eating mammalian meat or gelatin, triggered by tick-bite-induced immunoglobulin E (IgE) to galactose-alpha-1,3-galactose. In a 2019 study of 261 children and adults (aged 5 to 82) who reported red-meat allergy, symptoms began 2 hours or more after eating mammalian meat in 81%, so the delay is typical but not universal; 93% reported hives, 64% gut symptoms and 60% anaphylaxis, and the authors concluded that the allergy is just as common in people who have no other allergies.
- Histamine intolerance — symptoms with histamine-rich or histamine-releasing foods (aged cheese, cured meats, alcohol, fermented foods); often from low diamine oxidase (DAO) activity.
- Carcinoid and other paraneoplastic flushing — episodic flushing with diarrhea and right-sided heart valve disease; rare but important.
- Rosacea-related flushing — persistent or episodic facial flushing, often triggered by heat, alcohol, spicy food, sun, or stress.
Common Causes
- Foods — nuts, shellfish, eggs, milk, wheat, soy, sesame in classic immunoglobulin E allergy; high-histamine foods in histamine intolerance; mammalian meat in alpha-gal syndrome.
- Medications — penicillins, nonsteroidal anti-inflammatory drugs (NSAIDs), opioids, vancomycin (red-man syndrome), radiocontrast.
- Insect stings and bites — bees, wasps, fire ants; tick bites can trigger alpha-gal sensitization.
- Infections — viral upper respiratory infections, hepatitis, mononucleosis, parasitic infections.
- Mast cell activation syndrome — non-IgE mast-cell hyperreactivity to a wide variety of triggers (foods, exercise, heat, stress, hormones).
- Autoimmune urticaria — immunoglobulin G (IgG) against immunoglobulin E or its receptor; associated with autoimmune thyroid disease, vitiligo, celiac disease.
- Physical triggers — pressure, cold, heat, sun, water, exercise.
- Environmental allergens — pollen, dust mite, animal dander.
- Hormonal — perimenstrual flares, menopause flushing, pregnancy.
- Carcinoid tumor and pheochromocytoma — rare but consider with sustained or paroxysmal flushing, diarrhea, palpitations, or hypertension.
- Mastocytosis — clonal mast-cell disease (cutaneous or systemic) with persistent skin lesions and recurrent anaphylaxis.
Mechanisms
- Mast-cell degranulation — histamine, tryptase, prostaglandin D2, leukotrienes, platelet-activating factor and cytokines released from skin and gut mast cells produce vasodilation, plasma extravasation (wheal), pruritus, and smooth-muscle effects.
- Immunoglobulin E-mediated — allergen cross-links immunoglobulin E on mast cells via the high-affinity FcεRI receptor; classic in food, drug, and insect-sting anaphylaxis.
- Non-IgE mast-cell activation — complement (C3a, C5a), neuropeptides (substance P), MRGPRX2 receptor signaling (vancomycin, opioids), physical stimuli, and idiopathic triggers in mast cell activation syndrome.
- Autoimmune urticaria — circulating immunoglobulin G autoantibodies against immunoglobulin E or FcεRI cross-link the receptor independent of allergen.
- Neurogenic flushing — vasodilatory neuropeptides released from sympathetic and parasympathetic nerves; rosacea, menopause, and emotional flushing.
- Tumor mediator release — serotonin, kallikrein, and other mediators from carcinoid tumors metastatic to liver.
Evaluation
- History — timing, duration of individual lesions, triggers, food and medication diary, recent infections, tick bites, geographic exposures.
- Physical exam — check for dermographism, look for residual pigmentation (suggests urticarial vasculitis), photograph or document active lesions when present.
- CBC, CMP, ESR, C-reactive protein (CRP), thyroid-stimulating hormone (TSH) and thyroid antibodies — baseline workup in chronic urticaria.
- Total immunoglobulin E and specific immunoglobulin E — if specific food or environmental trigger suspected.
- Alpha-gal immunoglobulin E — in any patient with delayed reactions to mammalian meat, particularly with tick exposure.
- Baseline serum tryptase — persistently elevated levels suggest mastocytosis; transient elevations during reactions support mast cell activation syndrome or anaphylaxis.
- 24-hour urinary N-methylhistamine, prostaglandin D2 metabolites — if mast cell activation syndrome suspected.
- Skin biopsy — if lesions last more than 24 hours, are painful, leave bruising, or are atypical (rule out urticarial vasculitis).
- 5-HIAA in 24-hour urine — if carcinoid suspected (sustained flushing with diarrhea).
- Plasma metanephrines — if pheochromocytoma suspected (paroxysmal flushing, hypertension, palpitations).
Management
- Trigger avoidance — food, medication, insect, alcohol, heat, exercise as identified.
- Second-generation H1 antihistamines — cetirizine, loratadine, fexofenadine, levocetirizine. The 2026 international urticaria guideline recommends raising the dose up to fourfold in chronic urticaria when the standard dose does not control symptoms; it notes that this higher dosing is off-label and that going above fourfold is not recommended because it has not been tested.
- H2 antihistamines — famotidine; helps in some patients, particularly with gastrointestinal symptoms.
- Mast-cell stabilizers — cromolyn sodium (oral for gastrointestinal symptoms), ketotifen, quercetin, luteolin; particularly useful in mast cell activation syndrome.
- Leukotriene receptor antagonists — montelukast as adjunct in chronic urticaria, particularly aspirin-exacerbated.
- Omalizumab — anti-IgE monoclonal antibody; transformative for refractory chronic spontaneous urticaria. The 2026 international guideline places omalizumab as the next step for people who do not get enough benefit from a second-generation H1 antihistamine.
- Dupilumab — an injected antibody that blocks interleukin-4 and interleukin-13 signalling. In the LIBERTY-CSU CUPID trials, it reduced hive and itch scores more than placebo in 138 people with chronic spontaneous urticaria who had never used omalizumab (Study A); in 108 people who had not done well on or could not tolerate omalizumab (Study B), the effect was small and the main goal was not met. The current U.S. label (DailyMed) lists dupilumab for adults and children aged 2 years and older with chronic spontaneous urticaria who remain symptomatic despite H1 antihistamine treatment.
- Remibrutinib — a pill that blocks the enzyme Bruton's tyrosine kinase. In two identical trials (REMIX-1 with 470 people and REMIX-2 with 455, all with chronic spontaneous urticaria that continued after second-generation H1 antihistamines), hives and itch were completely gone (urticaria activity score UAS7 of 0) at week 12 in 31.1% and 27.9% of people on remibrutinib, against 10.5% and 6.5% on placebo; small pinpoint skin bleeds (petechiae) were more common on the drug (3.8% vs 0.3%). A pooled safety analysis of the same trials (606 people on remibrutinib, 306 on placebo) found the same rate of any side effect (64.9% vs 64.7%) and of infections (33.5% vs 34.3%), but more mostly mild skin and mucous-membrane bleeding such as petechiae (9.1% vs 2.0%). The current U.S. label (DailyMed) lists remibrutinib for adults with chronic spontaneous urticaria or symptomatic dermographism who remain symptomatic despite H1 antihistamine treatment.
- Cyclosporine — for severe, antihistamine-resistant chronic urticaria. The 2026 international guideline notes that it is off-label for urticaria, has more side effects (especially with long-term use), and is recommended only for severe disease that has not responded to licensed treatments.
- Short courses of corticosteroids — for severe acute flares. The 2026 international guideline describes a short course of at most 10 days for acute urticaria and flares of chronic spontaneous urticaria, and strongly recommends against prolonged use, because the doses needed (20–50 mg a day of prednisone or its equivalent in adults) cause side effects over the long term.
- Epinephrine auto-injector — prescribed for any patient with prior anaphylaxis, alpha-gal syndrome, or systemic mast cell activation syndrome.
- Low-histamine diet trial — when histamine intolerance is suspected, with symptoms reassessed after 4–6 weeks.
- Treating the underlying disease — thyroid replacement in autoimmune thyroiditis, somatostatin analogs for carcinoid, alpha-blockade for pheochromocytoma.
The 2026 international urticaria guideline (developed with 210 delegates from 107 societies in 59 countries; consensus conference December 2024) lays out a stepwise treatment algorithm: a second-generation H1 antihistamine at the standard dose, then up to four times that dose, then omalizumab. It describes dupilumab and remibrutinib as add-on treatments with phase 3 results, and keeps ciclosporin for severe disease that has not responded to licensed treatments. The guideline also states that omalizumab, dupilumab and remibrutinib are limited in practice by their high cost. It updates the 2018 and 2022 versions of the same guideline.
When to Seek Medical Care
- Difficulty breathing, throat tightness, hoarseness, or tongue swelling — suspect anaphylaxis, use epinephrine, call 911.
- Fainting, drop in blood pressure, or rapid pulse with hives.
- Hives with high fever, joint pain, or weight loss (consider urticarial vasculitis or systemic disease).
- Individual lesions lasting more than 24 hours, painful, or leaving bruises.
- Hives in a pregnant woman with abdominal pain, jaundice, or pruritus without rash (rule out cholestasis of pregnancy).
- Sustained flushing with diarrhea, weight loss, or wheezing (rule out carcinoid).
- Paroxysmal flushing with hypertension, palpitations, headache (rule out pheochromocytoma).
Connections
- All Symptoms
- Mast Cell Activation Syndrome
- Alpha-Gal Syndrome
- Allergies
- Brain Fog
- Rosacea
- Eczema
- Hashimoto's Thyroiditis
- Bloating
- Postural Orthostatic Tachycardia Syndrome
- Food Intolerance
- Postural Orthostatic Tachycardia Syndrome/Mast Cell Activation Syndrome/EDS Triad
- Alpha-Gal Natural History
- Asthma
- Pheochromocytoma
- Celiac Disease
- Anaphylaxis Emergency Plan
- Itching (Pruritus)
Key Research Papers
- Zuberbier T, Aberer W, Asero R, et al. The EAACI/GA2LEN/EDF/WAO guideline for the definition, classification, diagnosis and management of urticaria. Allergy. 2018;73(7):1393-1414. — doi:10.1111/all.13397
- Zuberbier T, Abdul Latiff AH, Abuzakouk M, et al. The international EAACI/GA²LEN/EuroGuiDerm/APAAACI guideline for the definition, classification, diagnosis, and management of urticaria. Allergy. 2022;77(3):734-766. — doi:10.1111/all.15090
- Zuberbier T, Ansari ZA, Abdul Latiff AH, et al. The International Guideline for the Definition, Classification, Diagnosis and Management of Urticaria. Allergy. 2026;81(8):2582-2632. — doi:10.1111/all.70210
- Maurer M, Rosen K, Hsieh HJ, et al. Omalizumab for the treatment of chronic idiopathic or spontaneous urticaria. New England Journal of Medicine. 2013;368(10):924-935. — doi:10.1056/NEJMoa1215372
- Metz M, Giménez-Arnau A, Hide M, et al. Remibrutinib in chronic spontaneous urticaria. New England Journal of Medicine. 2025;392(10):984-994. — doi:10.1056/NEJMoa2408792
- Giménez-Arnau AM, Zharkov A, Yang B, et al. Safety of remibrutinib in chronic spontaneous urticaria: a pooled analysis of REMIX-1 and REMIX-2 trials. Journal of Allergy and Clinical Immunology: In Practice. 2026;14(8):1901-1913. — doi:10.1016/j.jaip.2026.05.027
- Maurer M, Casale TB, Saini SS, et al. Dupilumab in patients with chronic spontaneous urticaria (LIBERTY-CSU CUPID): two randomized, double-blind, placebo-controlled, phase 3 trials. Journal of Allergy and Clinical Immunology. 2024;154(1):184-194. — doi:10.1016/j.jaci.2024.01.028
- Akin C, Valent P, Metcalfe DD. Mast cell activation syndrome: proposed diagnostic criteria. Journal of Allergy and Clinical Immunology. 2010;126(6):1099-1104. — doi:10.1016/j.jaci.2010.08.035
- Commins SP, Satinover SM, Hosen J, et al. Delayed anaphylaxis, angioedema, or urticaria after consumption of red meat in patients with IgE antibodies specific for galactose-α-1,3-galactose. Journal of Allergy and Clinical Immunology. 2009;123(2):426-433. — doi:10.1016/j.jaci.2008.10.052
- Valent P, Akin C, Bonadonna P, et al. Proposed diagnostic algorithm for patients with suspected mast cell activation syndrome. Journal of Allergy and Clinical Immunology: In Practice. 2019;7(4):1125-1133. — doi:10.1016/j.jaip.2019.01.006
- Saini SS, Kaplan AP. Chronic spontaneous urticaria: the devil's itch. Journal of Allergy and Clinical Immunology: In Practice. 2018;6(4):1097-1106. — doi:10.1016/j.jaip.2018.04.013
- Khan DA. Chronic urticaria: diagnosis and management. Allergy and Asthma Proceedings. 2008;29(5):439-446. — doi:10.2500/aap.2008.29.3151
- Wilson JM, Schuyler AJ, Workman L, et al. Investigation into the α-Gal syndrome: characteristics of 261 children and adults reporting red meat allergy. Journal of Allergy and Clinical Immunology: In Practice. 2019;7(7):2348-2358.e4. — doi:10.1016/j.jaip.2019.03.031
- Maintz L, Novak N. Histamine and histamine intolerance. American Journal of Clinical Nutrition. 2007;85(5):1185-1196. — doi:10.1093/ajcn/85.5.1185
- Izikson L, English JC III, Zirwas MJ. The flushing patient: differential diagnosis, workup, and treatment. Journal of the American Academy of Dermatology. 2006;55(2):193-208. — doi:10.1016/j.jaad.2005.07.057
PubMed Topic Searches
Featured Videos
