Chronic Diarrhea

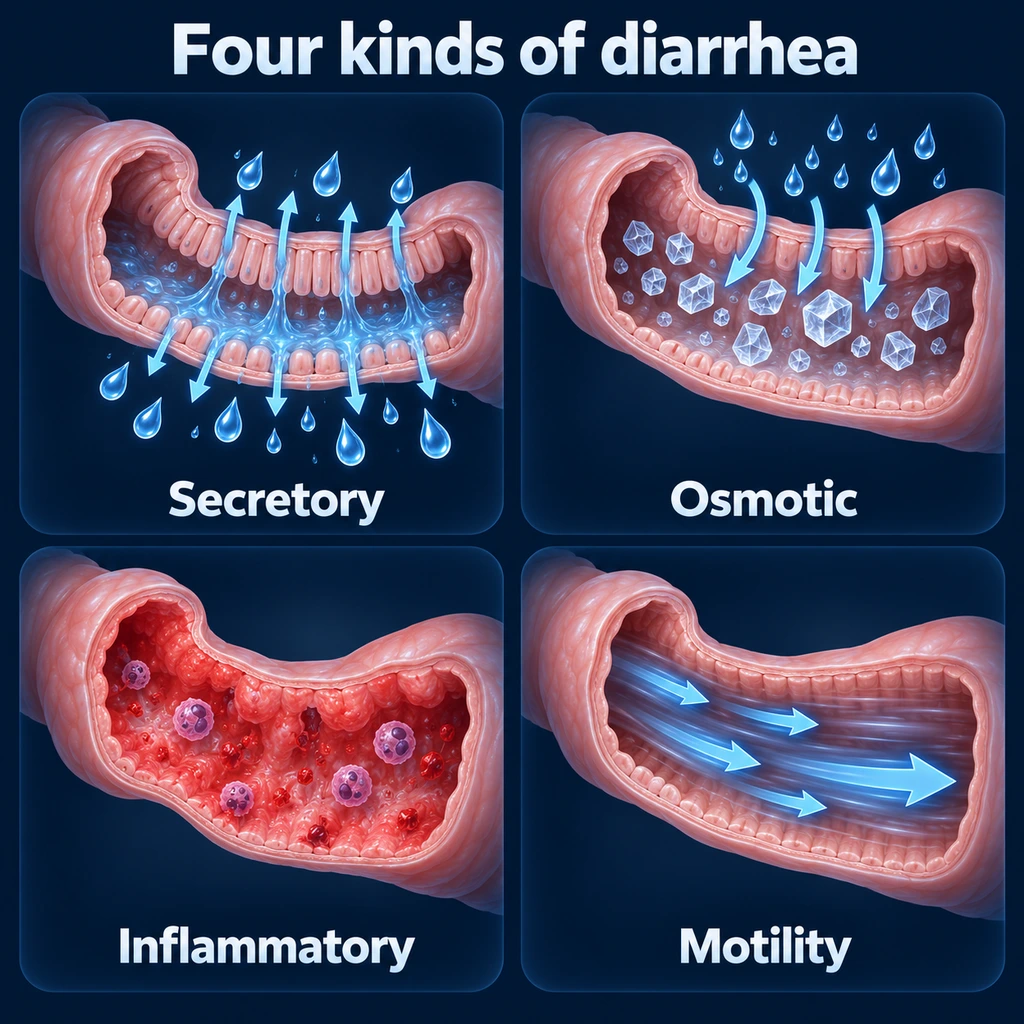
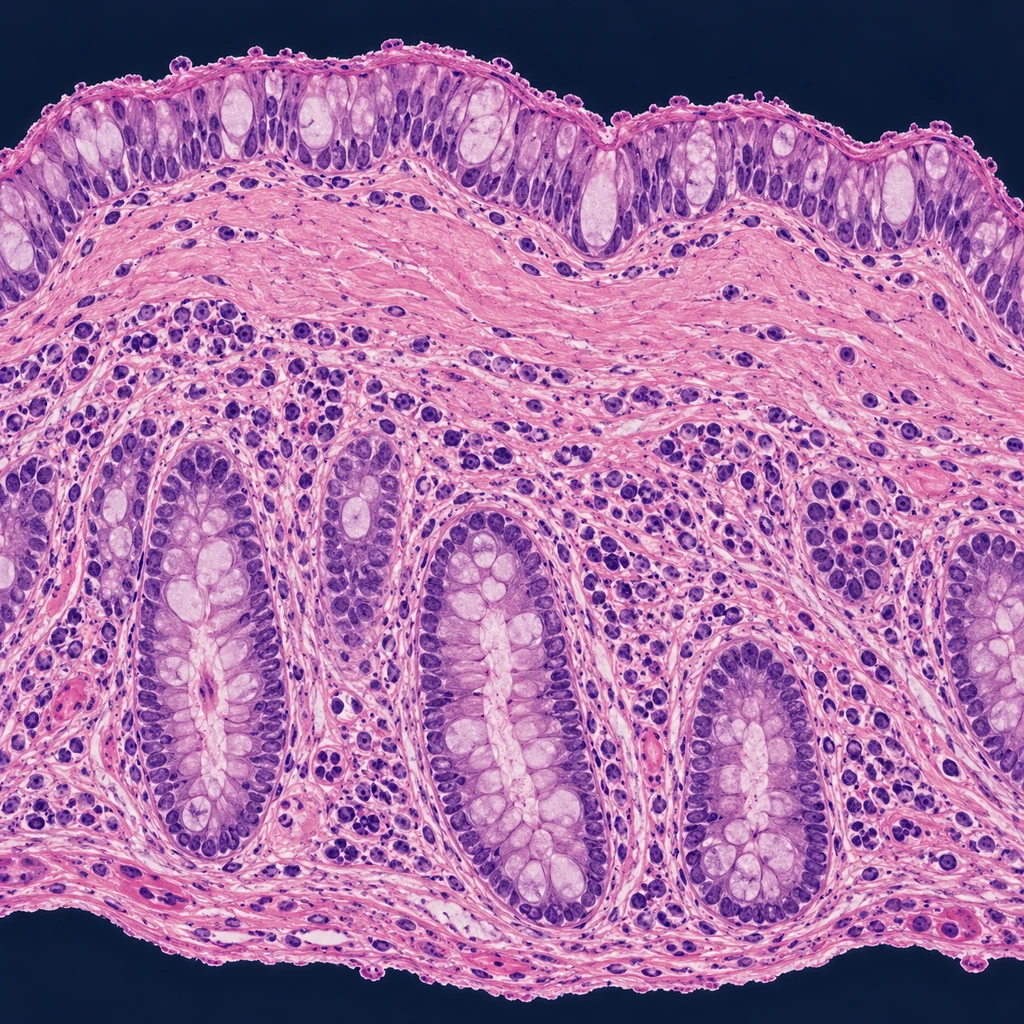
Table of Contents
Overview
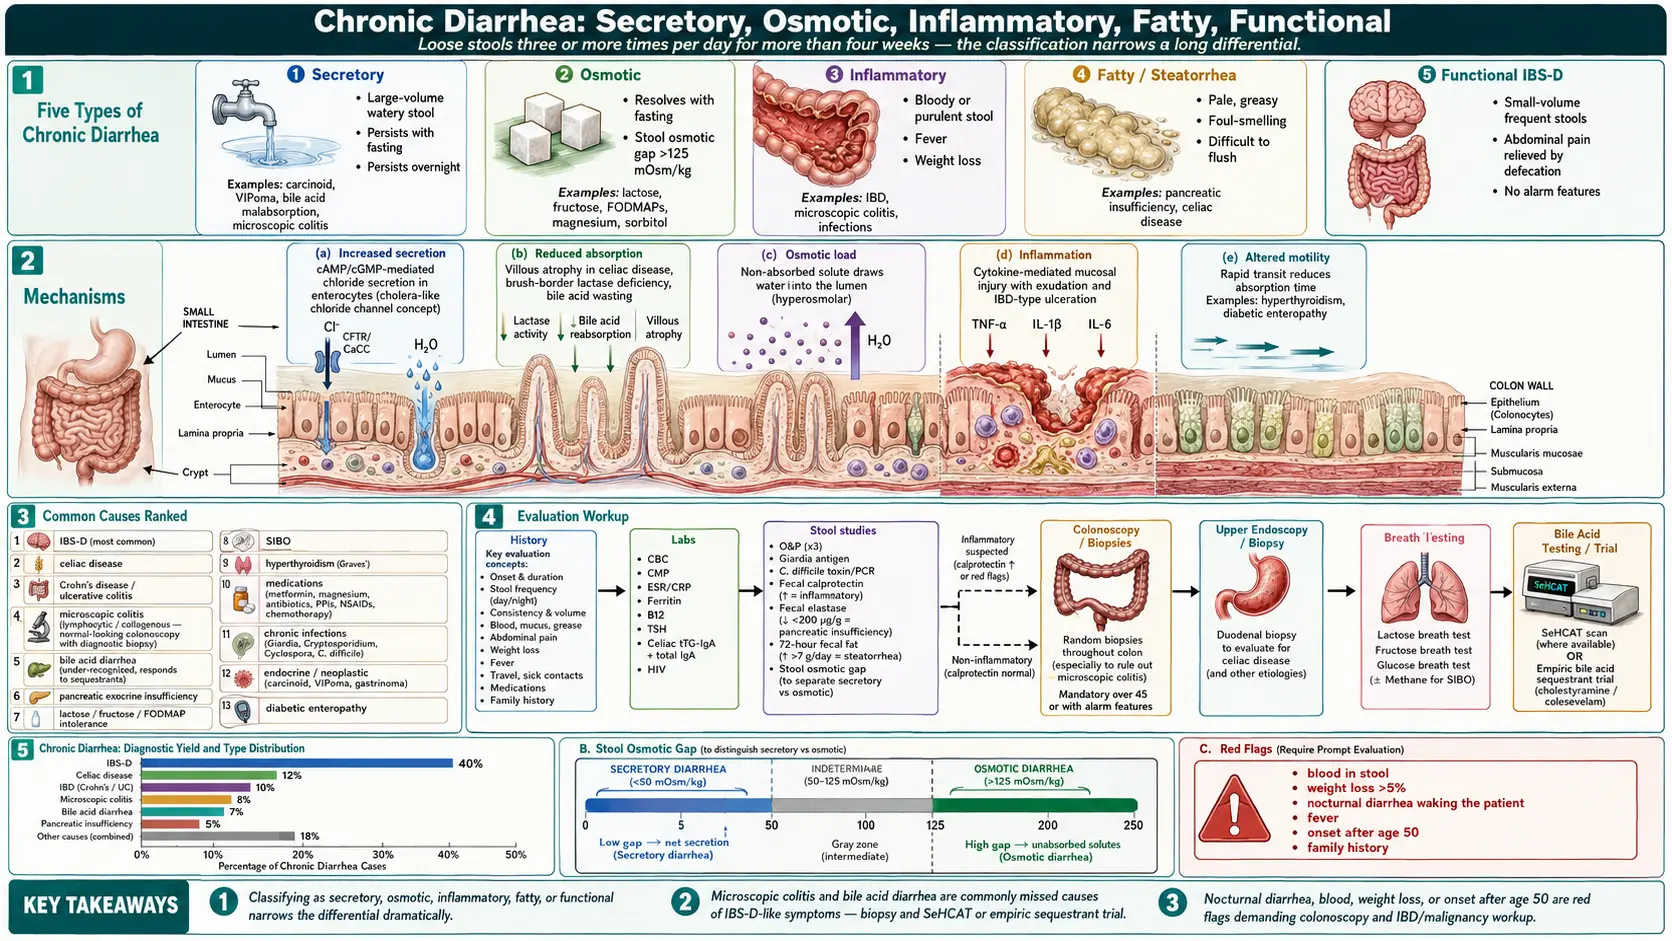
Chronic diarrhea is loose or watery stools occurring three or more times per day, persisting for more than four weeks. It is one of the most common reasons for gastroenterology referral, and unlike acute diarrhea (which is almost always infectious and self-limited), chronic diarrhea has a long differential that includes irritable bowel syndrome, celiac disease, inflammatory bowel disease, microscopic colitis, bile acid malabsorption, lactose and fructose intolerance, hyperthyroidism, and pancreatic insufficiency. The classic categorization — secretory, osmotic, inflammatory, and motility-related — helps narrow the workup.
Types of Chronic Diarrhea
- Secretory — large-volume, watery stools that persist with fasting; persistent overnight; due to abnormal ion transport. Causes include carcinoid, VIPoma (a tumor that releases vasoactive intestinal peptide), bile acid malabsorption, microscopic colitis.
- Osmotic — resolves with fasting; stool osmotic gap >125 mOsm/kg. Causes include lactose / fructose / FODMAP intolerance, magnesium-containing laxatives, sorbitol.
- Inflammatory — bloody or pus-containing stool, fever, weight loss, abdominal pain. Inflammatory bowel disease (IBD), microscopic colitis, infections.
- Fatty (steatorrhea) — pale, greasy, foul-smelling, hard to flush. Pancreatic insufficiency, celiac, small-bowel disease.
- Functional (diarrhea-predominant irritable bowel syndrome, IBS-D) — small-volume frequent stools associated with abdominal pain; relieved by defecation; no alarm features.
Common Causes
- Irritable bowel syndrome (diarrhea-predominant irritable bowel syndrome) — the most common cause; functional, with normal labs and imaging.
- Celiac disease — gluten-driven small-bowel inflammation.
- Crohn's disease and ulcerative colitis — chronic inflammatory bowel disease.
- Microscopic colitis (lymphocytic, collagenous) — large-volume watery diarrhea with normal-looking colonoscopy; biopsy is diagnostic.
- Bile acid diarrhea — under-recognized cause of diarrhea-predominant irritable bowel syndrome-like symptoms; responds to bile acid sequestrants. It is common rather than rare: a 2016 meta-analysis of 36 studies (5,028 patients with functional bowel disorders with diarrhea) found an abnormal SeHCAT test in about 31% of those tested with it, and, averaged across the different tests, evidence of bile acid diarrhea in about 25%.
- Pancreatic exocrine insufficiency — chronic pancreatitis, cystic fibrosis, pancreatic resection; presents with steatorrhea and weight loss.
- Lactose, fructose, FODMAP intolerance — osmotic diarrhea after specific foods.
- Small intestinal bacterial overgrowth — particularly in patients with motility disorders or surgical history.
- Hyperthyroidism (Graves' disease) — rapid gastrointestinal (GI) transit causes diarrhea.
- Medications — metformin, magnesium, antibiotics, proton pump inhibitors (PPIs), nonsteroidal anti-inflammatory drugs (NSAIDs), chemotherapy.
- Infections (chronic) — Giardia, Cryptosporidium, Cyclospora, Clostridioides difficile, post-infectious irritable bowel syndrome (IBS).
- Endocrine and neoplastic — carcinoid syndrome, VIPoma, gastrinoma (Zollinger-Ellison), medullary thyroid cancer.
- Diabetic enteropathy — autonomic neuropathy with rapid transit.
Mechanisms
- Increased secretion — abnormal cAMP- or cGMP-mediated chloride secretion from enterocytes (cholera-like).
- Reduced absorption — mucosal injury (celiac, inflammatory bowel disease), brush-border enzyme deficiency (lactase), bile acid wasting.
- Osmotic load — non-absorbed solutes (lactose, fructose, FODMAPs, magnesium, mannitol) draw water into the lumen.
- Inflammation — cytokine-mediated mucosal injury and exudation.
- Altered motility — rapid transit reduces absorption time; relevant in hyperthyroidism, diarrhea-predominant irritable bowel syndrome, diabetic enteropathy.
Evaluation
The British Society of Gastroenterology's guideline for investigating chronic diarrhoea in adults (3rd edition, 2018), written by a 13-member group that graded its evidence with the GRADE system, is one of the main references for these tests.
- History — duration, stool description, weight loss, blood, nocturnal symptoms, travel, food triggers, medications, family history of inflammatory bowel disease or celiac.
- Bloodwork — complete blood count (CBC), comprehensive metabolic panel (CMP), erythrocyte sedimentation rate (ESR)/C-reactive protein (CRP), ferritin, B12, thyroid-stimulating hormone (TSH), celiac serology (tissue transglutaminase immunoglobulin A antibody, tTG-IgA, + total immunoglobulin A, IgA), human immunodeficiency virus (HIV).
- Stool studies — ova and parasites, Giardia antigen, C. difficile, fecal calprotectin (separates inflammatory from functional), fecal elastase (pancreatic insufficiency).
- 72-hour fecal fat — for steatorrhea workup.
- Stool osmotic gap — secretory vs osmotic.
- Colonoscopy with random biopsies — rules out microscopic colitis and inflammatory bowel disease; used when alarm features are present, and US colorectal cancer screening (US Preventive Services Task Force, 2021) begins at age 45.
- Upper endoscopy with duodenal biopsy — if celiac or small-bowel disease suspected.
- Hydrogen / methane breath testing — lactose, fructose, small intestinal bacterial overgrowth (SIBO); see the Breath Test Guide.
- SeHCAT (75selenium homotaurocholic acid) retention test — a single nuclear-medicine test for bile acid diarrhea; retention below 10% is read as abnormal. It is not widely available outside Europe and Canada, including in the U.S.
- Empiric trial of bile acid sequestrant — in suspected bile acid diarrhea when SeHCAT is not available.
Management
- Treat the underlying cause — gluten-free diet for celiac, biologics for inflammatory bowel disease, levothyroxine taper or treatment for hyperthyroidism, pancreatic enzymes for insufficiency, rifaximin for small intestinal bacterial overgrowth, bismuth or budesonide for microscopic colitis.
- Diarrhea-predominant irritable bowel syndrome — low-FODMAP (fermentable oligosaccharides, disaccharides, monosaccharides and polyols) diet, soluble fiber, peppermint oil, antispasmodics, eluxadoline, alosetron, rifaximin, low-dose tricyclics, gut-directed hypnotherapy. The 2022 American Gastroenterological Association (AGA) guideline on medicines for IBS with diarrhea graded the evidence: it made conditional recommendations for eluxadoline, rifaximin and alosetron (moderate-certainty evidence), loperamide (very low certainty), and tricyclic antidepressants and antispasmodics (low certainty), and a conditional recommendation against selective serotonin reuptake inhibitor (SSRI) antidepressants (low certainty).
- Bile acid sequestrants — cholestyramine, colesevelam, colestipol for bile acid diarrhea.
- Loperamide — symptomatic, after infection ruled out and root cause being addressed; in the 2022 AGA guideline its evidence in IBS with diarrhea was rated very low certainty.
- Diet modification — lactose-free, low-FODMAP, fat-restricted (in steatorrhea), gluten-free (in celiac).
- Hydration and electrolyte repletion — oral rehydration solutions in severe diarrhea.
- Probiotics — mixed evidence; Saccharomyces boulardii for antibiotic-associated diarrhea.
Warning Signs Doctors Treat as Urgent
- Blood in the stool, melena, or persistent rectal bleeding.
- Unintentional weight loss greater than 5 percent of body weight.
- Nocturnal diarrhea waking the patient from sleep.
- Persistent fever with diarrhea.
- Severe abdominal pain or progressive distension.
- Signs of dehydration (dizziness, decreased urine output).
- Diarrhea after recent travel, antibiotics, or hospitalization.
- Family history of colon cancer, inflammatory bowel disease, or celiac disease.
- New onset at age 45 or older (the age at which US colorectal cancer screening begins); doctors look for cancer and microscopic colitis.
Connections
- All Symptoms
- Irritable Bowel Syndrome
- Celiac Disease
- Inflammatory Bowel Disease
- Small Intestinal Bacterial Overgrowth
- Crohn's Disease
- Graves' Disease
- Abdominal Pain
- Small Intestinal Bacterial Overgrowth Breath Test Guide
- Constipation
- Gut Healing
- Bloating
- Gluten-Free Diet Guide
- Ulcerative Colitis
- Magnesium
- Peppermint
- Surgery Decisions Resection J Pouch Ostomy
- Bile Acid Malabsorption in Irritable Bowel Syndrome D
Key Research Papers
Historical Background
The 1971 publication of the bile acid diarrhea concept (Hofmann), the 1980 description of microscopic colitis (Read), and the 2015 validation of a blood test for anti-CdtB and anti-vinculin antibodies in diarrhea-predominant irritable bowel syndrome each transformed pieces of what had been called "functional diarrhea" into specific diagnoses with targeted treatments.
Key Research Papers
- Smalley W, Falck-Ytter C, Carrasco-Labra A, Wani S, Lytvyn L, Falck-Ytter Y. AGA clinical practice guidelines on the laboratory evaluation of functional diarrhea and diarrhea-predominant irritable bowel syndrome in adults. Gastroenterology. 2019;157(3):851-854. — doi:10.1053/j.gastro.2019.07.004
- Vijayvargiya P, Camilleri M, Carlson P, et al. Performance characteristics of serum C4 and FGF19 measurements to exclude the diagnosis of bile acid diarrhoea in IBS-diarrhoea and functional diarrhoea. Alimentary Pharmacology & Therapeutics. 2017;46(6):581-588. — doi:10.1111/apt.14214
- Schiller LR, Pardi DS, Sellin JH. Chronic diarrhea: diagnosis and management. Clinical Gastroenterology and Hepatology. 2017;15(2):182-193. — doi:10.1016/j.cgh.2016.07.028
- Pardi DS, Kelly CP. Microscopic colitis. Gastroenterology. 2011;140(4):1155-1165. — doi:10.1053/j.gastro.2011.02.003
- Mayer EA, Savidge T, Shulman RJ. Brain-gut microbiome interactions and functional bowel disorders. Gastroenterology. 2014;146(6):1500-1512. — doi:10.1053/j.gastro.2014.02.037
- Halmos EP, Power VA, Shepherd SJ, Gibson PR, Muir JG. A diet low in FODMAPs reduces symptoms of irritable bowel syndrome. Gastroenterology. 2014;146(1):67-75. — doi:10.1053/j.gastro.2013.09.046
- Hill ID, Fasano A, Guandalini S, et al. NASPGHAN clinical report on the diagnosis and treatment of gluten-related disorders. Journal of Pediatric Gastroenterology and Nutrition. 2016;63(1):156-165. PubMed PMID: 27035374
- Lacy BE, Pimentel M, Brenner DM, et al. ACG clinical guideline: management of irritable bowel syndrome. American Journal of Gastroenterology. 2021;116(1):17-44. — doi:10.14309/ajg.0000000000001036
- Vijayvargiya P, Busciglio I, Burton D, Donato L, Lueke A, Camilleri M. Bile acid deficiency in a subgroup of patients with irritable bowel syndrome with constipation based on biomarkers in serum and fecal samples. Clinical Gastroenterology and Hepatology. 2018;16(4):522-527. — doi:10.1016/j.cgh.2017.06.039
- Pimentel M, Morales W, Rezaie A, et al. Development and validation of a biomarker for diarrhea-predominant irritable bowel syndrome in human subjects. PLoS One. 2015;10(5):e0126438. — doi:10.1371/journal.pone.0126438
- Valentin N, Camilleri M, Altayar O, Vijayvargiya P, Acosta A, Nelson AD, Murad MH. Biomarkers for bile acid diarrhoea in functional bowel disorder with diarrhoea: a systematic review and meta-analysis. Gut. 2016;65(12):1951-1959. — PubMed PMID: 26347530
- Lembo A, Sultan S, Chang L, Heidelbaugh JJ, Smalley W, Verne GN. AGA clinical practice guideline on the pharmacological management of irritable bowel syndrome with diarrhea. Gastroenterology. 2022;163(1):137-151. — PubMed PMID: 35738725
- Arasaradnam RP, Brown S, Forbes A, et al. Guidelines for the investigation of chronic diarrhoea in adults: British Society of Gastroenterology, 3rd edition. Gut. 2018;67(8):1380-1399. — PubMed PMID: 29653941
- US Preventive Services Task Force, Davidson KW, Barry MJ, et al. Screening for colorectal cancer: US Preventive Services Task Force recommendation statement. JAMA. 2021;325(19):1965-1977. — PubMed PMID: 34003218
PubMed Topic Searches
Featured Videos