Postmenopausal Osteoporosis and Hormone Therapy
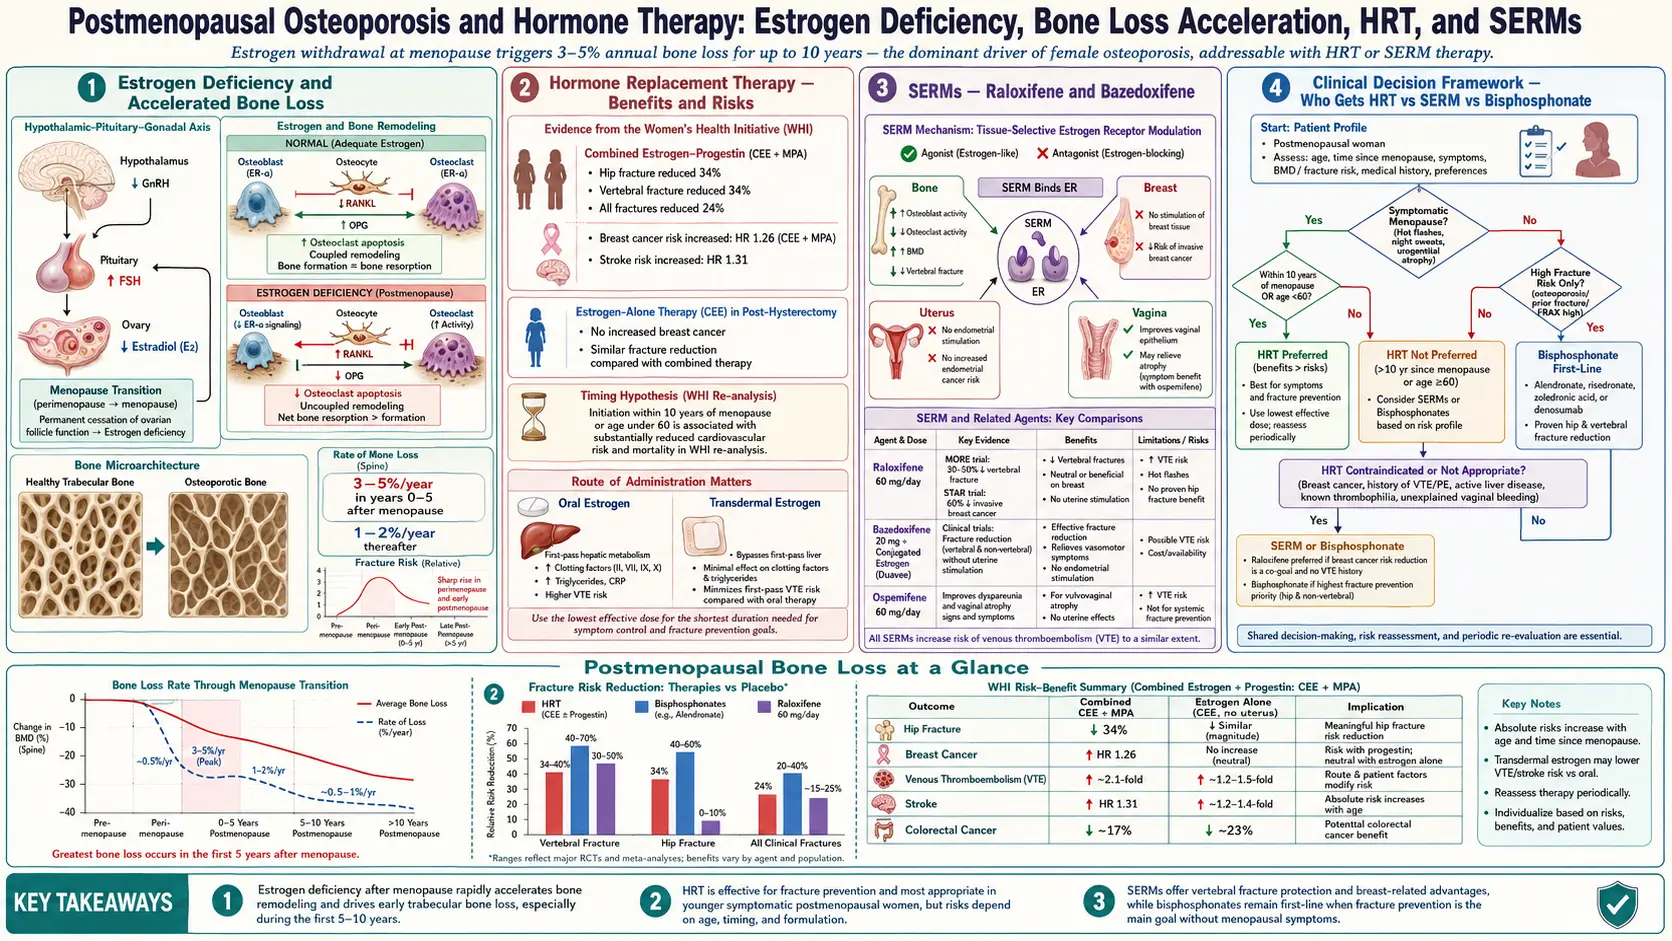
Table of Contents
- Why Menopause Hammers Your Skeleton
- The Bone Loss Pattern — Years 1 to 10
- Type I Primary Osteoporosis
- What Estrogen Actually Does to Bone
- The WHI Study — What It Really Showed
- The Timing Hypothesis — Age of Initiation Matters
- Hormone Therapy and Fracture Reduction
- Transdermal vs Oral Estrogen — The VTE Difference
- Why Progesterone Is Paired with Estrogen When the Uterus Is Intact
- SERMs — Raloxifene and the MORE Trial
- Bazedoxifene / Conjugated Estrogens
- Tibolone — The European Option
- When a Bisphosphonate Beats Hormone Therapy
- How Long to Stay on Hormone Therapy
- What Happens When HT Stops
- High-Risk Patients — Combining or Switching
- Non-Hormonal Options When HT Is Off the Table
- What Clinicians Weigh Before Hormone Therapy
- Key Research Papers
- Connections
- Featured Videos
Why Menopause Hammers Your Skeleton
For most of your adult life, your skeleton is in a slow, steady remodeling loop. Cells called osteoclasts chew away small patches of old bone; cells called osteoblasts follow behind and lay down fresh bone in the same spot. For roughly thirty years — from peak bone mass in your late twenties until your mid-forties — the two teams stay nearly balanced, with maybe a 0.3–0.5% loss per year.
Then estrogen levels start falling. The ovaries wind down across perimenopause, and the final menstrual period marks a sharp cliff in circulating estradiol — from premenopausal levels of 50–400 pg/mL down to under 20 pg/mL within a year or two. Estrogen was quietly doing three things for your skeleton every single day: restraining the osteoclasts, prolonging the life of osteoblasts, and dampening inflammatory signals (especially RANKL) that recruit new bone-chewing cells. When estrogen drops, all three brakes release at once.
The result is the most rapid bone loss any healthy adult experiences outside of disease. A woman can lose more bone density in the five years after her final period than she lost in the previous twenty. This is not a gentle glide path. It is a free fall followed by a shallower but permanent descent.
The Bone Loss Pattern — Years 1 to 10
The numbers that matter to you, broken into phases:
- Perimenopause (roughly ages 45–51). Bone loss accelerates modestly — about 0.5–1% per year — even before periods stop.
- Early postmenopause (year 0 through year 3–5). The steepest phase. Trabecular (spongy) bone in the spine and inner hip loses 3–5% per year. Cortical (dense outer) bone loses roughly 1–2%. Over five years, that adds up to a 10–25% reduction in spinal bone density for an untreated woman.
- Late postmenopause (year 5 onward). The curve flattens to roughly 1–2% per year, a rate that continues for the rest of life. This slower loss is still substantial — another 20% over the next two decades.
Two women the same age can look entirely different on a DEXA scan depending on where they sit in this timeline. A 52-year-old who reached menopause at 48 is mid-avalanche. A 52-year-old whose periods stopped at 51 has barely started. Treatment decisions often hinge on which phase you are in — not just your T-score. See DEXA Scan, T-Score, and Z-Score Explained for the numbers that define osteopenia and osteoporosis.
Type I Primary Osteoporosis
Clinicians still use the old Riggs-Melton classification. Type I (postmenopausal) osteoporosis is the estrogen-deficiency form. It hits women six times more often than men, peaks in the 15 years after menopause, and preferentially damages trabecular bone — which is why the vertebrae and distal radius (wrist) are the early fracture sites. The classic presentation: a woman in her late fifties or sixties sustains a Colles fracture after a minor fall, or develops unexplained back pain that turns out to be a vertebral compression fracture.
Type II (senile) osteoporosis, by contrast, affects both sexes, peaks after age 70, and damages cortical bone more broadly. The hallmark fracture is the hip. In practice the two types blur — a 75-year-old woman usually has both processes stacked on top of each other — but the distinction matters because the early postmenopausal phase is the window where estrogen replacement is most mechanistically sensible.
What Estrogen Actually Does to Bone
At the cell level, estrogen works through the RANK / RANKL / OPG system. RANKL is a signaling molecule that osteoblasts (and immune cells) release to recruit and activate osteoclasts. OPG (osteoprotegerin) is a decoy receptor that mops up RANKL and blocks its signal. Estrogen suppresses RANKL production and boosts OPG. When estrogen falls, RANKL rises, OPG falls, and osteoclast activity surges.
Estrogen also lengthens osteoblast lifespan (osteoblasts die off faster without it) and shortens osteoclast lifespan (osteoclasts linger longer and chew more bone without it). The result of combining all three effects is what bone researchers call an uncoupled remodeling state — resorption running ahead of formation, with every remodeling cycle leaving a net bone deficit.
This is why hormone therapy is the single most physiologically direct osteoporosis treatment available. Bisphosphonates slow osteoclasts chemically; denosumab blocks RANKL directly; hormone therapy restores the upstream signal that controlled everything else.
The WHI Study — What It Really Showed
The Women's Health Initiative (WHI) is the single most influential — and most misread — study in the history of hormone therapy. Two randomized arms mattered: the estrogen-plus-progestin arm (n = 16,608, using conjugated equine estrogens 0.625 mg plus medroxyprogesterone acetate 2.5 mg daily) and the estrogen-alone arm (n = 10,739, conjugated equine estrogens in women with prior hysterectomy).
The combined arm was halted early in 2002 amid headlines about elevated breast cancer, stroke, coronary events, and venous thromboembolism (VTE). What the headlines buried:
- Hip fractures fell by 34%. Clinical vertebral fractures fell by 34%. Total fractures fell by 24%. This was the first randomized trial ever to prove hormone therapy cut hip fractures (hazard ratio 0.66; in absolute terms, 5 fewer hip fractures per 10,000 women per year). All-cause mortality was not affected during the trial, and the authors concluded that, overall, health risks exceeded benefits for this regimen over the average 5.2-year follow-up.
- The average participant age was 63, with many women 15+ years past menopause — the wrong population to enroll for a cardiovascular primary-prevention trial.
- The estrogen-alone arm (hysterectomized women) showed no increase in breast cancer (104 versus 135 invasive breast cancers during the intervention, hazard ratio 0.79, not statistically significant) — and later follow-up showed a significant decrease (168 versus 216 cases cumulatively, hazard ratio 0.79, 95% CI 0.65–0.97; Manson 2013).
- The absolute risk increases were small — on the order of 8 additional breast cancers per 10,000 women per year in the combined arm.
A generation of women were taken off hormone therapy on the basis of relative-risk headlines that did not apply to women in their early fifties using modern formulations.
The 2025 label change. On 10 November 2025 the FDA announced that it is initiating removal of the broad boxed (“black box”) warnings from menopausal hormone therapy products. The agency is working with companies to remove label references to risks of cardiovascular disease, breast cancer and probable dementia; it is not seeking to remove the boxed warning for endometrial cancer on systemic estrogen-alone products. The announcement said the WHI participants averaged 63 years of age — over a decade past the average age of menopause — and were given a hormone formulation no longer in common use. The FDA’s labeled recommendation will be to start systemic hormone therapy within 10 years of menopause onset or before age 60.
The Timing Hypothesis — Age of Initiation Matters
When researchers reanalyzed the WHI data by age and years-since-menopause, a cleaner picture emerged. Women who started hormone therapy within ten years of menopause or before age 60 had:
- Reduced all-cause mortality (hazard ratio roughly 0.70–0.75).
- No increase — and possibly a decrease — in coronary heart disease.
- Strong fracture protection.
- Modest, delayed breast-cancer risk (combined HT only).
Women who started HT 20+ years past menopause or after age 70 had the opposite: more cardiovascular events, more strokes, and no mortality benefit. The hypothesis: young postmenopausal arteries are still healthy and respond to estrogen with vasodilation and lipid benefits. Older arteries with established atherosclerotic plaque are destabilized by estrogen instead.
The clinical translation is now codified in North American Menopause Society (NAMS) 2022 and Endocrine Society guidelines: hormone therapy is reasonable for symptomatic women under 60 or within 10 years of menopause, and that window also provides the most favorable risk profile for bone protection.
Hormone Therapy and Fracture Reduction
Across the major randomized trials and meta-analyses, hormone therapy reduces fractures at every skeletal site studied:
- Hip: approximately 30–40% reduction.
- Vertebral (spine): approximately 30–35% reduction.
- Wrist: approximately 20–30% reduction.
- Total fractures: approximately 20–25% reduction.
Importantly, the WHI showed these reductions even in women with normal baseline bone density. Most osteoporosis drugs only work in women who already have osteoporosis; hormone therapy is one of the few proven interventions in the larger osteopenic population. That makes it a uniquely useful tool in the first decade after menopause, when T-scores have often drifted into osteopenia (−1.0 to −2.4) but not yet reached osteoporosis (≤−2.5).
The WHI fracture numbers (Cauley 2003). Over an average of 5.6 years, 733 of 8,506 women (8.6%) taking estrogen plus progestin had a fracture, compared with 896 of 8,102 (11.1%) on placebo (hazard ratio 0.76). In the 1,024 women whose bone density was scanned, total hip density rose 3.7% after 3 years of treatment versus 0.14% on placebo. The lower fracture risk appeared in every subgroup examined — by age, body weight, smoking, falls, fracture history, calcium intake, past hormone use and bone density. But when the trial’s global index of other outcomes (heart disease, stroke, blood clots in the lungs, cancers and death) was counted alongside fractures, there was no net benefit, even in women at high risk of fracture.
Transdermal vs Oral Estrogen — The VTE Difference
Not all estrogen is delivered equally. Oral estrogen passes through the liver first, raising hepatic production of clotting factors and C-reactive protein. Transdermal estrogen (patch, gel, or spray) bypasses first-pass metabolism and enters the bloodstream directly.
The clinical consequence: observational cohort studies (notably the French ESTHER study) and subsequent meta-analyses show that oral estrogen roughly doubles the risk of venous thromboembolism (deep vein thrombosis and pulmonary embolism), while transdermal estrogen at standard doses carries no measurable increase. Stroke risk shows a similar pattern — elevated with oral, neutral with transdermal.
Current practice for any woman with baseline VTE risk factors (obesity, prior clot, Factor V Leiden, migraine with aura, heavy smoker, age over 60) is to default to transdermal estradiol. Typical starting doses: a 0.025–0.05 mg/day estradiol patch or a pump of 0.06% estradiol gel. Bone-protective doses generally start at 0.05 mg/day patch.
Why Progesterone Is Paired with Estrogen When the Uterus Is Intact
Unopposed estrogen stimulates the uterine lining and substantially increases the risk of endometrial hyperplasia and endometrial cancer. Women who still have a uterus take a progestogen alongside estrogen to keep the lining in check; this is why the FDA is keeping the endometrial-cancer boxed warning on estrogen-alone products. The options:
- Micronized progesterone (100–200 mg nightly). Chemically identical to the body's own progesterone. Sedating, so it is usually taken at bedtime. Generally considered the most favorable profile for breast and cardiovascular risk.
- Medroxyprogesterone acetate (MPA). The progestin used in WHI. Widely available, cheap, but the synthetic progestin most strongly associated with the breast-cancer and cardiovascular signals.
- Levonorgestrel intrauterine system (hormonal IUD). Delivers progestin locally to the uterus with minimal systemic absorption. A reasonable option for women who tolerate oral progestogens poorly.
Women who have had a hysterectomy do not need a progestogen and can use estrogen alone — which simplifies everything and avoids the component most associated with increased breast-cancer risk.
SERMs — Raloxifene and the MORE Trial
Selective estrogen receptor modulators (SERMs) are drugs that act like estrogen in some tissues and against estrogen in others. Raloxifene (60 mg daily) is the SERM with the largest osteoporosis evidence base.
The pivotal MORE trial (Multiple Outcomes of Raloxifene Evaluation, n = 7,705, postmenopausal women with osteoporosis, 3 years) and its four-year CORE extension showed:
- Vertebral fracture reduction of about 30% at the approved 60 mg dose (relative risk 0.7) and about 50% at 120 mg (relative risk 0.5). Over 3 years in MORE, a new vertebral fracture showed up on X-ray in 10.1% of women on placebo, 6.6% on 60 mg and 5.4% on 120 mg.
- Compared with placebo, the 60 mg dose raised spine density by 2.6% and femoral-neck density by 2.1%.
- No significant reduction in non-vertebral or hip fractures (non-vertebral relative risk 0.9, 95% CI 0.8–1.1, in MORE).
- A 72% reduction in invasive breast cancer (estrogen-receptor-positive tumors specifically).
- A roughly threefold higher VTE risk than placebo in MORE (relative risk 3.1, 95% CI 1.5–6.2).
- Worsening of hot flashes — which is why raloxifene is generally not used in women still in the vasomotor-symptom phase of menopause.
Raloxifene earned U.S. Food and Drug Administration (FDA) approval both for osteoporosis and for breast-cancer risk reduction. It is used mainly in postmenopausal women whose hot flashes have resolved, who have vertebral-dominant osteoporosis, who carry elevated breast-cancer risk, and who have no VTE history. It is generally not used in symptomatic perimenopausal women or anyone with prior clots.
Bazedoxifene / Conjugated Estrogens
Conjugated estrogens/bazedoxifene is a single pill that combines conjugated equine estrogens (0.45 mg) with the SERM bazedoxifene (20 mg). The concept is called a tissue-selective estrogen complex (TSEC): the estrogen delivers its bone and hot-flash benefits, while bazedoxifene blocks the estrogen effect specifically in breast and uterine tissue — so no separate progestogen is required to protect the endometrium.
The SMART trials showed the combination improved lumbar spine bone density by roughly 1.5–2% more than placebo over two years, reduced hot flashes, protected the endometrium, and did not increase breast density on mammography (a surrogate for breast-cancer risk). VTE risk remained elevated, similar to oral estrogen.
The combination fills a particular niche: a woman with an intact uterus who wants symptom relief and bone protection, can't or won't take a progestogen, and has no VTE history. It is not usually a first-line osteoporosis drug in its own right, but for the right candidate it is uniquely convenient.
Tibolone — The European Option
Tibolone (usually 2.5 mg daily) is a synthetic steroid that metabolizes into compounds with estrogenic, progestogenic, and weak androgenic activity. It is widely used in Europe and other countries but has never been approved by the US FDA.
The LIFT trial (Long-term Intervention on Fractures with Tibolone, n = 4,538, women aged 60–85 with osteoporosis) used a lower dose, 1.25 mg once daily. Over a median of 34 months it reduced vertebral fractures by 45% (70 versus 126 cases per 1,000 person-years), non-vertebral fractures by 26%, invasive breast cancer by 68%, and possibly colon cancer (relative hazard 0.31). But it increased the risk of stroke by 2.2-fold in this older cohort, and the study was stopped in February 2006 for that reason. There were no significant differences in coronary heart disease or venous thromboembolism.
In countries where tibolone is available, it is used in younger postmenopausal women (under 60) without cardiovascular risk factors for symptom relief and bone protection, and users generally also report improved libido (the androgenic component). It is not an approved drug in the US. In the US, the choice is to go without or pursue compounding.
When a Bisphosphonate Beats Hormone Therapy
Hormone therapy is not a first-line osteoporosis drug in most current US guidelines — not because it doesn't work, but because the average osteoporosis patient is 70+ years old, well outside the timing-hypothesis window, and a bisphosphonate delivers cleaner fracture reduction without cardiovascular concerns.
Guidelines generally list a bisphosphonate ahead of hormone therapy when:
- Age over 60 or more than 10 years past menopause.
- T-score already ≤−2.5 with established osteoporosis.
- Prior fragility fracture (especially hip or vertebral).
- Established cardiovascular disease, prior stroke, or clotting history.
- Personal or strong family history of breast cancer.
- Uterine cancer history.
- Active liver disease (bisphosphonate alendronate is actually fine; transdermal estrogen is also fine; oral estrogen is not).
Hormone therapy is generally listed first (often alongside a discussion of bisphosphonates, not instead of one) when:
- Early postmenopause (within 10 years, under age 60) with osteopenia not yet meeting osteoporosis thresholds.
- Disruptive hot flashes, night sweats, genitourinary symptoms, or sleep disruption alongside bone loss.
- Premature ovarian insufficiency (menopause before age 40) — HT through at least the average menopausal age of 51 is standard of care regardless of bone status.
- Intolerance to bisphosphonates (gastrointestinal (GI) upset, jaw concerns, atypical femur concerns after prolonged use).
How Long to Stay on Hormone Therapy
There is no fixed expiration date. The old "five years and stop" rule was driven by WHI fallout and does not map cleanly onto modern formulations or the timing hypothesis. Current NAMS and Endocrine Society guidance is individualized:
- For vasomotor symptoms, guidance supports continuing as long as symptoms persist and benefits exceed risks — often 5–10 years, sometimes longer.
- For bone protection specifically, the benefit lasts while the drug is taken. After stopping, bone loss resumes at about the ordinary postmenopausal rate (see below).
- The 2022 NAMS statement calls for periodic reevaluation of the benefits and risks of continuing; follow-up commonly tracks blood pressure, breast exam and mammogram, any new cardiovascular symptoms, VTE risk factors.
- For women with premature ovarian insufficiency or early menopause (under 45), guidance is to continue at least until about age 51, the average age of menopause.
"The lowest effective dose for the shortest needed duration" remains the boilerplate, but neither half of that phrase has a fixed number attached — it means the dose that controls your symptoms and the duration you continue to benefit.
What Happens When HT Stops
This is the single most under-discussed aspect of hormone therapy and osteoporosis. When HT stops, bone density starts falling again. The PEPI Safety Follow-up Study (Greendale 2002) measured how fast in 495 women from a 3-year trial: women who stopped after 3 years lost about 1% a year (−1.01% at the hip, −1.04% at the spine), and women who stopped after 1 year lost 0.54% (hip) and 0.81% (spine) a year over the next 2 years. These rates did not differ significantly from women who never used hormone therapy, and the authors wrote that their results “do not support the hypothesis that bone is lost at an unusually fast rate after discontinuation.” Women who continued hormone therapy after the 3-year trial gained no further bone density.
Fracture risk mirrors this: the WHI follow-up showed that within several years of stopping combined HT, hip-fracture incidence had drifted back up toward the placebo group rate. The long-term WHI report (Manson 2013) found that most of the risks and benefits seen during treatment faded after the intervention ended. The bone benefit is not durable without the drug.
Women in their early sixties who used HT for symptom relief and are stopping commonly follow one of three routes:
- Moving to a bisphosphonate (oral alendronate or risedronate weekly, or zoledronic acid intravenous (IV) yearly) as HT is tapered. This "locks in" the bone density gained and continues protection.
- A repeat DEXA 1–2 years after stopping HT, with a fresh assessment then.
- Continuing HT at a lower maintenance dose when symptoms return and the risk-benefit still favors continuation.
High-Risk Patients — Combining or Switching
For women with severe osteoporosis, multiple vertebral fractures, or very low T-scores (≤−3.0), hormone therapy alone is rarely enough. These patients are usually treated with an anabolic agent such as teriparatide, abaloparatide, or romosozumab for 1–2 years to rebuild bone, followed by a bisphosphonate or denosumab to maintain.
In these high-risk cases, if the woman is also early postmenopausal and symptomatic, transdermal estrogen can provide symptom relief alongside anabolic therapy — but the bone-rebuilding work is done by the anabolic agent, not the hormones. In this setting HT serves as adjunctive comfort and modest additional protection, not primary therapy.
Non-Hormonal Options When HT Is Off the Table
Some women cannot take hormones: prior estrogen-receptor-positive breast cancer, recent stroke, active VTE, active liver disease. For these patients the osteoporosis armamentarium still includes:
- Bisphosphonates — alendronate, risedronate, zoledronic acid. First-line for nearly everyone in this group.
- Denosumab — subcutaneous injection every 6 months. Particularly useful with kidney disease or poor oral bisphosphonate tolerance. Stopping it without a bisphosphonate bridge is followed by well-documented rebound vertebral fractures.
- Raloxifene — if breast-cancer prevention is a priority and VTE risk is acceptable.
- Anabolic agents for severe disease.
- Calcium 1,000–1,200 mg/day, vitamin D to a level of 30–50 ng/mL, and protein 1.0–1.2 g/kg/day — foundational. See Calcium, Vitamin D, and Protein.
- Weight-bearing and resistance exercise 3–4 times per week. See the exercise protocol.
For vasomotor symptoms without hormones: low-dose paroxetine (7.5 mg) is U.S. Food and Drug Administration-approved for hot flashes. Venlafaxine, gabapentin, oxybutynin, and the neurokinin-3 antagonist fezolinetant are additional non-hormonal options. None of these protect bone.
What Clinicians Weigh Before Hormone Therapy
Many primary-care offices have long worked from the 2002–2003 WHI headlines, and the broad boxed warnings drawn from them stayed on hormone therapy labels until the FDA began removing them in November 2025 (see the WHI section above). A woman asking about hormone therapy may still meet a knee-jerk "we don't do that anymore" reply that ignores two decades of reanalysis. The details menopause guidelines use to weigh hormone therapy are:
- Your exact age and date of final menstrual period.
- A current DEXA result with T-scores at lumbar spine, total hip, and femoral neck.
- Your FRAX 10-year fracture risk.
- Personal and family history of breast cancer, cardiovascular disease, stroke, and clotting disorders.
- A list of your menopausal symptoms and how disruptive they are.
- The central question those details answer: whether her age, timing, and risk profile make her a candidate for transdermal estradiol with micronized progesterone.
Menopause specialists see these decisions most often — the NAMS (now Menopause Society) website maintains a searchable list of certified practitioners. Women's health is an area where a second opinion from someone who reads the current literature often changes the plan.
Key Research Papers
The Women's Health Initiative primary trials and timing-hypothesis reanalyses, the ESTHER and other transdermal-route VTE studies, the SERM trials (MORE, RUTH), tibolone (LIFT), and current Menopause Society and Endocrine Society guidelines that frame hormone therapy as a bone treatment.
- Rossouw JE, Anderson GL, Prentice RL, et al. Risks and Benefits of Estrogen Plus Progestin in Healthy Postmenopausal Women: Principal Results From the Women's Health Initiative Randomized Controlled Trial. JAMA. 2002;288(3):321–333. — doi:10.1001/jama.288.3.321
- Anderson GL, Limacher M, Assaf AR, et al. Effects of Conjugated Equine Estrogen in Postmenopausal Women with Hysterectomy: The Women's Health Initiative Randomized Controlled Trial. JAMA. 2004;291(14):1701–1712. — doi:10.1001/jama.291.14.1701
- Manson JE, Chlebowski RT, Stefanick ML, et al. Menopausal Hormone Therapy and Health Outcomes During the Intervention and Extended Poststopping Phases of the Women's Health Initiative Randomized Trials. JAMA. 2013;310(13):1353–1368. — doi:10.1001/jama.2013.278040
- Rossouw JE, Prentice RL, Manson JE, et al. Postmenopausal Hormone Therapy and Risk of Cardiovascular Disease by Age and Years Since Menopause. JAMA. 2007;297(13):1465–1477. — doi:10.1001/jama.297.13.1465
- Cauley JA, Robbins J, Chen Z, et al. Effects of Estrogen Plus Progestin on Risk of Fracture and Bone Mineral Density: The Women's Health Initiative Randomized Trial. JAMA. 2003;290(13):1729–1738. — doi:10.1001/jama.290.13.1729
- Canonico M, Oger E, Plu-Bureau G, et al. Hormone Therapy and Venous Thromboembolism Among Postmenopausal Women: Impact of the Route of Estrogen Administration and Progestogens — The ESTHER Study. Circulation. 2007;115(7):840–845. — doi:10.1161/CIRCULATIONAHA.106.642280
- Ettinger B, Black DM, Mitlak BH, et al. Reduction of Vertebral Fracture Risk in Postmenopausal Women with Osteoporosis Treated with Raloxifene: Results From a 3-Year Randomized Clinical Trial (MORE). JAMA. 1999;282(7):637–645. — doi:10.1001/jama.282.7.637
- Barrett-Connor E, Mosca L, Collins P, et al. Effects of Raloxifene on Cardiovascular Events and Breast Cancer in Postmenopausal Women (RUTH). New England Journal of Medicine. 2006;355(2):125–137. — doi:10.1056/NEJMoa062462
- Cummings SR, Ettinger B, Delmas PD, et al. The Effects of Tibolone in Older Postmenopausal Women (LIFT). New England Journal of Medicine. 2008;359(7):697–708. — doi:10.1056/NEJMoa0800743
- The 2022 Hormone Therapy Position Statement of The North American Menopause Society Advisory Panel. The 2022 Hormone Therapy Position Statement of The North American Menopause Society. Menopause. 2022;29(7):767–794. — doi:10.1097/GME.0000000000002028
- Eastell R, Rosen CJ, Black DM, Cheung AM, Murad MH, Shoback D. Pharmacological Management of Osteoporosis in Postmenopausal Women: An Endocrine Society Clinical Practice Guideline. Journal of Clinical Endocrinology & Metabolism. 2019;104(5):1595–1622. — doi:10.1210/jc.2019-00221
- Greendale GA, Espeland M, Slone S, Marcus R, Barrett-Connor E. Bone Mass Response to Discontinuation of Long-Term Hormone Replacement Therapy: Results from the Postmenopausal Estrogen/Progestin Interventions (PEPI) Safety Follow-up Study. Archives of Internal Medicine. 2002;162(6):665–672. — doi:10.1001/archinte.162.6.665
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
Connections
- Rheumatology
- Bone Remodeling & Calcium Balance — interactive animation
- Osteoporosis
- Bisphosphonates
- DEXA Scan: T-Score and Z-Score
- Weight-Bearing and Resistance Exercise
- Denosumab, Romosozumab and Teriparatide
- Calcium, Vitamin D and Protein Intake
- FRAX Risk Assessment
- Secondary Osteoporosis Causes
- Fracture Prevention and Fall Risk
- Arthritis
- Pregnancy and Hashimoto's
- Cancer
- Stroke
- Calcium
- Cardiovascular Disease
- Perimenopause
- Menopause — the estrogen decline that drives Type I postmenopausal bone loss.