⚠ Evidence warning: Clinical trials or other evidence do not support the claims that rituximab brings clearer benefit in Sjogren's subgroups with active systemic disease, and that hydroxychloroquine brings modest relief of dryness and clear relief of joint pain and fatigue. This page keeps it as a report of what people, websites or other media say.
Lupus and Sjögren's Overlap — Secondary Sjögren's Syndrome
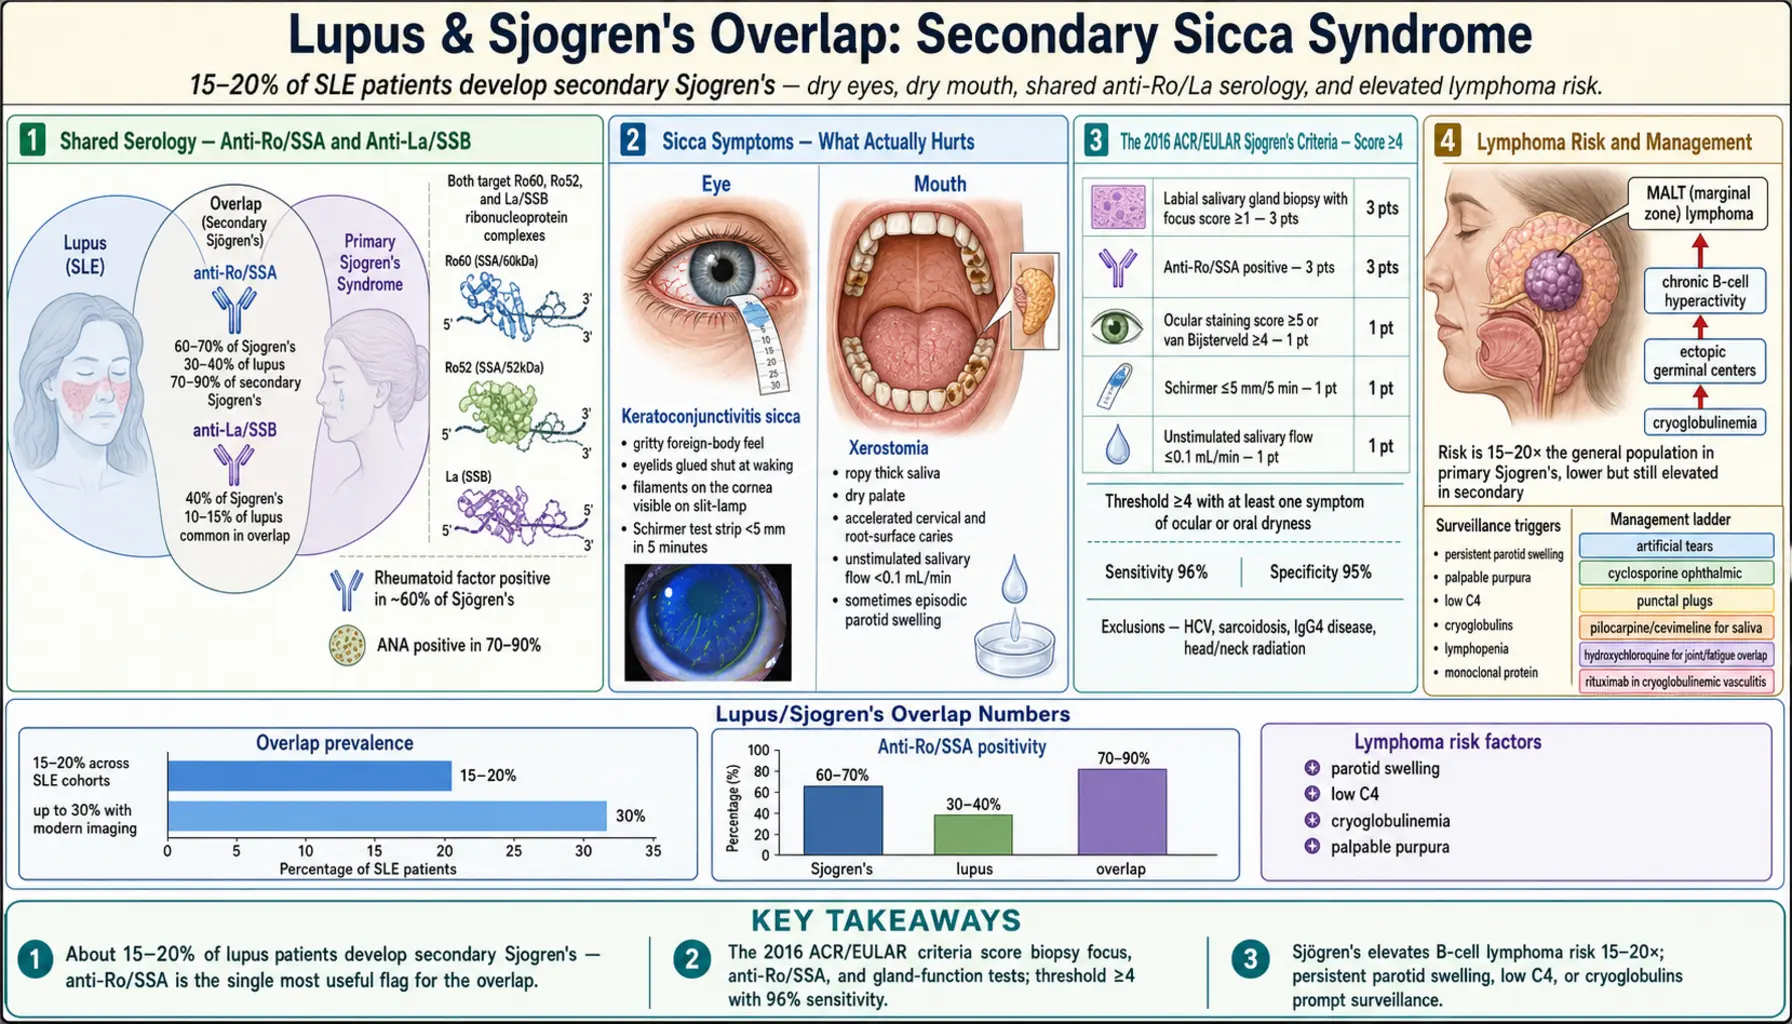
Table of Contents
- What Secondary Sjögren's Is
- How Often It Happens in Lupus
- Primary vs Secondary Sjögren's
- Shared Serology: Anti-Ro/SSA and Anti-La/SSB
- Sicca Symptoms — What You Feel
- The Diagnostic Workup Step by Step
- ACR/EULAR 2016 Classification Criteria
- Extraglandular Manifestations
- Lymphoma Risk and MALT
- How Sjögren's Differs From a Drug Side Effect
- Management — From Eye Drops to Rituximab
- Dental Decay Prevention
- Daily Life and Practical Tips
- Key Research Papers
- Connections
- Featured Videos
What Secondary Sjögren's Is
Sjögren's syndrome is a chronic autoimmune disease in which the immune system attacks the glands that make tears and saliva. The result is dry eyes and dry mouth — the "sicca" symptoms — along with a wider set of systemic problems ranging from joint pain to lung and kidney involvement. When Sjögren's appears on its own, it is called primary Sjögren's. When it appears in someone who already carries a diagnosis of another connective tissue disease — most commonly lupus (systemic lupus erythematosus, SLE), rheumatoid arthritis, or systemic sclerosis — it is called secondary Sjögren's.
The "secondary" label is not a judgment about severity. Secondary Sjögren's can be just as symptomatic, just as tissue-destructive, and just as exhausting as the primary form. It simply means lupus is the dominant disease driving care. Lupus may have been recognized first with Sjögren's joining the picture afterward, the two may have been diagnosed close together, or Sjögren's may have come first, as it did in 18 of 26 overlap patients in one cohort.
For lupus patients, the overlap matters because it changes day-to-day quality of life, shifts a few pieces of the diagnostic puzzle, raises the long-term risk of B-cell lymphoma, and opens specific treatment options (like pilocarpine or punctal plugs) that plain lupus management does not usually address. See the Sjögren's Syndrome overview for the disease in isolation.
How Often It Happens in Lupus
Across published cohorts, roughly 15–20% of people with systemic lupus erythematosus develop secondary Sjögren's syndrome. Some single-center studies put the figure as high as 30% when modern salivary gland imaging is used liberally, and some as low as 9% when strict classification criteria are applied. The most widely cited meta-analyses land in the 14–18% range. In one cohort of 283 consecutive lupus patients assessed with the American-European criteria, Sjögren's was found in 26 (9.2%). Compared with lupus patients without it, those with both were older and more often had Raynaud's, anti-Ro/SSA, anti-La/SSB and rheumatoid factor, and less often had kidney involvement, swollen lymph nodes and low platelets.
A few patterns stand out:
- Secondary Sjögren's is often described as appearing later in the lupus course — median onset about 7–10 years after the systemic lupus erythematosus diagnosis, though some patients carry both from the start. The order is not fixed: in the 283-patient cohort, Sjögren's came before lupus in 18 of the 26 people with both (69.2%).
- It is more common in older-onset lupus (women diagnosed after age 50) than in classic early-adult systemic lupus erythematosus.
- Women are affected about 9–20 times more often than men, mirroring the general female predominance of both diseases.
- Patients with secondary Sjögren's are more likely to carry anti-Ro/SSA antibodies, less likely to have severe renal disease, and more likely to have joint pain and Raynaud's than lupus patients without the overlap.
Primary vs Secondary Sjögren's
The distinction is clinical, not biochemical — the two forms share most of the same autoantibodies. But the differences matter for how rheumatologists frame treatment.
Primary Sjögren's patients tend to have more prominent glandular disease (severe xerostomia, parotid gland swelling), a higher frequency of anti-La/SSB antibodies, and a markedly elevated lymphoma risk (5–10% lifetime). Their therapy is organized around glandular symptoms and surveillance.
Secondary Sjögren's in lupus patients is often described as having milder glandular symptoms but more active systemic inflammation driven by the underlying systemic lupus erythematosus, though a cohort comparing 26 overlap patients with 86 people with primary Sjögren's found a clinically similar sicca syndrome. Anti-La/SSB is described as less common than in primary disease, though in that cohort it was more frequent than in lupus without Sjögren's. The lymphoma risk is still elevated above the general population but appears lower than in primary Sjögren's. Therapy is organized around the dominant disease (lupus) with added attention to sicca symptoms.
One practical consequence: when someone with lupus develops new dry eyes and dry mouth, a rheumatologist may not immediately apply the full ACR/EULAR 2016 Sjögren's criteria — the label does not change whether artificial tears, pilocarpine, or intensified hydroxychloroquine are used. A formal workup still matters because a confirmed diagnosis guides lymphoma surveillance and unlocks specific insurance coverage for cyclosporine ophthalmic drops and similar agents.
Shared Serology: Anti-Ro/SSA and Anti-La/SSB
Lupus and Sjögren's share an unusually tight serologic overlap. Two antibodies dominate the picture:
- Anti-Ro/SSA — present in roughly 60–70% of Sjögren's patients and 30–40% of lupus patients. In lupus patients with secondary Sjögren's, anti-Ro/SSA is present in 70–90%. It is the single most useful antibody for flagging the overlap.
- Anti-La/SSB — present in about 40% of primary Sjögren's but only 10–15% of lupus patients. When anti-La/SSB is present in a systemic lupus erythematosus patient, secondary Sjögren's is very likely.
Both antibodies target small nuclear ribonucleoprotein complexes — Ro60 and Ro52 for anti-SSA, and La/SSB for anti-La. They cross the placenta in pregnancy and are responsible for neonatal lupus and, in a small percentage, congenital heart block. Once an anti-Ro/SSA positive mother has had one affected baby, the historical rate of it happening again is 18%. In the PATCH trial, 54 such pregnancies took hydroxychloroquine 400 mg daily, started before the end of week 10 and continued through pregnancy, and 4 of the 54 (7.4%) developed second- or third-degree heart block. The trial had no placebo group; it compared against the historical rate. See the Lupus and Pregnancy page for monitoring protocols.
Rheumatoid factor is also frequently positive in Sjögren's (about 60%), and hypergammaglobulinemia (high total immunoglobulin G, IgG) is common. A polyclonal elevation in immunoglobulin G on a serum protein electrophoresis (SPEP) is a soft clue that Sjögren's may be active.
Sicca Symptoms — What You Feel
Dry eyes (keratoconjunctivitis sicca). Not simply "my eyes feel tired at the end of the day." Sjögren's dryness feels gritty, like sand under the eyelids. You may wake up with eyelids glued shut. Contact lenses become intolerable. Reading or screen work causes blurred vision that improves when you blink or use drops. In severe cases the cornea develops filaments — strands of mucus that stick to it — which an ophthalmologist can see on slit-lamp exam.
Dry mouth (xerostomia). Again, not simply "I get thirsty." Patients describe needing to sip water to swallow dry food, carrying a water bottle everywhere, waking at night to drink, and a thick ropy saliva that feels glue-like. Food sticks to the palate. Taste dulls. Speaking for long periods becomes effortful. Dental checkups start turning up new cavities in places you never had them before — particularly along the gumline and on the roots of teeth.
Other dry tissues. Sjögren's can affect every exocrine gland, not just eyes and mouth. Vaginal dryness is common and often under-reported. Dry skin, dry nasal passages (with nosebleeds), dry throat, and dry bronchi (chronic non-productive cough) are all part of the picture. Reflux worsens because saliva normally neutralizes esophageal acid.
Parotid and submandibular swelling. Episodic swelling of the large salivary glands in front of the ears or under the jaw. It can be painful, mimic mumps, and sometimes signals a secondary bacterial infection or, rarely, early lymphoma.
The Diagnostic Workup Step by Step
A complete Sjögren's workup layers objective tests on top of your symptom report. No single test is diagnostic; the picture is pieced together.
Schirmer test. A small strip of filter paper is tucked under the lower eyelid for five minutes. 5 mm of wetting or less in five minutes is abnormal and supports keratoconjunctivitis sicca. It is simple, cheap, and done in any ophthalmology office.
Ocular staining score. The ophthalmologist drops fluorescein and lissamine green onto the eye and grades areas of dead or damaged surface cells on a 0–12 scale per eye. A score of ≥5 in at least one eye is a positive ACR/EULAR criterion. This test picks up surface damage that Schirmer alone can miss.
Unstimulated whole-salivary flow (sialometry). You sit quietly and spit into a cup for five minutes. A flow of ≤0.1 mL/minute is abnormal. Simple, free, and surprisingly reproducible when done carefully.
Labial salivary gland biopsy. The gold standard. An oral surgeon or rheumatologist removes four to six tiny minor salivary glands from the inside of the lower lip under local anesthesia. A pathologist looks for focal lymphocytic sialadenitis and calculates the focus score — the number of focal lymphocytic aggregates (each containing ≥50 lymphocytes) per 4 mm² of tissue. A focus score of ≥1 is positive. The biopsy leaves a small internal stitch and usually heals in a week. It is the one piece of the workup that definitively confirms glandular autoimmunity when serology is ambiguous.
Salivary gland imaging. Ultrasound of the parotid and submandibular glands is increasingly used as a non-invasive first step; it shows characteristic hypoechoic foci that correlate well with biopsy. Magnetic resonance imaging (MRI) and sialography are alternatives but less common in routine practice.
Blood work. Antinuclear antibody (ANA), anti-Ro/SSA, anti-La/SSB, rheumatoid factor, complete blood count (to look for cytopenias), SPEP and quantitative immunoglobulins, and a complement panel (C3, C4) if not already done as part of lupus monitoring. See the autoantibody article for how these fit into the broader lupus serology.
ACR/EULAR 2016 Classification Criteria
The 2016 American College of Rheumatology / European League Against Rheumatism criteria are the standard reference for classifying a patient as having Sjögren's syndrome in research and most clinical settings. Classification takes a total score of ≥4 from the following items, in a patient who has at least one sicca symptom or a suggestive systemic feature:
- Labial salivary gland biopsy with focus score ≥1 — 3 points
- Anti-Ro/SSA positive — 3 points
- Ocular staining score ≥5 in at least one eye — 1 point
- Schirmer ≤5 mm/5 min in at least one eye — 1 point
- Unstimulated salivary flow ≤0.1 mL/min — 1 point
Exclusions include head and neck radiation, active hepatitis C, human immunodeficiency virus (HIV), sarcoidosis, amyloidosis, graft-versus-host disease, and IgG4-related disease — each of which can mimic Sjögren's and is ruled out first.
These criteria were built for primary Sjögren's, and their authors describe them as "well-suited as criteria for enrollment in clinical trials". In the validation cohort they reached 96% sensitivity and 95% specificity against experts' judgment. They were not built for lupus overlap, so using them in someone with lupus, as below, goes beyond the group they were validated in.
In a lupus patient, reaching a score of 4 is straightforward with a positive anti-Ro/SSA (3 points) and a positive Schirmer or ocular staining or salivary flow test (1 point). That is why serology plus a simple office test is usually enough — the biopsy is reserved for ambiguous cases.
Extraglandular Manifestations
Sjögren's is not just a dry mouth and dry eye disease. A meaningful minority of patients develop problems far from the salivary glands, and when these show up in a lupus patient, it can be hard to tell which disease is driving them.
- Cutaneous vasculitis. Palpable purpura on the legs, often associated with cryoglobulinemia. In a lupus patient, this overlaps with lupus vasculitis but the cryoglobulin pattern and tissue biopsy help sort it out.
- Peripheral neuropathy. Sensory neuropathy (burning feet, numbness, small-fiber loss) is the most common pattern. Sjögren's is one of the top autoimmune causes of small-fiber neuropathy, diagnosed by skin punch biopsy with intraepidermal nerve fiber density staining.
- Interstitial lung disease. Nonspecific interstitial pneumonia (NSIP) and lymphocytic interstitial pneumonia (LIP) are characteristic. Chronic dry cough plus a crackly exam plus a high-resolution chest computed tomography (CT) is the usual path to diagnosis.
- Renal tubular acidosis. Distinct from lupus nephritis — Sjögren's classically causes type 1 (distal) renal tubular acidosis with hypokalemia, nephrocalcinosis, and kidney stones. Lupus nephritis is glomerular; Sjögren's kidney disease is tubulointerstitial. Both can coexist.
- Autonomic dysfunction. Some patients develop orthostatic intolerance, slow gastric emptying, or postural orthostatic tachycardia syndrome-like features.
- Arthritis. Non-erosive polyarthritis very similar to lupus joint disease — see the Arthritis page.
- Raynaud's phenomenon. Extremely common in secondary Sjögren's, reported in 30–50% of patients. See Raynaud's Disease.
Lymphoma Risk and MALT
The most serious long-term complication of Sjögren's is non-Hodgkin B-cell lymphoma, most commonly mucosa-associated lymphoid tissue (MALT) lymphoma arising in the parotid gland. Primary Sjögren's patients have roughly a 5–10% lifetime risk, about 15–20 times the general population rate. In secondary Sjögren's overlapping with lupus, the risk appears lower but is still elevated — estimates range from 2–5% lifetime.
Known risk factors for lymphoma in Sjögren's:
- Persistent parotid gland swelling (especially unilateral)
- Palpable purpura or cryoglobulinemia
- Low C4 complement
- Lymphopenia or CD4+ T-cell lymphopenia
- Monoclonal gammopathy on SPEP
- High EULAR Sjögren's Syndrome Disease Activity Index (ESSDAI) score
- Newer predictors named in a 2015 review of primary Sjögren's: germinal-centre-like structures (small immune clusters) in the salivary gland, high BAFF and Flt3-ligand levels in the blood, and inherited changes in the TNFAIP3 gene
People with any of these are usually watched more closely — typically with an annual physical exam of the lymph nodes and salivary glands, and imaging (ultrasound or magnetic resonance imaging) if a gland becomes persistently enlarged. A dominant salivary gland mass that does not resolve is an accepted reason for biopsy. MALT lymphoma, when caught early and still confined to the gland, is highly treatable.
How Sjögren's Differs From a Drug Side Effect
Many medications cause dry mouth and dry eyes, and lupus patients are often on several of them at once. The medication list is therefore a known alternative explanation to a secondary Sjögren's label. Common culprits:
- Antihistamines (diphenhydramine, cetirizine) — strong anticholinergic drying.
- Tricyclic antidepressants (amitriptyline, nortriptyline) — frequent cause of xerostomia.
- Selective serotonin reuptake inhibitors (SSRIs) and serotonin-norepinephrine reuptake inhibitors (SNRIs) (sertraline, venlafaxine) — milder but real.
- Diuretics (hydrochlorothiazide, furosemide) — dehydration-related dryness.
- Opioids — classic dry mouth.
- Anticholinergics for overactive bladder (oxybutynin, tolterodine).
- Beta blockers — decreased tear film in some patients.
- Isotretinoin — profoundly drying to all mucous membranes.
Drug-induced sicca is usually reversible within weeks of stopping the offending agent. Sjögren's is not. And importantly, drug-induced sicca does not produce a positive anti-Ro/SSA, a positive Schirmer with objective ocular surface damage on staining, or a focal lymphocytic biopsy. The distinction is clean when you do the objective tests.
Management — From Eye Drops to Rituximab
Treatment is built up in layers, matching intensity to symptoms and organ involvement.
Layer 1: environmental and over-the-counter measures. Preservative-free artificial tears four to six times daily. Nighttime gel or ointment. A humidifier by the bed. Wraparound sunglasses outdoors. Frequent sips of water through the day. Sugar-free xylitol gum or lozenges to stimulate residual saliva.
Layer 2: prescription eye drops.
- Cyclosporine 0.05% or 0.09% ophthalmic — suppresses local T-cell inflammation on the ocular surface. Takes 3–6 months to reach full effect. Burns on instillation for the first few weeks.
- Lifitegrast 5% — blocks a different inflammatory pathway (LFA-1/ICAM-1). Faster onset than cyclosporine.
- Punctal plugs. Tiny silicone or collagen plugs inserted into the tear drainage ducts by an ophthalmologist. Keeps your own tears (and any drops) on the eye surface longer. Collagen plugs dissolve in weeks; silicone plugs are semi-permanent.
Layer 3: secretagogues for dry mouth.
- Pilocarpine, 5 mg four times daily. A muscarinic agonist that stimulates residual salivary tissue. Side effects: sweating, flushing, frequent urination, sometimes gastrointestinal (GI) cramping. A lower 2.5 mg starting dose is described for testing tolerance.
- Cevimeline, 30 mg three times daily. More selective for M3 receptors on salivary glands with somewhat less systemic cholinergic effect. Often better tolerated than pilocarpine.
Layer 4: systemic disease-modifying therapy.
- Hydroxychloroquine — most lupus patients with secondary Sjögren's are already on it. It is described as giving modest benefit for sicca symptoms and clear benefit for joint pain and fatigue. The JOQUER trial, in 120 people with primary Sjögren's rather than lupus overlap, found 17.9% on 400 mg daily against 17.2% on placebo reached its main measure of dryness, pain and fatigue at 24 weeks (P = .98). See the hydroxychloroquine article.
- Methotrexate, azathioprine, mycophenolate — used when systemic or extraglandular features (arthritis, interstitial lung disease, vasculitis) dominate. Chosen by the systemic lupus erythematosus picture more than the Sjögren's picture.
- Rituximab — anti-CD20 B-cell depletion. Reserved for refractory extraglandular disease: severe cryoglobulinemic vasculitis, progressive interstitial lung disease, significant neuropathy, or MALT lymphoma. Two trials in primary Sjögren's reported these results: in TEARS (120 patients) the difference on the main measure at week 24 was 1.0% (95% CI -16.7 to 18.7), with some earlier relief, including of fatigue; in TRACTISS (133 patients) 39.8% against 36.8% responded at 48 weeks, and only unstimulated saliva flow improved. A clearer benefit in subgroups with active systemic disease is claimed, but neither trial's summary states it. See the biologics article.
- Belimumab — primarily used for lupus activity; emerging data in Sjögren's, especially in combination with rituximab.
- Ianalumab — an experimental injected drug that suppresses B cells. In a 190-patient phase 2b trial in primary Sjögren's, it met its main goal of a dose-related fall in disease activity at 24 weeks; the change at the top dose against placebo was -1.92 points (95% CI -4.15 to 0.32). A 2026 review states that no disease-modifying therapy for Sjögren's has yet been approved.
Nonsteroidal anti-inflammatory drugs (NSAIDs) and short corticosteroid courses are used for joint flares as in lupus. Chronic high-dose steroids are avoided — they do not help sicca and carry the usual bone, skin, and infection risks.
Dental Decay Prevention
Saliva is the mouth's natural defense against cavities. Without it, tooth decay accelerates dramatically — patients can go from no cavities to multiple root caries within a year or two. Aggressive prevention matters more than any medication.
- Dental visits every 3–4 months, not the usual 6, are a common schedule for dry mouth, with "Sjögren's / xerostomia" noted in the chart so the stakes are clear.
- High-fluoride prescription toothpaste — 1.1% sodium fluoride (5000 ppm). Typically used nightly after brushing, spitting out the excess without rinsing.
- Daily fluoride rinse or custom fluoride trays for 5-minute nightly applications in high-risk patients.
- Xylitol — gum, mints, or lozenges 5–6 times daily. Xylitol is a sugar alcohol that cavity-causing bacteria cannot metabolize; regular exposure lowers bacterial counts.
- Constant sipping of acidic drinks — sparkling water, lemon water, diet sodas. They strip enamel in a dry mouth. Plain water does not, and a straw plus a water rinse afterward lessens contact with the teeth.
- Saliva substitutes, sprays and xylitol discs overnight for comfort and buffering.
- Oral candidiasis — a red, sore tongue with cracked corners of the mouth. It is treated with nystatin or fluconazole and does not clear on its own in a dry mouth.
Daily Life and Practical Tips
- Water and saliva. Sipping water constantly actually washes out the small amount of saliva and mucin left. Secretagogues and xylitol keep the mouth moist in a way that volume of water does not.
- Bedroom humidity. Running a cool-mist humidifier overnight dramatically improves morning eye and mouth symptoms. Weekly cleaning prevents mold.
- Eyes outdoors. Wraparound sunglasses cut tear evaporation from wind. In very dry climates or on airplanes, moisture chamber goggles help.
- Lubrication and screens. Artificial tears work best before computer work starts, not after the eyes already sting. Some people set a timer to blink fully every 20 minutes.
- Flares. Long flights, dry air-conditioned offices, and winter heating all worsen sicca, which is why many people carry their drops everywhere.
- Vaginal dryness is treatable. Local vaginal moisturizers and, when appropriate, low-dose vaginal estrogen are described as safe and effective. Most patients never volunteer the symptom.
- New symptoms. Persistent unilateral salivary gland swelling, unexplained weight loss, drenching night sweats, or new enlarged lymph nodes are lymphoma warning signs that rheumatologists treat as needing prompt evaluation.
Key Research Papers
- Shiboski CH, et al. 2016 American College of Rheumatology/European League Against Rheumatism Classification Criteria for Primary Sjögren's Syndrome. Arthritis Rheumatol. 2017. — doi:10.1002/art.39859
- Ramos-Casals M, et al. EULAR recommendations for the management of Sjögren's syndrome with topical and systemic therapies. Ann Rheum Dis. 2020. — doi:10.1136/annrheumdis-2019-216114
- Brito-Zerón P, et al. Sjögren syndrome. Nat Rev Dis Primers. 2016. — doi:10.1038/nrdp.2016.47
- Baer AN, et al. The SSB-positive/SSA-negative antibody profile is not associated with key phenotypic features of Sjögren's syndrome. Ann Rheum Dis. 2015. — PubMed PMID: 25735642
- Nocturne G, Mariette X. Sjögren syndrome-associated lymphomas: an update on pathogenesis and management. Br J Haematol. 2015. — doi:10.1111/bjh.13192
- Devauchelle-Pensec V, et al. Treatment of primary Sjögren syndrome with rituximab: a randomized trial. Ann Intern Med. 2014;160(4):233-242. — doi:10.7326/M13-1085
- Bowman SJ, Everett CC, O'Dwyer JL, et al. Randomized Controlled Trial of Rituximab and Cost-Effectiveness Analysis in Treating Fatigue and Oral Dryness in Primary Sjögren's Syndrome. Arthritis Rheumatol. 2017;69(7):1440-1450. — PubMed PMID: 28296257
- Gottenberg JE, Ravaud P, Puéchal X, et al. Effects of hydroxychloroquine on symptomatic improvement in primary Sjögren syndrome: the JOQUER randomized clinical trial. JAMA. 2014;312(3):249-258. — PubMed PMID: 25027140
- Manoussakis MN, Georgopoulou C, Zintzaras E, et al. Sjögren's syndrome associated with systemic lupus erythematosus: clinical and laboratory profiles and comparison with primary Sjögren's syndrome. Arthritis Rheum. 2004;50(3):882-891. — PubMed PMID: 15022331
- Izmirly P, Kim M, Friedman DM, et al. Hydroxychloroquine to Prevent Recurrent Congenital Heart Block in Fetuses of Anti-SSA/Ro-Positive Mothers. J Am Coll Cardiol. 2020;76(3):292-302. — PubMed PMID: 32674792
- Bowman SJ, Fox R, Dörner T, et al. Safety and efficacy of subcutaneous ianalumab (VAY736) in patients with primary Sjögren's syndrome: a randomised, double-blind, placebo-controlled, phase 2b dose-finding trial. Lancet. 2022;399(10320):161-171. — PubMed PMID: 34861168
- Marques-Gomes C, Bowman SJ, Nayar S, Fisher BA. Emerging treatments for Sjögren's disease: promising drugs on the horizon. RMD Open. 2026;12(2). — PubMed PMID: 42342283
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on lupus-Sjögren's overlap, diagnosis, and management:
- PubMed: Secondary Sjögren's in systemic lupus erythematosus
- PubMed: Anti-Ro/SSA and anti-La/SSB in lupus and Sjögren's
- PubMed: Labial salivary gland biopsy and focus score
- PubMed: ACR/EULAR 2016 Sjögren's classification criteria
- PubMed: Sjögren's and MALT lymphoma risk
- PubMed: Pilocarpine and cevimeline for xerostomia
- PubMed: Rituximab in Sjögren's syndrome trials
- PubMed: Renal tubular acidosis in Sjögren's
- PubMed: Interstitial lung disease in Sjögren's
- PubMed: Xerostomia and dental caries prevention
Connections
- Rheumatology
- Lupus Overview
- Sjogren's Syndrome
- Arthritis
- Raynaud's Disease
- Biologics: Belimumab, Anifrolumab and Rituximab
- Antinuclear Antibody, dsDNA and Lupus Autoantibodies
- Hydroxychloroquine and Antimalarials
- Lupus and Pregnancy
- Neuropsychiatric Lupus
- ACR-EULAR 2019 Classification Criteria
- Cutaneous Lupus and Photoprotection
- Lupus Nephritis and Kidney Involvement
- Lymphoma
- Kidney Disease
- Interstitial Lung Disease