Cutaneous Lupus and Photoprotection
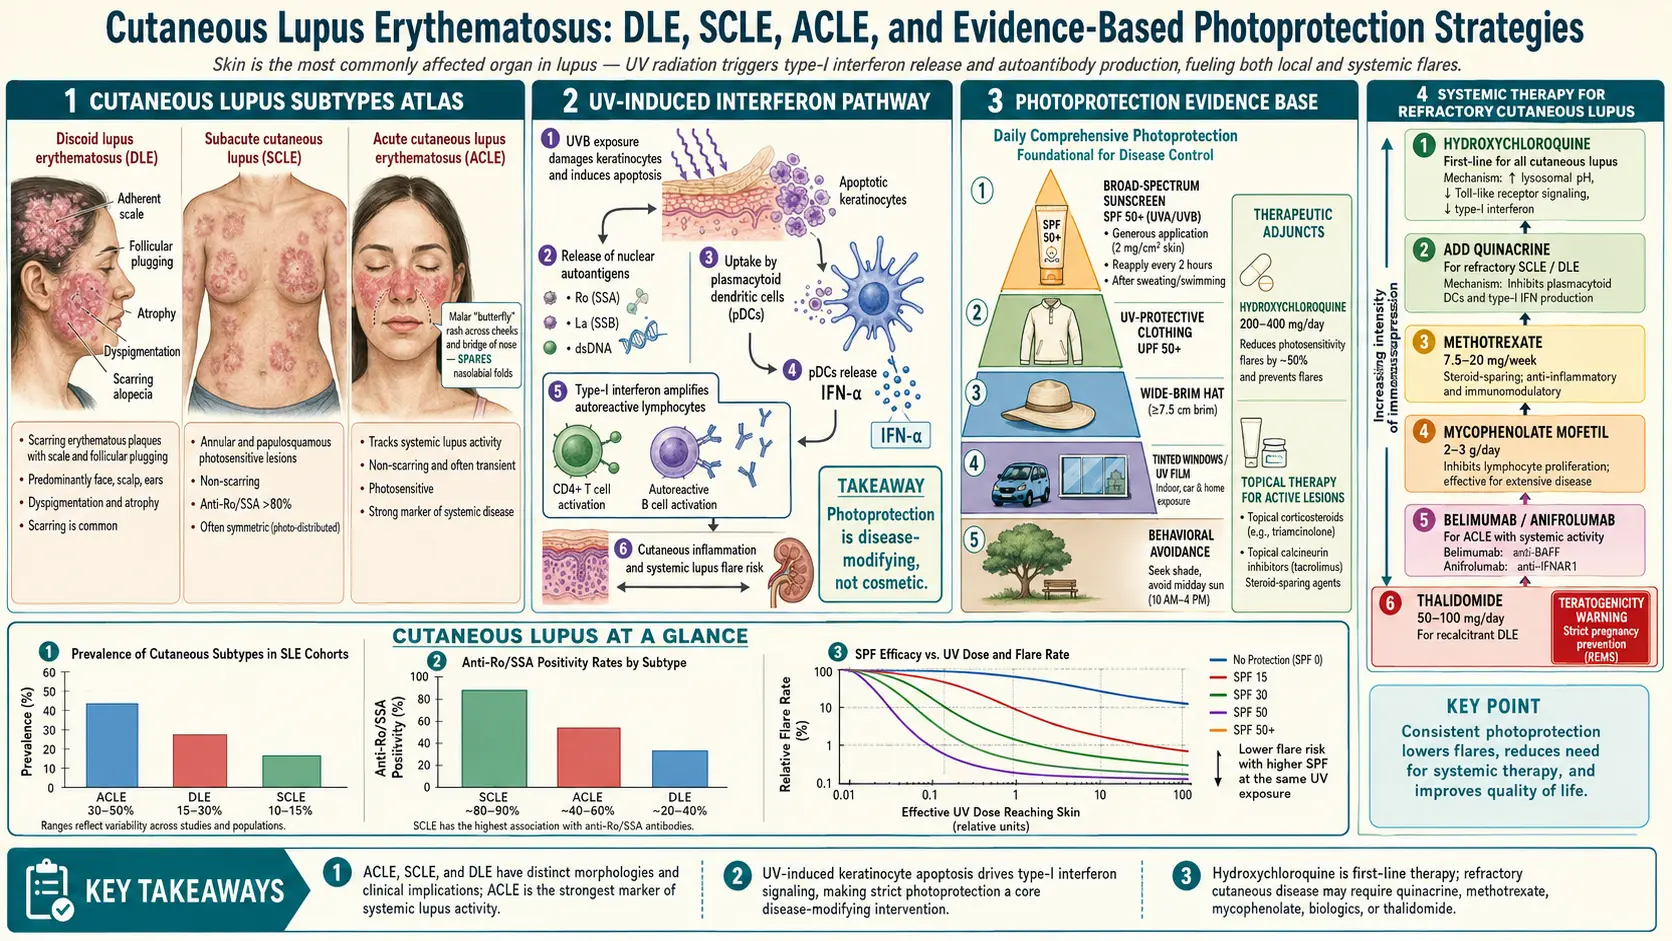
Table of Contents
- Why the Skin Is Ground Zero in Lupus
- Acute Cutaneous Lupus (ACLE) — The Butterfly Rash
- Subacute Cutaneous Lupus (SCLE)
- Chronic Cutaneous Lupus — Discoid and Beyond
- Non-Specific Lesions: Bullous, Panniculitis, Tumidus
- How Ultraviolet Light Triggers Lupus Skin
- Sunscreen — Broad-Spectrum, Visible Light, Iron Oxides
- UPF Clothing, Tinted Window Film, Physical Measures
- Topical Steroids and Calcineurin Inhibitors
- Hydroxychloroquine and Quinacrine
- Thalidomide, Lenalidomide, and Refractory DLE
- Anifrolumab and the Interferon Pathway
- Managing Scars, Hair Loss, and Hyperpigmentation
- A Realistic Daily Routine
- Key Research Papers
- Connections
- Featured Videos
Why the Skin Is Ground Zero in Lupus
Roughly 70–80% of people with systemic lupus erythematosus (SLE) develop skin involvement at some point, and for many of them the rash was the first clue anything was wrong. A separate group has lupus that stays in the skin — cutaneous lupus erythematosus (CLE) without ever crossing the threshold into systemic disease. Understanding which form you have matters because the prognosis, workup, and treatment priorities are different.
Dermatologists split lupus skin disease into three buckets based on how long the lesions last and how deep the damage goes: acute (ACLE), subacute (SCLE), and chronic (CCLE). On top of those, there is a grab-bag of non-specific lesions — bullous lupus, lupus panniculitis (profundus), and lupus tumidus — that don't fit neatly into the three main categories but still belong to the lupus family. What unites almost all of them is photosensitivity: sunlight, fluorescent light, and even the visible light from a laptop screen can trigger flares that last weeks.
This page walks through each subtype, then spends serious time on photoprotection — the single most effective, under-used intervention in lupus skin care — followed by topical and systemic treatments that actually move the needle.
Acute Cutaneous Lupus (ACLE) — The Butterfly Rash
ACLE is the classic lupus rash most people recognize from medical textbooks: the malar or “butterfly” rash that splays across the cheeks and bridge of the nose while sparing the nasolabial folds (the creases running from nose to mouth corners). The rash is flat or slightly raised, pink to violaceous red, and often feels warm. It does not usually itch or scale, which helps distinguish it from rosacea or seborrheic dermatitis.
A key feature is that ACLE tracks the sun. Most flares follow a sunny weekend, a beach day, or even a long drive with an unprotected left arm and face. Lesions appear within hours to a few days and typically resolve within weeks — without scarring — once the trigger stops and treatment begins.
There is also a generalized form of ACLE: a widespread maculopapular rash on the trunk, arms, and V of the neck. It looks like a drug reaction or a viral exanthem and is sometimes mistaken for one.
The clinical bottom line: ACLE almost always means you have systemic lupus. Unlike SCLE and discoid lupus, ACLE rarely occurs as a purely skin-limited disease. When a butterfly rash is confirmed on biopsy, a full systemic lupus erythematosus workup (antinuclear antibody (ANA), anti-dsDNA, complement, complete blood count (CBC), urinalysis) is standard practice. See the lupus autoantibodies guide for what those numbers mean.
Subacute Cutaneous Lupus (SCLE)
SCLE sits in the middle of the spectrum. About 50% of SCLE patients meet criteria for systemic lupus erythematosus, but the systemic disease tends to be milder — joints, skin, and fatigue rather than kidneys or brain. The hallmark is extreme photosensitivity, usually on the upper back, chest, shoulders, and outer arms (the classic sun-exposed “shawl” distribution). The face can be involved but is often spared.
SCLE comes in two morphologies that can occur in the same patient:
- Annular SCLE — ring-shaped lesions with a raised red border and a pale, often slightly scaly center. They can merge into arcs and polycyclic patterns.
- Papulosquamous SCLE — red, scaly plaques that look a lot like psoriasis or eczema. Dermatologists who aren't thinking about lupus frequently misdiagnose this form for years.
About 70–90% of SCLE patients are anti-Ro/SSA positive, and many are also anti-La/SSB positive — the same antibodies central to Sjögren's syndrome. This matters for two reasons: (1) SCLE patients often develop dry eyes and dry mouth, and (2) pregnant SCLE patients with anti-Ro are at risk for neonatal lupus and congenital heart block, so the pregnancy plan needs an anti-Ro-aware obstetrician (see lupus and pregnancy).
Drug-induced SCLE is real and common. More than 100 medications have been reported to trigger it; the top offenders are hydrochlorothiazide (a very common blood-pressure drug), terbinafine (antifungal), proton-pump inhibitors, angiotensin-converting enzyme inhibitors (ACE inhibitors), calcium channel blockers, and tumor necrosis factor (TNF) inhibitors. Onset is weeks to months after starting the drug. When an SCLE flare begins after a new prescription, the newly started drug is a likely trigger, and stopping the offending drug usually clears the rash over 6–12 weeks.
SCLE lesions generally heal without scars but can leave long-lasting hypopigmentation — pale patches that last months to years and stand out against tanned skin. Patients with darker skin tones may find these cosmetically distressing; camouflage makeup and time are usually the answer, because the pigment eventually returns.
Chronic Cutaneous Lupus — Discoid and Beyond
The chronic cutaneous category is dominated by discoid lupus erythematosus (DLE), the most common scarring form of cutaneous lupus. Discoid lesions start as red, scaly, coin-shaped plaques, usually on the face, scalp, and ears. Over months they develop three signature features:
- Follicular plugging — small keratin plugs in hair follicles that feel like a bed of nails when you run a finger across the plaque.
- Atrophy and scarring — the central plaque sinks, thins, and loses its normal skin markings.
- Dyspigmentation — the center becomes pale (hypopigmented) while the border darkens (hyperpigmented). In darker skin tones this contrast is dramatic and emotionally hard.
When DLE hits the scalp, the result is permanent, scarring alopecia — the hair follicle itself is destroyed, so no amount of minoxidil or transplant will bring it back. Early treatment is the only way to save the follicles, which is why a new scaly scalp patch in a lupus patient is a dermatology emergency, not a cosmetic concern.
DLE comes in two distributions: localized (head and neck only) and generalized (below the neck, usually on arms and upper trunk). Generalized DLE is more likely to be associated with systemic disease.
The systemic lupus erythematosus progression question. Patients with isolated DLE ask whether their skin disease will turn into systemic lupus. The data are reassuring but not zero: about 5–10% of DLE patients eventually progress to systemic lupus erythematosus, usually within the first few years after diagnosis. Risk factors include generalized (below-the-neck) lesions, a positive antinuclear antibody at high titer, low complement, arthralgias, and cytopenias. Isolated, localized DLE with a negative antinuclear antibody almost never progresses. Because the risk is not zero, these risk factors are what follow-up rheumatology bloodwork looks for.
Other chronic forms include hypertrophic (verrucous) DLE, which looks warty and can mimic squamous cell carcinoma, and chilblain lupus, which produces painful, cold-induced purple nodules on fingers and toes — overlapping clinically with Raynaud's but with biopsy-proven lupus pathology.
Non-Specific Lesions: Bullous, Panniculitis, Tumidus
A handful of lupus skin manifestations don't fit the acute/subacute/chronic grid cleanly:
- Bullous lupus erythematosus — tense fluid-filled blisters on sun-exposed skin, driven by autoantibodies against type VII collagen (the same target as epidermolysis bullosa acquisita). Rare but dramatic; usually responds beautifully to dapsone.
- Lupus panniculitis (lupus profundus) — deep, painful, firm nodules in the subcutaneous fat, most often on the upper arms, thighs, buttocks, and face. When they heal they leave depressed, saucer-shaped scars that can be cosmetically severe. Hydroxychloroquine is first-line.
- Lupus tumidus (lupus erythematosus tumidus) — juicy, smooth, pink-to-violet plaques on sun-exposed skin without scale, follicular plugging, or scarring. It's the most exquisitely photosensitive form of lupus skin — some patients flare after a single lunch outside — but it also has the best prognosis, heals without scarring, and rarely associates with systemic disease.
How Ultraviolet Light Triggers Lupus Skin
Sunlight triggers lupus through at least three overlapping mechanisms. Understanding them makes photoprotection choices easier.
1. Ultraviolet (UV) induces keratinocyte apoptosis. When ultraviolet light hits skin cells, it damages DNA and triggers programmed cell death. Normally, dying cells are swept up quietly by macrophages. In lupus, clearance is slow, and dying cells spill their contents — including nuclear proteins like Ro/SSA — onto the cell surface and into the local tissue. Autoantibodies grab these exposed antigens and call in inflammation.
2. Ultraviolet drives a type I interferon response. Damaged skin cells release interferon-alpha and -beta, cytokines that are elevated in lupus blood at baseline and that orchestrate most of the downstream skin inflammation. This is the pathway that anifrolumab blocks.
3. Visible light and near-infrared also matter. For decades, photoprotection was designed around ultraviolet B (UVB) (sunburn wavelengths, 290–320 nm) and ultraviolet A (UVA) (320–400 nm). Visible light (400–700 nm) is also described as a trigger of lupus flares, especially in patients with darker skin and in SCLE. This is why standard clear sunscreens — which block ultraviolet but let visible light through — sometimes fail to protect lupus skin, and why tinted sunscreens with iron oxides are a game-changer (next section).
What is not known. The evidence that visible light on its own sets off lupus skin lesions is thin. The controlled light-testing studies in cutaneous lupus used ultraviolet A and ultraviolet B light: in a 2011 randomized study, ultraviolet light brought out lupus lesions on unprotected skin in 16 of 25 people with light-sensitive cutaneous lupus. A 2021 review of tinted sunscreens reports that visible light can redden light skin and darken (pigment) dark skin, and describes tinted sunscreens as useful for skin diseases set off by visible light.
Sunscreen — Broad-Spectrum, Visible Light, Iron Oxides
In lupus, sunscreen works as a treatment, not a cosmetic. The one controlled test of sunscreen in cutaneous lupus was a 2011 randomized, double-blind study of 25 people with light-sensitive cutaneous lupus: after ultraviolet A and B light testing, lupus lesions appeared on unprotected skin in 16 people and on skin treated with the cream base without sun filters (the vehicle) in 14, but on sunscreen-treated skin in none. The authors note that results from standardized light testing might not carry over fully to everyday life. What dermatology sources describe for products and routine:
- Broad-spectrum SPF 50+. “Broad-spectrum” means ultraviolet A and ultraviolet B. SPF refers mostly to ultraviolet B protection; a high SPF with strong ultraviolet A coverage (shown by the PA++++ rating, or by the circled “UVA” logo on European products) is the baseline.
- Mineral filters. Zinc oxide and titanium dioxide block a broader range of wavelengths than many chemical filters and are less irritating on inflamed lupus skin. A combination of mineral plus modern chemical filters (newer broad-spectrum filters, well-stabilized avobenzone) is often the most elegant. A 2021 review of tinted sunscreens notes that most mineral sunscreens use these filters as nanoparticles to avoid a white cast, and in that form they do not protect against visible light.
- Tinted formulations with iron oxides. Iron oxides are the pigments that make a sunscreen look beige or brown. The 2021 review of tinted sunscreens explains that to block visible light a sunscreen has to be visible on the skin: ordinary broad-spectrum sunscreens do not adequately protect against visible light, while tinted sunscreens do so with iron oxides and pigment-grade (non-nano) titanium dioxide. The review describes tinted sunscreens as useful for skin diseases set off by visible light and for dark-patch disorders such as melasma. For SCLE, tumidus, melasma-like hyperpigmentation, and anyone with skin of color, tinted mineral sunscreen is described as outperforming clear sunscreen.
- Amount. Sunscreen studies use 2 mg/cm², which works out to a full teaspoon for the face and neck alone. Most people apply a quarter of that and get a quarter of the labeled SPF.
- Reapplication. The usual interval is every 2 hours outdoors, and after swimming or sweating; some people use a phone alarm as a reminder.
- Indoors near windows. Ordinary window glass blocks ultraviolet B but lets ultraviolet A and visible light through, so a sunlit desk, car commute, or kitchen window can drive a flare.
UPF Clothing, Tinted Window Film, Physical Measures
Sunscreen is only one layer of protection in active cutaneous lupus. Skin covered with fabric is protected essentially 24/7 and without reapplication. Clothing and gear used for this:
- UPF 50+ long-sleeve shirts. Many outdoor and sun-protective clothing makers sell breathable, lightweight options. A UPF rating of 50 blocks 98% of ultraviolet.
- Wide-brim hats. At least a 3-inch (7.5 cm) brim all the way around — baseball caps leave the ears and neck exposed. A neck drape adds cover for people with scalp discoid lupus.
- Wraparound ultraviolet-blocking sunglasses. Protects periocular skin and reduces photosensitive headache.
- Ultraviolet gloves for driving. The left arm and left cheek of drivers in right-hand-traffic countries (and the right arm in the UK/Japan/Australia) take a disproportionate ultraviolet dose through the driver's window.
Tinted window film is underused and under-prescribed. High-quality ceramic or nano-carbon films block 99% of ultraviolet A/ultraviolet B and reduce visible light by 20–70% depending on shade. Applied to home windows (especially south- and west-facing), car side windows, and office glass, film turns high-risk environments into safe ones. U.S. state laws regulate car-window tint darkness, but a medical exemption for lupus is available in most states, usually with a letter from a rheumatologist or dermatologist stating the reason. Professional installation runs $200–$800 for a car and $5–$15 per square foot for home windows. For people with severe photosensitivity, film protects every hour spent in that car or room without any reapplication.
Indoor fluorescent and some LED lighting also emit low-level ultraviolet. When flares track a work week spent under harsh fluorescent tubes, the options people use are filtered LED bulbs or ultraviolet-blocking sleeves on the tubes.
Topical Steroids and Calcineurin Inhibitors
For active lesions, topical anti-inflammatories are first-line. The decision is which potency and where.
- Low-potency topical steroids (hydrocortisone 2.5%, desonide) — face, neck, skin folds. Safe for short courses (2–4 weeks) to calm ACLE flares.
- Mid-potency steroids (triamcinolone 0.1%, mometasone) — trunk, arms, legs.
- High-potency steroids (clobetasol 0.05%, halobetasol) — scalp DLE, thick discoid plaques, palms/soles. Potent steroids thin facial skin quickly, so on the face they are generally used only in short pulses directed by a dermatologist.
- Intralesional triamcinolone — injected directly into stubborn discoid plaques every 4–6 weeks. Dramatic for isolated lesions that resist topicals.
- Topical calcineurin inhibitors (tacrolimus 0.1% ointment, pimecrolimus 1% cream) — these non-steroid immunomodulators are a huge win for facial and intertriginous lupus because they don't cause skin atrophy. Used long-term on the face without the thinning, telangiectasia, or perioral dermatitis that steroids cause. They are applied twice daily; a mild burning sensation in the first few days is common and subsides.
Hydroxychloroquine and Quinacrine
For any cutaneous lupus that isn't controlled by topicals — and certainly for any patient with systemic lupus erythematosus — hydroxychloroquine (HCQ) is first-line systemic therapy. It is the single most important drug in lupus, with evidence for reducing flares, protecting the kidneys, reducing thrombosis risk, and improving survival. See the hydroxychloroquine guide for dosing, monitoring, and the retinal toxicity question.
For cutaneous disease specifically, dosing is the same (5 mg/kg of actual body weight per day, capped around 400 mg). It takes 6–12 weeks for skin response, which is frustrating when lesions are actively spreading; topicals and, in severe cases, a short course of prednisone are used as a bridge.
Roughly one-third of cutaneous lupus patients don't respond adequately to HCQ alone. The next step, classically, is adding quinacrine (mepacrine) — another antimalarial from the same era as HCQ and chloroquine. Quinacrine is not sold by standard U.S. pharmacies; it has to be obtained from a compounding pharmacy (common dose 100 mg daily). It does not carry the retinal toxicity risk of HCQ, so the ophthalmology monitoring burden doesn't double. The main side effect is yellow-orange skin discoloration that reverses when the drug is stopped. The HCQ-plus-quinacrine combination rescues many patients who had been considered antimalarial failures.
If hydroxychloroquine plus quinacrine still fails, the options are to switch HCQ to chloroquine (slightly more potent, higher retinal risk), or to move up to immunosuppressants (methotrexate, mycophenolate, azathioprine) or to biologics.
Smoking and antimalarial response. A 2015 pooled analysis of 10 studies covering 1,398 people with cutaneous lupus found that smokers responded less often to antimalarial drugs such as hydroxychloroquine than non-smokers (odds ratio 0.53); the authors describe this as a two-fold drop in the share of patients whose skin improved. A 2019 review of smoking and lupus found the same 0.53 figure for skin response to hydroxychloroquine, found that smoking also reduced the response to belimumab in whole-body (systemic) lupus (hazard ratio 0.10), and found that current smokers had about 1.5 times the odds of developing lupus (odds ratio 1.49, from 9 case-control studies), while former smokers were not at higher risk.
The current European guideline. The European Alliance of Associations for Rheumatology (EULAR) updated its lupus recommendations in 2023 (published January 2024), replacing the 2019 version. It recommends hydroxychloroquine for all patients with lupus at a target dose of 5 mg/kg of real body weight per day, weighing each person’s risk of flares and of eye (retinal) damage. Steroids are described as a “bridge” during active disease, with maintenance kept at 5 mg/day of prednisone or less and stopped when possible, and early use of immunosuppressants and/or the biologics anifrolumab or belimumab is to be considered to control the disease and help taper steroids. The update also contains specific recommendations for skin disease.
Thalidomide, Lenalidomide, and Refractory DLE
For scarring discoid lupus and other cutaneous lupus that has resisted antimalarials, topicals, and standard immunosuppressants, thalidomide often clears the skin. In a 2012 study of 60 consecutive patients with treatment-resistant cutaneous lupus given thalidomide 100 mg a day, 58 of the 59 who stayed on it (98%) responded, with improvement visible from 2 weeks, and 50 (85%) cleared completely. Relapse was common: 70% relapsed, usually about 5 months after the drug was stopped or the dose cut. Discoid lupus was the form most likely to relapse and needed a long-term maintenance dose, while subacute lupus (SCLE) tended to stay in remission after stopping. Its mechanism involves inhibition of tumor necrosis factor-alpha and modulation of T-cell responses. The catches are serious:
- Severe teratogen. Thalidomide caused one of the worst pharmaceutical disasters of the 20th century. In the U.S. it is available only through a restricted-distribution safety program (Risk Evaluation and Mitigation Strategy, REMS); the drug label requires two negative pregnancy tests before starting, then tests weekly in the first month and monthly after that (every 2 weeks with irregular periods) for patients who can become pregnant, plus strict contraception requirements.
- Peripheral neuropathy. Thalidomide can damage the sensory nerves (sensory neuropathy) — numbness, tingling, and burning in the feet. In the 2012 study, 11 patients (18%) reported tingling or pins and needles (paraesthesia), and nerve conduction studies confirmed sensory nerve damage (polyneuropathy) in 5 of them; the symptoms resolved in about 12 months (range 6–18) after thalidomide was stopped. Regular nerve checks and nerve conduction studies are part of monitoring.
- Sedation, constipation, thrombosis risk. In the 2012 study, two patients who were heavy smokers had a stroke-type event (cerebral ischaemic event).
Because of the neuropathy and teratogenicity, many dermatologists now use lenalidomide (a thalidomide analog originally developed for multiple myeloma) at 5–10 mg daily instead. Lenalidomide has a much lower neuropathy risk and similar efficacy in refractory DLE, though it remains teratogenic and expensive.
These drugs are reserved for patients with relentless scarring disease — not for mild cosmetic concerns — and are always prescribed by a dermatologist or rheumatologist experienced with them.
Anifrolumab and the Interferon Pathway
Anifrolumab is a monoclonal antibody that blocks the type I interferon receptor. It was approved by the U.S. Food and Drug Administration (FDA) in 2021 for moderate-to-severe systemic lupus erythematosus, and the pivotal TULIP-1 and TULIP-2 trials showed skin-score improvement in patients with active cutaneous disease. In TULIP-1, among patients whose skin score (Cutaneous Lupus Erythematosus Disease Area and Severity Index, CLASI) activity was 10 or higher at the start, 42% on anifrolumab 300 mg had their CLASI activity score cut by at least half by week 12, against 25% on placebo (the confidence interval of that difference just crossed zero, and TULIP-1 missed its main goal). In TULIP-2, the improvement in skin-disease severity was significantly better than placebo. For systemic lupus erythematosus patients whose dominant active feature is skin, anifrolumab is often the biologic of choice.
Dosing is a monthly intravenous infusion (300 mg). The main risks are infections (particularly viral upper respiratory) and herpes zoster reactivation; in TULIP-2, shingles (herpes zoster) occurred in 7.2% of patients on anifrolumab, and the drug label calls for vaccinations to be brought up to date under current guidelines before starting, with no live vaccines during treatment. The label states that the limited human data in pregnancy are not enough to show the drug’s risk to a pregnancy.
An under-the-skin (subcutaneous) form, anifrolumab 120 mg once a week, was tested in the phase 3 TULIP-SC trial in adults with moderate-to-severe systemic lupus: at the planned interim analysis of 220 patients, 59.4% on anifrolumab responded on the trial’s main lupus-activity measure (British Isles Lupus Assessment Group-based Composite Lupus Assessment, BICLA) at week 52, against 43.9% on placebo; shingles occurred in 3.8% versus 1.1%.
See the lupus biologics page for full comparisons with belimumab and rituximab.
Belimumab, a BLyS inhibitor, has less dramatic skin-specific data but also helps cutaneous disease as part of overall systemic lupus erythematosus control. For purely skin-limited CLE without systemic activity, neither biologic is formally approved, though off-label use in severe refractory cases is described.
Drugs in testing for skin-only lupus. No targeted drug is yet approved for cutaneous lupus. In the phase 2 part of the AMETHYST trial (published 2026), litifilimab — an antibody aimed at BDCA2, a receptor on the immune cells that make type I interferon — given as 225 mg every 4 weeks cleared or almost cleared skin redness in 14.7% of participants versus 2.9% on placebo at week 16, and 21.7% versus 5.8% reached a 70% drop in CLASI score at week 24. The study was not designed with enough participants to test its secondary results for statistical significance.
Managing Scars, Hair Loss, and Hyperpigmentation
Once DLE scars or SCLE pigment changes are set, no drug reverses them quickly — but several interventions help.
- Hyperpigmentation (dark spots) — topical azelaic acid 15–20%, tranexamic acid (topical or oral), niacinamide, and hydroquinone 4% (short courses, under dermatologist supervision) fade dark macules over 3–6 months. Daily SPF 50+ tinted sunscreen is described as essential alongside them — without it, these treatments are reported not to work.
- Hypopigmentation (pale spots) — harder to treat. Pigment sometimes returns on its own over a year or more. Excimer laser and narrow-band ultraviolet B (carefully targeted, under dermatologist supervision only — home phototherapy is not used for lupus skin, because ultraviolet light itself triggers lupus lesions) can sometimes restore melanocyte function.
- Scarring alopecia — if follicles are destroyed, no drug regrows hair. Options are hair systems (wigs and toppers), scalp micropigmentation, and — once disease is quiescent for at least two years — hair transplantation into scarred areas, though grafts can be poorly vascularized. Minoxidil doesn't help scarred follicles.
- Panniculitis scars (depressions in the face or arm) — hyaluronic acid fillers can cosmetically raise sunken areas. Autologous fat transfer is another option. These are generally done only after the disease has been stable for at least 6–12 months, because active panniculitis can destroy injected material.
- Makeup camouflage — waterproof high-coverage camouflage foundations cover both red active lesions and pigment changes. Color-correcting green or peach primers neutralize red and brown tones before foundation. This is not vanity; it is daily functioning for many patients.
A Realistic Daily Routine
What does photoprotection actually look like on a Tuesday? Something like this:
- Morning: gentle cleanser; bland moisturizer; tinted broad-spectrum mineral sunscreen SPF 50+ with iron oxides (full teaspoon for face, neck, ears, V of chest, and tops of hands).
- Before leaving the house: UPF 50 long-sleeve layer, wide-brim hat, wraparound sunglasses, ultraviolet driving gloves if going to the car.
- Every two hours outside: sunscreen reapplied — a mineral powder or stick is practical over makeup.
- At work: a seat more than an arm's length from sunlit windows; tinted window film or blinds on the worst ones.
- Evening: gentle cleanser to remove sunscreen (double-cleanse if wearing a heavy mineral product); topical medication (tacrolimus to active patches, clobetasol to thick scalp plaques per dermatologist); bland moisturizer; HCQ with dinner to reduce nausea.
- Monthly: a check of sunscreen and medication supplies; a new hat or UPF shirt when the elastic is dying; dermatology follow-up every 3–6 months during active disease.
- Annually: eye exam (uveitis screen, HCQ retinal screening by year five), vitamin D level (strict sun avoidance causes deficiency — 1000–2000 international units (IU) daily is a commonly described supplement range for lupus patients), full skin check, and lupus bloodwork per rheumatology.
This is a lot. It gets easier once it becomes habit — the sunscreen and hat are just what you do before leaving the house, the same way brushing your teeth is. Many patients report fewer flares once the routine becomes habit.
Key Research Papers
- Okon LG, Werth VP. Cutaneous lupus erythematosus: diagnosis and treatment. Best Pract Res Clin Rheumatol. 2013. — doi:10.1016/j.berh.2013.07.008 (Foundational review of CLE classification and management.)
- Morand EF, et al. Trial of anifrolumab in active systemic lupus erythematosus (TULIP-2). N Engl J Med. 2020. — doi:10.1056/NEJMoa1912196
- Furie R, et al. Type I interferon inhibitor anifrolumab in active systemic lupus erythematosus (TULIP-1). Lancet Rheumatol. 2019. — doi:10.1016/S2665-9913(19)30076-1
- Kuhn A, Gensch K, Haust M, et al. Photoprotective effects of a broad-spectrum sunscreen in ultraviolet-induced cutaneous lupus erythematosus: a randomized, vehicle-controlled, double-blind study. J Am Acad Dermatol. 2011;64(1):37–48. — PubMed PMID: 21167404
- Lyons AB, Trullas C, Kohli I, Hamzavi IH, Lim HW. Photoprotection beyond ultraviolet radiation: a review of tinted sunscreens. J Am Acad Dermatol. 2021;84(5):1393–1397. — PubMed PMID: 32335182
- Cortés-Hernández J, Torres-Salido M, Castro-Marrero J, et al. Thalidomide in the treatment of refractory cutaneous lupus erythematosus: prognostic factors of clinical outcome. Br J Dermatol. 2012;166(3):616–623. — PubMed PMID: 21999437
- Fennira F, et al. Lenalidomide for refractory chronic and subacute cutaneous lupus erythematosus. J Am Acad Dermatol. 2016. — doi:10.1016/j.jaad.2016.01.054
- Fanouriakis A, Kostopoulou M, Alunno A, et al. 2019 update of the EULAR recommendations for the management of systemic lupus erythematosus. Ann Rheum Dis. 2019;78(6):736–745. — doi:10.1136/annrheumdis-2019-215089 (Superseded by the 2023 update below.)
- Fanouriakis A, Kostopoulou M, Andersen J, et al. EULAR recommendations for the management of systemic lupus erythematosus: 2023 update. Ann Rheum Dis. 2024;83(1):15–29. — PubMed PMID: 37827694
- Chasset F, Francès C, Barete S, Amoura Z, Arnaud L. Influence of smoking on the efficacy of antimalarials in cutaneous lupus: a meta-analysis of the literature. J Am Acad Dermatol. 2015;72(4):634–639. — PubMed PMID: 25648824
- Parisis D, Bernier C, Chasset F, Arnaud L. Impact of tobacco smoking upon disease risk, activity and therapeutic response in systemic lupus erythematosus: a systematic review and meta-analysis. Autoimmun Rev. 2019;18(11):102393. — PubMed PMID: 31520802
- Manzi S, Bruce IN, Morand EF, et al. Efficacy and safety of subcutaneous anifrolumab in systemic lupus erythematosus: a randomized, phase 3 study. Arthritis Rheumatol. 2026;78(6):1258–1267. — PubMed PMID: 41466456
- Merola JF, Werth VP, Chong BF, et al. Efficacy and safety of litifilimab in cutaneous lupus erythematosus: 24-week results of the randomized phase 2 study, AMETHYST. J Am Acad Dermatol. 2026 (online ahead of print). — PubMed PMID: 42892381
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on cutaneous lupus subtypes, photoprotection, and treatment:
- PubMed: Cutaneous lupus erythematosus classification
- PubMed: Discoid lupus and scarring alopecia
- PubMed: Drug-induced subacute cutaneous lupus
- PubMed: Cutaneous lupus photoprotection and iron oxide sunscreen
- PubMed: Visible light and cutaneous lupus
- PubMed: Hydroxychloroquine plus quinacrine in cutaneous lupus
- PubMed: Thalidomide and lenalidomide for refractory discoid lupus
- PubMed: Anifrolumab and cutaneous lupus CLASI response
Connections
- Rheumatology
- Lupus Overview
- Lupus and Pregnancy
- Biologics: Belimumab, Anifrolumab and Rituximab
- Antinuclear Antibody, dsDNA and Lupus Autoantibodies
- Hydroxychloroquine and Antimalarials
- Neuropsychiatric Lupus
- ACR-EULAR 2019 Classification Criteria
- Lupus-Sjogren's Overlap
- Lupus Nephritis and Kidney Involvement
- Raynaud's Disease
- Sjogren's Syndrome
- Vitamin D3
- Alopecia
- Full Body Magnetic Resonance Imaging
- Psoriasis