ACR/EULAR 2019 Classification Criteria for Systemic Lupus Erythematosus (SLE)
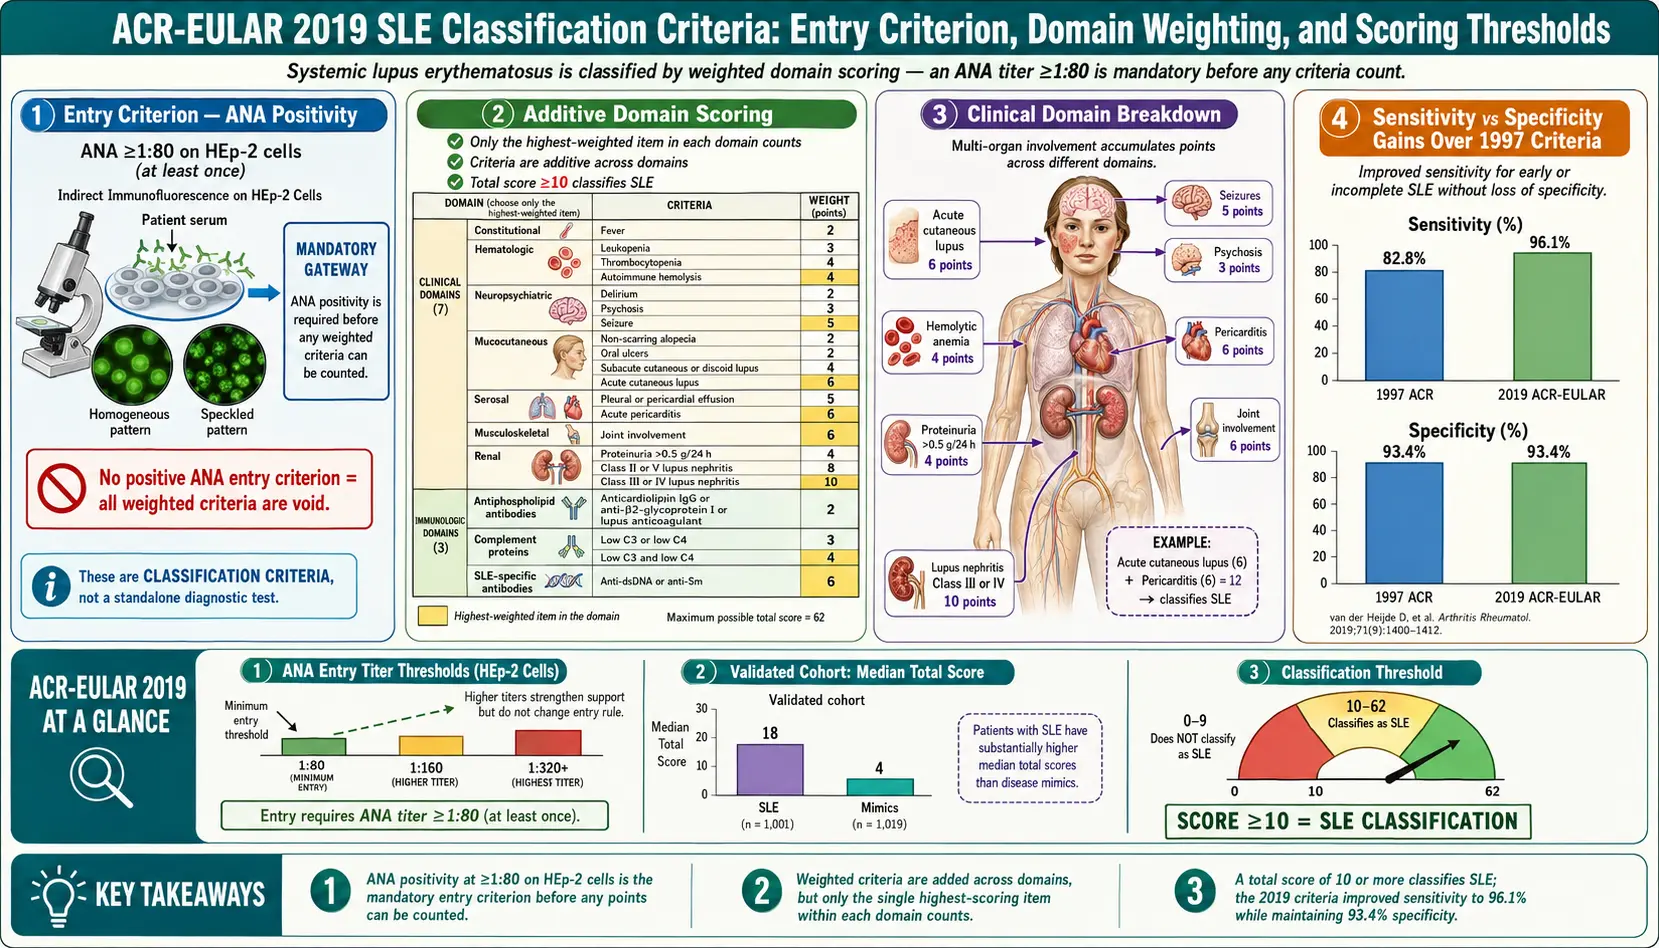
Table of Contents
- Why Classification Criteria Exist
- The Evolution: 1982 → SLICC 2012 → ACR/EULAR 2019
- The Entry Criterion: Antinuclear Antibody ≥1:80
- The Ten Weighted Domains
- Scoring Rules — ≥10 Points and One Clinical Criterion
- How Well It Performs: 96% Sensitivity, 93% Specificity
- Classification Is Not Diagnosis
- Limitations: Young Patients, Early Disease, Rare Presentations
- Worked Examples
- What a Score Does and Does Not Tell You
- Key Research Papers
- Connections
- Featured Videos
Why Classification Criteria Exist
If you have been told you "meet lupus criteria" — or worse, that you "don't meet criteria" and therefore don't have lupus — it helps to understand what the criteria actually are, why they exist, and what they cannot do.
Classification criteria were invented so that researchers running clinical trials could be sure that everyone enrolled in a "lupus" study actually had the same disease. Without a standard, one hospital's trial of 100 "lupus patients" might overlap only loosely with another hospital's 100 "lupus patients," and the drug results would be impossible to compare. Classification criteria solve that problem — they create a shared rulebook for research.
That is all they were designed to do. They were never meant to be a diagnostic checklist a physician uses in clinic to decide whether to treat you. The person making your diagnosis is a rheumatologist applying clinical judgment to your full picture: symptoms, physical exam, labs, imaging, biopsies, family history, and response to therapy. Criteria are a reference point, not a verdict. This distinction matters enormously, and we come back to it in section 7.
The Evolution: 1982 → SLICC 2012 → ACR/EULAR 2019
Three generations of criteria have shaped how we classify systemic lupus erythematosus (SLE):
The 1982 ACR Criteria (revised 1997)
The original American College of Rheumatology (ACR) criteria listed eleven items — malar rash, discoid rash, photosensitivity, oral ulcers, arthritis, serositis, renal disorder, neurologic disorder, hematologic disorder, immunologic disorder, and a positive antinuclear antibody (ANA). A patient needed at least 4 of 11, either simultaneously or serially, to be classified as having systemic lupus erythematosus. The criteria were simple and durable, used in thousands of studies, but they had known gaps. Lupus nephritis confirmed on biopsy — a slam-dunk piece of evidence — only counted as one item. Patients with severe single-organ disease often failed to reach four and were excluded from trials.
The SLICC 2012 Criteria
The Systemic Lupus International Collaborating Clinics (SLICC) group expanded the list to 17 items split into clinical and immunologic categories. A patient met criteria with at least 4 items including at least one from each category, or with biopsy-proven lupus nephritis plus a positive antinuclear antibody or anti-dsDNA. In its validation set of 690 expert-rated patient scenarios, sensitivity improved (97% versus 83% for the ACR criteria) but specificity dropped (84% versus 96%) — SLICC 2012 pulled in more true cases but also more false positives. In the earlier derivation set of 702 scenarios, SLICC sensitivity was 94% versus 86% for the ACR criteria, with about equal specificity (92% versus 93%).
The ACR/EULAR 2019 Criteria
In 2019 the American College of Rheumatology and the European League Against Rheumatism (EULAR, now the European Alliance of Associations for Rheumatology) jointly published a new system built from the ground up. Three innovations set it apart:
- A mandatory entry criterion — antinuclear antibody positive at ≥1:80 — before any other item is counted.
- Weighted scoring. Items are not all worth one point. Lupus nephritis class III/IV on biopsy is worth 10. Leukopenia is worth 3. The weights reflect how strongly each finding points toward systemic lupus erythematosus.
- An “attribution rule.” An item only counts if there is no better explanation than lupus. Fever from a clear urinary tract infection does not count. Arthritis from a fresh ankle sprain does not count.
The result is a more flexible, more discriminating rulebook. A single heavily-weighted finding plus the right background can cross the threshold; a scatter of weak findings cannot. The full reference is Aringer et al., Arthritis & Rheumatology 2019 (DOI below).
The Entry Criterion: Antinuclear Antibody ≥1:80
The 2019 system starts with a gatekeeper: you must have a positive antinuclear antibody (ANA) at a titer of at least 1:80, measured by the reference method — indirect immunofluorescence on HEp-2 cells — at some point in your history. If you have never had an antinuclear antibody at 1:80 or higher, the criteria stop there. Nothing else you could score matters; you are not classified as systemic lupus erythematosus by this system.
The logic is straightforward. Roughly 97–98% of people with lupus have a positive antinuclear antibody at 1:80 or higher at some point. Requiring it up front dramatically reduces false positives — patients with unrelated diseases whose rash or joint pain might otherwise accidentally score points.
A few nuances patients ask about:
- Once positive, always counts. If your antinuclear antibody was 1:160 five years ago and is 1:40 today, the entry criterion is still met. Antinuclear antibody titers fluctuate; the system treats any historical positive at 1:80+ as qualifying.
- Method matters. Many commercial labs use ELISA or multiplex bead assays rather than HEp-2 immunofluorescence. Results do not always match. An ELISA-based antinuclear antibody can be negative when a HEp-2 immunofluorescence test would be positive. HEp-2 immunofluorescence is the method the criteria reference.
- A low-titer antinuclear antibody is not lupus. In a 1997 study in which 15 international laboratories tested the blood of healthy people on HEp-2 cells, about 1 in 3 (31.7%) were positive at 1:40, 13.3% at 1:80, 5.0% at 1:160 and 3.3% at 1:320; the rate did not differ significantly between age groups from 20 to 60 years. Each step up in titer leaves fewer healthy people positive, which is why the 2019 system sets its gate at 1:80 rather than 1:40. An antinuclear antibody alone — without symptoms, without other labs — is not a diagnosis of anything. See the antinuclear antibody and autoantibody article for the full interpretation guide.
The Ten Weighted Domains
Past the entry criterion, findings are grouped into ten domains — seven clinical and three immunologic. Within each domain, only the single highest-scoring item counts. You do not add up multiple items from the same domain. This prevents, say, three different skin findings from quadruple-counting.
Clinical Domains
- Constitutional — unexplained fever over 38.3°C (2 points).
- Hematologic — leukopenia, white count below 4,000 (3 points); thrombocytopenia, platelet count below 100,000 (4 points); autoimmune hemolysis (4 points).
- Neuropsychiatric — delirium (2), psychosis (3), seizure (5). Each demands careful exclusion of other causes. See the neuropsychiatric lupus article.
- Mucocutaneous — non-scarring alopecia (2), oral ulcers (2), subacute cutaneous or discoid lupus (4), acute cutaneous lupus (6, the classic malar "butterfly" rash). See the cutaneous lupus page.
- Serosal — pleural or pericardial effusion (5), acute pericarditis (6).
- Musculoskeletal — joint involvement (6): at least two joints with synovitis or tender joints with more than 30 minutes of morning stiffness.
- Renal — proteinuria over 0.5 g / 24 hours (4), kidney biopsy showing class II or V lupus nephritis (8), kidney biopsy showing class III or IV lupus nephritis (10). Class III/IV is a one-shot ticket across the threshold. See the lupus nephritis article.
Immunologic Domains
- Antiphospholipid antibodies — anti-cardiolipin, anti-beta-2-glycoprotein I, or lupus anticoagulant positive at medium-high titer (2 points).
- Complement proteins — low C3 or low C4 (3 points); low C3 and low C4 (4 points).
- Systemic lupus erythematosus-specific antibodies — anti-dsDNA or anti-Smith, either one present (6 points).
A subtle point about the "only the highest counts within a domain" rule: a patient with both thrombocytopenia and autoimmune hemolytic anemia scores 4 (not 4+4=8) in the hematologic domain. A patient with both low C3 and low C4 scores 4 in the complement domain. Across different domains the scores add freely.
Scoring Rules — ≥10 Points and One Clinical Criterion
Three rules must all be met:
- Entry criterion — antinuclear antibody ≥1:80 at least once.
- Attribution — each item is only counted if lupus is the most likely explanation. The attending rheumatologist makes the call.
- Total ≥10 points with at least one clinical criterion. You cannot meet the threshold on immunologic findings alone, no matter how striking the labs look.
The "at least one clinical" rule matters. A hypothetical patient with a positive antinuclear antibody, high-titer anti-dsDNA (6), low C3 and C4 (4), and antiphospholipid antibodies (2) scores 12 on labs alone — but without a single clinical feature they do not classify as systemic lupus erythematosus. In real practice this almost never happens; labs this striking usually come with at least some clinical finding. The rule is a backstop against pure-lab classifications.
Time window: items need not appear simultaneously. Anything documented at any point in the patient's history counts, as long as the attribution rule still holds.
How Well It Performs: 96% Sensitivity, 93% Specificity
The criteria were refined in a derivation cohort of 1,001 people and then tested in a separate validation cohort of 1,270 people. In the validation cohort, performance measured:
- Sensitivity: 96.1% — of patients with a rheumatologist's diagnosis of systemic lupus erythematosus, 96% also met the 2019 criteria.
- Specificity: 93.4% — of patients with a non-SLE connective tissue disease (Sjögren's, rheumatoid arthritis, scleroderma, and so on), 93% did not meet criteria.
Compared to the earlier systems, the 2019 criteria improved specificity over SLICC 2012 (83.7% to 93.4%) and improved sensitivity over the 1997 ACR criteria (82.8% to 96.1%). It is the most accurate classification tool systemic lupus erythematosus has ever had.
Side by side in the same validation cohort of 1,270 people:
- ACR/EULAR 2019: sensitivity 96.1%, specificity 93.4%.
- ACR 1997: sensitivity 82.8%, specificity 93.4% — just as good at ruling out other diseases, but it missed more of the people with lupus.
- SLICC 2012: sensitivity 96.7%, specificity 83.7% — it caught as many people with lupus, but wrongly classified more of the people with other diseases.
So the 2019 system keeps the 1997 criteria’s strength at ruling out other diseases and the SLICC criteria’s strength at catching true cases.
Sensitivity also depends on how long the disease has been present. A 2020 analysis of the validation cohort found that among patients with 1 to under 3 years of disease, the 2019 criteria had 97% sensitivity, compared with 81% for the ACR criteria. That analysis did not report figures for the first months of symptoms — when organ damage may not yet have accumulated and antibody profiles may still be evolving. This early window is discussed further below.
The same 2020 study, from 21 lupus centres in 16 countries, checked whether the 2019 criteria work equally well for different groups of people. Sensitivity was 93% and specificity 96% in men, and 97% and 94% in women. In Black patients sensitivity was 98% and specificity 100%. Compared with the ACR criteria, sensitivity was higher in Hispanic patients (100% versus 86%) and Asian patients (97% versus 77%). The groups were of very different sizes: 941 white, 124 Hispanic, 118 Asian and 68 Black patients.
Classification Is Not Diagnosis
This is the single most common source of confusion, and it is worth being blunt about it.
Classification criteria are for research cohorts. Diagnosis is what a rheumatologist does in clinic. A physician can, and routinely does, diagnose lupus in patients who do not meet classification criteria — because the clinical picture is obvious, because a biopsy shows classic pathology, because the patient responds to hydroxychloroquine the way lupus patients respond, because other diseases have been ruled out. Physicians can also withhold a lupus diagnosis from a patient who technically meets criteria if the individual items are better explained by something else, even after attribution review.
If a clinician tells you "you don't meet criteria, so you don't have lupus," that is a misuse of the tool. The correct question is "what do you think this is, and how are we going to work it up?" — not "did you score ten points on a rubric?"
The inverse is also true. "Meeting criteria" is not the same as "definitely has lupus." It means "looks enough like lupus that a research study would enroll this person." Most people who meet criteria do indeed have systemic lupus erythematosus, but the criteria are not perfect: in the 2019 validation study, about 7 in 100 patients who had other diseases that mimic lupus still reached 10 points. Classification is an approximation, not a pronouncement.
Limitations: Young Patients, Early Disease, Rare Presentations
Several real-world situations expose the limits of any classification tool:
- Early disease. In the first six to twelve months, many patients have only a handful of features — photosensitive rash plus arthralgia plus a positive antinuclear antibody, for example — that do not yet total ten points. They may still have lupus. Early-SLE cohorts consistently show that criteria accumulate over time; the clock does not start at ten and count down.
- Pediatric and adolescent lupus. Children with systemic lupus erythematosus often present with kidney or hematologic disease that scores heavily and tends to meet criteria earlier. But rare juvenile variants (for example, monogenic interferonopathies that mimic lupus) may score high without being classical systemic lupus erythematosus.
- Drug-induced lupus. Hydralazine, procainamide, minocycline, tumor necrosis factor (TNF) inhibitors, and a few others cause a lupus-like syndrome that can score points. The attribution rule is supposed to screen these out, but the clinical call can be difficult when a patient has been on the drug for years.
- Isolated cutaneous lupus. Discoid lupus confined to the skin, without systemic involvement, often does not cross the threshold. That is appropriate — skin-limited disease is biologically distinct and treated differently. See the cutaneous lupus article.
- Overlap syndromes. Patients with mixed connective tissue disease, undifferentiated connective tissue disease, or lupus-Sjögren's overlap may score points from features belonging to either condition. The attribution rule helps, but the lines are fuzzy. See the lupus-Sjögren's overlap article.
- Antinuclear antibody-negative lupus. Roughly 2–3% of systemic lupus erythematosus patients have a persistently negative antinuclear antibody by immunofluorescence, often with anti-Ro/SSA antibodies instead. These patients cannot meet the 2019 criteria by definition. They still have lupus. A rheumatologist can diagnose and treat them; they simply would not be enrolled in a strictly 2019-criteria trial.
Worked Examples
Three composite cases illustrate how the arithmetic plays out.
Example 1: Meets Criteria Easily
A 28-year-old woman with:
- Antinuclear antibody 1:640 (entry met)
- Malar rash — acute cutaneous lupus (6)
- Arthritis of wrists and MCP joints (6)
- Anti-dsDNA positive (6)
- Low C3 and C4 (4)
Total: 22. Meets criteria comfortably, with multiple clinical items.
Example 2: Borderline, Pending Biopsy
A 34-year-old man with:
- Antinuclear antibody 1:320 (entry met)
- Oral ulcers (2)
- Non-scarring alopecia (2)
- Proteinuria 1.2 g / 24 hours (4)
- Low C3 only (3)
Total: 11, with clinical criteria present. Meets 2019 criteria. A kidney biopsy would add weight (class III nephritis would push the total to 17 and dictate treatment).
Example 3: Does Not Meet — But May Still Have Lupus
A 19-year-old woman, three months into symptoms:
- Antinuclear antibody 1:160 (entry met)
- Photosensitive rash that is not clearly acute cutaneous lupus (0, unless dermatology attributes it)
- Arthralgia without objective synovitis (0 — tenderness alone does not count without morning stiffness ≥30 min)
- Mild leukopenia at 3,800 (3)
Total: 3. Does not meet criteria. She does not "not have lupus." She has early, evolving disease, and the rheumatologist will follow her closely, check dsDNA and complement over time, and reassess. Half of patients in this pattern go on to meet criteria within two years.
What a Score Does and Does Not Tell You
When a clinician quotes an ACR/EULAR 2019 score, these are the parts that sit behind the number:
- The breakdown. The score is a sum of points from separate domains, so it can be broken down into which domains contributed which points.
- Attribution. Some items may have been left out because the rheumatologist judged another cause more likely; each of those is a judgment with a reason behind it.
- Missing information. Tests that have not been done score nothing: an anti-dsDNA test, complement levels, or a kidney biopsy when there is protein in the urine can each change the score and the treatment plan.
- The score is not the diagnosis. The clinical diagnosis, the clinician’s confidence in it and the list of other possible diseases (the differential) are separate from the score.
- Symptoms without meeting criteria. Undifferentiated connective tissue disease, follow-up intervals and early hydroxychloroquine are the topics that come up in this situation — in some early-SLE cohorts, early hydroxychloroquine slows progression to full systemic lupus erythematosus. See the hydroxychloroquine article.
For the full picture of how classification interacts with treatment decisions, medication selection, and long-term monitoring, start at the lupus overview. If kidneys are involved, the lupus nephritis article covers biopsy classes and induction therapy in depth; see also kidney disease for broader context. Pregnancy changes monitoring considerably — see lupus and pregnancy.
Key Research Papers
- Aringer M, Costenbader K, Daikh D, et al. 2019 European League Against Rheumatism/American College of Rheumatology classification criteria for systemic lupus erythematosus. Arthritis Rheumatol. 2019;71(9):1400–1412. — doi:10.1002/art.40930
- Aringer M, Costenbader K, Daikh D, et al. 2019 EULAR/ACR classification criteria for systemic lupus erythematosus. Ann Rheum Dis. 2019;78(9):1151–1159. — doi:10.1136/annrheumdis-2018-214819
- Petri M, Orbai AM, Alarcón GS, et al. Derivation and validation of the Systemic Lupus International Collaborating Clinics classification criteria for systemic lupus erythematosus. Arthritis Rheum. 2012;64(8):2677–2686. — doi:10.1002/art.34473
- Hochberg MC. Updating the American College of Rheumatology revised criteria for the classification of systemic lupus erythematosus. Arthritis Rheum. 1997;40(9):1725. — doi:10.1002/art.1780400928
- Tan EM, Cohen AS, Fries JF, et al. The 1982 revised criteria for the classification of systemic lupus erythematosus. Arthritis Rheum. 1982;25(11):1271–1277. — doi:10.1002/art.1780251101
- Fanouriakis A, Kostopoulou M, Andersen J, et al. EULAR recommendations for the management of systemic lupus erythematosus: 2023 update. Ann Rheum Dis. 2024;83(1):15–29. — doi:10.1136/ard-2023-224762
- Tan EM, Feltkamp TE, Smolen JS, et al. Range of antinuclear antibodies in “healthy” individuals. Arthritis Rheum. 1997;40(9):1601–1611. — PubMed PMID: 9324014
- Johnson SR, Brinks R, Costenbader KH, et al. Performance of the 2019 EULAR/ACR classification criteria for systemic lupus erythematosus in early disease, across sexes and ethnicities. Ann Rheum Dis. 2020;79(10):1333–1339. — PubMed PMID: 32816709
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on systemic lupus erythematosus classification, validation cohorts, and real-world application of the 2019 criteria:
- PubMed: ACR/EULAR 2019 classification criteria for SLE
- PubMed: SLICC 2012 classification criteria validation
- PubMed: ANA as entry criterion in lupus classification
- PubMed: Early undifferentiated connective tissue disease progressing to SLE
- PubMed: ANA-negative lupus and anti-Ro antibodies
- PubMed: Pediatric SLE and classification criteria performance
- PubMed: Drug-induced lupus and classification criteria
- PubMed: Lupus nephritis biopsy classes (ISN/RPS)
Connections
- Rheumatology
- Lupus Overview
- Antinuclear Antibody, dsDNA and Lupus Autoantibodies
- Neuropsychiatric Lupus
- Lupus and Pregnancy
- Cutaneous Lupus and Photoprotection
- Lupus-Sjogren's Overlap
- Hydroxychloroquine and Antimalarials
- Lupus Nephritis and Kidney Involvement
- Biologics: Belimumab, Anifrolumab and Rituximab
- Kidney Disease
- Arthritis
- Sjogren's Syndrome
- Thrombocytopenia
- Alopecia
- Full Body Magnetic Resonance Imaging