Classical and Vascular Ehlers-Danlos Syndrome (EDS)
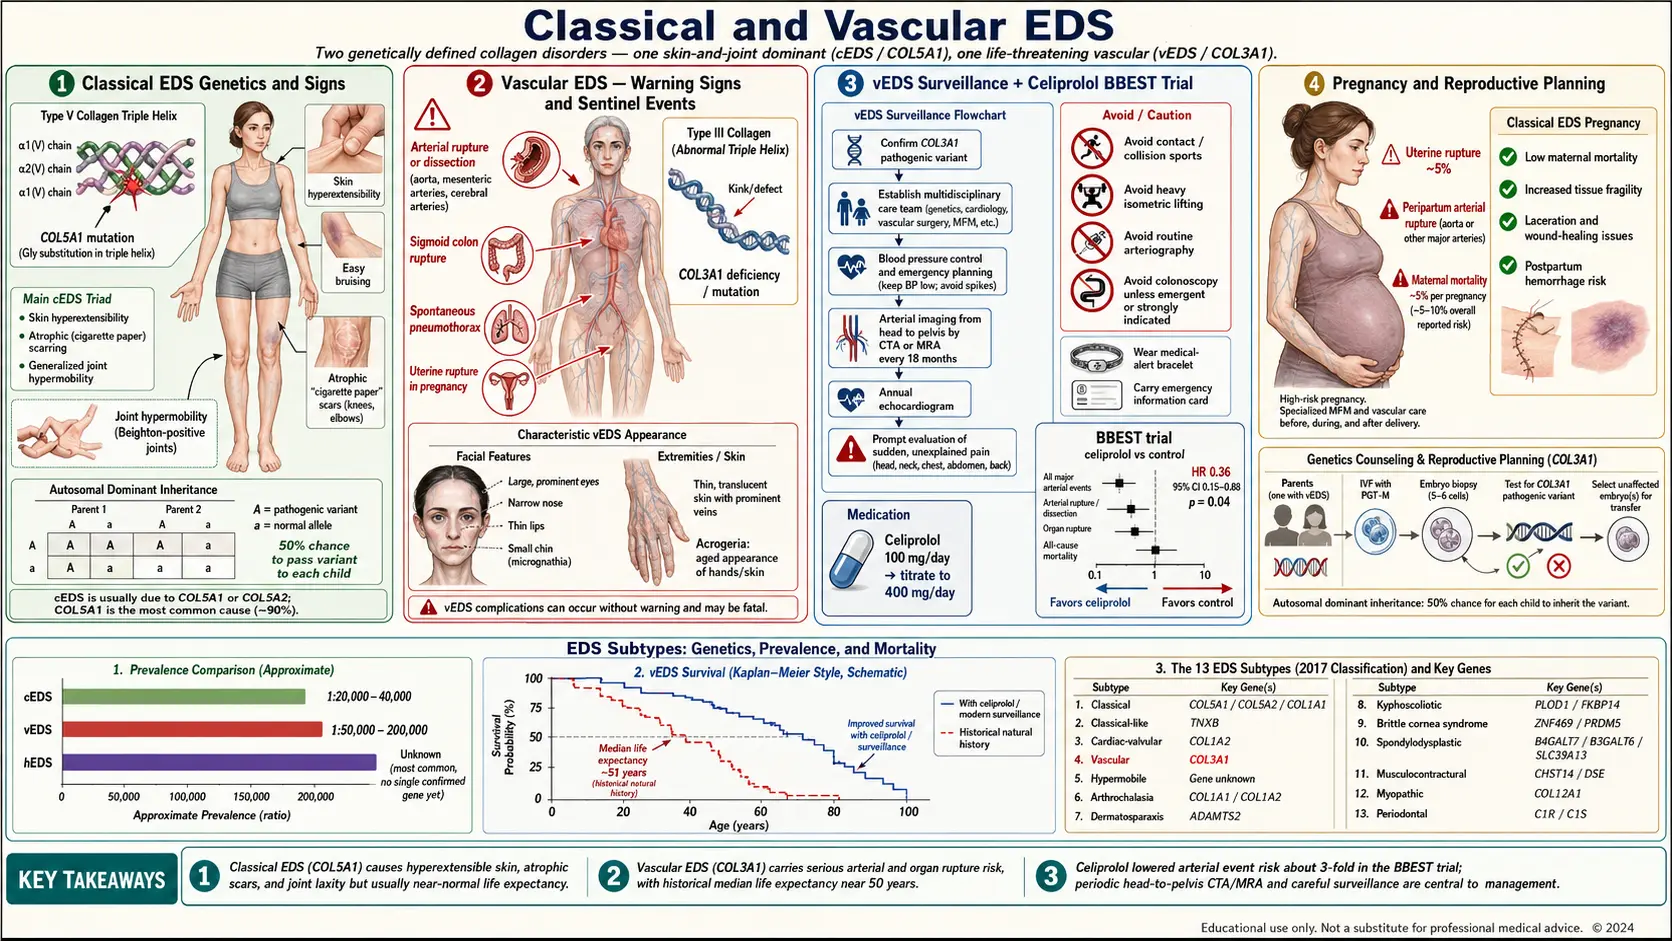
Table of Contents
- Why Classical and Vascular Ehlers-Danlos Syndrome Are Grouped Here
- Classical Ehlers-Danlos Syndrome — Genetics and How Common
- Classical Ehlers-Danlos Syndrome — What It Looks and Feels Like
- Classical Ehlers-Danlos Syndrome — The 2017 Diagnostic Criteria
- Classical Ehlers-Danlos Syndrome — Day-to-Day Management
- Vascular Ehlers-Danlos Syndrome — Genetics and How Common
- Vascular Ehlers-Danlos Syndrome — The Warning Signs
- Vascular Ehlers-Danlos Syndrome — Sentinel Events and Life Expectancy
- Vascular Ehlers-Danlos Syndrome — Urgent Workup and Surveillance
- Vascular Ehlers-Danlos Syndrome — Celiprolol and the BBEST Trial
- Vascular Ehlers-Danlos Syndrome — Lifestyle, Surgery, Emergency Prep
- Vascular Ehlers-Danlos Syndrome and Pregnancy
- Other Rarer Ehlers-Danlos Syndrome Subtypes in Brief
- Genetic Counseling and Reproductive Planning
- Key Research Papers
- Connections
- Featured Videos
Why Classical and Vascular Ehlers-Danlos Syndrome Are Grouped Here
Of the thirteen subtypes recognized in the 2017 international Ehlers-Danlos syndrome (EDS) classification, classical Ehlers-Danlos syndrome (cEDS) and vascular Ehlers-Danlos syndrome (vEDS) are the two that almost every clinician has heard of, and the two where a specific collagen gene mutation can be confirmed in a blood test. They also sit at opposite ends of the risk spectrum. Classical Ehlers-Danlos syndrome is the "textbook" connective-tissue disorder — stretchy skin, wide scars, wobbly joints — and while it complicates life, it rarely shortens it. Vascular Ehlers-Danlos syndrome is the form in which an artery or the bowel can tear suddenly, sometimes fatally, with little warning. Understanding which one is on the table — or whether a third, less alarming subtype fits better — changes everything about surveillance, pregnancy planning, emergency care, and how much a family has reason to worry.
This article walks through both in patient-friendly language, explains how they differ from hypermobile Ehlers-Danlos syndrome (the form most Ehlers-Danlos syndrome patients have), and gives a brief map of the other rarer subtypes so you know where your diagnosis fits on the larger landscape.
Classical Ehlers-Danlos Syndrome — Genetics and How Common
Classical Ehlers-Danlos syndrome is caused in more than 90% of cases by a mutation in COL5A1 or COL5A2, the two genes that code for type V collagen. Type V is a minor collagen by volume but a major regulator: it acts like a quality-control supervisor for type I collagen fibril assembly in skin, tendon, and blood vessel walls. Lose half the working copies of COL5A1 (the usual mechanism — haploinsufficiency) and the collagen bundles in your skin end up disorganized, too large, and mechanically weak.
Inheritance is autosomal dominant. One copy of the mutation is enough to cause disease, each child of an affected parent has a 50% chance of inheriting it, and men and women are affected equally. A small minority of cases (a few percent) carry a specific mutation in COL1A1 at position c.934C>T (p.Arg312Cys) that produces a classical-EDS-like phenotype, sometimes with extra vascular risk.
Estimated prevalence is roughly 1 in 20,000 to 1 in 50,000. That puts it well ahead of vascular Ehlers-Danlos syndrome for frequency but well behind hypermobile Ehlers-Danlos syndrome, which is not rare at all and may affect 1 in 500 to 1 in 5,000 depending on how it is counted.
Classical Ehlers-Danlos Syndrome — What It Looks and Feels Like
The three findings that define classical Ehlers-Danlos syndrome in the clinic are skin hyperextensibility, atrophic scarring, and generalized joint hypermobility. Each deserves a closer look.
Skin hyperextensibility. This is tested by the pinch-and-pull maneuver: a clinician grabs a fold of skin on the volar forearm (palm side) away from joints and lifts it. Classical-EDS skin stretches dramatically — typically more than 1.5 cm — and then snaps back smartly when released. It does not hang loose like cutis laxa; it recoils. The skin also feels distinctly soft and doughy, a texture most patients and their parents recognize without prompting.
Atrophic "cigarette-paper" scars. When classical-EDS skin is cut, punctured, or scraped, it heals with a wide, thin, papery scar that often darkens over time and appears to float slightly below the surrounding skin. Knees, shins, elbows, chin, and forehead are the classic sites because these are the places children fall and adults bang into things. By adulthood many patients have dozens of these scars. They are the single most specific sign for the subtype.
Generalized joint hypermobility. Measured by the Beighton score (a 9-point examination of thumb-to-forearm, fifth-finger extension, elbow hyperextension, knee hyperextension, and palms-to-floor). Most classical-EDS patients score 5 or higher in childhood, though flexibility tends to decrease with age.
Other common findings: easy bruising disproportionate to trauma, molluscoid pseudotumors (small fleshy lumps that form at pressure points like the heels and over scars), spheroid subcutaneous masses (pea-sized mobile lumps you can roll under the skin, often on shins and forearms — these are calcified fat cysts), poor wound healing, and a tendency toward hernias, rectal prolapse in childhood, and cervical insufficiency in pregnancy.
Classical Ehlers-Danlos Syndrome — The 2017 Diagnostic Criteria
The international consortium led by Fransiska Malfait published updated criteria in 2017 (American Journal of Medical Genetics, DOI below). For classical Ehlers-Danlos syndrome they define:
Major criteria (both must be present):
- Skin hyperextensibility and atrophic scarring
- Generalized joint hypermobility (Beighton score ≥ 5 in adults, ≥ 6 in children and adolescents, or a history of it)
Minor criteria (contribute to the clinical picture):
- Easy bruising
- Soft, doughy skin
- Skin fragility (or traumatic splitting)
- Molluscoid pseudotumors
- Subcutaneous spheroids
- Hernias
- Epicanthic folds
- Complications of joint hypermobility (sprains, subluxations, pes planus)
- Family history of a first-degree relative meeting criteria
A clinical diagnosis requires both major criteria plus at least three minor criteria. A definitive diagnosis requires genetic confirmation — a pathogenic variant in COL5A1, COL5A2, or (rarely) the specific COL1A1 Arg312Cys substitution. Modern panels run all three for a few hundred dollars and are covered by most insurance when clinical criteria are met.
Classical Ehlers-Danlos Syndrome — Day-to-Day Management
There is no disease-modifying drug for classical Ehlers-Danlos syndrome. Management is about protecting tissue that does not heal well and screening for the small but real complications.
Wound care. Cuts in classical-EDS skin heal poorly. Wound-care measures described for classical Ehlers-Danlos syndrome include:
- Longer suture retention — typically twice as long as standard (14 days on the face instead of 5–7; 21 days on the trunk instead of 10–14).
- Double-layer closure when possible — a deep absorbable suture layer plus a surface layer takes tension off the skin edge.
- Wound reinforcement with adhesive strips (Steri-Strips) for weeks after sutures come out.
- Longer splinting of ligament and tendon injuries — typical healing times are about 50% longer than textbook.
Physical therapy and joint protection. A physical therapist who knows connective-tissue disease can design a low-impact strengthening program that stabilizes joints without stretching already-lax ligaments. Isometric work, closed-chain exercises, bracing of the most unstable joints (wrists, ankles, patellae), and swimming are cornerstones. Contact sports and heavy weightlifting are generally discouraged in adolescence, though this is individualized.
Cardiac screening. Classical Ehlers-Danlos syndrome carries a small but measurable risk of aortic root dilation — lower than vascular Ehlers-Danlos syndrome but not zero. Most specialists recommend a baseline echocardiogram at diagnosis and repeat imaging every 3–5 years if the root is normal, more often if it is enlarged. Mitral valve prolapse is also more common than in the general population.
Dental and oral care. Gingival fragility is common; soft-bristle brushes, careful flossing, and alerting dentists before cleanings (which can cause bruising) reduce trouble.
Life expectancy. Normal. Classical Ehlers-Danlos syndrome is a quality-of-life disease, not a life-shortening one.
Vascular Ehlers-Danlos Syndrome — Genetics and How Common
Vascular Ehlers-Danlos syndrome is caused in more than 95% of confirmed cases by a mutation in COL3A1, the gene for type III collagen. Type III is the collagen that reinforces the walls of medium and large arteries, the bowel, and the uterus — precisely the tissues that rupture in this disease. A small number of cases are caused by rare variants in COL1A1 or in the gene for type I collagen processing enzymes.
Inheritance is again autosomal dominant, though roughly half of cases are de novo — the affected person is the first in their family, with no parental history. Estimated prevalence is 1 in 50,000 to 1 in 200,000, though many experts suspect it is under-diagnosed because sudden deaths from unexplained dissection or bowel rupture are often not worked up genetically.
Vascular Ehlers-Danlos Syndrome — The Warning Signs
Vascular Ehlers-Danlos syndrome does not look like classical Ehlers-Danlos syndrome. The skin is not especially hyperextensible; instead it is thin and translucent, so much so that a web of veins is clearly visible on the chest, breasts, and abdomen in adults who are not thin. The face has a distinctive appearance called acrogeria: a thin narrow face, prominent cheekbones, thin nose, thin lips, hollowed cheeks, large-looking eyes that appear to protrude, and earlobes that are small or completely absent. Hands and feet look older than the person's age.
Joint hypermobility, if present, is usually limited to the small joints of the fingers and toes, not the large-joint generalized hypermobility of classical or hypermobile Ehlers-Danlos syndrome. Many vEDS patients do not feel unusually flexible at all.
The feature that is usually dramatic is bruising. Spontaneous or very-light-trauma bruises — sometimes large, sometimes appearing in sheets — are often the first thing a parent or partner notices. Children with vEDS are sometimes investigated for child abuse or clotting disorders before the real diagnosis is made. Varicose veins in young people, premature aging of the hands, and a history of pneumothorax (collapsed lung) also show up repeatedly.
Vascular Ehlers-Danlos Syndrome — Sentinel Events and Life Expectancy
The reason vEDS is feared is that the first serious presentation is often a sentinel event — a sudden, severe, sometimes fatal rupture of an artery or hollow organ. The three classic events are:
- Arterial dissection or rupture. Any medium or large artery is at risk. Aorta, carotid, vertebral, renal, mesenteric, iliac, splenic — all have been reported. Presentation is typically sudden severe pain (chest, abdomen, flank, or neck), stroke-like symptoms, or collapse.
- Bowel rupture. The sigmoid colon is the classic site. Presents as sudden severe abdominal pain and peritonitis in a young person with no prior gastrointestinal (GI) history.
- Uterine rupture during pregnancy or delivery — discussed below.
The best-known figures come from two natural-history studies by Melanie Pepin, Peter Byers and colleagues at the University of Washington. The 2000 study in the New England Journal of Medicine (220 index patients and 199 affected relatives, DOI below) found:
- Complications were rare in childhood; 25% of index patients had a first complication by age 20.
- More than 80% had had at least one complication by age 40 (artery, bowel or uterus; bowel rupture made up about a quarter of complications but rarely led to death).
- Median survival of the whole group: 48 years, with most deaths from arterial rupture.
The larger 2014 study in Genetics in Medicine (DOI below) reviewed the records of 1,231 people (630 index cases and 601 relatives) with COL3A1 mutations and found a median survival of 51 years, lower in men than in women and dependent on the type of COL3A1 mutation.
These are grim numbers. A 2019 study from a French national referral center followed 144 people with confirmed vEDS for a median of 5.3 years (2000–2017). By the end, 90.3% were taking celiprolol alone or with other drugs; more than two-thirds had no new clinical event, even though 51% already had arterial events or artery lesions when diagnosed. Overall survival was 71.6% and depended on the type of COL3A1 variant, age at diagnosis and medical treatment; people taking celiprolol survived longer than others, with the best protection at 400 mg a day. This was an observational study, not a randomized trial.
Vascular Ehlers-Danlos Syndrome — Urgent Workup and Surveillance
If vEDS is suspected clinically, the workup moves fast. A typical protocol:
- Genetic testing. A COL3A1 sequencing panel (usually a broader connective-tissue panel that also covers COL1A1, COL1A2, COL5A1, COL5A2, and the aortopathy genes) is ordered right away. Results typically take 2–4 weeks.
- Baseline whole-body magnetic resonance angiography (MRA) from the circle of Willis through the iliac arteries. Many centers use MRA rather than computed tomography (CT) angiography because it avoids radiation and iodinated contrast in people who need repeated imaging; the 2025 irbesartan trial (below) used scheduled head-to-pelvis CT angiography or duplex ultrasound. Imaging is typically repeated every 12–24 months for life, or sooner if symptoms change.
- Transthoracic echocardiogram at baseline to measure aortic root diameter and check valve function, typically repeated every one to two years.
- Baseline head and neck MRA to screen for intracranial aneurysms.
- Referral to a vascular surgeon who has treated vEDS before — emergency surgery on vEDS tissue is technically very different from standard vascular surgery and benefits enormously from experience.
Vascular Ehlers-Danlos Syndrome — Celiprolol and the BBEST Trial
For decades there was no drug proven to change vEDS outcomes. That changed with the BBEST trial (Beta-Blockers in Ehlers-Danlos Syndrome Treatment), published by Ong, Boutouyrie, and colleagues in The Lancet in 2010. The open trial, with blinded assessment of events, randomized 53 patients with clinically diagnosed vEDS (33 with confirmed COL3A1 mutations) to celiprolol — a cardioselective beta-blocker with partial beta-2 agonist activity — versus no treatment. Treatment was planned for five years; mean follow-up was 47 months (about four years) when the trial was stopped early.
Arterial events (dissection or rupture) occurred in 5 of 25 patients (20%) on celiprolol and 14 of 28 (50%) untreated controls (hazard ratio 0.36), and the trial was stopped early for treatment benefit. Celiprolol was the first drug tested in a randomized trial in vEDS.
A second trial followed in 2025. In a French randomized placebo-controlled trial, 57 adults with vEDS who were already taking celiprolol received irbesartan (an angiotensin II receptor blocker, 150 mg a day rising to 300 mg a day) or placebo for 2 years. Arterial events or new or worsening artery lesions on scheduled scans occurred in 8 of 29 people (27.6%) on irbesartan and 15 of 28 (53.6%) on placebo (hazard ratio 0.42). Eleven episodes of low blood pressure linked to irbesartan were recorded, leading to a lower dose in 4 people. The U.S. irbesartan label carries a boxed warning on fetal toxicity: the drug is to be stopped as soon as possible when pregnancy is detected, because drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus.
In the BBEST trial, celiprolol was given twice daily, starting at 100 mg a day and raised in 100 mg steps every 6 months to a maximum of 400 mg a day; one patient had severe fatigue after starting 100 mg and two had mild fatigue with dose increases. The goal is not aggressive blood-pressure lowering but a steady reduction in arterial wall stress. Celiprolol is not sold in the United States and has to be imported — a frustrating logistical fact that vEDS clinics help patients navigate. Alternative beta-blockers (atenolol, metoprolol, bisoprolol) are sometimes substituted when celiprolol is unobtainable, though the evidence for those is weaker. Blood-pressure control generally, avoiding hypertensive spikes, is a stated aim of vEDS care — see the hypertension page for general blood pressure (BP) management strategies.
Vascular Ehlers-Danlos Syndrome — Lifestyle, Surgery, Emergency Prep
Lifestyle modifications matter because tissue fragility compounds every risk.
- Contact sports. vEDS centers generally advise against football, rugby, hockey, boxing, martial arts, and most collision activities. Swimming, walking, light cycling, yoga (without extreme ranges), and low-weight strength training are generally described as safe.
- Heavy lifting and Valsalva straining. Anything that spikes intra-abdominal or intra-thoracic pressure (heavy deadlifts, aggressive weight training, straining on the toilet) is discouraged in vEDS care. Constipation is commonly managed with osmotic laxatives and fiber to limit straining.
- Nonsteroidal anti-inflammatory drugs and bleeding. Ibuprofen, naproxen, aspirin, and other nonsteroidal anti-inflammatory drugs increase bleeding risk into already-fragile tissue, which is why acetaminophen is the usual default pain reliever in vEDS care.
- Arterial catheterization and dissection risk. Elective coronary angiography, arterial lines, and cardiac catheterization carry real dissection risk, so vEDS centers prefer non-invasive imaging and keep catheterization for cases where it is genuinely necessary, done at a center experienced with vEDS.
- Medical ID bracelet and wallet card. vEDS centers describe carrying clear documentation: the diagnosis, COL3A1 mutation, medications (celiprolol), and a one-line instruction to emergency teams: "Avoid arterial catheterization; tissue is fragile; call genetics/vascular surgery."
- Surgery caution. Any surgery on vEDS tissue — whether elective or emergent — is technically harder. Sutures tear through, vessels do not hold clips well, and hemostasis is harder to achieve. Surgeons who know this operate more slowly, use pledgeted sutures, avoid aggressive retraction, and plan for longer recoveries.
Vascular Ehlers-Danlos Syndrome and Pregnancy
Pregnancy carries serious added risk for a woman with vEDS. A 2014 study of vEDS family trees counted pregnancy-related deaths in 30 of 565 deliveries (5.3%). In interviews with 39 women, 46% of deliveries were uncomplicated, and life-threatening complications occurred in 14.5% of deliveries, including arterial dissection or rupture (9.2%) and uterine rupture (2.6%). The same study found no difference in survival curves between women with vEDS who had given birth and those who had not. The earlier 2000 study counted deaths from pregnancy complications in 12 of the 81 women who became pregnant. Modern care at experienced centers brings this down substantially but never to baseline.
Decisions about pregnancy in vEDS are usually made with a maternal-fetal-medicine team, a vascular surgeon, a geneticist, and the patient's partner; the 2014 study's authors call for shared decision-making when pregnancy is contemplated, and found the data insufficient to say whether the mode or timing of delivery changes the risk. When pregnancy is undertaken, delivery is typically planned at a tertiary center with vascular surgery on standby, and the mode of delivery (scheduled cesarean versus vaginal) is individualized. Preimplantation genetic diagnosis is available for COL3A1 (see counseling section below). See also the Pregnancy and Ehlers-Danlos syndrome article for the broader Ehlers-Danlos syndrome-and-pregnancy picture.
Other Rarer Ehlers-Danlos Syndrome Subtypes in Brief
The 2017 classification recognizes thirteen Ehlers-Danlos syndrome subtypes. Beyond hypermobile, classical, and vascular, the others are rare but worth naming so patients know whether to seek out a specialist:
- Kyphoscoliotic Ehlers-Danlos syndrome — PLOD1 or FKBP14 mutations; severe scoliosis from birth, muscle hypotonia, globe fragility.
- Arthrochalasia Ehlers-Danlos syndrome — COL1A1 or COL1A2; congenital bilateral hip dislocation and extreme joint laxity.
- Dermatosparaxis Ehlers-Danlos syndrome — ADAMTS2; extremely fragile, saggy, redundant skin.
- Classical-like Ehlers-Danlos syndrome — TNXB (tenascin-X deficiency); looks like classical Ehlers-Danlos syndrome but with normal scars.
- Spondylodysplastic Ehlers-Danlos syndrome — short stature, bowed limbs.
- Musculocontractural Ehlers-Danlos syndrome — CHST14 or DSE; contractures, distinctive face.
- Myopathic Ehlers-Danlos syndrome — COL12A1; muscle weakness plus hypermobility.
- Cardiac-valvular Ehlers-Danlos syndrome — COL1A2; progressive severe valve disease.
- Periodontal Ehlers-Danlos syndrome — C1R or C1S; early aggressive periodontal disease.
- Brittle cornea syndrome — sometimes grouped with Ehlers-Danlos syndrome; ZNF469 or PRDM5.
If any of these labels fit your clinical picture better than hypermobile Ehlers-Danlos syndrome, a broader sequencing panel can test for them. Many of them have specific surveillance recommendations that are missed if the diagnosis is left at "Ehlers-Danlos syndrome, unspecified."
Genetic Counseling and Reproductive Planning
Any patient with confirmed or strongly suspected classical or vascular Ehlers-Danlos syndrome benefits from at least one session with a board-certified genetic counselor. The counselor can:
- Explain inheritance risk to children (50% for both cEDS and vEDS in dominant forms).
- Arrange cascade testing for at-risk relatives — especially important in vEDS, where a diagnosis can save a sibling or parent's life.
- Discuss preimplantation genetic diagnosis (PGD), available for COL3A1 and other single-gene Ehlers-Danlos syndrome mutations. PGD involves in vitro fertilization with embryo biopsy and selection of embryos that do not carry the mutation. Costs range from $15,000 to $30,000 per cycle and are sometimes partially covered by insurance when a severe dominant condition is involved.
- Discuss prenatal diagnosis (chorionic villus sampling at 10–13 weeks, amniocentesis at 15–20 weeks) for families who conceive naturally.
- Address the emotional side — grief, guilt, and the difficulty of telling family members about a dominant condition.
For vEDS, early diagnosis of relatives is not optional in the same way a hypermobile Ehlers-Danlos syndrome diagnosis sometimes feels optional. A 25-year-old second cousin who turns out to carry COL3A1 can be started on celiprolol and surveillance imaging before the first dissection — the kind of intervention that changes the rest of a life.
Key Research Papers
- Malfait F, Francomano C, Byers P, et al. The 2017 international classification of the Ehlers-Danlos syndromes. Am J Med Genet C Semin Med Genet. 2017. — doi:10.1002/ajmg.c.31552
- Bowen JM, Sobey GJ, Burrows NP, Colombi M, Lavallee ME, Malfait F, Francomano CA. Ehlers-Danlos syndrome, classical type. Am J Med Genet C Semin Med Genet. 2017;175(1):27-39. — doi:10.1002/ajmg.c.31548
- Pepin M, Schwarze U, Superti-Furga A, Byers PH. Clinical and genetic features of Ehlers-Danlos syndrome type IV, the vascular type. N Engl J Med. 2000;342(10):673-80. — doi:10.1056/NEJM200003093421001
- Pepin MG, Schwarze U, Rice KM, et al. Survival is affected by mutation type and molecular mechanism in vascular Ehlers-Danlos syndrome (EDS type IV). Genet Med. 2014. — doi:10.1038/gim.2014.72
- Murray ML, Pepin M, Peterson S, Byers PH. Pregnancy-related deaths and complications in women with vascular Ehlers-Danlos syndrome. Genet Med. 2014;16(12):874-80. — doi:10.1038/gim.2014.53
- Ong KT, Perdu J, De Backer J, et al. Effect of celiprolol on prevention of cardiovascular events in vascular Ehlers-Danlos syndrome: a prospective randomised, open, blinded-endpoints trial (BBEST). Lancet. 2010. — doi:10.1016/S0140-6736(10)60960-9
- Frank M, Adham S, Seigle S, et al. Vascular Ehlers-Danlos Syndrome: Long-Term Observational Study. J Am Coll Cardiol. 2019;73(15):1948-1957. — doi:10.1016/j.jacc.2019.01.058
- Jeunemaitre X, Mousseaux E, Frank M, et al. Efficacy of Irbesartan in Celiprolol-Treated Patients With Vascular Ehlers-Danlos Syndrome. Circulation. 2025;151(10):686-695. — doi:10.1161/CIRCULATIONAHA.124.072849
- U.S. National Library of Medicine. DailyMed: irbesartan tablets prescribing information, boxed warning “Fetal Toxicity”. — DailyMed irbesartan label
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on classical and vascular Ehlers-Danlos syndrome:
- PubMed: Classical EDS and COL5A1/COL5A2 mutations
- PubMed: Vascular EDS and COL3A1 mutations
- PubMed: Celiprolol in vascular EDS
- PubMed: Aortic root dilation in EDS
- PubMed: Vascular EDS and pregnancy outcomes
- PubMed: Wound healing and surgical considerations in EDS
- PubMed: 2017 international EDS classification
- PubMed: Preimplantation genetic diagnosis for COL3A1
Connections
- Rheumatology
- Ehlers-Danlos Syndrome
- Hypermobile Ehlers-Danlos Syndrome and 2017 Diagnostic Criteria
- Craniocervical Instability and AAI
- Gastrointestinal Involvement in Ehlers-Danlos Syndrome
- Postural Orthostatic Tachycardia Syndrome, Mast Cell Activation Syndrome and the Ehlers-Danlos Syndrome Triad
- Pain Management in hEDS
- Pediatric Ehlers-Danlos Syndrome and Transition of Care
- Physical Therapy and Joint Protection
- Pregnancy and Ehlers-Danlos Syndrome
- Hypertension
- Osteoporosis
- Postural Orthostatic Tachycardia Syndrome
- Postural Orthostatic Tachycardia Syndrome Subtypes
- Mast Cell Activation Syndrome
- Collagen