Cryptogenic Organizing Pneumonia
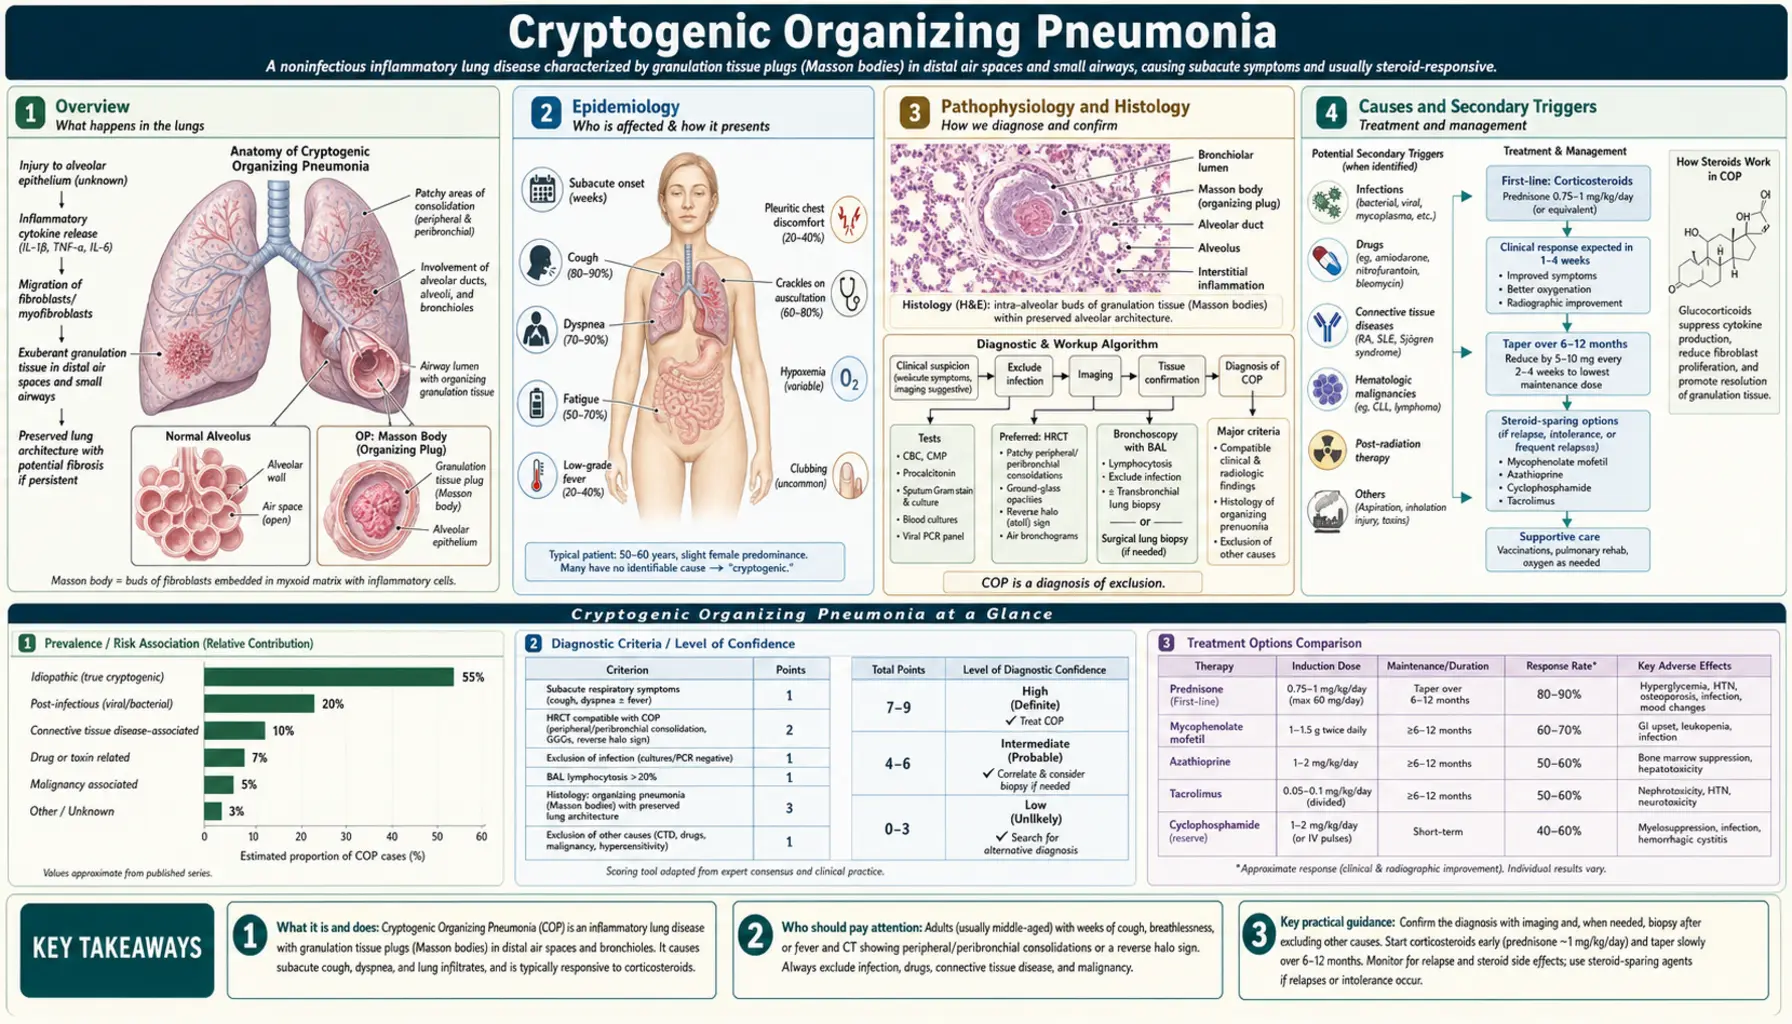
- Overview
- Epidemiology
- Pathophysiology and Histology
- Causes and Secondary Triggers
- Clinical Presentation
- Imaging Findings
- Diagnosis
- Treatment
- Prognosis and Recurrence
- Recent Research
- Key Research Papers
- Connections
- Featured Videos
1. Overview
Cryptogenic organizing pneumonia (COP) is a distinctive clinicopathological syndrome defined by a specific histological pattern — organizing pneumonia (OP) — in the absence of an identifiable cause. The term "cryptogenic" signals idiopathic origin; the same histological pattern arising from an identifiable cause is called "secondary organizing pneumonia." Davison and colleagues described 8 such patients in 1983 and suggested the name "cryptogenic organizing pneumonitis." COP was also long termed bronchiolitis obliterans organizing pneumonia (BOOP) — coined by Epler and colleagues in 1985, with King and Mortenson describing the North American experience in 1992 — but this name was abandoned because the word "bronchiolitis obliterans" implies fixed airway obstruction (as in constrictive bronchiolitis), when in fact COP causes restriction, not obstruction, and is reversible.
COP is part of the idiopathic interstitial pneumonias (IIPs) classification of the American Thoracic Society and European Respiratory Society (2013 update), where it holds a favorable position as the most steroid-responsive and best-prognosis IIP. The hallmark is Masson bodies — intraluminal buds of granulation tissue (fibroblasts embedded in myxoid stroma) filling alveolar ducts and alveoli — which resolve completely with corticosteroids without leaving fibrosis.
2. Epidemiology
COP is a rare condition. Estimated incidence is 1–3 cases per 100,000 per year in population-based studies, and it is likely underdiagnosed. A nationwide 20-year study in Iceland found 1.10 per 100,000 per year for COP and 1.97 for all organizing pneumonia. COP affects adults predominantly in the fifth and sixth decades of life (mean age 55–60 at diagnosis; the Icelandic mean was 67 and a two-hospital series reported 60.46), without strong sex predominance, though some series report a slight female predominance. Smokers are described as not disproportionately affected (unlike many other interstitial lung diseases) — COP occurs in both smokers and non-smokers. In the Icelandic series, 79 of 104 patients with COP or secondary organizing pneumonia were smokers; that report gives no comparison population.
There is no known geographic, occupational, or genetic predisposition for the cryptogenic form. Secondary organizing pneumonia may follow specific exposures (see Section 4). Population data improved after the 2002 American Thoracic Society and European Respiratory Society reclassification renamed BOOP to COP, clarifying the epidemiological picture by establishing consistent diagnostic terminology across centers worldwide.
3. Pathophysiology and Histology
The pathological hallmark of COP is the organizing pneumonia (OP) pattern — specific and reproducible on surgical lung biopsy. Understanding the histology is essential because the histological pattern determines both diagnosis and treatment choice.
Masson Bodies
Plugs of granulation tissue composed of young fibroblasts, myxomatous connective tissue, and inflammatory cells fill alveolar ducts, alveoli, and sometimes terminal bronchioles. These are buds — not obliterating plugs that scar — and when they resolve under corticosteroid treatment, lung architecture returns to normal. This reversibility is the critical distinction from usual interstitial pneumonia (the scarring pattern of idiopathic pulmonary fibrosis) and from constrictive bronchiolitis.
Preserved Alveolar Architecture
The alveolar walls remain intact with only mild lymphocytic infiltrate. There is no significant honeycomb change or fibroblastic foci, which are defining features of usual interstitial pneumonia and idiopathic pulmonary fibrosis. Masson bodies are distributed in a patchy, temporally uniform fashion — all lesions are at the same stage of development, unlike the temporal heterogeneity that characterizes usual interstitial pneumonia.
Inflammatory Infiltrate
Alveolar walls show mild lymphocyte and plasma cell infiltration. Intra-alveolar macrophages and foamy cells are present. Eosinophils occur in some cases. Neutrophils are uncommon; if prominent, infection is a possible alternative or contributing diagnosis. Vasculitis and necrotizing granulomas are absent — features that help distinguish COP from sarcoidosis and granulomatous infections.
Pathogenesis
COP is thought to begin with alveolar epithelial injury — from an infection, drug, toxin, or radiation — that triggers an abnormal repair response. Instead of normal epithelial regeneration, the injured alveolus is filled with a granulation tissue bud that matures incompletely and persists. Bronchoalveolar lavage (BAL) characteristically shows mixed lymphocytosis (CD8+ T cells predominantly, unlike sarcoidosis which is CD4+ dominant), eosinophilia, and foamy macrophages — reflecting alveolar inflammation without a specific pathological agent.
4. Causes and Secondary Triggers
When the OP histological pattern arises from an identifiable cause, it is classified as secondary organizing pneumonia (SOP). A thorough search for secondary causes is essential before diagnosing COP.
Infections
The most common cause of secondary OP. SARS-CoV-2 emerged as a recognized trigger post-2020, with patients developing organizing pneumonia pattern on computed tomography (CT) after acute COVID-19 infection, responsive to steroids. Other viral triggers include Influenza, respiratory syncytial virus (RSV), Adenovirus, cytomegalovirus (CMV), and Epstein-Barr virus (EBV). Bacterial causes include Mycoplasma pneumoniae (classic), Legionella, and Chlamydophila. Fungal causes include Pneumocystis jirovecii in immunocompromised patients.
Drug-Induced Organizing Pneumonia
Amiodarone is the most commonly implicated drug; amiodarone-induced OP may not fully resolve and can progress even after discontinuation due to the drug's long half-life (the FDA label gives a mean terminal half-life of 58 days, range 15 to 142 days, after a single dose, and 26 to 107 days after long-term oral therapy). Other culprit drugs include bleomycin, methotrexate, and immune checkpoint inhibitors such as pembrolizumab, nivolumab, and atezolizumab. Lung inflammation (pneumonitis) of any pattern was reported in 3.6% of patients on programmed death 1 (PD-1) drugs and 1.3% on programmed death-ligand 1 (PD-L1) drugs in a 2017 meta-analysis of lung cancer trials, and in 5% overall (3% on one drug, 10% on a combination) in a 2017 two-center series; those rates cover all pneumonitis, of which organizing pneumonia is one pattern. The clinical picture is bilateral ground glass and consolidation. Management described is holding the checkpoint inhibitor and starting corticosteroids; grade 3–4 toxicity leads to permanent discontinuation of the checkpoint inhibitor. Additional implicated agents include cyclophosphamide, nitrofurantoin, and gold therapy.
Connective Tissue Diseases
Rheumatoid arthritis is the most common connective tissue disease associated with OP pattern, occurring in approximately 10% of cases of interstitial lung disease in rheumatoid arthritis. Polymyositis and dermatomyositis — especially clinically amyopathic dermatomyositis (CADM) with anti-MDA5 antibody — are associated with rapidly progressive interstitial lung disease with an OP/nonspecific interstitial pneumonia pattern. Systemic sclerosis, Sjögren's syndrome, and mixed connective tissue disease (MCTD) are additional connective tissue disease triggers.
Radiation Pneumonitis
Organizing pneumonia can develop distal to or within the radiation field weeks to months after thoracic radiation therapy. Computed tomography shows consolidation in the radiation distribution, or sometimes a migratory or distal pattern. The condition responds well to corticosteroids.
Post-Transplant
Graft-versus-host lung disease in allogeneic stem cell transplant recipients can manifest as organizing pneumonia; prognosis in this setting is generally poor.
Idiopathic (COP)
No identifiable cause is found after thorough workup in approximately 50% of cases, yielding the diagnosis of cryptogenic organizing pneumonia.
5. Clinical Presentation
COP presents subacutely over weeks to a few months, with a typical course of 1–3 months before diagnosis. The clinical picture often mimics community-acquired pneumonia, and the failure to respond to antibiotics is a key diagnostic clue.
Prodrome and Respiratory Symptoms
Most patients describe a flu-like illness (fever, malaise, myalgia) lasting 1–3 weeks, followed by persistent dry cough and progressive dyspnea that do not respond to antibiotics. The cough is typically nonproductive. Progressive dyspnea on exertion and mild to moderate breathlessness are the dominant respiratory complaints. Pleuritic chest pain is less common. Hemoptysis is rare and raises concern for alternative diagnoses such as malignancy or vasculitis.
Constitutional Symptoms
Low-grade fever is present in 40–50% of patients — a feature that distinguishes COP from idiopathic pulmonary fibrosis where fever is absent. Fatigue, weight loss of 5–10 kg over weeks to months, and night sweats are common. The constellation of persistent cough, fever, and infiltrates not responding to antibiotics over 4–8 weeks is characteristic and is a recognized reason to consider COP urgently.
Physical Examination
Bilateral inspiratory crackles (Velcro crackles) are present in 70–75% of patients. Mild tachypnea is common. Importantly, clubbing is absent in COP — its presence is a feature of idiopathic pulmonary fibrosis, not COP — and this distinction is clinically valuable when evaluating patients with bilateral infiltrates.
Pulmonary Function
COP produces a restrictive pattern on spirometry: reduced forced vital capacity, reduced total lung capacity, and a normal or mildly reduced ratio of forced expiratory volume in 1 second to forced vital capacity. This differs fundamentally from obstructive conditions such as chronic obstructive pulmonary disease (COPD), asthma, and constrictive bronchiolitis. Diffusing capacity of the lung for carbon monoxide is reduced, reflecting alveolar filling and inflammation. Hypoxemia occurs on exertion or at rest in advanced cases.
Laboratory Findings
Elevated erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP) are common but nonspecific. Mild leukocytosis may be present. Serum lactate dehydrogenase (LDH) is mildly elevated in some patients. Antinuclear antibody (ANA) and rheumatoid factor are checked to screen for connective tissue disease-associated organizing pneumonia.
6. Imaging Findings
High-resolution CT (HRCT) of the chest is critical for diagnosis and shows characteristic patterns that, while not pathognomonic, are highly suggestive of COP in the right clinical context.
Bilateral Peripheral Consolidation
The most common pattern, present in 60–80% of cases. Patchy bilateral airspace consolidation appears in subpleural regions, predominantly in the lower lobes. A peribronchovascular distribution is often present. Ground-glass opacities surround or accompany areas of consolidation. This bilateral, lower-lobe, subpleural consolidation pattern mimics community-acquired pneumonia radiologically.
Reverse Halo Sign (Atoll Sign)
A ring of consolidation surrounding a central area of ground-glass opacity — a "hole" of ground glass inside a ring of denser consolidation. This finding is seen in approximately 19% of COP on computed tomography. Once considered fairly specific for COP, it is also reported in pulmonary infarction, fungal infection, tuberculosis, and lymphoma. When present in the appropriate clinical context, it is a helpful diagnostic clue.
Nodular Form
Multiple small nodules (5–10 mm) distributed along bronchovascular bundles; this pattern can mimic sarcoidosis or metastatic disease and may require tissue sampling to differentiate. FDG-PET/computed tomography is useful in this setting, as OP is PET-avid and can mimic malignancy.
Migratory Consolidation
One of the most characteristic and diagnostically helpful features of COP is the apparent migration of consolidative infiltrates from one region to another on serial computed tomography or chest X-ray, even without treatment. This spontaneous migratory quality is distinctive and is a recognized pointer to COP when observed.
Pleural Effusion
Present in approximately 30% of patients; typically small and bilateral. Unlike malignant effusions, COP-associated pleural effusions do not shift with gravity on decubitus films. Pleural involvement is less marked than in acute eosinophilic pneumonia (AEP).
What COP Does Not Look Like
COP does not produce significant honeycomb change (honeycomb remodeling signals fibrosis and idiopathic pulmonary fibrosis, not COP) and does not typically cause bilateral hilar lymphadenopathy that predominates (which suggests sarcoidosis). The absence of these features helps narrow the differential diagnosis toward COP.
7. Diagnosis
Diagnosis requires a compatible clinical-radiological picture, exclusion of infection and malignancy, and histological confirmation when transbronchial biopsy is nondiagnostic or when presentation is atypical.
Bronchoscopy with BAL
BAL shows lymphocytosis (typically 20–40% lymphocytes, with a decreased or normal CD4/CD8 ratio reflecting CD8 predominance); mild eosinophilia and neutrophilia may be present; foamy macrophages are present. BAL lymphocytosis supports an inflammatory etiology and is consistent with COP but is not specific. Cultures and special stains are essential to exclude infection before attributing findings to COP.
Transbronchial Lung Biopsy
Shows the OP pattern (Masson bodies) in approximately 70% of COP cases, yielding enough tissue to demonstrate the characteristic buds of granulation tissue. This is often sufficient when the clinical-CT picture is strongly consistent with COP. Risks include pneumothorax (~2%) and bleeding. Diagnostic yield is lower than surgical biopsy, and transbronchial biopsy may not provide sufficient tissue to distinguish COP from other OP-pattern interstitial lung diseases with confidence in atypical presentations.
Surgical Lung Biopsy (Gold Standard)
Video-assisted thoracoscopic surgery (VATS) biopsy from 2–3 lobes yields definitive diagnosis. Indicated when transbronchial biopsy is nondiagnostic, when clinical presentation is atypical, when computed tomography shows features suggesting an alternative diagnosis (usual interstitial pneumonia pattern, diffuse alveolar damage), or when computed tomography shows a predominantly nodular or peribronchovascular pattern without classic peripheral consolidation. Histology reveals Masson bodies in alveolar ducts, temporal uniformity, preserved alveolar architecture, and absence of vasculitis or necrotizing granulomas.
Ruling Out Secondary Causes
A systematic search for secondary OP is essential before diagnosing COP. This includes a full medication history (amiodarone, bleomycin, methotrexate, checkpoint inhibitors — with dates and doses); a comprehensive connective tissue disease serology panel (antinuclear antibody, anti-dsDNA, rheumatoid factor, anti-CCP, SSA/SSB, Scl-70, Jo-1, MDA5, PL-7, PL-12, Mi-2 for myositis antibodies); thorough infection workup (BAL cultures, serology for atypical pathogens, silver stain for Pneumocystis jirovecii); radiation history; and stem cell transplant history.
FDG-PET/Computed Tomography
Useful in nodular COP to distinguish from malignancy. OP is FDG-avid — PET-positive — mimicking lung cancer or lymphoma. A PET-positive consolidative or nodular lesion that resolves with a short steroid trial without biopsy is occasionally acceptable in elderly or frail patients with high surgical risk, though biopsy remains preferred when feasible.
8. Treatment
Corticosteroids are the cornerstone of treatment for COP, and the response is among the most dramatic of any interstitial lung disease.
Corticosteroids
COP responds to corticosteroids dramatically — one of the best responses among all idiopathic interstitial pneumonias. The typical regimen is prednisone 1 mg/kg/day (40–60 mg/day) for 4–8 weeks, followed by clinical and radiological reassessment, then a slow taper over 6–12 months total. A commonly used schedule is: 60 mg for 4 weeks, 40 mg for 4 weeks, 30 mg for 4 weeks, 20 mg for 4 weeks, 10 mg for 4 weeks, 5 mg for 4 weeks, then discontinue. Radiological clearing is typically evident by 4–6 weeks; functional improvement follows closely.
Speed of Response
Most patients notice dramatic symptom improvement within 2–4 weeks of starting prednisone. Fever resolves within days. Radiological improvement begins at 2–4 weeks; complete or near-complete radiological resolution typically occurs in 3–6 months. This speed of response is itself diagnostically confirming — an equally dramatic computed tomography response within weeks essentially excludes idiopathic pulmonary fibrosis, which does not respond to steroids.
Recurrence
30–50% of patients are commonly described as relapsing during or after steroid taper. Published series vary: one or more relapses in 58% of 48 patients in a 2000 series (68% of them still on treatment at first relapse), 37.8% at 1 year among 61 patients with COP or secondary organizing pneumonia in a 2011 series, and 20.9% of 268 patients in a 2026 Chinese cohort (median time to relapse 12 months). Importantly, relapse is not a sign of treatment failure or progressive disease — it indicates steroid-dependent disease. In the 2000 series relapses did not adversely affect outcome, delayed treatment raised the risk of relapse, and steroid side effects occurred in 25% of patients. Prednisone is usually reinitiated at the dose that previously controlled disease, and a slower taper is sometimes used on the second course. Most patients achieve long-term remission without permanent disability, even after multiple relapses.
Steroid-Sparing Agents
For recurrent, steroid-dependent, or steroid-intolerant COP, steroid-sparing immunosuppressives are used based on case series data (no randomized controlled trial (RCT) evidence in COP specifically). Azathioprine (1–3 mg/kg/day; complete blood count (CBC) is monitored for myelosuppression; thiopurine methyltransferase enzyme activity is checked before starting) is the most commonly used agent. Mycophenolate mofetil (1.5–3 g/day) and tacrolimus are alternatives. Choice is guided by individual patient comorbidities, tolerability, and prior treatment response.
Macrolide Antibiotics
A 2005 case series reports 3 patients with cryptogenic organizing pneumonia and 3 with radiation-related organizing pneumonia who responded to macrolide therapy. The authors attribute the response to anti-inflammatory effects of macrolides. This evidence is at case level only.
Checkpoint Inhibitor-Associated Organizing Pneumonia
Standard practice is that the checkpoint inhibitor is withheld upon diagnosis and high-dose prednisone is started at 1–2 mg/kg/day; most patients respond within 2–4 weeks. Grade 3 (requiring hospitalization and supplemental oxygen) or grade 4 (life-threatening) toxicity leads to permanent discontinuation of the checkpoint inhibitor. For steroid-refractory cases, infliximab or mycophenolate mofetil may be added. Rechallenge with a checkpoint inhibitor after grade 3–4 disease carries a high risk of recurrence, and oncologists generally do not restart the drug.
Secondary COP Treatment
Treatment of underlying cause plus corticosteroids is the dual approach for secondary organizing pneumonia. For connective tissue disease-associated OP, the approach is disease-modifying immunosuppression for the underlying disease plus corticosteroids for active OP. For organizing pneumonia with interstitial lung disease in rheumatoid arthritis specifically, rituximab may benefit both the rheumatoid arthritis and the lung disease. For amiodarone-induced OP, amiodarone is discontinued when clinically possible (the FDA label gives a half-life range of 15 to 142 days, with serum levels persisting for months), and corticosteroids are added.
Prophylaxis During Corticosteroid Therapy
Usual practice for people on prolonged corticosteroids includes calcium and vitamin D supplementation. A bisphosphonate (alendronate or risedronate) is commonly used for DEXA T-score below −2.5 or for anticipated treatment duration greater than 3 months. Prevention of Pneumocystis jirovecii pneumonia with trimethoprim-sulfamethoxazole DS three times weekly is commonly used for patients on prednisone greater than 20 mg/day for more than 4 weeks.
9. Prognosis and Recurrence
COP has an excellent prognosis compared with most other idiopathic interstitial pneumonias. Overall 5-year mortality from COP itself is low — estimated below 5% for cryptogenic COP in most published series. Most patients achieve complete or near-complete recovery of lung function. Pulmonary fibrosis is rare in COP, in stark contrast to idiopathic pulmonary fibrosis where progressive fibrosis is invariable and ultimately fatal.
A 2026 Chinese cohort of 268 patients reported survival from all causes of 99.6% at 1 year, 97.7% at 3 years, 94.5% at 5 years and 81.7% at 10 years. Of the 56 patients who relapsed, 62.5% did so after prednisone stopped, and fewer than 10% of relapses came at doses above 15 mg/day. No patient developed residual lung fibrosis on high-resolution CT, and no deaths were attributed to COP progression or relapse.
Key Prognostic Determinants
Clinical reviews describe cause as mattering: cryptogenic COP is said to have a better prognosis than connective tissue disease-associated OP, which depends heavily on the activity and severity of the underlying connective tissue disease; post-infectious OP is often self-limited. Comparing COP with all secondary OP together, a 2011 series found no differences in relapse rate or mortality, and the Icelandic study found no statistical difference in survival. Initial severity correlates with course — hypoxemia requiring supplemental oxygen or intensive care unit (ICU) admission predicts a more severe disease course. Histological subtype is prognostically important: a pure OP pattern carries a good prognosis, whereas an OP pattern overlapping with fibrosing nonspecific interstitial pneumonia carries a worse prognosis and is commonly followed closely.
Rapidly Progressive COP
A subset of approximately 5% of patients presents with rapidly progressive COP, manifesting as a syndrome close to acute respiratory distress syndrome, with acute respiratory failure, bilateral extensive infiltrates, and high early mortality. This form requires aggressive intensive care unit management and high-dose intravenous methylprednisolone (typically 500–1000 mg/day for 3–5 days), sometimes with additional immunosuppression.
Distinguishing COP from Idiopathic Pulmonary Fibrosis: The Critical Difference
COP is frequently misdiagnosed as idiopathic pulmonary fibrosis, and this error carries serious consequences because the treatments differ completely. Idiopathic pulmonary fibrosis (usual interstitial pneumonia pattern) causes progressive, irreversible fibrosis; corticosteroids do not help this disease and may cause harm; median survival is 3–5 years from diagnosis. COP causes reversible organizing pneumonia; it responds dramatically to corticosteroids; prognosis is excellent. The computed tomography pattern is the key discriminator: usual interstitial pneumonia (idiopathic pulmonary fibrosis) shows basal peripheral honeycombing with traction bronchiectasis and a subpleural gradient; COP shows bilateral peripheral consolidation, ground-glass opacities, the reverse halo sign, and no honeycombing. When doubt persists, surgical lung biopsy is the step used to tell usual interstitial pneumonia from OP histology before a patient is placed on an idiopathic pulmonary fibrosis management pathway.
10. Recent Research
Post-COVID Organizing Pneumonia
A recognized sequela of SARS-CoV-2 infection emerged prominently after 2020. Patients with persistence of ground-glass and consolidative opacities weeks to months after acute COVID-19, showing an OP pattern on BAL or biopsy, respond to corticosteroids confirming the OP diagnosis. Incidence remains under study and is likely underrecognized; recognition is clinically important as these patients benefit from steroid treatment rather than watchful waiting. In a 2021 follow-up of 837 survivors, 35 (reported as 4.8%) had persistent interstitial lung disease, predominantly organizing pneumonia, with significant functional deficit. In the 30 treated with steroids, transfer factor rose by a mean relative 31.6% and forced vital capacity by 9.6%. This was observational, with no untreated comparison group.
Checkpoint Inhibitor-Associated Organizing Pneumonia
As checkpoint inhibitor use in oncology expands dramatically, this organizing pneumonia is increasingly recognized as one of the most common lung toxicities of these drugs. Research is active in identifying predictive biomarkers for its risk — including baseline computed tomography features, tumor histology, drug type and dose — and in optimizing corticosteroid regimens and timing for different severity grades. The clinical overlap with other checkpoint inhibitor pneumonitis patterns (diffuse alveolar damage, nonspecific interstitial pneumonia, hypersensitivity pneumonitis) is under active investigation. In a 2017 series of 43 pneumonitis cases among 915 patients, onset ranged from 9 days to 19.2 months, 72% were grade 1 to 2, and 86% improved or resolved with holding the drug and immunosuppression. Five worsened and died during pneumonitis treatment: the proximal cause of death was pneumonitis in 1, infection related to immunosuppression in 3 and progressive cancer in 1.
Nintedanib in COP
Case reports and small series suggest potential benefit from nintedanib (a tyrosine kinase inhibitor approved for idiopathic pulmonary fibrosis, systemic sclerosis-related interstitial lung disease, and, on the FDA label, chronic fibrosing interstitial lung diseases with a progressive phenotype) in COP patients with a fibrosing component or steroid-dependent course. Prospective clinical trial data are lacking; use remains experimental and individual.
Immunosuppressive Combinations for Recurrent COP
Retrospective series examining azathioprine combined with corticosteroids for recurrent COP demonstrate meaningful steroid-dose reduction while maintaining remission, reducing the cumulative steroid burden and associated toxicities. Mycophenolate mofetil shows similar steroid-sparing properties in observational data.
Molecular Biomarkers
BAL lymphocyte subset analysis (CD4/CD8 ratio) and serum KL-6 (Krebs von den Lungen-6) levels are under study as non-invasive biomarkers for monitoring COP disease activity and predicting relapse risk. KL-6 is produced by type II pneumocytes and is elevated in interstitial lung disease more broadly; its kinetics during COP treatment correlate with radiological response in preliminary studies.
Key Research Papers
- Epler GR, et al. Bronchiolitis obliterans organizing pneumonia. N Engl J Med. 1985;312(3):152–158. — PubMed PMID: 3965933 · doi:10.1056/NEJM198501173120304
- Cordier JF. Cryptogenic organising pneumonia. Eur Respir J. 2006;28(2):422–446. — PubMed PMID: 16880372 · doi:10.1183/09031936.06.00013505
- Travis WD, et al. An official American Thoracic Society/European Respiratory Society statement: Update of the international multidisciplinary classification of the idiopathic interstitial pneumonias. Am J Respir Crit Care Med. 2013;188(6):733–748. — PubMed PMID: 24032382 · doi:10.1164/rccm.201308-1483ST
- Lee KS, Kullnig P, Hartman TE, Müller NL. Cryptogenic organizing pneumonia: CT findings in 43 patients. AJR Am J Roentgenol. 1994;162(3):543–546. — PubMed PMID: 8109493 · doi:10.2214/ajr.162.3.8109493
- Baque-Juston M, et al. Organizing pneumonia: what is it? A conceptual approach and pictorial review. Diagn Interv Imaging. 2014;95(9):771–777. — PubMed PMID: 24559802 · doi:10.1016/j.diii.2014.01.004
- Drakopanagiotakis F, et al. Cryptogenic and secondary organizing pneumonia: clinical presentation, radiographic findings, treatment response, and prognosis. Chest. 2011;139(4):893–900. — PubMed PMID: 20724743 · doi:10.1378/chest.10-0883
- Sveinsson OA, et al. Clinical features in secondary and cryptogenic organising pneumonia. Int J Tuberc Lung Dis. 2007;11(6):689–694. — PubMed PMID: 17519103
- Lazor R, et al. Cryptogenic organizing pneumonia. Characteristics of relapses in a series of 48 patients. Am J Respir Crit Care Med. 2000;162(2 Pt 1):571–577. — PubMed PMID: 10934089 · doi:10.1164/ajrccm.162.2.9909015
- Sulavik SB. The concept of "organizing pneumonia." Chest. 1989;96(5):967–969. — PubMed PMID: 2805864 · doi:10.1378/chest.96.5.967
- Khunger M, et al. Incidence of pneumonitis with use of programmed death 1 and programmed death-ligand 1 inhibitors in non-small cell lung cancer: a systematic review and meta-analysis of trials. Chest. 2017;152(2):271–281. — PubMed PMID: 28499515 · doi:10.1016/j.chest.2017.04.177
- Raghu G, et al. An Official ATS/ERS/JRS/ALAT Statement: Idiopathic Pulmonary Fibrosis: Evidence-based Guidelines for Diagnosis and Management. Am J Respir Crit Care Med. 2011;183(6):788–824. — PubMed PMID: 21471066 · doi:10.1164/rccm.2009-040GL
- King TE Jr, Mortenson RL. Cryptogenic organizing pneumonitis. The North American experience. Chest. 1992;102(1 Suppl):8S–13S. — PubMed PMID: 1623812
- Davison AG, Heard BE, McAllister WA, Turner-Warwick ME. Cryptogenic organizing pneumonitis. Q J Med. 1983;52(207):382–394. — PubMed PMID: 6647749
- Gudmundsson G, Sveinsson O, Isaksson HJ, et al. Epidemiology of organising pneumonia in Iceland. Thorax. 2006;61(9):805–808. — PubMed PMID: 16809413 · doi:10.1136/thx.2006.059469
- Naidoo J, Wang X, Woo KM, et al. Pneumonitis in patients treated with anti-programmed death-1/programmed death ligand 1 therapy. J Clin Oncol. 2017;35(7):709–717. — PubMed PMID: 27646942 · doi:10.1200/JCO.2016.68.2005
- Meng W, Xie B, Zhang S, et al. Characteristics, prognosis, and risk factors for relapse in patients with cryptogenic organizing pneumonia: A prospective cohort study in China. Chin Med J (Engl). 2026;139(18):2750–2759. — PubMed PMID: 42604996 · doi:10.1097/CM9.0000000000004247
- Myall KJ, Mukherjee B, Castanheira AM, et al. Persistent post-COVID-19 interstitial lung disease. An observational study of corticosteroid treatment. Ann Am Thorac Soc. 2021;18(5):799–806. — PubMed PMID: 33433263 · doi:10.1513/AnnalsATS.202008-1002OC
- Stover DE, Mangino D. Macrolides: a treatment alternative for bronchiolitis obliterans organizing pneumonia? Chest. 2005;128(5):3611–3617. — PubMed PMID: 16304320 · doi:10.1378/chest.128.5.3611
PubMed Topic Searches
- PubMed: Cryptogenic organizing pneumonia
- PubMed: Organizing pneumonia BOOP corticosteroid
- PubMed: Cryptogenic organizing pneumonia CT imaging
- PubMed: Organizing pneumonia reverse halo sign
- PubMed: Checkpoint inhibitor organizing pneumonia
- PubMed: Organizing pneumonia connective tissue disease
- PubMed: Post-COVID organizing pneumonia
- PubMed: Cryptogenic organizing pneumonia recurrence
- PubMed: Organizing pneumonia amiodarone drug-induced
- PubMed: Organizing pneumonia BAL lymphocytosis
- PubMed: Organizing pneumonia versus pulmonary fibrosis IPF
- PubMed: Organizing pneumonia Masson bodies histology