Feverfew
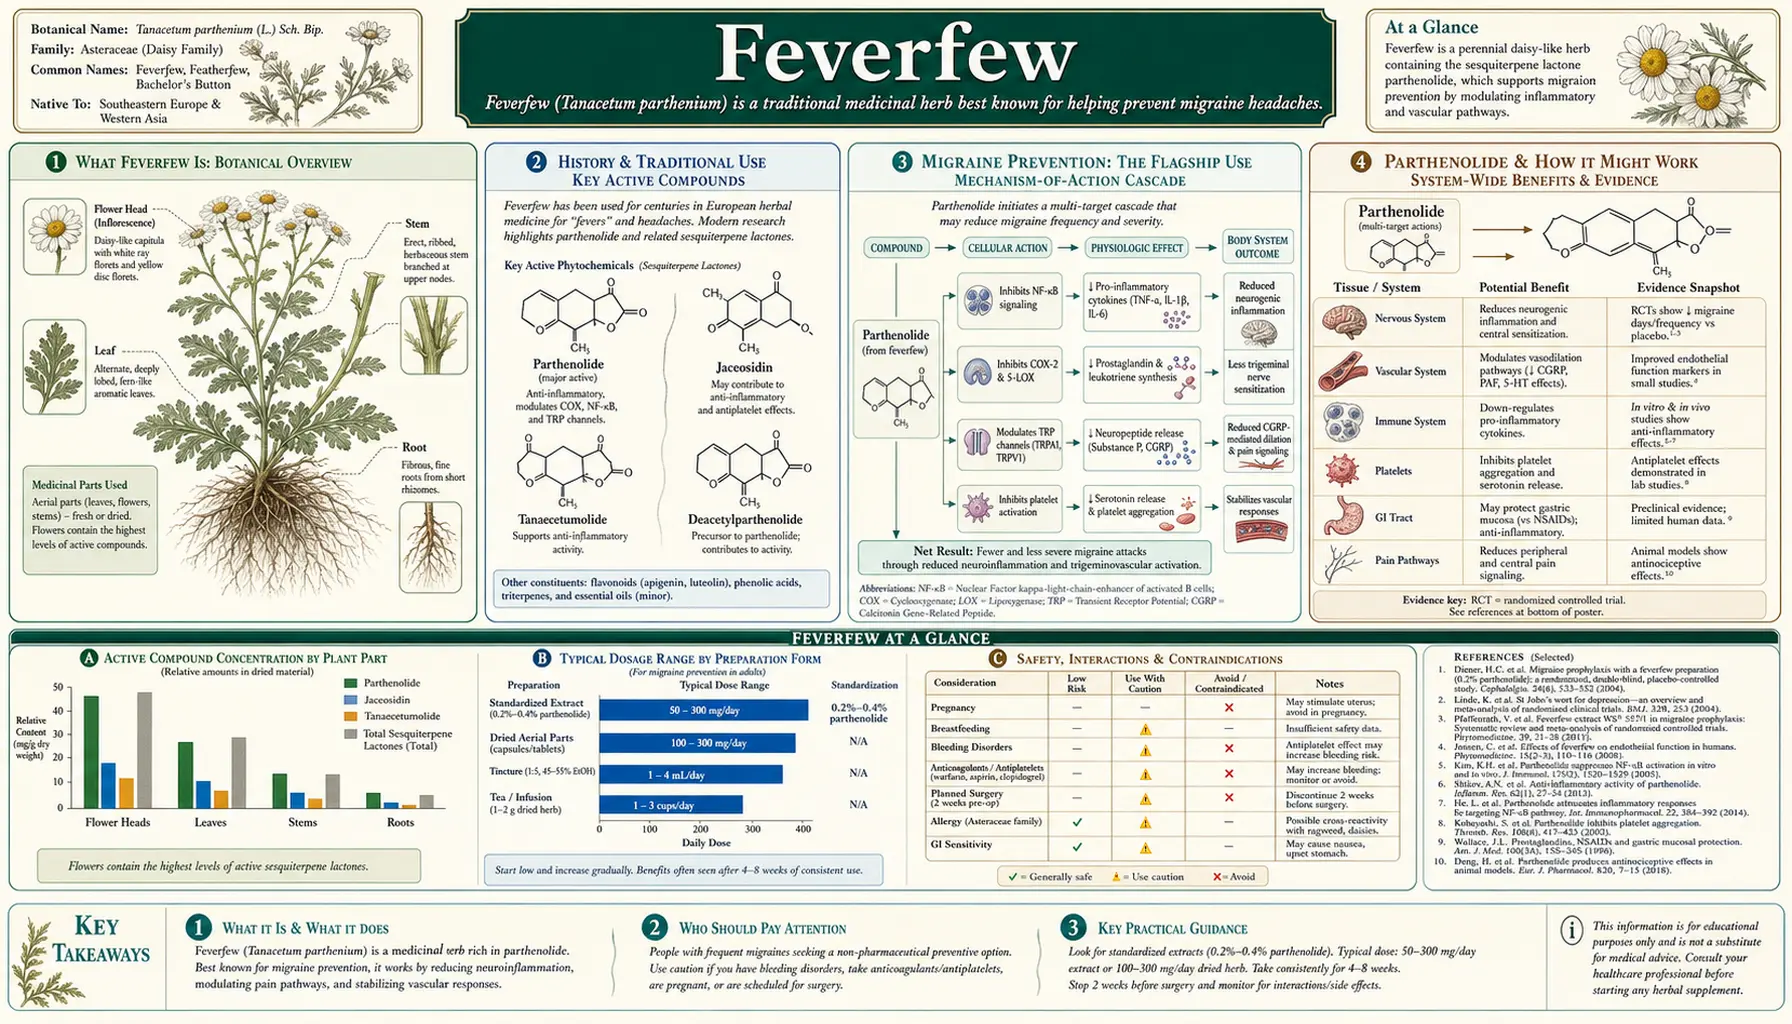
Feverfew (Tanacetum parthenium) is a small, cheerful daisy-family herb that has grown in cottage gardens and along roadsides across Europe for centuries. Its name is a clue to its oldest reputation — it comes from the Latin febrifugia, "fever reducer" — but that is not what feverfew is known for today. Its flagship modern use is migraine prevention: taken daily over weeks, it may reduce how often migraines strike in some people. That claim deserves an honest hearing, because the evidence is genuinely mixed. Some studies were positive, some found nothing, and a lot depends on which feverfew you take, since the plant's active chemistry varies enormously between products. This page walks through what feverfew is, where its reputation came from, what the research actually shows for migraine and arthritis, how its proposed active compound (parthenolide) might work, and the real safety cautions — including mouth ulcers, a rebound "post-feverfew" reaction if you stop suddenly, and who the cautions concern.
Table of Contents
- What Feverfew Is
- History & Traditional Use
- Migraine Prevention: The Flagship Use
- Parthenolide & How It Might Work
- Whole-Leaf vs Standardized Extract
- Feverfew for Arthritis
- Forms, Dosing & What to Look For
- Safety, Side Effects & Who the Cautions Concern
- Key Research Papers
- Connections
- Featured Videos
What Feverfew Is
Feverfew is a hardy perennial herb in the daisy family (Asteraceae, sometimes called Compositae) — the same botanical family as chamomile, chrysanthemums, marigolds, and ragweed, a relationship that matters for allergies (see Safety). Its botanical name is Tanacetum parthenium; older texts may list it as Chrysanthemum parthenium or Pyrethrum parthenium. Common folk names include featherfew, bachelor's buttons, wild chamomile, and midsummer daisy.
If you have seen it, you would recognize it: a bushy plant about knee-high, topped in summer with clusters of small daisy-like flowers — white petals around a flat yellow center — above feathery, yellow-green leaves. Crush a leaf and it gives off a strong, bitter, slightly citrusy scent that many people find unpleasant. Feverfew is native to the mountainous regions of southeastern Europe and Asia Minor (the Balkans and Anatolia) but has naturalized widely and is now a common garden and wayside plant across Europe, the Americas, and beyond.
The medicinal parts are the dried leaves and the leafy flowering tops (the "aerial parts"). These are what go into capsules, tablets, teas, and liquid extracts. Traditionally, people chewed the fresh green leaves directly — an approach that turns out to have a notable downside covered later on.
History & Traditional Use
Feverfew's name is a small history lesson in itself. It descends from the Latin febrifugia — from febris, "fever," and fugare, "to drive away" — literally a fever-driver. Over centuries the Latin softened through Old and Middle English into "featherfew" and finally "feverfew." The plant was, in other words, first prized as a remedy for fevers.
Its use reaches back to Greek and Roman antiquity. The first-century Greek physician Dioscorides is often cited as recommending it for fevers and inflammation, and it appears throughout the European herbal tradition that followed. By the medieval and early-modern period, feverfew had accumulated a long list of folk uses well beyond fever: headaches, menstrual difficulties, aiding childbirth, arthritis and joint pain, insect bites, stomach upset, and dizziness. The 17th-century English herbalists John Gerard and Nicholas Culpeper both wrote about it; Culpeper called it effectual "for all pains in the head," an early hint of the use that would eventually make it famous.
For most of that history, feverfew was a general-purpose folk remedy rather than a headache specialist. Its modern reputation is surprisingly recent. In 1970s and 1980s Britain, word spread — largely by personal recommendation and the popular press — that eating a few fresh feverfew leaves each day could prevent migraines. So many people began self-treating this way that British doctors and researchers took notice, and it was this grassroots enthusiasm that prompted the first proper clinical trials of feverfew for migraine. Feverfew is one of the few herbal remedies to make the leap from garden folklore to the pages of The Lancet and The BMJ largely because ordinary people were already using it.
Migraine Prevention: The Flagship Use
The single most important thing to understand about feverfew is how it is meant to be used for migraine. Feverfew is studied as a preventive (prophylactic) — something you take every day, for weeks to months, in the hope of reducing how often migraines occur and perhaps how severe they are. It is not a treatment for an attack already underway. If a migraine has started, feverfew is not the tool to reach for; it does its work quietly in the background, if at all. Any preventive also needs patience: benefits, when they appear, build over roughly one to two months rather than the first week.
The early trials
The first rigorous tests grew directly out of the British self-medication craze. In 1985, a team published a trial in The BMJ in people who were already eating feverfew leaves for their migraines: half were quietly switched to a placebo. Those taken off feverfew (given placebo) had more frequent and more severe headaches, suggesting the herb had been doing something (Johnson 1985). A few years later, a 1988 Lancet trial in migraine sufferers found that dried feverfew leaf modestly reduced the frequency and severity of attacks compared with placebo (Murphy 1988). These early studies were encouraging — but small, and complicated by the fact that participants were often experienced feverfew users who might have guessed which pill they were on.
Why the evidence looks mixed
Later trials were not all positive. A 1996 study using an alcoholic extract of feverfew found no benefit over placebo (De Weerdt 1996) — a result many researchers attribute to the particular preparation used, which may have delivered little of the active chemistry. This is the recurring theme with feverfew: the form of the herb seems to matter as much as the herb itself.
The most careful summary comes from the Cochrane review, an independent gold-standard analysis. Its 2015 update reviewed six randomized trials (561 patients); pooling their results was not possible because the trials measured different outcomes, and the largest trial found 0.6 fewer attacks per month with feverfew than with placebo, which the reviewers rated as low-quality evidence. Their conclusion was deliberately cautious: the evidence that feverfew prevents migraine is mixed and not convincing enough to be certain, and larger, more rigorous studies are needed. The reviewers noted that smaller, older trials tended to look more favorable than newer, more tightly controlled ones — a pattern that usually signals a real effect is smaller than it first appeared, or possibly absent (Wider, Pittler & Ernst 2015).
The stronger, standardized trials
The most persuasive positive evidence comes from a stable, standardized carbon-dioxide extract known by its research code MIG-99, developed specifically to solve feverfew's consistency problem. A 2002 dose-finding study found no significant preventive effect overall; only in a small predefined subgroup of 49 people with frequent attacks (at least four in 28 days) did attacks fall, most with 6.25 mg three times daily (Pfaffenrath 2002). A larger, well-designed 2005 trial of that dose found monthly attacks fell by 1.9 with MIG-99 and by 1.3 with placebo (Diener 2005). Because this extract is chemically consistent from batch to batch — unlike ordinary dried leaf — many experts consider these the most trustworthy feverfew trials.
The honest bottom line
Putting it together: feverfew may modestly reduce how often migraines happen in some people, and the case is strongest for standardized, stable extracts rather than random dried-leaf products. It is not a cure, the average benefit is modest, and rigorous trials disagree with each other. Reflecting this genuine-but-uncertain signal, an earlier (2012) guideline from the American Academy of Neurology and American Headache Society rated a standardized feverfew extract as "probably effective" (their Level B) for migraine prevention — a rating that has since been debated and revisited as newer evidence and product-quality concerns were weighed. Feverfew is a plant-based preventive with a modest, uncertain evidence base, not a miracle.
Parthenolide & How It Might Work
Feverfew contains dozens of natural compounds, but research attention has centered on one: parthenolide, a type of molecule called a sesquiterpene lactone, concentrated mainly in the leaves and flowers. Parthenolide is generally regarded as feverfew's principal active ingredient and is the compound most products are "standardized to" — though, as the next section explains, it may not be the whole story.
Several biological mechanisms have been proposed, each plausible and documented in the laboratory, though how strongly any of them explains fewer migraines in real patients is still not settled:
- Serotonin release. Feverfew extracts inhibit the release of serotonin (5-HT) from blood platelets (Heptinstall 1985). Serotonin is deeply involved in migraine biology, so damping its release is a mechanistically attractive idea.
- Platelet effects. Along with serotonin, feverfew inhibits platelet aggregation and the secretion of granules from platelets and certain white blood cells. This is relevant to migraine theories but is also the basis of a mild blood-thinning caution (see Safety).
- Anti-inflammatory / prostaglandin pathways. Parthenolide dampens the body's inflammatory signaling. It can inhibit the production of inflammatory prostaglandins and, at the molecular level, blocks NF-κB — a master switch that turns on many inflammatory genes (Hehner 1999). Migraine involves a wave of "neurogenic inflammation" around blood vessels and nerves, which this could theoretically calm.
- Trigeminal nerve channels (TRPA1). More recent work shows parthenolide acts on TRPA1, an irritant-sensing ion channel on the trigeminal nerves that drive migraine pain. By first activating and then desensitizing these channels, parthenolide reduced nerve firing and the vessel-widening that accompanies migraine in laboratory models (Materazzi 2013) — one of the more compelling modern mechanistic clues.
The takeaway is that feverfew's proposed mechanisms are not hand-waving — they rest on real pharmacology touching serotonin, inflammation, platelets, and pain-sensing nerves. What remains unproven is the final link: that these laboratory effects reliably add up to meaningfully fewer migraines in everyday use.
Whole-Leaf vs Standardized Extract
If there is one practical idea that explains feverfew's frustratingly inconsistent research, it is this: not all feverfew is the same feverfew. The amount of parthenolide in a plant — and therefore in the product on the shelf — varies dramatically depending on the plant's genetics, where it grew, the climate, which parts were harvested, and how the material was dried and stored.
Independent analyses over the years have found that some commercial feverfew products contain generous amounts of parthenolide while others contain very little or almost none. Worse, parthenolide is chemically unstable and degrades over time, especially with heat and prolonged storage. Two capsules labeled simply "feverfew" can be pharmacologically miles apart. When a study uses a weak or degraded preparation — as many suspect happened in the negative 1996 alcoholic-extract trial — a genuine effect could easily be missed.
This is exactly why the standardized, stable extract MIG-99 matters. It was engineered (using a supercritical carbon-dioxide extraction) to deliver a consistent, defined amount of active chemistry in every dose. The relatively strong results for MIG-99 may partly reflect the fact that researchers actually knew what they were giving people.
A complication worth honesty about: parthenolide may not be feverfew's only active compound. Researchers have found that feverfew preparations deliberately depleted of parthenolide still show some anti-inflammatory activity (Sur 2008), which suggests other constituents contribute. So "standardized to X% parthenolide" is a sensible quality marker — the best one we have — but not a perfect guarantee of effectiveness. Products that state a standardized parthenolide content are the ones whose strength can be compared, although the science behind that number is still imperfect.
Feverfew for Arthritis
Given feverfew's anti-inflammatory chemistry and its centuries-old folk reputation for "joint pains," it is natural to wonder whether it helps arthritis. Here the evidence is weaker than for migraine, and largely disappointing.
The clearest test was a double-blind, placebo-controlled trial in people with rheumatoid arthritis, who took either feverfew or placebo alongside their usual medication. It found no meaningful benefit from feverfew on measures of pain, stiffness, or grip strength (Pattrick 1989). One caveat is that participants kept taking their standard anti-inflammatory drugs, which may have left little room to detect an added effect, and the particular preparation and dose might not have been optimal. But there is no solid clinical evidence that feverfew relieves rheumatoid arthritis.
So while laboratory studies confirm that parthenolide and feverfew extracts have real anti-inflammatory actions, those effects have not translated into a proven benefit for arthritis in people. Easing arthritic joints remains an unsupported traditional claim rather than an evidence-based use.
Forms, Dosing & What to Look For
Feverfew is sold in several forms, and the choice interacts with the consistency problem above:
- Dried-leaf capsules and tablets — the most common form. Convenient, but parthenolide content can vary widely unless the product is standardized.
- Standardized extracts — formulated to provide a defined amount of parthenolide (or, in the case of MIG-99-type products, a stable, consistent extract). This is generally the most reliable option.
- Liquid extracts and tinctures — potency depends heavily on how they were made.
- Fresh leaves — the traditional method was to chew two or three small leaves a day. Chewing raw leaves frequently causes mouth ulcers, which the 2015 Cochrane review lists among the most common side effects in the trials (see Safety).
Doses used in research vary with the preparation. Dried-leaf studies commonly used roughly 50 to 150 mg of dried leaf per day, often with products aiming to supply a parthenolide content in the neighborhood of 0.2–0.7%. The standardized MIG-99 extract was studied at 6.25 mg three times a day. These are not interchangeable numbers — a milligram of a concentrated standardized extract is not the same as a milligram of raw leaf powder — which is why research doses only apply to the preparation that was studied.
Two practical expectations: first, feverfew is a slow, preventive approach, and the trials measured its effect over a couple of months or more. Second, product quality is so variable that the product chosen matters more with feverfew than with many other supplements.
Safety, Side Effects & Who the Cautions Concern
Feverfew is generally well tolerated by most adults for short-term use, but it has some genuinely important cautions — more than its gentle daisy appearance suggests.
Common side effects
- Mouth ulcers and mouth irritation. This is feverfew's signature side effect, and it is strongly linked to chewing raw or fresh leaves. People who chew the leaves frequently can develop painful mouth sores (aphthous ulcers), a sore or inflamed tongue and lips, swelling of the mouth, and sometimes a temporary loss of taste. Taking dried-leaf capsules instead of chewing greatly reduces this risk.
- Digestive upset. Nausea, indigestion, bloating, abdominal discomfort, and diarrhea can occur, usually mildly.
- Contact dermatitis. Handling the fresh plant can irritate the skin in sensitive people.
The "post-feverfew" rebound
One caution that catches people off guard concerns stopping long-term feverfew abruptly. Regular users who suddenly quit have reported a withdrawal-like cluster sometimes called "post-feverfew syndrome" — a rebound of headaches (often worse than before), along with anxiety, poor sleep, tiredness, and muscle and joint stiffness or aches. In a 1985 trial, long-term users switched to placebo had more frequent and severe headaches, nausea and vomiting, along with other unwanted effects (Johnson 1985). Herbal practitioners describe tapering the dose down gradually over a week or more rather than quitting cold.
Who the cautions concern
- Pregnancy and breastfeeding. Feverfew has a traditional reputation as an emmenagogue (a substance that stimulates menstruation) and was historically used to bring on menstruation and assist labor, raising a theoretical risk of stimulating uterine contractions. There is not enough safety data, so it is not considered safe in pregnancy, and there is no safety data for breastfeeding either.
- People allergic to the daisy (Asteraceae) family. Because feverfew belongs to the same botanical family as ragweed, chamomile, chrysanthemums, marigolds, and daisies, people allergic to any of these can experience cross-reactive allergic reactions to feverfew. The concern is greatest for people who react to ragweed pollen or chamomile tea.
- Anyone on blood thinners or facing surgery. Feverfew can inhibit platelet activity, which in theory adds to the effect of anticoagulant or antiplatelet medicines (such as warfarin, aspirin, or clopidogrel) and could increase bleeding risk. It is commonly advised to stop feverfew about two weeks before scheduled surgery and the concern is greatest for people taking blood-thinning drugs.
- Young children. Feverfew has not been adequately studied in children, so there is no safety data for them.
These interactions matter most for people who take prescription medication or have a chronic condition — particularly the blood-thinning interaction, and the fact that a herbal migraine preventive is often being added on top of other treatments.
Key Research Papers
- Wider B, Pittler MH, Ernst E. Feverfew for preventing migraine. Cochrane Database of Systematic Reviews. 2015;(4):CD002286. — The independent gold-standard review; reviewed six randomized trials (561 patients), found pooling not possible, and concluded the evidence for migraine prevention is mixed, low quality and not yet convincing, with smaller older trials looking more favorable than rigorous newer ones. — doi:10.1002/14651858.CD002286.pub3
- Diener HC, Pfaffenrath V, Schnitker J, Friede M, Henneicke-von Zepelin HH. Efficacy and safety of 6.25 mg t.i.d. feverfew CO2-extract (MIG-99) in migraine prevention — a randomized, double-blind, multicentre, placebo-controlled study. Cephalalgia. 2005;25(11):1031–1041. — The strongest positive trial, using a stable standardized extract; monthly attacks fell by 1.9 with MIG-99 versus 1.3 with placebo. — doi:10.1111/j.1468-2982.2005.00950.x
- Pfaffenrath V, Diener HC, Fischer M, Friede M, Henneicke-von Zepelin HH. The efficacy and safety of Tanacetum parthenium (feverfew) in migraine prophylaxis — a double-blind, multicentre, randomized placebo-controlled dose-response study. Cephalalgia. 2002;22(7):523–532. — The dose-finding study: no significant effect overall; benefit only in a small subgroup (n = 49) with at least four attacks in 28 days, best at 6.25 mg three times daily, the dose used in the 2005 trial. — doi:10.1046/j.1468-2982.2002.00396.x
- Murphy JJ, Heptinstall S, Mitchell JRA. Randomised double-blind placebo-controlled trial of feverfew in migraine prevention. The Lancet. 1988;332(8604):189–192. — A classic early trial in which dried feverfew leaf modestly reduced the frequency and severity of migraine attacks. — doi:10.1016/S0140-6736(88)92289-1
- Johnson ES, Kadam NP, Hylands DM, Hylands PJ. Efficacy of feverfew as prophylactic treatment of migraine. British Medical Journal (Clinical Research Ed.). 1985;291(6495):569–573. — The pioneering trial in habitual feverfew users; those switched to placebo had more frequent and severe headaches, and the study also described withdrawal-type symptoms on stopping. — doi:10.1136/bmj.291.6495.569
- De Weerdt CJ, Bootsma HPR, Hendriks H. Herbal medicines in migraine prevention: randomized double-blind placebo-controlled crossover trial of a feverfew preparation. Phytomedicine. 1996;3(3):225–230. — A negative trial using an alcoholic feverfew extract that found no benefit, widely cited as evidence that the preparation and its active content are decisive. — doi:10.1016/S0944-7113(96)80057-2
- Knight DW. Feverfew: chemistry and biological activity. Natural Product Reports. 1995;12(3):271–276. — A chemistry review of feverfew's sesquiterpene lactones, establishing parthenolide as the principal candidate active compound. — doi:10.1039/np9951200271
- Heptinstall S, White A, Williamson L, Mitchell JRA. Extracts of feverfew inhibit granule secretion in blood platelets and polymorphonuclear leucocytes. The Lancet. 1985;325(8437):1071–1074. — Foundational mechanism work showing feverfew inhibits serotonin release and granule secretion from platelets and white blood cells. — doi:10.1016/s0140-6736(85)92371-2
- Hehner SP, Hofmann TG, Dröge W, Schmitz ML. The antiinflammatory sesquiterpene lactone parthenolide inhibits NF-κB by targeting the IκB kinase complex. The Journal of Immunology. 1999;163(10):5617–5623. — Identifies a molecular basis for parthenolide's anti-inflammatory action: blockade of the NF-κB master inflammatory switch. — doi:10.4049/jimmunol.163.10.5617
- Materazzi S, Benemei S, Fusi C, et al. Parthenolide inhibits nociception and neurogenic vasodilatation in the trigeminovascular system by targeting the TRPA1 channel. Pain. 2013;154(12):2750–2758. — A modern mechanistic study linking parthenolide to the trigeminal TRPA1 channel central to migraine pain and vessel dilation. — doi:10.1016/j.pain.2013.08.002
- Pattrick M, Heptinstall S, Doherty M. Feverfew in rheumatoid arthritis: a double blind, placebo controlled study. Annals of the Rheumatic Diseases. 1989;48(7):547–549. — The clearest arthritis trial; feverfew showed no significant benefit over placebo, tempering the traditional joint-pain claim. — doi:10.1136/ard.48.7.547
- Pareek A, Suthar M, Rathore GS, Bansal V. Feverfew (Tanacetum parthenium L.): a systematic review. Pharmacognosy Reviews. 2011;5(9):103–110. — A broad review of feverfew's botany, history, parthenolide chemistry, proposed mechanisms, clinical uses, and safety. — doi:10.4103/0973-7847.79105
The fuller story — where Feverfew came from, who first wrote it down, and how it travelled into modern use — is told in the dedicated Feverfew: History and Traditional Use article.
Connections
- All Herbs
- Feverfew History
- Feverfew Benefits
- Migraine
- Ginger
- Ginger for Migraine and Pain — the Cady 2011 trial of the sublingual feverfew-plus-ginger combination.
- Discussed in depth on these pages: Magnesium, Riboflavin, and Supplements for Migraine
- Conditions on this site that reference this page: Neurology · Migraine