⚠ Evidence warning: Clinical trials or other evidence do not support the claims that the effect of low-dose naltrexone grows over 8 to 12 weeks and that a subset of patients are clear responders. This page keeps it as a report of what people, websites or other media say.
Non-Opioid Medications for Chronic Pain
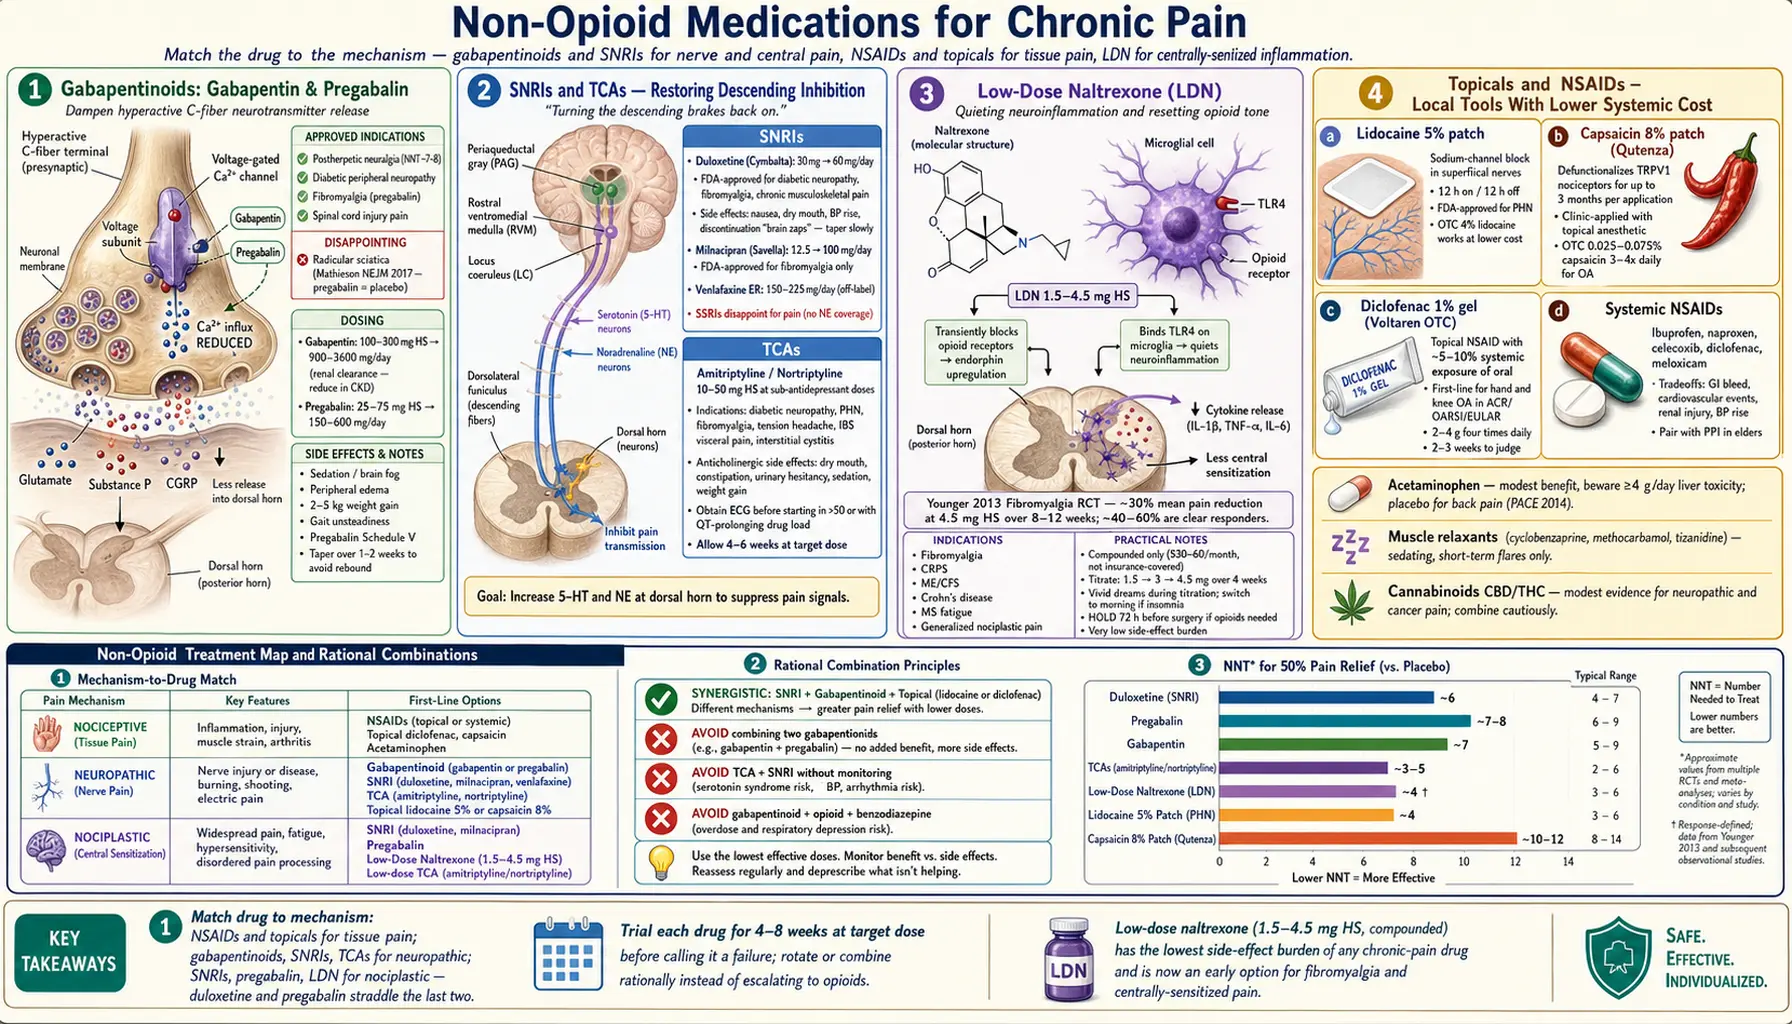
Table of Contents
- Why Non-Opioid Medicines Come First
- Matching the Drug to the Pain Type
- Gabapentinoids: Gabapentin and Pregabalin
- Serotonin-Norepinephrine Reuptake Inhibitors: Duloxetine, Milnacipran, Venlafaxine
- Tricyclic Antidepressants
- Selective Serotonin Reuptake Inhibitors — Why They Disappoint for Pain
- Low-Dose Naltrexone
- Topical Agents: Capsaicin, Lidocaine, Diclofenac
- Nonsteroidal Anti-Inflammatory Drugs and the Cardiovascular/Gastrointestinal/Renal Tradeoffs
- Acetaminophen — Limits of the Workhorse
- Muscle Relaxants and Tizanidine
- Cannabinoids: Cannabidiol and Tetrahydrocannabinol
- Combining Drugs Rationally
- Questions Worth Raising With a Prescriber
- Key Research Papers
- Connections
- Featured Videos
Why Non-Opioid Medicines Come First
If you live with chronic pain, the medication shelf looks crowded and contradictory. Your primary doctor suggests gabapentin. A neurologist adds duloxetine. A pain clinic mentions low-dose naltrexone. A friend swears by a lidocaine patch. The rheumatologist warns you about nonsteroidal anti-inflammatory drugs (NSAIDs). Meanwhile, opioids hover in the background — promised relief shadowed by tolerance, dependence, and the mountain of harm revealed over the last two decades.
The honest summary: no single non-opioid drug reliably relieves chronic pain in most people, but several of them help a meaningful minority, and unlike opioids, their benefits tend to hold up over time without the spiral of escalating doses. The modern pain-medicine playbook is to start with the non-opioid class that best matches your pain type, accept that the first drug may not work, and rotate or combine rationally rather than defaulting to stronger and stronger opioids.
This article walks through every major non-opioid class used for chronic non-cancer pain — what they do, who they help, how they are dosed, what side effects to watch for, and what the evidence actually shows. None of these are miracle drugs, and the evidence for each is set out here as it stands. We are going to help you have a more informed conversation with the person writing your prescriptions.
Matching the Drug to the Pain Type
Before any drug is chosen, your pain needs a category. The three clinical buckets (see the pain-type article) shape everything that follows:
- Nociceptive pain — tissue injury or inflammation (osteoarthritis, tendinopathy, acute musculoskeletal injury). Responds best to nonsteroidal anti-inflammatory drugs, acetaminophen, topical diclofenac, and physical rehabilitation.
- Neuropathic pain — damaged or dysfunctional nerves (diabetic neuropathy, postherpetic neuralgia, radiculopathy, chemotherapy-induced neuropathy, trigeminal neuralgia). Responds best to gabapentinoids, serotonin-norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), lidocaine patch, capsaicin 8% patch.
- Nociplastic pain — altered central pain processing without detectable tissue or nerve damage (fibromyalgia, many chronic low-back-pain syndromes, irritable bowel syndrome (IBS) visceral pain, tension headache, complex regional pain syndrome (CRPS) in its later stages). Responds best to serotonin-norepinephrine reuptake inhibitors, tricyclic antidepressants, low-dose naltrexone, and non-pharmacologic interventions including pain reprocessing therapy.
Most chronic pain patients have mixed pain — a bit of inflammation, a bit of nerve irritation, and years of central sensitization layered on top. That is why combination therapy is the rule, not the exception.
Gabapentinoids: Gabapentin and Pregabalin
What They Do
Gabapentin and pregabalin bind the α2δ subunit of voltage-gated calcium channels on overactive sensory neurons. By dampening calcium influx, they reduce the release of glutamate, substance P, and calcitonin gene-related peptide (CGRP) — the excitatory neurotransmitters that carry pain signals into the spinal cord. The net effect is quieter nerve firing.
Who Benefits
- Postherpetic neuralgia (the burning nerve pain after shingles) — U.S. Food and Drug Administration-approved for both drugs; number needed to treat (NNT) for 50% pain relief is roughly 7–8.
- Diabetic peripheral neuropathy — pregabalin is U.S. Food and Drug Administration-approved; gabapentin is a guideline-recommended first-line option.
- Fibromyalgia — pregabalin is U.S. Food and Drug Administration-approved; gabapentin is used off-label with similar but weaker evidence.
- Spinal cord injury pain — pregabalin is U.S. Food and Drug Administration-approved.
- Radicular (sciatic) pain — historically prescribed, but a New England Journal of Medicine trial (Mathieson 2017) found pregabalin no better than placebo for acute or chronic sciatica. Many guidelines now de-emphasize use for back pain alone.
Typical Dosing
- Gabapentin: start 100–300 mg at bedtime. Titrate by 300 mg every 3–7 days, split into three daily doses, to an effective range of 900–3600 mg/day. Doses are reduced substantially when the kidneys are weak, because gabapentin is cleared by the kidneys.
- Pregabalin: start 25–75 mg at bedtime. Titrate to 150–600 mg/day, split twice or three times daily. Effects usually visible within 1–2 weeks.
The Side Effects People Most Often Notice
The label lists a wall of possibilities. In real-world practice, four come up constantly:
- Sedation and "brain fog." Especially during titration and in older adults. Taking the largest dose at bedtime is a common way to lessen it.
- Peripheral edema. Puffy ankles and feet, sometimes face. Not dangerous but uncomfortable; often dose-related.
- Weight gain. Averages 2–5 kg (4–11 lb) over a few months, more with pregabalin than gabapentin. Mechanism is partly appetite-driven, partly fluid retention.
- Dizziness and gait unsteadiness. A real fall risk in older patients, especially combined with other central nervous system (CNS) depressants.
Abuse potential. Pregabalin is a Schedule V controlled substance in the U.S. Gabapentin is not federally controlled but is scheduled in several states. People with substance-use histories can misuse both drugs, particularly when combined with opioids or benzodiazepines; the combination increases overdose risk.
Stopping. Tapering usually takes 1–2 weeks. Abrupt discontinuation can cause rebound anxiety, insomnia, and, rarely, seizures.
Serotonin-Norepinephrine Reuptake Inhibitors: Duloxetine, Milnacipran, Venlafaxine
What They Do
Serotonin-norepinephrine reuptake inhibitors raise synaptic levels of both neurotransmitters in the descending inhibitory pain pathways — spinal cord circuits that originate in the brainstem and normally dampen incoming pain signals. In chronic pain, these pathways are underactive. Serotonin-norepinephrine reuptake inhibitors turn them back up.
Duloxetine
The most important non-opioid pain drug in modern practice. U.S. Food and Drug Administration-approved for:
- Diabetic peripheral neuropathy
- Fibromyalgia
- Chronic musculoskeletal pain (including chronic low-back pain and osteoarthritis knee pain)
Typical dose: start 30 mg once daily for one week, then 60 mg once daily. Maximum 120 mg/day, though benefit rarely increases above 60 mg. Effects on pain typically appear within 2–4 weeks.
Side effects: nausea (usually transient, and often eased by taking it with food), dry mouth, constipation, sweating, insomnia, sexual dysfunction. Blood pressure can rise modestly, so it is usually checked at follow-up. Discontinuation syndrome is real: skipping even one dose can produce "brain zaps," dizziness, and flu-like symptoms. Tapering is usually slow (reducing by 30 mg every 1–2 weeks, or alternate-day dosing before stopping). Liver disease and heavy alcohol use are contraindications.
Milnacipran
U.S. Food and Drug Administration-approved for fibromyalgia only. Dose: titrate from 12.5 mg once daily to 50 mg twice daily over a week. Slightly more norepinephrine-selective than duloxetine, which in theory explains its modest edge on fatigue in some patients. Side effects: nausea, headache, constipation, hot flushes, increased heart rate and blood pressure. Insurance coverage is patchier than duloxetine; generic is available.
Venlafaxine
Off-label for neuropathic pain and chronic musculoskeletal pain. At doses under 150 mg/day it acts mainly as a serotonin reuptake inhibitor; pain benefit requires 150–225 mg/day, where norepinephrine reuptake inhibition kicks in. Withdrawal is notoriously harsh; the extended-release form and a slow taper are the usual approach. Blood-pressure monitoring is important at higher doses.
Tricyclic Antidepressants
Tricyclic antidepressants are the oldest neuropathic-pain drugs and, for many patients, still the most effective. Amitriptyline has the largest evidence base; nortriptyline (its active metabolite) is better tolerated. Both work for pain at doses far below antidepressant doses — typically 10–50 mg at bedtime, compared with 100–150 mg for depression.
Who Benefits
- Diabetic peripheral neuropathy
- Postherpetic neuralgia
- Fibromyalgia (amitriptyline is older but still guideline-recommended)
- Chronic tension-type headache and migraine prevention
- Irritable bowel syndrome visceral pain
- Interstitial cystitis / bladder pain syndrome
Dosing in Practice
- Amitriptyline or nortriptyline: start 10 mg at bedtime. Increase by 10 mg every 1–2 weeks based on tolerance. Most responders land between 25 and 50 mg. Nortriptyline causes less daytime grogginess, dry mouth, and constipation than amitriptyline.
- Prescribers usually allow 4–6 weeks at target dose before judging whether a trial has worked.
Side Effects and Safety
Anticholinergic effects dominate: dry mouth, constipation, urinary hesitancy, blurred vision, daytime sedation, weight gain. These effects raise particular concerns in older adults with dementia, glaucoma, or an enlarged prostate (prostatic hypertrophy). QT prolongation matters at higher doses; a baseline electrocardiogram (ECG) is commonly taken in patients over 50 or those on other QT-prolonging drugs. Overdose is cardiotoxic, which is why these drugs are prescribed in small quantities if suicide risk is a concern.
Selective Serotonin Reuptake Inhibitors — Why They Disappoint for Pain
Selective serotonin reuptake inhibitors (sertraline, fluoxetine, citalopram, escitalopram, paroxetine) are excellent for depression and anxiety, both of which commonly ride alongside chronic pain. But as pain drugs in their own right, they are weak. The descending inhibitory pathway uses norepinephrine as well as serotonin, and selective serotonin reuptake inhibitors (SSRIs) ignore the noradrenergic half of the equation.
The practical point: when depression or anxiety is the dominant symptom and pain is secondary, a selective serotonin reuptake inhibitor fits that picture. When pain is the primary problem, the drugs that also act on norepinephrine — a TCA, a serotonin-norepinephrine reuptake inhibitor, or both in combination — match the pain mechanism better. Paroxetine is the partial exception: some neuropathic-pain trials show modest benefit, likely because it has some noradrenergic activity at higher doses. Not enough to make it a first choice.
Low-Dose Naltrexone
The Short Version
Naltrexone is an opioid-receptor antagonist used at 50 mg/day to block the effects of heroin or alcohol. At 1.5 to 4.5 mg once daily — roughly 1/10th to 1/30th of the addiction-medicine dose — it does something different. It transiently blocks opioid receptors for a few hours, triggering an upregulation of endogenous endorphins. More importantly, it binds toll-like receptor 4 (TLR4) on microglia, the brain's resident immune cells, and quiets the neuroinflammation that drives central sensitization.
This glial mechanism is why low dose naltrexone (LDN) shows up in chronic-pain practice despite the counterintuitive "opioid blocker relieves pain" branding.
What the Evidence Shows
Jarred Younger and colleagues at Stanford University ran the first positive human trials: small randomized crossover studies in fibromyalgia. In the 2013 trial (31 women, 4.5 mg daily), pain fell 28.8% on low-dose naltrexone against 18.0% on placebo (P = 0.016), so the gain over placebo was about 11 percentage points. Thirty-two percent of the women met the trial's response criteria (less pain plus less fatigue or fewer sleep problems) while on low-dose naltrexone, against 11% while on placebo; others saw little change. In these small crossover studies the effect grew over 8–12 weeks. A subset of patients are clear responders; others see nothing. See Younger's 2013 paper (linked below) and subsequent reviews.
Larger Trials Since 2023
Three larger or longer trials published since 2023 did not find a clear pain benefit:
- FINAL (Denmark, 2024) — 99 women with fibromyalgia, 6 mg daily or placebo for 12 weeks. Pain fell 1.3 points on low-dose naltrexone and 0.9 points on placebo (0–10 scale), a difference of 0.34 that was not significant (p = 0.27). Side effects were about as common as on placebo (84% vs 86% of patients). The authors note a possible improvement in fibromyalgia-related memory problems, which they suggest testing further.
- INNOVA (Spain, 2026) — 98 women with fibromyalgia, 4.5 mg daily or placebo, followed for 12 months. At 3 months pain fell 0.33 points on low-dose naltrexone and 0.64 points on placebo (adjusted difference 0.49, p = 0.236), with no clinically meaningful benefit at later visits. Low-dose naltrexone was well tolerated.
- Danish crossover trial (2023) — 58 patients with fibromyalgia, 4.5 mg daily or placebo over an 8-week crossover. The differences in the fibromyalgia impact score (P = 0.3) and in pain ratings (P = 0.4) showed no clinically relevant pain relief.
What is not known. The positive results come from small crossover studies such as the 2013 trial in 31 women, while the three larger or longer trials since 2023 were negative for pain. No trial has yet shown which people, if any, respond reliably, or at what dose. What practitioners and patients report is described below.
Beyond fibromyalgia, case series and small trials suggest benefit in:
- Complex regional pain syndrome
- Chronic fatigue syndrome / myalgic encephalomyelitis (ME)
- Crohn's disease (anti-inflammatory effect)
- Multiple sclerosis fatigue and spasticity
- Generalized chronic nociplastic pain
See the dedicated low dose naltrexone fibromyalgia article for the full trial list and patient stories.
Practical Considerations
- Compounded only. Low-dose naltrexone is not available as a commercial tablet. A compounding pharmacy prepares 1.5 mg, 3 mg, or 4.5 mg capsules. Typical cost in the U.S. is $30–$60 per month, usually not covered by insurance.
- Titration. A common schedule is 1.5 mg at bedtime for 1–2 weeks, then 3 mg for 1–2 weeks, then 4.5 mg. Vivid dreams and insomnia during titration are common; switching to morning dosing fixes them for most people.
- 2–3 months at 4.5 mg is the time practitioners usually allow before judging it.
- Opioid pain medicines. Low dose naltrexone blunts the effect of opioid analgesics. For surgery or acute opioid pain control, the usual practice is to hold low dose naltrexone for 72 hours before and after.
- Very low side-effect burden compared with gabapentinoids, serotonin-norepinephrine reuptake inhibitors, or tricyclic antidepressants — which is why many pain physicians now try it early rather than as a last resort.
Topical Agents: Capsaicin, Lidocaine, Diclofenac
Topical therapies deliver drug to painful tissue while keeping systemic exposure low. For localized pain, they are often under-used first-line options.
Lidocaine 5% Patch
Blocks sodium channels in superficial cutaneous nerves. U.S. Food and Drug Administration-approved for postherpetic neuralgia; used off-label for focal diabetic neuropathy, post-surgical nerve pain, and localized low-back pain. Up to three patches (covering the painful area) are worn for 12 hours on, 12 hours off. Almost no systemic absorption; main side effect is skin irritation. Over-the-counter 4% lidocaine patches are widely available and usually adequate substitutes at lower cost.
Capsaicin 8% Patch
A high-concentration patch applied in a clinic under a topical anesthetic. It defunctionalizes TRPV1-bearing nociceptive nerve fibers for up to three months per application. U.S. Food and Drug Administration-approved for postherpetic neuralgia and diabetic peripheral neuropathy of the feet. Intense burning is common during and briefly after the 30–60 minute application; patients often describe it as "worse before better." Low-concentration over-the-counter (OTC) capsaicin creams (0.025–0.075%) applied 3–4 times daily offer milder benefit for osteoarthritis and neuropathic pain.
Diclofenac 1% Gel
A topical nonsteroidal anti-inflammatory drug (NSAID) that is now over-the-counter in the U.S. Rubbed into joints affected by osteoarthritis — knees, hands, ankles. Delivers therapeutic drug concentration to the joint with roughly 5–10% of the systemic exposure of oral diclofenac, sharply reducing gastrointestinal (GI), cardiovascular, and renal risk. First-line for hand and knee osteoarthritis in every major guideline (American College of Rheumatology, Osteoarthritis Research Society International, and the European Alliance of Associations for Rheumatology). The usual dose is 2–4 g four times daily, with 2–3 weeks of consistent use before the effect is judged.
Nonsteroidal Anti-Inflammatory Drugs and the Cardiovascular/Gastrointestinal/Renal Tradeoffs
Oral nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, meloxicam, celecoxib, diclofenac, etodolac) suppress cyclooxygenase-1 (COX-1) and cyclooxygenase-2 (COX-2) enzymes, reducing prostaglandin-driven inflammation and pain. They are highly effective for nociceptive pain and for inflammatory conditions like rheumatoid arthritis and ankylosing spondylitis. They are not the right first drug for neuropathic or nociplastic pain — they do very little for either.
The three big tradeoffs:
- Gastrointestinal. Ulcers and bleeding, especially with age > 65, prior ulcer, concurrent steroid, anticoagulant, or selective serotonin reuptake inhibitor (SSRI). A proton pump inhibitor is commonly added when long-term use cannot be avoided.
- Cardiovascular. All non-aspirin nonsteroidal anti-inflammatory drugs raise risk of myocardial infarction and stroke. Naproxen appears safest; diclofenac and rofecoxib (withdrawn) are the worst. Celecoxib is intermediate. The risk matters most for people with established coronary disease, in whom all nonsteroidal anti-inflammatory drugs are generally avoided when possible.
- Renal. Nonsteroidal anti-inflammatory drugs constrict afferent glomerular arterioles and can precipitate acute kidney injury, especially during dehydration, heart failure, or with angiotensin-converting enzyme inhibitor (ACE inhibitor) / angiotensin receptor blocker (ARB) use (the "triple whammy"). They are generally avoided when the estimated glomerular filtration rate (eGFR) is below 30 and used cautiously at 30–60.
For most chronic pain patients, the usual sequence in practice is: topical diclofenac first, short courses of oral nonsteroidal anti-inflammatory drugs for flares, and serious reassessment before moving to daily long-term oral nonsteroidal anti-inflammatory drug use.
Acetaminophen — Limits of the Workhorse
Acetaminophen (paracetamol) is the default "safe" analgesic, but the evidence for chronic pain is weaker than the reputation. Cochrane reviews show minimal benefit for chronic low-back pain and only modest benefit for knee osteoarthritis, and the large PACE trial (Lancet 2014) in 1,652 people with acute low-back pain found no faster recovery than placebo (median 17 days on regular or as-needed paracetamol vs 16 days on placebo). It remains an option for patients who cannot tolerate nonsteroidal anti-inflammatory drugs, and it is useful as an opioid-sparing background analgesic.
Dosing: 3 grams per day maximum for chronic use (down from the older 4 g limit), 2 grams/day maximum for people who drink alcohol regularly or have any liver disease. Combination cold medicines often hide an extra 325–1000 mg, which counts toward the daily total. Acute acetaminophen overdose causes fulminant liver failure and is the leading cause of acute liver transplantation in the U.S.
Muscle Relaxants and Tizanidine
Cyclobenzaprine, methocarbamol, metaxalone, carisoprodol, tizanidine, and baclofen are grouped as "muscle relaxants" although their mechanisms are diverse. For acute musculoskeletal pain (a few days to two weeks), several show modest benefit, mostly through sedation rather than true muscle relaxation. For chronic pain, evidence is poor and side effects mount:
- Cyclobenzaprine: a TCA cousin. Sedating, anticholinergic. Generally used short-term only; 5 mg at bedtime is often enough.
- Carisoprodol: metabolized to meprobamate, a barbiturate-like drug. Abuse potential is high and benefit modest.
- Baclofen: gamma-aminobutyric acid-B agonist. Genuinely useful for spasticity in multiple sclerosis (MS), spinal cord injury, and cerebral palsy. Limited role in non-spastic chronic pain.
- Tizanidine: an alpha-2 agonist similar to clonidine. Works for spasticity, chronic tension headache, myofascial pain, and sometimes nighttime pain-driven insomnia (2–4 mg at bedtime). Low blood pressure (hypotension) and liver enzyme elevation are known effects; fluvoxamine and ciprofloxacin are contraindicated with it, because they block the liver enzyme CYP1A2 and raise tizanidine to toxic levels.
Cannabinoids: Cannabidiol and Tetrahydrocannabinol
Cannabis-derived compounds are commonly used by chronic-pain patients, but the evidence is messier than marketing suggests.
- cannabidiol (CBD): non-intoxicating. Randomized trials for chronic pain are small and mixed; the best evidence is for specific rare epilepsies (prescription cannabidiol oral solution) and some inflammatory/anxiety applications. For chronic pain, cannabidiol may help a subset, particularly when combined with sleep improvement. Quality of over-the-counter products varies enormously; a certificate of analysis (COA) from an independent lab is the usual way to check what a product contains.
- tetrahydrocannabinol (THC): intoxicating. Modest evidence for chronic neuropathic pain and for chemotherapy-induced nausea (nabilone, dronabinol). Side effects include cognitive slowing, dependence, cannabinoid hyperemesis syndrome with heavy use, and cardiovascular events in susceptible patients.
- Nabiximols (a tetrahydrocannabinol:cannabidiol mouth spray): approved in several countries for multiple sclerosis spasticity and cancer pain; not U.S. Food and Drug Administration-approved in the U.S.
Cannabinoids are not a primary pain therapy in current U.S. guidelines. Some clinicians use them as an add-on for motivated patients in states where access is legal, alongside the cognitive side effects and legal/employment implications.
Combining Drugs Rationally
Most chronic-pain patients end up on two or three agents. The goal is additive or synergistic mechanisms, not additive side effects. Combinations commonly used in practice, and what the trials show:
- TCA + gabapentinoid for severe neuropathic pain. In a 2009 crossover trial in 56 people with diabetic nerve pain or nerve pain after shingles, average daily pain at the highest tolerated dose was 2.3 out of 10 on nortriptyline plus gabapentin, against 2.9 on nortriptyline alone and 3.2 on gabapentin alone (from 5.4 at the start); dry mouth was the most common side effect.
- Duloxetine + gabapentin/pregabalin for diabetic neuropathy or fibromyalgia. The COMBO-DN trial (339 people with diabetic nerve pain who had not responded to standard doses) found duloxetine 60 mg plus pregabalin 300 mg not significantly better than raising either drug to its top dose: pain fell 2.35 vs 2.16 points (P = 0.370), and half-or-better relief came in 52.1% vs 39.3% (P = 0.068). In the first 8 weeks, duloxetine 60 mg a day relieved pain better than pregabalin 300 mg a day (an exploratory analysis).
- Low dose naltrexone + serotonin-norepinephrine reuptake inhibitor (SNRI) for fibromyalgia (different mechanisms, non-overlapping side effects).
- Topical diclofenac + acetaminophen for osteoarthritis.
- Lidocaine patch + oral neuropathic drug for focal neuropathic pain.
Combinations that raise safety concerns: TCA + serotonin-norepinephrine reuptake inhibitor (serotonin syndrome risk, additive anticholinergic load), gabapentinoid + opioid + benzodiazepine (respiratory depression), multiple sedating agents (falls in older adults). These interaction checks depend on the complete medication list — including over-the-counter products, supplements, and cannabis.
Questions Worth Raising With a Prescriber
- "Which pain type do you think I have — nociceptive, neuropathic, nociplastic, or mixed?" The answer shapes everything downstream.
- "What is the target dose, and how long until we know if this drug is working?" Most of these drugs need 2–6 weeks at a therapeutic dose, not just any dose.
- "What is the plan if this does not work — switch or add?" The next step is easier when it is mapped out before the first drug starts.
- "What side effects am I most likely to feel, and which ones should prompt a call?"
- "How will we taper this drug if we decide to stop?" Serotonin-norepinephrine reuptake inhibitors, gabapentinoids, and TCAs can all cause withdrawal effects when stopped abruptly, which is why a taper plan matters.
- "Is a topical option reasonable for my pain pattern?" Focal pain is often under-treated topically.
- "Can we consider low-dose naltrexone?" Many primary-care physicians are unfamiliar; pain specialists and functional-medicine clinicians prescribe it routinely.
Key Research Papers
- Finnerup NB, et al. Pharmacotherapy for neuropathic pain in adults: a systematic review and meta-analysis. Lancet Neurol. 2015. — doi:10.1016/S1474-4422(14)70251-0
- Mathieson S, et al. Trial of Pregabalin for Acute and Chronic Sciatica. N Engl J Med. 2017. — doi:10.1056/NEJMoa1614292
- Younger J, Noor N, McCue R, Mackey S. Low-dose naltrexone for the treatment of fibromyalgia: findings of a small, randomized, double-blind, placebo-controlled, counterbalanced, crossover trial assessing daily pain levels. Arthritis Rheum. 2013;65(2):529–38. — PubMed PMID: 23359310
- Brown N, Panksepp J. Low-dose naltrexone for disease prevention and quality of life. Med Hypotheses. 2009;72(3):333–7. — PubMed PMID: 19041189
- Williams CM, et al. Efficacy of paracetamol for acute low-back pain (PACE): a double-blind, randomised controlled trial. Lancet. 2014. — doi:10.1016/S0140-6736(14)60805-9
- Tesfaye S, et al. Duloxetine and pregabalin: high-dose monotherapy or their combination? The COMBO-DN study. Pain. 2013. — doi:10.1016/j.pain.2013.05.043
- Enke O, et al. Anticonvulsants in the treatment of low back pain and lumbar radicular pain: a systematic review and meta-analysis. CMAJ. 2018. — doi:10.1503/cmaj.171333
- Moore RA, Derry S, Aldington D, Cole P, Wiffen PJ. Amitriptyline for neuropathic pain in adults. Cochrane Database Syst Rev. 2015;2015(7):CD008242. — PubMed PMID: 26146793
- Gilron I, Bailey JM, Tu D, Holden RR, Jackson AC, Houlden RL. Nortriptyline and gabapentin, alone and in combination for neuropathic pain: a double-blind, randomised controlled crossover trial. Lancet. 2009;374(9697):1252–61. — PubMed PMID: 19796802
- Due Bruun K, Christensen R, Amris K, Vaegter HB, Blichfeldt-Eckhardt MR, Bye-Møller L, Holsgaard-Larsen A, Toft P. Naltrexone 6 mg once daily versus placebo in women with fibromyalgia: a randomised, double-blind, placebo-controlled trial. Lancet Rheumatol. 2024;6(1):e31–e39. — PubMed PMID: 38258677
- Rodríguez-Freire C, Navarrete J, Rozadilla-Sacanell A, Sanabria-Mazo JP, Del Pino-Gaya B, Borràs X, Feliu-Soler A, Luciano JV. Efficacy of Low-Dose Naltrexone in Women With Fibromyalgia Syndrome: A 12-Month Randomised, Double-Blind, Placebo-Controlled Single-Centre Clinical Trial (INNOVA Study). Eur J Pain. 2026;30(6):e70321. — PubMed PMID: 42385209
- Bested K, Jensen LM, Andresen T, Tarp G, Skovbjerg L, Johansen TSD, Schmedes AV, Storgaard IK, Madsen JS, Werner MU, Bendiksen A. Low-dose naltrexone for treatment of pain in patients with fibromyalgia: a randomized, double-blind, placebo-controlled, crossover study. Pain Rep. 2023;8(4):e1080. — PubMed PMID: 38226027
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on non-opioid chronic pain pharmacotherapy:
- PubMed: Gabapentinoids for neuropathic pain
- PubMed: Duloxetine for chronic pain and fibromyalgia
- PubMed: Milnacipran for fibromyalgia
- PubMed: TCAs for neuropathic pain
- PubMed: Low-dose naltrexone and chronic pain
- PubMed: Capsaicin 8% patch for neuropathic pain
- PubMed: Topical diclofenac for osteoarthritis
- PubMed: NSAID cardiovascular and renal risk
Connections
- Pain & Allergy
- Nociceptive vs Neuropathic vs Nociplastic Pain
- Low-Dose Naltrexone for Fibromyalgia
- Chronic Pain Overview
- Fibromyalgia
- Peripheral Neuropathy
- Complex Regional Pain Syndrome
- Central Sensitization and Nociplastic Pain
- Interventional Pain — Injections, Ablations, Neuromodulation
- Pain Reprocessing Therapy and PNE
- Chronic Low Back Pain — Evidence-Based Care
- Sleep, Exercise, and Lifestyle for Chronic Pain
- Opioids for Chronic Non-Cancer Pain
- Insomnia
- Depression
- Anxiety
- Chronic Fatigue Syndrome
- Migraine
- Arthritis