⚠ Evidence warning: Clinical trials or other evidence do not support the claims that a twelve-week aerobic program shifts the brain's pain-inhibition network, that time in nature lowers stress markers, and that nearly all people who quit smoking report less pain. This page keeps it as a report of what people, websites or other media say.
Sleep, Exercise, and Lifestyle for Chronic Pain
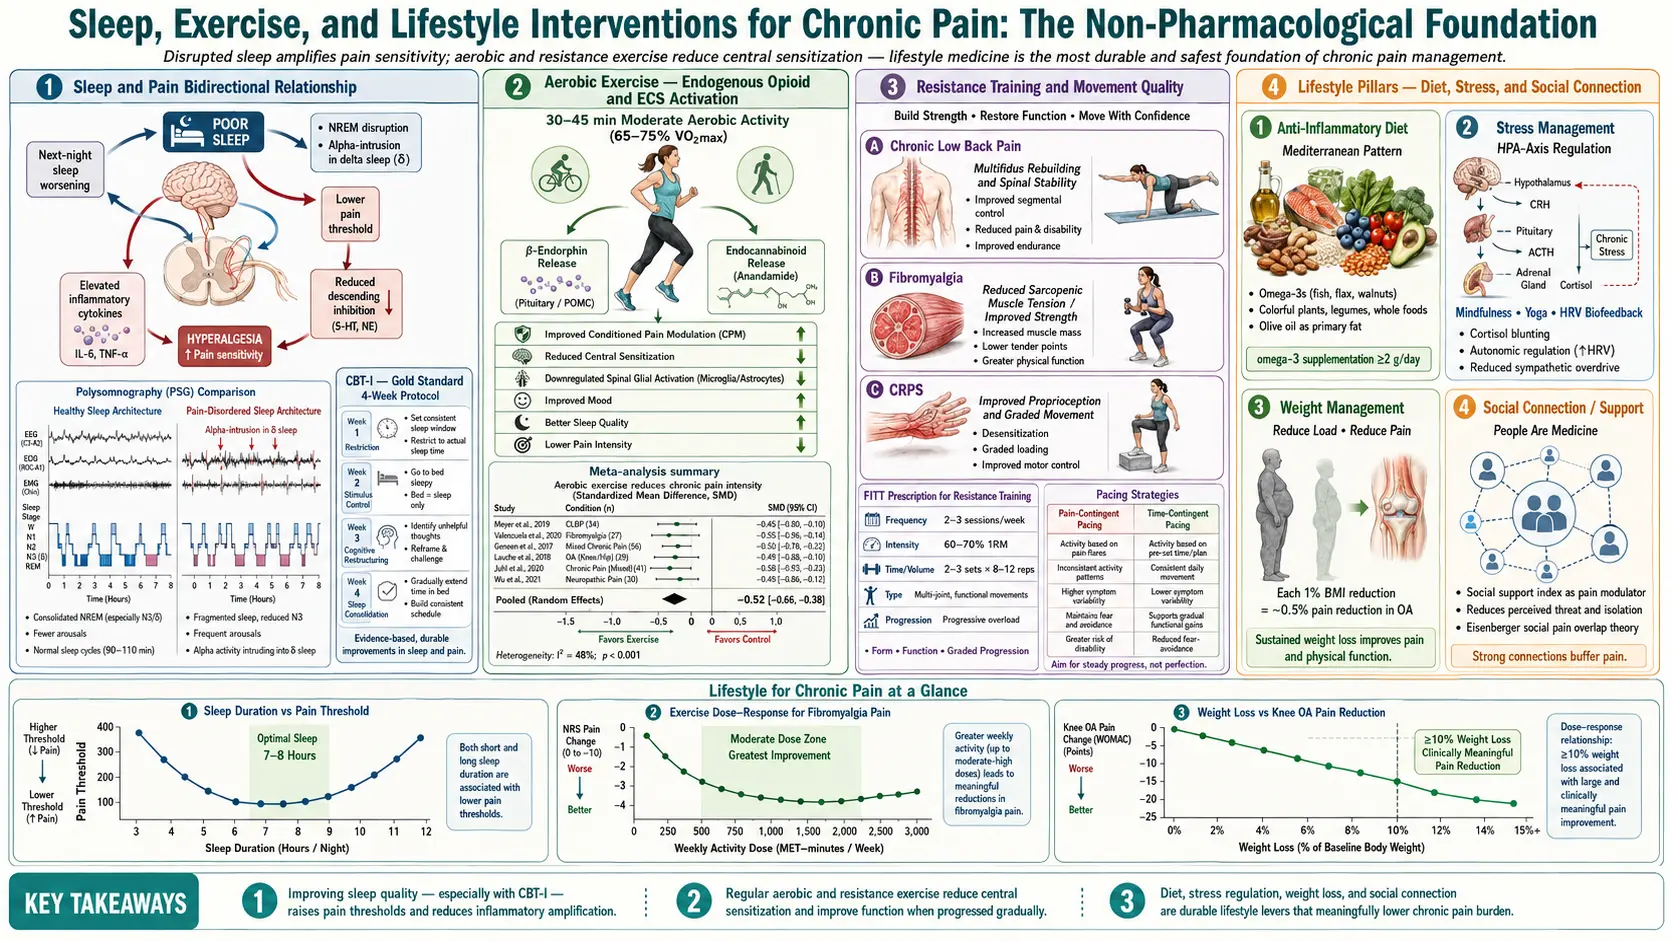
Table of Contents
- Why Lifestyle Matters More Than You Think
- The Sleep-Pain Loop — One Bad Night Costs You the Next Day
- Cognitive Behavioral Therapy for Insomnia (CBT-I) — The Evidence-Based Fix
- Sleep Hygiene — What Actually Helps and What Doesn't
- Exercise — The 150-Minute Threshold and Why Low Doses Still Count
- Strength Training — The Twice-a-Week Guideline Target
- Pacing and the 80/20 Rule — Breaking the Boom-Bust Cycle
- Mediterranean Eating — Lowering Background Inflammation
- Weight, Knee Osteoarthritis, and the 1-to-4 Ratio
- Smoking and Alcohol — Two Habits That Feed Pain
- Stress, Nervous System, and Pain Volume
- Social Connection, Loneliness, and Meaning
- Putting It Together — A Realistic Week
- Key Research Papers
- Connections
- Featured Videos
Why Lifestyle Matters More Than You Think
If you have lived with chronic pain for more than a few months, you have probably been told to "eat better, sleep more, and exercise." Maybe your doctor said it in thirty seconds on the way out of the room. Maybe a well-meaning relative said it over dinner. Either way, it probably felt dismissive — as if your pain were the result of bad habits rather than a real medical condition.
It is not that simple. Chronic pain is a real neurological condition involving sensitized pathways in your spinal cord and brain (see Central Sensitization). But the research over the last fifteen years has shown something important: the day-to-day inputs your nervous system receives — sleep, movement, food, stress, connection — directly turn the pain volume knob up or down. Not metaphorically. Measurably. In a laboratory study, acute sleep deprivation lowered pain thresholds. A twelve-week aerobic exercise program can shift the brain's descending pain-inhibition network. Losing one pound is linked to four pounds less load on a bad knee with each step.
This article is not about "trying harder." It is about the specific, measurable lifestyle levers that every major pain guideline — NICE, the American College of Physicians, the U.S. Centers for Disease Control and Prevention (CDC) — now ranks alongside or above medications for long-term outcomes. These are not alternatives to medical care. They are the foundation on which medication, injections, and therapy actually work.
The Sleep-Pain Loop — One Bad Night Costs You the Next Day
Sleep and pain are locked in a two-way relationship. Pain wakes you up and fragments your sleep. Poor sleep, in turn, lowers your pain threshold the next day. The loop tightens over weeks and months until many patients cannot tell which came first.
The laboratory evidence includes work from Michael Smith's lab at Johns Hopkins. In a controlled 2007 study, 32 healthy women were followed for 7 nights: forced awakenings or restricted sleep on 3 nights, then 36 hours without sleep. Sleep deprivation had no effect on mechanical pain thresholds, but the forced-awakening group lost pain inhibition (tested with a cold-water stimulus) and gained spontaneous pain, while the restricted-sleep group did not. In other words, the body's built-in pain brakes worked worse after broken sleep, and fragmented sleep (multiple awakenings) was more pain-provoking than simply short sleep. A 2019 brain-imaging study then found that acute sleep deprivation did lower pain thresholds to temperature, amplified pain reactivity in the brain's primary sensing cortex and blunted it in the striatum and insula.
Population studies echo this. In long-term cohorts, people with chronic insomnia are roughly twice as likely to develop chronic widespread pain within the following five to ten years, independent of depression and anxiety. Among people who already have pain, sleep disturbance predicts worse pain trajectories more reliably than the initial pain severity itself.
The practical implication is uncomfortable but empowering: researchers now describe sleep as a target for pain treatment. If you have been chasing sleep with over-the-counter aids, alcohol, or cannabis and waking up groggy and still in pain, you are treating the symptom while leaving the underlying sleep architecture broken.
Cognitive Behavioral Therapy for Insomnia (CBT-I) — The Evidence-Based Fix
Cognitive Behavioral Therapy for Insomnia (CBT-I) is the first-line treatment endorsed by the American College of Physicians, the American Academy of Sleep Medicine, the European Sleep Research Society, and essentially every major guideline body. In head-to-head trials against prescription sleep medications (zolpidem, eszopiclone, trazodone), cognitive behavioral therapy for insomnia matches or beats the drugs in the short term and clearly wins at 6 and 12 months because its effects persist after treatment ends. Drugs stop working the night you stop taking them.
Cognitive behavioral therapy for insomnia is not sleep hygiene. It is a structured, usually 4-to-8-session protocol combining:
- Sleep restriction — temporarily compressing your time in bed to match your actual sleep time, which consolidates fragmented sleep. Counterintuitive and brutal in week one. Transformative by week three.
- Stimulus control — the bed is only for sleep and sex. No reading, no phone, no worrying. The method has people get up after more than twenty minutes awake.
- Cognitive restructuring — identifying and defusing the catastrophic sleep thoughts that keep you awake ("if I don't sleep now I'll be destroyed tomorrow").
- Relaxation training and sleep education — how sleep actually works, why naps sabotage nighttime sleep, how caffeine lingers.
For people with comorbid chronic pain and insomnia — the typical situation — cognitive behavioral therapy for insomnia also improves the pain, not just the sleep. Randomized trials in fibromyalgia, osteoarthritis, and chronic low back pain populations have reported pain reductions alongside sleep gains. A 2021 meta-analysis of 12 trials (762 people) measured the sizes: a large effect on sleep right after treatment (standardized difference 0.89) and a small effect on pain (0.20). At follow-up of up to 12 months the sleep benefit remained (0.56), while the pain effect was no longer significant; the probability of having less pain was 58% right after treatment and 57% at follow-up. This is why the current guideline for a patient presenting with "I can't sleep because of my pain" is cognitive behavioral therapy for insomnia first, medication second.
Talk therapies have also been compared directly. A 2022 network analysis of 16 trials (1,094 people with both insomnia and chronic pain) found that insomnia-focused therapy beat control for sleep, pain, disability and depression right after treatment, while pain-focused therapy did not beat control on any outcome. The authors caution that the trials were small with a high risk of bias.
How it is accessed. Finding a cognitive behavioral therapy for insomnia therapist is harder than finding a prescriber. Options:
- In-person — psychologists trained in behavioral sleep medicine. The Society of Behavioral Sleep Medicine keeps a directory.
- Digital cognitive behavioral therapy for insomnia — evidence-based app-delivered programs have shown results nearly matching in-person therapy in randomized trials. One of them is U.S. Food and Drug Administration-cleared and sometimes insurance-covered.
- U.S. veterans — the Department of Veterans Affairs (VA) has rolled out cognitive behavioral therapy for insomnia across its system and it is one of the most-accessed therapies in its mental health services.
- Books — self-help workbooks walk readers through a self-guided version.
Sleep Hygiene — What Actually Helps and What Doesn't
"Sleep hygiene" is the term for the checklist of habits around sleep: cool room, dark room, consistent bedtime, no caffeine after noon, no screens before bed. The uncomfortable truth is that sleep hygiene alone rarely fixes established insomnia. Trials repeatedly show it underperforms cognitive behavioral therapy for insomnia. But the habits still matter as a foundation, especially for people whose sleep is borderline rather than severely broken.
Habits commonly listed:
- Consistent wake time, seven days a week. This anchors your circadian rhythm more powerfully than bedtime does. Sleeping in on weekends resets your body clock later every time.
- Cool, dark, quiet room. A commonly cited target is around 65–68°F (18–20°C). Blackout curtains. White noise or earplugs if needed.
- Morning daylight. 10–20 minutes of outdoor light within an hour of waking is the strongest circadian signal available. More effective than any supplement.
- Caffeine cutoff by noon. Caffeine's half-life is 5–6 hours; a 3 p.m. coffee still has meaningful levels in your system at midnight.
- No large meals within three hours of bed. Reflux and digestion both fragment sleep.
Common pitfalls that actively backfire:
- Going to bed earlier because you slept badly. This increases time-in-bed-awake, which trains your brain that bed means wakefulness. Counterintuitively, a slightly later bedtime usually helps.
- Alcohol as a sleep aid. It knocks you out but destroys deep and REM sleep in the second half of the night. You wake unrefreshed.
- Long daytime naps. If you have insomnia, a nap longer than twenty minutes after 2 p.m. steals from your nighttime sleep drive.
- Clock-watching. Knowing it is 3:47 a.m. never helped anyone fall back asleep.
- Over-the-counter diphenhydramine. Strongly anticholinergic. Disrupts deep sleep architecture, causes next-day fog, and is linked to cognitive decline in older adults.
Exercise — The 150-Minute Threshold and Why Low Doses Still Count
Exercise is the single most evidence-backed non-drug intervention for nearly every chronic pain condition studied — low back pain, knee osteoarthritis, fibromyalgia, neck pain, chronic widespread pain. Cochrane reviews have covered most of these conditions. Their 2017 overview (21 reviews, 381 studies, 37,143 people) rated the evidence as low quality: most studies had fewer than 50 people and rarely followed anyone past 3 to 6 months. Exercise did not consistently change pain scores at any single point, and physical function improved more reliably (significantly in 14 reviews, mostly with small-to-moderate effects). The overview describes exercise as having few adverse events; most were soreness or muscle pain that reportedly settled within a few weeks, although only 25% of studies actively reported them. Dropout was slightly, and not significantly, higher among exercisers (82.8 against 81 per 1,000). None of the reviews assessed chronic widespread pain as a condition of its own.
The current consensus target, from WHO and nearly every pain guideline, is 150 minutes of moderate aerobic activity per week, ideally spread across most days. "Moderate" means you can talk but not sing — roughly a brisk walk, easy bike, or slow jog. That works out to about 30 minutes five days a week, or 22 minutes every day.
If 150 minutes sounds impossible right now, missing the target does not cancel the gains from smaller amounts. The dose-response curve is not linear. The biggest gains, per minute invested, come at the low end — moving from zero to 30 minutes a week of walking is statistically a bigger jump in pain and function than moving from 150 to 250. People who do any exercise have measurably better outcomes than people who do none.
A realistic ramp for someone starting from near-zero:
- Week 1–2. 5–10 minutes of easy walking, most days. That is it. You are teaching your nervous system that movement is safe, not building cardiovascular fitness yet.
- Week 3–4. 15 minutes, five days a week.
- Week 5–8. Add a "long day" of 20–25 minutes, keeping the others at 15.
- Week 9–12. Work toward 30 minutes, five days a week — the 150-minute target.
This is the same structure as beginner walk-to-run programs, and anything can be substituted — walking, swimming, stationary bike, elliptical, recumbent bike. The modality matters less than the consistency. Swimming and aquatic exercise are gold-standard for anyone with knee, hip, or back arthritis because water offloads joint pressure by 75–90 percent.
Expect a paradox in the first two to four weeks: some people, some days, the pain may briefly worsen. This is not damage — it is a sensitized nervous system recalibrating. If you start at a low enough dose and hold steady, the flare-ups settle within a few weeks and pain begins to decrease. The patients who fail are almost always the ones who did too much on day one, spiked their pain, and quit.
Strength Training — The Twice-a-Week Guideline Target
Aerobic exercise is only half of the prescription. Every major guideline now recommends resistance (strength) training at least twice a week for chronic pain patients, particularly for osteoarthritis, low back pain, and fibromyalgia. The reasons are biomechanical and neurological:
- Stronger muscles offload joints. Quadriceps strength in knee osteoarthritis, core strength in back pain, and grip strength in hand osteoarthritis all independently predict better pain and function.
- Sarcopenia (age-related muscle loss) accelerates disability. Adults lose roughly 3–8 percent of muscle mass per decade after age thirty without resistance training.
- Strength training lowers central sensitization markers in fibromyalgia trials — not as dramatically as aerobic exercise, but additively.
You do not need a gym. Bodyweight squats, wall push-ups, sit-to-stand from a chair, step-ups, and resistance bands deliver most of the benefit. Two 20-to-30-minute sessions per week, covering major muscle groups (legs, back, chest, core), is enough. Progress by adding one rep, one set, or a small increment of resistance each week — the "progressive overload" principle.
A referral to physical therapy for an initial 4–8 weeks is one starting point. A physical therapist can screen for form issues, match the program to your specific pain pattern, and get you comfortable with the movements before you continue independently.
Pacing and the 80/20 Rule — Breaking the Boom-Bust Cycle
One of the most damaging patterns in chronic pain is boom-bust cycling. On a good day, you feel better, so you catch up on everything — cleaning, errands, the yard, a long walk. You overdo it. The next two or three days you are flat on the couch, hurting worse than before. Over months, your overall activity decreases because the crashes last longer than the boom days earn.
The alternative is called pacing. The core idea is simple: a consistent 80 percent of what you think you can do on a good day, every day, with the last 20 percent left in the tank. The shorthand is the "80/20 rule of pacing."
Concretely:
- Finding a baseline. The method picks one activity (walking, standing, gardening), times how long it can be done on an average day before pain forces a break, and takes 80 percent of that.
- Holding that 80 percent even on good days. This is the hardest part. You will feel like you are "wasting" a good day. You are not — you are breaking the cycle.
- Time, not pain, as the stop signal. With a baseline of 20 minutes of standing, the person stands for 20 minutes and sits down, even if still feeling okay.
- The baseline rises by 10 percent per week once stable. Slow, steady, boring — and effective.
Pacing is the operational counterpart to graded exercise. It is also the heart of programs for myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) (see Chronic Fatigue Syndrome), where pacing is even more critical because post-exertional malaise can last days or weeks. For fibromyalgia, pacing combined with graded aerobic exercise is evidence-based (see Exercise Pacing and Graded Movement).
Mediterranean Eating — Lowering Background Inflammation
Diet is not a cure for chronic pain. But the long-term pattern of what you eat influences systemic inflammation, body weight, insulin sensitivity, and gut health — all of which feed into pain.
The dietary pattern with the strongest evidence for pain and general health outcomes is the Mediterranean diet: olive oil as the primary fat, abundant vegetables and fruit, whole grains, beans and lentils, fish two or more times a week, moderate dairy (especially yogurt and cheese), limited red meat, nuts and seeds daily, and red wine only in moderation if at all.
In trials, Mediterranean-style eating lowers C-reactive protein (CRP) — a general marker of systemic inflammation — by 15–30 percent over 6–12 months. In osteoarthritis and rheumatoid arthritis cohorts, adherence to this pattern is associated with lower pain scores and better function. In migraine, it reduces frequency. The PREDIMED trial demonstrated cardiovascular and metabolic benefits that compound over years.
The specific anti-inflammatory components that matter most:
- Omega-3 fatty acids — fatty fish (salmon, sardines, mackerel) two to three times a week, or 1–2 g daily eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA) from supplements.
- Extra-virgin olive oil — oleocanthal, a compound in this oil, has ibuprofen-like effects on the same cyclooxygenase (COX) enzymes.
- Polyphenols from colorful vegetables, berries, green tea, dark chocolate.
- Fiber — 25–35 g/day feeds gut bacteria that produce short-chain fatty acids, which are systemically anti-inflammatory.
Foods most often linked to worse outcomes:
- Ultra-processed foods. In cohort studies, high intake is independently associated with more chronic pain and worse depression — probably through inflammation, obesity, and gut dysbiosis.
- Added sugar. Drives weight gain, insulin resistance, and C-reactive protein.
- Industrial seed oils used in large amounts for frying. The omega-6 to omega-3 ratio in most Western diets is wildly skewed.
Elimination diets are marketed as pain cures — gluten-free, dairy-free, nightshade-free. They have a clear reason in specific conditions (celiac disease, true food allergy). For most chronic pain patients, restrictive diets add stress and nutritional gaps without improving pain.
Weight, Knee Osteoarthritis, and the 1-to-4 Ratio
For pain conditions involving weight-bearing joints — knee osteoarthritis, hip osteoarthritis, chronic low back pain in people with obesity — weight loss is one of the most powerful interventions available.
The landmark data come from the IDEA trial (Intensive Diet and Exercise for Arthritis), led by Stephen Messier and published in JAMA in 2013. In 454 overweight and obese adults with knee osteoarthritis aged 55 or older, the combination of diet-driven weight loss plus exercise was compared with diet alone and with exercise alone. The combined group lost on average 23 lb (10.6 kg, 11.4% of body weight) over 18 months, against 8.9 kg with diet alone and 1.8 kg with exercise alone, and showed the largest improvements in pain, function, and walking speed. The knee-load figure comes from an earlier 2005 gait-analysis study by the same lead researcher, in 142 older adults with knee osteoarthritis, which reported an association: each pound of body weight lost reduced the load on the knee by roughly four pounds per step. A 20-pound loss took about 80 pounds of cumulative load off the knee with every stride.
What this means in practice:
- Modest losses matter. 5–10 percent of body weight delivers most of the pain benefit. You do not need to reach an "ideal" body mass index (BMI).
- Diet plus exercise beats either alone. Weight loss without strength training loses muscle and weakens the joint support. Exercise without diet change rarely produces enough weight loss to matter for severe knee osteoarthritis.
- The newer glucagon-like peptide-1 (GLP-1) medications (semaglutide, tirzepatide) are changing this conversation. For patients with obesity plus knee osteoarthritis, the STEP-9 trial (2024; 407 people, 68 weeks) found that weight fell 13.7% on weekly semaglutide 2.4 mg against 3.2% on placebo, and the 0–100 knee pain score fell 41.7 points against 27.5. Both groups also received counseling on physical activity and a reduced-calorie diet. These drugs are expensive. Side effects led 6.7% on semaglutide and 3.0% on placebo to stop permanently, most often because of gastrointestinal disorders; serious adverse events were similar in the two groups.
This is not about shaming body size. Plenty of people with chronic pain are not overweight. But if you have knee, hip, or lumbar osteoarthritis and excess weight, the mechanical math is unforgiving — and unusually responsive to change.
Smoking and Alcohol — Two Habits That Feed Pain
Smoking is a chronic pain risk factor. It is associated with higher rates of chronic low back pain, fibromyalgia, rheumatoid arthritis, and post-surgical pain. The mechanisms are multiple: nicotine directly sensitizes pain pathways, smoking reduces blood flow to spinal discs, and tobacco smoke is pro-inflammatory across nearly every tissue. Smokers also metabolize some pain medications (including opioids) faster and get less relief per dose.
Nicotine is a tricky drug for pain because acute nicotine can temporarily reduce pain — which is why smokers often say a cigarette "takes the edge off." But chronically, nicotine upregulates pain signaling. The withdrawal-use cycle makes baseline pain worse. Patients who quit smoking, with adequate nicotine-replacement support during the transition, almost uniformly report improvement in pain over 3–12 months.
If you smoke and have chronic pain, quitting is arguably one of the highest-leverage interventions available. Quit programs combine nicotine replacement, varenicline or bupropion, and behavioral support (quitlines, apps, groups). Some practitioners describe waiting until a major pain flare has settled before quitting.
Alcohol is more nuanced. Moderate intake is not strongly linked to chronic pain. But alcohol devastates sleep architecture: it shortens REM sleep, suppresses deep slow-wave sleep in the second half of the night, and fragments overall sleep. Because sleep is a core pain driver, any meaningful alcohol use (more than one drink a few times a week) commonly worsens pain through the sleep pathway.
Alcohol also interacts with many pain medications — benzodiazepines, opioids, gabapentinoids, and even over-the-counter acetaminophen (liver toxicity). If you are using alcohol to cope with pain or to sleep, it is one of the most common reversible causes of stalled treatment.
Stress, Nervous System, and Pain Volume
Chronic stress keeps the sympathetic nervous system (the fight-or-flight branch) persistently activated, which turns up the pain amplifier in the spinal cord and brain. Cortisol dysregulation, muscle guarding, shallow breathing, and reduced heart-rate variability all feed the pain loop. This is not psychological weakness — it is measurable physiology.
The evidence-based stress tools for pain:
- Mindfulness-Based Stress Reduction (MBSR) — 8-week group program developed by Jon Kabat-Zinn. Randomized trials in chronic low back pain, fibromyalgia, and mixed chronic pain show moderate but durable reductions in pain interference and catastrophizing.
- Paced breathing. 5–6 breaths per minute (roughly 5 seconds in, 5 seconds out) for 10 minutes daily raises heart-rate variability and downshifts the sympathetic nervous system.
- Yoga and tai chi. Both combine gentle movement, breath, and attention. Both have evidence for chronic low back pain, neck pain, and knee osteoarthritis.
- Cognitive behavioral therapy for pain — targets the thought-emotion-behavior patterns that amplify pain. See also Pain Reprocessing Therapy for a related approach.
- Time in nature. In healthy participants, a single 90-minute walk in a natural setting lowered self-reported rumination, while a 90-minute urban walk did not (2015). In a survey of 19,806 people, at least 120 minutes a week in nature was associated with reporting good health and well-being (2019). Time in nature is also described as lowering stress markers.
None of these replace medical care. All of them shift the background tone of your nervous system in a direction that makes every other treatment work better.
Social Connection, Loneliness, and Meaning
This last section may be the most uncomfortable, because it is the least controllable. But it is also among the most consistently supported in the pain literature.
Loneliness is a pain amplifier. Large cohort studies (including the English Longitudinal Study of Ageing and the U.S. Health and Retirement Study) have shown that people who report chronic loneliness have measurably higher rates of chronic pain, slower recovery from acute pain, and higher use of pain medications — independent of depression. Functional magnetic resonance imaging (fMRI) work by Naomi Eisenberger at UCLA showed that social rejection activates overlapping brain regions with physical pain, often summarized as the brain processing "I am alone and unsupported" through the same circuitry that processes tissue injury. Later work disputes this: a 2014 study of 60 participants found separate brain patterns for pain and for rejection despite common activity at the gross anatomical level, and concluded that rejection does not co-opt pain circuitry.
The flip side: social connection and purpose measurably buffer pain. Patients with strong support networks report lower pain at equivalent disease severity. Support groups for specific conditions (fibromyalgia, Ehlers-Danlos syndrome, complex regional pain syndrome) improve coping and reduce catastrophizing. Having a reason to get out of bed — work, caregiving, a hobby, a community role — predicts better function than pain severity alone.
Moves people with chronic pain describe:
- Reaching out to one person a week you have drifted from. A text, a short call, a coffee. Small doses add up.
- Finding people with the same condition. Online communities for a specific condition (discussion forums, social media groups moderated by clinicians, patient nonprofits) reduce the isolation of being misunderstood.
- Purposeful work or volunteering — even small amounts — is strongly protective. It gives the nervous system a reason to show up.
- Full retreat. Chronic pain often shrinks social life. That shrinkage then amplifies pain.
Putting It Together — A Realistic Week
None of this works if you try to do it all on Monday. A realistic starting plan for someone overwhelmed:
- Month 1. One habit. This plan starts with sleep — a consistent wake time, caffeine capped at noon, 10 minutes of morning daylight.
- Month 2. Daily walking, starting at 5–10 minutes and building 10 percent a week.
- Month 3. Twice-weekly strength work (bodyweight or bands), with a physical therapy referral as one option.
- Month 4. One meal a day shifted toward Mediterranean pattern — more vegetables, olive oil, beans; fewer ultra-processed foods.
- Month 5. A stress tool — mindfulness-based stress reduction, 10 minutes of paced breathing, yoga class, a cognitive behavioral therapist.
- Month 6. Smoking, alcohol, or social isolation, if any apply.
Six months. One thing at a time. This is the pattern that produces durable change. Trying to overhaul everything at once is the same boom-bust trap that drives pain flares — just at the lifestyle level.
Key Research Papers
- Smith MT, Edwards RR, McCann UD, Haythornthwaite JA. The effects of sleep deprivation on pain inhibition and spontaneous pain in women. Sleep. 2007;30(4):494-505. — doi:10.1093/sleep/30.4.494
- Messier SP, et al. Effects of intensive diet and exercise on knee joint loads, inflammation, and clinical outcomes among overweight and obese adults with knee osteoarthritis: the IDEA randomized clinical trial. JAMA. 2013. — doi:10.1001/jama.2013.277669
- Qaseem A, et al. Management of chronic insomnia disorder in adults: a clinical practice guideline from the American College of Physicians. Ann Intern Med. 2016. — doi:10.7326/M15-2175
- Geneen LJ, et al. Physical activity and exercise for chronic pain in adults: an overview of Cochrane reviews. Cochrane Database Syst Rev. 2017. — doi:10.1002/14651858.CD011279.pub3
- Estruch R, et al. Primary prevention of cardiovascular disease with a Mediterranean diet (PREDIMED). N Engl J Med. 2018. — doi:10.1056/NEJMoa1800389
- Bliddal H, et al. Once-weekly semaglutide in persons with obesity and knee osteoarthritis (STEP-9). N Engl J Med. 2024. — doi:10.1056/NEJMoa2403664
- Finan PH, Goodin BR, Smith MT. The association of sleep and pain: an update and a path forward. J Pain. 2013. — doi:10.1016/j.jpain.2013.08.007
- Eisenberger NI, Lieberman MD, Williams KD. Does rejection hurt? An fMRI study of social exclusion. Science. 2003. — doi:10.1126/science.1089134
- Krause AJ, Prather AA, Wager TD, Lindquist MA, Walker MP. The Pain of Sleep Loss: A Brain Characterization in Humans. J Neurosci. 2019;39(12):2291-2300. — PubMed PMID: 30692228
- Selvanathan J, Pham C, Nagappa M, et al. Cognitive behavioral therapy for insomnia in patients with chronic pain - A systematic review and meta-analysis of randomized controlled trials. Sleep Med Rev. 2021;60:101460. — PubMed PMID: 33610967
- Enomoto K, Adachi T, Fujino H, Kugo M, Tatsumi S, Sasaki J. Comparison of the effectiveness of cognitive behavioral therapy for insomnia, cognitive behavioral therapy for pain, and hybrid cognitive behavioral therapy for insomnia and pain in individuals with comorbid insomnia and chronic pain: A systematic review and network meta-analysis. Sleep Med Rev. 2022;66:101693. — PubMed PMID: 36410076
- Messier SP, Gutekunst DJ, Davis C, DeVita P. Weight loss reduces knee-joint loads in overweight and obese older adults with knee osteoarthritis. Arthritis Rheum. 2005;52(7):2026-2032. — PubMed PMID: 15986358
- Bratman GN, Hamilton JP, Hahn KS, Daily GC, Gross JJ. Nature experience reduces rumination and subgenual prefrontal cortex activation. Proc Natl Acad Sci U S A. 2015;112(28):8567-8572. — PubMed PMID: 26124129
- White MP, Alcock I, Grellier J, et al. Spending at least 120 minutes a week in nature is associated with good health and wellbeing. Sci Rep. 2019;9(1):7730. — PubMed PMID: 31197192
- Woo CW, Koban L, Kross E, et al. Separate neural representations for physical pain and social rejection. Nat Commun. 2014;5:5380. — PubMed PMID: 25400102
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on sleep, exercise, and lifestyle approaches to chronic pain:
- PubMed: Sleep deprivation and pain threshold
- PubMed: CBT-I for comorbid chronic pain and insomnia
- PubMed: Aerobic exercise dose-response in chronic pain
- PubMed: Resistance training in fibromyalgia and osteoarthritis
- PubMed: Activity pacing for chronic pain
- PubMed: Mediterranean diet, CRP, and pain
- PubMed: Weight loss and knee osteoarthritis joint load
- PubMed: Smoking as a chronic pain risk factor
- PubMed: Loneliness, social isolation, and chronic pain
- PubMed: Mindfulness and MBSR for chronic pain
Connections
- Pain & Allergy
- Chronic Fatigue Syndrome
- Exercise Pacing and Graded Movement
- Central Sensitization and Nociplastic Pain
- Pain Reprocessing Therapy and PNE
- Chronic Low Back Pain — Evidence-Based Care
- Chronic Pain Overview
- Fibromyalgia
- Insomnia
- Non-Opioid Medications — Gabapentinoids, serotonin-norepinephrine reuptake inhibitors (SNRIs), low dose naltrexone (LDN)
- Interventional Pain — Injections, Ablations, Neuromodulation
- Nociceptive vs Neuropathic vs Nociplastic Pain
- Opioids for Chronic Non-Cancer Pain
- Complex Regional Pain Syndrome
- Sleep and Non-Restorative Sleep
- Arthritis
- Depression
- Obesity
- Sleep Hygiene