Tuberous Sclerosis Complex
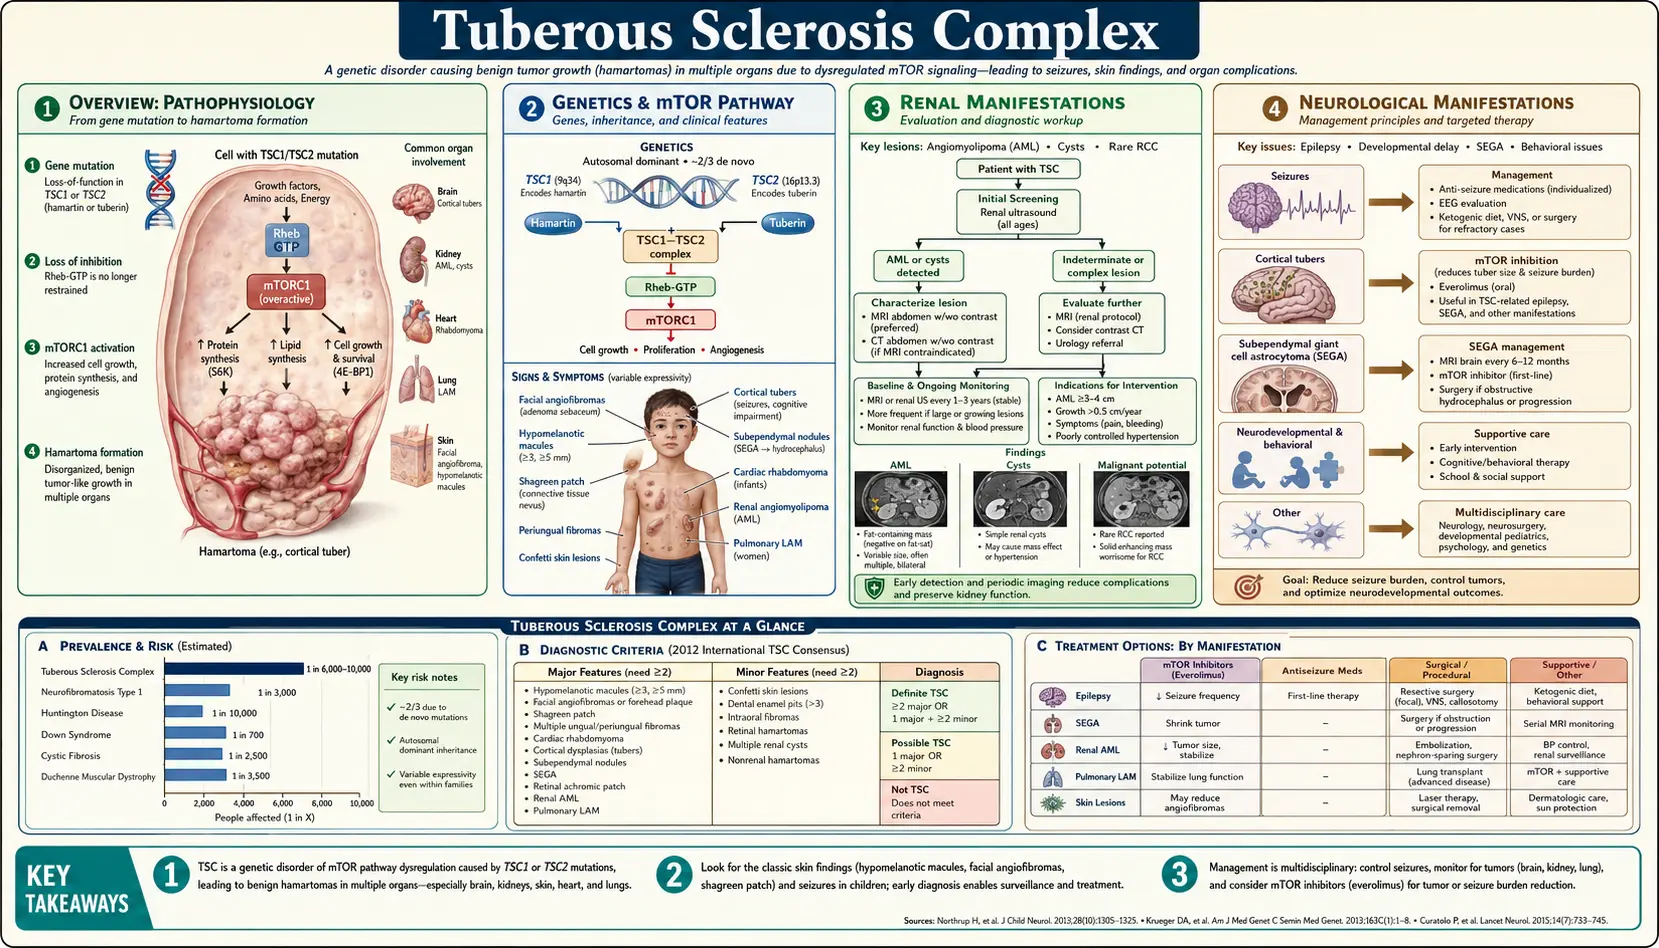
Tuberous sclerosis complex (TSC) is an autosomal dominant multisystem disorder caused by loss-of-function mutations in TSC1 or TSC2 genes, resulting in dysregulated mTORC1 signaling and benign hamartoma formation in the brain, kidneys, lungs, skin, and heart. The disorder affects approximately 1 in 6,000 individuals worldwide and is a leading genetic cause of epilepsy, intellectual disability, and renal angiomyolipomas.
Table of Contents
1. Overview
Tuberous sclerosis complex (TSC, OMIM #191100/#613254) is a rare autosomal dominant neurocutaneous syndrome characterized by formation of benign hamartomas in multiple organs. Named for the “tuber-like” calcified cortical lesions observed on pathology (first described by Désiré-Magloire Bourneville in 1880), TSC has a population prevalence of ~1 in 6,000 and affects approximately 1 million people worldwide. New mutations account for two-thirds of cases (de novo). The disorder spans a wide clinical spectrum — from minimally symptomatic to severely affected — and is the second most common genetic cause of epilepsy after Dravet syndrome. The molecular basis (TSC1/TSC2 mutations → mTORC1 hyperactivation) has enabled targeted therapy with mechanistic target of rapamycin (mTOR) inhibitors (everolimus, sirolimus), transforming management.
2. Genetics and Mechanistic Target of Rapamycin Pathway
Two causative genes: TSC1 (chromosome 9q34, encodes hamartin) and TSC2 (chromosome 16p13.3, encodes tuberin). TSC2 mutations are ~4× more common than TSC1 and correlate with more severe phenotype (lower IQ, more renal AMLs, earlier ESRD, more retinal hamartomas). De novo mutations account for ~65–70% of all TSC cases (neither parent affected). Approximately 10–15% of patients have no identifiable mutation due to somatic mosaicism, deep intronic variants, or structural rearrangements.
Molecular mechanism: Hamartin and tuberin form a functional dimer (TSC1–TSC2 complex) that acts as a GTPase-activating protein (GAP) for Rheb (Ras homolog enriched in brain). Active Rheb-GTP activates mTORC1 (mechanistic target of rapamycin complex 1), a master regulator of protein synthesis, cell growth, autophagy, and metabolism. Loss of TSC1 or TSC2 function eliminates the GAP activity → constitutively active Rheb → chronic mTORC1 hyperactivation → uncontrolled cell growth, proliferation, and survival → hamartoma formation. Second-hit somatic mutations in the remaining wild-type allele occur in hamartoma cells (loss of heterozygosity), explaining the focal nature of lesions despite a germline mutation.
3. Renal Manifestations
Renal disease is a leading cause of TSC-related mortality, affecting ~1% of TSC patients annually from life-threatening complications.
Angiomyolipomas (AMLs): Found in 55–80% of TSC patients. Benign mesenchymal tumors composed of abnormal blood vessels (tortuous, thin-walled, aneurysm-prone), smooth muscle cells, and adipose tissue. Typically bilateral and multiple. Enlarge over a lifetime at a linear growth rate of ~0.8 cm/year. Critical size threshold: AMLs ≥4 cm carry high risk of spontaneous hemorrhage (Wunderlich syndrome — retroperitoneal bleeding, potentially life-threatening). Risk factors for bleeding: size ≥4 cm, aneurysm ≥0.5 cm. Epithelioid AML variant is rare, potentially malignant, and may metastasize.
Renal cysts: Present in 20–30% of TSC patients. Typically multiple bilateral simple cysts. May be associated with a TSC2/PKD1 contiguous gene deletion syndrome (chromosome 16p13.3 deletion spanning both genes) — causes severe early-onset polycystic kidney disease mimicking ARPKD, leading to renal failure in childhood. A PKD1-adjacent TSC2 deletion is the usual suspicion when TSC comes with severe childhood polycystic disease.
Renal cell carcinoma (RCC): Risk 2–4× that of the general population. May occur at a younger age and be bilateral or multifocal. Most are clear cell or chromophobe type. It is watched for with the regular abdominal magnetic resonance imaging described under Surveillance.
Renal failure: Occurs in ~1–2% of TSC patients from AML replacement of renal parenchyma, cystic disease (TSC2/PKD1), or bilateral AML hemorrhage.
4. Neurological Manifestations
Brain involvement is the primary driver of morbidity in TSC.
Cortical tubers: Focal dysplastic cortical lesions (disorganized neurons and giant cells) resulting from impaired neuronal migration and maturation. Found in 80–90% of TSC patients. Number and location correlate with epilepsy severity and cognitive outcomes. Magnetic resonance imaging (MRI) shows T2-hyperintense cortical/subcortical lesions that are pathognomonic.
Subependymal nodules (SENs): Hamartomatous nodules along the ventricular walls that calcify with age (“candle drippings” on computed tomography, CT). Found in 80% of TSC patients. Usually asymptomatic but can evolve into SEGAs.
Subependymal giant cell astrocytomas (SEGAs): Low-grade tumors arising from SENs at the foramen of Monro. Occur in 5–20% of TSC patients. Growth can cause obstructive hydrocephalus and raised intracranial pressure — a medical emergency. Treatment: everolimus (first-line for growing SEGAs) or surgical resection.
Epilepsy: Affects 90% of TSC patients; onset in infancy in >60% (infantile spasms with hypsarrhythmia on electroencephalogram (EEG) in the first year of life in 30–35%). Infantile spasms are treated urgently with vigabatrin (first-line for TSC-associated infantile spasms, per the TSC Consensus guidelines) ± adrenocorticotropic hormone (ACTH). Drug-resistant focal epilepsy from tubers is common. Epilepsy surgery (tuber resection) and dietary therapies (ketogenic diet) benefit selected patients. Everolimus demonstrated efficacy for refractory seizures in the EXIST-3 trial.
Neurodevelopmental outcomes: Intellectual disability in ~40–50% (IQ ranges widely). Autism spectrum disorder in 40–50% — a higher rate than any other single-gene cause of autism. Attention-deficit/hyperactivity disorder (ADHD), anxiety, and sleep disorders are common. The TSC-Associated Neuropsychiatric Disorders (TAND) framework guides structured assessment.
Treating before seizures start: the US PREVeNT trial tested whether giving vigabatrin to infants with TSC before seizures could prevent intellectual disability and autism. Of 84 infants enrolled, 65 completed assessments to 36 months. There were no significant differences in development or autism outcomes between the treatment groups; 31% of the 58 children with a final rating were rated as having autism, and no child without epilepsy was diagnosed with autism (O’Kelley 2025). The authors note that early seizure detection, closer follow-up in the trial and the pandemic may have affected the result.
5. Dermatological Manifestations
Skin findings are often the first clinical sign leading to a TSC diagnosis.
Hypomelanotic macules (“ash-leaf spots”): Oval or lance-ovate hypopigmented patches (3–15 mm), present at birth in >90% of TSC patients. Best visualized under Wood’s lamp (ultraviolet (UV) light). Three or more hypomelanotic macules constitute a major diagnostic criterion.
Facial angiofibromas: Reddish-brown papules distributed symmetrically across the nose, cheeks, and nasolabial folds (“butterfly rash”). Present in 75% of patients, typically appearing in childhood (ages 2–5). Composed of fibrous tissue and ectatic blood vessels — not acne. Can cause significant cosmetic distress. Topical rapamycin (sirolimus) reduces angiofibromas in randomized controlled trials (RCTs), including the TREATMENT trial (Koenig 2018) and a sirolimus gel trial (Wataya-Kaneda 2018). In TREATMENT, 179 patients applied 1% rapamycin, 0.1% rapamycin or a plain base (vehicle) every night for 6 months: photos were rated “better” for 81.8% on 1% rapamycin, 65.5% on 0.1% and 25.5% on vehicle, with most of the improvement in the first month. No rapamycin was measurable in the blood, and drug-related side effects (skin discomfort or pain, itching, redness, irritation) each occurred in 10% or fewer and were nearly all mild.
Shagreen patches: Connective tissue nevi — irregularly surfaced, skin-colored plaques on the lower back or lumbosacral region with an “orange peel” or “leather” texture. Present in 20–30% of patients.
Ungual (periungual) fibromas (Koenen tumors): Flesh-colored fibrous outgrowths from the nail beds of fingers or toes. Develop in adolescence or adulthood, found in 15–20% of patients. Pathognomonic when present.
Confetti lesions: Multiple small (1–3 mm) hypopigmented macules on the extremities; present in ~10% of patients.
Fibrous cephalic plaques: Irregular, raised, skin-colored to yellowish plaques on the forehead or scalp.
6. Pulmonary Manifestations (LAM)
Lymphangioleiomyomatosis (LAM): Proliferation of abnormal TSC2-mutant smooth muscle-like LAM cells throughout the lung parenchyma. LAM occurs virtually exclusively in females. In a review of chest CT scans of 101 women with TSC at one US clinic (Cudzilo 2013), 47.5% met criteria for LAM; prevalence was 27% under age 21 and 81% over age 40, rising about 8% a year, and the authors concluded that most women with TSC eventually develop cystic changes consistent with LAM. It is characterized by progressive bilateral cystic lung destruction and presents with progressive dyspnea on exertion, recurrent pneumothorax (hallmark — occurring in 50–70% of symptomatic LAM patients), and chylous pleural effusions.
Imaging: High-resolution CT (HRCT) shows multiple bilateral thin-walled cysts throughout the lungs, distinguishable from emphysema by their round, uniform shape and normal intervening parenchyma. Lung biopsy is not usually required if clinical and radiologic criteria are met and serum VEGF-D is ≥800 pg/mL or HMB45-positive cells are found in bronchoalveolar lavage.
Treatment: Sirolimus slows the decline in FEV1 and improves quality of life (MILES trial, McCormack et al., N Engl J Med 2011). Lung transplantation is reserved for advanced disease (LAM may recur in the donor lung). Exogenous estrogen is believed to accelerate progression.
TSC-LAM vs. sporadic LAM: Sporadic LAM (no TSC germline) arises from somatic biallelic TSC2 loss in LAM cells; it tends to present later and may be more severe.
7. Cardiac and Other Manifestations
Cardiac rhabdomyomas: Benign intracardiac hamartomas found in 50–65% of newborns with TSC, often diagnosed prenatally on fetal echocardiography. Multiple, usually located in ventricular walls. Most regress spontaneously by childhood — the majority are asymptomatic by age 6. Fetal arrhythmia or hydrops may occur in rare cases with massive tumors. Wolff-Parkinson-White (WPW) pattern or other arrhythmias may occur if tumors involve the conduction system. Prenatal diagnosis of multiple cardiac rhabdomyomas is a common reason for TSC genetic testing.
Hepatic angiomyolipomas: Similar to renal AMLs; present in ~15% of TSC patients. Usually asymptomatic and rarely require intervention.
Bone cysts and sclerotic lesions: Incidental finding on imaging in >50% of patients; rarely symptomatic.
Retinal astrocytic hamartomas: Present in 30–50% of TSC patients. Usually asymptomatic and rarely affect vision. Mulberry-like calcified nodules near the optic disc, or flat semitransparent lesions. Calcified forms are pathognomonic.
Aortic aneurysm: Rare association, particularly in TSC2 patients.
8. Diagnosis
Clinical diagnostic criteria were set by the 2012 International TSC Consensus (Northrup and Krueger) and updated in 2021 (Northrup 2021), which made only two changes: “multiple cortical tubers and/or radial migration lines” replaced the general term “cortical dysplasias”, and sclerotic bone lesions were reinstated as a minor feature. Definite TSC = 2 major features OR 1 major + 2 minor features.
Major features (11): hypomelanotic macules ≥3 (≥5 mm); facial angiofibromas or fibrous cephalic plaque; ungual fibromas ≥2; shagreen patch; multiple retinal hamartomas; multiple cortical tubers and/or radial migration lines; subependymal nodule; subependymal giant cell astrocytoma; cardiac rhabdomyoma; lymphangioleiomyomatosis; angiomyolipomas ≥2.
Minor features (7): confetti skin lesions; dental enamel pits ≥3; intraoral fibromas ≥2; retinal achromic patch; multiple renal cysts; nonrenal hamartomas; sclerotic bone lesions.
Genetic diagnosis: A pathogenic TSC1 or TSC2 variant alone is sufficient for definitive diagnosis regardless of clinical features.
Differential diagnosis: Neurofibromatosis type 1 (café-au-lait spots, not ash-leaf; Lisch nodules; no renal AMLs), Sturge-Weber syndrome, isolated sporadic LAM, isolated renal AML.
Neuroimaging: Brain magnetic resonance imaging (cortical tubers, SENs, SEGAs). Abdominal magnetic resonance imaging (preferred over computed tomography for AML and renal cyst assessment — avoids radiation, better fat characterization). Chest HRCT (LAM screening). Echocardiography (newborns). Ophthalmology examination. Electroencephalogram. Neuropsychological assessment.
9. Treatment
Mechanistic Target of Rapamycin Inhibitors (cornerstone of targeted therapy)
Everolimus: Oral mechanistic target of rapamycin inhibitor. U.S. Food and Drug Administration-approved for: (1) growing SEGA — EXIST-1 trial: in 35% of patients on everolimus the SEGA shrank by half or more, versus none on placebo; (2) renal AMLs ≥3 cm not requiring urgent surgery — EXIST-2 trial: in 42% of patients on everolimus the angiomyolipomas shrank by half or more, versus 0% on placebo; (3) refractory focal seizures — EXIST-3 trial: seizures fell by half or more in 15.1% on placebo, 28.2% at low everolimus blood levels and 40.0% at high levels, and the median drop in seizure frequency was 14.9%, 29.3% and 39.6% respectively. Dose: 4.5 mg/m² (SEGA), 10 mg/day (AML/LAM). Side effects: aphthous stomatitis, infections, hyperlipidemia, pulmonary toxicity, impaired wound healing. Tumor regrowth occurs after stopping — long-term or continuous therapy is often required.
What the pooled trials show: a 2023 Cochrane review (Sasongko) of 10 randomized trials with 1,008 people found that, with oral everolimus, more people had their kidney angiomyolipomas or SEGAs shrink by half than with placebo (high- and moderate-certainty evidence), and more had skin responses. Total side effects did not differ, but more people on everolimus needed a dose cut, a pause or withdrawal, and more reported severe side effects. In the topical studies, rapamycin applied to the skin improved facial angiofibromas more often than placebo.
Sirolimus (rapamycin): Same mechanism as everolimus. U.S. Food and Drug Administration-approved for LAM (MILES trial — stabilizes FEV1 decline). Topical sirolimus for facial angiofibromas (TREATMENT trial and a sirolimus gel trial). Used off-label for renal AMLs.
AML Management
AMLs <3 cm: surveillance with annual magnetic resonance imaging. AMLs ≥3 cm or growing: first-line everolimus (reduces need for invasive procedures). Acute hemorrhage (Wunderlich syndrome): selective arterial embolization (SAE) — embolize the feeding artery; nephron-sparing; surgery (partial nephrectomy) if embolization fails or tumor is epithelioid. Nephrectomy is avoided when possible to preserve renal function. Prophylactic embolization for AMLs ≥4 cm with aneurysm is debated; everolimus is preferred over prophylactic embolization in current guidelines.
Epilepsy
Vigabatrin is first-line for infantile spasms in TSC under the TSC Consensus guidelines. The UK Infantile Spasms Study (UKISS) was a trial of infantile spasms from any cause, not of TSC: spasms had stopped on days 13–14 in 73% of infants on hormonal treatment versus 54% on vigabatrin (Lux 2004). Standard antiseizure medications (carbamazepine, levetiracetam, lamotrigine) for ongoing seizures. Everolimus for refractory seizures. Epilepsy surgery for drug-resistant focal seizures localized to a resectable tuber. Ketogenic diet and vagus nerve stimulation are additional options.
SEGA
Everolimus is first-line for asymptomatic growing SEGA. Surgical resection is indicated for symptomatic SEGA causing acute hydrocephalus.
LAM
Sirolimus for progressive LAM (FEV1 <70% predicted or rapid decline). Supplemental oxygen as needed. Pleurodesis for recurrent pneumothorax. Lung transplantation for advanced disease.
10. Surveillance and Monitoring
The intervals below follow the International TSC Consensus (2012) recommendations. The 2021 update (Northrup 2021) put more emphasis on early screening for EEG abnormalities, on closer surveillance and management of TSC-associated neuropsychiatric disorders (TAND), and on newly approved medicines.
Renal: magnetic resonance imaging abdomen every 1–3 years (AML and cyst monitoring). Annual blood pressure and renal function tests. More frequent surveillance if AMLs are ≥3 cm, bilateral, or actively growing.
Brain: magnetic resonance imaging brain every 1–3 years in children (more frequent if SEGA is present or growing). Annual electroencephalogram if seizure control is inadequate. Neuropsychological assessment every 3 years.
Pulmonary (females ≥18 years): Baseline HRCT chest; if cysts are present, spirometry annually and HRCT every 2–3 years; measure serum VEGF-D.
Cardiac: Echocardiogram in neonates and infants; electrocardiogram (ECG) if arrhythmia symptoms develop. After rhabdomyoma regression is confirmed, cardiac surveillance can be discontinued unless arrhythmia is present.
Dermatology: Annual skin examination. Ophthalmology: Baseline and periodic retinal examination. Dentistry: Annual dental examination (enamel pits, gingival fibromas).
Neurodevelopmental (TAND): Formal assessment at key developmental stages (infancy, pre-school, school entry, adolescence, adulthood). The TAND Checklist guides primary care screening.
Key Research Papers
- Northrup H, Krueger DA; International Tuberous Sclerosis Complex Consensus Group. Tuberous sclerosis complex diagnostic criteria update: recommendations of the 2012 International Tuberous Sclerosis Complex Consensus Conference. Pediatr Neurol. 2013;49(4):243–254. — PubMed PMID: 24053982 · doi:10.1016/j.pediatrneurol.2013.08.001
- Franz DN, et al. Efficacy and safety of everolimus for subependymal giant cell astrocytomas associated with tuberous sclerosis complex (EXIST-1): a multicentre, randomised, placebo-controlled phase 3 trial. Lancet. 2013;381(9861):125–132. — PubMed PMID: 23158522 · doi:10.1016/S0140-6736(12)61134-9
- Bissler JJ, et al. Everolimus for angiomyolipoma associated with tuberous sclerosis complex or sporadic lymphangioleiomyomatosis (EXIST-2): a multicentre, randomised, double-blind, placebo-controlled trial. Lancet. 2013;381(9869):817–824. — PubMed PMID: 23312829 · doi:10.1016/S0140-6736(12)61767-X
- French JA, et al. Adjunctive everolimus therapy for treatment-resistant focal-onset seizures associated with tuberous sclerosis (EXIST-3): a phase 3, randomised, double-blind, placebo-controlled study. Lancet. 2016;388(10056):2153–2163. — PubMed PMID: 27613521 · doi:10.1016/S0140-6736(16)31419-2
- McCormack FX, et al. Efficacy and safety of sirolimus in lymphangioleiomyomatosis (MILES Trial). N Engl J Med. 2011;364(17):1595–1606. — PubMed PMID: 21410393 · doi:10.1056/NEJMoa1100391
- O’Callaghan FJ, Lux AL, Darke K, et al. The effect of lead time to treatment and of age of onset on developmental outcome at 4 years in infantile spasms: evidence from the United Kingdom Infantile Spasms Study. Epilepsia. 2011;52(7):1359–1364. — PubMed PMID: 21668442 · doi:10.1111/j.1528-1167.2011.03127.x
- Franz DN, Lawson JA, Yapici Z, et al. Adjunctive everolimus therapy for tuberous sclerosis complex-associated refractory seizures: Results from the postextension phase of EXIST-3. Epilepsia. 2021;62(12):3029–3041. — PubMed PMID: 34693520 · doi:10.1111/epi.17099
- Henske EP, et al. Tuberous sclerosis complex. Nat Rev Dis Primers. 2016;2:16035. — PubMed PMID: 27226234 · doi:10.1038/nrdp.2016.35
- Roach ES, et al. Tuberous sclerosis complex consensus conference: revised clinical diagnostic criteria. J Child Neurol. 1998;13(12):624–628. — PubMed PMID: 9881533 · doi:10.1177/088307389801301206
- Kingswood JC, Belousova E, Benedik MP, et al. Renal angiomyolipoma in patients with tuberous sclerosis complex: findings from the TuberOus SClerosis registry to increase disease Awareness. Nephrol Dial Transplant. 2019;34(3):502–508. — PubMed PMID: 29697822 · doi:10.1093/ndt/gfy063
- Dabora SL, et al. Mutational analysis in a cohort of 224 tuberous sclerosis patients indicates increased severity of TSC2, compared with TSC1, disease in multiple organs. Am J Hum Genet. 2001;68(1):64–80. — PubMed PMID: 11112665 · doi:10.1086/316951
- Bissler JJ, Kingswood JC. Renal angiomyolipomata. Kidney Int. 2004;66(3):924–934. — PubMed PMID: 15327383 · doi:10.1111/j.1523-1755.2004.00838.x
- Northrup H, Aronow ME, Bebin EM, et al. Updated International Tuberous Sclerosis Complex Diagnostic Criteria and Surveillance and Management Recommendations. Pediatr Neurol. 2021;123:50–66. — PubMed PMID: 34399110 · doi:10.1016/j.pediatrneurol.2021.07.011
- Lux AL, Edwards SW, Hancock E, et al. The United Kingdom Infantile Spasms Study comparing vigabatrin with prednisolone or tetracosactide at 14 days: a multicentre, randomised controlled trial. Lancet. 2004;364(9447):1773–1778. — PubMed PMID: 15541450 · doi:10.1016/S0140-6736(04)17400-X
- Cudzilo CJ, Szczesniak RD, Brody AS, et al. Lymphangioleiomyomatosis screening in women with tuberous sclerosis. Chest. 2013;144(2):578–585. — PubMed PMID: 23539171 · doi:10.1378/chest.12-2813
- Koenig MK, Bell CS, Hebert AA, et al. Efficacy and Safety of Topical Rapamycin in Patients With Facial Angiofibromas Secondary to Tuberous Sclerosis Complex: The TREATMENT Randomized Clinical Trial. JAMA Dermatol. 2018;154(7):773–780. — PubMed PMID: 29800048 · doi:10.1001/jamadermatol.2018.0464
- Wataya-Kaneda M, Ohno Y, Fujita Y, et al. Sirolimus Gel Treatment vs Placebo for Facial Angiofibromas in Patients With Tuberous Sclerosis Complex: A Randomized Clinical Trial. JAMA Dermatol. 2018;154(7):781–788. — PubMed PMID: 29800026 · doi:10.1001/jamadermatol.2018.1408
- Sasongko TH, Kademane K, Chai Soon Hou S, Jocelyn TXY, Zabidi-Hussin Z. Rapamycin and rapalogs for tuberous sclerosis complex. Cochrane Database Syst Rev. 2023;7(7):CD011272. — PubMed PMID: 37432030 · doi:10.1002/14651858.CD011272.pub3
- O’Kelley SE, Capal JK, McPherson TO, et al. Neurodevelopmental Outcomes From the PREVeNT Trial. Pediatr Neurol. 2025;173:88–97. — PubMed PMID: 41061327 · doi:10.1016/j.pediatrneurol.2025.09.006
PubMed Topic Searches
- PubMed: Tuberous sclerosis complex TSC1 TSC2 mTOR
- PubMed: Tuberous sclerosis renal angiomyolipoma everolimus EXIST-2
- PubMed: Tuberous sclerosis epilepsy vigabatrin infantile spasms
- PubMed: TSC lymphangioleiomyomatosis sirolimus MILES trial
- PubMed: Subependymal giant cell astrocytoma TSC everolimus EXIST-1
- PubMed: Tuberous sclerosis autism neuropsychiatric