⚠ Evidence warning: Clinical trials or other evidence do not support the claims that wheat releases histamine from mast cells, that mast-cell drugs shrink food-sensitivity lists, and that a gluten-free diet relieves fibromyalgia. This page keeps it as a report of what people, websites or other media say.
Non-Celiac Gluten Sensitivity (NCGS)
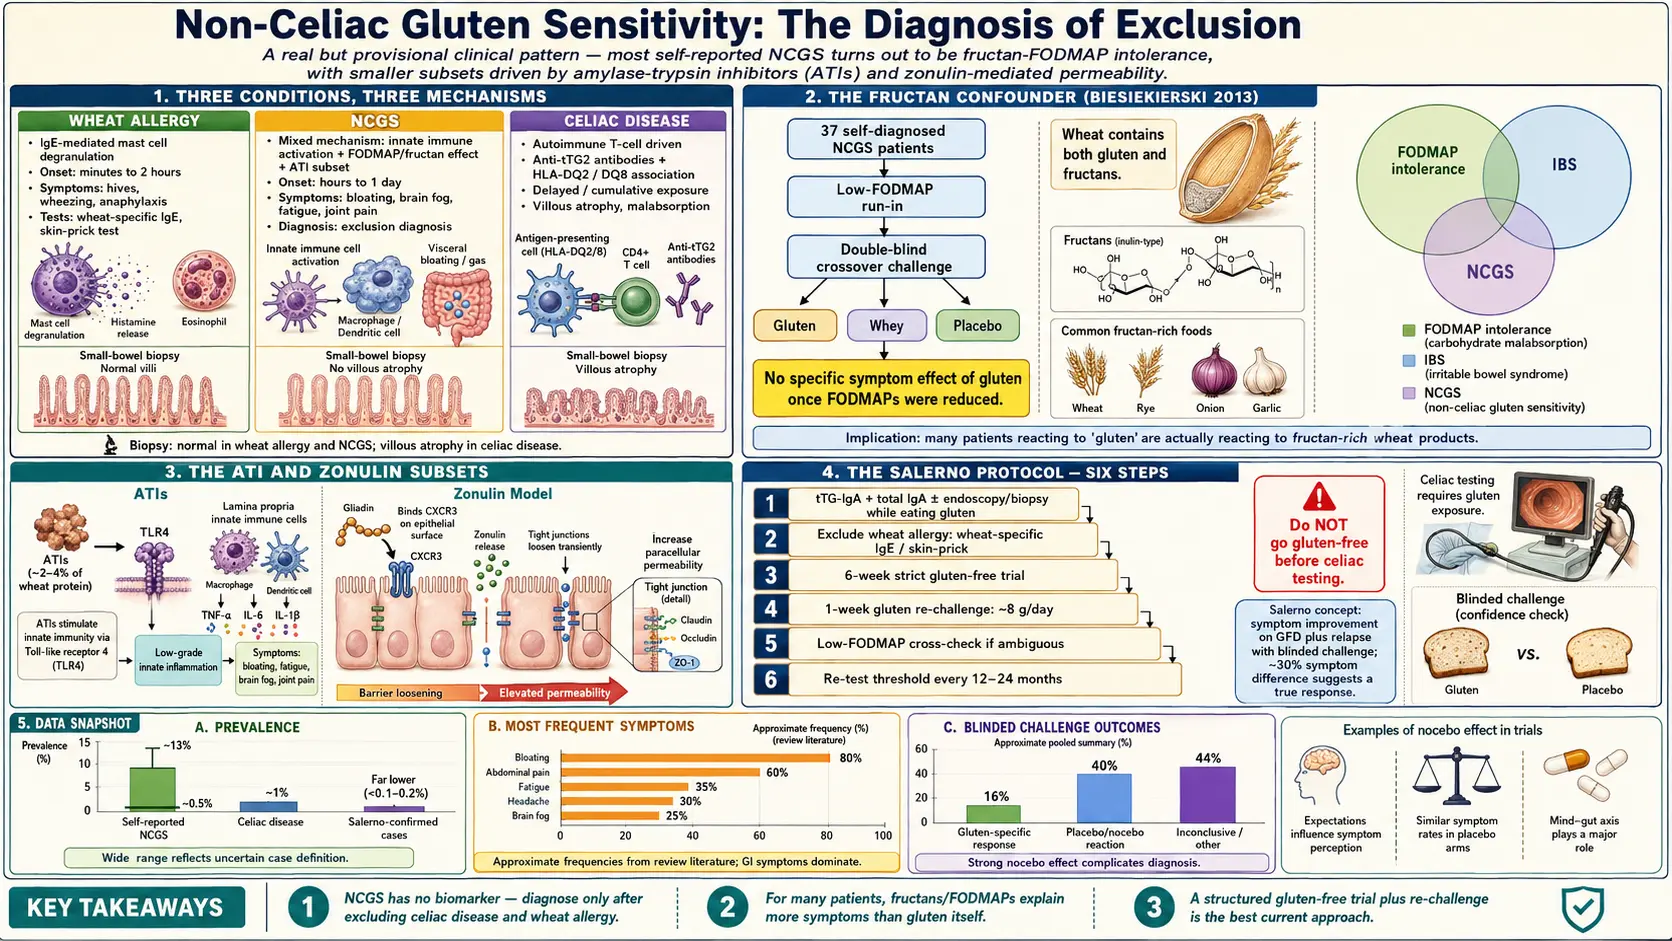
Table of Contents
- What NCGS Is (and What It Is Not)
- The Salerno Experts' Criteria (2014)
- Symptom Profile
- How Common It Is: The 0.5-to-10% Problem
- The Monash Trial and the Oslo Fructan Trial — Why "Gluten" May Not Be Gluten
- The ATI Hypothesis — A Real Non-Celiac Wheat Reaction
- Zonulin and Leaky Gut — The Emerging Subset
- How NCGS Is Diagnosed — The Salerno Protocol
- Self-Trialing Risks
- Wheat Allergy vs NCGS vs Celiac
- Why the Stakes Are Lower Than Celiac
- Overlap with Mast Cell Activation Syndrome, Hashimoto's, and Fibromyalgia
- When "Better Off Gluten" Is Really "Less Ultra-Processed Food"
- Practical Points in Summary
- Key Research Papers
- Connections
- Featured Videos
What NCGS Is (and What It Is Not)
Non-celiac gluten sensitivity is the name given to people who feel clearly worse when they eat gluten-containing foods (wheat, barley, rye), yet do not have celiac disease and do not have a classical wheat allergy. It is a diagnosis of exclusion. Your gastroenterologist cannot order a blood test to confirm it, cannot biopsy for it, and cannot point to a single validated biomarker. NCGS exists as a clinical pattern — an honest shrug that says: "Something about wheat bothers this patient, but it is not the two things we know how to measure."
For decades, skeptical physicians dismissed NCGS as anxiety or fad dieting. That has shifted. Gastroenterology now broadly accepts NCGS as a real phenomenon — but also accepts that the label is a provisional umbrella over several different biological processes, and that many people who believe they have NCGS actually have something else entirely. The practical task is to sort out which group you fall into, because the answer changes which foods matter, what can be re-introduced safely, and how strictly you have to read labels.
The clean negative definition: NCGS is not celiac disease (no tissue transglutaminase antibodies, no villous atrophy on duodenal biopsy while eating gluten), it is not wheat allergy (no wheat-specific immunoglobulin E (IgE), negative skin prick test, no hives or anaphylaxis on exposure), and it is not irritable bowel syndrome alone (though these can coexist). What remains is a patient whose gut and nervous system change state predictably on and off wheat.
The Salerno Experts' Criteria (2014)
In 2014 an international panel convened in Salerno, Italy, to agree on a minimum standard for diagnosing NCGS. The published consensus — Catassi and colleagues, 2015 — is still the reference framework and is usually called the Salerno Experts' Criteria. The criteria boil down to three requirements:
- Celiac disease must be ruled out while the patient is still eating gluten. That means tissue transglutaminase immunoglobulin A (tTG-IgA) must be negative and duodenal biopsy — if performed — must show a normal Marsh classification (Marsh 0, normal villi). A gluten-free trial before this step sabotages the workup, because both serology and biopsy can normalize within weeks off gluten.
- Wheat allergy must be ruled out. Skin prick test and wheat-specific immunoglobulin E negative.
- Symptoms must respond to gluten withdrawal and recur on gluten re-challenge in a structured way — ideally double-blind and placebo-controlled, though in everyday practice a careful open challenge with a symptom diary is more realistic.
The Salerno protocol also specifies a symptom-scoring instrument (a modified Gastrointestinal Symptom Rating Scale plus extra-intestinal items), a six-week gluten-free run-in, and a double-blind re-challenge: 8 g of gluten per day for one week (a dose the paper describes as close to the average Western intake of 10–15 g a day), a one-week washout on a strict gluten-free diet, then crossover to one week of placebo. The panel says the best carrier food is yet to be developed — for instance a muesli bar, bread or muffin — and that it should be free of FODMAPs. A symptom-score change of at least 30% in one to three main symptoms between arms is considered positive.
The response rule for the gluten-free phase, in plain words: the person picks one to three main symptoms and follows them through at least six weeks gluten-free. A responder has a reduction of more than 30% in those symptoms (or at least one symptom improved with no others worse) for at least half of the weekly checks, which means at least three of the six. The Salerno panel states that the diagnosis is excluded in anyone who does not improve after six weeks gluten-free. It also says the 30% threshold is somewhat arbitrary and still needs scientific validation.
Few patients ever get this full protocol outside research studies, but understanding the logic is useful — it explains why your doctor is not satisfied when you say "I just know gluten wrecks me."
Symptom Profile
NCGS symptoms fall into two camps, and most patients have some of each.
Gastrointestinal. Bloating is the near-universal complaint — a distended belly a few hours after a wheat meal, often visible enough that patients describe "pregnancy belly" or having to unbutton their pants. Abdominal pain, cramping, and altered bowel habits are common: some patients run toward diarrhea, others toward constipation, and a large subset alternate between the two. Nausea, reflux, and excess gas round out the picture. In pure form, this overlaps heavily with irritable bowel syndrome (IBS) — and that overlap is not accidental (see the Biesiekierski section below).
Extra-intestinal. This is where NCGS diverges most clearly from plain irritable bowel syndrome and becomes interesting. Reported symptoms include:
- Brain fog — slowed thinking, word-finding difficulty, a feeling of being wrapped in cotton that clears within days off gluten.
- Fatigue — disproportionate to sleep, often worse a few hours after a wheat meal.
- Headache and migraine.
- Joint and muscle pain — diffuse, migratory, without swelling or measurable inflammation.
- Dermatitis — eczema-like rash, sometimes prurigo or an urticaria-like picture (distinct from dermatitis herpetiformis, which is a celiac-specific rash).
- Anxiety and low mood — real and reproducible in some patients, likely gut-brain axis driven.
- Numbness or tingling in hands and feet in a minority.
Symptom onset is typically hours to a day after a gluten exposure and resolves within a few days off gluten. This fast-on/fast-off pattern is one reason NCGS presents differently from celiac, where damage and symptoms accumulate over months.
A 2025 single-blind crossover study compared 16 people with NCGS and 20 healthy controls on five days of muffins with 16 g of gluten a day or gluten-free muffins. Belly pain and bloating rose more in the NCGS group than in the controls whether or not the muffins held gluten, and no biological marker differed. The authors say nocebo effects (symptoms from expecting harm) may explain this.
How Common It Is: The 0.5-to-10% Problem
Prevalence estimates for NCGS range from under 1% to more than 10% of the adult population depending on how the question is asked. Self-report surveys — "Do you feel worse when you eat gluten?" — yield the 6-to-13% range. Rigorous double-blind placebo-controlled challenge studies shrink that number dramatically, often to under 20% of the self-reported group — implying a true biological NCGS prevalence closer to 1–2%.
The gap between what people report and what challenge testing confirms is wide. A 2017 analysis of 10 double-blind, placebo-controlled gluten-challenge trials (1,312 adults) found gluten-specific symptoms in only 38 of 231 people with NCGS (16%), and 40% of these subjects had a nocebo response, meaning similar or worse symptoms on placebo. A 2025 Lancet review states that about 10% of adults worldwide report gluten or wheat sensitivity, that in controlled challenge studies 16–30% of them have symptoms specifically triggered by gluten, and that the exact trigger remains unclear. Two honest interpretations coexist:
- A large fraction of self-reported NCGS is non-gluten wheat reactivity (fermentable oligosaccharides, disaccharides, monosaccharides and polyols, known as FODMAPs, or amylase-trypsin inhibitors, known as ATIs) or a nocebo/expectation effect.
- Challenge protocols are short, artificial, and probably miss real but delayed reactions.
Both are partially true. The clinical consequence is humility: if you feel better off gluten, that is meaningful, but the reason you feel better may not be gluten.
The Monash Trial and the Oslo Fructan Trial — Why "Gluten" May Not Be Gluten
The single most important study in the NCGS literature is Biesiekierski and colleagues, published in Gastroenterology in 2013, from the Monash University FODMAP research group. They took 37 patients who had already self-diagnosed as NCGS and who also met the Rome III criteria for irritable bowel syndrome, placed them on a low-FODMAP diet for two weeks, and then challenged them — double-blind, crossover — for one week each with a high-gluten diet (16 g of gluten a day), a low-gluten diet (2 g of gluten plus 14 g of whey protein a day), or a control diet (16 g of whey protein a day). Twenty-two of them then took gluten, whey or no added protein for three days.
The result surprised the field. On the low-FODMAP background, almost no one reacted specifically to gluten: gluten-specific effects appeared in only 8% of participants. Symptoms improved on the low-FODMAP run-in, then worsened to a similar degree on gluten or on whey, and an order effect was seen. The authors concluded there was "no evidence of specific or dose-dependent effects of gluten" in these patients on a low-FODMAP diet. This trial did not test fructans.
Fructans — short-chain fermentable carbohydrates concentrated in wheat, rye, onion, and garlic — were tested in a 2018 trial at Oslo University Hospital. Fifty-nine people on a self-chosen gluten-free diet ate muesli bars holding gluten (5.7 g), fructans (2.1 g) or neither for 7 days each, double-blind. Overall symptom scores averaged 33.1 on gluten, 38.6 on fructans and 34.3 on placebo. Scores were higher on fructans than on gluten, and gluten did not differ from placebo.
Wheat contains both. When a patient cuts gluten-containing grains, they simultaneously cut fructans. It has always been confounded. If the real trigger is fructans, then the correct diagnosis is irritable bowel syndrome with fructan intolerance, and the diet aimed at it is a structured low-FODMAP diet, not lifelong gluten avoidance. That distinction matters enormously — fructan tolerance can be rebuilt in stages using a reintroduction protocol, whereas people who believe themselves gluten-sensitive often police traces of gluten for life.
A practical tell: if small amounts of garlic, onion, or inulin-fortified foods also cause bloating, fructans are a strong suspect. If 100% spelt sourdough (long-fermented, naturally fructan-reduced) is tolerated while standard wheat bread is not, that also points at fructans, because long fermentation degrades fructans but does not remove gluten.
The ATI Hypothesis — A Real Non-Celiac Wheat Reaction
A smaller subset of patients appears to react to wheat even when FODMAPs are controlled. The leading candidate molecules are amylase-trypsin inhibitors (ATIs) — plant defense proteins that make up roughly 2–4% of the protein in modern wheat. Detlef Schuppan's laboratory at Johannes Gutenberg University in Mainz has shown that ATIs activate Toll-like receptor 4 (TLR4) on intestinal immune cells, triggering a low-grade innate immune response without the autoimmune T-cell cascade of celiac.
ATIs contribute to pest resistance and baking properties in wheat, which led to the idea that modern bread wheat was bred for high ATI content. Measurements of old and new wheats have not borne that out: in a 2025 study of 14 German landraces and 6 modern varieties, ATI content did not differ, and the authors concluded that landraces are unlikely to be better tolerated. A 2026 laboratory study of ATIs from 60 German wheats bred between 1891 and 2010 found no consistent difference between old and modern cultivars in their TLR4 activity. ATIs still matter because they offer a plausible mechanism distinct from both celiac and FODMAP intolerance. ATI-driven inflammation could explain the extra-intestinal symptoms — joint pain, brain fog, fatigue — that a simple FODMAP story struggles with.
ATIs are present in wheat, rye, and barley but are low in einkorn, spelt (to a lesser extent), rice, oats, and gluten-free grains. Some patients who react to modern wheat tolerate einkorn or traditional long-fermented sourdoughs, which is consistent with an ATI mechanism rather than a gluten-peptide mechanism.
Zonulin and Leaky Gut — The Emerging Subset
Alessio Fasano's group at Massachusetts General Hospital has proposed that a subset of NCGS patients show elevated serum zonulin, a regulator of intestinal tight junctions. Their own lactulose/mannitol study (Sapone and colleagues, 2011), however, did not find a leakier gut: "Unlike CD, GS is not associated with increased intestinal permeability." Permeability was in fact significantly lower in the gluten-sensitive group than in controls (P = 0.0308). In their model, gluten (specifically the gliadin peptide) binds the C-X-C chemokine receptor type 3 (CXCR3) on gut epithelial cells and transiently opens tight junctions in susceptible individuals, allowing food antigens and bacterial products into the lamina propria where they drive low-grade systemic inflammation.
A different kind of measurement did find changes in a subset. A 2016 study reported raised blood markers of bacterial exposure and gut-cell damage (soluble CD14, lipopolysaccharide-binding protein and fatty acid-binding protein 2) in people reporting wheat sensitivity, with celiac disease and wheat allergy ruled out, and these markers moved toward normal in a subgroup who stopped wheat and related cereals. So the sugar-probe permeability test found no increase, while blood markers in a subset did change. This is one of the few measurable findings in the condition.
The zonulin story is biologically appealing and fits patient reports of systemic symptoms, but the evidence is still preliminary, zonulin assays have reproducibility problems, and permeability testing is not a routine clinical tool. It is a hypothesis worth watching, not a diagnostic test worth ordering.
How NCGS Is Diagnosed — The Salerno Protocol
The sequence matters, because each step depends on the one before. The Salerno criteria and the celiac testing they rely on run in this order.
Step 1 — Celiac is ruled out first, while still eating gluten. Testing comes before any gluten is cut: tTG-IgA and total immunoglobulin A (to exclude immunoglobulin A deficiency, which invalidates the tTG test). If those are suspicious or borderline, deamidated gliadin peptide antibodies (DGP-IgG) and endomysial antibodies (EMA) are added. If any serology is positive, the next test is upper endoscopy with four to six duodenal biopsies plus one or two from the bulb while still eating gluten. See the serology article and endoscopy article. Every later step rests on this one. Going gluten-free first is the single most common mistake and it can cost a person a definitive diagnosis for years.
Step 2 — Wheat allergy is ruled out. The tests are a wheat skin prick and specific immunoglobulin E, which matter most in anyone with a history of hives, throat tightness, or exercise-induced anaphylaxis after eating wheat.
Step 3 — Structured six-week gluten-free trial. The trial means strict elimination of all wheat, barley, and rye (and contaminated oats) for six full weeks, with a daily symptom diary rated 0–10 across bloating, pain, stool form (Bristol 1–7), fatigue, brain fog, headache, joint pain, and mood. New supplements, a sudden workout plan or a low-FODMAP overlay at the same time all blur the result, because the point is to isolate the gluten variable.
Step 4 — Gluten re-challenge. After six weeks of clear benefit, gluten goes back in at roughly 8 g per day for up to a week. The Salerno protocol recommends a double-blind placebo-controlled challenge with a one-week washout and crossover; in the real world, an open challenge with the same symptom diary is what most people get. A clear recurrence of symptoms within a week supports NCGS.
Step 5 — A low-FODMAP cross-check when the result is ambiguous. When the gluten-free benefit was modest, or when garlic, onion, apples, and legumes also cause reactions, the next test is a structured low-FODMAP diet (often with a registered dietitian). When symptoms resolve on low-FODMAP regardless of gluten, the diagnosis is irritable bowel syndrome with fructan-dominant intolerance, not NCGS.
Step 6 — Re-test periodically. Unlike celiac, NCGS is not necessarily lifelong. Some people try a controlled re-introduction every 12–24 months to see whether their threshold has shifted. Some patients tolerate small amounts again, particularly if gut health is otherwise improved.
Self-Trialing Risks
The most important practical hazard: going gluten-free before celiac testing can hide celiac disease. A few weeks off gluten can normalize tTG-IgA and begin healing duodenal villi. A celiac workup after that can come back falsely normal, and a person with true celiac then walks around with ongoing silent damage — to bone density, micronutrient absorption, and long-term cancer risk — while believing they have merely "non-celiac sensitivity."
If you have already gone gluten-free and now want definitive testing, the only path is a gluten challenge: eating at least 3 g of gluten daily (one to two slices of wheat bread) before serology and biopsy. Schedules of 6–8 weeks are often described, but a shorter one can be enough: in a 2013 study of 20 adults with biopsy-proven celiac disease, a 14-day challenge at 3 g or more a day caused tissue and antibody changes in the majority, antibodies rose slightly by day 14 and markedly by day 28, and the authors concluded that many people will meet celiac diagnostic criteria after two weeks. This is miserable for someone who knows wheat makes them sick, but it is the only way to reach a diagnostic answer. An alternative in ambiguous cases is HLA-DQ2/DQ8 genetic testing — a negative result essentially excludes celiac and spares you the challenge; a positive result is consistent with celiac but does not confirm it, since 30–40% of the general population carries these haplotypes without disease. See the HLA-DQ2/DQ8 article.
Other self-trial traps:
- The "gluten-free aisle" substitution. Replacing regular bread with gluten-free bread, cookies, and pasta often adds refined starches, gums, and emulsifiers. If you feel better, it may be because you are eating less wheat-based ultra-processed food, not because gluten was the villain.
- Placebo and nocebo. Blinded challenge studies reliably show placebo responses in the 30–40% range. Expectation is powerful. This does not mean your symptoms are imaginary — it means the causal attribution may be wrong.
- Missing a real diagnosis. A gluten-free diet can mask symptoms of celiac, microscopic colitis, small intestinal bacterial overgrowth (SIBO), bile acid malabsorption, pancreatic insufficiency, lactose intolerance, or inflammatory bowel disease — each of which has specific treatments you would be delaying.
Wheat Allergy vs NCGS vs Celiac
These three conditions get collapsed in everyday speech but are biologically distinct. Knowing the differences helps you explain your situation to family, restaurants, and skeptical clinicians.
| Feature | Wheat Allergy | NCGS | Celiac Disease |
|---|---|---|---|
| Mechanism | Immunoglobulin E-mediated allergy | Innate immune / FODMAP / ATI (mixed) | Autoimmune (T-cell, tTG, HLA-DQ2/DQ8) |
| Onset after exposure | Minutes to 2 hours | Hours to a day | Days to years of cumulative damage |
| Hallmark symptoms | Hives, wheeze, swelling, anaphylaxis | Bloating, brain fog, fatigue, joint pain | Diarrhea, weight loss, deficiencies, or silent |
| Diagnostic test | Skin prick, wheat-specific immunoglobulin E | Exclusion + structured challenge | tTG-IgA, DGP, EMA, duodenal biopsy |
| Villous atrophy? | No | No | Yes (Marsh 3) |
| Cross-contamination risk | High (trace can trigger anaphylaxis) | Low (symptoms dose-dependent) | High (20 ppm threshold, silent damage) |
| Long-term complications | Anaphylaxis if not avoided | Not established either way (a 2025 review reports anemia in 15–43%) | Osteoporosis, anemia, lymphoma, infertility |
| Strict 20 ppm required? | Depends on threshold | No | Yes |
| Reintroduction possible? | Rarely, under oral immunotherapy | Yes, periodically | No, lifelong |
Why the Stakes Are Lower Than Celiac
This is one of the most important practical points in the whole conversation. NCGS, as currently understood, does not cause villous atrophy, nutrient malabsorption, demonstrable bone density loss, or the increased small-bowel lymphoma risk seen in untreated celiac disease. Long-term outcomes have not been established either way. The nearest long-term data, Lebwohl and colleagues' 2017 BMJ analysis, followed 64,714 women and 45,303 men for coronary heart disease by estimated gluten intake. It did not study gluten avoiders, villous atrophy, malabsorption, bone loss or lymphoma. It found that gluten intake was not linked to heart disease (hazard ratio 0.95, 95% confidence interval 0.88–1.02), and its authors note that avoiding gluten "may result in reduced consumption of beneficial whole grains."
One complication has been reported. A 2025 systematic review of 18 studies found anemia in 15–43% of people with non-celiac gluten sensitivity, with hemoglobin improving on a gluten-free diet. Only 6 of those studies used the Salerno criteria, and the review says their methods need to improve. The 2016 blood-marker study described in the zonulin section also found signs of gut-cell damage in a subset.
The practical implications for someone with confirmed NCGS are substantial:
- The 20 parts-per-million cross-contamination threshold that defines "gluten-free" for celiac patients is not strictly required for NCGS. Most NCGS patients tolerate trace cross-contamination without symptoms.
- Separate toasters, dedicated cutting boards, and deep cleaning of shared cookware are generally described as unnecessary for NCGS, unlike celiac.
- Restaurants that cannot guarantee a celiac-safe kitchen are generally described as workable for NCGS, as long as the dish itself is gluten-free.
- Periodic small exposures (a slice of wedding cake, a communion wafer, a bite of your kid's sandwich) are not known to accumulate long-term damage, though long-term outcomes have not been established.
- Annual serology monitoring and follow-up endoscopy belong to celiac care. NCGS has no blood test or biopsy finding to follow.
This does not make the symptoms any less real. It means that in NCGS strictness is usually set by symptoms rather than by the much higher celiac safety standard.
Overlap with Mast Cell Activation Syndrome, Hashimoto's, and Fibromyalgia
NCGS rarely travels alone. Three overlaps are worth knowing.
Mast Cell Activation Syndrome (MCAS). Wheat is a histamine liberator — it does not contain high histamine itself, but it can prompt mast cells to degranulate in susceptible people. Patients with mast cell activation syndrome often describe "gluten reactions" that on closer inspection are histamine reactions to wheat, fermented sauces, or aged cheeses. If your NCGS symptoms include flushing, itching, palpitations, or post-meal urticaria, those are the features allergists look at in a mast cell activation syndrome workup. Treatment (H1/H2 antihistamines, mast cell stabilizers) can dramatically shrink food sensitivity lists.
Hashimoto's thyroiditis. Patients with autoimmune thyroid disease often report feeling better on a gluten-free or grain-free diet. Proposed mechanisms include molecular mimicry between gliadin and thyroid peroxidase, and shared HLA-DQ2/DQ8 susceptibility. The evidence is mixed — clear for coexisting celiac (which is more common in Hashimoto's patients than in the general population), less clear for NCGS alone. Many Hashimoto's patients elect a trial elimination anyway and document the effect on thyroid peroxidase (TPO) antibodies and symptoms. See Hashimoto's thyroiditis and the AIP and gluten elimination deep dive.
Fibromyalgia and chronic fatigue. A meaningful minority of fibromyalgia patients report substantial improvement in widespread pain and fatigue on a gluten-free diet even in the absence of celiac. Small uncontrolled trials support this; rigorous blinded trials are sparse. A structured six-week trial is the usual way people test this; when no benefit appears, nothing on this evidence supports the cost of expensive branded gluten-free products.
When "Better Off Gluten" Is Really "Less Ultra-Processed Food"
Here is an uncomfortable but commonly true explanation for why people feel better on a gluten-free diet. The Standard American Diet is dominated by wheat-based ultra-processed food: breakfast cereals, packaged bread, crackers, cookies, pastries, pasta, pizza, frozen meals, fast-food buns. When you "go gluten-free" and do the job seriously, you typically replace that category with whole foods — rice, potatoes, vegetables, eggs, meat, fish, fruit — because the gluten-free processed substitutes are expensive and often unsatisfying. The actual change in your diet is not the removal of a single protein. It is the removal of a large block of refined carbohydrate, industrial emulsifiers, seed oils, and caloric density.
If that is what is really happening, two predictions follow. First, you will feel as good on a whole-food diet that includes traditionally prepared wheat (sourdough, pasta made fresh, plain bread eaten with protein and vegetables) as you do on a gluten-free diet of whole foods. Second, a diet of gluten-free packaged cookies will not feel any better than a diet of regular packaged cookies. Many patients discover this when they start eating gluten-free snack foods regularly and find their symptoms creep back.
This is not an argument against gluten avoidance — it is an argument for clean experimental design. A structured trial with a careful symptom diary that shows a clear gluten effect independent of overall diet quality is strong personal evidence. A muddy result points toward the refined-carbohydrate variable.
Practical Points in Summary
The points above, in short:
- Celiac testing comes first. It is only reliable on a gluten-containing diet.
- Wheat allergy is the next check, above all after any hives, wheeze, or throat tightness with wheat.
- A clean six-week gluten-free trial uses a daily symptom diary and keeps other variables the same.
- The re-challenge makes the diagnosis. Without the challenge step, there is a hypothesis, not a diagnosis.
- A muddy picture leads to a low-FODMAP trial. Many NCGS diagnoses are really fructan-dominant irritable bowel syndrome and respond better to a structured FODMAP reintroduction than to lifelong gluten avoidance.
- Strictness follows symptoms. NCGS is not celiac. Silent harm from trace cross-contamination has not been shown, though long-term outcomes have not been established either way. Social and travel life can follow from that.
- Tolerance can shift as gut health improves, which is why some people re-test every year or two.
- Overlapping diagnoses — mast cell activation syndrome, Hashimoto's, fibromyalgia, small intestinal bacterial overgrowth — may be the actual driver or a co-driver of symptoms.
- Gluten-free packaged food is not automatically healthier. Often it is less filling, more processed, and worse for blood sugar than a whole-food diet that includes modest amounts of traditionally prepared wheat.
Key Research Papers
- Catassi C, et al. Diagnosis of Non-Celiac Gluten Sensitivity (NCGS): The Salerno Experts' Criteria. Nutrients. 2015;7(6):4966-77. — doi:10.3390/nu7064966
- Biesiekierski JR, et al. No effects of gluten in patients with self-reported non-celiac gluten sensitivity after dietary reduction of fermentable, poorly absorbed, short-chain carbohydrates. Gastroenterology. 2013;145(2):320-8. — doi:10.1053/j.gastro.2013.04.051
- Sapone A, et al. Spectrum of gluten-related disorders: consensus on new nomenclature and classification. BMC Med. 2012;10:13. — doi:10.1186/1741-7015-10-13
- Lebwohl B, et al. Long term gluten consumption in adults without celiac disease and risk of coronary heart disease: prospective cohort study. BMJ. 2017;357:j1892. — doi:10.1136/bmj.j1892
- Skodje GI, et al. Fructan, Rather Than Gluten, Induces Symptoms in Patients With Self-Reported Non-Celiac Gluten Sensitivity. Gastroenterology. 2018;154(3):529-539. — PubMed PMID: 29102613
- Molina-Infante J, Carroccio A. Suspected Nonceliac Gluten Sensitivity Confirmed in Few Patients After Gluten Challenge in Double-Blind, Placebo-Controlled Trials. Clin Gastroenterol Hepatol. 2017;15(3):339-348. — PubMed PMID: 27523634
- Biesiekierski JR, et al. Non-coeliac gluten sensitivity. Lancet. 2025;406(10518):2494-2508. — PubMed PMID: 41138740
- Iven J, et al. Impact of Acute and Sub-Acute Gluten Exposure on Gastrointestinal Symptoms and Psychological Responses in Non-Coeliac Gluten Sensitivity: A Randomised Crossover Study. United European Gastroenterol J. 2025;13(7):1295-1306. — PubMed PMID: 40138597
- Junker Y, et al. Wheat amylase trypsin inhibitors drive intestinal inflammation via activation of toll-like receptor 4. J Exp Med. 2012;209(13):2395-408. — PubMed PMID: 23209313
- Jahn N, et al. Amylase/trypsin-inhibitor content and inhibitory activity of German common wheat landraces and modern varieties do not differ. NPJ Sci Food. 2025;9(1):24. — PubMed PMID: 39979280
- Neerukonda M, et al. In Vitro TLR4 Stimulating Bioactivities of Amylase/Trypsin-Inhibitors from Wheat (Triticum aestivum L.) Bred from 1891 to 2010. Foods. 2026;15(9):1541. — PubMed PMID: 42121484
- Sapone A, et al. Divergence of gut permeability and mucosal immune gene expression in two gluten-associated conditions: celiac disease and gluten sensitivity. BMC Med. 2011;9:23. — PubMed PMID: 21392369
- Uhde M, et al. Intestinal cell damage and systemic immune activation in individuals reporting sensitivity to wheat in the absence of coeliac disease. Gut. 2016;65(12):1930-1937. — PubMed PMID: 27459152
- Leffler D, et al. Kinetics of the histological, serological and symptomatic responses to gluten challenge in adults with coeliac disease. Gut. 2013;62(7):996-1004. — PubMed PMID: 22619366
- Correa-Ventura N. Anemia in non-celiac gluten sensitivity: a systematic review. Rev Clin Esp (Barc). 2025;225(8):502351. — PubMed PMID: 40907742
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on NCGS biology, diagnosis, and overlap with irritable bowel syndrome and autoimmune disease:
- PubMed: Non-celiac gluten sensitivity and the Salerno criteria
- PubMed: NCGS double-blind placebo-controlled challenge studies
- PubMed: Wheat fructans, FODMAPs, and IBS
- PubMed: Amylase-trypsin inhibitors, wheat, and TLR4 activation
- PubMed: Zonulin, intestinal permeability, and gluten
- PubMed: NCGS extra-intestinal symptoms and brain fog
- PubMed: Gluten-free diet and Hashimoto's thyroiditis
- PubMed: Gluten challenge protocols for celiac diagnosis
Connections
- Gastroenterology
- Celiac Disease Overview
- Gluten-Free Diet: A Practical Guide
- Celiac Serology Testing: tTG, DGP, EMA
- Endoscopy, Biopsy, and Marsh Classification
- HLA-DQ2 and HLA-DQ8 Genetic Testing
- Nutritional Deficiencies and Bone Health
- Associated Autoimmune Conditions
- Mast Cell Activation Syndrome
- Hashimoto's Thyroiditis
- AIP and Gluten Elimination
- Irritable Bowel Syndrome
- Low-FODMAP Diet for Irritable Bowel Syndrome
- Elimination Diet
- Small Intestinal Bacterial Overgrowth
- Dermatitis Herpetiformis
- Refractory Celiac and EATL