Refractory Celiac Disease and EATL
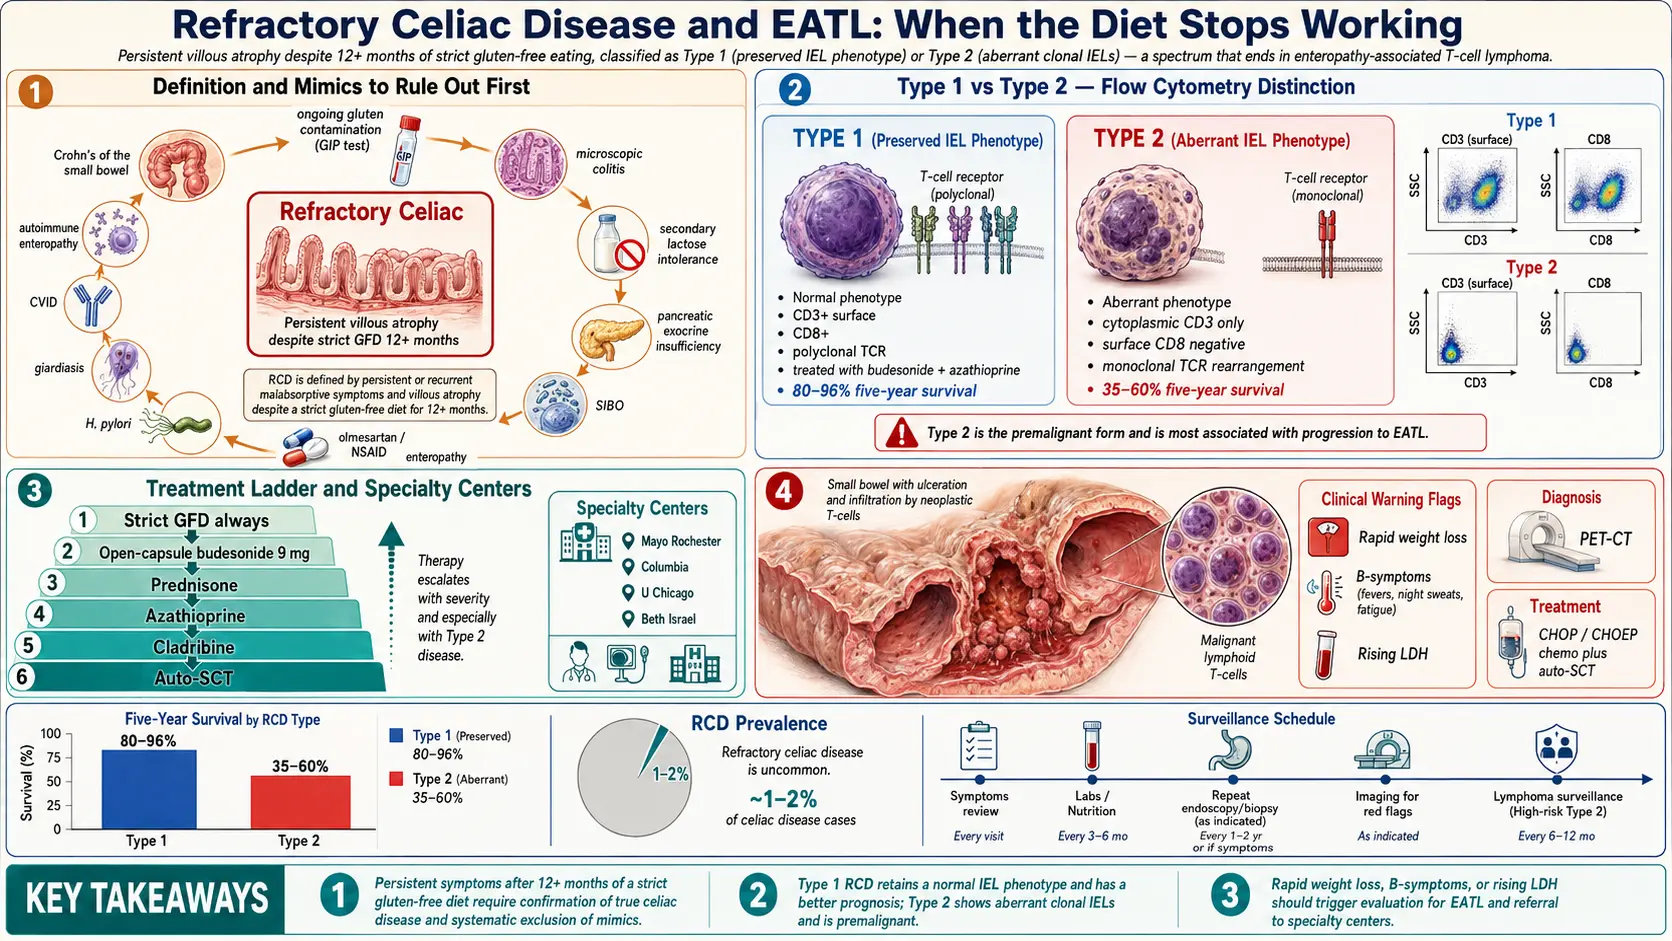
Table of Contents
- What Refractory Celiac Disease Actually Is
- How Common Refractory Celiac Disease Is
- Type 1 versus Type 2 — Why the Distinction Matters
- Conditions Ruled Out Before the Diagnosis
- The Full Workup
- Treating Type 1 Refractory Celiac
- Treating Type 2 Refractory Celiac
- EATL — Enteropathy-Associated T-Cell Lymphoma
- Prognosis — The Honest Numbers
- Specialist Centers and Second Opinions
- Monitoring Cadence
- Living With Refractory Disease
- Key Research Papers
- Connections
- Featured Videos
What Refractory Celiac Disease Actually Is
If you have celiac disease, the standard story is simple and reassuring: cut out gluten, give your small intestine six to twenty-four months to heal, and the villi grow back, the symptoms fade, and the antibody tests turn negative. The overwhelming majority of patients follow exactly this arc.
A small minority do not. Refractory celiac disease (RCD) is the formal name for the situation in which malabsorptive symptoms — diarrhea, weight loss, fatigue, anemia, low albumin — persist or come back despite at least twelve months on a strict gluten-free diet, and a repeat biopsy still shows villous atrophy. The key word is "despite." By definition, if you are still being exposed to gluten, you do not have refractory disease — you have an unhealed gut from ongoing exposure, which is a completely different problem with a much better prognosis.
Refractory celiac is a diagnosis of exclusion. Three conditions must all be true:
- A prior, well-documented celiac diagnosis — positive tissue transglutaminase IgA (tTG-IgA) or endomysial antibody (EMA) plus biopsy showing Marsh 3 villous atrophy, plus supportive HLA DQ2/DQ8 genetics.
- Persistent or recurrent malabsorptive symptoms plus ongoing villous atrophy on follow-up biopsy after twelve or more months of strict gluten-free eating.
- Gluten contamination ruled out as the cause, along with all the other mimics that can keep a celiac patient sick (listed in the next section).
If all three are met, you have refractory celiac disease. The next step is to figure out which type.
How Common Refractory Celiac Disease Is
In large referral-center series, roughly 1–2% of celiac patients eventually meet criteria for refractory disease. That number sounds small, but celiac itself affects about 1% of the general population — so we are talking about tens of thousands of people in the United States alone.
Real-world numbers are almost certainly lower than 1–2%, because most studies come from tertiary centers that receive the hardest cases. Community-practice estimates suggest the true incidence is well under 1% of all diagnosed celiacs. The overall point stands: if you are a celiac patient doing badly, the statistical odds still favor gluten contamination, a missed mimic, or a coexisting condition — not refractory disease. Clinicians investigate those first for a reason.
Healing matters for the cancer risk too. In a Swedish population study of 7,625 celiac patients who had a follow-up biopsy, 3,308 (43%) still had villous atrophy. Their risk of lymphoma-type cancers (lymphoproliferative malignancy) was 3.78 times that of the general population, compared with 1.50 times — a difference too small to be certain — in patients whose gut lining had healed; across all patients it was 2.81 times. PubMed PMID: 23922062
Type 1 versus Type 2 — Why the Distinction Matters
Refractory celiac comes in two flavors, and they are treated as different diseases because their cell biology — and their prognosis — are genuinely different.
Type 1 (RCD-I)
The intraepithelial lymphocytes (IELs) that live between your gut lining cells look normal under the pathologist's microscope and on flow cytometry. They express the full complement of surface markers a healthy T cell should: CD3 positive, CD8 positive, TCR-αβ positive. There is no clonal rearrangement of their T-cell receptor genes — the population is diverse, the way a normal immune response should be.
Type 1 behaves a lot like a stubborn, smoldering version of ordinary celiac disease. It usually responds to immunosuppression (steroids, budesonide, sometimes azathioprine), and most patients regain a near-normal life expectancy.
Type 2 (RCD-II)
The IELs are aberrant. They have lost surface CD8, lost their surface T-cell receptor, and show cytoplasmic CD3 only — a telltale pattern on flow cytometry. Their T-cell-receptor genes show a monoclonal rearrangement, meaning a single abnormal clone has expanded to dominate the IEL population.
This is no longer quite celiac disease. It is a low-grade T-cell neoplasia confined to the intestinal epithelium — a precursor state on a continuous spectrum that ends in overt T-cell lymphoma. Type 2 is the dangerous one, and it is the form that most often progresses to EATL.
The laboratory distinction between Type 1 and Type 2 is not subtle, but it requires a pathology lab that can do flow cytometry on intraepithelial lymphocytes and TCR gene rearrangement studies. Many community hospitals cannot. This is one of the main reasons refractory celiac is referred to specialty centers — getting the subtype right changes everything that follows.
Conditions Ruled Out Before the Diagnosis
Experienced gastroenterologists typically spend more time excluding mimics than confirming refractory disease. The list is long because each of these conditions is treatable, and several are far more common than true RCD.
- Ongoing gluten exposure. The single biggest cause of persistent symptoms in a diagnosed celiac. Modern testing includes gluten immunogenic peptide (GIP) assays on urine or stool — sold as home test kits. A positive GIP test on a patient who believes they are strict proves hidden exposure and reframes the entire case. A formal sit-down with a celiac-experienced registered dietitian catches contamination sources most patients miss (shared toaster, oats that are not certified gluten-free, medications with wheat starch, lip balm, communion wafers, restaurant fryer oil).
- Microscopic colitis — lymphocytic or collagenous colitis causes watery diarrhea and is more common in celiac patients than in the general population. Colonoscopy with random biopsies catches it.
- Lactose intolerance. Damaged villi cannot make lactase. Many newly diagnosed celiacs also cannot tolerate dairy for months after starting the diet, even once gluten is out.
- Pancreatic exocrine insufficiency. Celiac can impair the hormonal signals that tell the pancreas to release enzymes. A stool test, fecal elastase, screens for it — a level under 200 µg/g suggests insufficiency, and under 100 µg/g is generally read as definitive. A short trial of pancreatic enzyme replacement (pancrelipase) can be diagnostic and therapeutic.
- Small intestinal bacterial overgrowth (SIBO). Damaged small-bowel motility and architecture invite bacterial colonization. A glucose or lactulose breath test clarifies. Treatment with rifaximin often unlocks months of symptom improvement.
- Lymphocytic enteritis from other causes — medications (especially olmesartan, nonsteroidal anti-inflammatory drugs (NSAIDs), mycophenolate), Helicobacter pylori, giardiasis, common variable immunodeficiency (CVID), tropical sprue, autoimmune enteropathy.
- Other enteropathies that mimic celiac. Crohn's disease of the small bowel, eosinophilic enteritis, Whipple's disease, and autoimmune enteropathy can all look like celiac on a superficial biopsy read.
Running this exclusion list takes weeks or months. That is normal, and it is worth doing carefully — finding a treatable mimic is far better news than landing on a refractory diagnosis.
The Full Workup
Once the mimics are excluded and twelve months of documented strict gluten-free eating still leaves you with symptoms and villous atrophy, the specialty workup kicks in:
- Repeat upper endoscopy (EGD) with duodenal biopsies — at least four specimens from the distal duodenum plus one or two from the bulb. The pathologist re-confirms Marsh 3 atrophy.
- Flow cytometry on fresh IELs — this is the test that separates Type 1 (normal phenotype) from Type 2 (aberrant, CD3+ cytoplasmic, surface-CD8 negative, surface-TCR negative). It must be ordered prospectively because the sample has to reach the flow lab alive.
- T-cell receptor gene rearrangement study — a polymerase chain reaction-based test looking for a monoclonal TCRγ or TCRβ clone in the IEL population. A monoclonal result supports Type 2.
- Human leukocyte antigen (HLA) typing — specifically, DQ2.5 homozygosity (inheriting DQ2.5 from both parents) is a known risk factor for progressing to Type 2 and EATL.
- Small-bowel imaging — magnetic resonance enterography (MRE) or video capsule endoscopy to look for wall thickening, masses, strictures, or ulcerative jejunitis (deep ulcers in the jejunum that carry a very high risk of progression to lymphoma).
- Positron emission tomography/computed tomography (PET-CT) scan — reserved mostly for suspected Type 2 or any suspicion of EATL. Fluorodeoxyglucose-avid bowel wall or mesenteric lymph nodes are treated as a warning sign.
- Labs — complete blood count (CBC), comprehensive metabolic panel, albumin, ferritin, vitamin B12, folate, vitamin D, zinc, copper, magnesium, tTG-IgA (to track diet adherence), and lactate dehydrogenase (LDH) (a rough lymphoma marker).
Treating Type 1 Refractory Celiac
The good news first: Type 1 responds to treatment in roughly 75–80% of patients, and the goal is durable symptom remission plus mucosal healing.
Strict gluten-free eating continues — always. Even though the diet alone is not enough, stopping it makes everything worse. This is the foundation on which every other therapy is layered.
Corticosteroids are usually first-line. Two patterns:
- Oral prednisone at 20–40 mg daily, tapered over two to three months once symptoms settle. Effective but carries the usual steroid burden — bone loss, blood sugar rise, mood change, cataracts with long use.
- Budesonide 9 mg a day, often given as the enteric-release capsule opened (open-capsule format) so more of the drug reaches the upper small bowel rather than releasing mainly in the terminal ileum. Budesonide has a much smaller systemic steroid footprint because 80–90% is cleared on first pass through the liver. Many celiac centers now start here rather than with prednisone.
A 2024 study of 50 people with non-responsive or refractory celiac disease compared budesonide given as opened capsules (3 mg three times a day, 35 patients) with closed capsules (9 mg once a day, 16 patients). Healing of the gut lining and symptom improvement were both significantly greater with the opened capsules, which were linked to improvement on biopsy in 83% and in symptoms in 90%; side effects were mild and short-lived and were reported in 25% of both groups. PubMed PMID: 38683433
Azathioprine (2–2.5 mg/kg/day) is the usual steroid-sparing agent for patients who relapse on taper or cannot come off budesonide. Thiopurine methyltransferase (TPMT) activity is checked before starting, because people with low TPMT activity can develop profound bone-marrow suppression (myelosuppression) on azathioprine. 6-mercaptopurine is used as an alternative.
With this approach, five-year survival in Type 1 is 80–96% across published series — close to, though not identical to, the general celiac population.
Treating Type 2 Refractory Celiac
Type 2 is genuinely hard. Nothing on the shelf reliably induces deep remission, and the threat of progression to lymphoma colors every decision.
The general strategy:
- Nutritional rescue first. Many patients arrive malnourished. Albumin under 3.0, severe weight loss, or refeeding risk calls for nutritional support — sometimes enteral tube feeding with an elemental formula, occasionally parenteral nutrition.
- Open-capsule budesonide 9 mg daily is still used for symptom control, though it does not clear the aberrant clone.
- Cladribine (2-chlorodeoxyadenosine) — a purine analog chemotherapy agent given in short intravenous (IV) cycles. Published series from the Amsterdam and Paris celiac centers show roughly half of treated Type 2 patients achieve clinical and histologic response, though the aberrant IEL clone often persists. In an Amsterdam cohort of 32 Type 2 patients treated from 2000 to 2010, 18 responded well; two-year clinical, histological and immune response rates were 81%, 47% and 41%; five-year survival was 83% in responders and 22% in non-responders; and 16% progressed to EATL. PubMed PMID: 21274381
- Autologous hematopoietic stem-cell transplant (auto-HSCT) — reserved for Type 2 patients who fail cladribine. The Amsterdam group at VU University Medical Center (Al-Toma and colleagues) has the longest experience; in its 2007 series, 7 Type 2 patients underwent transplantation and no transplantation-related deaths were observed. Patient-reported outcomes can be dramatic, but the treatment carries real transplant mortality risk and is offered only at a handful of centers worldwide.
- Emerging cell-targeted therapies — anti-IL-15 monoclonal antibodies (which target the cytokine driving aberrant IEL survival), JAK inhibitors, and CD30/CD52-directed agents are in clinical trials. In the first placebo-controlled trial of an anti-IL-15 antibody (AMG 714; 28 adults with Type 2, seven doses over 10 weeks), the antibody did not reduce the abnormal lymphocytes more than placebo at week 12; diarrhea fell from 53% to 37% of treated patients while it rose from 22% to 44% on placebo. PubMed PMID: 31494097 None of these agents is standard of care yet; they are available mainly through clinical trials at specialty centers.
Five-year survival in Type 2 is reported between 35% and 60%, with the main driver being progression to EATL.
EATL — Enteropathy-Associated T-Cell Lymphoma
EATL is the feared endpoint. It is a rare but aggressive T-cell non-Hodgkin lymphoma that arises from the same aberrant intraepithelial lymphocyte population that defines Type 2 refractory disease.
How rare. The US Surveillance, Epidemiology, and End Results (SEER) cancer registry counted 463 cases from 2000 to 2020, an age-adjusted incidence rate of 0.014 per 100,000 people, rising by 2.58% a year; median survival was 6 months. PubMed PMID: 38235779 The cases are heavily concentrated in the Type 2 refractory subgroup: in an Amsterdam series, 52% of Type 2 patients developed EATL within 4 to 6 years of diagnosis. PubMed PMID: 17470479 For ordinary, diet-responsive celiac the lifetime risk is very low — reassurance, not alarm, is the right frame for most patients.
Presentation. Rapid weight loss, worsening abdominal pain, new palpable lymphadenopathy, a palpable abdominal mass, bowel obstruction, or acute perforation. Fevers and drenching night sweats (classic "B symptoms") may be present. Lactate dehydrogenase often rises. A sudden turn for the worse in a well-diagnosed celiac — especially on a Type 2 trajectory — is treated by specialists as urgent, calling for imaging and a surgical-oncology opinion.
Diagnosis is made on biopsy of the involved bowel, a surgical resection specimen, or a lymph node. PET-CT stages the disease. Bone marrow biopsy completes the workup.
Treatment combines surgical management of any obstruction or perforation, CHOP-like chemotherapy (cyclophosphamide, doxorubicin, vincristine, prednisone, sometimes with etoposide added as CHOEP), followed by consolidation autologous stem-cell transplant in patients fit enough to tolerate it. Brentuximab vedotin (anti-CD30) is used in CD30-expressing tumors.
In a Dutch national registry of all 351 patients diagnosed from 1989 to 2021, five-year survival among treated patients was 19% with limited-stage and 9% with advanced-stage disease. Two-year survival improved over time from 21% to 33%, a change short of statistical certainty (p = 0.06). Chemotherapy followed by autologous stem-cell transplant was linked to better survival (hazard ratio 0.31), adding etoposide made no measurable difference, and the authors concluded that current first-line treatment is ineffective. PubMed PMID: 39691269 An international study of 1,153 T-cell and natural-killer-cell lymphomas from 22 centers found EATL made up 5.4% of them, most often in Europe (9.1%), followed by North America (5.8%) and Asia (1.9%); median overall survival was 10 months. PubMed PMID: 21566094 The disease remains one of the most difficult lymphomas to cure.
Prognosis — The Honest Numbers
The numbers from three specialty-center cohorts — Paris (2009), Amsterdam (2007) and a US center (2009):
- Type 1 refractory celiac — 80 to 96% five-year survival (93% in Paris, 96% in Amsterdam, 80% at the US center). Most patients reach remission, and many live a normal lifespan. The main long-term burdens are steroid side effects and the modest background risk of progression.
- Type 2 refractory celiac — 44 to 58% five-year survival (44% in Paris, 58% in Amsterdam, 45% at the US center). The driver of mortality is progression to EATL, not the malabsorption itself; in the Amsterdam series 52% of Type 2 patients developed EATL within 4 to 6 years. Catching the transition early is the single most useful thing surveillance can do.
- EATL — five-year survival 8% after EATL developed from Type 2 in the Amsterdam series, and 19% (limited stage) and 9% (advanced stage) among treated patients in the Dutch national registry, where chemotherapy followed by autologous stem-cell transplant was linked to better survival.
These numbers come from specialty-center cohorts, which are inherently enriched for the sickest patients. If you are reading this because you or someone you love just heard the words "refractory celiac," please remember — most patients fall into Type 1, most respond to treatment, and "refractory" does not mean "untreatable."
Specialist Centers and Second Opinions
Refractory celiac is a disease where experience matters enormously. The diagnostic tests (IEL flow cytometry, TCR rearrangement) are not universally available, and treatment choices (cladribine, auto-HSCT, trial enrollment) require centers that see many cases a year. In the U.S. and Europe, a small number of specialist celiac centers, mostly university hospitals with dedicated celiac programs, have all of these capabilities. The research on this page comes largely from such centers:
- Specialist celiac groups in France — the French Coeliac Disease Study Group first described the aberrant clonal intraepithelial T-cell population in 2000, finding it in up to 75% of patients with refractory sprue, and a Paris group published a foundational comparison of Type 1 with Type 2 (2009).
- Specialist celiac groups in the Netherlands — the source of the published cladribine and autologous stem-cell transplant series for Type 2.
- Specialist celiac centers in the United States — university-based programs within gastroenterology departments; one US center published a clinical staging system (2009) and a widely cited review of how refractory celiac is classified and managed (Rubio-Tapia and Murray, 2010).
- Specialist centers for gluten-related disorders in the United Kingdom.
Referral to such a center is commonly considered when the local team does not offer IEL flow cytometry; when a Type 2 diagnosis is being considered; before cladribine, long-term azathioprine, or auto-HSCT; or when positron emission tomography/computed tomography or small-bowel imaging shows anything worrisome. Second opinions at celiac-focused centers are routine and welcome — many accept email-based record reviews before a patient travels.
Monitoring Cadence
Once refractory disease is diagnosed and treatment is underway, surveillance has to be tight enough to catch trouble but not so heavy that it dominates your life.
- tTG-IgA (plus total immunoglobulin A, IgA) every 3–6 months — not because it tracks the refractory disease itself, but because rising antibodies point to gluten exposure and reopen that whole question.
- Clinical visit every 3 months at a minimum during active treatment — weight, albumin, CBC, comprehensive metabolic panel, vitamin D, ferritin, B12, magnesium.
- Repeat endoscopy with biopsy + IEL flow cytometry at 6–12 month intervals while symptomatic, and whenever clinical status changes.
- Small-bowel imaging (MRE or capsule) annually in Type 2 or any patient with persistent atrophy.
- PET-CT whenever new B symptoms, a palpable mass, rising lactate dehydrogenase, or unexplained weight loss appear, rather than waiting for the annual scan.
- Bone density scan (dual-energy X-ray absorptiometry, DEXA) every 1–2 years, especially on chronic steroids.
- Registered dietitian check-ins at least annually — contamination sneaks back in over time.
Living With Refractory Disease
Refractory celiac is hard in ways ordinary celiac is not. The diet you trusted to be the cure has not been enough. Immunosuppressive drugs carry their own side effects. The words "T-cell lymphoma" float at the edge of every appointment. None of that is fair, and pretending otherwise would insult your experience.
At the same time, three things are worth holding on to:
- Most people diagnosed with refractory celiac have Type 1, which is a treatable chronic condition rather than a cancer precursor.
- Research is active. Anti-IL-15 antibodies, selective immune-cell depleters, and autologous stem-cell transplant protocols are being studied for Type 2, although the first placebo-controlled anti-IL-15 trial missed its main goal (see Treating Type 2 above).
- Specialty centers — some reachable by telehealth — offer the diagnostic tests and treatment options that a community gastrointestinal (GI) practice often lacks.
Practical points: copies of every biopsy report and flow cytometry result make a second opinion easier; the open-capsule budesonide format is a specific formulation (closed capsules release mainly further down the bowel); a food-and-symptom diary kept for two weeks before each specialist visit shows patterns rather than memories; and a GIP test in someone confident they are strict but still sick gives a useful result either way.
Key Research Papers
- Rubio-Tapia A, Murray JA. Classification and management of refractory coeliac disease. Gut. 2010;59(4):547-57. — PubMed PMID: 20332526
- Malamut G, Afchain P, Verkarre V, et al. Presentation and long-term follow-up of refractory celiac disease: comparison of type I with type II. Gastroenterology. 2009;136(1):81-90. — PubMed PMID: 19014942
- Al-toma A, Visser OJ, van Roessel HM, et al. Autologous hematopoietic stem cell transplantation in refractory celiac disease with aberrant T cells. Blood. 2007;109(5):2243-9. — doi:10.1182/blood-2006-08-042820
- Cellier C, Delabesse E, et al. Refractory sprue, coeliac disease, and enteropathy-associated T-cell lymphoma. Lancet. 2000. — doi:10.1016/s0140-6736(00)02481-8
- Al-Toma A, Verbeek WH, Hadithi M, et al. Survival in refractory coeliac disease and enteropathy-associated T-cell lymphoma: retrospective evaluation of single-centre experience. Gut. 2007;56(10):1373-8. — PubMed PMID: 17470479
- Rubio-Tapia A, Kelly DG, Lahr BD, et al. Clinical staging and survival in refractory celiac disease: a single center experience. Gastroenterology. 2009;136(1):99-107. — PubMed PMID: 18996383
- Tack GJ, Verbeek WH, Al-Toma A, et al. Evaluation of Cladribine treatment in refractory celiac disease type II. World Journal of Gastroenterology. 2011;17(4):506-13. — PubMed PMID: 21274381
- Cellier C, Bouma G, van Gils T, et al. Safety and efficacy of AMG 714 in patients with type 2 refractory coeliac disease: a phase 2a, randomised, double-blind, placebo-controlled, parallel-group study. Lancet Gastroenterology & Hepatology. 2019;4(12):960-970. — PubMed PMID: 31494097
- Saitta D, Henneken LM, Apputhurai P, et al. Budesonide induces favourable histologic and symptomatic recovery in patients with non-responsive and refractory coeliac disease when given in an open capsule format. Digestive Diseases and Sciences. 2024;69(7):2548-2557. — PubMed PMID: 38683433
- Lebwohl B, Granath F, Ekbom A, et al. Mucosal healing and risk for lymphoproliferative malignancy in celiac disease: a population-based cohort study. Annals of Internal Medicine. 2013;159(3):169-75. — PubMed PMID: 23922062
- Hujoel IA, Hujoel MLA. The rising incidence and poor outcomes of enteropathy-associated T-cell lymphoma. American Journal of Gastroenterology. 2024;119(7):1412-1416. — PubMed PMID: 38235779
- Meeuwes FO, Brink M, Plattel WJ, et al. Enteropathy-associated T-cell lymphoma: a population-based cohort study on incidence, treatment, and outcome in the Netherlands. EJHaem. 2024;5(6):1215-1222. — PubMed PMID: 39691269
- Delabie J, Holte H, Vose JM, et al. Enteropathy-associated T-cell lymphoma: clinical and histological findings from the international peripheral T-cell lymphoma project. Blood. 2011;118(1):148-55. — PubMed PMID: 21566094
PubMed Topic Searches
For further reading, the following PubMed searches return the current peer-reviewed literature on refractory celiac disease and EATL:
- PubMed: Refractory celiac disease classification and diagnosis
- PubMed: Aberrant intraepithelial lymphocytes in RCD Type 2
- PubMed: Open-capsule budesonide in refractory celiac
- PubMed: Cladribine treatment in RCD Type 2
- PubMed: Autologous HSCT in refractory celiac disease
- PubMed: Enteropathy-associated T-cell lymphoma (EATL)
- PubMed: Gluten immunogenic peptide testing (GIP)
- PubMed: HLA DQ2.5 homozygosity and refractory disease risk
- PubMed: Ulcerative jejunitis and celiac disease
- PubMed: Anti-IL-15 therapies in celiac clinical trials
Connections
- Gastroenterology
- Celiac Disease Overview
- Gluten-Free Diet: A Practical Guide
- Non-Celiac Gluten Sensitivity
- Celiac Serology Testing: tTG, DGP, EMA
- Associated Autoimmune Conditions
- Endoscopy, Biopsy, and Marsh Classification
- HLA-DQ2 and HLA-DQ8 Genetic Testing
- Nutritional Deficiencies and Bone Health
- Lymphoma
- Crohn's Disease
- Inflammatory Bowel Disease
- Small Intestinal Bacterial Overgrowth Breath Test Guide
- Anemia
- Vitamin D3
- Dermatitis Herpetiformis