⚠ Evidence warning: Clinical trials or other evidence do not support the claims that a 6-week gluten challenge at 3 g a day finds about 90% of cases, that one question prevents 90% of mis-ordered panels, that several named countries routinely skip biopsy in adults, that blood tests catch most dietary slips, and the rankings of the most common testing mistakes. This page keeps it as a report of what people, websites or other media say.
Celiac Serology Testing: tTG, DGP, EMA, and the Traps
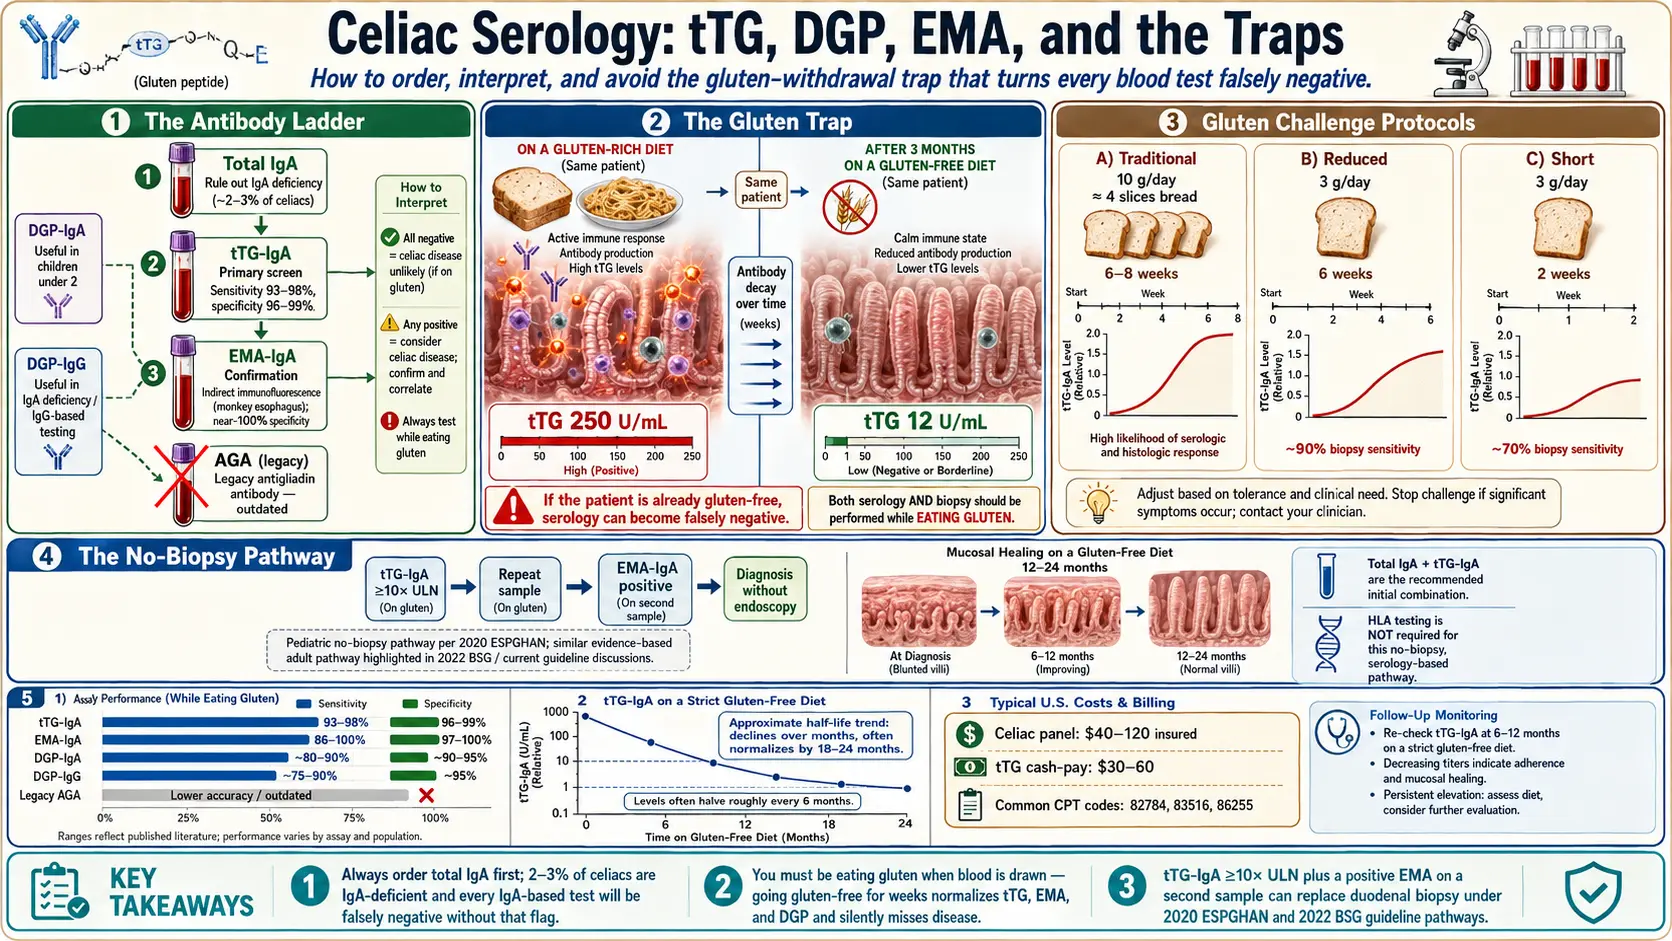
Table of Contents
- Why Getting the Order Right Matters
- Step One: Total Immunoglobulin A Is Checked First
- tTG-IgA — The Primary Screen
- EMA-IgA — The Confirmatory Test
- DGP-IgA and DGP-IgG — The Specialists' Test
- Why the Old AGA Test Is Outdated
- Titer Magnitude: When Numbers Replace Biopsy
- The Critical Trap: Tests Need Gluten in the Diet
- Gluten Challenge Protocols
- Seronegative Celiac — When Blood Tests Miss It
- Post-Diagnosis: Using tTG to Track Healing
- Home and Mail-In Test Kits
- Insurance, Coding, and Cost
- Pediatric vs Adult Panels
- Ordering Pitfalls — What Labs Actually Run
- Why a Gastroenterologist Will Not Just "Test You"
- Key Research Papers
- Connections
- Featured Videos
Why Getting the Order Right Matters
Celiac disease is one of the most under-diagnosed autoimmune conditions in medicine. Roughly 1% of the population has it, but most walk around undiagnosed for years — some for decades. The reason is almost never that the blood tests are bad. The tests are excellent. The reason is that the tests get ordered wrong, run wrong, or interpreted wrong — and that the patient often is not eating gluten when the blood is drawn, which silently destroys every result on the panel.
This article is the map. It walks through every blood test used to screen for and confirm celiac disease, in the order a smart clinician (or a smart patient advocating for themselves) would use them. It flags the traps that cause false negatives, the rules that let you skip the biopsy in certain cases, and the insurance and lab-order details that decide whether your workup costs $40 or $400.
If you read one section, read The Critical Trap: Tests Need Gluten in the Diet. That single mistake — going gluten-free before testing — is the number-one reason people get told "you don't have celiac" when they actually do.
Step One: Total Immunoglobulin A Is Checked First
Before any celiac-specific antibody is ordered, a competent workup starts with a total serum immunoglobulin A (IgA) level. Here is why.
Most celiac antibodies are immunoglobulin A class antibodies — they belong to the branch of the immune system that patrols mucosal surfaces, including the lining of the gut. That is a design feature: gluten hits the gut first, so the gut's immune system responds first, and the antibodies it makes are mostly immunoglobulin A. Unfortunately, 2–3% of people with celiac disease are selective immunoglobulin A deficient, compared to roughly 0.2% of the general population. If you are in that group, your body simply cannot produce meaningful quantities of immunoglobulin A, and every immunoglobulin A-based celiac test will come back falsely negative no matter how sick your gut is.
A total immunoglobulin A measurement costs around $10–$25 and takes a single extra tube of blood. If it comes back low (typically under 7 mg/dL for adults, lower cutoffs for kids), your clinician switches to immunoglobulin G-based celiac tests: tTG-IgG and DGP-IgG. If it is normal, you proceed with the standard immunoglobulin A panel. Skipping this step is the second most common mistake in celiac testing, after drawing blood off-gluten.
tTG-IgA — The Primary Screen
Tissue transglutaminase immunoglobulin A (tTG-IgA) is the single most important celiac test. It is the first blood test every major guideline body — the American College of Gastroenterology, the European Society for Paediatric Gastroenterology Hepatology and Nutrition (ESPGHAN), the British Society of Gastroenterology — recommends for anyone with suspected celiac disease. If you are going to order one test, this is it.
What it measures: tissue transglutaminase is the enzyme inside your intestinal lining that modifies gluten peptides after you eat them. In celiac disease, the immune system mistakenly starts producing antibodies against this enzyme. Those antibodies circulate in blood and are easy to detect with an ELISA assay.
Figures of 93–98% sensitivity (it catches most cases) and 96–99% specificity (it rarely lights up when celiac is absent) are often quoted for adults eating a normal gluten-containing diet. A 2022 pooled analysis of 113 studies, all in hospital or specialist settings, measured lower figures at the most commonly reported cut-offs: in adults, sensitivity 90.7% (95% confidence interval 87.3–93.2%) and specificity 87.4% (84.4–90.0%); in children, sensitivity 97.7% and specificity 70.2%. It stays the first-line screen in the guidelines above.
Known caveats:
- Young children under 2 sometimes mount a weaker tTG response. Pediatric panels therefore add DGP (see below).
- Mild false positives (usually 1–3× upper limit) can occur in chronic liver disease, heart failure, type 1 diabetes, and other autoimmune conditions — a reason endomysial antibody (EMA) or biopsy is used to confirm.
- The test is immunoglobulin A-based, so selective immunoglobulin A deficiency will falsely lower it. A total immunoglobulin A result shows whether this applies.
EMA-IgA — The Confirmatory Test
Endomysial antibody immunoglobulin A (EMA-IgA) is celiac serology's gold standard for specificity. It is reported as a titer on a dilution series (1:5, 1:10, 1:20, etc.) and uses an old-school immunofluorescence assay, where a technician looks through a microscope at monkey esophagus or human umbilical cord tissue and scores the pattern of antibody binding. It is labor-intensive and operator-dependent, which is why it costs more (roughly $100–$200) and is not the first-line screen.
What it buys you is near-perfect specificity — essentially 100% in experienced labs. The same 2022 pooled analysis found IgA endomysial antibody specificity of 99.6% in adults (sensitivity 88.0%) and 93.8% in children (sensitivity 94.5%), and its authors say the high adult specificity supports using it to rule celiac disease in. A positive EMA-IgA in a symptomatic patient, with a positive tTG-IgA, is so specific for celiac that under the 2020 ESPGHAN pediatric guidelines it can replace the duodenal biopsy in carefully selected cases, and British Society of Gastroenterology interim guidance opened a no-biopsy route for some adults (see Titer Magnitude).
EMA is not used in isolation. The standard workflow is: screen with tTG-IgA, and if positive (especially if borderline), confirm with EMA-IgA on the same sample or a repeat draw.
DGP-IgA and DGP-IgG — The Specialists' Test
Deamidated gliadin peptide (DGP) antibodies target a chemically modified form of gliadin — the fragment of gluten that the enzyme tissue transglutaminase has "deamidated" inside the gut wall. Think of it as the crime scene residue: if your immune system has been reacting to gluten as processed by celiac gut chemistry, you will usually have anti-DGP antibodies in your blood.
DGP has three main uses:
- Children under 2 years old. Their tTG response can be sluggish; DGP-IgG catches cases that tTG-IgA misses.
- Immunoglobulin A-deficient patients. DGP-IgG is one of the two go-to tests (along with tTG-IgG) when immunoglobulin A is unavailable.
- Suspected seronegative celiac. When a patient's symptoms scream celiac but tTG-IgA is negative, adding DGP-IgA/immunoglobulin G (IgG) occasionally catches a case that would otherwise go to biopsy without a positive antibody.
DGP is not routinely better than tTG for the average adult screen. If your lab offers a "celiac panel" that runs tTG-IgA, EMA-IgA, total immunoglobulin A, and DGP-IgG all at once, that is fine — comprehensive. If your insurer only pays for one test, tTG-IgA is still the right pick.
Why the Old AGA Test Is Outdated
Older charts sometimes still list anti-gliadin antibody (AGA) — the original celiac blood test from the 1980s. It is no longer part of the standard workup. AGA targets native (unprocessed) gliadin and lights up in a wide range of conditions, including non-celiac gluten sensitivity, wheat allergy, Crohn's disease, and healthy wheat eaters with no gut disease at all. Its specificity is poor enough that modern guidelines explicitly recommend against it.
When "AGA" or "anti-gliadin immunoglobulin G/immunoglobulin A" appears on a celiac workup in 2026, the modern replacement is DGP. Many electronic health records still carry both order sets and the defaults drift.
Titer Magnitude: When Numbers Replace Biopsy
For decades, a duodenal biopsy was mandatory to confirm celiac disease. Then in 2012, ESPGHAN changed pediatric practice: children with a tTG-IgA at or above 10 times the upper limit of normal (≥10× ULN), confirmed by a positive EMA on a second blood draw, plus HLA-DQ2 or DQ8 positivity, could be diagnosed without endoscopy. The 2020 ESPGHAN update dropped the human leukocyte antigen (HLA) requirement, further simplifying the path.
During the COVID-19 pandemic, emergency interim guidance from the British Society of Gastroenterology extended a similar option to adults: a no-biopsy diagnosis became possible for selected adults with tTG-IgA ≥10× ULN and other clinical factors. Some descriptions add a positive EMA on a second sample; a 7-year hospital review of 433 people with a positive tTG-IgA found that adding EMA changed the predictions little (high titers 95% confirmed on biopsy, low titers 75%). The American College of Gastroenterology's 2023 update still states that biopsy is required in most patients and suggests a no-biopsy strategy only in selected children. The British society published new adult guidelines in Gut in July 2026; the published summary does not state their no-biopsy criteria.
The 10-times rule has been measured in adults. A study of three groups (740 specialist-clinic patients, 532 low-suspicion endoscopy patients and 145 people with raised tTG from several countries) found that 95.2% to 100% of people at or above 10× ULN had Marsh 3 gut damage. Its sensitivity was only 30% to 54%, so many people with that damage fall below 10× ULN. In Scotland, 320 of 322 adults at or above 10× ULN who had a biopsy were diagnosed with celiac disease.
Practical takeaway: if your tTG-IgA comes back at, say, 250 U/mL on an assay whose normal is under 20 U/mL, that is a 12× ULN result. Whether the biopsy-optional pathway applies differs by region. Many countries, including the UK, the Netherlands, and parts of Scandinavia, are said to routinely skip scopes in high-titer adults now. In the U.S., biopsy remains the default but a strong case can be made.
The Critical Trap: Tests Need Gluten in the Diet
This is the most important paragraph in this article. Every celiac blood test depends on an active immune reaction to gluten. If you stop eating gluten, your tTG-IgA, EMA, and DGP levels begin to fall within weeks, and over the following months they can reach normal. In a study of 260 children on a gluten-free diet, the median time to a normal tTG was 11.7 months on one lab method (ELISA) and 14.7 months on another (chemiluminescence), and higher starting levels took longer. Once levels are normal, the tests cannot distinguish you from a healthy person. A gastroenterologist who runs celiac serology on a patient who has been gluten-free for months is running a test that can come back negative whether or not the underlying disease is there.
This happens all the time. A patient feels better after going gluten-free on their own, later asks their doctor "could I have celiac?" and gets blood drawn that same week. The result comes back negative and the patient is told they just have "gluten sensitivity." Months or years later, symptoms return, damage accumulates in the small intestine, and the real diagnosis is missed — sometimes until a vitamin deficiency or osteoporosis forces the question open again.
Because the antibodies fall once gluten stops, testing after going gluten-free can miss the disease; the tests are built for people eating gluten. For someone already gluten-free who wants testing, two choices are described: accepting that the blood work will be uninformative, or doing a gluten challenge to reactivate the antibody response.
Gluten Challenge Protocols
A gluten challenge means eating gluten deliberately, at a meaningful dose, for a defined period so that celiac serology can detect the disease if it is present. The traditional protocol, validated in research settings and still used by most U.S. academic centers:
- Dose: roughly 10 grams of gluten per day — the equivalent of about 4 slices of normal wheat bread, or 2 slices plus a bowl of pasta, daily.
- Duration: 6 to 8 weeks before blood is drawn. Some protocols go to 12 weeks if serology is still negative but suspicion is high.
- End with blood work, and a biopsy if serology is positive.
That is a brutal protocol for someone whose symptoms go away on a gluten-free diet. More recent studies have looked at whether shorter, lower-dose challenges can still trigger detectable antibody and histologic changes. Two reduced protocols now appear in the literature:
- 3 g/day (about 1.5 to 2 slices of wheat bread) for 2 weeks — in a study of only 20 adults with known celiac disease, given 3 or 7.5 g/day, 68% had Marsh 3 gut damage by day 14 and 65% had raised antibodies by day 28, two weeks after the challenge ended. Antibodies rose only slightly by day 14, and the two doses did not differ.
- 3 g/day for 6 weeks — described as catching closer to 90% of cases on biopsy; still not a perfect substitute for the full 10g/8-week protocol for serology. The authors of the 20-adult study wrote that about 90% of patients can be expected to develop findings consistent with celiac disease after a two-week challenge, and suggested extending it by up to six more weeks if it is tolerated.
Dose may matter for what a two-week biopsy shows. In a small 2021 randomized trial of 14 adults with celiac disease, the fall in the villous height to crypt depth ratio after 14 days was significant at 10 g of gluten a day but not at 3 g, while symptoms and blood interleukin-2 rose at both doses (significantly or nearly so). The 20-adult study above saw no difference between 3 g and 7.5 g.
If you cannot tolerate a full challenge (some patients get so sick they abandon it), a short challenge followed by both serology and biopsy is still better than nothing — and human leukocyte antigen genetic testing can help: if you are negative for HLA-DQ2 and DQ8, celiac disease is essentially ruled out without any gluten at all (see the human leukocyte antigen genetic testing article).
Seronegative Celiac — When Blood Tests Miss It
Roughly 5–10% of adults with biopsy-proven celiac disease have negative or borderline serology despite eating gluten. The Marsh lesions are there. The villi are blunted. The tTG is stubbornly under the cutoff.
Much is not known. A 2024 review says data on how common seronegative celiac is, its features and its outcome are inconclusive, because few studies exist and few patients have been diagnosed. The same review says it can be suspected with flat villi, positive HLA-DQ2 and/or HLA-DQ8 and no celiac antibodies; once other causes are ruled out, the diagnosis can be confirmed by clinical and biopsy improvement after 1 year on a gluten-free diet.
Why this happens is not fully understood. Some patients have very localized, low-grade disease. Some have mild immunoglobulin A deficiency that falls inside the "normal" range but low enough to suppress tTG-IgA. Some have partially treated celiac from inadvertently reduced-gluten diets before testing.
The practical implication: a negative blood test in a high-suspicion patient is not the end of the workup. If you have iron-deficiency anemia that will not respond to oral iron, unexplained elevated liver enzymes, a first-degree relative with celiac, type 1 diabetes, Hashimoto's thyroiditis, osteoporosis before age 50, or dermatitis herpetiformis, a referral for endoscopic biopsy is appropriate regardless of blood results. See the biopsy and Marsh classification article for what the procedure finds.
Post-Diagnosis: Using tTG to Track Healing
Once you are diagnosed and start a strict gluten-free diet, tTG-IgA becomes one of the cheapest and most useful follow-up tools in medicine. Antibody levels are commonly described as roughly halving every six months and normalizing within 12 to 24 months in most patients on a truly gluten-free diet. Measured times depend on the lab method: among 260 children, the median time to normal was 11.7 months by ELISA and 14.7 months by chemiluminescence, with 86% and 70% normal at 30 months, and older age at diagnosis and higher starting levels meant longer times.
What that means in practice:
- If your tTG was 250 at diagnosis and is 15 (normal) eighteen months later, your diet appears to be working, but normal antibodies do not show that the gut has healed (see below).
- If your tTG was 250 at diagnosis and is still 180 a year later, you are getting gluten from somewhere — cross-contamination at home, hidden gluten in medications or supplements, eating out mistakes. This is a diet-detective problem, not a treatment-failure problem.
- If tTG normalizes and then rises again, you have slipped. Common culprits: new medication with wheat starch, switching to a restaurant that has stopped being careful, a new partner or roommate cross-contaminating the kitchen.
Most guidelines recommend tTG-IgA retesting at 6 months, 12 months, and annually thereafter. It does not replace a follow-up endoscopy in complicated cases — villous atrophy can persist even when antibodies normalize — but it is described as catching the majority of dietary slips cheaply. Blood tests are weak at finding ongoing gut damage: a 2017 pooled analysis of 26 studies of people on a gluten-free diet found that tTG-IgA picked up only about half of those with persistent villous atrophy (sensitivity 0.50; EMA-IgA 0.45), with specificity of 0.83 and 0.91.
Home and Mail-In Test Kits
Several direct-to-consumer companies now sell celiac serology by mail. You order online, receive a finger-prick or mail-in venous kit, and get results back in one to two weeks. Typical price: $70–$150.
Known caveats of these kits:
- They use real tTG assays, usually the same ELISA kits hospitals use. The science is legitimate.
- Most do not include a total immunoglobulin A. If you are immunoglobulin A-deficient, the test will be falsely negative and the report will read as normal.
- None can interpret your diet. If you were on a reduced-gluten diet when you tested, the result is uninformative regardless of assay quality.
- A positive mail-in result still requires a real gastroenterologist referral for endomysial antibody confirmation and biopsy planning. Insurance will usually re-run the panel.
- A negative mail-in result in a symptomatic patient is not reassurance. See seronegative celiac.
Home kits are most useful as a screening nudge — "am I in the neighborhood?" — for people whose insurance hassles them about ordering the lab traditionally. They are not a substitute for a proper workup.
Insurance, Coding, and Cost
In the United States, a standard celiac panel (total immunoglobulin A + tTG-IgA, sometimes with EMA reflex) runs about $40–$120 at a large reference laboratory on a commercial insurance plan, and commonly costs nothing out-of-pocket when ordered with a documented clinical indication. Relevant CPT codes include 82784 (total immunoglobulin A), 83516 or 86364 (tTG-IgA), 86255/86256 (EMA titer), and 83516 (DGP variants).
Indications written on the order include "chronic diarrhea," "iron deficiency anemia," "unexplained weight loss," "family history of celiac disease," or "autoimmune thyroid disease" — all recognized indications that meet medical-necessity criteria.
Without insurance, a cash-pay tTG at a direct-to-consumer lab service runs about $30–$60 — often cheaper than a home kit and including a real draw. This is one path open to uninsured patients.
Pediatric vs Adult Panels
Pediatric and adult panels overlap but are not identical.
- Under 2 years old: tTG-IgA alone is unreliable. The standard workup is tTG-IgA + DGP-IgG + total immunoglobulin A. If still equivocal, proceed to biopsy.
- Ages 2–18: tTG-IgA + total immunoglobulin A is the primary screen. Positive results trigger EMA-IgA confirmation. Under 2020 ESPGHAN rules, tTG-IgA ≥10× ULN with positive EMA on a second sample can skip the biopsy entirely.
- Adults: tTG-IgA + total immunoglobulin A is the screen. In the U.S., a positive result virtually always triggers endoscopy. In the UK and parts of Europe, high-titer cases may skip biopsy under British Society of Gastroenterology interim guidance.
Pediatric gastroenterology practices tend to be more aggressive about testing first-degree relatives, particularly siblings, because early detection changes growth trajectory and bone density outcomes. Parents of a diagnosed child can expect their other children to be offered testing over the next several years.
Ordering Pitfalls — What Labs Actually Run
A "celiac panel" means different things at different labs. Common variations you may see:
- Minimal panel: tTG-IgA only. Cheap, but misses immunoglobulin A-deficient patients.
- Standard panel: tTG-IgA + total immunoglobulin A. This is the bare-minimum competent order.
- Comprehensive panel: tTG-IgA + tTG-IgG + DGP-IgA + DGP-IgG + total immunoglobulin A + EMA-IgA reflex. This catches essentially everything. Often the right order for a patient with strong suspicion and a history of intermittent gluten avoidance.
- Legacy panels that still include AGA — the AGA result adds little.
Some patients ask their gastroenterologist or primary care physician directly: "Are you ordering tTG-IgA, total immunoglobulin A, and DGP-IgG? And EMA if tTG is positive?" That five-second clarification is said to prevent 90% of mis-ordered panels.
Some electronic health record systems have a default "Celiac Screen" order that includes only tTG-IgA, no total immunoglobulin A, and no DGP. That is not wrong, but it is not ideal — especially for a first workup.
Why a Gastroenterologist Will Not Just "Test You"
Patients frequently walk into a gastroenterologist's office saying "I've been gluten-free for a year and I want to know if I have celiac. Can you just test me?" The answer, almost always, is no — not usefully. Here is what the gastroenterologist hears and why they push back:
- Your tTG is likely to be normal whether you have celiac or not. The test has nothing to react to because you are not eating the trigger.
- A duodenal biopsy on a long-term gluten-free patient often shows a normal or near-normal villous architecture, even in real celiac disease. The gut heals. Biopsy without a gluten challenge is not a reliable diagnostic either.
- HLA-DQ2/DQ8 genetic testing can be run off-gluten. A negative human leukocyte antigen essentially rules celiac out. A positive human leukocyte antigen is consistent with celiac but also with 30–40% of the general population — it does not diagnose anyone.
The realistic options, if you are already gluten-free and want a definitive answer:
- HLA-DQ2/DQ8 testing first. If negative, celiac is off the table and you can stay gluten-free for symptomatic reasons without medical surveillance. See the human leukocyte antigen article.
- Gluten challenge + serology + biopsy. The gold-standard path if human leukocyte antigen is positive and you want certainty. Plan for 6–8 weeks of feeling terrible.
- Accept uncertainty. If symptoms are controlled and you have no red-flag features (anemia, osteoporosis, family history, failure to thrive, associated autoimmune disease), some patients reasonably choose to remain gluten-free without a formal diagnosis. The trade-off is that you will not qualify for celiac-specific services, some insurance accommodations, or post-diagnosis monitoring.
A good gastroenterologist will lay out all three paths and let you choose. When one refuses to test but gives no reason, the reasoning above is usually what lies behind it.
Key Research Papers
Peer-reviewed work on celiac antibody assay performance, the no-biopsy pathway, immunoglobulin A-deficiency workarounds, HLA-DQ2/DQ8 typing, and the histopathology that serology is meant to predict.
- Rubio-Tapia A, Hill ID, Kelly CP, Calderwood AH, Murray JA. ACG Clinical Guidelines: Diagnosis and Management of Celiac Disease. American Journal of Gastroenterology. 2013;108(5):656-676. — doi:10.1038/ajg.2013.79
- Husby S, Koletzko S, Korponay-Szabó IR, et al. European Society Paediatric Gastroenterology, Hepatology and Nutrition Guidelines for Diagnosing Coeliac Disease 2020. Journal of Pediatric Gastroenterology and Nutrition. 2020;70(1):141-156. — doi:10.1097/MPG.0000000000002497
- Lebwohl B, Sanders DS, Green PHR. Coeliac Disease. Lancet. 2018;391(10115):70-81. — doi:10.1016/S0140-6736(17)31796-8
- Singh P, Arora A, Strand TA, et al. Global Prevalence of Celiac Disease: Systematic Review and Meta-Analysis. Clinical Gastroenterology and Hepatology. 2018;16(6):823-836.e2. — doi:10.1016/j.cgh.2017.06.037
- Werkstetter KJ, Korponay-Szabó IR, Popp A, et al. Accuracy in Diagnosis of Celiac Disease without Biopsies in Clinical Practice. Gastroenterology. 2017;153(4):924-935. — doi:10.1053/j.gastro.2017.06.002
- Tonutti E, Bizzaro N. Diagnosis and Classification of Celiac Disease and Gluten Sensitivity. Autoimmunity Reviews. 2014;13(4-5):472-476. — doi:10.1016/j.autrev.2014.01.043
- Lewis NR, Scott BB. Meta-Analysis: Deamidated Gliadin Peptide Antibody and Tissue Transglutaminase Antibody Compared as Screening Tests for Coeliac Disease. Alimentary Pharmacology & Therapeutics. 2010;31(1):73-81. — doi:10.1111/j.1365-2036.2009.04110.x
- Sblattero D, Berti I, Trevisiol C, et al. Human Recombinant Tissue Transglutaminase ELISA: An Innovative Diagnostic Assay for Celiac Disease. American Journal of Gastroenterology. 2000;95(5):1253-1257. — doi:10.1111/j.1572-0241.2000.02018.x
- Volta U, Granito A, Parisi C, et al. Deamidated Gliadin Peptide Antibodies as a Routine Test for Celiac Disease: A Prospective Analysis. Journal of Clinical Gastroenterology. 2010;44(3):186-190. — doi:10.1097/MCG.0b013e3181c378f6
- Megiorni F, Pizzuti A. HLA-DQA1 and HLA-DQB1 in Celiac Disease Predisposition: Practical Implications of the HLA Molecular Typing. Journal of Biomedical Science. 2012;19(1):88. — doi:10.1186/1423-0127-19-88
- Marsh MN. Gluten, Major Histocompatibility Complex, and the Small Intestine: A Molecular and Immunobiologic Approach to the Spectrum of Gluten Sensitivity. Gastroenterology. 1992;102(1):330-354. — doi:10.1016/0016-5085(92)91819-P
- Oberhuber G, Granditsch G, Vogelsang H. The Histopathology of Coeliac Disease: Time for a Standardized Report Scheme for Pathologists. European Journal of Gastroenterology & Hepatology. 1999;11(10):1185-1194. — doi:10.1097/00042737-199910000-00019
- Schyum AC, Rumessen JJ. Serological Testing for Celiac Disease in Adults. United European Gastroenterology Journal. 2013;1(5):319-325. — doi:10.1177/2050640613502788
- Caio G, Volta U, Sapone A, et al. Celiac Disease: A Comprehensive Current Review. BMC Medicine. 2019;17(1):142. — doi:10.1186/s12916-019-1380-z
- Rubio-Tapia A, Hill ID, Semrad C, et al. American College of Gastroenterology Guidelines Update: Diagnosis and Management of Celiac Disease. American Journal of Gastroenterology. 2023;118(1):59-76. — PubMed PMID: 36602836
- Penny HA, Shiha MG, Raju SA, et al. The 2026 British Society of Gastroenterology guidelines on the diagnosis and management of adult coeliac disease. Gut. 2026 (online ahead of print). — PubMed PMID: 42437688
- Sheppard AL, Elwenspoek MMC, Scott LJ, et al. Systematic review with meta-analysis: the accuracy of serological tests to support the diagnosis of coeliac disease. Alimentary Pharmacology & Therapeutics. 2022;55(5):514-527. — PubMed PMID: 35043426
- Penny HA, Raju SA, Lau MS, et al. Accuracy of a no-biopsy approach for the diagnosis of coeliac disease across different adult cohorts. Gut. 2021;70(5):876-883. — PubMed PMID: 33139268
- Johnston RD, Chan YJ, Mubashar T, et al. No-biopsy pathway following the interim BSG guidance reliably diagnoses adult coeliac disease. Frontline Gastroenterology. 2022;13(1):73-76. — PubMed PMID: 34966534
- Hoyle A, Gillett P, Gillett HR, et al. No-biopsy strategy for coeliac disease is applicable in adult patients: a 'real-world' Scottish experience. Frontline Gastroenterology. 2023;14(2):97-102. — PubMed PMID: 36818788
- Leffler D, Schuppan D, Pallav K, et al. Kinetics of the histological, serological and symptomatic responses to gluten challenge in adults with coeliac disease. Gut. 2013;62(7):996-1004. — PubMed PMID: 22619366
- Leonard MM, Silvester JA, Leffler D, et al. Evaluating Responses to Gluten Challenge: A Randomized, Double-Blind, 2-Dose Gluten Challenge Trial. Gastroenterology. 2021;160(3):720-733.e8. — PubMed PMID: 33130104
- Sansotta N, Alessio MG, Norsa L, et al. Trend of Antitissue Transglutaminase Antibody Normalization in Children With Celiac Disease Started on Gluten-free Diet: A Comparative Study Between Chemiluminescence and ELISA Serum Assays. Journal of Pediatric Gastroenterology and Nutrition. 2020;70(1):37-41. — PubMed PMID: 31599818
- Silvester JA, Kurada S, Szwajcer A, et al. Tests for Serum Transglutaminase and Endomysial Antibodies Do Not Detect Most Patients With Celiac Disease and Persistent Villous Atrophy on Gluten-free Diets: a Meta-analysis. Gastroenterology. 2017;153(3):689-701.e1. — PubMed PMID: 28545781
- Volta U, Rostami K, Auricchio R, Lundin KEA. Diagnosis of Seronegative and Ultrashort Celiac Disease. Gastroenterology. 2024;167(1):104-115. — PubMed PMID: 38286391
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: TTG-IgA sensitivity and specificity for celiac disease
- PubMed: Endomysial antibody testing in celiac disease
- PubMed: Deamidated gliadin peptide (DGP) antibodies
- PubMed: IgA deficiency and celiac disease screening
- PubMed: Gluten challenge protocols and short-course challenges
- PubMed: Seronegative celiac disease
- PubMed: TTG follow-up and gluten-free diet adherence
- PubMed: ESPGHAN no-biopsy pathway and high-titer tTG
Connections
- Gastroenterology
- Celiac Disease Overview
- Gluten-Free Diet: A Practical Guide
- Endoscopy, Biopsy, and Marsh Classification
- HLA-DQ2 and HLA-DQ8 Genetic Testing
- Nutritional Deficiencies and Bone Health
- Non-Celiac Gluten Sensitivity
- Associated Autoimmune Conditions
- Refractory Celiac Disease and EATL
- Hashimoto's Thyroiditis
- TPO and TgAb Antibodies Explained
- Irritable Bowel Syndrome
- Small Intestinal Bacterial Overgrowth
- Homocysteine Lab Test
- Anemia
- Dermatitis Herpetiformis
- Lab Tests