Selenium, Zinc, Iron, and Iodine for Hashimoto's
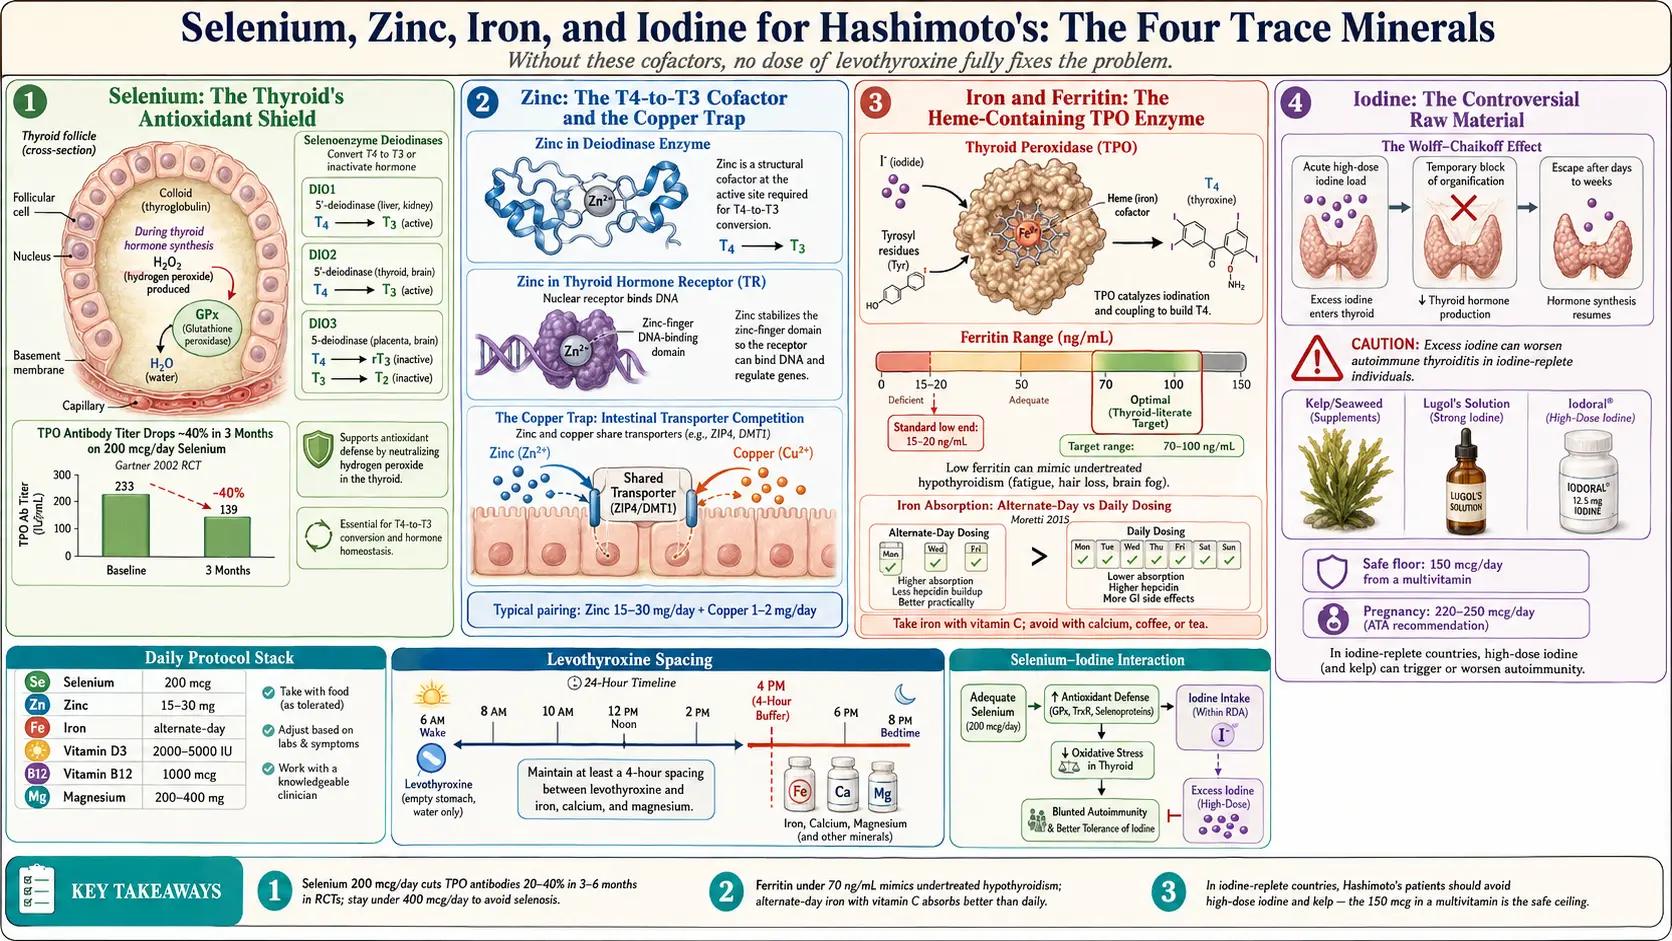
Table of Contents
- Why Trace Minerals Matter
- Selenium — The Thyroid's Antioxidant Shield
- Selenium — What the Trials Show
- Selenium Dosing and Forms
- Selenium Toxicity — The Upper Limit
- Zinc — The T4-to-T3 Cofactor
- Zinc Dosing and the Copper Problem
- Zinc Testing — What Actually Works
- Iron and Ferritin — The Missing Piece
- Iron Dosing — Alternate-Day Is Better
- Ferritin Targets for Thyroid Patients
- Iron Pitfalls
- Iodine — The Controversial One
- When Iodine Is OK
- Kelp and Seaweed — Unpredictable Iodine Doses
- The Selenium-Iodine Interaction
- Other Relevant Cofactors
- The Stack Practitioners Describe for Hashimoto's
- Cost, Forms, and Quality
- Timing Around Levothyroxine
- Key Research Papers
- Connections
- Featured Videos
Why Trace Minerals Matter
Your thyroid is not a standalone organ. It is a chemistry lab that depends on a specific set of trace minerals to build hormones, convert them to their active form, and protect itself from the oxidative damage generated as a byproduct of that very chemistry. When these minerals are low, no dose of levothyroxine fully fixes the problem — because the drug replaces T4, but T4 still has to be converted to T3, and that conversion needs minerals the pill cannot provide.
Four minerals dominate the thyroid literature: selenium, zinc, iron, and iodine. Each sits at a specific enzymatic step. Selenium powers the deiodinase enzymes that strip an iodine atom off T4 to make T3. Zinc is a structural cofactor for the same deiodinases and for the thyroid hormone receptor itself. Iron is required for thyroid peroxidase (TPO), the enzyme that builds thyroid hormone in the first place. Iodine is the raw material — four atoms per T4, three per T3.
In Hashimoto's, the system is already under immune attack. Running it on depleted cofactors is like asking a damaged engine to perform on low-octane fuel. This article walks through each mineral in order of clinical impact: what it does, how to test it, how to dose it, how much is too much, and what to do when standard labs come back "normal" but you still feel sick.
Selenium — The Thyroid's Antioxidant Shield
The thyroid gland contains the highest concentration of selenium per gram of any tissue in the body. That is not a coincidence. Making thyroid hormone generates hydrogen peroxide as a necessary intermediate, and hydrogen peroxide is toxic to the cells producing it. Selenium-containing enzymes neutralize the peroxide before it can damage thyroid tissue.
Three selenium-dependent jobs matter for Hashimoto's:
- Glutathione peroxidase (GPx). The thyroid's antioxidant defense. Without enough selenium, GPx activity drops and thyroid follicles accumulate oxidative damage, feeding the autoimmune attack.
- Deiodinases (DIO1, DIO2, DIO3). All three selenoproteins. These enzymes convert T4 to active T3 (DIO1, DIO2) or inactivate thyroid hormone (DIO3). No selenium, no T3.
- TPO antibody reduction. Multiple trials have shown that selenium supplementation drops TPO antibody titers by 20–40% over 3–6 months. This does not cure the disease, but it correlates with less inflammation and, in many patients, better day-to-day energy.
Selenium — What the Trials Show
Selenium is one of the few Hashimoto's supplements with real randomized trial evidence:
- Gärtner 2002 (the seminal randomized controlled trial, RCT). 70 women with autoimmune thyroiditis, 200 mcg/day sodium selenite (36 women) or placebo (34 women) for 3 months. Average TPO antibodies fell to 63.6% of their starting level on selenium, against 88% on placebo. In the subgroup with TPO antibodies above 1,200 IU/ml, they fell 40% on selenium and rose 10% on placebo. Nine patients on selenium normalized their antibodies completely, against two on placebo.
- Turker 2006. Compared 200 mcg/day with 100 mcg/day of L-selenomethionine over 9 months. TPO antibodies fell on 200 mcg/day and rose 38.1% in women whose dose was lowered to 100 mcg/day. The authors concluded that suppression requires doses higher than 100 mcg/day and that the suppression rate decreases with time. No dose above 200 mcg/day was tested.
- Toulis meta-analysis 2010. Pooled data from four randomized controlled trials (RCTs); confirmed that 3 months of selenium supplementation significantly lowers TPO antibodies in Hashimoto's patients, though heterogeneity in trial quality was substantial.
- CATALYST trial (Larsen 2024). 412 patients took 200 mcg/day selenium yeast or placebo for 12 months alongside levothyroxine. Quality of life improved in both groups, with no difference in any of the ThyPRO-39 quality-of-life scales between selenium and placebo. Antibody reduction is a surrogate marker: lower antibodies do not automatically mean fewer symptoms.
The honest summary: selenium is one of the most evidence-backed interventions in Hashimoto's, and its measured effects are modest. Think of it as tuning the engine, not rebuilding it.
Selenium Dosing and Forms
Dose used in the trials above: 200 mcg per day. It is commonly taken with food, typically breakfast.
Form matters. In order of bioavailability and retention:
- Selenomethionine — the amino-acid-bound form; well absorbed and incorporates into body stores. A solid default.
- Selenium yeast (high-selenium yeast) — a mix of selenomethionine and other organic selenoamino acids; used in most of the big randomized controlled trials and comparable to pure selenomethionine.
- Sodium selenite / selenate — inorganic forms; absorbed but not retained as well. Gärtner 2002 used selenite successfully, so it works, but organic forms are the modern preference.
Food source: Brazil nuts. One to two Brazil nuts per day is the classic folk-medicine approach and can deliver 70–200 mcg depending on the nut. The problem is extreme variability: selenium in Brazil nuts comes from the soil where the tree grew, and a single nut can range from 10 mcg to over 90 mcg. Daily Brazil nuts on top of a supplement can push the total past the upper limit without anyone knowing it.
Selenium Toxicity — The Upper Limit
Selenium has a narrow therapeutic window. The U.S. tolerable upper intake level for adults is 400 mcg/day, and chronic intake above that causes selenosis. Signs include:
- Brittle, ridged, or shedding nails
- Hair loss (paradoxical — you thought selenium was supposed to help)
- A distinct garlic odor on the breath and sweat (a classic tell)
- Peripheral neuropathy — tingling or numbness in the hands and feet
- Gastrointestinal upset, fatigue, and irritability
Practitioners keep a dedicated supplement at 200 mcg/day or less, which leaves room under the 400 mcg limit for selenium from food. Many multivitamins contain 50–100 mcg of selenium, which adds to a separate supplement, and daily Brazil nuts add more. Garlic-scented breath or sweat is a recognised sign of too much selenium; practitioners report that levels normalize within a few weeks of stopping.
Zinc — The T4-to-T3 Cofactor
Zinc is less studied than selenium in Hashimoto's but its role is well established. Three thyroid-relevant functions:
- Deiodinase structure. Zinc is a structural cofactor in the deiodinases that selenium powers. Zinc-deficient animals show reduced T4-to-T3 conversion even when selenium status is normal.
- Thyroid-stimulating hormone receptor and thyroid hormone receptor function. Zinc is required for the three-dimensional folding of the nuclear thyroid hormone receptor. Without zinc, T3 can bind but downstream gene transcription suffers.
- Immune modulation. Zinc balances Th1/Th2/Th17 signaling. Deficiency tilts toward autoimmune inflammation; repletion calms it.
Patients with hypothyroidism often have low zinc on blood testing, and zinc-deficient patients often have low T3 — a chicken-and-egg relationship that, in practice, is treated by repleting both.
Zinc Dosing and the Copper Problem
Doses practitioners commonly use: 15–30 mg elemental zinc per day, taken with food (zinc on an empty stomach causes nausea in most people). The Institute of Medicine (IOM) adult Tolerable Upper Intake Level (UL) for zinc is 40 mg/day from food, water and supplements together.
Forms in common use:
- Zinc picolinate — well absorbed, widely available, inexpensive.
- Zinc glycinate (bisglycinate) — gentle on the stomach; good for people who get queasy on picolinate.
- Zinc citrate — decent absorption, cheap.
- Zinc oxide — poorly absorbed; better known as a sunscreen ingredient.
The copper trap. Zinc and copper compete for the same intestinal transporter, and high zinc intake can cause copper deficiency, which itself causes anemia, neuropathy, and immune dysfunction — the same symptoms the zinc was meant to fix. The IOM set the 40 mg/day zinc limit on a drop in a copper-dependent red-cell enzyme (copper-zinc superoxide dismutase); the lowest intake shown to cause that drop was 60 mg/day (a 50 mg supplement plus diet). Practitioners pair zinc with 1–2 mg of copper (as copper bisglycinate or copper gluconate), taken at a different time of day. Many zinc products are sold as "zinc + copper" combos for this reason.
Zinc Testing — What Actually Works
Zinc testing is notoriously unreliable. Standard serum zinc has a broad reference range (typically 60–120 mcg/dL) and can look normal even in functional deficiency, because the body pulls zinc out of tissues to keep serum stable. It is also affected by recent meals and time of day.
Better options:
- Red blood cell (RBC) zinc — reflects longer-term status; less affected by acute fluctuation. Available through most specialty labs.
- Plasma zinc after a 12-hour fast, drawn in the morning — the most reproducible version of the standard test.
The pragmatic approach practitioners describe. When serum zinc is in the lower third of the reference range and there are suggestive symptoms — slow wound healing, frequent colds, changes in taste or smell, new white spots on fingernails, hair thinning — they use a 2–3 month trial of 15–30 mg/day with copper, which stays under the 40 mg/day upper limit, then re-test and reassess symptoms at 3 months.
Iron and Ferritin — The Missing Piece
Iron is the most commonly missed thyroid cofactor in primary care. A classic presentation: the thyroid labs look "optimal" on paper — thyroid-stimulating hormone around 1.5, free T4 mid-range, free T3 acceptable — and the patient still has fatigue, hair loss, cold intolerance, and brain fog. Practitioners report that ferritin in these patients is often under 30 ng/mL.
Why iron matters for thyroid:
- TPO enzyme. Thyroid peroxidase, the enzyme that builds T4 from iodine and tyrosine, is a heme-containing enzyme. Iron-deficient TPO cannot synthesize hormone at full capacity.
- T4-to-T3 conversion. Low iron impairs deiodinase activity indirectly via mitochondrial dysfunction.
- Hair, nails, skin. Three tissues that fail first when either iron or thyroid hormone is low. Combined deficiency is devastating.
- Oxygen delivery. Low ferritin without overt anemia still compromises tissue oxygenation, which the patient experiences as crushing fatigue even at a hemoglobin of 12.
Standard labs call anemia at hemoglobin below 12 (women) or 13.5 (men). But the thyroid patient with ferritin of 25 and hemoglobin of 13 is functionally iron-deficient — the stores are empty even though the circulating red cell count has not yet fallen.
Iron Dosing — Alternate-Day Is Better
A 2015 study by Moretti and colleagues in the journal Blood (54 iron-depleted young women) found that 24 hours after an iron dose of 60 mg or more, the hormone hepcidin was raised and the next day's iron absorption fell by 35–45%. The authors wrote that this supports alternate-day supplementation, with the longer-term effects still to be studied. A 2017 trial by Stoffel and colleagues in Lancet Haematology then compared the two schedules directly: in plain English, women absorbed 21.8% of the iron on alternate days against 16.3% on consecutive days.
The protocol practitioners describe:
- Dose: 40–65 mg elemental iron, every other day, in the morning on an empty stomach. The IOM adult upper limit (UL) for iron is 45 mg/day, a level based on stomach and gut upset (gastrointestinal distress), so a dose above 45 mg exceeds it.
- Taken with 250–500 mg of vitamin C to enhance absorption.
- Coffee, tea, dairy, and calcium supplements within 2 hours before or after all reduce absorption.
- At least 4 hours apart from levothyroxine. Iron binds levothyroxine in the gut and torpedoes its absorption. Most patients take thyroid medication on waking and iron mid-morning or lunchtime on alternate days.
Forms, in order of tolerability:
- Ferrous bisglycinate — gentle on the gut, well absorbed; the modern first choice. Typical dose 25–27 mg elemental per capsule.
- Heme iron polypeptide — very well absorbed, expensive.
- Ferrous sulfate — cheapest, proven; rougher on the stomach and more likely to cause constipation and black stools.
- Ferrous fumarate / gluconate — middle of the road on both counts.
Ferritin Targets for Thyroid Patients
General population reference ranges (ferritin above 15 or 20 ng/mL) are too low for thyroid patients. A target cited by thyroid-literate practitioners is 70–100 ng/mL. Hair-loss clinicians often push for 70 minimum; some endocrinologists are happy at 50.
Practitioners retest ferritin, complete blood count (CBC), and iron saturation at 3 months. When ferritin has not moved at least 20 points, the usual causes looked for are ongoing blood loss (heavy periods, gastrointestinal (GI) bleeding), celiac disease or gluten-related malabsorption, H. pylori infection, or poor stomach acid (common in Hashimoto's because autoimmune gastritis frequently overlaps).
Once ferritin reaches 70–100 ng/mL, practitioners drop to a maintenance dose or stop and recheck in 6 months. Continuing to supplement past a good ferritin level risks iron overload, which is its own problem.
Iron Pitfalls
- Iron without labs carries a risk. Iron overload (hemochromatosis) is genetic and more common than most people realize; supplementing blindly can accelerate organ damage. Ferritin and transferrin saturation show iron stores before starting.
- Hemochromatosis screening is the usual step when a first-degree relative has it, or when ferritin comes back unexpectedly high (over 300 ng/mL with no obvious cause).
- Too much iron causes oxidative stress. Iron drives Fenton-reaction free radicals; in excess it feeds the exact oxidative damage selenium is protecting the thyroid from.
- Men and postmenopausal women rarely need iron supplementation and carry the higher risk of overload — they are not losing iron monthly and accumulate it more readily.
Iodine — The Controversial One
Iodine is the single most misunderstood nutrient in the Hashimoto's world. The logic sounds airtight: the thyroid makes iodine-containing hormones, so iodine must help. In practice, for Hashimoto's patients in an iodine-replete country like the United States, high-dose iodine supplementation often makes the disease worse.
The mechanism has two parts:
- The Wolff-Chaikoff effect. A sudden surge of iodine temporarily shuts down thyroid hormone production. Most healthy thyroids escape this within a few days; Hashimoto's thyroids often do not, and hypothyroidism worsens.
- Antigenic modification. Iodine incorporation into thyroglobulin makes it a more visible target for autoimmune antibodies. Studies in iodine-deficient regions show that iodine repletion programs are followed by an uptick in Hashimoto's incidence. This is not a reason to reverse public-health iodization — it prevents far more goiter and developmental disability than it causes — but it tells you that iodine is not benign in autoimmune thyroid disease.
The populations at highest risk from high-dose iodine are exactly the patients most likely to be self-medicating: those who have already been diagnosed with Hashimoto's, who read online that "iodine fixes thyroid," and who start 12.5 mg or 50 mg daily doses of Lugol's solution or high-dose iodine tablets. This is a common route into worsening disease and rising TPO titers. The IOM adult upper limit (UL) for iodine is 1,100 mcg (1.1 mg) a day; 12.5 mg is about 11 times that limit and 50 mg about 45 times.
When Iodine Is OK
Iodine is not always bad. The cases where supplementation is appropriate:
- Documented deficiency. Spot urinary iodine concentration under 100 mcg/L (ideally confirmed on a 24-hour urine or a second spot test) is the standard cutoff for population-level deficiency.
- Pregnancy and breastfeeding. Fetal brain development requires iodine. The American Thyroid Association recommends 150 mcg/day preconception and 220–250 mcg/day in pregnancy, usually delivered through a prenatal multivitamin. The advice applies to pregnant women with Hashimoto's as well.
- Restrictive diets. Strict vegans who avoid iodized salt, dairy, eggs, and seafood can become deficient. A standard multivitamin supplies 150 mcg/day.
The everyday amount practitioners describe for an adult with Hashimoto's is the 150 mcg included in most multivitamins. The IOM adult upper limit for iodine from all sources is 1,100 mcg/day.
Kelp and Seaweed — Unpredictable Iodine Doses
Kelp, kombu, bladderwrack, and other seaweeds are marketed as "natural thyroid support." The problem is dose unpredictability. A single serving of kelp can contain 500 to 10,000 mcg of iodine, depending on species, harvest location, and processing — routinely ten to fifty times the recommended daily intake.
Case reports and small series link daily kelp consumption to new-onset thyroiditis, worsening Hashimoto's, and iodine-induced hyperthyroidism. For people with Hashimoto's:
- Daily kelp or seaweed supplements can supply many times the adult iodine upper limit of 1,100 mcg/day: a single serving of kelp can hold 500 to 10,000 mcg.
- Practitioners describe occasional sushi (a nori wrap, a miso soup) as unproblematic; daily miso, daily seaweed snacks, and kelp capsules are where people report trouble.
- Hidden kelp is a surprisingly common ingredient in multivitamins and "thyroid support" blends; the ingredient label lists it.
The Selenium-Iodine Interaction
Selenium and iodine work as a team. Iodine is the raw material for hormone synthesis; selenium protects the thyroid from the oxidative damage that synthesis generates. When iodine intake rises without enough selenium, the thyroid is flooded with peroxide it cannot neutralize, and follicular cells suffer.
Animal models and observational human data suggest that selenium adequacy blunts iodine-induced thyroid autoimmunity. In practical terms, when a Hashimoto's patient takes iodine (pregnancy, documented deficiency), practitioners make sure of selenium sufficiency first. They describe high-dose iodine without enough selenium as the combination most likely to spike TPO antibodies.
Other Relevant Cofactors
A brief tour of the supporting cast:
- Vitamin D. Low vitamin D is nearly universal in autoimmune thyroid disease. Practitioners target a 25-hydroxyvitamin D level of 40–60 ng/mL and commonly use 2,000–5,000 international units (IU)/day of D3; the IOM adult upper limit for vitamin D is 4,000 IU (100 mcg) a day, so 5,000 IU is above it. They pair it with K2 (100–200 mcg menaquinone-7, MK-7) as a useful companion for calcium metabolism.
- Vitamin B12. Autoimmune gastritis and parietal-cell antibodies cluster with Hashimoto's, and B12 deficiency is common. Practitioners aim to keep serum B12 above 500 pg/mL and use 1,000 mcg methylcobalamin daily when it is low.
- Tyrosine. Thyroid hormone is built from tyrosine plus iodine. Tyrosine deficiency is rare in anyone eating adequate protein. Supplementation rarely helps outside a very restricted diet.
- Magnesium. A cofactor in hundreds of enzymes, including some in the deiodinase pathway. Practitioners report that many people's intake is low and use 200–400 mg/day of magnesium glycinate or citrate as an add-on. The IOM adult upper limit for magnesium from supplements is 350 mg/day, so 400 mg is above it.
The Stack Practitioners Describe for Hashimoto's
Pulled together, the starting protocol practitioners describe looks like this, shown beside the IOM adult upper limits:
- Selenium 200 mcg/day (selenomethionine or selenium yeast) with breakfast. Upper limit: 400 mcg/day from all sources.
- Zinc 15–30 mg/day with dinner, paired with copper 1–2 mg/day taken at a different meal. Upper limit for zinc: 40 mg/day.
- Iron — dose based on ferritin. If ferritin is under 70 ng/mL, 40–65 mg elemental ferrous bisglycinate every other day with vitamin C, on an empty stomach, at least 4 hours from levothyroxine. Upper limit: 45 mg/day, so a dose above 45 mg exceeds it.
- Vitamin D3 2,000–5,000 international units/day with a fat-containing meal when 25(OH)D is under 40 ng/mL, retested at 3 months. Upper limit: 4,000 IU/day, so 5,000 IU is above it.
- Vitamin B12 1,000 mcg methylcobalamin if serum B12 is under 500 pg/mL.
- Magnesium 200–400 mg/day in glycinate or citrate form, taken at bedtime. Upper limit for supplemental magnesium: 350 mg/day, so 400 mg is above it.
- Iodine: no separate supplement unless a urinary iodine test shows deficiency, during pregnancy, or on a strict vegan diet. A 150 mcg multivitamin stays well under the 1,100 mcg/day upper limit; high-dose iodine (12.5–50 mg) is 11 to 45 times over it.
Practitioners retest TPO antibodies, thyroid-stimulating hormone, free T4, free T3, ferritin, vitamin D, and B12 at 3 months and adjust by the numbers and symptoms rather than online consensus.
Cost, Forms, and Quality
Dietary supplements are not approved by the FDA before they are sold, so the bottle's label is the maker's own claim. What the common quality marks mean:
- USP Verified or NSF Certified — an outside organization has tested the product against its label (what it contains and how much) and for contaminants.
- "GMP-compliant" — refers to the good-manufacturing-practice rules every US supplement maker must follow; on its own it is the maker's statement, not outside testing.
- The form on the label — the forms described above as better absorbed are selenomethionine or selenium yeast, zinc picolinate, glycinate or citrate, ferrous bisglycinate, and magnesium glycinate or citrate; oxide forms of minerals are poorly absorbed.
Approximate monthly cost for the whole stack above: $30–$50 at budget and mid-range prices, $60–$100 for premium practitioner lines. Generic drugstore multivitamins are inexpensive but often use oxide forms of minerals (poorly absorbed) and may contain hidden kelp or iodine; the ingredient label lists both.
Timing Around Levothyroxine
Thyroid hormone absorption is easy to disrupt. The timings practitioners describe:
- Levothyroxine on waking, with water only, at least 30–60 minutes before food or coffee.
- Iron, calcium, magnesium: at least 4 hours apart from levothyroxine.
- Selenium and zinc: taken with food to reduce nausea. Timing relative to thyroid medication matters less, but keeping them at lunch or dinner is simplest.
- Vitamin D and B12: no strong interaction with levothyroxine, so timing is flexible. Vitamin D needs fat to absorb.
- Coffee: delays levothyroxine absorption by up to an hour even without cream. Practitioners describe waiting at least 30 minutes after the pill, ideally 60.
The simplest schedule practitioners describe: thyroid pill on waking, coffee and breakfast an hour later with selenium, zinc and dinner, iron on alternate days at lunch with vitamin C, magnesium at bedtime. Some people write it on a card taped to the medicine cabinet until it becomes automatic.
Key Research Papers
Foundational and recent peer-reviewed publications on the four micronutrients most implicated in thyroid function — selenium, zinc, iron, and iodine — plus the absorption-and-dosing literature that shapes practical use. Each citation links to the full text via DOI.
- Gärtner R, Gasnier BCH, Dietrich JW, Krebs B, Angstwurm MWA. Selenium Supplementation in Patients with Autoimmune Thyroiditis Decreases Thyroid Peroxidase Antibodies Concentrations. Journal of Clinical Endocrinology & Metabolism. 2002;87(4):1687–1691. — doi:10.1210/jcem.87.4.8421
- Toulis KA, Anastasilakis AD, Tzellos TG, Goulis DG, Kouvelas D. Selenium Supplementation in the Treatment of Hashimoto's Thyroiditis: A Systematic Review and a Meta-Analysis. Thyroid. 2010;20(10):1163–1173. — PubMed PMID: 20883174
- Turker O, Kumanlioglu K, Karapolat I, Dogan I. Selenium Treatment in Autoimmune Thyroiditis: 9-Month Follow-Up with Variable Doses. Journal of Endocrinology. 2006;190(1):151–156. — PubMed PMID: 16837619
- Larsen C, Winther KH, Cramon PK, et al. Selenium Supplementation and Placebo Are Equally Effective in Improving Quality of Life in Patients with Hypothyroidism. European Thyroid Journal. 2024;13(1):e230175. — PubMed PMID: 38215286
- Wichman J, Winther KH, Bonnema SJ, Hegedus L. Selenium Supplementation Significantly Reduces Thyroid Autoantibody Levels in Patients with Chronic Autoimmune Thyroiditis: A Systematic Review and Meta-Analysis. Thyroid. 2016;26(12):1681–1692. — doi:10.1089/thy.2016.0256
- Mazokopakis EE, Papadakis JA, Papadomanolaki MG, et al. Effects of 12 Months Treatment with L-Selenomethionine on Serum Anti-TPO Levels in Patients with Hashimoto's Thyroiditis. Thyroid. 2007;17(7):609–612. — doi:10.1089/thy.2007.0040
- Zimmermann MB, Boelaert K. Iodine Deficiency and Thyroid Disorders. Lancet Diabetes & Endocrinology. 2015;3(4):286–295. — doi:10.1016/S2213-8587(14)70225-6
- Moretti D, Goede JS, Zeder C, et al. Oral Iron Supplements Increase Hepcidin and Decrease Iron Absorption from Daily or Twice-Daily Doses in Iron-Depleted Young Women. Blood. 2015;126(17):1981–1989. — doi:10.1182/blood-2015-05-642223
- Stoffel NU, Cercamondi CI, Brittenham G, et al. Iron Absorption from Oral Iron Supplements Given on Consecutive versus Alternate Days and as Single Morning Doses versus Twice-Daily Split Dosing in Iron-Depleted Women: Two Open-Label, Randomised Controlled Trials. Lancet Haematology. 2017;4(11):e524–e533. — PubMed PMID: 29032957
- Stoffaneller R, Morse NL. A Review of Dietary Selenium Intake and Selenium Status in Europe and the Middle East. Nutrients. 2015;7(3):1494–1537. — doi:10.3390/nu7031494
- Rayman MP. Multiple Nutritional Factors and Thyroid Disease, with Particular Reference to Autoimmune Thyroid Disease. Proceedings of the Nutrition Society. 2019;78(1):34–44. — doi:10.1017/S0029665118001192
- Sategna-Guidetti C, Volta U, Ciacci C, et al. Prevalence of Thyroid Disorders in Untreated Adult Celiac Disease Patients and Effect of Gluten Withdrawal: An Italian Multicenter Study. American Journal of Gastroenterology. 2001;96(3):751–757. — doi:10.1016/s0002-9270(00)02410-2
- Betsy A, Binitha MP, Sarita S. Zinc Deficiency Associated with Hypothyroidism: An Overlooked Cause of Severe Alopecia. International Journal of Trichology. 2013;5(1):40–42. — doi:10.4103/0974-7753.114714
- Hess SY. The Impact of Common Micronutrient Deficiencies on Iodine and Thyroid Metabolism: The Evidence from Human Studies. Best Practice & Research Clinical Endocrinology & Metabolism. 2010;24(1):117–132. — doi:10.1016/j.beem.2009.08.012
- Centanni M, Gargano L, Canettieri G, et al. Thyroxine in Goiter, Helicobacter pylori Infection, and Chronic Gastritis. New England Journal of Medicine. 2006;354(17):1787–1795. — doi:10.1056/NEJMoa043903
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: selenium RCTs Hashimoto's
- PubMed: ferritin + thyroid + hair loss
- PubMed: iodine + Hashimoto's controversy
- PubMed: zinc + T4-to-T3 conversion
- PubMed: alternate-day iron + hepcidin
- PubMed: vitamin D + autoimmune thyroiditis
- PubMed: Wolff-Chaikoff + iodine excess
- PubMed: selenium-iodine interaction
Connections
- Endocrinology
- How Your Thyroid Is Controlled — interactive animation
- Selenium
- Iodine
- Zinc
- Iron
- Magnesium
- Hashimoto's Thyroiditis
- Vitamin D3
- Vitamin B12
- Thyroid-Stimulating Hormone, T4 & T3 Optimal Ranges
- AIP and Gluten Elimination
- Levothyroxine vs NDT vs T3
- TPO and TgAb Antibodies
- Reverse T3 and Low T3 Syndrome
- Copper & Iron Dysregulation
- Copper
- Tyrosine
- Anemia
- Celiac Disease