Alpha Lipoic Acid for Blood Sugar & Insulin Sensitivity
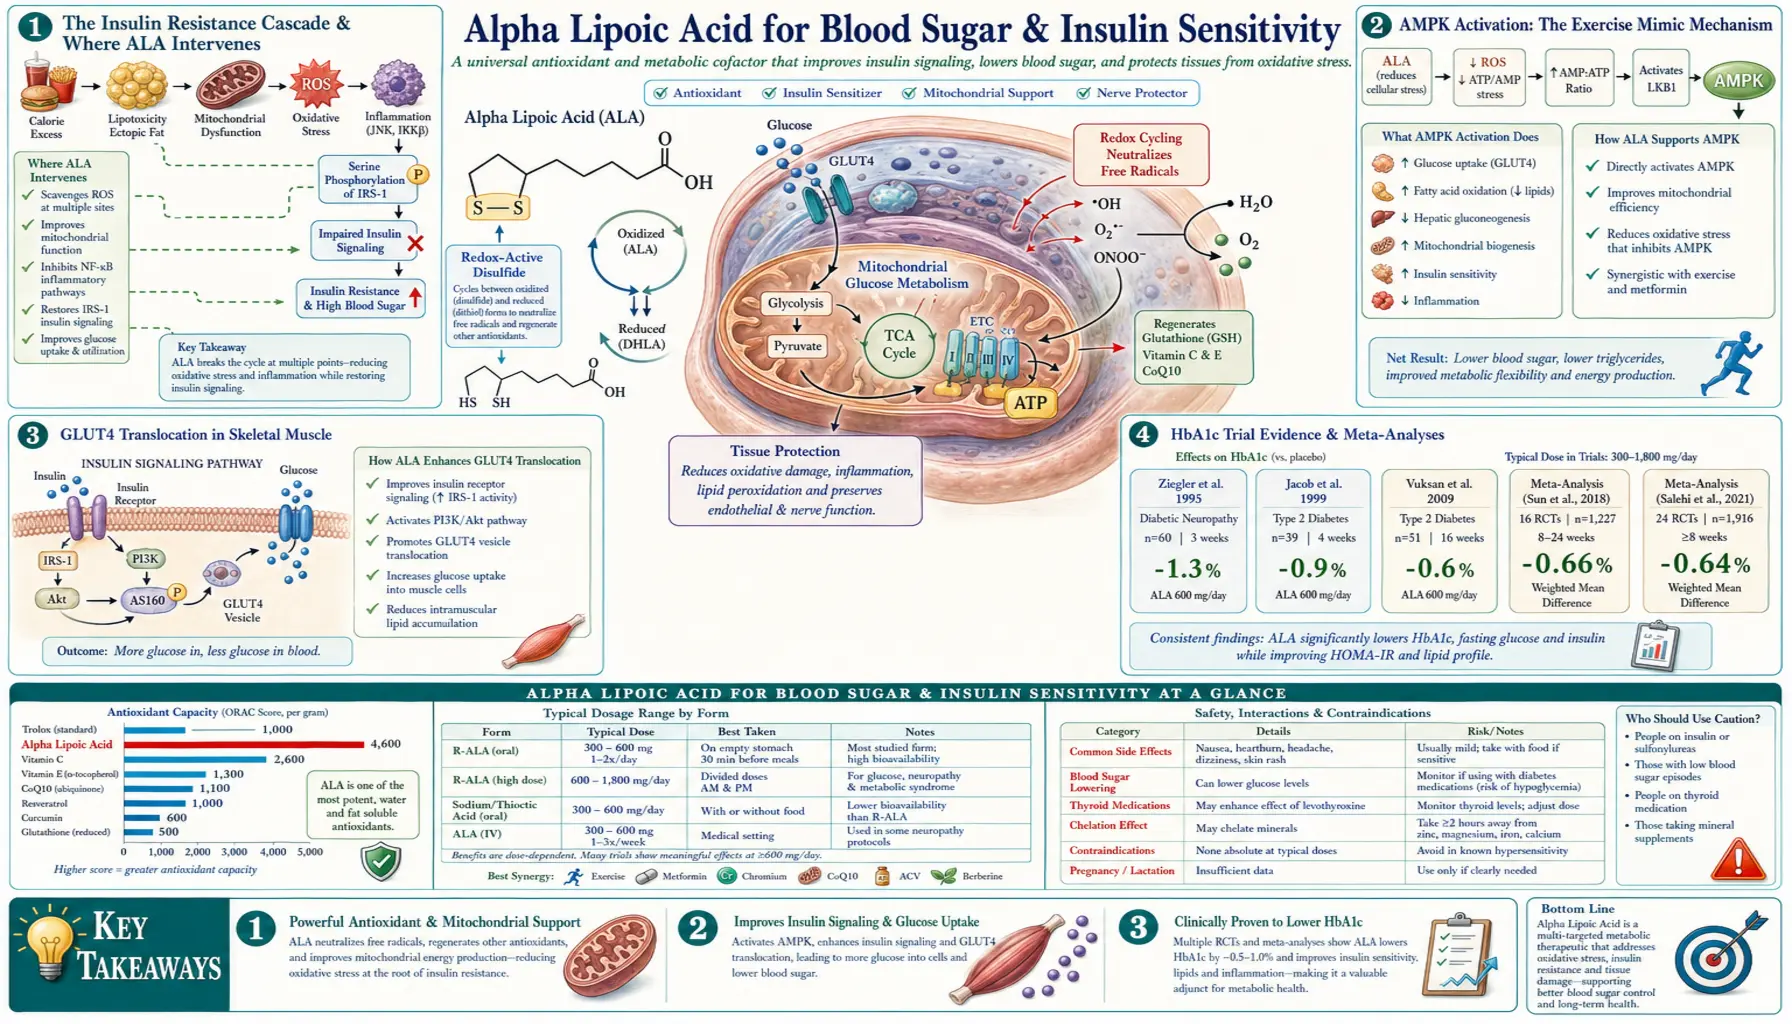
In cell and animal studies, alpha lipoic acid (ALA) increased glucose uptake into muscle and fat cells, and in obese rats it activated AMP-activated protein kinase (AMPK) in skeletal muscle and improved insulin sensitivity. In people the effect on blood sugar is small: a 2022 dose-response meta-analysis of oral alpha-lipoic acid in type 2 diabetes found statistically significant reductions in hemoglobin A1c (HbA1c), fasting glucose and body weight, but every estimate was below the threshold the authors considered clinically important, and a 2017 meta-analysis found 1.27 kg greater weight loss than placebo. This page covers the laboratory findings, the human trials and meta-analyses, the doses the studies used, and the cautions the research raises, including insulin autoimmune syndrome, which has been reported in Japanese and in European patients.
Interactive Visualization Free Radicals & Your Antioxidant Network Follow one superoxide radical down the whole relay — superoxide dismutase (SOD), catalase, glutathione, vitamin E, vitamin C, reduced nicotinamide adenine dinucleotide phosphate (NADPH) — then release free iron and watch a membrane tear itself apart. Launch →
Table of Contents
- The Insulin Resistance Cascade & What Studies Report for Alpha-Lipoic Acid
- AMP-Activated Protein Kinase Activation in Animal Studies
- GLUT4 and Glucose Uptake: Cell and Clamp Studies
- Hemoglobin A1c Trial Evidence & Meta-Analyses
- Metabolic Syndrome, Weight & Lipids
- Alpha-Lipoic Acid With Other Glucose-Lowering Agents: What Was Studied
- Doses Used in Studies
- Hypoglycemia and Diabetes Medicines: What the Research Shows
- Insulin Autoimmune Syndrome (Hirata Disease)
- How the Trials Measured Glucose
- Key Research Papers
- Connections
- Featured Videos
The Insulin Resistance Cascade & What Studies Report for Alpha-Lipoic Acid
Insulin resistance underlies type 2 diabetes and metabolic syndrome and is common in non-alcoholic fatty liver disease (NAFLD) and polycystic ovary syndrome (PCOS). It develops through a cascade of changes:
- Adipose tissue inflammation — expanding fat tissue attracts macrophages and releases inflammatory cytokines such as tumor necrosis factor alpha (TNFα) and interleukin-6 (IL-6)
- Hepatic insulin resistance — impaired insulin signaling in the liver raises glucose output and fasting glucose
- Skeletal muscle insulin resistance — impaired muscle insulin signaling reduces glucose uptake after meals
- Pancreatic compensation, then failure — the pancreas first makes more insulin; as beta-cell function declines, diabetes develops
Research on alpha-lipoic acid touches several of these steps, mostly in cells and animals:
- Skeletal muscle — in obese rats alpha-lipoic acid activated AMP-activated protein kinase in muscle and increased insulin-stimulated glucose disposal (Lee 2005); in cultured muscle and fat cells it increased glucose uptake (Estrada 1996).
- Oxidative stress and inflammation — cell and animal research describes alpha-lipoic acid improving glucose handling and lowering NF-κB-driven inflammatory signaling (Shay 2009).
- People with type 2 diabetes — small human studies measured insulin sensitivity directly (Jacob 1999; Konrad 1999), and meta-analyses pooled trials of glucose, hemoglobin A1c and weight (below).
AMP-activated protein kinase is also activated by exercise and by metformin.
AMP-Activated Protein Kinase Activation in Animal Studies
AMP-activated protein kinase (AMPK) is a cellular energy sensor. When adenosine triphosphate (ATP) is used faster than it is regenerated — during exercise, fasting or cellular stress — AMP-activated protein kinase is activated and shifts the cell toward energy-producing metabolism:
- Glucose uptake — AMP-activated protein kinase promotes movement of GLUT4 glucose transporters to the muscle cell surface
- Fatty acid oxidation — AMP-activated protein kinase inhibits acetyl-CoA carboxylase, lowering malonyl-CoA and releasing the brake on fatty acid entry into mitochondria
- Lower glucose output and fat synthesis in the liver
- Mitochondrial biogenesis over longer periods, through PGC-1α
In obese rats, Lee et al. (2005) found that alpha-lipoic acid activated AMP-activated protein kinase in skeletal muscle, increased fatty acid oxidation, and increased insulin-stimulated glucose disposal in the whole body and in muscle. When AMP-activated protein kinase was blocked in muscle with a dominant-negative AMP-activated protein kinase, the alpha-lipoic acid-induced rise in fatty acid oxidation and insulin-stimulated glucose uptake did not occur, so the authors concluded the effect was mediated by AMP-activated protein kinase and reduced triglyceride accumulation in muscle. This is animal evidence; it does not show the same mechanism at the doses used in people.
GLUT4 and Glucose Uptake: Cell and Clamp Studies
Skeletal muscle takes up much of the glucose cleared under insulin stimulation. Glucose enters muscle cells through the GLUT4 transporter, which is stored inside the cell and moved to the cell membrane in response to insulin or exercise; in insulin resistance this response is impaired.
Cell studies. In cultured L6 muscle cells and 3T3-L1 fat cells, R-lipoic acid rapidly increased glucose uptake, more than the S-isomer or the racemic mixture, to a degree comparable with insulin. The effect was abolished by wortmannin, an inhibitor of PI3-kinase (an insulin-signaling enzyme), and was accompanied by a redistribution of GLUT1 and GLUT4 transporters similar to that caused by insulin (Estrada 1996).
Clamp studies in people. In a 4-week placebo-controlled pilot trial in 74 people with type 2 diabetes, oral alpha-lipoic acid at 600, 1,200 or 1,800 mg/day raised insulin-stimulated glucose disposal on an isoglycemic clamp; with no dose effect seen, the combined alpha-lipoic acid groups changed 27% more than placebo (Jacob 1999). In a smaller study, 600 mg twice daily for 4 weeks increased glucose effectiveness in lean and obese patients with type 2 diabetes, raised insulin sensitivity in the lean patients only, and lowered serum lactate and pyruvate by about 45% (Konrad 1999).
These studies were short and small. The longer trials and meta-analyses below measured hemoglobin A1c and fasting glucose.
Hemoglobin A1c Trial Evidence & Meta-Analyses
Akbari et al. (2018)
A meta-analysis of 24 randomized trials in people with metabolic diseases found that alpha-lipoic acid lowered fasting glucose, fasting insulin, insulin resistance (homeostatic model assessment of insulin resistance, HOMA-IR) and hemoglobin A1c, and triglycerides, total and low-density lipoprotein (LDL) cholesterol, with no effect on high-density lipoprotein (HDL) cholesterol. Results were reported as standardized mean differences (for hemoglobin A1c, −1.22), which do not translate directly into percentage points.
Jibril et al. (2022)
A dose-response meta-analysis limited to oral alpha-lipoic acid in type 2 diabetes (16 trials, 1,035 patients). Each 500 mg/day of alpha-lipoic acid significantly reduced hemoglobin A1c, body weight, C-reactive protein, fasting glucose and triglycerides; the hemoglobin A1c curve was roughly J-shaped (mean difference −0.32 percentage points), and fasting glucose and low-density lipoprotein cholesterol fell up to 600 mg/day. Every point estimate was below the threshold the authors considered a minimal clinically important difference, and they concluded the effects were not clinically important.
What this means
Across these analyses, oral alpha-lipoic acid lowered glucose markers by small amounts. Neither meta-analysis compared alpha-lipoic acid with diabetes medicines, and the trials were mostly short. Diabetes care is covered on the Diabetes page.
Metabolic Syndrome, Weight & Lipids
- Weight — a 2017 meta-analysis of 10 randomized, double-blind, placebo-controlled trials (Kucukgoncu et al.) found 1.27 kg greater mean weight loss with alpha-lipoic acid than with placebo and a body mass index (BMI) difference of −0.43 kg/m². The authors described the effect as small and short-term, with no relationship to dose. In the Jibril 2022 analysis, body weight fell by 0.30 kg at 600 mg/day.
- Insulin resistance — homeostatic model assessment of insulin resistance fell in the Akbari 2018 meta-analysis of people with metabolic diseases.
- Blood lipids — triglycerides, total and low-density lipoprotein cholesterol fell in the Akbari 2018 meta-analysis; in Jibril 2022 the effects on triglycerides and low-density lipoprotein cholesterol were statistically significant but below clinically important thresholds.
- Fatty liver — a 2026 meta-analysis of seven randomized trials in non-alcoholic fatty liver disease (414 participants) found that alpha-lipoic acid did not improve liver enzymes, lipid profiles, glycemic indices, adipocytokines or obesity measures (Li 2026).
The trials in metabolic syndrome and prediabetes were small and short.
Alpha-Lipoic Acid With Other Glucose-Lowering Agents: What Was Studied
- Diabetes medicines — a single-dose study in 24 healthy volunteers found no drug interaction between alpha-lipoic acid and glibenclamide (glyburide) or acarbose, in blood levels or in insulin and glucose (Gleiter 1999); longer combined use was not examined there.
- Metformin — both alpha-lipoic acid (in animal studies) and metformin activate AMP-activated protein kinase. The meta-analyses above did not report a separate result for alpha-lipoic acid added to metformin.
- Supplement combinations — the trials on this page tested alpha-lipoic acid alone against placebo. PubMed searches for alpha-lipoic acid combined with berberine or metformin are listed under Key Research Papers.
Other compounds studied for blood sugar are covered on their own pages: berberine, cinnamon, chromium, magnesium glycinate, vitamin D3 and coenzyme Q10 (CoQ10).
Doses Used in Studies
These are the doses and schedules the cited studies used, not instructions.
- Insulin sensitivity (clamp studies) — 600, 1,200 or 1,800 mg/day orally for 4 weeks (Jacob 1999); 600 mg twice daily for 4 weeks (Konrad 1999).
- Hemoglobin A1c, glucose and weight — the Jibril 2022 meta-analysis modeled oral doses in steps of 500 mg/day; fasting glucose and low-density lipoprotein cholesterol fell up to 600 mg/day, and body weight fell linearly above 600 mg/day.
- Weight — the Kucukgoncu 2017 meta-analysis found no relationship between dose and weight change.
- Diabetic neuropathy — 600 mg/day was the dose most trials used; see the neuropathy page.
Form. In a small crossover trial in progressive multiple sclerosis, 600 mg of R-ALA gave R-ALA blood levels bioequivalent to 1,200 mg of the racemic mixture (Cameron 2020).
Food. The Linus Pauling Institute summarizes that taking lipoic acid with food decreased peak plasma concentrations by about 30% and total plasma concentrations by about 20%, and that plasma concentrations generally peak within an hour or less and decline rapidly.
Hypoglycemia and Diabetes Medicines: What the Research Shows
Because alpha-lipoic acid lowered fasting glucose modestly in meta-analyses, the question arises whether adding it to glucose-lowering medicines increases the risk of low blood sugar.
- Interaction study — in 24 healthy volunteers, single doses of alpha-lipoic acid given with glibenclamide (glyburide) or acarbose changed neither drug's blood levels nor insulin and glucose responses (Gleiter 1999). Longer combined use, and combinations with insulin, were not examined there.
- Size of the glucose effect — in the Jibril 2022 meta-analysis of type 2 diabetes, the fall in fasting glucose was below the threshold the authors considered clinically important.
- Mechanism of risk — sulfonylureas and glinides cause insulin release regardless of blood glucose and can cause hypoglycemia on their own; metformin, dipeptidyl peptidase-4 (DPP-4) inhibitors, sodium-glucose cotransporter-2 (SGLT2) inhibitors and glucagon-like peptide-1 (GLP-1) agonists rarely do when used alone. None of the trials on this page studied alpha-lipoic acid combined with each of these drug classes.
- Insulin autoimmune syndrome — a separate, immune-mediated cause of hypoglycemia linked to alpha-lipoic acid (next section).
Decisions about medicines and supplements belong with a clinician.
Insulin Autoimmune Syndrome (Hirata Disease)
Insulin autoimmune syndrome (IAS), also called Hirata disease after its first description in Japan in 1970, is a rare, immune-mediated cause of hypoglycemia with high levels of insulin autoantibodies (Cappellani 2020). The autoantibodies bind insulin; after a meal they can keep insulin from acting, and later they release it regardless of blood glucose, causing hypoglycemia.
Who it has been reported in. In Japanese people IAS is associated with the HLA-DRB1*04:06 allele and often follows exposure to sulfhydryl-containing compounds, including lipoic acid (Gullo 2014; Uchigata 2007). It is not limited to East Asian people: Gullo et al. (2014) described six white European patients taking alpha-lipoic acid 600 mg/day whose fasting and post-meal hypoglycemia began 30–120 days after starting it; five carried HLA-DRB1*04:03 and one HLA-DRB1*04:06. The authors noted that HLA-DRB1*04:03 is more common in white and other populations, and that growing alpha-lipoic acid use may lead to more cases.
The European Food Safety Authority's 2021 opinion reviewed 49 case reports in which IAS developed after alpha-lipoic acid; in all of them IAS resolved within weeks to months after alpha-lipoic acid was stopped. European Food Safety Authority (EFSA) concluded that alpha-lipoic acid added to foods, including supplements, is likely to increase IAS risk in people with certain genetic variants who cannot be identified without genetic testing, that no dose below which IAS is not expected could be set, and that incidence in Europe is low — likely lower than in Japan, estimated at 0.017 per 100,000 inhabitants in 2017–2018 (European Food Safety Authority 2021).
What the case reports describe
- Spontaneous hypoglycemia, often fasting or a few hours after meals, in people not taking insulin
- Diagnosis by finding insulin autoantibodies in the blood, after other causes of high-insulin hypoglycemia are excluded (Cappellani 2020)
- In the Gullo series, stopping alpha-lipoic acid reduced hypoglycemic episodes; all six patients were treated with glucose and prednisone
- IAS is often self-remitting; Cappellani (2020) describes management mostly by dietary measures, with drugs in severe cases
How the Trials Measured Glucose
The studies on this page measured glucose with fasting blood tests, hemoglobin A1c, oral and intravenous glucose tolerance tests, and insulin clamp studies. None of the cited trials used continuous glucose monitoring (CGM) to measure alpha-lipoic acid's effect, so there are no trial data on how alpha-lipoic acid changes CGM measures such as time-in-range.
CGM systems record glucose every few minutes and report measures such as time-in-range and overnight glucose; see the CGM page for how these are interpreted.
Key Research Papers
- Akbari M, Ostadmohammadi V, Lankarani KB, Tabrizi R, Kolahdooz F, Khatibi SR, Asemi Z (2018). The effects of alpha-lipoic acid supplementation on glucose control and lipid profiles among patients with metabolic diseases: A systematic review and meta-analysis of randomized controlled trials. Metabolism: Clinical and Experimental 87:56-69. — PubMed PMID: 29990473
- Jibril AT, Jayedi A, Shab-Bidar S (2022). Efficacy and safety of oral alpha-lipoic acid supplementation for type 2 diabetes management: a systematic review and dose-response meta-analysis of randomized trials. Endocrine Connections 11(10):e220322. — PubMed PMID: 36006850
- Kucukgoncu S, Zhou E, Lucas KB, Tek C (2017). Alpha-lipoic acid (ALA) as a supplementation for weight loss: results from a meta-analysis of randomized controlled trials. Obesity Reviews 18(5):594-601. — PubMed PMID: 28295905
- Jacob S, Ruus P, Hermann R, Tritschler HJ, Maerker E, Renn W, et al. (1999). Oral administration of RAC-alpha-lipoic acid modulates insulin sensitivity in patients with type-2 diabetes mellitus: a placebo-controlled pilot trial. Free Radical Biology & Medicine 27(3-4):309-14. — PubMed PMID: 10468203
- Konrad T, Vicini P, Kusterer K, Höflich A, Assadkhani A, Böhles HJ, et al. (1999). alpha-Lipoic acid treatment decreases serum lactate and pyruvate concentrations and improves glucose effectiveness in lean and obese patients with type 2 diabetes. Diabetes Care 22(2):280-7. — PubMed PMID: 10333946
- Lee WJ, Song KH, Koh EH, Won JC, Kim HS, Park HS, et al. (2005). Alpha-lipoic acid increases insulin sensitivity by activating AMPK in skeletal muscle. Biochemical and Biophysical Research Communications 332(3):885-91. — PubMed PMID: 15913551
- Estrada DE, Ewart HS, Tsakiridis T, Volchuk A, Ramlal T, Tritschler H, et al. (1996). Stimulation of glucose uptake by the natural coenzyme alpha-lipoic acid/thioctic acid: participation of elements of the insulin signaling pathway. Diabetes 45(12):1798-804. — PubMed PMID: 8922368
- Shay KP, Moreau RF, Smith EJ, Smith AR, Hagen TM (2009). Alpha-lipoic acid as a dietary supplement: molecular mechanisms and therapeutic potential. Biochimica et Biophysica Acta 1790(10):1149-60. — PubMed PMID: 19664690
- Gleiter CH, Schreeb KH, Freudenthaler S, Thomas M, Elze M, Fieger-Büschges H, et al. (1999). Lack of interaction between thioctic acid, glibenclamide and acarbose. British Journal of Clinical Pharmacology 48(6):819-25. — PubMed PMID: 10594485
- Li T, Liu H, Zeng J (2026). Effects of alpha-lipoic acid supplementation on patients with nonalcoholic fatty liver disease: a systematic review and meta-analysis of randomized clinical trials. BMC Endocrine Disorders 26(1):133. — PubMed PMID: 41917882
- Gullo D, Evans JL, Sortino G, Goldfine ID, Vigneri R (2014). Insulin autoimmune syndrome (Hirata Disease) in European Caucasians taking α-lipoic acid. Clinical Endocrinology 81(2):204-9. — PubMed PMID: 24111525
- Uchigata Y (2007). The novel agent, alpha lipoic acid, can cause the development of insulin autoimmune syndrome. Internal Medicine 46(17):1321-2. — PubMed PMID: 17827827
- Cappellani D, Macchia E, Falorni A, Marchetti P (2020). Insulin Autoimmune Syndrome (Hirata Disease): A Comprehensive Review Fifty Years After Its First Description. Diabetes, Metabolic Syndrome and Obesity 13:963-978. — PubMed PMID: 32308449
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA); Turck D, Castenmiller J, de Henauw S, Hirsch-Ernst KI, Kearney J, Knutsen HK, et al. (2021). Scientific opinion on the relationship between intake of alpha-lipoic acid (thioctic acid) and the risk of insulin autoimmune syndrome. EFSA Journal 19(6):e06577. — PubMed PMID: 34122657
- Cameron M, Taylor C, Lapidus J, Ramsey K, Koop D, Spain R (2020). Gastrointestinal Tolerability and Absorption of R- Versus R,S-Lipoic Acid in Progressive Multiple Sclerosis: A Randomized Crossover Trial. Journal of Clinical Pharmacology 60(8):1099-1106. — PubMed PMID: 32212340
PubMed Topic Searches
- PubMed: ALA HbA1c
- PubMed: ALA insulin sensitivity
- PubMed: ALA AMPK activation
- PubMed: ALA GLUT4 translocation
- PubMed: ALA + metformin combination
- PubMed: ALA + berberine combination
- PubMed: ALA polycystic ovary syndrome (PCOS)
- PubMed: ALA non-alcoholic fatty liver disease (NAFLD)
- PubMed: ALA gestational diabetes
Connections
- Free Radicals & Your Antioxidant Network — interactive animation
- Alpha Lipoic Acid Overview
- Alpha-Lipoic Acid Benefits Hub
- Alpha-Lipoic Acid for Neuropathy
- Alpha-Lipoic Acid for Mitochondria
- Alpha-Lipoic Acid for Neuroprotection
- Diabetes
- Diabetes Remission
- Hemoglobin A1c
- Fasting Insulin
- Continuous Glucose Monitor
- Berberine
- Cinnamon
- Gymnema
- Magnesium Glycinate
- Chromium
- Vitamin D3
- Coenzyme Q10
- Blood Sugar (General)
- Anti-Inflammatory Diet
- Metformin — a first-line diabetes drug that, like alpha-lipoic acid in animal studies, activates AMP-activated protein kinase.
- History