Spirulina for Allergic Rhinitis
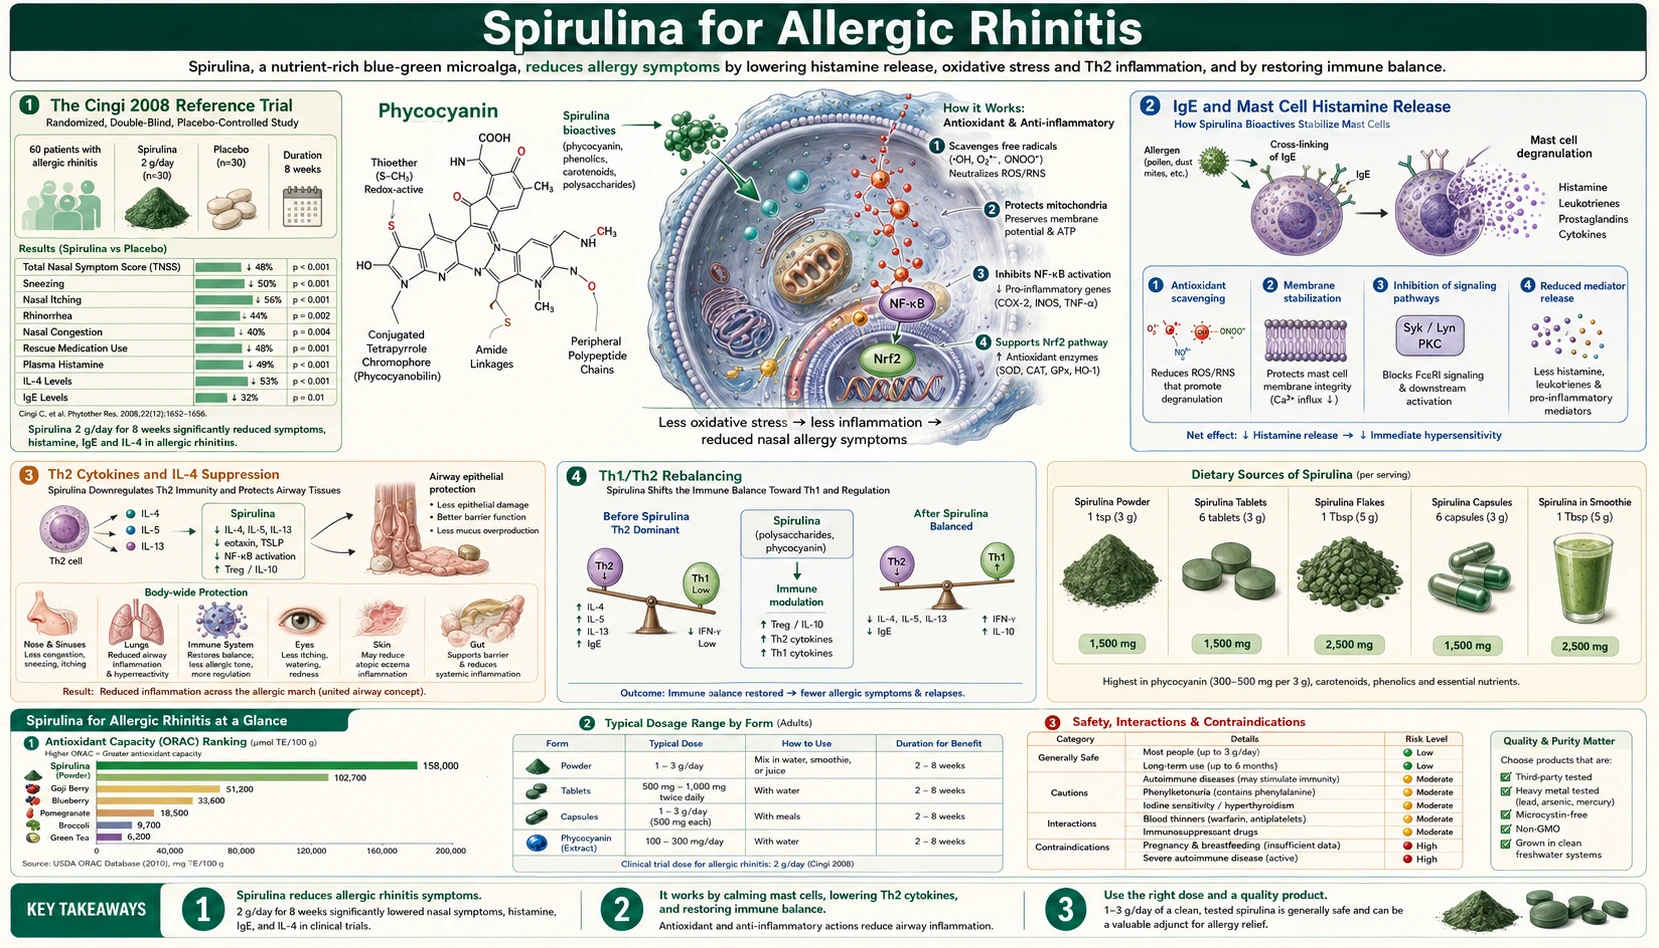
Allergic rhinitis is the single clinical indication where Spirulina has the most consistent and best-controlled randomized trial evidence. The Cingi 2008 double-blind placebo-controlled trial in patients with allergic rhinitis — published in European Archives of Oto-Rhino-Laryngology — found that Spirulina significantly improved nasal discharge, sneezing, nasal congestion, and itching compared with placebo (P < 0.001). A separate 2020 randomized trial in 53 patients compared Spirulina 2 g/day with cetirizine 10 mg/day for two months and reported greater improvement in runny nose, nasal obstruction, and reduced smell in the Spirulina group. The mechanism is suppression of IgE-driven mast cell histamine release, downregulation of IL-4 production by Th2 cells, and rebalancing of the Th1/Th2 cytokine axis — producing the same end result as antihistamine drugs but through a completely different molecular pathway. Spirulina is one of several natural interventions with controlled trials in allergic rhinitis (butterbur has the larger trial record), a finding most relevant to people who tolerate antihistamines poorly (sedation, anticholinergic effects, tachyphylaxis) or who prefer a non-pharmaceutical option.
Table of Contents
- The Cingi 2008 Reference Trial
- IgE and Mast Cell Histamine Release
- Th2 Cytokines and IL-4 Suppression
- Th1/Th2 Rebalancing
- Polysaccharide Effects on Dendritic Cells
- Spirulina vs Antihistamines — Head-to-Head Data
- Allergic Asthma Overlap
- Atopic Dermatitis Suggestive Evidence
- Doses Used in Allergic Rhinitis Research
- Cautions in the Research
- Key Research Papers
- Connections
- Featured Videos
The Cingi 2008 Reference Trial
The Cingi et al. 2008 trial, from the ENT department of Eskisehir Osmangazi University in Turkey, is the trial most often cited for Spirulina in allergic rhinitis. What its published abstract reports:
- Design: double-blind, placebo-controlled, evaluating the effectiveness and tolerability of Spirulina in patients with allergic rhinitis
- Outcomes: symptoms and physical findings, including nasal discharge, sneezing, nasal congestion, and itching
- Result: Spirulina significantly improved the symptoms and physical findings compared with placebo (P < 0.001)
- Authors' conclusion: Spirulina is clinically effective on allergic rhinitis compared with placebo, and further studies are needed to clarify the mechanism
The abstract does not give the number of participants, the dose, or the trial length, and figures for these that circulate online are not confirmed by it. It remains a single trial from one centre; a 2020 trial against cetirizine (below) is the only other controlled human trial in allergic rhinitis cited on this page.
IgE and Mast Cell Histamine Release
The proposed mechanism for Spirulina in allergic rhinitis starts from the pathophysiology. Allergic rhinitis is an IgE-mediated type I hypersensitivity reaction. The cascade:
- An aeroallergen (pollen, dust mite, animal dander, mold spore) is presented to a naive B cell by a dendritic cell in mucosal lymphoid tissue under Th2-cytokine conditions (IL-4 in particular)
- The B cell undergoes class-switch recombination from IgM to IgE
- The allergen-specific IgE binds to high-affinity FcepsilonRI receptors on tissue mast cells and circulating basophils, "arming" them
- On subsequent allergen exposure, allergen cross-links the IgE on mast cell surfaces, triggering degranulation
- Mast cells release histamine, tryptase, prostaglandin D2, leukotrienes (LTC4, LTD4, LTE4), and chemokines that recruit eosinophils
- The cascade produces the classic allergic rhinitis symptoms: rhinorrhea (histamine on H1 receptors), congestion (vasodilation), sneezing (sensory nerve stimulation), itching (sensory nerve stimulation)
Conventional antihistamines (loratadine, fexofenadine, cetirizine, levocetirizine) block H1 receptors on tissues, preventing histamine's downstream effects. They do not prevent mast cell degranulation, so the inflammatory mediators are still released — just unable to bind H1 receptors.
Spirulina operates upstream. In vitro and in animal models, Spirulina extracts inhibit IgE-mediated mast cell degranulation, reducing the release of histamine, tryptase, and downstream chemokines. This is mechanistically more comparable to mast-cell-stabilizer drugs (cromolyn sodium) than to antihistamines, although the effect appears to involve both surface IgE-FcepsilonRI signaling interference and intracellular signaling pathway modulation.
Th2 Cytokines and IL-4 Suppression
Beyond acute mast cell stabilization, Spirulina addresses the upstream Th2 polarization that drives initial IgE production and the ongoing allergic inflammation. The Mao et al. study (UC Davis) demonstrated that Spirulina supplementation in human subjects reduced IL-4 production by stimulated peripheral blood mononuclear cells (PBMCs) by approximately 32%.
This is mechanistically important because:
- IL-4 drives B-cell class-switching to IgE (the antibody isotype responsible for allergic disease)
- IL-4 promotes Th2 polarization of naive T cells encountering antigen
- IL-4 amplifies mucosal eosinophil recruitment
- IL-4 sustains the survival of Th2 cells already polarized to the allergic phenotype
Reducing IL-4 production interrupts the self-amplifying allergic inflammation loop. New IgE production is reduced, new Th2 cells are not as readily polarized, and the existing Th2 population is not as well sustained. The clinical implication is that the symptomatic benefit of Spirulina supplementation may continue to grow over months as the underlying immunologic state shifts, not just provide acute symptom relief.
Th1/Th2 Rebalancing
The atopic march of childhood — eczema, food allergy, asthma, allergic rhinitis — is associated with a developmental skewing of the immune system toward Th2 polarization. The "hygiene hypothesis" framework suggests that reduced infectious-disease exposure in early childhood (cleaner water, vaccines, antibiotics) leaves the immune system inadequately educated by Th1-promoting infectious stimuli, resulting in a population-level shift toward Th2-dominated atopic disease.
The implication for therapy is that interventions that shift the Th1/Th2 balance toward Th1 may have systemic anti-atopic effects, going beyond simple symptom management. Spirulina's polysaccharide-mediated immune effects, particularly through immulina and calcium-spirulan, promote Th1-type cytokine production (IFN-gamma, IL-12) by dendritic cells and natural killer cells, while reducing Th2 cytokine production.
Hayashi et al. demonstrated in mice that oral Spirulina enhanced both serum IgG production (Th1-associated antibody isotype) and reduced serum IgE production (Th2-associated allergic antibody isotype). The Th1/Th2 ratio shift suggests that long-term Spirulina supplementation may contribute to a more durable improvement in atopic disease beyond simply suppressing symptoms during exposure periods.
The Th1/Th2 paradigm and its role in atopic and autoimmune disease are covered on the Th1/Th2 Balance page.
Polysaccharide Effects on Dendritic Cells
Two specific Spirulina polysaccharides — immulina and calcium-spirulan — act directly on dendritic cells through pattern-recognition receptors (TLR2, TLR4, dectin-1). The dendritic-cell engagement triggers production of IL-12, which polarizes naive T cells toward Th1 rather than Th2. This provides the molecular basis for the Th1/Th2 shift observed at the whole-system level.
Notably, immulina also enhances natural killer (NK) cell cytotoxic activity, which is part of innate antiviral defense and contributes to the broader immune-supporting effects of Spirulina that extend beyond allergy. The dual action — reducing pathologic Th2-driven allergic inflammation while enhancing protective NK-cell function — is one of the more elegant aspects of the Spirulina pharmacology.
Spirulina vs Antihistamines — Head-to-Head Data
Nourollahian and colleagues (2020, Mashhad University of Medical Sciences, Iran) randomized 53 patients with allergic rhinitis to Spirulina 2 g/day or cetirizine 10 mg/day for two months. There was no placebo group and no combined-therapy group. Findings reported in the paper:
- Symptoms: runny nose (P = 0.021), nasal obstruction (P = 0.039), and reduced sense of smell (P = 0.030) improved significantly more in the Spirulina group than in the cetirizine group
- Daily life: sleep, daily work, and social activity improved significantly in the Spirulina group (P < 0.05)
- Inflammatory markers: after one month, IL-1α, IL-1β, and IL-4 were significantly lower and IL-10 significantly higher in the Spirulina group
- Authors' conclusion: Spirulina was more effective than cetirizine for the cardinal symptoms and can be considered an alternative treatment
The trial was small, from one centre, and compared two active treatments without a placebo, so it cannot show how much of either effect was placebo response. Cetirizine is an established fast-acting antihistamine; the trial measured outcomes over weeks, not hours.
Allergic Asthma Overlap
Allergic asthma shares the IgE-mast-cell-Th2 axis with allergic rhinitis, and the two conditions co-exist in a majority of atopic patients. The Spirulina effects on Th2 cytokine production and mast cell stabilization would, in principle, translate to benefit in allergic asthma as well.
The trial evidence in asthma specifically is much weaker than for allergic rhinitis. Small open-label and observational studies have suggested reduced inhaler use and improved asthma control questionnaire scores in patients adding Spirulina to standard asthma therapy, but the randomized controlled trials with bronchial challenge endpoints and objective spirometry have not been done.
Those small studies looked at Spirulina only as an adjunct added to standard asthma therapy. None tested it as a replacement for inhaled corticosteroids, long-acting beta-agonists, or rescue albuterol, and the research does not support substituting it for them in established asthma. The risk of an asthma exacerbation from inadequate maintenance therapy substantially exceeds any potential benefit from Spirulina.
Allergic asthma management is covered on the Allergic Asthma page.
Atopic Dermatitis Suggestive Evidence
Atopic dermatitis (eczema) shares the Th2 polarization and IgE-mediated mechanisms with allergic rhinitis. Small observational studies and a few open-label trials have suggested benefit of Spirulina supplementation for atopic dermatitis severity scores, particularly in pediatric patients (under physician supervision).
Randomized controlled trials specifically in atopic dermatitis remain limited. The mechanistic case is similar to allergic rhinitis — reduce Th2 cytokine production, reduce mast cell histamine release, support Th1/Th2 rebalancing. Adults with both allergic rhinitis and atopic dermatitis taking the 2 g/day allergic rhinitis dose may see incidental skin improvement, but the evidence does not support Spirulina as the primary therapy for moderate-to-severe atopic dermatitis, where standard care uses topical corticosteroids, topical calcineurin inhibitors, or systemic immunosuppressants under dermatology guidance.
Doses Used in Allergic Rhinitis Research
- Standard dose: 2 g/day, the dose used in the 2020 cetirizine comparison trial, taken either as a single dose or split morning/evening. Taking it with food is commonly described as reducing any gastrointestinal discomfort.
- Start timing: the timing usually described is a start several weeks before the expected allergy season; the 2020 trial assessed inflammatory markers at one month and symptoms at two months. In perennial allergic rhinitis (year-round dust mite or pet dander), continuous use is described.
- Acute breakthrough symptoms: there is no evidence that raising the Spirulina dose acutely helps; breakthrough symptoms are conventionally treated with a short course of antihistamine (loratadine, fexofenadine, cetirizine). Baseline Spirulina supplementation does not block use of acute antihistamines.
- Combined therapy: no clinically significant drug interactions have been reported between Spirulina and intranasal corticosteroids (fluticasone, mometasone, budesonide), antihistamines, or leukotriene antagonists (montelukast).
- Pediatric dosing: limited safety data for high-dose Spirulina in children. Modest dietary amounts (1-2 g/day) appear well tolerated in school-age children; safety data at higher doses are lacking.
- Duration: described as indefinite in chronic allergic rhinitis; in purely seasonal allergic rhinitis, use is described as ending with the allergy season
- Forms: capsules or tablets are easier than powder for daily compliance at the 2 g/day dose
Cautions in the Research
- Severe asthma — the research does not support Spirulina as a substitute for asthma controller therapy; inadequate controller therapy carries a risk of life-threatening exacerbation
- Anaphylaxis history — Spirulina does not prevent anaphylaxis. Spirulina use does not change the standard guidance that people with food allergy, insect sting allergy, or drug allergy with anaphylaxis history carry epinephrine auto-injectors.
- Autoimmune disease — theoretical concern that Th1-promoting effects could exacerbate Th1-driven autoimmune disease (multiple sclerosis, rheumatoid arthritis, lupus). Clinical evidence is mixed and largely reassuring, but the research raises a theoretical concern for people with active autoimmune disease; decisions about supplements belong with a clinician.
- Source quality — heavy metal and microcystin testing is regarded as essential, as for all Spirulina supplementation
- Phenylketonuria — absolute contraindication
- Pregnancy — insufficient data for high-dose use; modest dietary amounts are considered likely safe
- Immunosuppressive therapy — the research raises a theoretical concern for people on cyclosporine, tacrolimus, or biologic immune-modulators (rituximab, dupilumab, omalizumab): a possible interaction with the targeted immunologic mechanisms
- Time to effect — the trials assessed outcomes after one to two months of daily intake, so the absence of benefit at 2-3 weeks falls inside that window
Key Research Papers
- Cingi C, Conk-Dalay M, Cakli H, Bal C (2008). The effects of Spirulina on allergic rhinitis. European Archives of Oto-Rhino-Laryngology. — PubMed
- Nourollahian M, Rasoulian B, Gafari A, Anoushiravani M, Jabari F, Bakhshaee M (2020). Clinical comparison of the efficacy of spirulina platensis and cetirizine for treatment of allergic rhinitis. Acta Otorhinolaryngologica Italica 40(3):224-229 — PubMed PMID: 32773785
- Mao TK, Van de Water J, Gershwin ME (2005). Effects of a Spirulina-based dietary supplement on cytokine production from allergic rhinitis patients. Journal of Medicinal Food. — PubMed PMID: 15857205
- Mao TK, Van de Water J, Gershwin ME. Effect of Spirulina on the secretion of cytokines from peripheral blood mononuclear cells. Journal of Medicinal Food. — PubMed PMID: 19281334
- Hayashi O et al. Class-specific influence of dietary Spirulina platensis on antibody production in mice. Journal of Nutritional Science and Vitaminology. — PubMed PMID: 10197315
- Yang HN et al. Spirulina platensis inhibits anaphylactic reaction. Life Sciences. — PubMed PMID: 9324065
- Kim HM et al. Inhibitory effect of mast cell-mediated immediate-type allergic reactions in rats by Spirulina. Biochemical Pharmacology. — PubMed PMID: 9605430
- Pugh N et al. Isolation of three high molecular weight polysaccharide preparations with potent immunostimulatory activity from Spirulina platensis. Planta Medica. — PubMed PMID: 11731916
- Lobner M et al. Enhancement of human adaptive immune responses by administration of a high-molecular-weight polysaccharide extract from the cyanobacterium Arthrospira platensis. Journal of Medicinal Food. — PubMed PMID: 18598175
- Nemoto-Kawamura C et al. Phycocyanin enhances secretory IgA antibody response and suppresses allergic IgE antibody response in mice. Journal of Nutritional Science and Vitaminology. — PubMed
- Selmi C, Leung PSC, Fischer L et al. The effects of Spirulina on anemia and immune function in senior citizens. Cellular and Molecular Immunology. — PubMed PMID: 21278762
- Karkos PD, Leong SC, Karkos CD, Sivaji N, Assimakopoulos DA. Spirulina in clinical practice: evidence-based human applications. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 18955364
- Hayashi T, Hayashi K, Maeda M, Kojima I. Calcium-spirulan, an inhibitor of enveloped virus replication, from a blue-green alga Spirulina platensis. Journal of Natural Products. — PubMed
PubMed Topic Searches
Connections
- Spirulina Overview
- Spirulina Benefits Hub
- Spirulina Phycocyanin & Antioxidant
- Spirulina Cholesterol & Cardiovascular
- Spirulina Athletic Performance
- Allergic Rhinitis
- Atopic Dermatitis (Eczema)
- Allergic Asthma
- Th1/Th2 Balance
- Stinging Nettle
- Butterbur
- Vitamin C (Natural Antihistamine)
- Quercetin (Mast Cell Stabilizer)
- Immune Boosting
- History