Butterbur
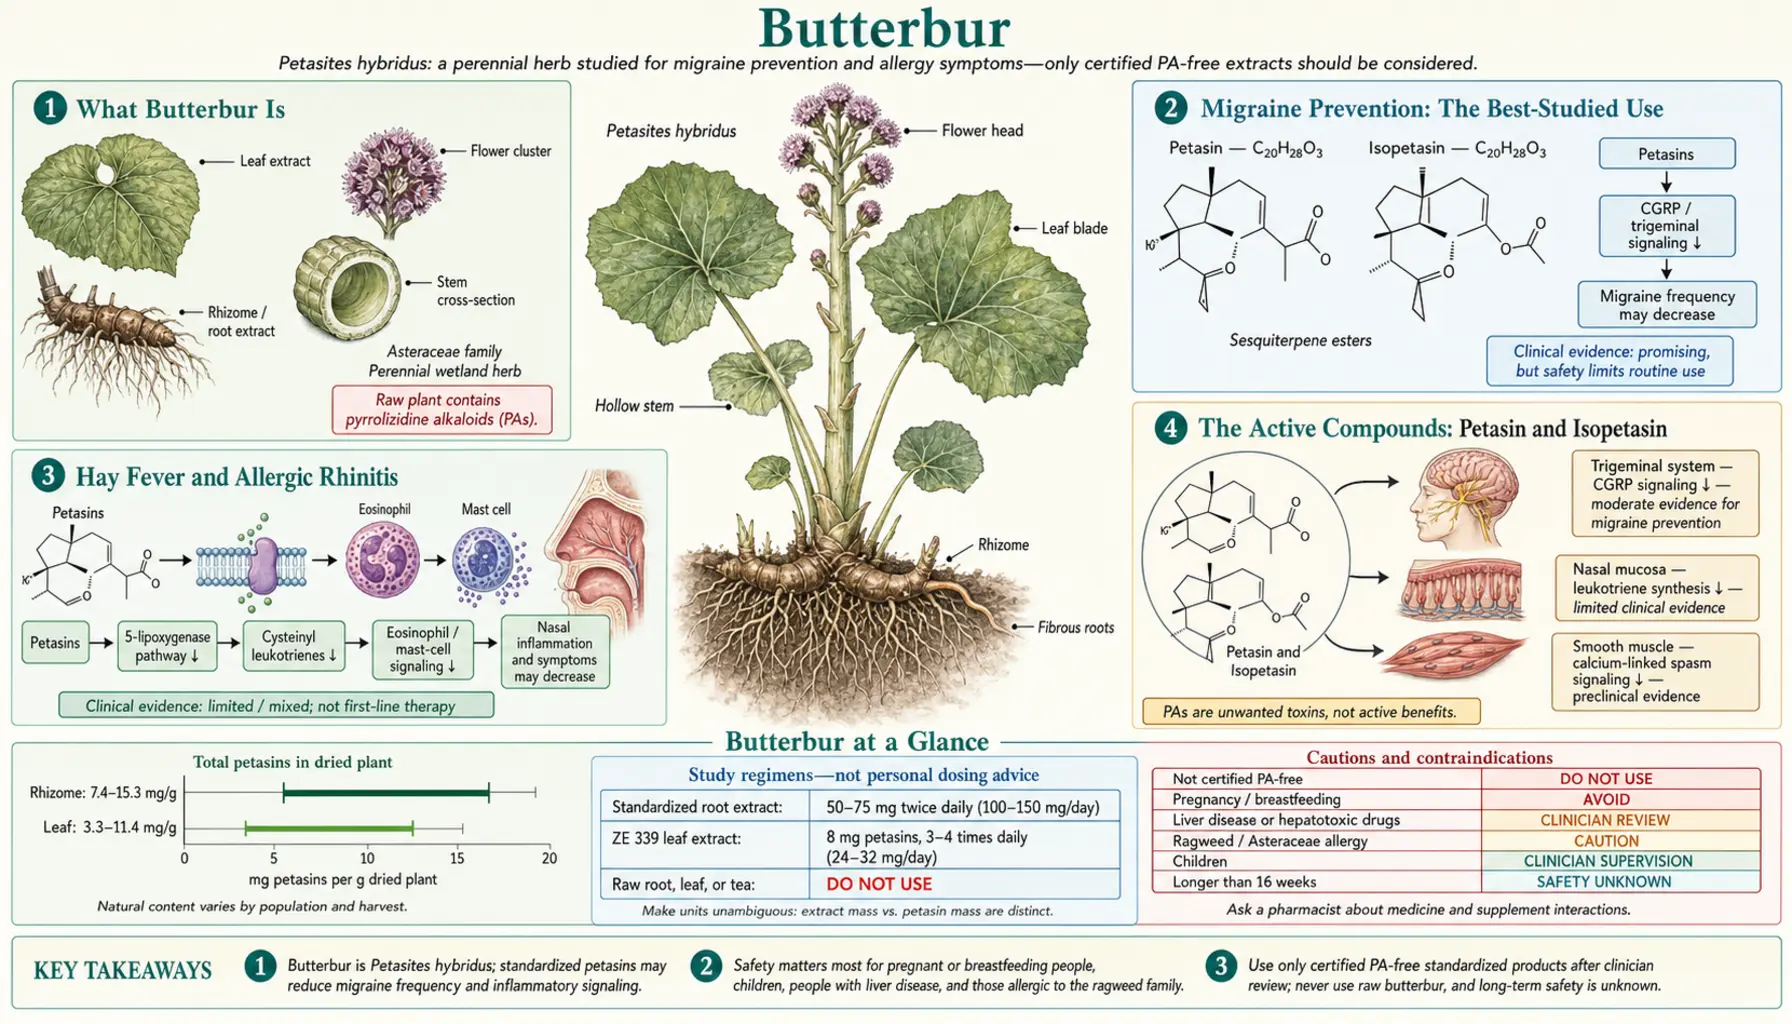
Butterbur (Petasites hybridus) is one of the rare herbs that has genuinely good clinical evidence behind it — and, at the same time, one of the most important cautionary tales in herbal medicine. Carefully processed butterbur extracts have reduced migraine frequency and eased hay fever in real randomized trials, and for a while the herb even earned a top rating from a major neurology guideline. But the raw plant contains natural compounds called pyrrolizidine alkaloids that can seriously damage the liver and may cause cancer. Because of those safety concerns, that guideline endorsement was later withdrawn, and butterbur products have been restricted or pulled from the market in several countries. This page explains, plainly and honestly, what butterbur can do, how it works, and why the research applies only to certified “PA-free” standardized extracts — not to the raw plant or homemade teas, which contain the liver-damaging alkaloids, or to unverified products, which may.
Interactive Visualization Histamine, Mast Cells & Allergy — trigger a mast cell yourself Arm a mast cell with immunoglobulin E (IgE), let the allergen cross-link it, and watch histamine burst out to raise a wheal — then block the H1 receptor and see symptoms fall while histamine still pours out. Launch →
Table of Contents
- What Butterbur Is
- Migraine Prevention: The Best-Studied Use
- Hay Fever and Allergic Rhinitis
- The Active Compounds: Petasin and Isopetasin
- How Butterbur Is Thought to Work
- The Critical Safety Issue: Pyrrolizidine Alkaloids
- Who the Research Raises Concerns For
- Choosing a Product and Typical Dosing
- Lower-Risk Options for the Same Problems
- The Honest Bottom Line
- Key Research Papers
- Connections
- Featured Videos
What Butterbur Is
Butterbur is a hardy perennial plant that grows in damp, marshy ground — riverbanks, ditches, and wet meadows across Europe, Asia, and parts of North America. It sends up thick flower spikes in early spring, followed by very large, rhubarb-like leaves. Those broad leaves are where the name comes from: in the days before refrigeration, they were used to wrap butter and keep it cool. The plant belongs to the Asteraceae (daisy) family, which also includes ragweed, marigolds, and chrysanthemums — a detail that matters for people with pollen allergies, as we’ll see.
Herbalists have reached for butterbur for centuries. In medieval Europe it was a treatment for plague and fever — one old name, “pestilence wort,” reflects that use — and later for coughs, asthma, spasms, and wounds. Today, almost none of that folklore is what butterbur is studied for. Modern interest centers on two conditions with real trial support: migraine prevention and allergic rhinitis (hay fever).
Crucially, the butterbur used in those studies is not the raw herb. It is a highly processed root extract in which the dangerous pyrrolizidine alkaloids have been stripped out and the beneficial compounds concentrated and standardized. The best-known is a standardized pyrrolizidine-alkaloid-free root extract, made with carbon dioxide and with a set content of its active petasins; another, a leaf extract studied for hay fever, was developed for allergic rhinitis. When researchers say “butterbur works,” they mean these specific, purified, standardized extracts — not a plant you could pick or brew yourself.
Migraine Prevention: The Best-Studied Use
The flagship use of butterbur is preventing migraine — reducing how often attacks happen, taken daily over time, rather than stopping a headache once it starts. Here the evidence is genuinely encouraging, which is what makes the herb’s safety problems so frustrating.
An early placebo-controlled trial by Grossmann and Schmidramsl (2000) found that a standardized butterbur extract at 50 mg twice daily cut migraine frequency more than placebo. The pivotal study came in 2004, when Lipton and colleagues published a randomized trial in Neurology of 245 people. Over four months, those taking 75 mg of the standardized extract twice daily saw migraine attack frequency fall by about 48%, compared with roughly 26% on placebo — and the 75 mg dose worked better than the lower 50 mg dose. A systematic review by Agosti and colleagues (2006) of the two available trials (293 patients, both using the same proprietary root extract) found “moderate evidence of effectiveness” for a higher-than-recommended dose, and said further rigorous studies were required to confirm effectiveness and long-term safety before the extract could be recommended.
That evidence was strong enough that, in 2012, the American Academy of Neurology and the American Headache Society issued a guideline (Holland and colleagues) rating Petasites (butterbur) as “Level A” — meaning “effective” and worth offering — for episodic migraine prevention. It was the only herbal remedy to reach that top tier.
But here is the honest and essential part of the story: that guideline was later retired. In 2015 the American Academy of Neurology withdrew the recommendation, driven largely by mounting concern about butterbur’s liver safety and uncertainty about whether marketed products were reliably free of the toxic alkaloids (see the safety section below). The published guideline record now literally carries a “[RETIRED]” label. So the accurate picture is this: butterbur earned its high rating on real efficacy data, and that endorsement was pulled not because the herb stopped working, but because experts decided the safety risks and quality uncertainties outweighed the benefit. Both halves of that sentence are true, and you deserve to hear both.
Hay Fever and Allergic Rhinitis
Butterbur’s second well-studied use is seasonal allergic rhinitis — the sneezing, itchy eyes, and runny nose of hay fever. Several trials of a standardized leaf extract studied for hay fever are surprisingly positive.
In a randomized trial published in BMJ in 2002, Schapowal compared butterbur with cetirizine (a standard antihistamine) for seasonal allergic rhinitis. Both improved symptoms to a comparable degree — but butterbur did not cause the drowsiness that some antihistamines can. A 2005 study by the same investigator compared butterbur with fexofenadine and placebo for intermittent allergic rhinitis, finding butterbur as effective as the antihistamine and both better than placebo. A smaller mechanistic study by Lee and colleagues (2003) showed butterbur blunted the nose’s reactivity to an inhaled challenge.
This is good evidence — comparable to antihistamines in several trials — but it is not the last word. The studies are relatively few and mostly used one proprietary product, and independent reviews have judged the overall evidence promising but not definitive. The evidence for butterbur in asthma is weaker still. And, as with migraine, every bit of this benefit comes with the same overriding safety condition: it applies only to a certified, PA-free, standardized extract.
The Active Compounds: Petasin and Isopetasin
The compounds credited with butterbur’s benefits are a family of sesquiterpene esters called petasins — chiefly petasin and its close relative isopetasin (along with oxopetasin). Good standardized extracts are measured and labeled by their petasin content, so “standardized to petasins” is a marker of a quality product.
It is worth being clear that petasins are the good molecules. They are entirely separate from the pyrrolizidine alkaloids — the harmful molecules — that also occur naturally in the raw plant. The whole point of proper manufacturing is to keep the petasins while removing the alkaloids. A well-made extract is high in petasins and, when correctly processed and tested, essentially free of pyrrolizidine alkaloids.
How Butterbur Is Thought to Work
Researchers have proposed a few overlapping mechanisms for the petasins, which help explain why one plant might help both migraine and allergy:
- Calming blood-vessel and muscle spasm. Petasin appears to reduce the flow of calcium into smooth-muscle and vascular cells, relaxing them. In migraine, this smooth-muscle and vascular effect may help stabilize the blood vessels and nerves involved in an attack.
- Damping inflammation. Petasins inhibit the production of leukotrienes — inflammatory signaling molecules that drive allergic swelling and mucus. That helps account for the hay-fever benefit and the herb’s traditional anti-spasmodic, anti-inflammatory reputation.
- Reducing inflammatory mediators generally, which may contribute to both uses.
These mechanisms are plausible and supported by laboratory work, but they remain a simplified picture rather than a fully settled account. What is settled is that the clinical results, not the mechanism, are the reason anyone considers butterbur at all.
The Critical Safety Issue: Pyrrolizidine Alkaloids
This is the section that matters most, and it comes before anything about dosing.
The raw butterbur plant — root, leaves, and all — naturally contains pyrrolizidine alkaloids (PAs), a class of compounds that are toxic to the liver and can cause cancer. PAs are known to trigger a serious liver condition called hepatic veno-occlusive disease (also called sinusoidal obstruction syndrome), in which small liver blood vessels become blocked. Some PAs are also genotoxic and carcinogenic, and they can cross the placenta into a developing baby. These are not theoretical worries; pyrrolizidine alkaloids from various plants have caused mass poisonings and liver failure around the world.
Because of this, the research draws one firm line:
- The trials used only specially processed, certified “PA-free” standardized extracts. These products are manufactured and laboratory-tested to remove the alkaloids down to strictly limited levels.
- Raw, wild-harvested, homemade, or unverified butterbur still contains the alkaloids — home-picked leaves, homemade teas or tinctures, and bulk powder of unknown origin alike. There is no known way to remove them at home.
Commercial products have also been linked to liver problems. There have been case reports of liver injury in people taking butterbur supplements, including the standardized root extract used in the migraine trials. A 2019 review by Anderson and Borlak of the reports for that extract found that most people had only mild changes in liver blood tests, but nine developed severe herb-induced liver injury; the cases resolved after the extract was stopped, though two patients needed liver transplants, and 22 patients had also taken other medicines that can harm the liver. Experts still debate whether these events reflected residual alkaloids, other constituents, or rare individual (idiosyncratic) reactions; the review’s authors judged the cases rare and idiosyncratic. The uncertainty itself is part of the problem.
Regulators have acted on these concerns. Butterbur products have been restricted or withdrawn in several countries — for example, in the United Kingdom, unlicensed butterbur products were pulled from sale over the liver-safety risk, and other European regulators have suspended or tightly limited certain products. As noted above, these same safety concerns are why the American Academy of Neurology retired its migraine guideline that had endorsed the herb. In the United States, butterbur is sold as a dietary supplement, which means the U.S. Food and Drug Administration (FDA) does not verify in advance that a given product is truly PA-free — the PA-free claim on a U.S. label rests on the manufacturer and on any third-party testing.
Who the Research Raises Concerns For
The safety concerns apply most strongly to these groups, even with a certified PA-free form:
- Pregnant or breastfeeding people. Pyrrolizidine alkaloids can cross the placenta and enter breast milk, and are hepatotoxic and potentially carcinogenic. Butterbur is not considered safe in pregnancy or lactation.
- Children. Although a few studies included young people, the same liver-safety concerns apply to children.
- Anyone with liver disease, or anyone taking other medications or supplements that can stress the liver. Butterbur adds risk to an already vulnerable organ.
- People allergic to ragweed, marigolds, daisies, or chrysanthemums. Butterbur is in the same Asteraceae plant family, so cross-reactive allergic reactions are possible. (This is a common overlap, since ragweed allergy and hay fever often go together.)
- Anyone using a product that cannot be confirmed as certified PA-free. An unverified product may contain the liver-damaging alkaloids.
Butterbur may lower blood pressure slightly. In laboratory tests on human liver cells, high petasin levels (49 times the peak blood level) together with ordinary concentrations of ibuprofen, paracetamol (acetaminophen) and naratriptan changed liver enzymes, including the CYP enzymes that break down many drugs; and in the 2019 review of liver-injury reports, 22 of the patients had also taken medicines that can harm the liver.
Choosing a Product and Typical Dosing
Product quality decides much of the risk. The quality markers are:
- Explicit “PA-free” certification — labeled as certified free of, or tested for, pyrrolizidine alkaloids.
- Standardization to petasins (petasin and isopetasin), with the amount stated on the label.
- A reputable manufacturer with independent, third-party testing.
For reference, the doses used in the clinical trials were:
- Migraine prevention: a standardized extract at 75 mg twice daily (the effective dose in the 2004 Neurology trial); 50 mg twice daily was used in earlier work but appeared less effective.
- Allergic rhinitis: the leaf extract studied for hay fever, one tablet (standardized to petasines) taken several times daily during allergy season, was the regimen in the hay-fever trials.
The signs of liver injury are yellowing of the skin or eyes (jaundice), dark urine, pale stools, persistent nausea, abdominal pain, or unusual fatigue; hospitals treat these as urgent. In the 2019 review of reported cases, the liver injury resolved after the extract was stopped. Some clinicians check liver enzymes before and during use. Butterbur is generally taken only for a limited period, not indefinitely.
Lower-Risk Options for the Same Problems
One reason many clinicians are cautious about butterbur is that reasonable, better-understood alternatives exist for both of its main uses.
For migraine prevention, options with supportive evidence and cleaner safety records include magnesium, riboflavin (vitamin B2), and coenzyme Q10, alongside prescription preventives. Feverfew is the other herb most studied for migraine, though it carries its own cautions. Butterbur and feverfew are, in fact, the two best-known migraine herbs.
For hay fever, intranasal corticosteroid sprays and non-sedating second-generation antihistamines are effective and well-characterized, and simple saline rinses help. Gentler natural options some people try include quercetin and stinging nettle.
None of this means butterbur is worthless — its trial data are real. It means that when an equally or more effective option carries less risk, clinicians usually turn to that option first.
The Honest Bottom Line
Butterbur is a genuine puzzle: an herb with real randomized-trial evidence for two common problems, migraine and hay fever, that also carries a serious, well-documented safety liability. Holding both truths at once is the only honest way to think about it.
- It can work. Standardized butterbur extract reduced migraine frequency in placebo-controlled trials and eased allergic rhinitis about as well as antihistamines. That is more than most herbs can claim.
- But the safety risk is real and specific. The raw plant is liver-toxic and potentially carcinogenic; even standardized products have been linked to liver injury and withdrawn or restricted in several countries; and the top guideline endorsement it once held was retired precisely over these concerns.
- The research applies only to certified PA-free, standardized products from independently tested makers, at the studied doses, for a limited time; the safety concerns are greatest in pregnancy, breastfeeding and childhood, and for people with liver disease or ragweed-family allergy.
- Lower-risk options exist for both uses: magnesium and riboflavin for migraine prevention, and nasal steroid sprays and antihistamines for hay fever, all with better-understood safety records.
Butterbur is a case where “natural” and “safe” are clearly not the same thing. Both the evidence and the risk are real.
Key Research Papers
- Lipton RB, Göbel H, Einhäupl KM, Wilks K, Mauskop A. Petasites hybridus root (butterbur) is an effective preventive treatment for migraine. Neurology. 2004;63(12):2240–2244. — Pivotal RCT: 75 mg twice daily cut migraine frequency about 48% vs 26% on placebo. — doi:10.1212/01.WNL.0000147290.68260.11
- Grossmann M, Schmidramsl H. An extract of Petasites hybridus is effective in the prophylaxis of migraine. Int J Clin Pharmacol Ther. 2000;38(9):430–435. — Earlier placebo-controlled trial showing reduced migraine frequency. — doi:10.5414/cpp38430
- Diener HC, Rahlfs VW, Danesch U. The first placebo-controlled trial of a special butterbur root extract for the prevention of migraine: reanalysis of efficacy criteria. Eur Neurol. 2004;51(2):89–97. — Independent reanalysis of a 60-patient trial whose original analysis had major shortcomings; concluded that “this small trial indicates that butterbur may be effective.” — doi:10.1159/000076535
- Agosti R, Duke RK, Chrubasik JE, Chrubasik S. Effectiveness of Petasites hybridus preparations in the prophylaxis of migraine: a systematic review. Phytomedicine. 2006;13(9–10):743–746. — Review of two trials (293 patients): “moderate evidence of effectiveness” for the higher dose; further rigorous studies required on effectiveness and long-term safety. — doi:10.1016/j.phymed.2006.02.008
- Oelkers-Ax R, et al. Butterbur root extract and music therapy in the prevention of childhood migraine: an explorative study. Eur J Pain. 2008;12(3):301–313. — Exploratory pediatric study of butterbur for childhood migraine. — doi:10.1016/j.ejpain.2007.06.003
- Holland S, Silberstein SD, Freitag F, et al. Evidence-based guideline update: NSAIDs and other complementary treatments for episodic migraine prevention in adults [RETIRED]. Neurology. 2012;78(17):1346–1353. — The AAN/AHS guideline that rated butterbur Level A; note the “[RETIRED]” status, withdrawn over safety concerns. — doi:10.1212/WNL.0b013e3182535d0c
- Sutherland A, Sweet BV. Butterbur: an alternative therapy for migraine prevention. Am J Health Syst Pharm. 2010;67(9):705–711. — Pharmacy review of efficacy and the importance of PA-free products. — doi:10.2146/ajhp090136
- Schapowal A; Petasites Study Group. Randomised controlled trial of butterbur and cetirizine for treating seasonal allergic rhinitis. BMJ. 2002;324(7330):144–146. — Butterbur comparable to the antihistamine cetirizine for hay fever, without sedation. — doi:10.1136/bmj.324.7330.144
- Schapowal A. Treating intermittent allergic rhinitis: a prospective, randomized, placebo and antihistamine-controlled study of butterbur extract Ze 339. Phytother Res. 2005;19(6):530–537. — The leaf extract was as effective as fexofenadine and superior to placebo. — doi:10.1002/ptr.1705
- Lee DK, Carstairs IJ, Haggart K, Jackson CM, Currie GP, Lipworth BJ. Butterbur, a herbal remedy, attenuates adenosine monophosphate induced nasal responsiveness in seasonal allergic rhinitis. Clin Exp Allergy. 2003;33(7):882–886. — Mechanistic evidence that butterbur reduces nasal reactivity. — doi:10.1046/j.1365-2222.2003.01705.x
- Anderson N, Borlak J. Hepatobiliary events in migraine therapy with herbs—the case of Petadolex, a Petasites hybridus extract. J Clin Med. 2019;8(5):652. — Review of reported liver-injury cases with a standardized butterbur root extract: nine severe cases, two needing liver transplants. — doi:10.3390/jcm8050652
- Moreira R, Pereira DM, Valentão P, Andrade PB. Pyrrolizidine alkaloids: chemistry, pharmacology, toxicology and food safety. Int J Mol Sci. 2018;19(6):1668. — Background on why pyrrolizidine alkaloids are hepatotoxic and carcinogenic. — doi:10.3390/ijms19061668
Connections
- All Herbs
- Histamine, Mast Cells & Allergy — interactive animation
- Feverfew
- Stinging Nettle
- Ginger
- Milk Thistle
- Migraine
- Pain & Allergy
- Magnesium
- Vitamin B2 (Riboflavin)
- Quercetin
- Toxins
- Magnesium, Riboflavin, and Supplements for Migraine
- Conditions on this site that reference this page: Neurology · Allergic Rhinitis (Hay Fever)