Threonine for Gut Mucin and the Intestinal Barrier
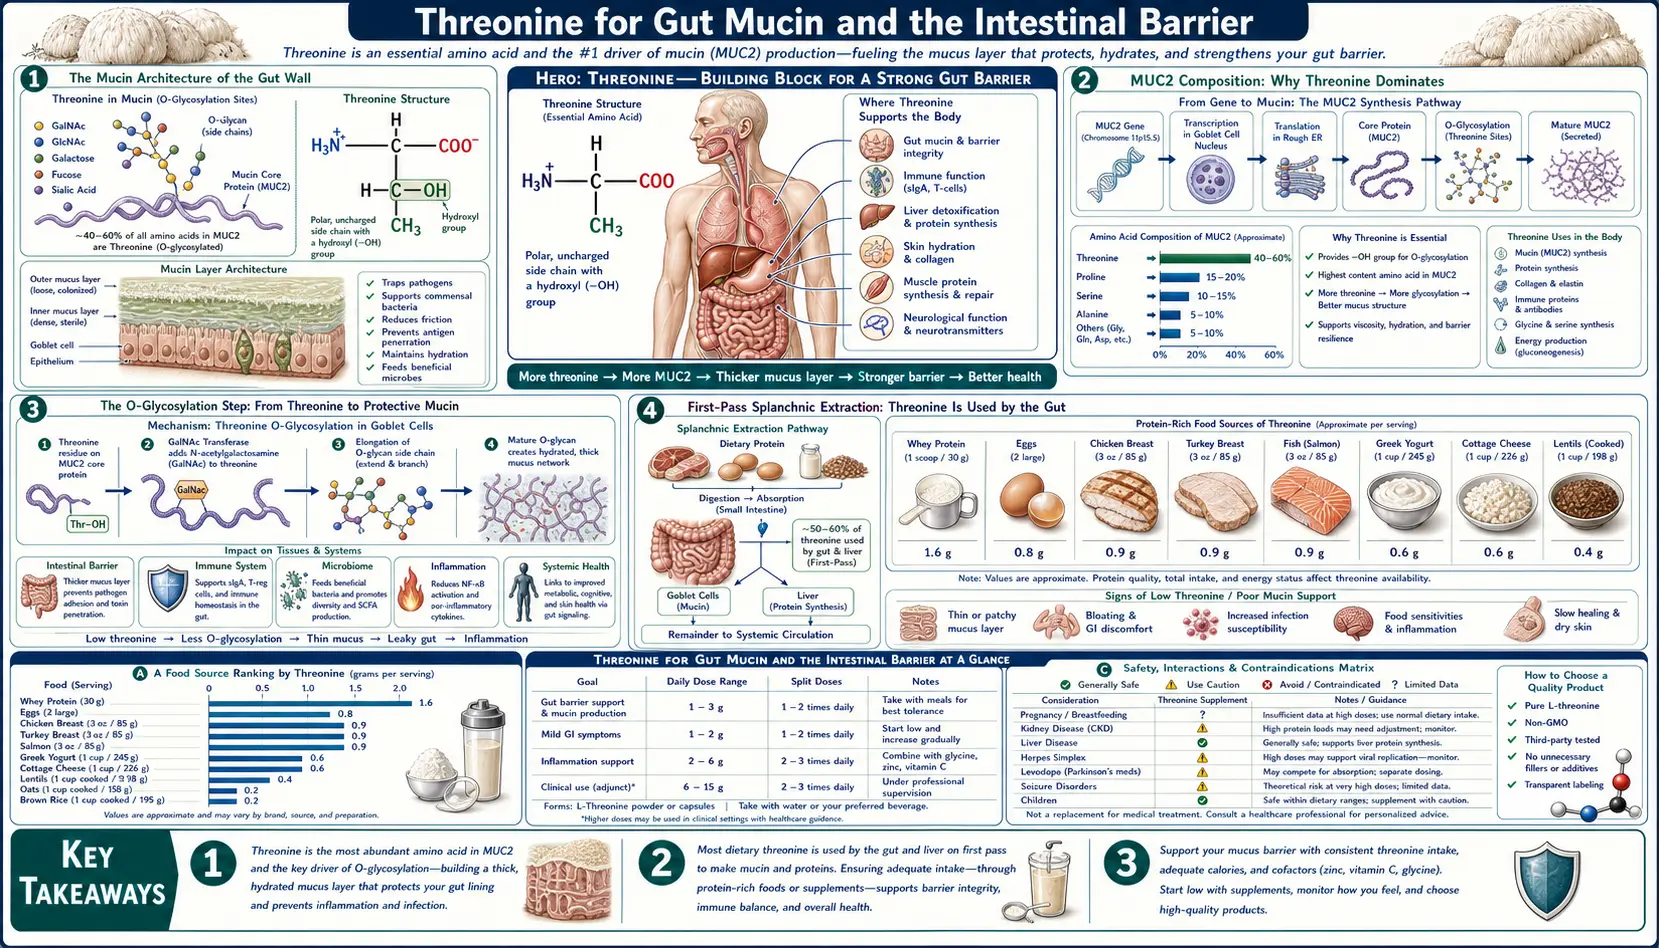
Threonine sits at the absolute foundation of intestinal-barrier biology. The dominant mucin secreted into the gut lumen — MUC2 — is roughly 30% threonine by amino-acid composition (with serine and proline filling the next two slots), making threonine the single most-required dietary amino acid for mucin synthesis. Without an intact MUC2 layer, the colon becomes directly exposed to its own bacterial inhabitants, which is the proximate mechanism that drives ulcerative colitis in MUC2-knockout mice and a recognized contributor to human inflammatory bowel disease. Wang and colleagues' 2010 piglet experiments found that both too little and too much dietary threonine damaged the lining of the small intestine and lowered its mucin production. This page walks through the chemistry of mucin O-glycosylation, why threonine demand exceeds supply at the gut wall, and what the animal data tells human patients with inflammatory bowel disease (IBD), ulcerative colitis, and post-infectious gut barrier dysfunction.
Table of Contents
- The Mucin Architecture of the Gut Wall
- MUC2 Composition: Why Threonine Dominates
- The O-Glycosylation Step
- First-Pass Splanchnic Extraction
- The Wang 2010 Piglet Studies
- The Two-Layer Colonic Mucus System
- MUC2 Knockout Mice and Spontaneous Colitis
- Translation to Human Inflammatory Bowel Disease and Ulcerative Colitis
- When Gut Bacteria Eat the Mucus Layer
- Clinical Situations and Doses Used in Practice
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Mucin Architecture of the Gut Wall
The lining of the human gastrointestinal tract is one of the largest interfaces between the body and the outside world — roughly 32 square meters of surface area when the villi and microvilli are accounted for, larger than a tennis court. This vast surface is covered continuously by a layer of mucus secreted by specialized goblet cells embedded in the epithelium. The mucus is not a passive coating. It is a structured gel built from large, heavily glycosylated proteins called mucins, and its integrity is the single most important determinant of whether the trillions of bacteria in the colonic lumen remain peacefully separated from the host or instead trigger destructive inflammation.
In the small intestine, the mucus is thinner and more permeable, allowing nutrient absorption while still providing a chemical and physical barrier to pathogens. In the colon, where the bacterial load is highest (1011-1012 organisms per gram of luminal content), the mucus is organized into two distinct layers: an inner, dense, stratified layer firmly adherent to the epithelium that is essentially bacteria-free, and an outer, looser layer that is colonized by commensal bacteria. The inner layer is renewed every hour by continuous secretion from goblet cells, and the outer layer is gradually solubilized by bacterial enzymes and shed into the stool.
The molecular building block of this mucus barrier is MUC2 (Mucin 2), a giant gel-forming mucin protein produced by goblet cells throughout the small and large intestine. Each MUC2 monomer is approximately 5,200 amino acids long, polymerizes head-to-head and tail-to-tail into massive multimers via cysteine disulfide bonds, and is so heavily glycosylated that 70-80% of its final mass is sugar rather than protein. This dense glycan coating creates the gel-like consistency that allows the mucus to trap pathogens and maintain its structural integrity under the mechanical stress of peristalsis.
MUC2 Composition: Why Threonine Dominates
The central region of MUC2 contains two large PTS (Proline-Threonine-Serine) tandem repeat domains. These regions are extraordinarily enriched in threonine, serine, and proline, and the hydroxyl groups of threonine and serine serve as the attachment points for the O-linked sugar chains that constitute the bulk of the molecule's mass.
Quantitative amino acid analysis of purified intestinal mucin yields a striking distribution:
- Threonine: approximately 28-32% of total amino acid residues
- Serine: approximately 16-20%
- Proline: approximately 13-18%
- All 17 other amino acids combined: the remaining 30-43%
For comparison, in the average tissue protein of the human body, threonine constitutes only about 5-6% of amino acid residues. The threonine content of MUC2 is therefore approximately five to six times higher than the body average. When the gut is producing mucin actively, the amino acid demand at the goblet cell is fundamentally skewed — the cell needs threonine at a rate that far exceeds what would be predicted from generic protein synthesis.
This explains an observation that has puzzled clinical nutritionists since the 1990s: dietary threonine seems to disappear into the gut. Stable-isotope tracer studies in young pigs (van Goudoever et al., Bertolo et al.) and in human infants show that a large share of dietary threonine is taken up by the splanchnic bed (gut plus liver) on first pass and never reaches systemic circulation — 70-82% in preterm infants. In healthy adult men, however, the figure was far lower, 17.9% (see the next section). In young animals, a large proportion of dietary threonine goes into building the gut lining's proteins, especially mucin.
The O-Glycosylation Step
The reason threonine matters so much to mucin is the chemistry of O-glycosylation. After the MUC2 protein backbone is synthesized in the rough endoplasmic reticulum of the goblet cell, it moves to the Golgi apparatus, where a family of enzymes called polypeptide N-acetylgalactosaminyltransferases (GalNAc-Ts) transfer a single N-acetylgalactosamine sugar onto the hydroxyl oxygen of selected threonine and serine residues. This initial GalNAc attachment is the "Tn antigen" the founding sugar of every O-linked glycan on the mucin.
From the Tn antigen, additional sugar units are added in a stepwise fashion by glycosyltransferases: galactose, N-acetylglucosamine, fucose, and terminal sialic acid or sulfate. The mature O-glycan chains extend outward from the protein backbone like the bristles of a bottle brush, creating the characteristic "Christmas tree" appearance of fully glycosylated mucin under high-resolution microscopy.
Crucially, only threonine and serine residues can serve as O-glycosylation sites — the chemistry requires a hydroxyl group on the amino acid side chain, and no other naturally occurring amino acid offers one in the right configuration (tyrosine has a hydroxyl but is positioned differently and is not used in mucin-type O-glycosylation). Because the PTS repeats of MUC2 are densely packed with threonine, almost every glycosylation site in the central region is a threonine. The polypeptide GalNAc-T family even shows substrate preference for threonine over serine in many sequence contexts (Wandall et al.), reinforcing the dominance of threonine residues as the chemical anchors for the entire glycan coat.
Without adequate threonine supply during MUC2 synthesis, two things go wrong. First, MUC2 backbones may be made with under-glycosylated PTS regions because some threonine sites are missing or substituted — the resulting mucin is structurally inferior and forms a thinner, less protective gel. Second, the total quantity of MUC2 produced drops because the goblet cell hits a threonine-limited synthesis ceiling. Either failure mode leaves the underlying epithelium exposed.
First-Pass Splanchnic Extraction
One of the most counterintuitive facts about threonine metabolism is the extraordinary fraction of dietary threonine that the gut and liver extract before it ever reaches the systemic circulation. Bertolo and colleagues at the University of Guelph in Canada documented this in newborn piglets (1998). Using a breath-test method (phenylalanine oxidation) to find the threonine requirement, they found a mean requirement of 0.19 g per kg per day when the diet was given intravenously (total parenteral nutrition, TPN, which bypasses the gut) but 0.42 g per kg per day when the identical diet was given into the stomach — the intravenous requirement was about 45% of the oral one. The gap is the threonine being intercepted and used by the gut tissue itself, primarily for mucin synthesis.
In people, the size of this first-pass uptake depends strongly on age. In eight preterm infants, the gut took up 70% of dietary threonine on first pass during full tube feeding and 82% when only part of the feed went through the gut (van der Schoor 2007, a paper titled "The gut takes nearly all"). In newborns, the splanchnic bed took up 43% of threonine but only 12% of lysine. In six healthy adult men studied with 13C tracers (Chapman 2013), however, first-pass splanchnic uptake was 17.9% for threonine and 18.5% for lysine — no different. The "gut takes nearly all" pattern is therefore an infant finding; in healthy adult men on a liquid amino-acid formula, the gut's threonine need was similar to its lysine need.
This has two possible implications. First, recommended threonine intake values calibrated to systemic requirements (such as the World Health Organization 15 mg/kg adult value) may underestimate true requirements in patients with increased gut mucin turnover — including inflammatory bowel disease, post-infectious diarrhea, post-antibiotic gut recovery, and chronic nonsteroidal anti-inflammatory drug (NSAID)-induced gut injury. Second, the piglet data run the other way for intravenous feeding: because TPN bypasses the gut, newborn piglets on TPN needed less threonine — about 45% of the oral requirement.
The Wang 2010 Piglet Studies
The most-cited demonstration of threonine's role in maintaining the gut barrier comes from a series of experiments in young piglets by Wang and colleagues at China Agricultural University and parallel groups elsewhere. Piglets are an unusually good model for human infant gastrointestinal physiology because of similarities in gut anatomy, mucin composition, and microbial colonization patterns.
Wang's 2010 study in the Journal of Nutrition fed four groups of weanling piglets (8 per group) diets containing 0.37%, 0.74%, 0.89% or 1.11% true ileal digestible threonine for 14 days, then examined the lining of the small intestine and its mucins. Key findings:
- Piglets on both the lowest (0.37%) and the highest (1.11%) threonine diets had distorted villi in the duodenum
- Compared with the 0.89% diet, both the 0.37% and the 1.11% diets lowered the total amount of mucins in the duodenum and the activity of the MUC2 gene (MUC2 mRNA) in the duodenum and jejunum
- Compared with the 0.74% diet, the 0.37% diet lowered acidic mucins in the ileum and the 1.11% diet lowered sulfated mucins in the duodenum
- Cell death (apoptosis) was higher on the 1.11% diet than on the 0.74% and 0.89% diets
- The authors concluded that both a deficiency and an excess of threonine harm the mucosal barrier, with the best level at 0.89% of the diet — a U-shaped result showing that more threonine is not better
An earlier 2007 study by the same research group (diets of 0.37%, 0.74% or 1.11% threonine for 14 days) found the same U shape for protein building: both too little and too much threonine reduced the rate of protein synthesis in the jejunal lining, in its mucins and in skeletal muscle. A 2011 review from the group explains why the gut is so sensitive: a large proportion of dietary threonine is used to build the gut lining's proteins, especially mucin; the lining cells do not burn threonine for fuel; and because mucin proteins cannot be digested and reused, every bit of mucus the gut secretes is a net loss of threonine from the body.
Parallel work by Faure and colleagues (2006) studied rats with chemically induced colitis (dextran sulfate sodium, DSS). The rats were fed a diet with extra threonine, serine, proline and cysteine from 8 days before to 28 days after the colitis was induced. The higher dose increased the number of Muc2-containing goblet cells in the ulcerated area, raised colonic mucin production, and increased the colonic mucin synthesis rate by 95%, while overall protein turnover was unchanged.
The piglet data are mechanistic and show a U-shaped dose response. Whether the principle applies to humans has not been tested directly; the groups most often suggested as at risk of inadequate threonine relative to gut demand are people with low protein intake, vegan diets that do not combine complementary proteins, and inflammatory bowel disease patients with increased mucin turnover.
The Two-Layer Colonic Mucus System
The Gunnar Hansson laboratory at the University of Gothenburg, working through the 2000s and 2010s, established the modern understanding of the colonic mucus as a two-layer system. Using live-tissue imaging of mouse colon explants and bacterial visualization with FISH (fluorescent in situ hybridization), the Hansson group showed that:
- The inner mucus layer — approximately 50 micrometers thick in the mouse, perhaps 200 micrometers in the human — is firmly adherent to the epithelium and is essentially bacteria-free. It is built from densely packed, sulfated, and sialylated MUC2 polymers that form a near-impermeable physical barrier.
- The outer mucus layer — about 100 micrometers in mouse, much thicker in human — is structurally identical to the inner layer (same MUC2 backbone, same glycan coat) but has been partially proteolytically cleaved by bacterial enzymes. This loosens the gel, allowing commensal bacteria to colonize it. The outer layer functions as a colonization niche that confines bacteria to a defined region while the inner layer protects the epithelium.
Hansson's critical insight is that the inner layer is renewed continuously by goblet cell secretion at the base, while bacterial proteolysis erodes the outer surface. The system is in dynamic balance — if mucin secretion drops or proteolysis accelerates, the inner layer thins. When it thins to the point that bacteria can reach the epithelium, the host responds with inflammation, which is the precipitating event of ulcerative colitis.
Threonine availability is proposed as a rate-limiting nutritional input for the renewal side of this balance. On this view, when threonine is inadequate, MUC2 secretion drops, the inner layer cannot keep pace with bacterial erosion, and the colon transitions from a tolerated commensal state to an inflamed state.
MUC2 Knockout Mice and Spontaneous Colitis
Genetic ablation of MUC2 in mice produces one of the cleanest models of inflammatory bowel disease in modern immunology. Velcich et al. (2002, Science) created Muc2−/− mice by targeted gene disruption. The phenotype was dramatic:
- The mice had abnormally shaped intestinal crypts and altered maturation and movement of the lining cells (Velcich 2002)
- Most notably, they frequently developed adenomas in the small intestine that progressed to invasive cancer (adenocarcinoma), as well as rectal tumors (Velcich 2002)
- A 2006 study by van der Sluis and colleagues found that Muc2-knockout mice show clinical signs of colitis from 5 weeks of age, worsening as they age, with a thickened lining, increased cell proliferation and superficial erosions; given the colitis-inducing chemical DSS, they fared worse than normal mice
- In Muc2-knockout mice, bacteria sit in direct contact with the colonic lining and far down in the crypts — no protective mucus layer exists (Johansson 2008)
These experiments establish that MUC2 is not merely beneficial but essential for colonic health in mice — loss of MUC2 is enough to produce colitis and intestinal and rectal tumors in otherwise genetically normal mice. It follows that anything which reduces MUC2 production (genetic, nutritional, pharmacological) would be expected to push the colon toward inflammation. Threonine shortage is proposed as one nutritional driver of low MUC2 production; how often it limits MUC2 in people has not been measured, and in healthy adult men the gut's first-pass use of threonine is similar to its use of lysine.
MUC2 expression is also lowered in human inflammatory bowel disease (as van der Sluis and colleagues note in the background to their mouse study), and rare germline mutations in MUC2 itself or in the enzymes responsible for mucin O-glycosylation are associated with familial inflammatory bowel disease phenotypes. The MUC2 mucus barrier is, in retrospect, one of the central nodes in inflammatory bowel disease pathogenesis.
Translation to Human Inflammatory Bowel Disease and Ulcerative Colitis
Several lines of evidence link impaired mucin biology in humans to inflammatory bowel disease, with implications for threonine nutrition as part of the broader treatment landscape.
Reduced mucus thickness in active ulcerative colitis. Pullan and colleagues (1994, Gut) measured the thickness of the adherent mucus gel on surgically removed colon specimens from 46 "control" patients (most of whom had colon cancer), 17 patients with ulcerative colitis (UC) and 15 with Crohn's disease. In the controls the layer averaged 107 micrometers in the right colon, 134 in the left colon and 155 in the rectum. In ulcerative colitis the values varied more widely, and areas with acute inflammation were stripped of the mucus layer altogether; in Crohn's disease the layer was normal or thicker than normal.
Reduced MUC2 expression and altered glycosylation. Biopsy studies in UC patients show reduced MUC2 protein expression, often with abnormal glycan structures (truncated O-glycans, reduced sulfation). These changes correlate with disease activity and inversely with the depth of clinical remission.
Plasma threonine in active inflammatory bowel disease. Several studies have documented reduced plasma threonine concentrations in patients with active Crohn's disease and ulcerative colitis. The mechanism is multifactorial — reduced intake due to anorexia, increased splanchnic extraction to compensate for accelerated mucin turnover, malabsorption, and increased catabolic losses in inflammation. The net result is that inflammatory bowel disease patients are at meaningfully increased risk for threonine inadequacy relative to their elevated demand.
Threonine supplementation in animal models of colitis. Multiple groups have shown that dietary threonine supplementation reduces severity of chemically induced colitis (dextran sulfate sodium, DSS; trinitrobenzene sulfonic acid, TNBS) in rats and mice, partly by restoring mucin synthesis and partly through reduction of pro-inflammatory cytokine expression. Whether this translates to human inflammatory bowel disease remains under investigation — there are no large randomized trials of isolated threonine supplementation in UC or Crohn's. Practical nutritional management in inflammatory bowel disease focuses on optimizing total protein intake from high-biological-value sources, which inherently provides adequate threonine.
For a broader treatment of inflammatory bowel disease pathogenesis and management, see our Inflammatory Bowel Disease page and the Crohn's Disease and Ulcerative Colitis deep-dives.
When Gut Bacteria Eat the Mucus Layer
A particularly elegant aspect of mucin biology that has emerged in the last fifteen years is that certain gut bacteria specialize in degrading the mucus layer as their primary carbon source. Akkermansia muciniphila, a Verrucomicrobia species first cultured by Derrien and colleagues in 2004, is the best-studied mucin-degrading bacterium and lives almost exclusively at the outer surface of the colonic mucus layer.
This sounds destructive, but it is actually a stable and beneficial relationship in the healthy gut. Akkermansia trims back the outer mucus layer at a rate that the goblet cells can match through new secretion, releasing oligosaccharides that other beneficial commensals (including butyrate-producing Firmicutes) consume. The result is a healthy steady-state turnover of the mucus layer. Akkermansia abundance correlates positively with metabolic health, reduced obesity, and reduced inflammation in dozens of cohort studies.
The problem arises when goblet cell secretion fails to match bacterial degradation. If MUC2 production drops — whether from threonine inadequacy, low-fiber diet that paradoxically increases mucin-degrading bacterial expansion, or genetic insufficiency — the inner mucus layer thins and bacteria gain access to the epithelium. Desai and colleagues (2016, Cell) showed in gnotobiotic mice fed a low-fiber diet that mucin-degrading bacteria preferentially shifted to consuming the host mucus layer, thinning it to the point of bacterial-epithelial contact and inflammation. Adding fiber back to the diet restored the mucus layer within days.
The take-home message is that the gut mucus barrier is the product of a three-way balance: dietary threonine (substrate for mucin synthesis), dietary fiber (alternative substrate that keeps mucin-degrading bacteria from eating too much of the host mucus), and adequate goblet cell health (mucin secretion capacity). Disruption of any one of these inputs — common in modern diets — predisposes to barrier failure and the chronic low-grade inflammation that follows.
Clinical Situations and Doses Used in Practice
For most healthy adults eating a varied diet with adequate protein, threonine intake comfortably exceeds the World Health Organization (WHO) recommendation of 15 mg/kg/day. The clinical situations where threonine supply may become limiting for mucin production are specific:
- Active inflammatory bowel disease with elevated mucin turnover — threonine demand is increased and intake is often reduced. Protein intakes of 1.2-1.5 g/kg/day from high-quality sources (eggs, fish, poultry, dairy if tolerated, plus plant proteins) are commonly described in this setting. Whey protein concentrate is particularly threonine-dense.
- Post-antibiotic gut recovery — the period after broad-spectrum antibiotics is described as a time when the mucin layer is thin. Approaches practitioners describe include adequate protein, fermented foods, and a short course of L-threonine (500-1,000 mg/day in divided doses for 4-8 weeks) when intake is uncertain.
- Parenteral nutrition — standard TPN amino acid solutions provide threonine, but the gut is bypassed and atrophies during prolonged TPN; in newborn piglets, intravenous feeding lowered the threonine requirement to about 45% of the oral one. Small amounts of enteral nutrition ("trophic feeds") are used to keep the gut working and are described as maintaining gut mucin production better than threonine dosing alone.
- Strict vegan diets without protein combining — threonine intake from grain-only diets can be marginal because grains are limiting in threonine. Combining grains with legumes, fermented soy foods (natto, tempeh, miso), quinoa or seeds raises threonine intake. Diets based only on rice are particularly low in threonine.
- Bariatric surgery patients — reduced food volume and altered absorption can drop threonine intake below requirements. Lifelong attention to protein intake (60-80 g/day minimum from high-biological-value sources) is standard.
Standalone L-threonine supplementation is rarely used when total protein intake is adequate. Where it is used, doses described in practice are 100-500 mg three times daily between meals. Some clinicians use higher doses (1-2 g/day) for short-term gut healing protocols, divided into 3-4 doses. Doses above 2 g/day are rarely used and risk amino acid imbalance — isolated dosing of any single essential amino acid can interfere with absorption of others at the gut wall.
Cautions
- Threonine alone is not a treatment for inflammatory bowel disease. Inflammatory bowel disease is multifactorial. Threonine optimization is supportive nutritional care, not a substitute for medical management with mesalamine, biologics, immunomodulators, or surgical care as appropriate.
- Renal impairment — isolated amino acid supplementation increases nitrogen load. In advanced chronic kidney disease the kidneys have less capacity to clear this extra nitrogen, and high-dose single amino acid supplements add to the load.
- Phenylketonuria and other inborn errors of amino acid metabolism — threonine catabolism feeds into the threonine-aldolase or threonine-dehydratase pathways, neither of which is affected by classical PKU. Threonine is generally safe in PKU patients; in other inborn errors, the effect of any single amino acid supplement depends on which pathway is affected.
- Pregnancy — there is no established role for isolated threonine supplementation in pregnancy, where protein needs are normally met from whole foods.
- The mucus barrier needs more than threonine. Mucin O-glycosylation requires UDP-GalNAc, UDP-Gal, UDP-GlcNAc, GDP-fucose, and CMP-sialic acid, all of which depend on adequate carbohydrate and intermediate metabolism. Severe carbohydrate restriction (long-term strict ketogenic diets, prolonged fasting) reduces the substrates available for glycan synthesis even when threonine is plentiful.
Key Research Papers
- Wang W, Zeng X, Mao X, Wu G, Qiao S (2010). Optimal dietary true ileal digestible threonine for supporting the mucosal barrier in small intestine of weanling pigs. Journal of Nutrition. — PubMed PMID: 20335627
- Wang X, Qiao S, Yin Y, Yue L, Wang Z, Wu G (2007). A deficiency or excess of dietary threonine reduces protein synthesis in jejunum and skeletal muscle of young pigs. Journal of Nutrition. — PubMed PMID: 17513404
- Mao X, Zeng X, Qiao S, Wu G, Li D (2011). Specific roles of threonine in intestinal mucosal integrity and barrier function. Frontiers in Bioscience (Elite Edition). — PubMed PMID: 21622125
- Velcich A, Yang W, Heyer J, et al. (2002). Colorectal cancer in mice genetically deficient in the mucin Muc2. Science. — PubMed PMID: 11872843
- van der Sluis M et al. (2006). Muc2-deficient mice spontaneously develop colitis, indicating that MUC2 is critical for colonic protection. Gastroenterology. — PubMed PMID: 16831596
- Johansson ME, Phillipson M, Petersson J, Velcich A, Holm L, Hansson GC (2008). The inner of the two Muc2 mucin-dependent mucus layers in colon is devoid of bacteria. PNAS. — PubMed PMID: 18806221
- Hansson GC (2012). Role of mucus layers in gut infection and inflammation. Current Opinion in Microbiology. — PubMed PMID: 22177113
- Pullan RD et al. (1994). Thickness of adherent mucus gel on colonic mucosa in humans and its relevance to colitis. Gut. — PubMed PMID: 8150346
- Bertolo RF et al. (1998). Threonine requirement of neonatal piglets receiving total parenteral nutrition is considerably lower than that of piglets receiving an identical diet intragastrically. Journal of Nutrition. — PubMed PMID: 9772146
- Faure M et al. (2006). Specific amino acids increase mucin synthesis and microbiota in dextran sulfate sodium-treated rats. Journal of Nutrition. — PubMed PMID: 16702321
- Derrien M et al. (2004). Akkermansia muciniphila gen. nov., sp. nov., a human intestinal mucin-degrading bacterium. International Journal of Systematic and Evolutionary Microbiology. — PubMed PMID: 15388697
- Desai MS et al. (2016). A dietary fiber-deprived gut microbiota degrades the colonic mucus barrier and enhances pathogen susceptibility. Cell. — PubMed PMID: 27863247
- van Goudoever JB, Stoll B, Henry JF, Burrin DG, Reeds PJ (2000). Adaptive regulation of intestinal lysine metabolism. PNAS. (Methodologic basis for splanchnic-extraction studies that later targeted threonine.) — PubMed PMID: 11016965
- Wandall HH, Hassan H, Mirgorodskaya E, et al. (1997). Substrate specificities of three members of the human UDP-N-acetyl-alpha-D-galactosamine:Polypeptide N-acetylgalactosaminyltransferase family, GalNAc-T1, -T2, and -T3. Journal of Biological Chemistry. — PubMed PMID: 9295285
- Bansil R, Turner BS (2018). The biology of mucus: composition, synthesis and organization. Advanced Drug Delivery Reviews. — PubMed PMID: 28970050
- Chapman KP, Elango R, Ball RO, Pencharz PB (2013). Splanchnic first pass disappearance of threonine and lysine do not differ in healthy men in the fed state. Journal of Nutrition. — PubMed PMID: 23325919
- van der Schoor SR, Wattimena DL, Huijmans J, Vermes A, van Goudoever JB (2007). The gut takes nearly all: threonine kinetics in infants. American Journal of Clinical Nutrition. — PubMed PMID: 17921393
PubMed Topic Searches
Connections
- All Amino Acids
- Threonine Overview
- Threonine Benefits Hub
- Threonine for Collagen
- Threonine for Immune Function
- Threonine for Liver Health
- Glutamine (Enterocyte Fuel)
- Serine (Co-residue in PTS Repeats)
- Proline (Third PTS Residue)
- Glycine
- Inflammatory Bowel Disease
- Ulcerative Colitis
- Crohn's Disease
- Leaky Gut Syndrome
- Small Intestinal Bacterial Overgrowth
- Gut-Brain Axis
- Bone Broth
- Eggs
- History
- Sources