Lysine for Herpes Prevention
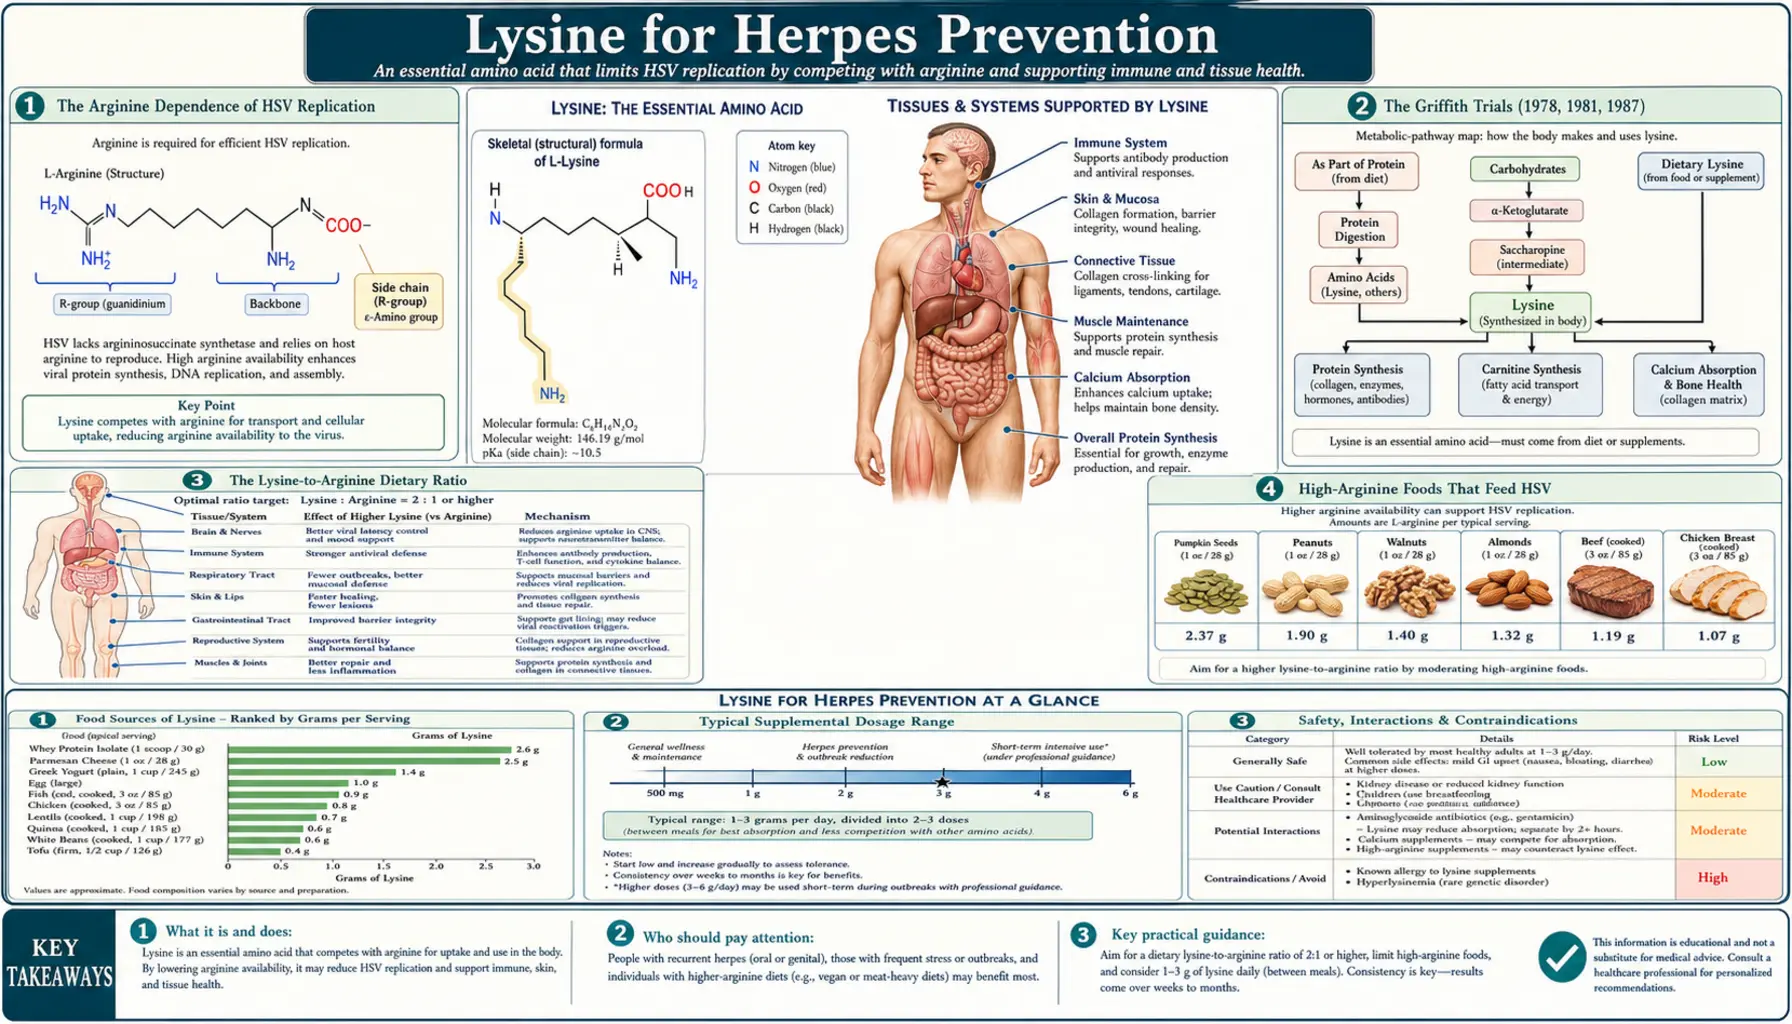
Lysine's best-known proposed clinical use is reducing recurrences of herpes simplex virus (HSV) infection — HSV-1 cold sores and HSV-2 genital herpes. The idea rests on cell-culture findings: in tissue culture HSV needs arginine to replicate, and lysine partly antagonises that effect. Christopher Kagan, Richard Griffith and colleagues reported on lysine and herpes between 1974 and 1987. The human trials are small and their results are mixed: some found fewer or milder recurrences on lysine, others found no benefit, and a 2015 Cochrane review of interventions for preventing cold sores found no evidence of efficacy for lysine. This deep-dive covers the cell-culture mechanism, the dietary-ratio idea, the trials and the doses they used, and how the evidence compares with the prescription antivirals acyclovir, valacyclovir and famciclovir.
Table of Contents
- The Arginine Dependence of HSV Replication
- The Griffith Studies (1978, 1981, 1987) and Other Trials
- The Lysine-to-Arginine Dietary Ratio
- Foods Described as High in Arginine
- Foods Described as High in Lysine
- Doses Used in the Trials
- The Topical Lysine Question
- Comparison to Acyclovir, Valacyclovir, and Famciclovir
- Other Agents Discussed for Herpes (Vitamin C, Zinc, Monolaurin, Lemon Balm)
- Cautions and Drug Interactions
- Evidence Quality Summary
- Key Research Papers
- Connections
- Featured Videos
The Arginine Dependence of HSV Replication
Herpes simplex virus type 1 (the usual cause of cold sores) and type 2 (the usual cause of genital herpes) are DNA viruses that persist in a latent state in sensory nerve ganglia — the trigeminal ganglia for oral herpes, the sacral ganglia for genital herpes — and periodically reactivate to produce lesions at or near the original site. A 2022 narrative review notes that the usual antiviral therapies act on the virus during entry, replication and reactivation but do not reach it in its latent state (Pedrazini 2022).
In 1964 Tankersley reported that in human cells in tissue culture, HSV produced neither cytopathic effects nor new virus when arginine was withheld, and that a prompt and extensive infection followed once arginine was replaced; lysine was not required by the virus and partially inhibited its multiplication. Griffith, DeLong and Nelson reported in 1981 that arginine deficiency suppressed HSV replication in tissue culture and that lysine, acting as an arginine analogue, antagonised arginine's growth-promoting effect. The 2022 review describes lysine as interfering with the formation of viral capsid proteins and DNA through competitive antagonism with arginine, and by increasing arginase, the enzyme that breaks arginine down.
These are cell-culture (in-vitro) findings. Whether oral lysine at supplement doses shifts arginine availability inside infected skin cells enough to matter is the question the human trials below set out to test.
The Griffith Studies (1978, 1981, 1987) and Other Trials
Clinical interest followed Kagan's 1974 letter to The Lancet on lysine therapy for herpes simplex. Griffith's 1981 paper was the tissue-culture study described above; the human studies, in date order:
- Griffith RS, Norins AL, Kagan C (1978), Dermatologica. 45 patients with frequently recurring herpes infection were given 312–1,200 mg of lysine daily in single or multiple doses. The authors reported that supplementary lysine accelerated recovery and suppressed recurrence. The abstract describes no placebo or control group.
- Milman N, Scheibel J, Jessen O (1980), Acta Dermato-Venereologica. A double-blind, placebo-controlled crossover study in 65 patients with recurrent cold sores: 1,000 mg of L-lysine monohydrochloride daily for 12 weeks, then placebo for a similar period. Overall, lysine had no effect on the recurrence rate, although significantly more patients were recurrence-free during lysine than during placebo (p = 0.05). Lysine had no effect on healing rate or on how the lesions looked at their worst.
- DiGiovanna JJ, Blank H (1984), Archives of Dermatology. A double-blind, placebo-controlled trial of 400 mg lysine hydrochloride three times a day in 21 patients with frequently recurring infection. The investigators found no substantial benefit, either as treatment for episodes in progress or as prevention of recurrences.
- McCune MA, Perry HO, Muller SA, O'Fallon WM (1984), Cutis. A randomized, double-blind, placebo-controlled crossover study in 41 patients. 1,248 mg a day of L-lysine monohydrochloride showed evidence of decreasing the recurrence rate; 624 mg a day was not effective. Neither dose shortened healing time compared with placebo.
- Thein DJ, Hurt WC (1984), Oral Surgery, Oral Medicine, Oral Pathology. 26 volunteers with frequently recurring cold sores completed a 12-month double-blind crossover study of 1,000 mg L-lysine daily. In most instances the lysine group reported significantly fewer lesions, and recurrence rose when lysine was withdrawn. Recurrence fell significantly when serum lysine exceeded 165 nmol/mL and rose when it fell below that level.
- Griffith RS, Walsh DE, Myrmel KH, Thompson RW, Behforooz A (1987), Dermatologica. A double-blind, placebo-controlled, multicenter trial of 1,000 mg L-lysine (as the monohydrochloride) three times a day for six months. 27 participants on lysine and 25 on placebo completed the trial. The lysine group had an average of 2.4 fewer HSV infections (p < 0.05), with significantly milder symptoms and shorter healing time.
Reviews reach cautious conclusions. Mailoo and Rampes (2017, Integrative Medicine: A Clinician's Journal) — a literature review, not a meta-analysis — concluded that lysine appears ineffective for prophylaxis or treatment at doses below 1 g/day without a low-arginine diet, that doses above 3 g/day appear to improve patients' subjective experience of the disease, and that longer controlled studies of doses above 1.2 g/day are needed to test its role definitively. The 2015 Cochrane review of interventions for preventing cold sores (32 randomized trials, 2,640 participants, 19 treatments) found no evidence of efficacy for lysine in preventing herpes labialis.
The Lysine-to-Arginine Dietary Ratio
Because the cell-culture effect is competitive, proponents of lysine therapy frame the relevant dietary variable as the ratio of lysine to arginine rather than lysine intake alone. Griffith and colleagues' 1978 paper summarised tissue-culture work in which an arginine-to-lysine ratio favouring arginine enhanced viral replication and a ratio favouring lysine suppressed it. Their 1981 paper proposed that these in-vitro data could support limiting excess dietary arginine, and possibly adding lysine, in people prone to herpes lesions.
No trial was found that tested a dietary lysine-to-arginine ratio against herpes recurrence. The Mailoo and Rampes review notes that the low-dose trials which found no benefit did not combine lysine with a low-arginine diet. Specific ratio targets (such as 2:1 or 3:1) and per-food ratios circulate in popular sources; none was found in a controlled study, so none is given here.
Foods Described as High in Arginine
Popular low-arginine diet lists for herpes most often name the foods below as high in arginine relative to lysine. These lists draw on food-composition data and practitioner advice; no trial was found showing that eating less of these foods prevents outbreaks.
- Chocolate and cocoa — the food most often named in these lists.
- Nuts and peanuts — almonds, walnuts, cashews, hazelnuts, pecans, Brazil nuts, pistachios, pine nuts, and peanuts (botanically a legume).
- Seeds — sesame, sunflower, pumpkin, flax, chia, hemp.
- Coconut — coconut meat and coconut milk.
- Grains — wheat, oats, rice, barley, corn, buckwheat.
- Carob — often used in place of chocolate.
These lists are usually framed around outbreaks rather than year-round restriction; no study was found that measured the effect of either approach.
Foods Described as High in Lysine
The same popular sources list foods in which lysine is abundant relative to arginine, mostly animal proteins:
- Fish and shellfish — cod, salmon, sardines, tuna, mackerel, shrimp, scallops.
- Poultry — chicken, turkey.
- Red meat — beef, lamb, bison, pork.
- Eggs.
- Dairy products — milk, yogurt, cheese.
- Legumes — lentils, beans, tempeh; lysine-rich among plant foods but also carrying substantial arginine.
- Brewer's yeast and nutritional yeast.
As with the high-arginine list, no trial was found that tested eating more of these foods against herpes recurrence. Lysine content of individual foods is covered on the Lysine Sources page (see Connections).
Doses Used in the Trials
The trials described above gave L-lysine by mouth, mostly as L-lysine monohydrochloride, at these doses:
- 312–1,200 mg/day — Griffith 1978 (no control group; benefit reported).
- 400 mg three times a day — DiGiovanna & Blank 1984 (no substantial benefit).
- 624 mg/day and 1,248 mg/day — McCune 1984 (the lower dose was not effective; the higher dose showed evidence of fewer recurrences).
- 1,000 mg/day — Milman 1980 (no overall effect on recurrence rate) and Thein & Hurt 1984 (fewer lesions, linked to serum lysine above 165 nmol/mL).
- 1,000 mg three times a day for six months — Griffith 1987 (2.4 fewer infections on average than placebo).
The Mailoo and Rampes review describes doses below 1 g/day as appearing ineffective without a low-arginine diet and doses above 3 g/day as appearing to improve patients' subjective experience. No trial was found that compared a higher "outbreak" dose with a lower maintenance dose, or that tested taking lysine with or without meals.
The Topical Lysine Question
Topical products containing lysine are sold for cold sores, but no controlled trial of lysine alone applied to the skin was found.
Singh and colleagues (2005, Alternative Medicine Review) ran a small open-label pilot study in 30 participants using an ointment that combined L-lysine with zinc and herbal ingredients; there was no placebo comparison. The authors reported full resolution in 40 percent of participants by the third day and in 87 percent by the end of the sixth day, and no adverse effects. Because the product was a combination and the study was uncontrolled, the contribution of lysine itself cannot be separated out.
The oral trials described above remain the main human evidence on lysine for herpes.
Comparison to Acyclovir, Valacyclovir, and Famciclovir
Three oral nucleoside-analogue antivirals are used for herpes simplex: acyclovir, valacyclovir (a prodrug of acyclovir) and famciclovir (a prodrug of penciclovir). The US prescribing information for valacyclovir lists treatment of cold sores, treatment of initial and recurrent genital herpes, suppression of genital herpes, and reduction of transmission among its adult indications.
- Genital herpes — the CDC's sexually transmitted infections treatment guideline states that suppressive therapy reduces the frequency of genital herpes recurrences by 70–80% among patients who have frequent recurrences. The suppressive regimens it lists are acyclovir 400 mg twice a day, valacyclovir 500 mg or 1 g once a day, and famciclovir 250 mg twice a day. The guideline does not mention lysine.
- Cold sores — the 2015 Cochrane review concluded that long-term use of oral antivirals can prevent herpes labialis but that the clinical benefit is small; in one trial long-term oral acyclovir reduced clinical recurrences from 1.80 to 0.85 episodes per participant over four months. The same review found no evidence of efficacy for lysine.
- Side effects — the valacyclovir prescribing information lists headache, nausea and abdominal pain as the most common adverse reactions. Its warnings include acute kidney failure and central nervous system effects (agitation, hallucinations, confusion), particularly in older adults and in people with kidney disease given doses too high for their kidney function, and thrombotic thrombocytopenic purpura/hemolytic uremic syndrome in specific immunocompromised groups given 8 g/day in trials.
- Combination — no study of lysine taken together with acyclovir, valacyclovir or famciclovir was found. The valacyclovir label states that no clinically significant drug–drug or drug–food interactions with valacyclovir are known.
No head-to-head trial comparing lysine with an antiviral drug was found.
Other Agents Discussed for Herpes (Vitamin C, Zinc, Monolaurin, Lemon Balm)
Several other agents are often discussed alongside lysine for herpes. The evidence for each is of a different kind:
- Vitamin C — no controlled trial of oral vitamin C for preventing herpes recurrences was found for this page. Its roles in immune function and collagen formation are covered on the Vitamin C page.
- Zinc — in a laboratory study, 50 mM zinc gluconate for 2 hours inactivated more than 98% of the virus in seven of ten clinical HSV isolates, and the effect was concentration-dependent (Arens & Travis 2000). This is a test-tube finding, not a human trial. More on the Zinc page.
- Monolaurin (glycerol monolaurate) — monolaurin is the monoglyceride of lauric acid, a medium-chain fatty acid. In a 1987 laboratory study, medium-chain fatty acids and their monoglycerides inactivated enveloped viruses including HSV by disrupting the viral envelope; at higher concentrations they also destroyed the membranes of the cultured cells (Thormar 1987). No human trial of monolaurin for herpes was found.
- Lemon balm (Melissa officinalis) — in a double-blind, placebo-controlled trial in 66 patients with recurrent cold sores, a cream containing 1% dried lemon balm leaf extract, applied four times daily for five days, produced a lower combined symptom score on day 2 than placebo (Koytchev 1999). A 2025 systematic review reported that lemon balm preparations consistently reduced pain and swelling, with some studies also reporting smaller lesions (Anheyer 2025). More on the Lemon Balm page.
- Olive leaf extract — the same review included a trial of a topical olive leaf extract that showed faster symptom improvement and shorter healing time than acyclovir.
- Propolis (topical) — in the trials in that review, propolis formulations shortened the median time to crusting and complete healing compared with acyclovir.
The review authors describe the herbal trials as small and heterogeneous (Anheyer 2025). No trial was found that tested lysine combined with any of these agents.
Cautions and Drug Interactions
- Pregnancy and lactation — no safety data on supplemental lysine doses in pregnancy or breastfeeding were found.
- Kidney — a 1996 case report describes a 44-year-old woman who developed Fanconi's syndrome and severe tubulointerstitial nephritis, progressing to chronic kidney failure, in association with oral L-lysine taken as a supplement (Lo 1996).
- Cardiovascular and gallbladder disease — the Mailoo and Rampes review states that people with cardiovascular or gallbladder disease face theoretical risks from lysine supplementation and that they warrant caution.
- Lysinuric protein intolerance — a rare genetic disorder of cationic amino acid transport. People with this diagnosis have their lysine, arginine and ornithine intake managed under specialist care.
- Drug interactions — no study of lysine taken with the HSV antivirals was found (see the comparison section above). Flodin's 1997 review surveys lysine's pharmacology and toxicity data, including the safety of chronic dosage levels.
- Calcium — in a 1992 human study, 400 mg of L-lysine taken with an oral calcium load blunted urinary calcium loss in healthy women, and 800 mg/day of L-lysine increased intestinal calcium absorption in osteoporotic patients (Civitelli 1992). More on the Calcium Absorption page.
- What lysine does not do — the trials measured recurrences, severity and healing time; none tested or claimed a cure. HSV stays latent in sensory ganglia, and the 2022 review notes that even the antiviral drugs do not act on latent virus.
Decisions about medicines and supplements belong with a clinician.
Evidence Quality Summary
Where the evidence stands as of 2026:
- Mechanism — cell-culture studies (Tankersley 1964; Griffith 1981) show that HSV replication depends on arginine and that lysine partly inhibits it. These are in-vitro findings.
- Clinical effect in humans — small trials published between 1978 and 1987 give mixed results. Griffith 1987, Thein & Hurt 1984 and the higher dose in McCune 1984 reported fewer or milder recurrences; DiGiovanna & Blank 1984 found no substantial benefit, and Milman 1980 found no overall effect on recurrence rate. The 2015 Cochrane review found no evidence of efficacy for lysine in preventing cold sores, and the 2017 Mailoo and Rampes review called for longer controlled studies at higher doses.
- Compared with antivirals — the CDC guideline reports a 70–80% reduction in genital herpes recurrences on suppressive antiviral therapy in people with frequent recurrences; the Cochrane review describes a small benefit of long-term oral antivirals for cold sores. No head-to-head trial with lysine was found.
- Safety — the trial abstracts summarised here do not report safety outcomes (the topical Singh pilot reported no adverse effects); a 1996 case report links L-lysine supplementation to kidney injury, and the Mailoo and Rampes review lists theoretical risks in cardiovascular and gallbladder disease.
Key Research Papers
- Griffith RS, Norins AL, Kagan C (1978). A multicentered study of lysine therapy in Herpes simplex infection. Dermatologica 156(5):257-67. — PubMed PMID: 640102
- Griffith RS, Walsh DE, Myrmel KH, Thompson RW, Behforooz A (1987). Success of L-lysine therapy in frequently recurrent herpes simplex infection. Treatment and prophylaxis. Dermatologica 175(4):183-90. — PubMed PMID: 3115841
- Thein DJ, Hurt WC (1984). Lysine as a prophylactic agent in the treatment of recurrent herpes simplex labialis. Oral Surgery, Oral Medicine, Oral Pathology 58(6):659-66. — PubMed PMID: 6438572
- Tankersley RW Jr (1964). Amino acid requirements of herpes simplex virus in human cells. Journal of Bacteriology 87(3):609-13. — PubMed PMID: 14127578
- Kagan C (1974). Letter: Lysine therapy for herpes simplex. The Lancet 1(7848):137. — PubMed PMID: 4130340
- DiGiovanna JJ, Blank H (1984). Failure of lysine in frequently recurrent herpes simplex infection. Treatment and prophylaxis. Archives of Dermatology 120(1):48-51. — PubMed PMID: 6419679
- Milman N, Scheibel J, Jessen O (1980). Lysine prophylaxis in recurrent herpes simplex labialis: a double-blind, controlled crossover study. Acta Dermato-Venereologica 60(1):85-7. — PubMed PMID: 6153847
- McCune MA, Perry HO, Muller SA, O'Fallon WM (1984). Treatment of recurrent herpes simplex infections with L-lysine monohydrochloride. Cutis 34(4):366-73. — PubMed PMID: 6435961
- Mailoo VJ, Rampes S (2017). Lysine for Herpes Simplex Prophylaxis: A Review of the Evidence. Integrative Medicine (Encinitas) 16(3):42-46. — PubMed PMID: 30881246
- Singh BB, Udani J, Vinjamury SP, Der-Martirosian C, Gandhi S, Khorsan R et al. (2005). Safety and effectiveness of an L-lysine, zinc, and herbal-based product on the treatment of facial and circumoral herpes. Alternative Medicine Review 10(2):123-7. — PubMed PMID: 15989381
- Flodin NW (1997). The metabolic roles, pharmacology, and toxicology of lysine. Journal of the American College of Nutrition 16(1):7-21. — PubMed PMID: 9013429
- Pedrazini MC, da Silva MH, Groppo FC (2022). L-lysine: Its antagonism with L-arginine in controlling viral infection. Narrative literature review. British Journal of Clinical Pharmacology 88(11):4708-4723. — PubMed PMID: 35723628 (Editorial note: this entry previously gave the year as 2018 and the journal as the Brazilian Journal of Implantology and Health Sciences; corrected 2026-10-13 against PubMed.)
- Chen F, Tholouli E (2004). Lysine and herpes simplex. British Journal of Dermatology. (Editorial note, 2026-10-13: no record of this paper was found in PubMed or Crossref; it is kept here for transparency, and no statement on this page rests on it. Its former search link is listed under PubMed Topic Searches.)
- Civitelli R, Villareal DT, Agnusdei D, Nardi P, Avioli LV, Gennari C (1992). Dietary L-lysine and calcium metabolism in humans. Nutrition 8(6):400-5. — PubMed PMID: 1486246
- Griffith RS, DeLong DC, Nelson JD (1981). Relation of arginine-lysine antagonism to herpes simplex growth in tissue culture. Chemotherapy 27(3):209-13. — PubMed PMID: 6262023
- Chi CC, Wang SH, Delamere FM, Wojnarowska F, Peters MC, Kanjirath PP (2015). Interventions for prevention of herpes simplex labialis (cold sores on the lips). Cochrane Database of Systematic Reviews (8):CD010095. — PubMed PMID: 26252373
- Lo JC, Chertow GM, Rennke H, Seifter JL (1996). Fanconi's syndrome and tubulointerstitial nephritis in association with L-lysine ingestion. American Journal of Kidney Diseases 28(4):614-7. — PubMed PMID: 8840955
- Koytchev R, Alken RG, Dundarov S (1999). Balm mint extract (Lo-701) for topical treatment of recurring herpes labialis. Phytomedicine 6(4):225-30. — PubMed PMID: 10589440
- Anheyer M, Cramer H, Ostermann T, Längler A, Anheyer D (2025). Herbal Medicine for Treating Herpes Labialis: A Systematic Review. Journal of Integrative and Complementary Medicine 31(11):946-954. — PubMed PMID: 40526027
- Arens M, Travis S (2000). Zinc salts inactivate clinical isolates of herpes simplex virus in vitro. Journal of Clinical Microbiology 38(5):1758-62. — PubMed PMID: 10790094
- Thormar H, Isaacs CE, Brown HR, Barshatzky MR, Pessolano T (1987). Inactivation of enveloped viruses and killing of cells by fatty acids and monoglycerides. Antimicrobial Agents and Chemotherapy 31(1):27-31. — PubMed PMID: 3032090
- Centers for Disease Control and Prevention. Sexually Transmitted Infections Treatment Guidelines, 2021: Genital Herpes. — cdc.gov
- Valacyclovir tablets, US prescribing information (generic label, DailyMed). — DailyMed