⚠ Evidence warning: Clinical trials or other evidence do not support the claims that raising nicotinamide adenine dinucleotide with supplements slows aging, relieves fatigue, speeds recovery or helps older adults more. This page keeps it as a report of what people, websites or other media say.
Vitamin B3 as a Nicotinamide Adenine Dinucleotide (NAD+) Precursor — Why All Roads Lead to Nicotinamide Adenine Dinucleotide (NAD+)
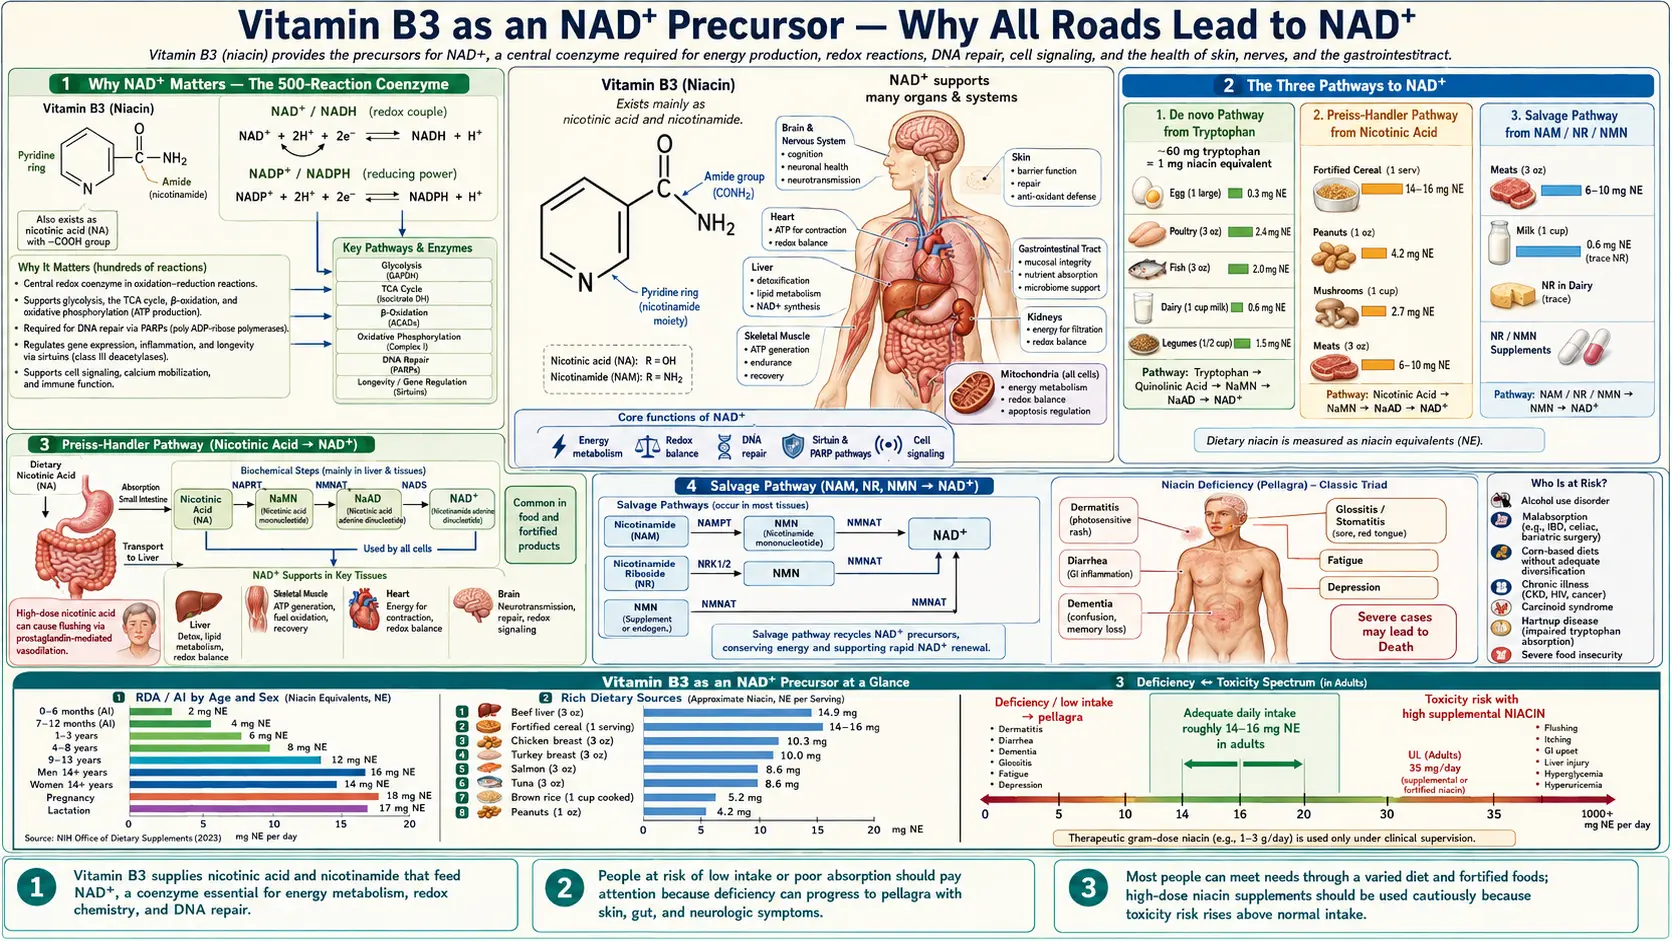
Niacin (nicotinic acid), nicotinamide (NAM), nicotinamide riboside (NR), nicotinamide mononucleotide (NMN), and even the amino acid tryptophan all converge on the same destination — nicotinamide adenine dinucleotide (NAD+). Three biosynthetic routes carry them there: the Preiss-Handler pathway (nicotinic acid), the salvage pathway (NAM, NR, nicotinamide mononucleotide via NAMPT and NRK enzymes), and the de novo kynurenine pathway from tryptophan. Because all four B3 family members reach nicotinamide adenine dinucleotide within a few enzymatic steps, the cost-effective nicotinamide adenine dinucleotide supplementation question becomes a pharmacology question, not a metaphysical one: which precursor reaches which tissue at which dose, and at what cost.
Table of Contents
- Why Nicotinamide Adenine Dinucleotide Matters — The 500-Reaction Coenzyme
- The Three Pathways to Nicotinamide Adenine Dinucleotide
- Preiss-Handler Pathway (Nicotinic Acid → Nicotinamide Adenine Dinucleotide)
- Salvage Pathway (NAM, NR, Nicotinamide Mononucleotide → Nicotinamide Adenine Dinucleotide)
- De Novo Pathway (Tryptophan → Nicotinamide Adenine Dinucleotide)
- Nicotinamide Riboside/Nicotinamide Mononucleotide vs Plain Niacin/NAM — The Cost-Effectiveness Question
- Flush vs Flush-Free — The Practical Choice
- Nicotinamide Adenine Dinucleotide Decline With Aging
- Doses Described in Protocols and Trials
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Why Nicotinamide Adenine Dinucleotide Matters — The 500-Reaction Coenzyme
Nicotinamide adenine dinucleotide is the most-used coenzyme in human biology. It participates in more than 500 distinct enzymatic reactions, dwarfing every other vitamin-derived cofactor. Three broad categories of nicotinamide adenine dinucleotide-dependent reactions explain its centrality:
- Redox reactions (electron carrier). Nicotinamide adenine dinucleotide accepts a pair of electrons (becoming reduced nicotinamide adenine dinucleotide, NADH) during glycolysis at glyceraldehyde-3-phosphate dehydrogenase, during the pyruvate dehydrogenase complex, during three of the eight Krebs cycle reactions (isocitrate dehydrogenase, α-ketoglutarate dehydrogenase, malate dehydrogenase), and during every round of fatty-acid beta-oxidation. Reduced nicotinamide adenine dinucleotide then donates those electrons to Complex I of the mitochondrial electron transport chain, driving roughly 2.5 adenosine triphosphate (ATP) per molecule. Without nicotinamide adenine dinucleotide, oxidative metabolism halts within seconds.
- Substrate for nicotinamide adenine dinucleotide-consuming enzymes. The seven sirtuins (SIRT1-SIRT7), the 17 PARPs (poly-ADP-ribose polymerases), and CD38 all use nicotinamide adenine dinucleotide as a substrate rather than a recyclable cofactor — they cleave nicotinamide adenine dinucleotide into nicotinamide plus an ADP-ribose moiety used for protein modification. Sirtuin deacetylation, PARP-mediated DNA repair, and CD38-mediated cyclic-ADP-ribose signaling all literally consume nicotinamide adenine dinucleotide. The cell must continuously resynthesize nicotinamide adenine dinucleotide from precursors to keep up.
- Reduced nicotinamide adenine dinucleotide phosphate (NADPH) (anabolic reductant). Nicotinamide adenine dinucleotide kinase phosphorylates nicotinamide adenine dinucleotide to NADP+, the precursor of reduced nicotinamide adenine dinucleotide phosphate. Reduced nicotinamide adenine dinucleotide phosphate drives reductive biosynthesis (fatty acids, cholesterol, steroid hormones), regenerates oxidized glutathione (GSSG → reduced glutathione, GSH) via glutathione reductase, powers cytochrome P450 Phase I detoxification, and supplies electrons to the NADPH oxidase enzyme in phagocytes for the oxidative burst. Without reduced nicotinamide adenine dinucleotide phosphate, the entire antioxidant defense system collapses.
This breadth means that nicotinamide adenine dinucleotide supply is rate-limiting for energy metabolism, longevity signaling, DNA repair, and antioxidant defense simultaneously. Even modest reductions in nicotinamide adenine dinucleotide availability create metabolic bottlenecks felt as fatigue, slowed recovery, accelerated aging signatures, and impaired detoxification.
What is not known: that last statement is not tied to a study on this page. A 2021 review across species (Peluso and colleagues) found the evidence for an overall fall in nicotinamide adenine dinucleotide with aging "very limited" and often restricted to a single tissue or cell type, particularly in humans, where levels during aging are still poorly characterized.
The Three Pathways to Nicotinamide Adenine Dinucleotide
Mammals build nicotinamide adenine dinucleotide from three different starting molecules through three distinct enzymatic routes. Knowing them explains how the supplements differ.
| Pathway | Starting Molecule | Key Enzymes | Steps to nicotinamide adenine dinucleotide |
|---|---|---|---|
| Preiss-Handler | Nicotinic acid (NA) | NAPRT → NMNAT → NADS | 3 enzymatic steps |
| Salvage (NAM) | Nicotinamide (NAM) | NAMPT → NMNAT | 2 enzymatic steps |
| Salvage (nicotinamide riboside) | Nicotinamide riboside (NR) | NRK1/NRK2 → NMNAT | 2 enzymatic steps |
| Salvage (nicotinamide mononucleotide) | Nicotinamide mononucleotide (NMN) | NMNAT (or de-phosphorylated to nicotinamide riboside first) | 1 enzymatic step |
| De Novo (kynurenine) | Tryptophan | TDO/IDO → 5+ enzymes → QPRT | 8 enzymatic steps |
Every precursor reaches the same destination — nicotinamide adenine dinucleotide — but the kinetics, tissue distribution, and side-effect profile differ. The salvage pathway dominates day-to-day nicotinamide adenine dinucleotide maintenance because sirtuins, PARPs, and CD38 continuously release NAM as they consume nicotinamide adenine dinucleotide, and the cell salvages that NAM back to nicotinamide mononucleotide and then nicotinamide adenine dinucleotide via NAMPT (the rate-limiting enzyme of the salvage pathway).
Preiss-Handler Pathway (Nicotinic Acid → Nicotinamide Adenine Dinucleotide)
Described by Jack Preiss and Philip Handler in their 1958 Journal of Biological Chemistry papers, this is the route that nicotinic acid (the "niacin" of pellagra rescue and lipid-lowering therapy) takes to nicotinamide adenine dinucleotide:
- Step 1: Nicotinic acid + PRPP (5-phosphoribosyl-1-pyrophosphate) → nicotinic acid mononucleotide (NaMN). Catalyzed by NAPRT (nicotinate phosphoribosyltransferase).
- Step 2: NaMN + adenosine triphosphate → nicotinic acid adenine dinucleotide (NaAD). Catalyzed by NMNAT (nicotinamide mononucleotide adenylyltransferase, three isoforms NMNAT1/2/3 with different subcellular localizations).
- Step 3: NaAD + glutamine + adenosine triphosphate → nicotinamide adenine dinucleotide + glutamate. Catalyzed by NADS (nicotinamide adenine dinucleotide (NAD) synthase). This is the amidation step that converts the carboxylic acid (nicotinic) to the amide (nicotinamide) form.
The Preiss-Handler pathway is highly active in the liver and adipose tissue, which is why orally administered nicotinic acid produces such powerful systemic effects on lipid metabolism, despite the gut and liver removing most of the nicotinic acid on first pass.
Salvage Pathway (NAM, NR, Nicotinamide Mononucleotide → Nicotinamide Adenine Dinucleotide)
The salvage pathway is the workhorse of cellular nicotinamide adenine dinucleotide maintenance. It exists primarily to recycle the nicotinamide (NAM) released by sirtuins, PARPs, and CD38 back into fresh nicotinamide adenine dinucleotide — but the same enzymes accept dietary NAM, NR, and nicotinamide mononucleotide.
NAM route
- Step 1: NAM + PRPP → nicotinamide mononucleotide. Catalyzed by NAMPT (nicotinamide phosphoribosyltransferase) — the rate-limiting enzyme of the salvage pathway.
- Step 2: nicotinamide mononucleotide + adenosine triphosphate → nicotinamide adenine dinucleotide. Catalyzed by NMNAT.
Nicotinamide Riboside route (described by Charles Brenner, 2004)
- Step 1: nicotinamide riboside + adenosine triphosphate → nicotinamide mononucleotide. Catalyzed by NRK1 or NRK2 (nicotinamide riboside kinases). NRK1 is ubiquitous; NRK2 is enriched in skeletal muscle, heart, and brain.
- Step 2: nicotinamide mononucleotide + adenosine triphosphate → nicotinamide adenine dinucleotide. Catalyzed by NMNAT, the same enzyme as the NAM route.
Nicotinamide Mononucleotide route
- Direct: nicotinamide mononucleotide + adenosine triphosphate → nicotinamide adenine dinucleotide. Catalyzed by NMNAT — one step from nicotinamide adenine dinucleotide.
- Caveat: Orally administered nicotinamide mononucleotide is rapidly de-phosphorylated by intestinal CD73 to nicotinamide riboside, then taken up across the enterocyte membrane, then re-phosphorylated to nicotinamide mononucleotide intracellularly. So although nicotinamide mononucleotide is "closer" to nicotinamide adenine dinucleotide on paper, it enters cells largely through the nicotinamide riboside route. This is why some pharmacologists argue nicotinamide riboside and nicotinamide mononucleotide are functionally equivalent for oral supplementation.
NAMPT, the rate-limiting NAM-salvage enzyme, is itself regulated by circadian clock genes and declines with age — one mechanism behind age-related nicotinamide adenine dinucleotide depletion. Nicotinamide riboside and nicotinamide mononucleotide bypass NAMPT, which is part of why they may raise nicotinamide adenine dinucleotide more effectively than equivalent NAM doses in older tissues.
De Novo Pathway (Tryptophan → Nicotinamide Adenine Dinucleotide)
The de novo or "kynurenine" pathway builds nicotinamide adenine dinucleotide from scratch starting with the essential amino acid tryptophan:
- Tryptophan → N-formylkynurenine (by TDO in liver, IDO in inflammation/extrahepatic tissue)
- N-formylkynurenine → kynurenine
- Kynurenine → 3-hydroxykynurenine (requires vitamin B2/FAD as cofactor for kynurenine 3-monooxygenase)
- 3-hydroxykynurenine → 3-hydroxyanthranilic acid (requires vitamin B6/PLP for kynureninase)
- 3-hydroxyanthranilic acid → 2-amino-3-carboxymuconate-semialdehyde → quinolinic acid
- Quinolinic acid + PRPP → NaMN. Catalyzed by QPRT (quinolinate phosphoribosyltransferase).
- NaMN then enters the Preiss-Handler pathway and proceeds through NMNAT and NADS to nicotinamide adenine dinucleotide.
The conversion ratio is approximately 60 mg of tryptophan per 1 mg of niacin equivalent (NE). So a steak with 1.5 g of dietary tryptophan provides about 25 mg NE on top of its preformed niacin content. This is why diets adequate in animal protein rarely cause pellagra even if preformed niacin is low.
The vitamin-cofactor catch: the de novo pathway requires B2, B6, and iron as cofactors. Deficiency of any of these can functionally impair tryptophan-to-NAD+ conversion and cause secondary niacin insufficiency even with adequate dietary tryptophan. This is why isoniazid (which depletes B6) causes pellagra-like symptoms, and why patients with hyperemesis or refeeding-syndrome contexts need broad B-vitamin replacement, not just B1.
The quinolinic acid hazard: quinolinic acid is also a potent N-methyl-D-aspartate-receptor agonist and excitotoxin. In chronic inflammation (IDO induction), the kynurenine pathway diverts away from nicotinamide adenine dinucleotide production and toward neurotoxic quinolinic acid accumulation — implicated in depression, human immunodeficiency virus-associated dementia, and neurodegeneration. See our Tryptophan page for the broader context.
Nicotinamide Riboside/Nicotinamide Mononucleotide vs Plain Niacin/NAM — The Cost-Effectiveness Question
Nicotinamide riboside (NR) and nicotinamide mononucleotide (NMN, popularized by David Sinclair's research at Harvard) have generated enormous enthusiasm as "next-generation" nicotinamide adenine dinucleotide precursors. The marketing claims they raise nicotinamide adenine dinucleotide more efficiently than plain niacin or NAM. Is it true?
What the human trials actually show
- Trammell et al. (2016, Nature Communications) — single-dose nicotinamide riboside pharmacokinetics (how the body absorbs and clears it) in healthy humans confirmed bioavailability and showed dose-dependent nicotinamide adenine dinucleotide increases in blood.
- Martens et al. (2018, Nature Communications) — chronic 1000 mg/day nicotinamide riboside for 6 weeks in middle-aged/older adults raised blood nicotinamide adenine dinucleotide by ~60%, with no significant adverse effects.
- Plain nicotinamide at similar gram-range doses also robustly raises tissue nicotinamide adenine dinucleotide. The 2000 Knip safety review called gram-range NAM well tolerated with a wide safety margin, but it also reported reversible liver toxicity at very high doses in animals and humans, infrequent minor liver enzyme changes at diabetes-prevention doses, and minor insulin resistance, and it classed NAM as a drug with toxic potential above 3 g/day in adults. In the ENDIT trial itself (552 relatives of people with type 1 diabetes, 5 years), serious adverse events did not differ from placebo, and nicotinamide "was ineffective at the dose we used" for preventing diabetes (see also Cautions for the sirtuin-inhibition concern).
- Head-to-head nicotinamide riboside vs NAM in older adults at equivalent nicotinamide adenine dinucleotide-raising doses are still relatively limited. The mechanistic advantage of nicotinamide riboside/nicotinamide mononucleotide is bypassing NAMPT (which declines with age), but the magnitude of clinical-outcome difference is not yet established.
- Yoshino et al. (2021, Science) — a 10-week randomized, double-blind trial of nicotinamide mononucleotide in postmenopausal women with prediabetes who were overweight or obese. Muscle insulin sensitivity, measured with a clamp test, rose on nicotinamide mononucleotide and did not change on placebo. The abstract gives no figure for the size of the change.
- The NICE trial (McDermott et al., 2024, Nature Communications) — 90 people with leg artery disease, 6 months. The 6-minute walk changed by +7.0 metres on nicotinamide riboside and −10.6 metres on placebo, a difference of 17.6 metres. Adding resveratrol added nothing. The authors say a larger trial is needed.
- Zhang et al. (2025, Critical Reviews in Food Science and Nutrition) — a review of 12 trials (513 people) found nicotinamide mononucleotide raises blood nicotinamide adenine dinucleotide, but most health measures did not differ from control. Every trial had some concerns or a high risk of bias, and the authors write that "an exaggeration of the benefits of NMN supplementation may exist in the field."
- Yang et al. (2026, Nutrients) — a review of 15 trials at 250-2000 mg/day for 14 days to 24 weeks found no increase in adverse events and no clear rise in liver enzymes over those short periods. Weight, glucose, lipids and systolic blood pressure did not change significantly; diastolic blood pressure fell slightly.
The cost reality
| Form | Approximate Cost per Gram | Cost per Month at nicotinamide adenine dinucleotide-raising dose |
|---|---|---|
| Plain nicotinamide (NAM) | $0.05-0.10 | $3-10 (at 500-1000 mg/day) |
| Nicotinic acid (immediate-release) | $0.10-0.20 | $5-20 |
| Nicotinamide riboside (NR) | $1-2 | $30-60 (at 250-500 mg/day) |
| Nicotinamide mononucleotide (NMN) | $1-3 | $30-90 |
For pure nicotinamide adenine dinucleotide raising in a budget-conscious patient, plain nicotinamide is the low-cost option — 20-40x cheaper than nicotinamide riboside or nicotinamide mononucleotide for an effect that some describe as in the same ballpark. No human comparison is cited here (head-to-head trials are limited, as above), and the Trammell 2016 paper reported that in mouse liver nicotinamide riboside had "distinct and superior pharmacokinetics" to nicotinic acid and nicotinamide. Nicotinamide riboside and nicotinamide mononucleotide are chosen when (1) the patient can afford them, (2) age-related NAMPT decline is a specific concern, or (3) tissue-distribution differences matter for a specific indication (some animal data suggest nicotinamide riboside reaches certain tissues more efficiently than NAM). For deeper comparison see nicotinamide adenine dinucleotide Precursors Compared on the nicotinamide adenine dinucleotide/nicotinamide mononucleotide page.
Flush vs Flush-Free — The Practical Choice
The prostaglandin-mediated niacin flush — a warm, tingling, red sensation of skin (face, neck, chest) starting 20-30 minutes after a 50+ mg dose of immediate-release nicotinic acid — is harmless but uncomfortable. It is the single most common reason patients abandon niacin therapy.
Who flushes
- Nicotinic acid at any dose above ~50 mg, particularly on an empty stomach, reliably flushes.
- Nicotinamide (NAM), NR, and nicotinamide mononucleotide do NOT flush at any dose. Flushing is specific to the carboxylic-acid form that activates GPR109A on Langerhans cells in the skin.
- Tachyphylaxis develops with repeated dosing — the flush typically diminishes substantially within 1-2 weeks of consistent use.
How the flush is managed in practice
- Slow titration: protocols begin at 100 mg with the largest meal of the day and double every 5-7 days as tolerated.
- Aspirin pre-treatment: 325 mg aspirin 30 minutes before the niacin dose blocks the prostaglandin D2 release that drives the flush.
- Food: taking it with food slows absorption and reduces peak flush intensity.
- Alcohol and hot beverages around the dose both potentiate the flush.
- Sustained-release (SR) caution: SR niacin causes much less flushing but carries substantially higher hepatotoxicity risk than immediate-release at equivalent doses (see Cautions).
When NAM/NR/Nicotinamide Mononucleotide Is Chosen Over Nicotinic Acid
- The indication is nicotinamide adenine dinucleotide raising rather than lipid management — flush-free forms work just as well for nicotinamide adenine dinucleotide.
- The patient has experienced significant flushing distress with nicotinic acid.
- The patient has a history of peptic ulcer disease — nicotinic acid can activate latent ulcers, NAM does not.
- The patient has active gout — nicotinic acid competes with uric acid for renal excretion, NAM does not.
"No-flush" niacin (inositol hexanicotinate) warning: this product is marketed as flush-free niacin but the inositol hexanicotinate complex releases very little free nicotinic acid in humans, and the lipid-modifying benefits of true nicotinic acid largely do not occur. Plain NAM raises nicotinamide adenine dinucleotide without flush; the lipid benefits of nicotinic acid come with some flushing.
Nicotinamide Adenine Dinucleotide Decline With Aging
A widely repeated statement in aging biology is that nicotinamide adenine dinucleotide levels decline substantially with age — roughly 50% between ages 40 and 60 in many tissues, with continued decline thereafter. A 2021 review across species (Peluso and colleagues) found the evidence "very limited" and often restricted to a single tissue or cell type, particularly in humans; a 2019 human muscle trial (Elhassan and colleagues) also calls human data "sparse". Three mechanisms are proposed:
- NAMPT decline. The rate-limiting salvage-pathway enzyme falls with age in many tissues, reducing the cell's ability to recycle NAM back to nicotinamide mononucleotide and nicotinamide adenine dinucleotide. Both transcriptional decline and post-translational regulation contribute.
- CD38 rise. CD38, a nicotinamide adenine dinucleotide-consuming ectoenzyme, increases dramatically in aged tissue — partly because tissue inflammation increases with age and CD38 is induced by inflammatory cytokines. The Camacho-Pereira et al. (2016, Cell Metabolism) mouse work titled "CD38 Dictates Age-Related NAD Decline and Mitochondrial Dysfunction through an SIRT3-Dependent Mechanism" made this case forcefully.
- PARP hyperactivation. Accumulated DNA damage with age chronically activates PARPs, which consume nicotinamide adenine dinucleotide at high rates during repair attempts. PARP1 alone can account for a substantial fraction of cellular nicotinamide adenine dinucleotide turnover in damaged tissue.
A commonly stated implication is that older adults benefit more from nicotinamide adenine dinucleotide precursor supplementation than younger adults — not because young people don't need nicotinamide adenine dinucleotide, but because young people's salvage and de novo pathways are working at full capacity already. In aged tissue, exogenous precursors can fill a gap that endogenous synthesis can no longer cover. The sources on this page do not compare benefit by age.
A 2025 pooled analysis of trials in people with mean ages from 60.9 to 83 (Prokopidis and colleagues) found no significant effect of nicotinamide mononucleotide on muscle mass, grip strength or walking speed. Nicotinamide riboside was linked to a longer 6-minute walk in people with leg artery disease, and to lower physical-performance scores in people with mild cognitive impairment. The authors conclude that current evidence "does not support NMN and NR supplementation for preserving muscle mass and function" in this age group.
Doses Described in Protocols and Trials
The figures below report what protocols and trials describe.
For Nicotinamide Adenine Dinucleotide raising (anti-aging, mitochondrial support)
- Plain nicotinamide (NAM): 500-1000 mg/day, sometimes split into 2 doses. Cheap, flush-free, and described as effective. Some protocols set a ceiling of 3000 mg/day because of sirtuin product inhibition (see Cautions).
- Nicotinamide riboside (NR): 250-500 mg/day (typical commercial dosing). Some users go to 1000 mg/day, the dose in the Martens 2018 trial.
- Nicotinamide mononucleotide: 250-1000 mg/day. Sublingual products dissolve in saliva for buccal absorption, which may bypass intestinal CD73 conversion to nicotinamide riboside.
For lipid management (statin-intolerant or Lp(a)-elevated patients)
- Immediate-release nicotinic acid. Sustained-release at gram-range doses carries a much higher hepatotoxicity risk (see Cautions).
- Protocols start at 100 mg with the largest meal of the day and rise by 100 mg every 5-7 days as the flush is tolerated, to 1000-2000 mg/day divided into 2-3 doses with meals.
- Aspirin 325 mg 30 minutes before each dose dramatically reduces flushing in the titration phase.
- Protocols check liver enzymes (alanine aminotransferase (ALT), aspartate aminotransferase (AST)) at baseline, 3 months, 6 months, then annually, along with fasting glucose and uric acid.
- See Cholesterol & Cardiovascular for the full clinical protocol.
For pellagra treatment
- Nicotinamide 300-500 mg/day in divided doses (NAM rather than nicotinic acid — flushing in a malnourished patient is undesirable).
- Improvement typically begins within 24-48 hours; full recovery over weeks if treated before neurological damage is established.
- A broad B-complex including B1, B2, B6, B12, and folate is usually given alongside — pellagra rarely occurs in isolation.
Cofactor stacking note: protocols using gram-range NAM or nicotinamide riboside/nicotinamide mononucleotide for nicotinamide adenine dinucleotide raising list B2 (riboflavin, 10-25 mg/day) and B6 (pyridoxine or P5P, 25-50 mg/day) because they are cofactors for both the tryptophan-NAD+ pathway and the glutathione regeneration that reduced nicotinamide adenine dinucleotide phosphate drives.
Cautions
- HEPATOTOXICITY — sustained-release nicotinic acid at >1 g/day. This is the single most important safety issue. SR-niacin causes elevated transaminases, cholestatic jaundice, and in rare cases fulminant hepatic failure. The McKenney 1994 JAMA paper directly compared SR vs immediate-release at equivalent lipid-modifying doses and found dramatically higher hepatotoxicity in the SR arm: 12 of 23 patients on sustained-release developed liver toxicity, and 0 of 23 on immediate-release. Even with immediate-release niacin, protocols check alanine aminotransferase/aspartate aminotransferase at baseline, 3 months, 6 months, and annually thereafter, and stop it if alanine aminotransferase exceeds 3x upper limit of normal.
- Hyperglycemia. Pharmacological-dose nicotinic acid (>1 g/day) raises fasting glucose by 5-10 mg/dL and hemoglobin A1c (HbA1c) by 0.3-0.4 in many patients — via increased adipose lipolysis and free fatty acid release driving hepatic gluconeogenesis. In type 2 diabetes, blood glucose is monitored closely after initiation and titration. NAM, NR, and nicotinamide mononucleotide do not have this effect.
- Gout / hyperuricemia. Nicotinic acid competes with uric acid for renal tubular excretion, raising serum uric acid and potentially triggering gout flares. In active gout, protocols describe allopurinol alongside nicotinic acid, or NAM in its place.
- Flush. Harmless but uncomfortable; see flush management section above.
- Peptic ulcer activation. Nicotinic acid increases gastric acid secretion and can reactivate latent peptic ulcers. In active peptic ulcer disease, protocols describe NAM in its place.
- Sirtuin product inhibition (high-dose NAM). At sustained doses above 3000 mg/day, NAM accumulates intracellularly and can inhibit sirtuins as a product-feedback inhibitor — the opposite of the desired longevity effect. Some protocols use a lower ceiling of ~2000 mg/day for nicotinamide adenine dinucleotide goals; the Knip review classes NAM as a drug with toxic potential above 3 g/day in adults. Nicotinamide riboside and nicotinamide mononucleotide are often described as free of this concern, but they do produce NAM: in a 2018 mouse tracer study, oral doses of both were metabolized to nicotinamide in the liver, and in a 2019 trial (12 aged men, 1 g nicotinamide riboside/day, 21 days) muscle showed increased nicotinamide clearance products.
- Pregnancy. Niacin requirements rise modestly during pregnancy (Recommended Dietary Allowance (RDA) 18 mg NE). Pharmacological doses (gram-range nicotinic acid) are not established as safe in pregnancy.
- Statin interaction. The AIM-HIGH and HPS2-THRIVE trials showed no incremental cardiovascular benefit from adding niacin to optimized statin therapy. AIM-HIGH (3,414 patients) was stopped after a mean of 3 years for lack of efficacy (events in 16.4% on niacin, 16.2% on placebo). HPS2-THRIVE (25,673 adults, 2 g extended-release niacin with laropiprant) had no significant fall in major vascular events (13.2% vs 13.7%) and more serious problems: diabetes control +3.7 percentage points, new diabetes diagnoses +1.3, infection +1.4, bleeding +0.7, gastrointestinal +1.0, musculoskeletal +0.7, skin +0.3. Niacin's modern niche is largely in statin-intolerant patients with persistent dyslipidemia, not as add-on to statins.
- Niacin breakdown products and heart events. A 2024 study linked two breakdown products of excess niacin (2PY and 4PY) in the blood with more major cardiovascular events over 3 years, in US and European groups (hazard ratios 1.64 and 2.02 for 2PY, 1.89 and 1.99 for 4PY). In mice, 4PY at physiological levels made blood vessel linings more inflamed and sticky to white blood cells. This is an association in people and does not prove that niacin intake causes heart disease.
Key Research Papers
- Preiss J, Handler P (1958). Biosynthesis of diphosphopyridine nucleotide. I. Identification of intermediates. J Biol Chem. — PubMed PMID: 13563526
- Preiss J, Handler P (1958). Biosynthesis of diphosphopyridine nucleotide. II. Enzymatic aspects. J Biol Chem. — PubMed PMID: 13563527
- Bieganowski P, Brenner C (2004). Discoveries of nicotinamide riboside as a nutrient and conserved NRK genes establish a Preiss-Handler independent route to NAD+. Cell. — PubMed PMID: 15137942
- Trammell SA et al. (2016). Nicotinamide riboside is uniquely and orally bioavailable in mice and humans. Nature Communications. — PubMed PMID: 27721479
- Martens CR et al. (2018). Chronic nicotinamide riboside supplementation is well-tolerated and elevates NAD+ in healthy middle-aged and older adults. Nature Communications. — PubMed PMID: 29599478
- Mills KF et al. (2016). Long-term administration of nicotinamide mononucleotide mitigates age-associated physiological decline in mice. Cell Metabolism. — PubMed PMID: 28068222
- Yoshino J et al. (2018). NAD+ intermediates: the biology and therapeutic potential of NMN and NR. Cell Metabolism. — PubMed PMID: 29249689
- Camacho-Pereira J et al. (2016). CD38 Dictates Age-Related NAD Decline and Mitochondrial Dysfunction through an SIRT3-Dependent Mechanism. Cell Metabolism. — PubMed PMID: 27304511
- Imai S, Guarente L (2014). NAD+ and sirtuins in aging and disease. Trends Cell Biol. — PubMed PMID: 24786309
- Verdin E (2015). NAD+ in aging, metabolism, and neurodegeneration. Science. — PubMed PMID: 26785480
- Canto C et al. (2012). The NAD+ precursor nicotinamide riboside enhances oxidative metabolism and protects against high-fat diet-induced obesity. Cell Metabolism. — PubMed PMID: 22682224
- McKenney JM et al. (1994). A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA. — PubMed PMID: 8309029
- Knip M et al. (2000). Safety of high-dose nicotinamide: a review. Diabetologia. — PubMed PMID: 11126400
- Gale EA et al. (2004). European Nicotinamide Diabetes Intervention Trial (ENDIT): a randomised controlled trial of intervention before the onset of type 1 diabetes. Lancet. — PubMed PMID: 15043959
- Liu L et al. (2018). Quantitative Analysis of NAD Synthesis-Breakdown Fluxes. Cell Metabolism. — PubMed PMID: 29685734
- Elhassan YS et al. (2019). Nicotinamide Riboside Augments the Aged Human Skeletal Muscle NAD(+) Metabolome and Induces Transcriptomic and Anti-inflammatory Signatures. Cell Reports. — PubMed PMID: 31412242
- Peluso A et al. (2021). Age-Dependent Decline of NAD(+)-Universal Truth or Confounded Consensus? Nutrients. — PubMed PMID: 35010977
- Yoshino M et al. (2021). Nicotinamide mononucleotide increases muscle insulin sensitivity in prediabetic women. Science. — PubMed PMID: 33888596
- McDermott MM et al. (2024). Nicotinamide riboside for peripheral artery disease: the NICE randomized clinical trial. Nature Communications. — PubMed PMID: 38871717
- Zhang J et al. (2025). Efficacy of oral nicotinamide mononucleotide supplementation on glucose and lipid metabolism for adults: a systematic review with meta-analysis on randomized controlled trials. Critical Reviews in Food Science and Nutrition. — PubMed PMID: 39116016
- Yang W et al. (2026). Safety and Metabolism-Related Outcomes of Oral Nicotinamide Mononucleotide Supplementation in Adults: A Systematic Review and Meta-Analysis. Nutrients. — PubMed PMID: 42514320
- Prokopidis K et al. (2025). The Effect of Nicotinamide Mononucleotide and Riboside on Skeletal Muscle Mass and Function: A Systematic Review and Meta-Analysis. Journal of Cachexia, Sarcopenia and Muscle. — PubMed PMID: 40275690
- Ferrell M et al. (2024). A terminal metabolite of niacin promotes vascular inflammation and contributes to cardiovascular disease risk. Nature Medicine. — PubMed PMID: 38374343
- AIM-HIGH Investigators, Boden WE et al. (2011). Niacin in patients with low HDL cholesterol levels receiving intensive statin therapy. New England Journal of Medicine. — PubMed PMID: 22085343
- HPS2-THRIVE Collaborative Group, Landray MJ et al. (2014). Effects of extended-release niacin with laropiprant in high-risk patients. New England Journal of Medicine. — PubMed PMID: 25014686
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B3 Overview
- B3 Benefits Hub
- B3 for Cholesterol & Cardiovascular
- B3 for Pellagra & Skin
- B3 for Schizophrenia & Mental Health
- Nicotinamide Adenine Dinucleotide / Nicotinamide Mononucleotide
- Tryptophan
- Glutathione
- Vitamin B2 (Riboflavin)
- Vitamin B6 (Pyridoxine)
- Vitamin B1 (Thiamine)
- Cholesterol Management
- Niacin in Gerson Therapy
- Lipid Panel
- Deficiency
- Toxicity
- History
- Sources