⚠ Evidence warning: Clinical trials or other evidence do not support the claims that marginal riboflavin is the most common cause of incomplete response to glutathione precursors, that riboflavin status is checked or supplemented in anyone suspected of glutathione depletion, that vitamin B2 enhances iron absorption and mobilization, and that the GlyNAC protocol works because most Western adults have adequate B2 and selenium. This page keeps it as a report of what people, websites or other media say.
Riboflavin (Vitamin B2) as the Glutathione Reductase Cofactor
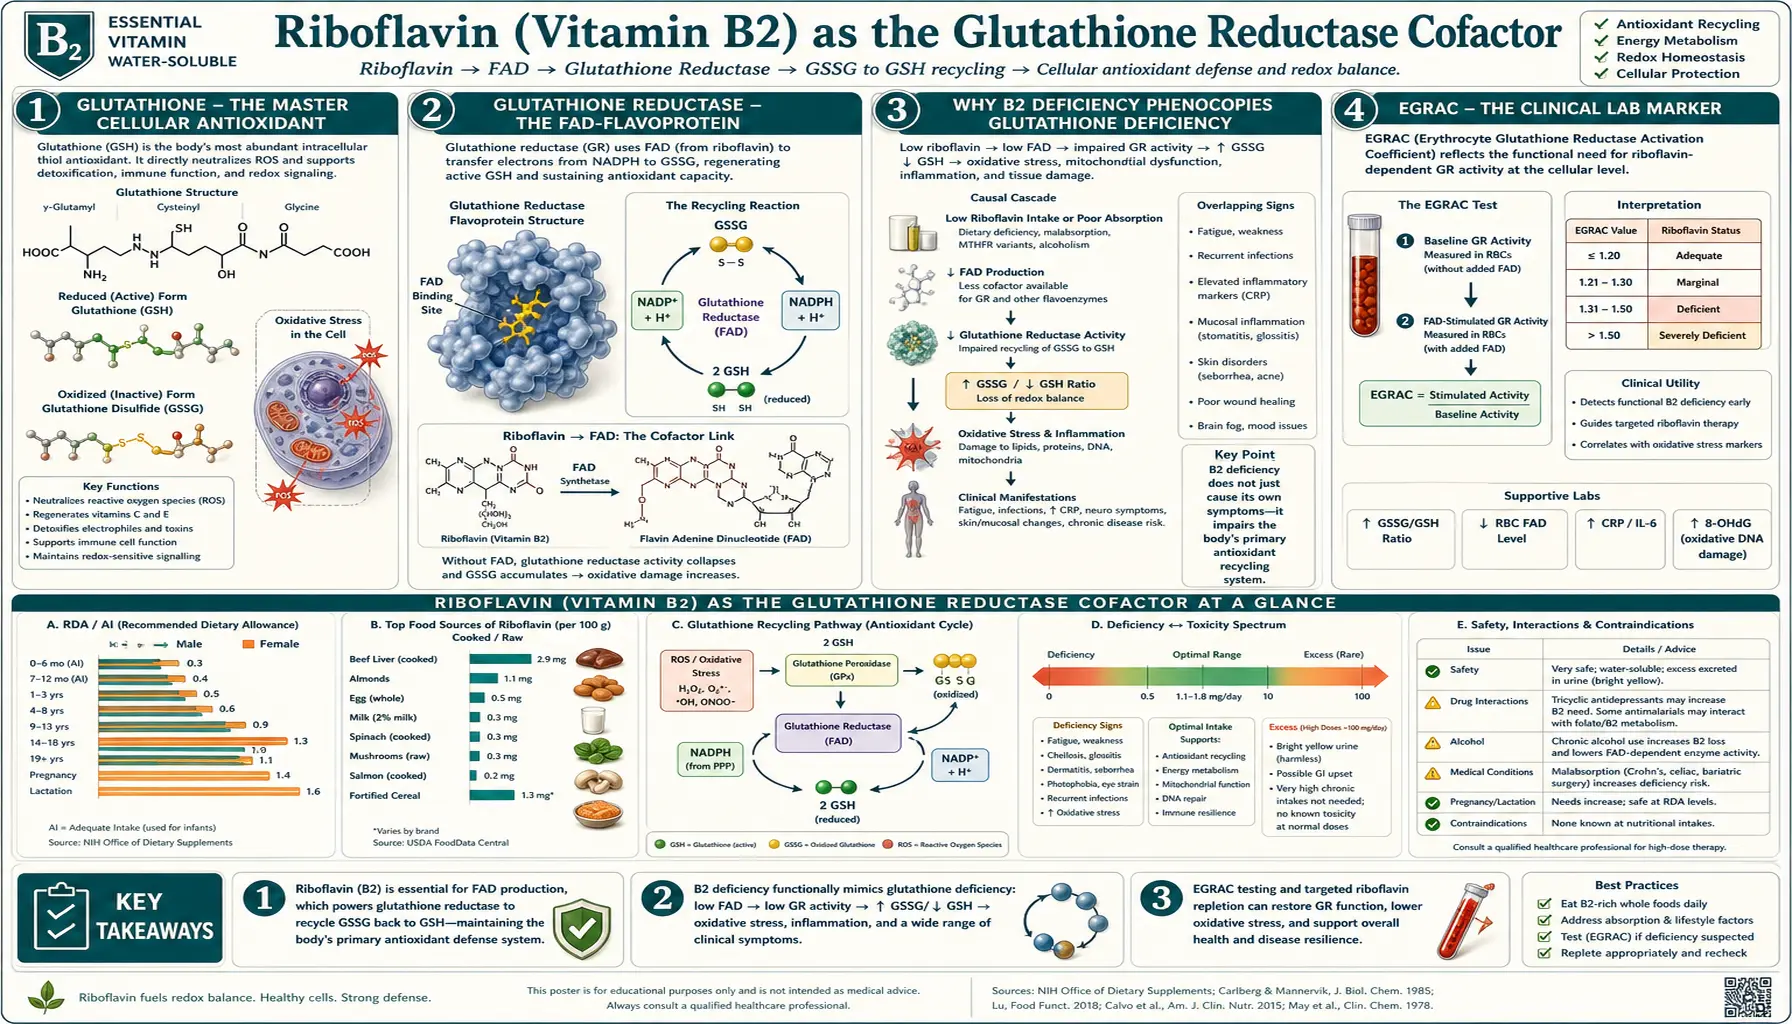
Glutathione is the body's master intracellular antioxidant. It is only effective in its reduced form (reduced glutathione, GSH). After scavenging a reactive oxygen species, reduced glutathione becomes oxidized glutathione disulfide (GSSG), which must be regenerated to reduced glutathione to keep working. The enzyme that performs this regeneration is glutathione reductase (GR) — and GR is a FAD-flavoprotein that absolutely requires riboflavin. Without adequate B2, the entire glutathione antioxidant system fails. Riboflavin deficiency phenocopies glutathione deficiency at the cellular level. The clinical relevance reaches from red blood cell stability and eye lens cataract prevention to liver detoxification and the rationale behind the GlyNAC anti-aging protocol. This deep-dive covers the GR mechanism, the EGRAC clinical lab marker, the cataract and ocular evidence, and how riboflavin slots into the broader glutathione-replenishment toolkit alongside N-acetylcysteine (NAC), glycine, selenium, and sulfur.
Table of Contents
- Glutathione — the Master Cellular Antioxidant
- Glutathione Reductase — the FAD-Flavoprotein
- Why B2 Deficiency Phenocopies Glutathione Deficiency
- EGRAC — the Clinical Lab Marker
- The Eye Lens, Reduced Glutathione, and Cataract Prevention
- Red Blood Cell Stability and Oxidative Hemolysis
- Liver Detoxification and Glutathione Conjugation
- The GlyNAC Protocol and Where Riboflavin Fits
- Selenium, Sulfur, and the Broader Redox Network
- Riboflavin Doses Used in Studies and Described in Practice
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Glutathione — the Master Cellular Antioxidant
Glutathione is a tripeptide of glutamate, cysteine, and glycine (γ-Glu-Cys-Gly), synthesized inside every cell in two adenosine triphosphate-dependent steps by glutamate-cysteine ligase (GCL, the rate-limiting enzyme) and glutathione synthetase. Cellular concentrations are in the millimolar range — among the highest of any small molecule in the cell — reflecting the central role it plays in redox defense.
Glutathione's antioxidant work depends on the thiol (–SH) group of its cysteine residue. When reduced glutathione encounters a reactive oxygen species (hydrogen peroxide, lipid peroxide, hydroxyl radical, or a reactive electrophile), the cysteine thiol donates an electron to neutralize it. The resulting glutathione radical pairs with a second glutathione radical to form glutathione disulfide (GSSG), in which two glutathione molecules are linked through their cysteine sulfurs.
GSSG is biologically inactive as an antioxidant — the working thiols are tied up. For the antioxidant system to keep functioning, GSSG must be reduced back to two molecules of reduced glutathione. This regeneration is performed by glutathione reductase.
The healthy cellular ratio is approximately GSH:GSSG = 100:1 in well-perfused tissue under normal conditions. The ratio is one of the most sensitive markers of cellular oxidative stress — when GSH:GSSG drops to 10:1 or below, the cell is in serious redox crisis, and signaling cascades that trigger apoptosis (caspase activation, JNK phosphorylation) begin.
Maintaining the high GSH:GSSG ratio is therefore a continuous, energy-intensive task. The cell does this in two ways:
- De novo synthesis of new glutathione from amino acid precursors (glutamate + cysteine + glycine) — the substrate-supply pathway addressed by the GlyNAC protocol
- Regeneration of existing GSSG back to reduced glutathione by glutathione reductase — the riboflavin-dependent pathway
Both pathways must function for cellular redox balance. Substrate supply without regeneration fails; regeneration without substrate supply fails. Riboflavin is the limiting factor for the regeneration arm.
Glutathione Reductase — the FAD-Flavoprotein
Glutathione reductase (GR; gene GSR) is a homodimeric flavoenzyme of the pyridine-nucleotide-disulfide oxidoreductase family (which also includes thioredoxin reductase, lipoamide dehydrogenase, and trypanothione reductase). Each subunit binds:
- One FAD molecule — non-covalently but tightly bound
- One reduced nicotinamide adenine dinucleotide phosphate-binding site
- One GSSG-binding site with a redox-active cysteine disulfide
The reaction GR catalyzes:
GSSG + NADPH + H+ → 2 GSH + NADP+
Mechanism: reduced nicotinamide adenine dinucleotide phosphate (NADPH) (the high-energy electron donor produced by the pentose phosphate pathway) docks on one face of the FAD and transfers a hydride. The reduced FADH2 then reduces the active-site cysteine disulfide, which in turn reduces the bound GSSG, yielding two free reduced glutathione. The enzyme returns to its oxidized state and begins another cycle.
The key feature for our purposes: no FAD, no GR activity. Riboflavin status is the upstream determinant of how much functional glutathione reductase a cell can deploy. In riboflavin deficiency, GR is synthesized as the apoenzyme (without bound FAD) and is catalytically inert. Adding riboflavin restores GR activity proportionally to flavin loading.
The human evidence for this comes from a 1969 study of red blood cells. Adding small amounts of FAD — but not riboflavin itself or flavin mononucleotide — to red-cell extracts switched on extra glutathione reductase activity, showing that part of the enzyme was sitting idle without its FAD. In people, 5 mg of riboflavin a day produced a marked rise in red-cell glutathione reductase activity within only 2 days, and the activity began to fall again after the riboflavin was stopped. The rise was larger in people whose diets were lower in riboflavin (Beutler 1969).
GR is expressed in essentially every tissue but is particularly abundant in liver, red blood cells, and the eye lens — the three tissues that face the highest oxidative loads and that demonstrate the clearest clinical consequences of B2 deficiency.
Why B2 Deficiency Phenocopies Glutathione Deficiency
A patient with adequate glutathione synthesis but inadequate riboflavin will, paradoxically, present with the clinical features of glutathione deficiency:
- Elevated oxidative stress markers — F2-isoprostanes, 8-hydroxydeoxyguanosine, malondialdehyde all rise
- Low GSH:GSSG ratio on cellular measurement — even when total glutathione is normal, the equilibrium has shifted to the oxidized side because GR cannot regenerate it
- Reduced erythrocyte resistance to oxidative challenge — clinically detectable as hemolysis in response to oxidative stressors
- Increased lens opacity and cataract risk — because the lens depends on reduced glutathione and lacks its own glutathione synthesis after maturation
- Reduced Phase II liver conjugation capacity — because Phase II depends on reduced glutathione for glutathione-S-transferase reactions
- Impaired methylmercury, acetaminophen, and reactive electrophile detoxification
- Lower nasal/conjunctival mucosal defense against oxidative pollutants
Bonus mechanism: methylation cycle disruption. Reduced glutathione provides the cysteine substrate that the trans-sulfuration pathway uses to make taurine, sulfate, and additional reduced glutathione. Riboflavin deficiency (via low GSH:GSSG and via the parallel methylenetetrahydrofolate reductase (MTHFR) cofactor failure) compounds disruption of one-carbon metabolism downstream.
The clinical implication: in any patient suspected of glutathione depletion, riboflavin status is checked or empirically supplemented.
The reasoning that follows from this mechanism: when riboflavin status is marginal, giving N-acetylcysteine and glycine raises substrate supply for a regeneration enzyme that may not be able to keep up. This is the most common cause of incomplete clinical response to glutathione-precursor supplementation. This is a hypothesis. The GlyNAC trials, which corrected red-cell glutathione deficiency in older adults, did not measure or report riboflavin status (Kumar 2021; Kumar 2023), and no study cited here measures how often marginal riboflavin limits the response to glutathione precursors.
EGRAC — the Clinical Lab Marker
The most clinically useful lab measure of riboflavin functional status is the erythrocyte glutathione reductase activity coefficient (EGRAC). The assay:
- Measure baseline glutathione reductase activity in lysed red blood cells (this is the apoenzyme + holoenzyme activity that is present at the moment of sampling)
- Add exogenous FAD to a parallel aliquot and re-measure GR activity (this saturates any unliganded apoenzyme with FAD and gives the maximum possible activity)
- EGRAC = activity-with-FAD / activity-without-FAD
Interpretation:
- EGRAC < 1.20 — normal riboflavin status; almost all GR is already loaded with FAD; little additional activity is unlocked by exogenous FAD
- EGRAC 1.20-1.40 — marginal status; some unliganded apoenzyme present
- EGRAC > 1.40 — deficiency; substantial apoenzyme that becomes catalytically active when given FAD — meaning the patient was carrying unliganded enzyme because cellular flavin was insufficient
EGRAC is the gold-standard functional marker because it measures the cellular consequence of B2 status, not just blood concentration. Plasma riboflavin and urinary riboflavin can be normal in patients whose intracellular FAD loading is inadequate (because of poor uptake or recent intake variability), but EGRAC reflects the actual enzymatic deficit.
Practical caveats: EGRAC is offered only at specialized reference laboratories, not routine commercial labs. It is also unreliable in patients with glucose-6-phosphate dehydrogenase (G6PD) deficiency, which has its own effect on red blood cell GR activity. Practitioners describe an empirical approach instead: giving riboflavin 25-100 mg/day and watching the clinical response and the bright-yellow urine it produces.
Deficiency measured by this test is common, even in rich countries. A 2026 study that used EGRAC 1.40 or higher as the cut-off found riboflavin deficiency in 48% of unsupplemented women aged 18 to 45 in Ireland (251 women) and 50% in Britain (163 women); in Irish women, status fell step by step as dietary riboflavin fell. Rates were higher in low- and middle-income countries: 72% of women in Malaysia and 82% in Cambodia (McAnena 2026).
For comparison with intake, the European Food Safety Authority (EFSA) panel set the adult average requirement at 1.3 mg of riboflavin a day and the population reference intake at 1.6 mg a day, rising to 1.9 mg in pregnancy and 2.0 mg when breastfeeding. The panel judged EGRAC a useful marker of riboflavin status that has limitations, and based its figures on the intake at which urinary riboflavin excretion rises sharply, a sign the body is saturated (EFSA 2017).
The Eye Lens, Reduced Glutathione, and Cataract Prevention
The crystalline lens of the eye has one of the highest reduced glutathione concentrations of any tissue and one of the most exquisite dependences on GR activity. Several anatomical facts make the lens uniquely vulnerable to riboflavin deficiency:
- The lens is avascular — it receives nutrients by diffusion from the aqueous humor only
- The lens cortex is metabolically active but the central nucleus is post-mitotic and cannot replace damaged proteins
- Lens crystallin proteins are extraordinarily long-lived — the same molecules synthesized in fetal life persist until death
- Ultraviolet-A exposure generates continuous oxidative stress in the anterior lens
- Cataract is the accumulation of oxidized, cross-linked crystallin aggregates — the irreversible end-stage of lifelong oxidative damage
Glutathione is the lens's primary defense. The lens cortex synthesizes reduced glutathione and pumps it into the nucleus, where it scavenges reactive oxygen species generated by ultraviolet (UV) exposure. The high GSH:GSSG ratio is maintained by GR, which requires FAD, which requires riboflavin.
Observational studies have linked higher dietary riboflavin intake with fewer cataracts:
- Blue Mountains Eye Study — a cross-sectional study of 2,900 people aged 49 to 97 living near Sydney, Australia. After adjusting for known cataract risk factors, people in the top fifth of riboflavin intake had about half the odds of nuclear cataract (in the centre of the lens) of those in the bottom fifth (odds ratio 0.5, 95% confidence interval 0.3-0.9). Protein, vitamin A, niacin and thiamin showed similar links (Cumming 2000).
- Lens Opacities Case-Control Study — 1,380 eye-clinic patients aged 40 to 79. Dietary riboflavin, together with vitamins C and E and carotene, was linked to lower risk of cortical, nuclear and mixed cataract, and regular multivitamin use to lower risk of all cataract types (odds ratio 0.63) (Leske 1991).
- Age-Related Eye Disease Study — 3,115 people aged 55 to 80, followed for an average of 9.6 years. At the start of the study, people with the highest dietary riboflavin had lower odds of cataract than those with the lowest: mild nuclear cataract odds ratio 0.78, moderate nuclear cataract 0.62 and mild cortical cataract 0.80 (Glaser 2015).
These are observational findings, not trials, so they show a link rather than proof that riboflavin prevents cataract. The proposed mechanism: more B2 → more functional GR → higher GSH:GSSG in the lens → less crystallin oxidation → lower cataract incidence. It has also been proposed that populations with chronic marginal riboflavin intake (parts of South Asia and Sub-Saharan Africa with low-dairy, low-meat diets) have correspondingly high age-related cataract incidence; no study cited on this page tests that link.
Bonus mechanism: corneal cross-linking (CXL) for keratoconus. In this clinical procedure, the cornea is saturated with topical riboflavin and then exposed to ultraviolet-A light. The riboflavin acts as an ultraviolet-activated photosensitizer that generates singlet oxygen and free radicals locally, which cross-link the corneal collagen and stiffen the cornea, halting keratoconus progression. This is the only currently approved disease-modifying treatment for keratoconus and a striking demonstration of how riboflavin's redox chemistry has been weaponized therapeutically.
Intake figures for comparison: the adult population reference intake set by EFSA is 1.6 mg a day (EFSA 2017); the 5-25 mg/day range that some writers describe as the Recommended Dietary Allowance (RDA) plus a safety margin is several times higher. Practitioners describe modest supplementation for people at higher risk of cataract (those with diabetes, chronic ultraviolet exposure, a family history of early cataract, or a vegan diet without B-complex supplements), and describe higher doses as adding no further cataract protection once glutathione reductase is saturated. No trial cited here tested riboflavin supplements for cataract.
Red Blood Cell Stability and Oxidative Hemolysis
Red blood cells are uniquely vulnerable to oxidative damage. They carry oxygen (which makes them constant sources of reactive oxygen species), they have no mitochondria (so they cannot generate reduced nicotinamide adenine dinucleotide phosphate via the Krebs cycle), and they cannot synthesize new proteins to replace oxidatively damaged ones. Their entire antioxidant defense rests on the pentose phosphate pathway (which generates reduced nicotinamide adenine dinucleotide phosphate from glucose-6-phosphate via glucose-6-phosphate dehydrogenase) and the GSH-GR-NADPH loop.
- Glucose-6-phosphate dehydrogenase generates reduced nicotinamide adenine dinucleotide phosphate in the pentose phosphate pathway
- Reduced nicotinamide adenine dinucleotide phosphate is the electron donor for GR
- GR (FAD-flavoprotein) regenerates reduced glutathione from GSSG
- Reduced glutathione scavenges hydrogen peroxide and other reactive oxygen species (ROS) via glutathione peroxidase (a selenium-dependent enzyme)
Disruption at any node produces oxidative hemolysis. Glucose-6-phosphate dehydrogenase deficiency is the classic example (Heinz body hemolytic anemia in response to oxidative drugs like primaquine, fava beans, or sulfa antibiotics). Selenium deficiency reduces glutathione peroxidase activity. And riboflavin deficiency disrupts GR — producing a parallel but distinct hemolytic vulnerability.
The clinical implication: chronic riboflavin deficiency contributes to a mild normocytic, normochromic anemia that is often labeled idiopathic or attributed to chronic disease. It does not respond to iron supplementation (because the iron stores are adequate) but does respond to riboflavin repletion. In patients with glucose-6-phosphate dehydrogenase deficiency, riboflavin status is described as taking on extra importance, because their remaining GR capacity carries more of the load.
Riboflavin status also affects iron handling. B2 enhances iron absorption from the intestine, mobilization from ferritin stores, and incorporation into hemoglobin. A 2003 review found reasonably good evidence that poor riboflavin status interferes with iron handling and contributes to anemia when iron intakes are low; proposed mechanisms include effects on the gut that may hamper the handling of other nutrients (Powers 2003). In the RIBOFEM trial, 123 riboflavin-deficient women aged 19 to 25 in the United Kingdom (EGRAC above 1.40) took 2 or 4 mg of riboflavin or a placebo for 8 weeks. Hemoglobin rose as riboflavin status improved, and women with the poorest starting status (EGRAC above 1.65) gained the most, but dietary iron intake and iron absorption did not change during the study (Powers 2011). Practitioners report that iron-deficiency anemia that does not fully respond to oral iron sometimes improves when B2 is added, particularly in vegetarians and vegans with marginal dietary B2; no trial cited here tested this.
Liver Detoxification and Glutathione Conjugation
Hepatic Phase II detoxification depends on conjugation reactions that attach polar groups to lipid-soluble toxins, making them water-soluble for elimination. Glutathione-S-transferase (GST) is one of the major Phase II enzyme families, conjugating reduced glutathione onto a wide range of electrophilic toxins — including reactive metabolites of acetaminophen, polycyclic aromatic hydrocarbons, alkylating agents, and many drugs.
Each GST reaction consumes one reduced glutathione. In times of high toxin load, the cellular reduced glutathione pool depletes rapidly. The cell's ability to keep detoxifying depends on:
- De novo reduced glutathione synthesis from cysteine (N-acetylcysteine-supplementable)
- Regeneration of GSSG back to reduced glutathione by riboflavin-dependent GR
The acetaminophen overdose paradigm is the textbook case. N-acetylcysteine saves lives because it replenishes the cysteine substrate needed for new reduced glutathione synthesis. But background regeneration of GSSG by GR is also working continuously in the background, and adequate riboflavin status is what allows this regeneration to keep up.
For patients with chronic toxin exposure (industrial chemical workers, smokers, people with chronic alcohol use, those with high-pollution living environments), riboflavin status is a foundational determinant of detoxification capacity. The integrative medicine framing — the "tox-screen plus support" approach — routinely includes a B-complex with adequate B2 alongside N-acetylcysteine, glycine, milk thistle, and the cruciferous vegetables that upregulate Phase II enzyme expression.
The GlyNAC Protocol and Where Riboflavin Fits
The GlyNAC protocol (glycine + N-acetylcysteine) was developed by Rajagopal Sekhar and colleagues at Baylor College of Medicine to restore glutathione in aging adults. Two trials from the group documented that older adults have low reduced glutathione and that N-acetylcysteine (cysteine precursor) + glycine (also a glutathione constituent) corrected the red-blood-cell glutathione deficiency and improved inflammation markers, insulin resistance, mitochondrial function, walking speed, and strength: an open-label pilot trial in 8 older adults over 24 weeks, whose benefits declined after GlyNAC was stopped for 12 weeks (Kumar 2021), and a randomized placebo-controlled trial in 24 older adults over 16 weeks (Kumar 2023). The GlyNAC deep-dive covers the protocol in detail.
What GlyNAC addresses: substrate supply for de novo glutathione synthesis. Older adults often have inadequate cysteine intake (and reduced cysteine availability from the diet, particularly in low-protein elderly diets), so providing the rate-limiting amino acid precursors restores synthesis capacity.
What GlyNAC does not address: regeneration capacity. A patient with marginal riboflavin status whose GR is partially apoenzyme-loaded cannot fully utilize the new reduced glutathione produced by GlyNAC — the cell will continue to accumulate GSSG faster than it can regenerate it, and the cellular GSH:GSSG ratio will remain suboptimal even as total glutathione rises.
The doses used in the 2021 GlyNAC pilot trial, and the other nutrients that practitioners describe adding to it for older adults with oxidative stress and inflammation:
- Cysteine 0.81 mmol/kg/day, given as N-acetylcysteine — cysteine precursor for de novo reduced glutathione synthesis (the dose in the 2021 trial, given for 24 weeks; Kumar 2021). Practitioners also describe a flat 600-1200 mg/day of N-acetylcysteine, which is not the trial dose.
- Glycine 1.33 mmol/kg/day — the other glutathione constituent that often limits synthesis in elderly (the dose in the 2021 trial; Kumar 2021)
- Riboflavin 25-50 mg/day — FAD supply for the regeneration arm (a practitioner addition, not part of the GlyNAC trials)
- Selenium 100-200 mcg/day — glutathione peroxidase cofactor (where reduced glutathione actually neutralizes reactive oxygen species)
- Niacinamide 50-500 mg/day — NAD+/NADP+ precursor, since reduced nicotinamide adenine dinucleotide phosphate is the electron donor for GR
As practitioners describe it, this five-component "complete glutathione" combination aims at substrate supply (N-acetylcysteine + glycine), regeneration (B2 + niacinamide for reduced nicotinamide adenine dinucleotide phosphate), and downstream use (selenium for GPx). The bare GlyNAC protocol works because most middle-aged Western adults have adequate B2 and selenium incidentally; adding the supporting nutrients explicitly ensures the regeneration loop is intact. The combination itself has not been tested in a trial cited here. Riboflavin deficiency is not rare in Western adults: in 2026 data, about half of unsupplemented women aged 18 to 45 in Ireland (48%) and Britain (50%) had deficiency by the EGRAC test (McAnena 2026).
Selenium, Sulfur, and the Broader Redox Network
The cellular redox network is more than just glutathione and GR. Several other components are tightly coupled to B2 status:
- Glutathione peroxidase (GPx) — uses reduced glutathione as substrate to reduce hydrogen peroxide and lipid peroxides; requires selenium as a selenocysteine residue. GPx generates the GSSG that GR then regenerates. B2 ↔ selenium synergy.
- Thioredoxin reductase — another FAD-flavoprotein in the same enzyme family as GR; regenerates thioredoxin, a parallel cellular antioxidant. Also riboflavin-dependent.
- Peroxiredoxins — thiol-based peroxidases that use thioredoxin (and hence indirectly require functional thioredoxin reductase — another flavoprotein)
- Reduced nicotinamide adenine dinucleotide phosphate (the electron donor for GR) — comes from glucose-6-phosphate dehydrogenase activity (the pentose phosphate pathway) and from reduced nicotinamide adenine dinucleotide phosphate-isocitrate dehydrogenase. Reduced nicotinamide adenine dinucleotide phosphate availability is the kinetic upstream limit on GR.
- Sulfur amino acids — methionine and cysteine supply the trans-sulfuration pathway that generates the cysteine for de novo reduced glutathione synthesis. Methionine cycle integrity (which depends on B2 via methylenetetrahydrofolate reductase) feeds into the trans-sulfuration pathway.
The integrated picture: riboflavin status sets the ceiling for both glutathione reductase and thioredoxin reductase activity, the two FAD-flavoprotein guardians of the cellular thiol redox state. Compounding the effect, B2 deficiency (via methylenetetrahydrofolate reductase cofactor failure) disrupts the methionine cycle that feeds the trans-sulfuration pathway. The cumulative effect of marginal riboflavin status on cellular redox capacity is therefore larger than any single mechanism implies.
Riboflavin Doses Used in Studies and Described in Practice
Doses used in the studies cited here
- 5 mg/day riboflavin produced a marked rise in red-cell glutathione reductase activity within 2 days (Beutler 1969)
- 2 or 4 mg/day for 8 weeks improved riboflavin status in a dose-dependent way in deficient young women (Powers 2011)
- Single oral doses of 20, 40 and 60 mg were compared in healthy adults; the most riboflavin absorbed from a single dose was 27 mg per adult (Zempleni 1996)
- Glycine 1.33 mmol/kg/day and cysteine 0.81 mmol/kg/day as N-acetylcysteine for 24 weeks in the GlyNAC pilot trial, which contained no riboflavin (Kumar 2021)
- Reference intake: EFSA's adult population reference intake is 1.6 mg/day (EFSA 2017)
General redox-support amounts described in practice
- 25-50 mg/day as part of a B-complex — described by practitioners as the dose that saturates the cellular flavoenzyme pool in adults without unusual requirements
- Taking it with food is described as helping, because absorption is saturable and slower stomach emptying spreads it out
- Yellow urine within 24-48 hours is a sign that riboflavin was absorbed
Higher amounts practitioners describe for high-need situations
- Aging adults on GlyNAC — 50-100 mg/day riboflavin added, with the aim that GR regeneration keeps pace with new reduced glutathione synthesis
- Chronic oxidative-stress conditions (chronic infection, cancer survivorship, autoimmune disease, post-radiation): 100-200 mg/day
- Diabetic patients — chronic hyperglycemia produces ongoing reactive oxygen species; riboflavin status supports the GR-GSH axis. 50-100 mg/day.
- Heavy metal exposure / chelation therapy — mercury, lead, cadmium all consume reduced glutathione; B2 supports the regeneration arm. 50-100 mg/day.
- Chronic alcohol or chemical exposure — supports Phase II detoxification. 25-100 mg/day.
A wider redox-network combination described in practice
- Riboflavin 50-100 mg/day — FAD for GR and thioredoxin reductase
- N-acetylcysteine 600-1200 mg/day — cysteine precursor for reduced glutathione synthesis
- Glycine 3-6 g/day — second amino acid substrate for reduced glutathione
- Selenium 100-200 mcg/day (selenomethionine or yeast-bound) — GPx cofactor
- Niacinamide 100-500 mg/day — NADP+ precursor for the reduced nicotinamide adenine dinucleotide phosphate supply
- Alpha-lipoic acid 600 mg/day — antioxidant network regeneration including vitamins C and E
- Vitamin C 500-1000 mg/day — aqueous-phase antioxidant; spares reduced glutathione
- Vitamin E 200-400 international units (IU)/day (mixed tocopherols) — lipid-phase antioxidant
Monitoring described in practice
- EGRAC if available at a specialty reference lab
- Practical surrogates: plasma F2-isoprostanes (oxidative stress marker), high-sensitivity C-reactive protein (hs-CRP) (inflammation), patient-reported fatigue and exercise tolerance
- Bright yellow urine is the cheap home marker of adequate riboflavin absorption
Cautions
- Glucose-6-phosphate dehydrogenase deficiency — supplementation with riboflavin is safe and beneficial, but EGRAC interpretation is confounded by altered erythrocyte enzyme activity in glucose-6-phosphate dehydrogenase patients. Practitioners rely on clinical and exposure-based assessment rather than EGRAC in these patients.
- Light degradation — riboflavin is broken down by light; dark, opaque containers protect riboflavin and B-complex supplements, and foods, from light exposure
- Absorption saturation — the most riboflavin absorbed from a single oral dose was 27 mg per adult (Zempleni 1996); larger daily totals are often divided into several doses for this reason
- No conflict with N-acetylcysteine, glycine, or selenium — the regeneration-arm role is fully complementary to substrate-supply and downstream-effector nutrients
- Hepatic dysfunction — severe liver disease impairs riboflavin-to-FAD conversion; practitioners use R5P (riboflavin-5′-phosphate, the active FMN form) in such cases
- Drug interactions are minimal; tetracyclines, phenothiazines, and tricyclics may slightly reduce riboflavin utilization but the clinical relevance is small at supplemental doses
- Pregnancy and lactation — the need for riboflavin rises: EFSA's reference intakes are 1.9 mg/day in pregnancy and 2.0 mg/day when breastfeeding (EFSA 2017); the studies cited here give no safety data on high therapeutic doses in pregnancy
Key Research Papers
- Karplus PA & Schulz GE (1989). Substrate binding and catalysis by glutathione reductase as derived from refined enzyme: substrate crystal structures at 2 Å resolution. J Mol Biol 210(1):163-80. — PubMed PMID: 2585516
- Powers HJ (2003). Riboflavin (vitamin B-2) and health. American Journal of Clinical Nutrition 77(6):1352-60. — PubMed PMID: 12791609
- Sauberlich HE (1984). Implications of nutritional status on human biochemistry, physiology, and health. Clinical Biochemistry 17(2):132-42. — PubMed PMID: 6428773
- Cumming RG, Mitchell P, Smith W (2000). Diet and cataract: the Blue Mountains Eye Study. Ophthalmology 107(3):450-6. — PubMed PMID: 10711880
- Leske MC, Chylack LT Jr, Wu SY (1991). The Lens Opacities Case-Control Study. Risk factors for cataract. Archives of Ophthalmology 109(2):244-51. — PubMed PMID: 1993036
- Wollensak G, Spoerl E, Seiler T (2003). Riboflavin/ultraviolet-a-induced collagen crosslinking for the treatment of keratoconus. American Journal of Ophthalmology 135(5):620-7. — PubMed PMID: 12719068
- Kumar P, Liu C, Hsu JW, Chacko S, Minard C, Jahoor F, Sekhar RV (2021). Glycine and N-acetylcysteine (GlyNAC) supplementation in older adults improves glutathione deficiency, oxidative stress, mitochondrial dysfunction, inflammation, insulin resistance, endothelial dysfunction, genotoxicity, muscle strength, and cognition: Results of a pilot clinical trial. Clinical and Translational Medicine 11(3):e372. — PubMed PMID: 33783984
- Kumar P, Liu C, Suliburk J, Hsu JW, Muthupillai R, Jahoor F, Minard CG, Taffet GE, Sekhar RV (2023). Supplementing Glycine and N-Acetylcysteine (GlyNAC) in Older Adults Improves Glutathione Deficiency, Oxidative Stress, Mitochondrial Dysfunction, Inflammation, Physical Function, and Aging Hallmarks: A Randomized Clinical Trial. Journals of Gerontology Series A 78(1):75-89. — PubMed PMID: 35975308
- Powers HJ, Hill MH, Mushtaq S, Dainty JR, Majsak-Newman G, Williams EA (2011). Correcting a marginal riboflavin deficiency improves hematologic status in young women in the United Kingdom (RIBOFEM). American Journal of Clinical Nutrition 93(6):1274-84. — PubMed PMID: 21525198
- Ashoori M & Saedisomeolia A (2014). Riboflavin (vitamin B&sub2;) and oxidative stress: a review. British Journal of Nutrition. — PubMed PMID: 24650639
- Beutler E (1969). Effect of flavin compounds on glutathione reductase activity: in vivo and in vitro studies. Journal of Clinical Investigation. — PubMed PMID: 5822598
- McAnena L, Ward M, McCann A et al. (2026). Riboflavin Deficiency Is Highly Prevalent in Females and Children across High and Low/Middle Income Countries Worldwide. Journal of Nutrition 156(3):101277. — PubMed PMID: 41735095
- EFSA Panel on Dietetic Products, Nutrition and Allergies (NDA); Turck D, Bresson JL, Burlingame B et al. (2017). Dietary Reference Values for riboflavin. EFSA Journal 15(8):e04919. — PubMed PMID: 32625611
- Glaser TS, Doss LE, Shih G et al.; Age-Related Eye Disease Study Research Group (2015). The Association of Dietary Lutein plus Zeaxanthin and B Vitamins with Cataracts in the Age-Related Eye Disease Study: AREDS Report No. 37. Ophthalmology 122(7):1471-9. — PubMed PMID: 25972257
- Zempleni J, Galloway JR, McCormick DB (1996). Pharmacokinetics of orally and intravenously administered riboflavin in healthy humans. American Journal of Clinical Nutrition 63(1):54-66. — PubMed PMID: 8604671
- Lopez-Mirabal HR & Winther JR (2008). Redox characteristics of the eukaryotic cytosol. Biochim Biophys Acta. — PubMed PMID: 18039473
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B2 Overview
- B2 Benefits Hub
- B2 for Migraine Prevention
- B2 Mitochondrial Cofactor
- B2 for Methylenetetrahydrofolate Reductase & Methylation
- Glutathione (Hub)
- GlyNAC Protocol for Aging
- Glutathione Liver Detoxification
- N-Acetylcysteine
- Glutathione (Pathway)
- N-Acetylcysteine as Glutathione Precursor
- Glycine
- Selenium
- Sulfur
- Alpha Lipoic Acid
- Oxidative Stress
- Liver Cleansing
- Anemia
- Vitamin C
- Vitamin E
- Deficiency
- Toxicity
- History
- Sources