Riboflavin (Vitamin B2) for Methylenetetrahydrofolate Reductase (MTHFR) & Methylation
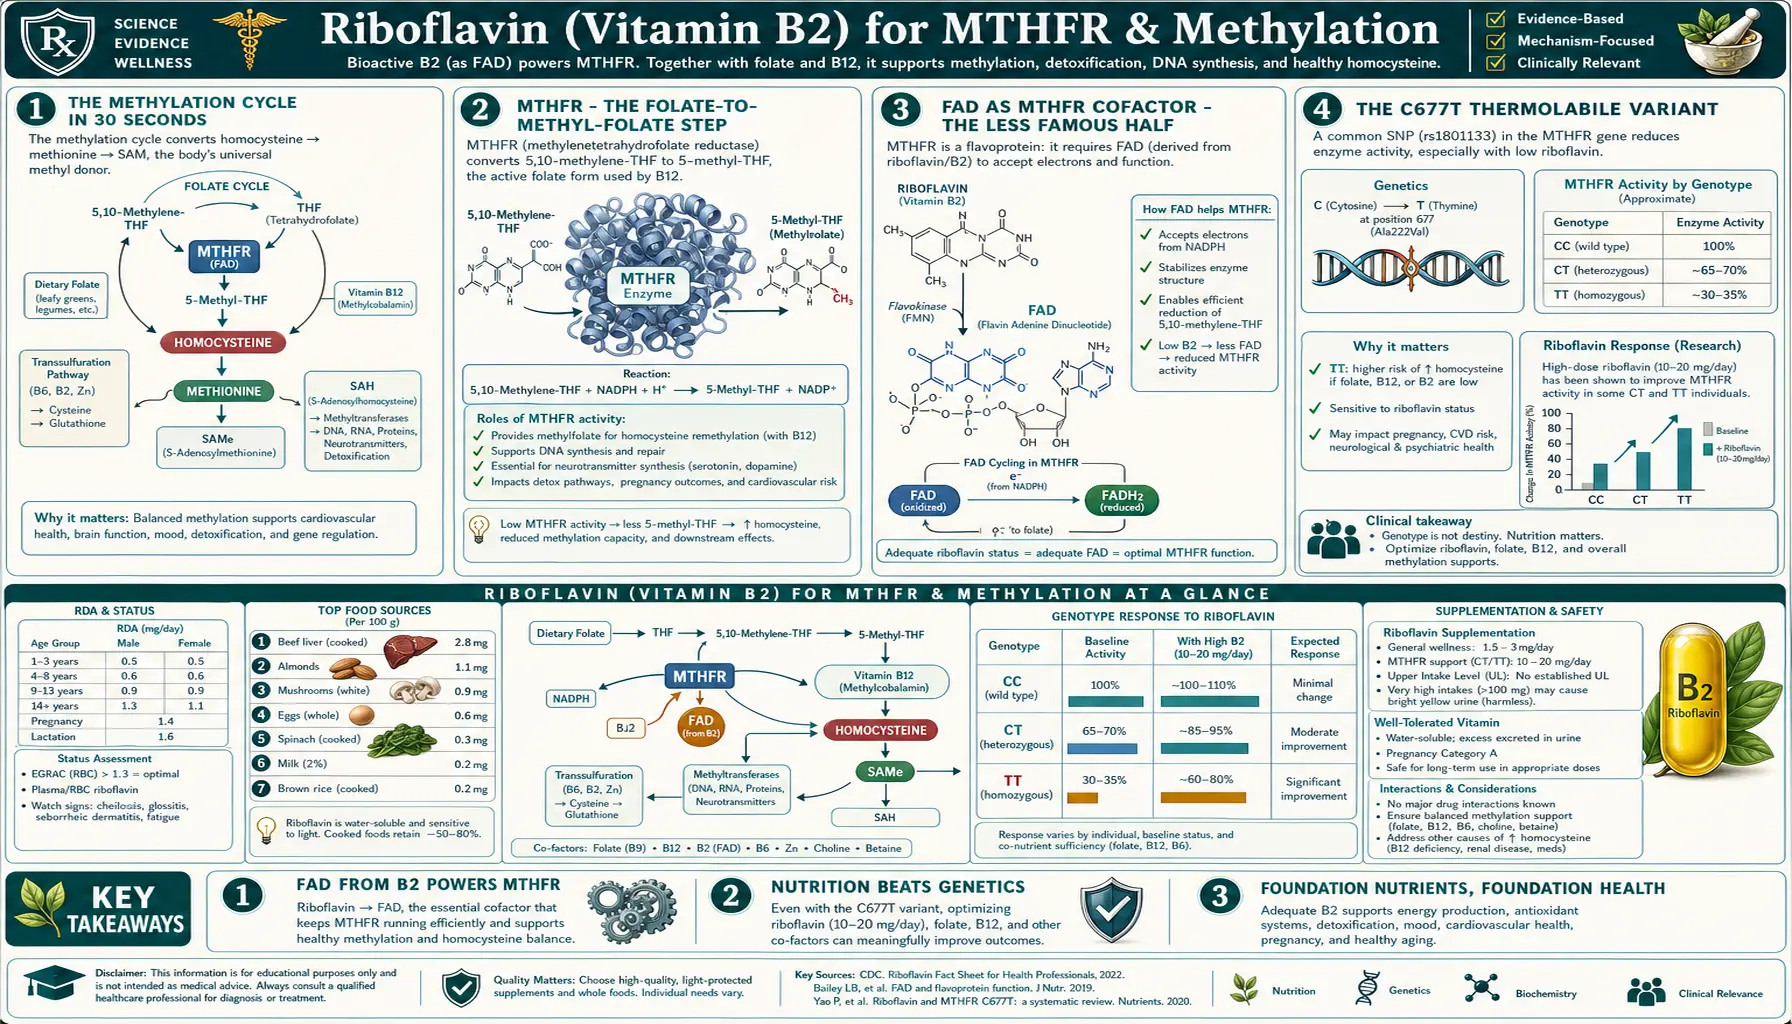
When people talk about methylenetetrahydrofolate reductase (MTHFR), they almost always talk about folate — the substrate that the enzyme acts on. The substrate matters, but the cofactor matters too, and it gets far less attention. Methylenetetrahydrofolate reductase (MTHFR) is a FAD-flavoprotein that requires riboflavin to function. In carriers of the common C677T thermolabile variant, the mutant enzyme has weaker FAD binding affinity and is unusually sensitive to riboflavin status. The McNulty, Wilson, Horigan, and Strain trials at Ulster University showed that B2 supplementation lowers homocysteine and blood pressure specifically in 677TT homozygotes — even in patients with adequate folate intake. The point for carriers of the methylenetetrahydrofolate reductase C677T variant: methylfolate alone is incomplete — riboflavin is the under-appreciated second cofactor and may be the rate-limiting nutrient.
Table of Contents
- The Methylation Cycle in 30 Seconds
- Methylenetetrahydrofolate Reductase — the Folate-to-Methyl-Folate Step
- FAD as Methylenetetrahydrofolate Reductase Cofactor — the Less Famous Half
- The C677T Thermolabile Variant
- Why C677T Mutants Are Riboflavin-Sensitive
- McNulty 2006 — the Homocysteine Randomized Controlled Trial
- Wilson, Horigan, and Strain — the Blood Pressure Trials
- Cardiovascular Implications of B2-MTHFR Optimization
- Bonaa NORVIT and the "Did Lowering Homocysteine Help?" Debate
- The Complete Methylation Stack
- Testing — Homocysteine, Methylenetetrahydrofolate Reductase Genotype, B2 Status
- Protocols Practitioners Describe
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Methylation Cycle in 30 Seconds
Methylation is the addition of a methyl group (–CH3) to a molecule. In the body, methylation is involved in:
- DNA methylation (gene expression regulation, epigenetics)
- Neurotransmitter synthesis (serotonin, dopamine, norepinephrine, epinephrine, melatonin)
- Phospholipid synthesis (phosphatidylcholine for cell membranes and bile)
- Creatine synthesis (skeletal muscle energy)
- Detoxification (catechol-O-methyltransferase, COMT, breaks down catecholamines and estrogens)
- Homocysteine remethylation (clearing this potentially toxic intermediate)
The universal methyl donor is S-adenosylmethionine (SAMe). After donating its methyl group, S-adenosylmethionine becomes S-adenosylhomocysteine (SAH), which is hydrolyzed to homocysteine.
Homocysteine has two fates:
- Remethylation back to methionine, which then makes more S-adenosylmethionine — the cycle continues. The methyl group comes from 5-methyl-tetrahydrofolate (5-methyl-THF) via methionine synthase (B12-dependent).
- Trans-sulfuration to cysteine, which then makes taurine, sulfate, and glutathione — the "exit" from the methylation cycle into sulfur metabolism. Requires vitamin B6.
The remethylation arm of this cycle depends on a steady supply of 5-methyl-THF. That supply is generated by methylenetetrahydrofolate reductase.
Methylenetetrahydrofolate Reductase — the Folate-to-Methyl-Folate Step
Methylenetetrahydrofolate reductase (MTHFR; gene MTHFR) reduces 5,10-methylene-tetrahydrofolate to 5-methyl-tetrahydrofolate. The methyl group on the resulting 5-methyl-THF is what eventually gets donated to homocysteine.
The reaction:
5,10-methylene-THF + NADPH → 5-methyl-THF + NADP+
(catalyzed by MTHFR, FAD-flavoprotein)
This is the committed step that diverts folate flux out of nucleotide synthesis (which needs the methylene form) and into the methylation cycle (which needs the methyl form). It is the one-way decision point in folate metabolism.
Because the reaction is essentially irreversible under cellular conditions, methylenetetrahydrofolate reductase activity sets the rate of methyl-folate production. Inadequate methylenetetrahydrofolate reductase activity means inadequate 5-methyl-THF, which means inadequate methyl donation to homocysteine, which means homocysteine accumulates in the blood — the classic biochemical signature of methylenetetrahydrofolate reductase dysfunction.
The standard supplement-industry response is to bypass the methylenetetrahydrofolate reductase step by giving preformed methylfolate (L-5-MTHF, sold as methylfolate under several trade names). This works, but it doesn't address why methylenetetrahydrofolate reductase is underperforming in the first place. In methylenetetrahydrofolate reductase C677T carriers, the answer is often inadequate riboflavin.
FAD as Methylenetetrahydrofolate Reductase Cofactor — the Less Famous Half
Methylenetetrahydrofolate reductase is a flavoprotein. Each subunit of the functional homodimer binds one FAD molecule, non-covalently but tightly. The reaction mechanism:
- Reduced nicotinamide adenine dinucleotide phosphate (NADPH) docks at the enzyme's reduced nicotinamide adenine dinucleotide phosphate-binding site and transfers a hydride to FAD, reducing it to FADH2
- FADH2 then transfers its electrons (effectively a hydride) to 5,10-methylene-THF, reducing it to 5-methyl-THF
- The oxidized FAD is regenerated, ready for another cycle
Without FAD bound, methylenetetrahydrofolate reductase is catalytically inert. In riboflavin deficiency, newly synthesized methylenetetrahydrofolate reductase protein exists in the cell as apoenzyme (without FAD), unable to convert methylene-THF to methyl-THF, and is gradually degraded.
The clinical relevance is greatest in methylenetetrahydrofolate reductase C677T carriers, where the mutant enzyme has reduced FAD-binding affinity (see the next section). In wild-type (677CC) individuals, methylenetetrahydrofolate reductase holds onto FAD tightly enough that ordinary dietary B2 intake is enough. In 677TT homozygotes, FAD dissociates from the mutant enzyme more readily, and the cell needs an elevated FAD pool (i.e., higher riboflavin intake) to keep methylenetetrahydrofolate reductase adequately loaded.
This is why the methylenetetrahydrofolate reductase conversation that focuses only on folate is incomplete. Folate is the substrate. FAD is the cofactor. Both must be present.
The C677T Thermolabile Variant
The methylenetetrahydrofolate reductase C677T variant (rs1801133) is a single nucleotide polymorphism that changes a cytosine to a thymine at position 677 of the MTHFR gene. The protein-level consequence: an alanine at residue 222 becomes a valine (A222V). This valine substitution destabilizes the FAD-binding domain of the enzyme.
The variant is extremely common. The population figures below are reported ranges, and they vary between studies:
- Worldwide allele frequency: Frosst 1995 found the substitution on approximately 38% of unselected chromosomes; reported ranges are 25-30% in Europeans, 30-35% in Hispanics, 10-15% in Sub-Saharan Africans, 35-45% in some East Asian and Italian populations
- 677TT homozygotes (two copies): 10-15% of Europeans, 20-25% of Hispanics, 1-3% of Sub-Saharan Africans
- 677CT heterozygotes (one copy): 40-45% of Europeans — the most common single genotype
Kang and colleagues described the variant enzyme in 1988 and called it "thermolabile" because it loses much more of its activity than the normal enzyme when heated to 46°C for five minutes in the laboratory; Frosst 1995 identified the C677T mutation behind it and confirmed its effect on thermolability. The heat sensitivity reflects reduced thermal stability of the FAD-binding domain. The same destabilization causes the FAD to dissociate more easily under physiological conditions.
The clinical phenotype of 677TT homozygotes:
- Approximately 30% of wild-type methylenetetrahydrofolate reductase activity at body temperature
- Elevated plasma homocysteine, particularly under conditions of marginal folate or riboflavin intake
- Increased risk of certain pregnancy complications (neural tube defects, recurrent pregnancy loss, placental abruption) when folate intake is inadequate
- Slightly increased risk of certain cardiovascular and stroke outcomes in some (not all) epidemiology studies
- In riboflavin-replete populations, the phenotype is largely silent — explaining why the variant has persisted at high allele frequencies
The widespread industrial folate fortification of grain products (mandatory in the US since 1998) has substantially blunted the population-level impact of C677T on neural tube defect rates. But the variant's effect on homocysteine and methylation is not fully neutralized by folate alone — particularly in the presence of marginal riboflavin status.
Why C677T Mutants Are Riboflavin-Sensitive
The Yamada 2001 paper provided the structural-biochemical proof. Recombinant 677TT mutant methylenetetrahydrofolate reductase was purified and characterized:
- The mutant enzyme binds FAD with substantially lower affinity than wild type
- FAD dissociates from the mutant enzyme far more rapidly under physiological conditions
- Adding excess FAD to the in vitro reaction restores activity of the mutant enzyme toward wild-type levels
- The phenotype is rescuable in vitro by increasing FAD concentration
The translation to in vivo physiology: a 677TT homozygote whose cellular FAD pool is at the low end of the normal range will have mutant methylenetetrahydrofolate reductase predominantly in the apoenzyme (FAD-free) state — functionally deficient. The same person with a higher cellular FAD pool (achieved by adequate dietary riboflavin or supplementation) will have mutant methylenetetrahydrofolate reductase predominantly loaded with FAD — functionally restored toward normal.
This is why riboflavin supplementation in 677TT homozygotes lowers homocysteine (which depends on methylenetetrahydrofolate reductase-generated methyl-folate for remethylation). It is also why the effect is small or absent in 677CC wild-type individuals, who don't have a destabilized FAD-binding domain to rescue.
The fundamental insight: the C677T mutation is, biochemically, a riboflavin-dependent gain of vitamin requirement. The variant person needs more B2 than the wild-type person to make the same amount of methyl-folate. Identifying the variant via genetic testing is one way to identify who benefits most from B2 supplementation.
McNulty 2006 — the Homocysteine Randomized Controlled Trial
McNulty et al. (2006, Circulation) published the pivotal randomized trial that established B2 as a homocysteine-lowering nutrient specifically in 677TT homozygotes. The design:
- 89 adults stratified by methylenetetrahydrofolate reductase C677T genotype (35 TT, 26 CT, 28 CC)
- Randomized to riboflavin 1.6 mg/day or placebo for 12 weeks
- Primary outcome: plasma homocysteine
- Folate, vitamin B6, and vitamin B12 intakes were adequate and were controlled across groups
Results were striking:
- In 677TT homozygotes, plasma homocysteine fell by approximately 22% in the riboflavin group, with no change on placebo
- In 677CT heterozygotes, no significant homocysteine reduction was observed
- In 677CC wild-types, no homocysteine reduction
- The effect was specific to the 677TT genotype and was achieved at a remarkably low dose (1.6 mg/day — within the dietary range, not the megadose territory)
This trial established three things:
- Riboflavin lowers homocysteine in 677TT homozygotes
- The effect is genotype-specific — the under-the-radar mechanism most homocysteine-lowering trials miss because they don't stratify by methylenetetrahydrofolate reductase genotype
- Modest doses (1.6 mg/day) are sufficient — this is achievable with dietary improvement plus a B-complex; mega-doses are not required
Wilson, Horigan, and Strain — the Blood Pressure Trials
The same Ulster University group (under McNulty, Scott, Strain) extended the homocysteine work to blood pressure. The logic: 677TT homozygotes have well-documented increased blood pressure risk and increased risk of stroke. If riboflavin restores methylenetetrahydrofolate reductase function in these patients, blood pressure should fall.
Horigan et al. (2010, Journal of Hypertension) — 197 premature cardiovascular disease patients selected by methylenetetrahydrofolate reductase genotype, 181 of whom completed 16 weeks of riboflavin 1.6 mg/day or placebo. In the 677TT group, riboflavin lowered mean blood pressure from 144/87 to 131/80 mmHg. In the CC and heterozygous (CT) groups, no response was observed.
Wilson et al. (2013, Hypertension) — 91 people with treated hypertension and the methylenetetrahydrofolate reductase 677TT genotype (without overt cardiovascular disease), given riboflavin 1.6 mg/day or placebo for 16 weeks. Riboflavin produced an overall treatment effect of 5.6 mmHg in systolic blood pressure (BP); the effect on diastolic BP was not significant. Critically, this was on top of existing antihypertensive treatment — the authors conclude that riboflavin targeted at this genotype can lower BP more effectively than antihypertensive drugs alone.
Wilson et al. (2012, American Journal of Clinical Nutrition) — a 4-year follow-up: 83 patients (all three genotypes) from the group's 2004 placebo-controlled trial took part again, and those with the 677TT genotype (31) received a second 16-week course of riboflavin 1.6 mg/day or placebo, with the 2004 groups reversed. At follow-up their blood pressure was unchanged from 4 years earlier despite major changes in antihypertensive therapy. Across the 2004 and 2008 courses, riboflavin produced an overall fall of 9.2 mmHg systolic and 6.0 mmHg diastolic.
The cumulative finding: in methylenetetrahydrofolate reductase C677T homozygotes (10-15% of the European population, more in some other ethnicities), riboflavin 1.6 mg/day reduced systolic blood pressure by about 5.6-13 mmHg across these trials (the group's 2016 review in the Proceedings of the Nutrition Society puts it at 5-13 mmHg). This is a clinically meaningful blood pressure reduction comparable in magnitude to single-agent antihypertensive therapy — achieved with a tiny dose of a vitamin, with no side effects, in a specific genotype subgroup that is easy to identify.
The researchers propose riboflavin, targeted at people with the 677TT genotype, as a low-cost, personalized approach to managing high blood pressure in this genetically at-risk group, and note that the findings still need confirming in the general population. This is one of the cleanest examples of pharmacogenomic-style personalization with a non-pharmaceutical intervention.
Cardiovascular Implications of B2-MTHFR Optimization
Elevated homocysteine is an independent risk factor for cardiovascular disease, stroke, peripheral artery disease, deep vein thrombosis, and dementia. The mechanisms include:
- Endothelial dysfunction (reduced nitric oxide bioavailability, increased oxidative stress)
- Vascular smooth muscle proliferation
- Increased thrombogenicity (platelet activation, decreased thrombomodulin)
- Disruption of methylation status of vascular regulatory genes
- Increased oxidative stress through disrupted glutathione pathways
In the methylenetetrahydrofolate reductase 677TT subset, homocysteine elevation is consistently observed when nutritional methylation cofactors are marginal. Riboflavin supplementation in this subset lowers homocysteine and produces a measurable blood pressure reduction. Whether this translates to fewer hard cardiovascular endpoints (heart attacks, strokes, deaths) at a population level requires longer-duration trials, but the mechanistic chain is plausible and the intermediate-endpoint evidence is robust.
The clinical practice that has emerged in cardiology integrative practice: in any patient with premature cardiovascular disease, recurrent thrombosis, unexplained hypertension, or a strong family history, check methylenetetrahydrofolate reductase genotype and homocysteine, and treat 677TT homozygotes with riboflavin 25-100 mg/day plus methylfolate 400-1000 mcg/day plus methylcobalamin 1000 mcg/day. The combination is inexpensive, safe, and addresses the specific upstream metabolic defect.
Bonaa NORVIT and the "Did Lowering Homocysteine Help?" Debate
Several large randomized controlled trials (RCTs) in the 2000s tested whether homocysteine reduction with folic acid + B12 + B6 reduces cardiovascular events in the general population:
- NORVIT (Bonaa 2006) — 3749 post-MI patients, folic acid 0.8 mg + B12 0.4 mg + B6 40 mg vs placebo. Homocysteine fell 27% in the active group. No reduction in primary cardiovascular endpoint over 40 months; in fact, a trend toward increased events in the most aggressive treatment arm.
- HOPE-2 (Lonn 2006) — 5522 high-risk patients, folic acid 2.5 mg + B6 50 mg + B12 1 mg vs placebo. Homocysteine fell, no reduction in primary endpoint.
- VISP (Toole 2004) — 3680 stroke patients. High-dose B vitamins vs low-dose. Homocysteine fell, no reduction in recurrent stroke.
The disappointing results led many clinicians to conclude that "lowering homocysteine doesn't help." That conclusion is too sweeping. Critiques:
- None of the trials stratified by methylenetetrahydrofolate reductase genotype. The 10-15% of patients who would benefit most (677TT homozygotes with the riboflavin-sensitive enzyme) were diluted into a population where methylenetetrahydrofolate reductase is fine. The genotype-stratified McNulty/Wilson/Horigan trials show specific 677TT benefit that gets washed out in unstratified pooled analyses.
- None of the trials tested riboflavin. NORVIT and HOPE-2 gave folic acid + B6 + B12 with no riboflavin, so in those trials the B2-MTHFR cofactor failure was left uncorrected, and methyl-folate generation in 677TT patients may have remained inefficient even on high-dose folic acid. In VISP, every participant in both arms also received a daily multivitamin containing the FDA reference daily intakes of other vitamins — riboflavin included, at the reference level — so riboflavin was not what that trial compared.
- Synthetic folic acid (the form used in these trials) may have unintended effects — including building up unmetabolized folic acid that interferes with methylfolate transport. Modern thinking prefers methylfolate (5-MTHF) over folic acid.
- The age of intervention may matter — treating after a cardiovascular event may be too late; lifelong methylation optimization starting decades earlier may have different effects.
The takeaway for B2-MTHFR optimization: the population-wide "just lower homocysteine" strategy disappointed because it was genotype-blind and riboflavin-light. The targeted strategy — identify 677TT homozygotes, give them adequate riboflavin alongside methylfolate, B12, and B6 — addresses a specific metabolic deficit and shows measurable physiological benefit in the relevant subgroup. Whether that translates to hard endpoints in long-term genotype-stratified trials remains an open question; the mechanism and intermediate endpoints argue it should.
The Complete Methylation Stack
Practitioners who work with methylenetetrahydrofolate reductase C677T carriers describe supporting all of the methylation cycle's cofactors and substrates, typically at these doses:
- Methylfolate (L-5-MTHF) 400-1000 mcg/day — preformed methyl-folate that bypasses the methylenetetrahydrofolate reductase step
- Methylcobalamin (B12) 500-1000 mcg/day — cofactor for methionine synthase (the enzyme that uses 5-methyl-THF to remethylate homocysteine)
- Pyridoxal-5′-phosphate (active B6) 25-100 mg/day — cofactor for the trans-sulfuration arm (CBS) that diverts homocysteine to cysteine
- Riboflavin (B2) 25-100 mg/day — cofactor for methylenetetrahydrofolate reductase (the under-appreciated piece). Higher doses in 677TT homozygotes (50-100 mg) and during initial repletion.
- Trimethylglycine (betaine, TMG) 500-3000 mg/day — alternative methyl donor for homocysteine via the BHMT pathway; complementary to the folate-dependent route
- Zinc 15-30 mg/day — cofactor for betaine-homocysteine methyltransferase and methionine adenosyltransferase
- Choline 500-1000 mg/day — precursor to betaine (TMG); also addresses phosphatidylcholine synthesis demands of the methylation cycle
A methylation B-complex supplies folate, B12, B6, and B2 in active forms; practitioners add TMG, choline, and zinc separately for fuller support, on the reasoning that missing any one component creates a bottleneck.
Practitioners describe a common over-supplementation pattern: starting on high-dose methylfolate alone (e.g., 5-15 mg/day) without B2, B12, or B6. They report "over-methylation" symptoms (anxiety, insomnia, agitation) in some sensitive individuals, which they attribute to the methylation cycle being pushed without adequate downstream capacity, and report that layered, balanced supplementation with all the cofactors prevents these effects.
Testing — Homocysteine, Methylenetetrahydrofolate Reductase Genotype, B2 Status
- Plasma total homocysteine (tHcy) — the single best functional marker of methylation cycle status. Normal < 7 µmol/L; intermediate 7-15; elevated > 15. Most labs offer this routinely.
- Methylenetetrahydrofolate reductase C677T and A1298C genotype — one-time test; shows whether a person carries the riboflavin-sensitive variants. Available through commercial genetic services, direct-to-consumer genetic-testing companies (some in their raw-data panels), or large commercial clinical laboratories on a clinician's order.
- EGRAC (erythrocyte glutathione reductase activity coefficient) — gold-standard functional B2 status marker; specialty reference labs only. Most clinicians use clinical and intake-history assessment instead.
- Plasma B12 + methylmalonic acid + folate + B6 — round out the methylation-cofactor status panel
- Yellow urine within 24-48 hours of starting riboflavin — cheapest home marker confirming B2 absorption
The minimum useful testing battery for someone investigating methylenetetrahydrofolate reductase-related methylation:
- Methylenetetrahydrofolate reductase C677T + A1298C genotype (one-time)
- Plasma homocysteine at baseline and 3-6 months after intervention
- Optional: full methylation-cofactor panel (folate, B12, B6, methylmalonic acid (MMA), holotranscobalamin)
Protocols Practitioners Describe
The doses below are the ones described in integrative practice. They are higher than the riboflavin 1.6 mg/day used in the Ulster trials described above, which tested riboflavin alone.
For Methylenetetrahydrofolate Reductase C677T homozygotes (677TT)
- Riboflavin 25-50 mg/day (or 100 mg/day during initial repletion for 3 months, then drop to maintenance) — addresses the genotype-specific cofactor weakness
- L-5-MTHF (methylfolate) 400-1000 mcg/day — bypasses the methylenetetrahydrofolate reductase step
- Methylcobalamin 500-1000 mcg/day — methionine synthase cofactor
- P-5-P (pyridoxal-5′-phosphate) 25-50 mg/day — CBS cofactor for the trans-sulfuration exit
- Homocysteine is rechecked at 3 months, with a target below 7 µmol/L
- Described as continued indefinitely; practitioners report that the benefits reverse when it is stopped
For Methylenetetrahydrofolate Reductase C677T heterozygotes (677CT)
- Lower-priority intervention; baseline genotype has 65% of wild-type activity
- The focus is adequate dietary B2, methylfolate, B12, B6
- If homocysteine is elevated, the 677TT approach is used
For Methylenetetrahydrofolate Reductase wild-type (677CC)
- No special methylenetetrahydrofolate reductase-related riboflavin need; standard B-complex coverage is fine
- Homocysteine that stays elevated despite this points to other contributors: B12 deficiency, B6 deficiency, hypothyroidism, kidney dysfunction, or others
For unknown Methylenetetrahydrofolate Reductase genotype with elevated homocysteine
- Empirical methylation B-complex (with methylated forms) often resolves the issue regardless of genotype
- If the response is incomplete, a methylenetetrahydrofolate reductase genotype test informs personalized dosing
Cautions
- The genotype is not the whole picture — a methylenetetrahydrofolate reductase C677T homozygote with normal homocysteine and no symptoms does not necessarily need aggressive supplementation. The variant is common, mostly silent, and not deterministic. Functional markers (homocysteine, clinical phenotype) guide treatment.
- Methylfolate sensitivity — practitioners report that a minority of patients (they estimate 5-10%) develop anxiety, insomnia, or agitation when starting methylfolate, even at low doses. They describe starting low (200-400 mcg/day) and increasing gradually, and report that adequate B2, B12, B6, and TMG prevent most over-methylation symptoms.
- The trials did not use megadoses — the McNulty trial lowered homocysteine with 1.6 mg/day. Practitioners describe 25-100 mg/day; 400 mg/day is the dose used in migraine trials, not in the methylenetetrahydrofolate reductase trials.
- Consumer genetic reports — raw genome data from consumer genetic-testing services is easily misread, and clinical-laboratory genotyping is the usual way such a finding is confirmed.
- Pregnancy — methylenetetrahydrofolate reductase optimization is particularly important before and during pregnancy (neural tube defect prevention, recurrent pregnancy loss). The Institute of Medicine (1998) sets the folate RDA in pregnancy at 600 µg a day of dietary folate equivalents; to reduce the risk of neural tube defects, its recommendation is that women capable of becoming pregnant take 400 µg of folic acid daily from fortified foods, supplements, or both, in addition to food folate from a varied diet. Its upper limit for folate from fortified foods or supplements is 1,000 µg a day from age 19 (800 µg at 14-18), in pregnancy as well.
- Riboflavin was added to blood-pressure medicines, not swapped for them — in the Horigan and Wilson trials most or all participants stayed on their antihypertensive drugs, with riboflavin added on top; none of the trials tested stopping those drugs.
- Riboflavin is light-sensitive and its absorption is saturable — which is why it is sold in opaque bottles, and why larger doses are usually divided and taken with food
Key Research Papers
- McNulty H et al. (2006). Riboflavin lowers homocysteine in individuals homozygous for the MTHFR 677C→T polymorphism. Circulation. — PubMed PMID: 16380544
- Horigan G et al. (2010). Riboflavin lowers blood pressure in cardiovascular disease patients homozygous for the 677C→T polymorphism in MTHFR. Journal of Hypertension. — PubMed PMID: 19952781
- Wilson CP et al. (2013). Blood pressure in treated hypertensive individuals with the MTHFR 677TT genotype is responsive to intervention with riboflavin: findings of a targeted randomized trial. Hypertension. — PubMed PMID: 23608654
- Wilson CP et al. (2012). Riboflavin offers a targeted strategy for managing hypertension in patients with the MTHFR 677TT genotype: a 4-y follow-up. American Journal of Clinical Nutrition. — PubMed PMID: 22277556
- McAuley E et al. (2016). Riboflavin status, MTHFR genotype and blood pressure: current evidence and implications for personalised nutrition. Proceedings of the Nutrition Society. — PubMed PMID: 27170501
- Yamada K et al. (2001). Effects of common polymorphisms on the properties of recombinant human MTHFR (FAD-binding affinity of C677T mutant). Proc Natl Acad Sci USA. — PubMed
- Frosst P et al. (1995). A candidate genetic risk factor for vascular disease: a common mutation in methylenetetrahydrofolate reductase. Nature Genetics. — PubMed PMID: 7647779
- Kang SS et al. (1988). Intermediate homocysteinemia: a thermolabile variant of methylenetetrahydrofolate reductase. American Journal of Human Genetics. — PubMed PMID: 3177384
- Hustad S et al. (2000). Riboflavin as a determinant of plasma total homocysteine: effect modification by the methylenetetrahydrofolate reductase C677T polymorphism. Clinical Chemistry. — PubMed
- Bonaa KH et al. (2006). Homocysteine lowering and cardiovascular events after acute myocardial infarction (NORVIT). New England Journal of Medicine. — PubMed PMID: 16531614
- Lonn E et al. (2006). Homocysteine lowering with folic acid and B vitamins in vascular disease (HOPE-2). New England Journal of Medicine. — Search PubMed
- Powers HJ (2005). Interaction among folate, riboflavin, genotype, and cancer, with reference to colorectal and cervical cancer. Journal of Nutrition. — PubMed PMID: 16317155
- Moat SJ et al. (2003). Effect of riboflavin status on the homocysteine-lowering effect of folate in relation to the MTHFR C677T genotype. Clinical Chemistry. — PubMed PMID: 12560354
- Jacques PF et al. (2002). The relationship between riboflavin and plasma total homocysteine in the Framingham Offspring cohort is influenced by folate status and the C677T transition in the methylenetetrahydrofolate reductase gene. Journal of Nutrition. — PubMed PMID: 11823591
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B2 Overview
- B2 Benefits Hub
- B2 for Migraine Prevention
- B2 Mitochondrial Cofactor
- B2 Glutathione Reductase Cofactor
- Vitamin B9 (Folate)
- Folate Methylation & Homocysteine
- Folate Cardiovascular & Stroke
- Vitamin B12 (Cobalamin)
- Vitamin B6 (Pyridoxine)
- Homocysteine
- Glutathione
- Sulfur & Trans-Sulfuration
- Zinc
- Hypertension
- Riboflavin and Energy Production
- Riboflavin and Migraine Prevention
- Deficiency
- Toxicity
- History
- Sources