⚠ Evidence warning: Clinical trials or other evidence do not support the claim that the missing upper limit for riboflavin is a positive finding of safety built on decades of use. This page keeps it as a report of what people, websites or other media say.
Riboflavin (Vitamin B2) Toxicity: What the Evidence Shows
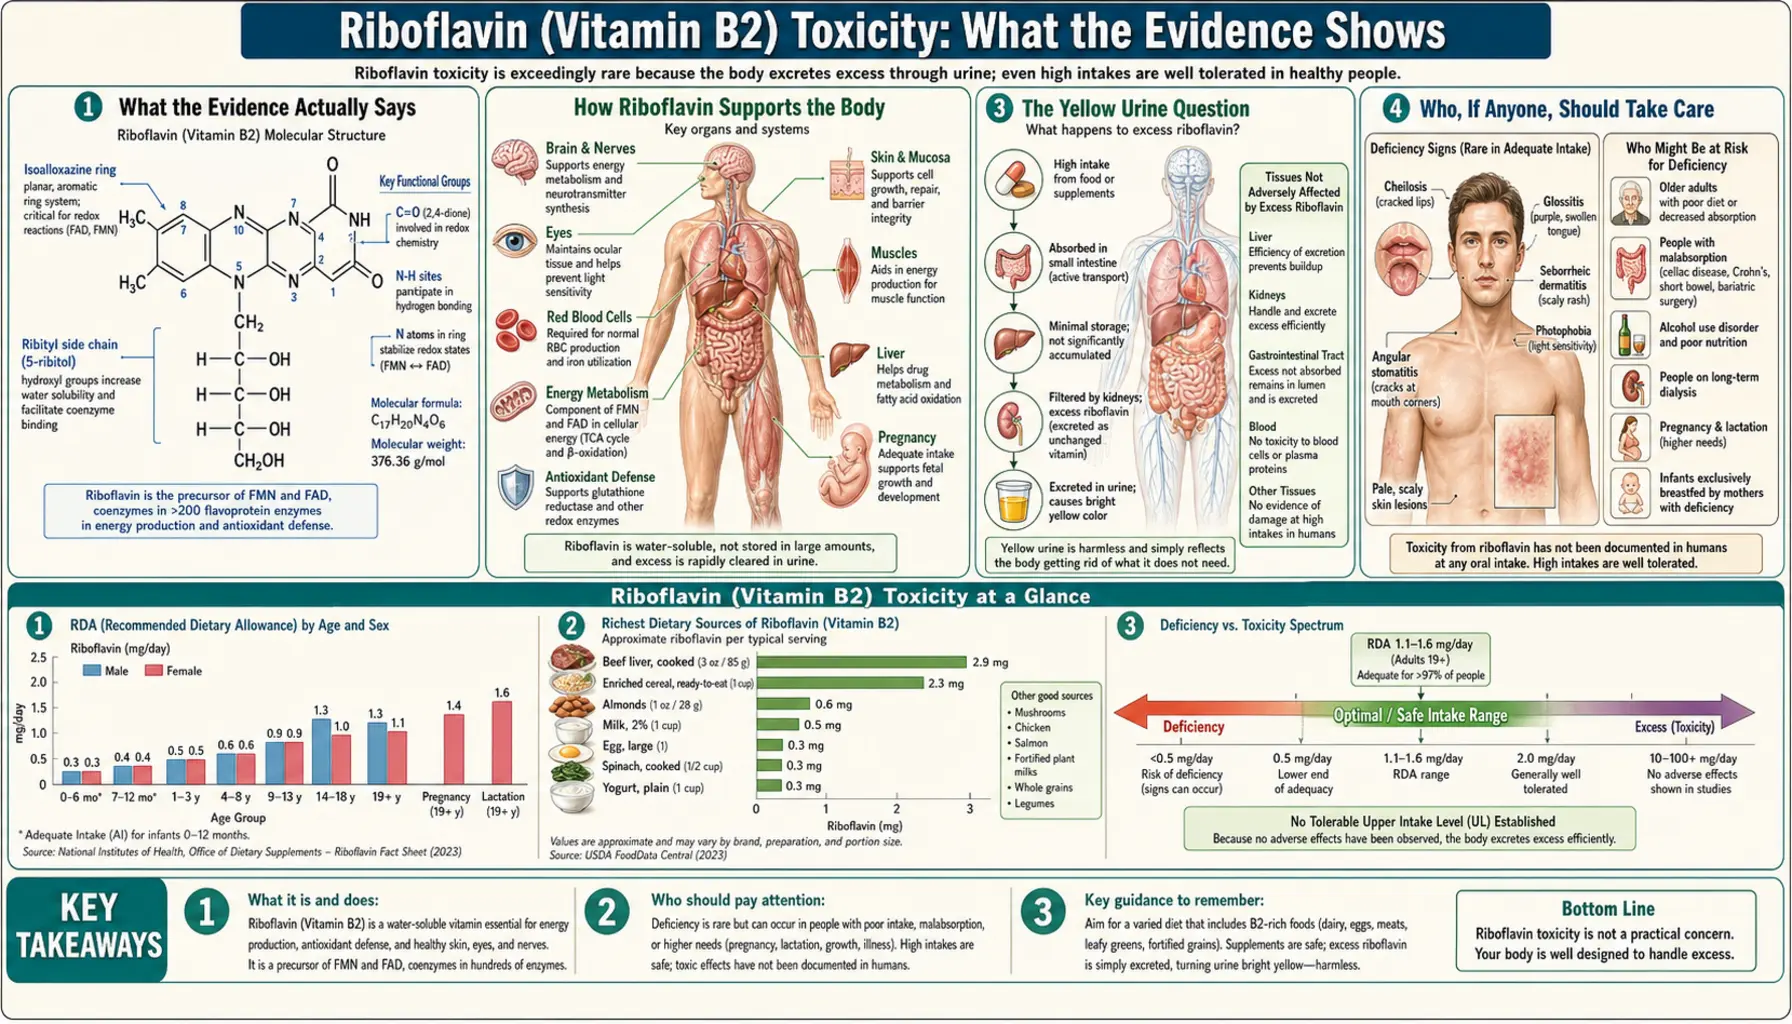
Here is the honest bottom line, stated up front: riboflavin (vitamin B2) has no recognized toxicity syndrome in humans. It is a water-soluble vitamin, your gut can only absorb so much at once, and your kidneys flush out whatever you don't use. There is no Tolerable Upper Intake Level for riboflavin — neither the U.S. Institute of Medicine (1998) nor the European Union’s Scientific Committee on Food (2000, a conclusion restated by the European Food Safety Authority in 2017) found enough evidence of harm on which to base one. The single visible effect of taking a large dose is harmless: your urine turns a bright, fluorescent yellow-green within hours (a sign called riboflavinuria), which simply means the excess left your body exactly as designed. You cannot overdose on riboflavin from food, and even the high-dose supplements used for migraine prevention (around 400 mg a day) are remarkably well tolerated. This page is deliberately short, because there is no toxicity syndrome to describe — only a few sensible caveats and one frequently-asked question about that startling yellow urine. If you are looking for a real B2-related problem, it is on the deficiency side, not here.
Table of Contents
What the Evidence Actually Says
It is worth being candid, because the internet is full of "too much of any vitamin is dangerous" warnings that simply do not apply here. Riboflavin is one of the safest substances in the entire nutrition cabinet. When the U.S. Institute of Medicine (now part of the National Academies) set Dietary Reference Intakes for the B vitamins, it reviewed the human and animal evidence and found that no adverse effects from riboflavin in food or supplements had been reported, but that the data on adverse effects were not sufficient for a quantitative risk assessment. For that reason no Tolerable Upper Intake Level (UL) — the ceiling above which a nutrient is expected to cause harm — could be derived. In Europe, the Scientific Committee on Food (SCF) could not derive an upper level in 2000 because there was not sufficient clinical evidence of adverse effects from high intakes; the European Food Safety Authority’s 2017 Dietary Reference Values report restated that conclusion and noted that revising the upper level was outside its scope.
The Institute of Medicine was careful about what this means. Studies of large doses “have not been designed to systematically evaluate adverse effects,” and the report adds: “This does not mean that there is no potential for adverse effects resulting from high intakes. Because data on the adverse effects of riboflavin intake are limited, caution may be warranted.” What the record does show is long use without harm being reported. This is not the same as saying "we don't know." It is a positive finding built on decades of use. Riboflavin has been given to people in doses many times the recommended intake — in research studies, in high-dose supplements, and in the treatment of certain rare inherited metabolic disorders — without a recognized toxicity syndrome emerging. The clearest everyday example is migraine prevention, where a standard regimen is 400 mg of riboflavin per day. To put that in perspective, the recommended dietary allowance for an adult is only about 1.1–1.3 mg per day, so 400 mg is roughly 300 times the daily requirement. In the landmark randomized trial of this dose (Schoenen and colleagues, 1998), the high-dose group tolerated it well; the side effects that did occur were minor and uncommon. People have taken this dose for months at a time as a preventive.
So when this page says there is "no toxicity," it is reporting what the major scientific bodies found — no reported harm, and too little data to set a ceiling — not glossing over a hidden danger. The honest framing is this: no toxicity has been reported at any realistic dose, the only universal effect of an excess is bright urine, and the practical questions people actually have are about that urine, about a couple of niche interactions, and about not wasting money on megadoses the body cannot use.
Why Riboflavin Is So Hard to Overdo
The reason riboflavin is so safe is not luck — it is built into how the body handles it. Three mechanisms work together to make an overdose almost impossible.
1. Absorption is capped and saturable. Riboflavin is taken up from the small intestine by specific transport proteins, and like any doorway with a limited number of doors, those transporters can only let so much through at a time. Once they are saturated, extra riboflavin sitting in the gut simply cannot get in — it passes through and is lost in the stool. This means that even if you swallow a very large dose, the fraction your body actually absorbs falls as the dose rises. The absorptive system has a built-in ceiling; you cannot force-feed your bloodstream by taking more.
2. The tissues hold only a limited reserve. Inside cells, riboflavin is converted into its working forms — flavin mononucleotide (FMN) and flavin adenine dinucleotide (FAD) — the cofactors that let dozens of enzymes carry energy and electrons around (this is riboflavin's real job, explained on the Benefits hub). But the enzymes that make FMN and FAD are themselves tightly regulated, so the body converts only what it needs and stores essentially no large surplus. There is no "riboflavin fat" for excess to pile into and accumulate over time.
3. The kidneys excrete the surplus immediately. Whatever riboflavin is absorbed but not needed does not linger — it is filtered by the kidneys and sent out in the urine, often within hours. Because riboflavin is brightly colored (it is, after all, the pigment that gives the vitamin its name, from the Latin flavus, "yellow"), you can literally see this happening. This is the crucial contrast with the fat-soluble vitamins — A, D, E, and K — which the body stores in fat and the liver and which therefore can build up to toxic levels. Water-soluble vitamins like riboflavin do the opposite: they wash out. That single difference — stored versus flushed — is why fat-soluble vitamins have meaningful upper limits and riboflavin does not.
Put simply: you can only get so much in, you store almost none of it, and you pee out the rest. There is no step in that chain where a dangerous amount can quietly accumulate.
The Yellow Urine Question
By far the most common thing people notice after taking a B-complex or riboflavin supplement is that their urine turns a vivid, almost neon yellow — sometimes greenish under bright light. This understandably alarms people who have never seen it. It is completely harmless. The medical name is riboflavinuria, and it means exactly one thing: you took in more riboflavin than your body needed, and the surplus is leaving in your urine, carrying its natural yellow color with it.
A few details that tend to reassure people:
- It is the vitamin itself you are seeing. Riboflavin is naturally yellow and even fluorescent — under ultraviolet light a riboflavin solution glows green-yellow. The color in your urine is simply the unused vitamin made visible. It is a sign the system is working, not failing.
- It is dose-related and temporary. The brighter and more saturated the color, the more excess you took in. It typically appears within a few hours of a dose and fades as the surplus clears, usually by the next day if you stop. Many people on a daily B-complex see it every morning.
- It does not mean the supplement is "useless." A common myth is that yellow urine proves the vitamin "passed straight through" and was wasted. That is only partly true: your body absorbs what it needs first and excretes the genuine surplus. The color tells you that you exceeded your current requirement — which for a water-soluble vitamin is normal and expected — not that none was absorbed.
- It can be a useful clue elsewhere. Because riboflavin colors urine so reliably, it is occasionally used in research as a harmless marker to check whether someone is actually taking their pills (adherence). That is how predictable and benign the effect is.
One honesty note worth keeping: bright or unusual urine color has many causes, and not all of them are riboflavin. Beets, food dyes, certain medications (for example, the urinary anesthetic phenazopyridine, or the antibiotic rifampin), dehydration, and some liver or muscle problems can all change urine color. If your urine is discolored and you are not taking a B vitamin — or if the change comes with pain, fever, or blood — that points to a cause other than riboflavin.
Who, If Anyone, the Caveats Concern
Because there is no toxicity syndrome, there is no group at risk of "riboflavin poisoning." But a few real, narrow caveats are worth knowing so this page is honest and complete rather than falsely blanket-reassuring.
- Theoretical photosensitivity at very high doses. Riboflavin absorbs light and can generate reactive molecules when illuminated — a property deliberately harnessed in medicine (for example, riboflavin plus ultraviolet light is used to treat the cornea in a procedure called corneal collagen cross-linking, and to inactivate pathogens in donated blood). The Institute of Medicine called it “theoretically plausible” that riboflavin increases sensitivity to ultraviolet light, but sun-sensitivity is not a recognized side effect of taking riboflavin supplements. The IOM also named one specific theoretical risk: in babies treated with light for jaundice (phototherapy for hyperbilirubinemia), excess riboflavin could increase light-driven oxidation of amino acids and proteins, and it noted that these infants may be sensitive to excess riboflavin. This is the one biological reason high-dose riboflavin is occasionally discussed in safety reviews; no harm from riboflavin in food or supplements has been reported.
- Drug interactions are minor, not dangerous. A handful of medications can lower riboflavin status or interact mildly — for instance, older tricyclic antidepressants and some antipsychotics (phenothiazines) can modestly impair the body's conversion of riboflavin to its active forms, and long-term use could nudge someone toward deficiency rather than excess. The diuretics and some other drugs increase its excretion. None of these create a toxicity risk; if anything they argue the opposite. There is no well-established medication that becomes dangerous because of riboflavin.
- Injuries to the system that normally protects you are extremely rare. The kidneys are what flush riboflavin out. In theory, someone with severe kidney failure would clear water-soluble vitamins more slowly — but riboflavin specifically has not been shown to accumulate to harmful levels even in that setting, and dialysis itself removes B vitamins (so the practical concern in kidney disease is usually deficiency, and patients are often supplemented). Again, the direction of real-world risk points away from toxicity.
- Pregnancy and breastfeeding. Riboflavin needs rise modestly in pregnancy and lactation, and prenatal vitamins routinely include it. There is no evidence that normal or even generous riboflavin intake is harmful in pregnancy; the concern, as everywhere with this vitamin, is getting enough, not too much.
Notice the pattern: apart from the theoretical concern in babies under phototherapy, every one of these caveats, examined honestly, points toward making sure you have enough riboflavin — not toward fear of an overdose.
Practical Facts: Food, Urine, Megadoses and Lab Tests
Plain facts for the questions people actually have:
- Food does not supply too much riboflavin. It is impossible to overdo riboflavin by eating — even riboflavin-rich foods like milk, yogurt, eggs, liver, almonds, and fortified grains deliver amounts the body comfortably handles. (For where it comes from, see Sources of Vitamin B2.)
- Bright yellow urine is expected. It is harmless; a lower dose gives less color, and the color fades once the surplus clears.
- Megadoses mostly cost money. This is a value-for-money point, not a safety warning. Because absorption is capped and the surplus is excreted, taking far more riboflavin than the body needs mostly produces expensive, brightly-colored urine. The well-supported reason for a large dose (around 400 mg/day) is migraine prevention: in the 1998 trial by Schoenen and colleagues, 55 people with migraine took 400 mg a day or a placebo for 3 months; two minor side effects occurred on riboflavin (diarrhea and passing more urine) and one on placebo, and none was serious (see Riboflavin for Migraine Prevention). Otherwise, the adult Recommended Dietary Allowance is 1.3 mg a day for men and 1.1 mg for women (Institute of Medicine), which a normal multivitamin or a balanced diet covers.
- Supplements and lab work. This is a small but genuinely useful fact. Riboflavin is fluorescent, and very high levels in the blood or urine can, in some laboratory assays, interfere with measurements (certain fluorescence-based or colorimetric tests). This is far less of a problem than the well-known biotin (vitamin B7) interference with immunoassays.
- Deficiency is the real B2 problem. The clinically meaningful B2 condition is a shortage, not an excess — it shows up as sore cracked lips, a sore tongue, and eye irritation. See the Riboflavin Deficiency hub.
When to Seek Care / Red Flags
To be clear and honest: there is no "riboflavin overdose" to watch for. Bright yellow urine after a B vitamin is not a red flag — it is the normal, harmless sign of excess being excreted. The red flags below are about other conditions that can be mistaken for, or coincide with, taking riboflavin — situations where the vitamin is not the explanation.
- Discolored urine when you are not taking a B vitamin — especially urine that is red, brown, tea-colored, or cloudy, which can signal blood, muscle breakdown, or a liver problem — signs that clinics treat as needing prompt assessment.
- Urine changes accompanied by pain, fever, burning, or back pain — these point toward a urinary-tract or kidney issue, not a vitamin.
- A rash, itching, swelling, or trouble breathing after a supplement — true allergy to riboflavin is very rare, but an allergic reaction to any product (including fillers or dyes in a tablet) is a medical concern, and swelling of the face or throat or trouble breathing are signs of a severe allergic reaction (anaphylaxis) that hospitals treat as an emergency.
- Symptoms of deficiency rather than excess — persistent cracks at the corners of the mouth, a sore magenta tongue, or gritty, light-sensitive eyes warrant a look at riboflavin status, on the Deficiency page.
For scale: the adult Recommended Dietary Allowance is 1.3 mg a day for men and 1.1 mg for women, no Tolerable Upper Intake Level has been set, and no adverse effects from riboflavin in food or supplements have been reported (Institute of Medicine, 1998).
Related Pages
If you arrived here looking for something specific about vitamin B2, these pages are likely what you want:
- The real B2 problem — Riboflavin Deficiency covers the shortage that actually causes symptoms (sore lips, sore tongue, eye irritation), who is at risk, and how it is corrected.
- What riboflavin does — the Benefits hub explains its role as the FAD/FMN cofactor behind energy production, and the evidence for migraine prevention (the main reason anyone takes a high dose).
- Where to get it — Sources of Vitamin B2 lists the richest foods and how much they provide.
- The whole vitamin — the Vitamin B2 overview ties it all together, and History of Vitamin B2 traces its discovery.
Key Research Papers
- Powers HJ (2003). Riboflavin (vitamin B-2) and health. The American Journal of Clinical Nutrition;77(6):1352-1360. — DOI: 10.1093/ajcn/77.6.1352. — doi:10.1093/ajcn/77.6.1352
- EFSA Panel on Dietetic Products, Nutrition and Allergies (NDA); Turck D, Bresson J-L, Burlingame B, et al. (2017). Dietary Reference Values for riboflavin. EFSA Journal;15(8):e04919. — DOI: 10.2903/j.efsa.2017.4919. — doi:10.2903/j.efsa.2017.4919
- Powers HJ (1999). Current knowledge concerning optimum nutritional status of riboflavin, niacin and pyridoxine. Proceedings of the Nutrition Society;58(2):435-440. — DOI: 10.1017/S0029665199000579. — doi:10.1017/S0029665199000579
- Bates CJ (1987). Human requirements for riboflavin. The American Journal of Clinical Nutrition;46(1):122-123. — DOI: 10.1093/ajcn/46.1.122. — doi:10.1093/ajcn/46.1.122
- Schoenen J, Jacquy J, Lenaerts M (1998). Effectiveness of high-dose riboflavin in migraine prophylaxis: a randomized controlled trial. Neurology;50(2):466-470. — DOI: 10.1212/WNL.50.2.466. — doi:10.1212/WNL.50.2.466
- Rooney M, Bottiglieri T, Wasek-Patterson B, McMahon A, et al. (2020). Impact of the MTHFR C677T polymorphism on one-carbon metabolites: Evidence from a randomised trial of riboflavin supplementation. Biochimie;173:91-99. — DOI: 10.1016/j.biochi.2020.04.004. — doi:10.1016/j.biochi.2020.04.004
- Jobe M, Ward M, Sonko B, Muhammad A-K, et al. (2020). Effect of riboflavin supplementation on blood pressure and possible effect modification by the MTHFR C677T polymorphism: a randomised trial in rural Gambia. F1000Research;9:1034. — DOI: 10.12688/f1000research.25113.1. — doi:10.12688/f1000research.25113.1
- Institute of Medicine (1998). Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline. Chapter 5, Riboflavin (no Tolerable Upper Intake Level could be derived; theoretical concern in infants treated for hyperbilirubinemia). Washington, DC: National Academies Press. — National Academies Press: chapter 5 — doi:10.17226/6015
PubMed Topic Searches
- PubMed: Riboflavin toxicity, safety, and upper intake level
- PubMed: Riboflavin absorption and saturable intestinal transport
- PubMed: High-dose riboflavin in migraine prophylaxis: tolerability
- PubMed: Riboflavinuria, urine color, and riboflavin excretion
- PubMed: Renal excretion and clearance of riboflavin