Vitamin E Toxicity: Blood-Thinner Interactions
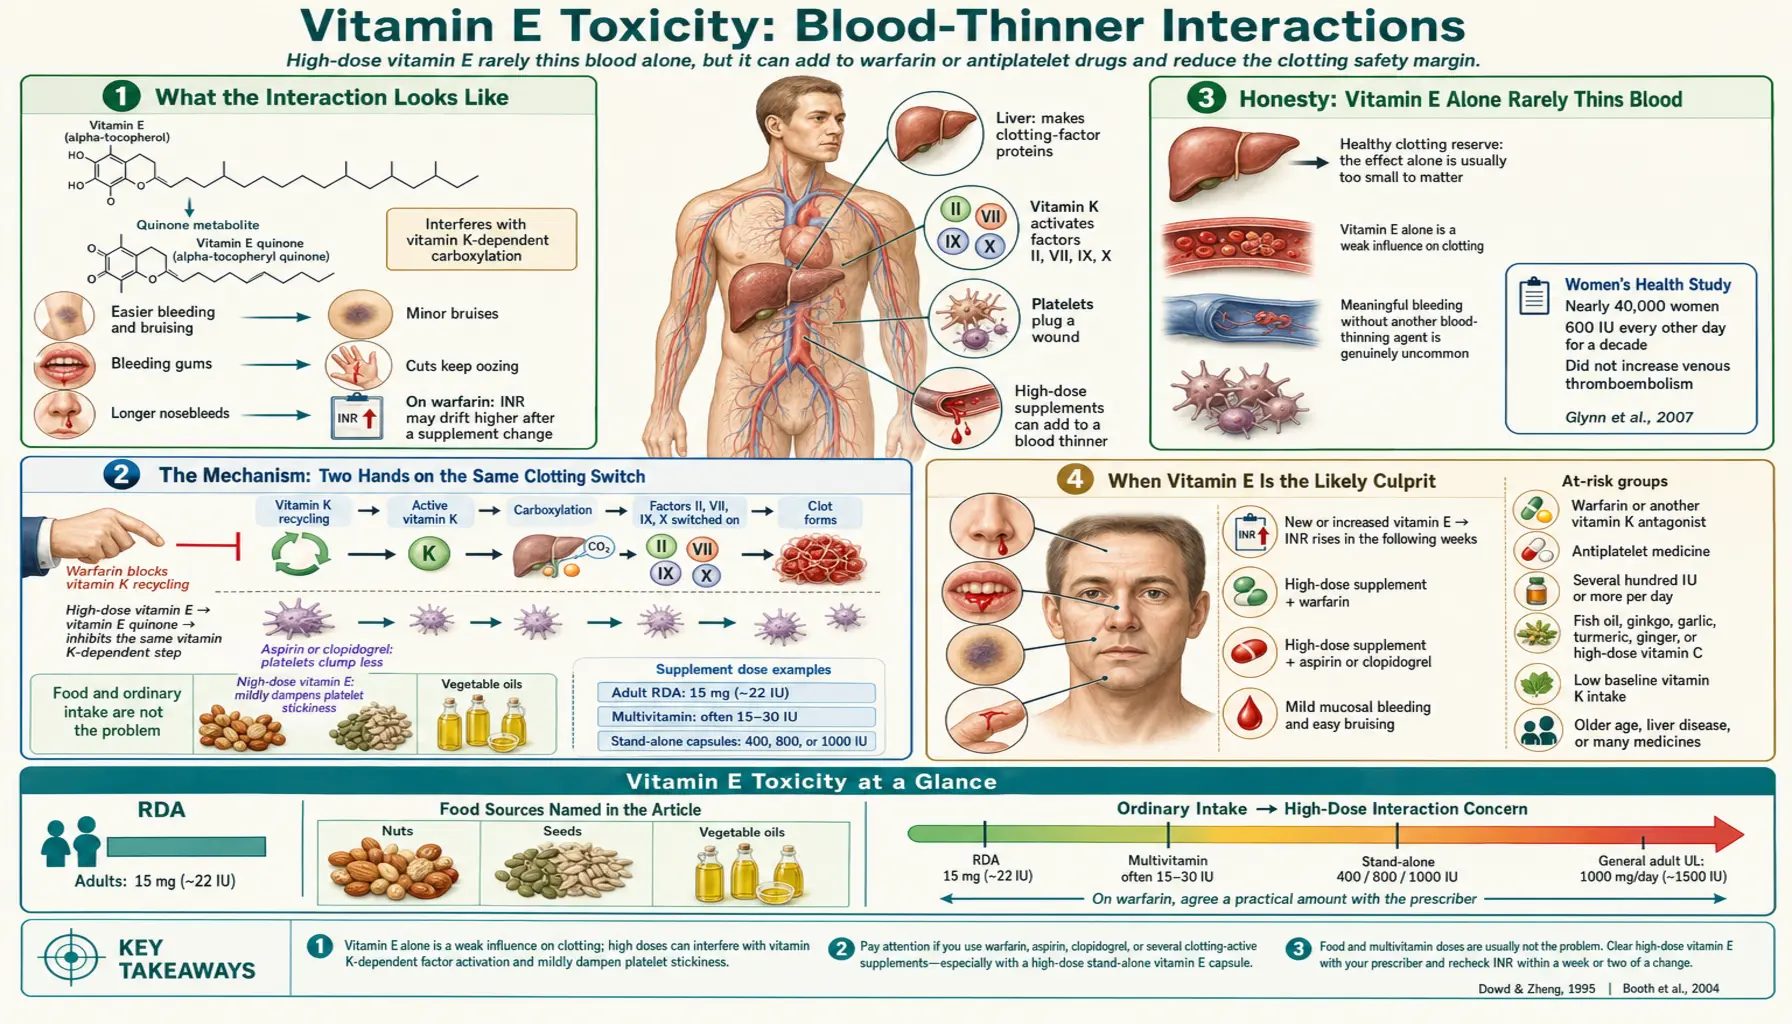
High-dose vitamin E and the blood thinner warfarin act on the same step of blood clotting from different sides, which is why the Institute of Medicine singles out people on anticoagulant therapy when it discusses vitamin E safety. On its own, vitamin E is rarely linked to a bleeding problem in a healthy person: the Institute of Medicine reported that up to 600 mg/day of alpha-tocopherol for up to three years caused no adverse blood-coagulation effects in apparently healthy volunteers (IOM, 2000). Layered on top of warfarin or an antiplatelet drug such as aspirin or clopidogrel, laboratory studies, case reports and trial subgroups describe an added push toward bleeding. This is less “vitamin E toxicity” in the way that too much vitamin A is toxic than an interaction — a small effect that matters because the medication has already narrowed the body's clotting reserve. This page covers how that interaction works, what the trials and case reports found, who the research raises concerns for, and how it is detected.
Table of Contents
- What the Interaction Looks Like
- The Mechanism: Two Hands on the Same Clotting Switch
- Honesty: Vitamin E Alone Rarely Thins Blood
- When Vitamin E Is the Likely Culprit
- What Makes the Interaction More Likely
- Dose: Where the Risk Actually Lives
- How It Is Detected: The INR and Coagulation Tests
- How It Is Managed: What the Guidance Describes
- Warning Signs of Over-Thinning
- Key Research Papers
- Connections
- Featured Videos
What the Interaction Looks Like
An interaction is not a feeling, so there is nothing to “notice” in the moment you swallow a vitamin E capsule alongside warfarin. What would show, if the interaction tipped over into a real effect, is the same thing any over-thinned blood produces: easier bleeding and bruising. The classic early signs are gums that bleed with brushing, nosebleeds that take longer to stop, bruises that appear from minor knocks no one remembers, and small cuts that keep oozing. In someone on warfarin, the more telling clue is often a lab number rather than a symptom — the INR (the blood test that measures how far warfarin has slowed clotting) drifts higher than usual even though nothing about the warfarin dose has changed.
It is worth being precise about what this page covers and what it does not. The bleeding and bruising themselves — how they look and how they are assessed — are covered on the sibling page Vitamin E and Bleeding & Bruising, and the most feared version, bleeding into the brain, is covered on Vitamin E and Hemorrhagic Stroke Risk. This page is specifically about the interaction with blood-thinning medication: why combining the two raises the stakes, who the research raises concerns for, and how it is managed. In short: vitamin E does not usually thin the blood on its own, but on top of a blood thinner it can shift an already-narrow margin in the wrong direction.
The Mechanism: Two Hands on the Same Clotting Switch
To see why the combination matters, it helps to know what each side does to the clotting system. Blood clotting depends on a series of proteins called clotting factors, and several of the most important ones — factors II (prothrombin), VII, IX, and X — can only do their job after they have been chemically “finished” by a reaction that requires vitamin K. Think of vitamin K as the tool that switches these factors on. Without it, the liver still makes the factor proteins, but they come off the line non-functional, like a tool that was never sharpened.
Warfarin works by blocking vitamin K. Specifically, it stops the enzyme that recycles vitamin K back into its active form, so the supply of usable vitamin K dwindles and fewer clotting factors get switched on. That is the entire point of the drug: by partially disabling vitamin K, warfarin keeps the blood from clotting too readily in people at risk of stroke or dangerous clots. The trade-off is a narrow margin: a systematic overview of warfarin interactions notes that the drug's use is limited by a well-founded fear of bleeding and that drug and food interactions are frequently cited causes of its adverse events (Holbrook et al., 2005; Ansell et al., 2008).
Here is where vitamin E comes in. An oxidized form of vitamin E, vitamin E quinone (alpha-tocopheryl quinone), proved in laboratory work to be a potent inhibitor of the vitamin K–dependent carboxylase — the enzyme that switches the clotting factors on — whereas vitamin E in its ordinary reduced form showed only very modest anticlotting activity (Dowd & Zheng, 1995). Earlier work by Corrigan found that vitamin E lowered functional prothrombin (factor II) further in warfarin-treated rats and people while the precursor protein itself was unchanged, which points to the vitamin K–dependent carboxylation step rather than to production of the factor (Corrigan & Ulfers, 1981; Corrigan, 1982). In people not on any blood thinner, two 12-week randomized trials of 1000 IU/day of natural vitamin E found a rise in PIVKA-II, an under-carboxylated form of prothrombin that signals poorer vitamin K status, while the other vitamin K measures did not change; the authors wrote that the clinical significance needs further study and that high doses of vitamin E may antagonize vitamin K (Booth et al., 2004).
An analogy. Picture vitamin K as the only key that unlocks the clotting factors, and warfarin as a thief who has already pocketed most of the keys. You can still open a few locks, just slowly — that controlled slowness is what keeps a warfarin patient safe. Now high-dose vitamin E quietly slips a couple more keys off the ring. On a full key ring (no warfarin) you would never notice the missing keys. But when the ring is already nearly empty, losing even two more can mean a lock that should have opened — a clot that should have formed to seal a small bleed — never gets opened at all. Same lever, two hands, and the second hand only matters because the first one has already done most of the pulling.
Antiplatelet drugs — aspirin, clopidogrel, and similar agents — work by a different route: they stop platelets, the tiny cell fragments that plug a wound, from clumping together. Vitamin E has a separate effect here: alpha-tocopherol inhibits platelet aggregation in laboratory studies, and in 15 healthy volunteers oral supplementation with 400 to 1200 IU/day inhibited one measure of platelet aggregation (Freedman et al., 1996). The Institute of Medicine noted that it is not clear these platelet effects are harmful in healthy people at any dose (IOM, 2000). So when vitamin E is combined with an antiplatelet drug, the overlap is on the platelet side rather than the vitamin K side — but the theme is identical: two influences pushing the same direction, with the medication having already used up the safety margin.
Honesty: Vitamin E Alone Rarely Thins Blood
It would be easy to read the section above and conclude that vitamin E is dangerous for everyone. The evidence in people who are not taking a blood thinner is more reassuring, and it is the part alarming headlines usually skip.
In healthy adults not taking a blood thinner, large vitamin E supplements have rarely been linked to meaningful bleeding. The Institute of Medicine found no adverse blood-coagulation effects from up to 600 mg/day of alpha-tocopherol for up to three years in apparently healthy volunteers (IOM, 2000), and Corrigan reported that the deeper coagulation defect seen in vitamin K–deficient animals and people given vitamin E was not seen in vitamin K–sufficient ones (Corrigan, 1982). In the Women's Health Study, which randomized 39,876 women to 600 IU of natural-source vitamin E or placebo every other day for a median of 10.2 years, venous thromboembolism (clots in the veins), a secondary endpoint, was 21% less common in the vitamin E group (relative hazard 0.79) (Glynn et al., 2007).
The well-known vitamin E controversies belong in the same perspective. A 2005 meta-analysis of 19 trials linked high-dose vitamin E (400 IU/day or more) to a small increase in all-cause mortality (Miller et al., 2005). A 2010 meta-analysis of nine trials found no effect on total stroke but a shift in stroke type: 22% more hemorrhagic (bleeding-type) strokes and 10% fewer ischemic (clot-type) strokes, which the authors put at one additional hemorrhagic stroke for every 1,250 people taking vitamin E against one ischemic stroke prevented per 476 (Schürks et al., 2010, discussed on the hemorrhagic stroke page). In the Physicians' Health Study II, 400 IU every other day for a mean of 8 years was associated with an increased risk of hemorrhagic stroke (hazard ratio 1.74, 95% CI 1.04–2.91) (Sesso et al., 2008), while the Women's Health Study found no significant effect on ischemic or hemorrhagic stroke (Lee et al., 2005). The large cardiovascular-prevention trials found no overall benefit for major cardiovascular events (Lee et al., 2005; Eidelman et al., 2004; Sesso et al., 2008). These are signals measured across very large populations; they do not describe people bleeding from vitamin E alone at dietary intakes.
So the honest bottom line is two-sided. Vitamin E alone is a weak influence on clotting and rarely a problem on its own — and that same weak influence becomes relevant when it is added to a drug that has already narrowed the clotting reserve. Both halves of that sentence are true at once, and holding them together is the whole point of this page.
When Vitamin E Is the Likely Culprit
Easy bleeding has many causes, so vitamin E is rarely the first suspect. A few patterns, though, point toward the supplement-plus-medication combination specifically:
- Vitamin E was started or increased, and the INR climbed. In someone taking warfarin, the pattern described is an INR (or prothrombin time) that rises after a vitamin E supplement is started or increased, with no change to the warfarin dose, diet or other medicines. A 1974 case report described abnormal blood coagulation in a patient on long-term warfarin who was taking vitamin E (Corrigan & Marcus, 1974; IOM, 2000). A timeline that lines up — new supplement, then rising INR — is the strongest single clue.
- A blood thinner plus a high-dose supplement. The concern centres on people combining an anticoagulant (warfarin) or antiplatelet drug (aspirin, clopidogrel) with vitamin E doses far above dietary intake; the studies in warfarin patients tested doses of 100 IU/day and above (Corrigan & Ulfers, 1981).
- Other supplements discussed for effects on clotting. Fish oil, ginkgo and garlic are often taken alongside vitamin E and are often discussed for possible effects on clotting. A 2005 systematic overview of warfarin interactions found that 84% of reported interactions rested on poor-quality evidence, most of it single case reports (Holbrook et al., 2005); how much several such supplements add together on top of a blood thinner has not been well measured.
- The bleeding described is mostly mild and mucosal. Reports linking vitamin E to bleeding mostly describe gums, nose and easy bruising. In a subgroup of a Finnish trial, gum bleeding on dental probing was most frequent in men taking both alpha-tocopherol (50 mg/day) and aspirin (Liede et al., 1998). Hemorrhagic stroke, discussed above, is the serious exception.
Conversely, several things make vitamin E an unlikely explanation and point elsewhere: bleeding in someone on no blood thinner who takes only a modest vitamin E dose; bleeding that began long before any supplement was started; or bleeding accompanied by other findings (weight loss, fevers, a very low platelet count) that suggest a different underlying problem. Honesty cuts both ways — just as vitamin E can be overlooked, it can also be wrongly blamed.
What Makes the Interaction More Likely
The interaction is not all-or-nothing; several factors raise or lower the odds that adding vitamin E will actually move the needle.
- Taking warfarin or another vitamin K antagonist. This is the central one. Because warfarin already works by suppressing vitamin K, any further nudge to the same pathway lands on an unprotected system. Warfarin also has a notoriously narrow therapeutic window — the gap between “thinned enough to prevent clots” and “thinned too far” is small — so even a modest extra push can carry the INR out of range (Ansell et al., 2008).
- Taking an antiplatelet drug. Aspirin, clopidogrel, prasugrel, ticagrelor, and similar agents are blood thinners of a different kind, and vitamin E's platelet effect overlaps with them. In the Finnish trial subgroup, gum bleeding was most common with alpha-tocopherol and aspirin together, and the authors concluded that alpha-tocopherol may increase the risk of clinically important bleeding, particularly when combined with aspirin (Liede et al., 1998). In a 2-year trial of 100 patients with transient ischemic attacks, vitamin E (400 IU/day) plus aspirin reduced ischemic events compared with aspirin alone; hemorrhagic stroke did not differ significantly, although both patients who had one were taking vitamin E (Steiner et al., 1995). Many people on these drugs do not think of themselves as being “on a blood thinner,” which makes the overlap easy to miss.
- High supplement doses. In 12 people taking warfarin, 100 or 400 IU/day of vitamin E for four weeks did not change the prothrombin time, although a ratio of functional to total prothrombin fell; the authors concluded that the effect is not clinically obvious at 400 IU/day or less (Corrigan & Ulfers, 1981). The concern in the literature centres on high-potency stand-alone supplements rather than the amounts in food. See the dose section below.
- Stacking other clotting-active supplements. Fish oil, ginkgo, garlic, turmeric/curcumin and ginger are often discussed for possible effects on clotting; the combined effect of several of them on top of a blood thinner has not been well measured.
- Low vitamin K status. Corrigan's studies found that vitamin E deepened the coagulation defect in vitamin K–deficient animals and people, including those made deficient by warfarin, but not in vitamin K–sufficient subjects (Corrigan, 1982), and the Institute of Medicine states that its upper limit applies to people with adequate vitamin K intake (IOM, 2000). (For warfarin patients, vitamin K intake is generally kept steady, not minimized.)
- Older age, frailty, and many medications. Older adults, people who are debilitated or malnourished, and anyone on a long medication list are more sensitive to shifts in warfarin effect; the 2008 ACCP guideline recommends a starting warfarin dose of 5 mg or less in elderly and other patients who are debilitated or malnourished (Ansell et al., 2008).
Dose: Where the Risk Actually Lives
Almost everything about this interaction comes down to how much vitamin E, so it is worth being concrete. Vitamin E is measured in milligrams (mg) of alpha-tocopherol or, on many labels, in International Units (IU). The Institute of Medicine's conversion table gives 1.49 IU per mg for natural vitamin E (RRR- or d-alpha-tocopherol) and 1.10 IU per mg for synthetic vitamin E (all-rac- or dl-alpha-tocopherol), and counts synthetic vitamin E at half the value of natural vitamin E toward the requirement (IOM, 2000).
- The daily requirement (RDA) is 15 mg/day of alpha-tocopherol for adults (IOM, 2000). Nuts, seeds and vegetable oils are the main food sources. No interaction has been described at this level.
- Multivitamins contain much smaller amounts than stand-alone capsules. The studies in warfarin patients tested stand-alone doses, not multivitamin amounts.
- Stand-alone vitamin E supplements are what the studies tested. The trials discussed here used 100 or 400 IU/day in warfarin patients (Corrigan & Ulfers, 1981), 400 IU every other day (Sesso et al., 2008), 600 IU every other day (Lee et al., 2005) and 1000 IU/day (Booth et al., 2004) — many times the daily requirement. In a double-blind trial in 21 people on long-term warfarin randomized to vitamin E or placebo, none of those given vitamin E had a significant change in INR (Kim & White, 1996).
- The tolerable upper intake level (UL) is 1,000 mg/day of any form of supplemental alpha-tocopherol for adults, set on the adverse effect of an increased tendency to hemorrhage (IOM, 2000). The critical data came from rats: the Institute of Medicine took a lowest-observed-adverse-effect level of 500 mg/kg body weight/day from a 104-week rat feeding study in which hemorrhages and prolonged prothrombin times appeared. The Institute of Medicine states that the UL applies to people with adequate vitamin K intake, that people who are deficient in vitamin K or on anticoagulant therapy are at increased risk of coagulation defects, and that patients on anticoagulant therapy taking vitamin E supplements should be monitored, as described by Kim and White (1996).
In short: no interaction has been described for vitamin E from food, and the studies above concern high-dose stand-alone supplements taken alongside a blood thinner that has already narrowed the clotting reserve.
How It Is Detected: The INR and Coagulation Tests
For warfarin, this interaction is measurable: the same blood test that guides warfarin therapy also shows the interaction.
For anyone on warfarin, the key test is the INR (International Normalized Ratio), part of a coagulation panel that also reports the prothrombin time (PT) and aPTT. The INR measures how long blood takes to clot compared with normal: a higher number means thinner blood. For most indications the target warfarin INR range is 2.0–3.0 (Ansell et al., 2008). If vitamin E (or a stack of clotting-active supplements) is pushing the system further toward bleeding, the INR rises — often the first objective sign, appearing before any bleeding does. Regular INR testing is part of warfarin management, and the Institute of Medicine notes that patients on anticoagulant therapy who take vitamin E supplements should be monitored (IOM, 2000).
A subtlety worth knowing: the INR is excellent for warfarin but does not reflect the effect of antiplatelet drugs like aspirin or clopidogrel, whose action on platelets the INR cannot see. For those, there is no simple everyday blood test; monitoring relies on watching for bleeding symptoms and reviewing the medication and supplement list. A basic blood count (a complete blood count) is sometimes used to confirm the platelet count is normal and to gauge blood loss if bleeding has occurred, but it does not measure the thinning effect itself.
The other half of detection is the medication-and-supplement review. Because the interaction depends on dose and combination, a complete list of medicines and supplements — including products people may not think of as drugs — is what lets clinicians assess it before any test is needed.
How It Is Managed: What the Guidance Describes
Management of this interaction is comparatively straightforward, because the added agent is a supplement rather than a disease. What the research and guidance describe runs from prevention to correction.
- Whether a high-dose supplement is needed at all. Large trials found that vitamin E did not prevent major cardiovascular events or cancer (Lee et al., 2005; Eidelman et al., 2004; Sesso et al., 2008), and pooled analyses link high doses to small harms (Miller et al., 2005; Schürks et al., 2010). Stopping a supplement removes its contribution to the interaction.
- Clinician involvement for people on a blood thinner. The Institute of Medicine states that patients on anticoagulant therapy who take vitamin E supplements should be monitored (IOM, 2000). Warfarin doses are matched to a person's usual intake, so the goal described is consistency: an abrupt change in a supplement in either direction can move the INR.
- INR checks around a change. The INR is the test that shows whether starting or stopping a vitamin E supplement has shifted warfarin's effect; it was the measure used in the controlled trial of vitamin E in warfarin patients (Kim & White, 1996). This is the same monitoring warfarin already requires.
- The whole supplement list, not just vitamin E. Fish oil, ginkgo, garlic, turmeric and ginger are commonly reviewed at the same time. For warfarin patients, the approach described for both supplements and vitamin K–rich foods is steady intake rather than swings from one extreme to another.
- Correcting over-anticoagulation. The 2008 ACCP guideline gives specific recommendations for INRs above the therapeutic range and for bleeding: oral rather than subcutaneous vitamin K to reverse a mildly elevated INR, and prothrombin complex concentrates or recombinant factor VIIa to reverse the INR immediately in life-threatening bleeding or intracranial hemorrhage (Ansell et al., 2008). Added vitamin K opposes warfarin and lowers the INR, so large vitamin K doses taken outside medical care to “counteract” a thinner can push warfarin control out of range in the opposite direction.
In short, the research concern centres on high-dose vitamin E added to a blood thinner; decisions about supplements alongside anticoagulants belong with a clinician.
Warning Signs of Over-Thinning
Most of the time this interaction is a quiet shift in a lab number, caught and corrected long before any harm. But certain signs are recognized markers that the blood may have been thinned too far, and they are treated as urgent — the severe ones as emergencies rather than matters for a routine appointment:
- Signs of bleeding in the brain — a sudden severe headache unlike any before, sudden confusion, weakness or numbness on one side, trouble speaking, or loss of vision. This is treated as a medical emergency. (See Vitamin E and Hemorrhagic Stroke Risk and Stroke.)
- Bleeding that will not stop — a nosebleed that does not stop with firm pressure, a cut that keeps bleeding despite firm pressure, or bleeding gums that do not settle.
- Blood where it does not belong — vomit that looks like coffee grounds or contains blood, black tarry stools or visible blood in the stool, or pink/red urine. These can signal internal bleeding and are treated as needing urgent assessment.
- Coughing or vomiting blood, or a sudden large bruise — especially a rapidly spreading bruise or swelling after a minor injury.
- Feeling faint, unusually short of breath, or very pale and tired — which can mean enough blood has been lost to matter, even without obvious external bleeding.
One lower-urgency but important flag: in someone on warfarin, an INR above the target range after a supplement is started is a finding anticoagulation services act on even when the person feels well, because the aim of monitoring is to catch the drift on paper, before a bleed happens.
Key Research Papers
- Booth SL, Golly I, Sacheck JM, et al. (2004). Effect of vitamin E supplementation on vitamin K status in adults with normal coagulation status. American Journal of Clinical Nutrition;80(1):143-148. — DOI: 10.1093/ajcn/80.1.143. — doi:10.1093/ajcn/80.1.143
- Dowd P, Zheng ZB (1995). On the mechanism of the anticlotting action of vitamin E quinone. Proceedings of the National Academy of Sciences;92(18):8171-8175. — DOI: 10.1073/pnas.92.18.8171. — doi:10.1073/pnas.92.18.8171
- Holbrook AM, Pereira JA, Labiris R, et al. (2005). Systematic Overview of Warfarin and Its Drug and Food Interactions. Archives of Internal Medicine;165(10):1095-1106. — DOI: 10.1001/archinte.165.10.1095. — doi:10.1001/archinte.165.10.1095
- Ansell J, Hirsh J, Hylek E, et al. (2008). Pharmacology and Management of the Vitamin K Antagonists. Chest;133(6 Suppl):160S-198S. — DOI: 10.1378/chest.08-0670. — doi:10.1378/chest.08-0670
- Glynn RJ, Ridker PM, Goldhaber SZ, et al. (2007). Effects of Random Allocation to Vitamin E Supplementation on the Occurrence of Venous Thromboembolism. Circulation;116(13):1497-1503. — DOI: 10.1161/CIRCULATIONAHA.107.716407. — doi:10.1161/CIRCULATIONAHA.107.716407
- Schürks M, Glynn RJ, Rist PM, et al. (2010). Effects of vitamin E on stroke subtypes: meta-analysis of randomised controlled trials. BMJ;341:c5702. — DOI: 10.1136/bmj.c5702. — doi:10.1136/bmj.c5702
- Lee IM, Cook NR, Gaziano JM, et al. (2005). Vitamin E in the primary prevention of cardiovascular disease and cancer: the Women's Health Study: a randomized controlled trial. JAMA;294(1):56-65. — DOI: 10.1001/jama.294.1.56. — doi:10.1001/jama.294.1.56
- Miller ER, Pastor-Barriuso R, Dalal D, et al. (2005). Meta-Analysis: High-Dosage Vitamin E Supplementation May Increase All-Cause Mortality. Annals of Internal Medicine;142(1):37-46. — DOI: 10.7326/0003-4819-142-1-200501040-00110. — doi:10.7326/0003-4819-142-1-200501040-00110
- Eidelman RS, Hollar D, Hebert PR, et al. (2004). Randomized Trials of Vitamin E in the Treatment and Prevention of Cardiovascular Disease. Archives of Internal Medicine;164(14):1552-1556. — DOI: 10.1001/archinte.164.14.1552. — doi:10.1001/archinte.164.14.1552
- Traber MG, Atkinson J (2007). Vitamin E, antioxidant and nothing more. Free Radical Biology and Medicine;43(1):4-15. — DOI: 10.1016/j.freeradbiomed.2007.03.024. — doi:10.1016/j.freeradbiomed.2007.03.024
- Booth SL (2009). Roles for Vitamin K Beyond Coagulation. Annual Review of Nutrition;29:89-110. — DOI: 10.1146/annurev-nutr-080508-141217. — doi:10.1146/annurev-nutr-080508-141217
- Corrigan JJ, Marcus FI (1974). Coagulopathy associated with vitamin E ingestion. JAMA;230(9):1300-1301. — PubMed PMID: 4479598
- Institute of Medicine (2000). Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Chapter 6, Vitamin E. Washington, DC: The National Academies Press. — doi:10.17226/9810
- Corrigan JJ Jr, Ulfers LL (1981). Effect of vitamin E on prothrombin levels in warfarin-induced vitamin K deficiency. American Journal of Clinical Nutrition;34(9):1701-1705. — PubMed PMID: 7282596
- Corrigan JJ Jr (1982). The effect of vitamin E on warfarin-induced vitamin K deficiency. Annals of the New York Academy of Sciences;393:361-368. — PubMed PMID: 6959563
- Kim JM, White RH (1996). Effect of vitamin E on the anticoagulant response to warfarin. American Journal of Cardiology;77(7):545-546. — PubMed PMID: 8629604
- Sesso HD, Buring JE, Christen WG, et al. (2008). Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomized controlled trial. JAMA;300(18):2123-2133. — PubMed PMID: 18997197
- Freedman JE, Farhat JH, Loscalzo J, Keaney JF Jr (1996). Alpha-tocopherol inhibits aggregation of human platelets by a protein kinase C-dependent mechanism. Circulation;94(10):2434-2440. — PubMed PMID: 8921785
- Liede KE, Haukka JK, Saxén LM, Heinonen OP (1998). Increased tendency towards gingival bleeding caused by joint effect of alpha-tocopherol supplementation and acetylsalicylic acid. Annals of Medicine;30(6):542-546. — PubMed PMID: 9920356
- Steiner M, Glantz M, Lekos A (1995). Vitamin E plus aspirin compared with aspirin alone in patients with transient ischemic attacks. American Journal of Clinical Nutrition;62(6 Suppl):1381S-1384S. — PubMed PMID: 7495235
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin E Toxicity Hub
- Vitamin E and Bleeding & Bruising
- Vitamin E and Hemorrhagic Stroke Risk
- Vitamin E Deficiency Hub
- Vitamin E Overview
- Vitamin E and Heart Health
- Vitamin K
- Vitamin K2
- Coagulation Panel (PT, INR, aPTT)
- Complete Blood Count
- Stroke
- Atrial Fibrillation
- Deep Vein Thrombosis
- Hematology
- Foods