⚠ Evidence warning: Clinical trials or other evidence do not support the claims that tocotrienols lower total and low-density lipoprotein cholesterol by 10 to 24 percent with an excellent safety profile, and that higher plasma alpha-tocopherol goes with lower coronary heart disease deaths in dose-response fashion. This page keeps it as a report of what people, websites or other media say.
Vitamin E and Heart Health
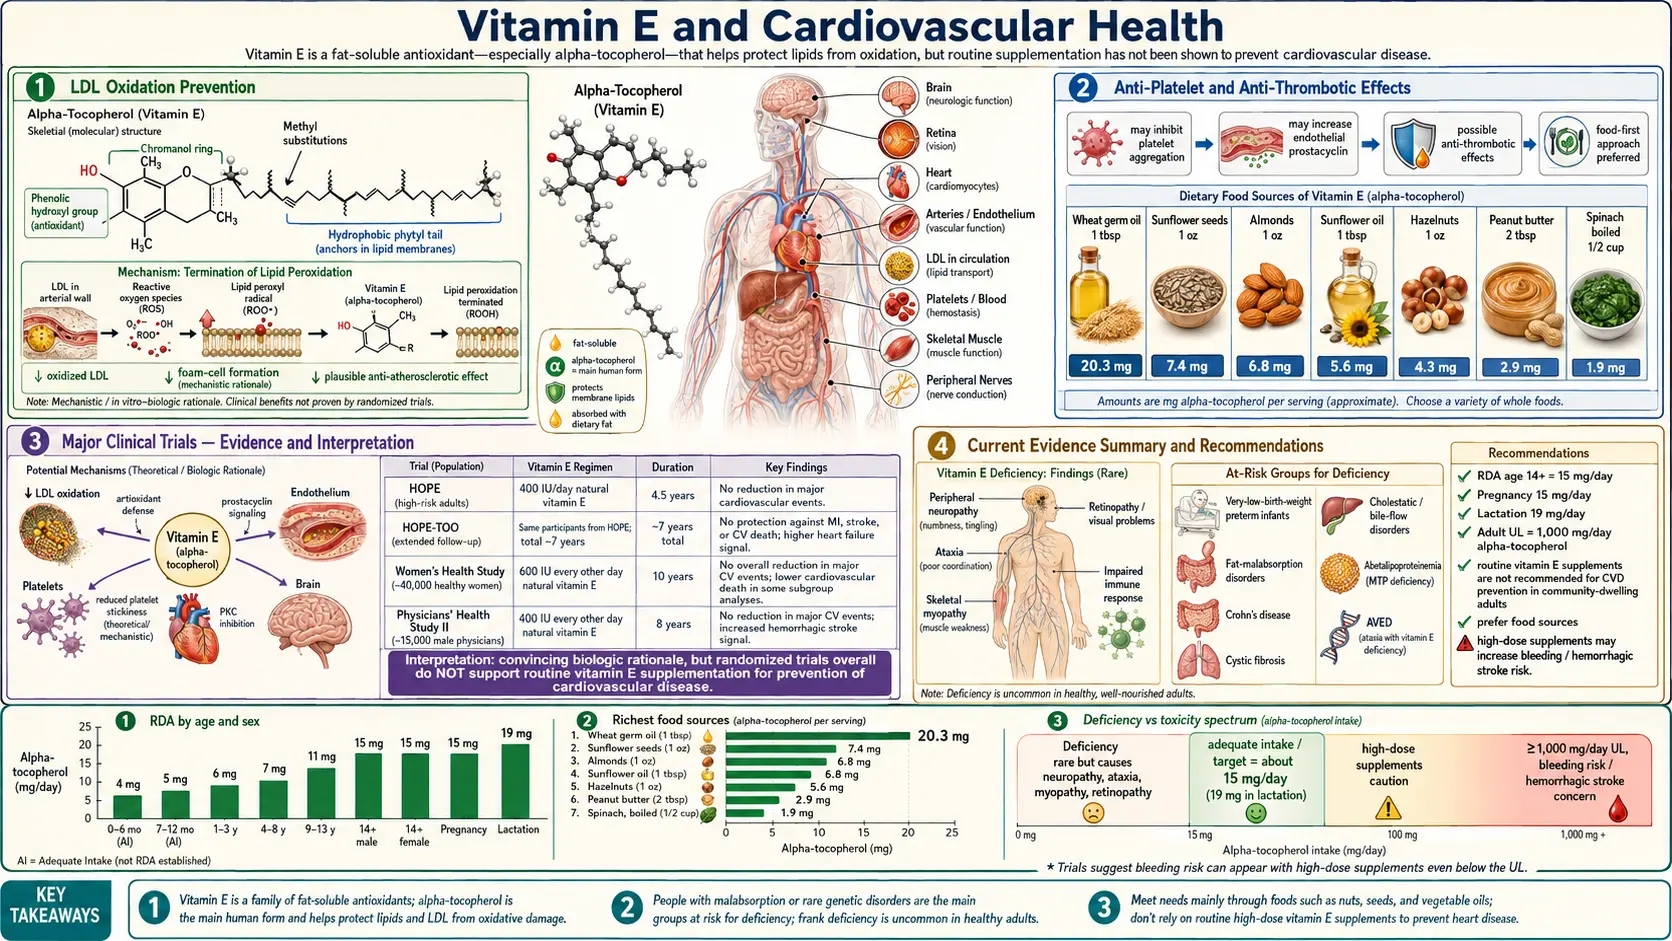
Table of Contents
- Overview
- Vitamin E Forms and Why Alpha-Tocopherol Alone Misled Us
- Mechanism — Lipid Peroxidation and Low-Density Lipoprotein Oxidation
- Gamma-Tocopherol and Reactive Nitrogen Species
- Tocotrienols and Cholesterol
- Major Cardiovascular Randomized Controlled Trials in Context
- Modern Evidence — Subgroups That Benefit
- Vitamin E and Atherosclerosis Progression
- Practical Dosing and Form
- Cautions and Drug Interactions
- Where the Official Guidance Stands Today
- Key Research Papers
- Connections
- Featured Videos
Overview
For three decades, vitamin E was the antioxidant of the century — the fat-soluble vitamin that would quench free radicals, stop the oxidation of low-density lipoprotein (LDL) cholesterol, and rescue arteries from atherosclerotic plaque. Observational studies from the early 1990s, most prominently the Nurses' Health Study and the Health Professionals Follow-up Study, reported that men and women in the highest quintile of vitamin E intake had roughly a 30 to 40 percent lower risk of coronary heart disease compared to the lowest quintile. Two decades later, the picture is dramatically more complicated — and dramatically more interesting.
Between 1994 and 2005, a series of large randomized controlled trials — ATBC, CHAOS, GISSI-Prevenzione, HOPE, HOPE-TOO, and the Women's Health Study — tested high-dose alpha-tocopherol against placebo for cardiovascular endpoints (synthetic dl-alpha-tocopherol in several, natural-source vitamin E in HOPE and the Women's Health Study). The results landed somewhere between disappointing and disturbing. HOPE found no benefit. GISSI-Prevenzione was essentially null. ATBC suggested a possible increase in hemorrhagic stroke. By 2005 the Annals of Internal Medicine meta-analysis suggested that doses of 400 international units (IU) per day or more might modestly increase all-cause mortality. The professional societies pulled back. Vitamin E went from miracle to malpractice in less than a decade.
The modern, evidence-aware answer is more nuanced than either extreme. The trials did not test vitamin E. They tested one synthetic isomer of one of vitamin E's eight natural forms, given in pharmacologic doses, to mixed populations, mostly without their natural partners (gamma-tocopherol, the four tocotrienols, vitamin C, selenium). The form mattered. The matrix mattered. The population mattered. The dose mattered. When you look at subgroups defined by haptoglobin genotype, at trials of mixed natural tocopherols, at the emerging tocotrienol literature, and at food-derived vitamin E intake, a more sensible picture emerges — one that is neither "antioxidant cure-all" nor "supplement that kills." This page lays out that picture.
Vitamin E Forms and Why Alpha-Tocopherol Alone Misled Us
"Vitamin E" is not one molecule. It is a family of eight structurally related fat-soluble compounds, all biosynthesized only by photosynthetic organisms (plants, algae, some cyanobacteria) and acquired by humans entirely through diet.
- Four tocopherols – alpha-, beta-, gamma-, and delta-tocopherol. These have a saturated 16-carbon phytyl side chain attached to a chromanol head. They differ in the number and position of methyl groups on the chromanol ring.
- Four tocotrienols – alpha-, beta-, gamma-, and delta-tocotrienol. Same head, but with an unsaturated farnesyl tail (three double bonds in the side chain). The tails sit differently in cell membranes and give tocotrienols mechanistic properties that alpha-tocopherol does not have.
- Natural vs synthetic alpha-tocopherol – Natural RRR-alpha-tocopherol (sometimes labeled d-alpha-tocopherol) has a single stereoisomer at three chiral centers. Synthetic all-rac-alpha-tocopherol (labeled dl-alpha-tocopherol) is an equal mix of eight stereoisomers, only one of which is the natural form. The natural form is preferentially retained by the liver's alpha-tocopherol transfer protein (alpha-TTP), giving it roughly twice the bioavailability of the synthetic mixture per unit weight.
- Why most trials used synthetic alpha alone – In the 1990s, synthetic dl-alpha-tocopherol was the cheapest, most stable, and most standardized form available. It gave a clean active-versus-placebo comparison. The cardiovascular randomized controlled trials (RCTs) of that era almost universally used 400 international units, 800 international units, or even 2,000 international units of synthetic alpha-tocopherol as a single agent.
- The displacement problem – High-dose supplemental alpha-tocopherol displaces gamma-tocopherol from cell membranes and from circulation. Plasma gamma-tocopherol falls by 30 to 50 percent within weeks of starting a high-dose alpha-tocopherol regimen. Since gamma-tocopherol carries distinct biological activity that alpha-tocopherol lacks (see next section), high-dose alpha-only supplementation may actually subtract a beneficial molecule while adding a less useful one.
- Implication for trial interpretation – The major cardiovascular randomized controlled trials did not test "vitamin E." They tested a particular intervention — pharmacologic dl-alpha-tocopherol monotherapy — that is almost the opposite of the food-pattern intake (mixed tocopherols, mostly gamma in the U.S. diet) that the observational studies had been measuring. The null result is consistent with both possibilities: vitamin E does nothing for the heart, or the specific intervention tested was the wrong one. The evidence since 2000 increasingly favors the second interpretation.
Mechanism — Lipid Peroxidation and Low-Density Lipoprotein Oxidation
The proposed cardioprotective mechanism of vitamin E starts inside the low-density lipoprotein particle and ends with the foam cell that builds atherosclerotic plaque.
- Chain-breaking antioxidant – Alpha-tocopherol's chromanol hydroxyl donates a hydrogen atom to a lipid peroxyl radical, neutralizing the radical and stopping the chain reaction of lipid peroxidation. The resulting tocopheroxyl radical is relatively stable and can be regenerated back to alpha-tocopherol by ascorbate (vitamin C), coenzyme Q10, glutathione, and other reductants. This is the classic "alpha-tocopherol is the front-line membrane antioxidant" picture taught in undergraduate biochemistry.
- Location matters – Alpha-tocopherol partitions into the phospholipid bilayer of cell membranes and into the surface monolayer of lipoprotein particles, including low-density lipoprotein. Each low-density lipoprotein particle carries roughly 6 to 12 alpha-tocopherol molecules, sitting at the lipid-water interface where peroxyl radicals attack the polyunsaturated fatty acids of the phospholipid surface.
- The oxidized-LDL hypothesis – Daniel Steinberg and colleagues at UC San Diego proposed in the late 1980s that native low-density lipoprotein is not particularly atherogenic. What drives atherosclerosis is oxidized low-density lipoprotein, which is taken up unregulated by macrophage scavenger receptors (CD36, SR-A), turning macrophages into cholesterol-loaded foam cells — the cellular signature of early atherosclerotic lesions. By this logic, anything that prevents low-density lipoprotein oxidation should slow atherogenesis. Vitamin E, sitting on the low-density lipoprotein surface, looked like the perfect candidate.
- Why the hypothesis was incomplete – Oxidized low-density lipoprotein is real, and it does promote foam-cell formation. But atherosclerosis involves many parallel processes — endothelial dysfunction, smooth muscle proliferation, inflammation, NLRP3 inflammasome activation, neutrophil extracellular traps, oxidized phospholipids signaling through TLR4 — and blocking one path with one antioxidant is unlikely to halt the disease. Alpha-tocopherol also fails to neutralize all oxidants. It is poor at scavenging reactive nitrogen species (peroxynitrite, NO2), which are major contributors to vascular inflammation and which gamma-tocopherol is better positioned to handle.
- Tocopherol-vitamin C recycling – Vitamin E and vitamin C work as a redox pair. Vitamin C in the aqueous phase regenerates oxidized vitamin E at the lipid-water interface. In experimental models, the cardioprotective effect of vitamin E is markedly enhanced when vitamin C is present at adequate levels, and high-dose vitamin E without adequate vitamin C can actually become pro-oxidant by leaving the membrane saturated with tocopheroxyl radicals that have no partner to recycle them. This is one mechanistic explanation for the disappointing results of alpha-tocopherol monotherapy.
Gamma-Tocopherol and Reactive Nitrogen Species
Gamma-tocopherol is the dominant form of vitamin E in the typical U.S. diet, largely because soybean oil, corn oil, and other commonly consumed seed oils are gamma-tocopherol rich. Plasma gamma-tocopherol concentrations in untreated Americans are typically 2 to 4 micromolar, while plasma alpha-tocopherol is around 25 to 35 micromolar. The natural ratio matters — and high-dose alpha-tocopherol supplementation disrupts it.
- Chemistry advantage – Gamma-tocopherol's chromanol ring has an unmethylated 5-position, giving it a structural feature that alpha-tocopherol lacks: the ability to trap reactive nitrogen species. When peroxynitrite (ONOO-) or nitrogen dioxide (NO2) attacks the 5-position, gamma-tocopherol forms 5-nitro-gamma-tocopherol — the same reaction does not occur with alpha-tocopherol because that position is already methylated. The body's plasma 5-nitro-gamma-tocopherol level is therefore a biomarker of in vivo reactive nitrogen species exposure.
- Relevance to atherosclerosis – Reactive nitrogen species are heavily implicated in endothelial dysfunction, vascular inflammation, and plaque instability. Macrophages and neutrophils generate peroxynitrite via the simultaneous production of superoxide and nitric oxide, especially in inflamed vessel walls. By neutralizing these species, gamma-tocopherol may protect against vascular inflammation in a way that alpha-tocopherol cannot.
- Anti-inflammatory effects – Gamma-tocopherol and its major metabolite gamma-CEHC (2,7,8-trimethyl-2-(beta-carboxyethyl)-6-hydroxychroman) suppress cyclooxygenase-2 (COX-2) activity, reducing prostaglandin E2 production in macrophages and epithelial cells. Several preclinical studies show that gamma-tocopherol-rich mixed tocopherol preparations reduce C-reactive protein, interleukin-6 (IL-6), and tumor necrosis factor-alpha in inflammation models — effects that pure alpha-tocopherol either lacks or shows weakly.
- The displacement issue, restated – Qing Jiang, Maret Traber, Bruce Ames, and colleagues showed in the 2000s that high-dose alpha-tocopherol supplementation depletes plasma and tissue gamma-tocopherol by 30 to 50 percent. If gamma-tocopherol is doing protective work, then trials of alpha-tocopherol monotherapy may have inadvertently removed the very molecule that mattered. This is a leading hypothesis for why mixed natural tocopherols outperform pure alpha-tocopherol in many surrogate-endpoint cardiovascular studies.
- Wagner et al. review – A 2004 review by Wagner, Kamal-Eldin, and Elmadfa in Annals of Nutrition and Metabolism summarized the gamma-tocopherol literature and argued that the food-pattern observational data were closer to a test of "all tocopherols, gamma-rich" while the randomized controlled trials were closer to a test of "pure alpha at pharmacologic dose, gamma depleted." The two interventions were essentially different molecules, and there is no logical inconsistency in observing benefit from the first and null from the second.
Tocotrienols and Cholesterol
Tocotrienols are the four-double-bond cousins of tocopherols. They are concentrated in the bran of rice and barley, in palm oil, and most cleanly in annatto seed extract (which is essentially pure delta- and gamma-tocotrienol with no tocopherol contamination). Tocotrienols have a different set of bioactivities than tocopherols — some of them clinically relevant for cardiovascular disease.
- HMG-CoA reductase suppression – A. Asaf Qureshi and colleagues showed in the 1980s and 1990s that delta- and gamma-tocotrienol post-transcriptionally suppress HMG-CoA reductase, the rate-limiting enzyme in cholesterol biosynthesis — the same target as statin drugs, but through a different molecular mechanism. Tocotrienols increase the rate of HMG-CoA reductase degradation and reduce its translation, lowering hepatic cholesterol synthesis. The effect is selective for delta- and gamma-tocotrienol; alpha-tocopherol actually antagonizes this effect, which is why tocopherol-rich tocotrienol preparations (e.g., from palm oil) produce smaller lipid effects than tocopherol-free annatto preparations.
- Annatto-source tocotrienol research – The cleanest tocotrienol randomized controlled trials use annatto-source delta- and gamma-tocotrienol (a tocotrienol supplement), typically dosed at 125 to 300 mg per day. Trials by Barrie Tan, Chandan Sen, and others have reported total cholesterol reductions of 10 to 17 percent and low-density lipoprotein reductions of 10 to 24 percent, alongside reductions in C-reactive protein and improvements in endothelial function. The effect size is modest compared to statins, but the safety profile is excellent and the mechanism is complementary. Researchers in this field have reported reductions in C-reactive protein and improvements in endothelial function. For cholesterol itself, a 2020 meta-analysis that pooled 15 randomized trials found that tocotrienols did not lower total cholesterol, low-density lipoprotein cholesterol or triglycerides overall; they did raise high-density lipoprotein (HDL, the “good” cholesterol) by about 0.15 mmol/L.
- What the pooled trials show and what is not known – In that 2020 meta-analysis (Zuo and colleagues), the rise in high-density lipoprotein was larger at doses of 200 mg a day or more (about 0.20 mmol/L) and in trials of 8 weeks or less, and the trials at 200 mg a day or more showed a small fall in triglycerides (about 0.18 mmol/L). The trials differed a great deal from each other, and none measured heart attacks or strokes, so whether these blood-fat changes protect the heart is not known.
- Anti-inflammatory and endothelial effects – Tocotrienols suppress NF-kB activation in endothelial cells, reduce VCAM-1 and ICAM-1 expression (the adhesion molecules that recruit monocytes to the vessel wall), and improve flow-mediated dilation. These are mechanistically relevant for the earliest stages of atherosclerosis, before lipid accumulation begins.
- Why tocotrienols are not in the major cardiovascular randomized controlled trials – The 1990s and early-2000s mega-trials predate the modern tocotrienol literature and used tocopherol preparations only. There is no HOPE-scale randomized controlled trial (RCT) of tocotrienols and hard cardiovascular endpoints (myocardial infarction (MI), stroke, cardiovascular death). What exists is a moderate-quality literature of surrogate-endpoint trials (lipids, inflammation, IMT, flow-mediated dilation) suggesting benefit, plus mechanistic plausibility. This literature is the basis on which some practitioners use mixed tocopherol + tocotrienol preparations; it does not show that they prevent heart attacks, strokes or cardiovascular deaths.
- Sen and Khanna alpha-tocotrienol neuroprotection – Chandan Sen and Savita Khanna's work at Ohio State showed that alpha-tocotrienol at nanomolar concentrations protects neurons from glutamate-induced excitotoxicity through a mechanism distinct from alpha-tocopherol's antioxidant action — specifically by suppressing 12-lipoxygenase and c-Src activation. While the primary application is stroke, the same vascular-protective biology is relevant for atherosclerotic disease.
Major Cardiovascular Randomized Controlled Trials in Context
The cardiovascular randomized controlled trials of the 1990s and early 2000s are the historical reason vitamin E acquired its current "doesn't work and may be harmful" reputation. Understanding what they actually tested — and what they did not test — is essential to interpreting modern evidence.
- ATBC (Alpha-Tocopherol, Beta-Carotene Cancer Prevention Study), 1994 – 29,133 Finnish male smokers, 50 mg per day dl-alpha-tocopherol versus placebo, mean 6.1 years. Designed for lung cancer endpoint; cardiovascular events were secondary. No reduction in coronary mortality. A statistically significant increase in hemorrhagic stroke in the alpha-tocopherol arm (50% relative increase, small absolute number) raised the first major safety signal.
- CHAOS (Cambridge Heart Antioxidant Study), 1996 – 2,002 patients with angiographically proven coronary atherosclerosis, randomized to 400 or 800 international units per day natural alpha-tocopherol or placebo. Median follow-up 510 days. CHAOS reported a 47% reduction in its combined primary endpoint of cardiovascular death plus nonfatal myocardial infarction (heart attack) (41 vs 64 events, relative risk 0.53), driven by a 77% fall in nonfatal heart attack (14 vs 41, relative risk 0.23), with slightly more cardiovascular deaths in the vitamin E group (27 vs 23, not statistically significant). It remains the only major secondary-prevention randomized controlled trial with a clearly positive primary endpoint. The trial was small, short, and used the natural RRR form rather than synthetic. Subsequent larger trials did not reproduce the magnitude.
- GISSI-Prevenzione, 1999 – 11,324 Italian patients within 3 months of myocardial infarction, randomized 2x2 to 300 mg per day synthetic vitamin E, 1 g per day omega-3 (eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA)), both, or neither. The omega-3 arm reduced cardiovascular mortality; the vitamin E arm did not reach statistical significance for the primary combined endpoint. A factorial analysis suggested a modest reduction in cardiovascular death with vitamin E, but the trial is generally read as null.
- HOPE (Heart Outcomes Prevention Evaluation), 2000 – 9,541 patients with vascular disease or diabetes plus one additional risk factor, randomized to 400 international units per day natural alpha-tocopherol or placebo for 4.5 years. HOPE was the methodologically cleanest, largest, and most-quoted of the trials. The primary outcome (composite of myocardial infarction, stroke, and cardiovascular death) showed no benefit (relative risk (RR) 1.05, 95% confidence interval (CI) 0.95-1.16). HOPE-TOO, an extension that brought median follow-up to 7 years, similarly showed no benefit for major cardiovascular events (relative risk 1.04) or cancer, and a higher risk of heart failure (relative risk 1.13) and of hospitalization for heart failure (relative risk 1.21).
- Women's Health Study, 2005 – 39,876 healthy women aged 45 and older, 600 international units natural alpha-tocopherol every other day versus placebo, 10.1 years. Primary endpoint (composite cardiovascular events) showed no significant reduction: 482 major cardiovascular events in the vitamin E group against 517 on placebo (relative risk 0.93, not statistically significant). There was no effect on heart attack, stroke, cancer or total deaths. A secondary endpoint of cardiovascular death was reduced by 24% (relative risk 0.76, 95% confidence interval 0.59-0.98), but the overall trial is generally classified as null. Notably, the dose was modest (600 international units every other day, roughly 300 international units per day equivalent) and the population was healthy — the absolute event rate was low.
- Physicians' Health Study II, 2008 – 14,641 US male doctors aged 50 or older took 400 international units of vitamin E every other day or placebo, for a mean of 8 years. Vitamin E had no effect on major cardiovascular events (hazard ratio 1.01), heart attack, stroke or cardiovascular death, and it was linked to more hemorrhagic (bleeding) strokes (hazard ratio 1.74, 95% confidence interval 1.04-2.91).
- Why the null results are not the whole story – Every one of these trials tested synthetic or natural alpha-tocopherol as monotherapy. None tested mixed tocopherols. None tested tocotrienols. None pre-stratified on haptoglobin genotype (the strongest known cardiovascular vitamin E responder phenotype, see next section). Most used populations on aggressive secondary-prevention regimens (aspirin, statins, angiotensin-converting enzyme inhibitors (ACE inhibitors), beta-blockers) where the addition of any single antioxidant against an already-heavily-treated background is unlikely to show effect. The trials answered the question they were designed to answer — "does pharmacologic alpha-tocopherol monotherapy added to standard therapy reduce hard cardiovascular endpoints in mixed populations?" — and the answer was no. They did not answer the broader question of whether dietary vitamin E patterns or carefully chosen subgroups might benefit.
Modern Evidence — Subgroups That Benefit
The most important post-HOPE development in vitamin E cardiovascular research is the recognition that pharmacogenomic and metabolic subgroups respond very differently to alpha-tocopherol supplementation. The clearest signal is from the haptoglobin (Hp) genotype literature led by Andrew Levy at Technion.
- The haptoglobin Hp 2-2 phenotype – Haptoglobin is the plasma protein that binds free hemoglobin (released from lysed red cells) and prevents it from acting as a pro-oxidant. There are three common phenotypes: Hp 1-1, Hp 2-1, and Hp 2-2. The Hp 2-2 protein is structurally inferior at neutralizing free hemoglobin; in diabetes, where chronic hyperglycemia promotes hemoglobin release, Hp 2-2 individuals have markedly elevated oxidative stress in the vasculature.
- ICARE trial (Milman, Blum, Levy, 2008) – The Israel Cardiovascular Events Reduction with Vitamin E trial randomized 1,434 Hp 2-2 diabetic patients to 400 international units per day natural alpha-tocopherol or placebo. The participants were people with type 2 diabetes aged 55 or older who carry the Hp 2-2 genotype, a group the authors put at 2% to 3% of the general population. At the first look at the results, 18 months in, 2.2% of the vitamin E group had had a heart attack, stroke or cardiovascular death, against 4.7% on placebo. The trial was stopped early for efficacy; trials stopped early tend to overstate the size of an effect. This is the strongest single-RCT evidence for cardiovascular benefit of vitamin E in any defined population.
- Mechanistic plausibility – Hp 2-2 diabetics have elevated high-density lipoprotein-associated oxidative stress, with dysfunctional high-density lipoprotein (HDL) that promotes rather than prevents low-density lipoprotein oxidation. Alpha-tocopherol supplementation reverses high-density lipoprotein dysfunction in this specific population, restoring high-density lipoprotein's antioxidant capacity. The same dose has no benefit (and possibly slight harm) in Hp 1-1 diabetics, where high-density lipoprotein is already functional and additional alpha-tocopherol may disturb the redox balance.
- HOPE secondary analysis – Re-analysis of HOPE participants by Hp phenotype showed that the Hp 2-2 diabetic subgroup, which represented roughly 16% of the diabetic participants, had a 43% reduction in cardiovascular events with alpha-tocopherol — replicating the ICARE signal in an independent dataset. The overall null HOPE result therefore conceals a strongly positive subgroup result diluted by neutral and possibly slightly harmful effects in other subgroups.
- Clinical implication – Researchers in this field describe 400 international units per day of alpha-tocopherol for Hp 2-2 diabetic patients as a low-cost, mechanism-based intervention. Haptoglobin phenotyping is inexpensive and clinically available. This is an example of pharmacogenomic medicine applied to a "failed" supplement — an important reminder that population-level randomized controlled trials can mask large, real, replicable effects in genetically or metabolically defined subgroups.
- Other potential responder phenotypes – Beyond Hp 2-2 diabetes, candidate responder subgroups under active study include individuals with elevated baseline oxidative stress markers (oxidized low-density lipoprotein, F2-isoprostanes, myeloperoxidase), individuals with low baseline plasma alpha-tocopherol (under 12 micromolar), and individuals with specific apolipoprotein E genotypes. The evidence base is weaker than for Hp 2-2 but mechanistically reasonable.
Vitamin E and Atherosclerosis Progression
Hard endpoints (myocardial infarction, stroke, cardiovascular death) are not the only relevant outcomes. Atherosclerosis progression measured by carotid intima-media thickness (IMT), coronary artery calcium scoring, and similar surrogate markers gives a more sensitive readout of vascular biology over the timeframes that supplementation trials can practically run.
- Carotid IMT trials – Several small-to-medium randomized controlled trials have used carotid IMT progression as the primary endpoint. The VEAPS (Vitamin E Atherosclerosis Prevention Study) randomized 353 men and women aged 40 and older with low-density lipoprotein above 130 mg/dL to 400 international units per day synthetic dl-alpha-tocopherol or placebo for 3 years. The participants had no signs or symptoms of heart disease. Vitamin E raised blood vitamin E levels and lowered oxidized low-density lipoprotein in the blood, but IMT progression was not different between groups.
- HATS antioxidant arm – In the HDL-Atherosclerosis Treatment Study (HATS), 153 people with coronary artery disease and low high-density lipoprotein took simvastatin plus niacin, an antioxidant cocktail (vitamins E and C, beta-carotene and selenium), both, or placebo for 12 months. With the antioxidants added, the rise in the HDL2 fraction of high-density lipoprotein fell from 42% to 0%, suggesting potential interference between supplemental alpha-tocopherol and niacin's high-density lipoprotein-raising mechanism — a counterintuitive finding that helped reshape thinking about antioxidant-statin and antioxidant-niacin interactions.
- Plasma observational data – Higher plasma alpha-tocopherol concentrations were reported to be associated with lower coronary heart disease mortality in dose-response fashion, even after adjustment for traditional risk factors and dietary patterns. Plasma alpha-tocopherol reflects dietary intake plus stable supplementation; it is a different measurement than the pharmacologic spike produced by acute high-dose intervention.
- Mixed tocopherol surrogate-endpoint trials – Several smaller trials of mixed tocopherol preparations (containing gamma- and delta-tocopherol alongside alpha-) report more favorable surrogate-marker results than equivalent-dose pure alpha-tocopherol trials. Effects include reductions in F2-isoprostanes, oxidized low-density lipoprotein, soluble vascular cell adhesion molecule-1, and improvements in flow-mediated dilation. The trials are too small and short for hard-endpoint inference, but they are consistent with the broader mechanistic argument that mixed tocopherols outperform pure alpha.
- The realistic interpretation – Vitamin E supplementation is unlikely to halt atherosclerosis progression as a single intervention in mixed populations. It may modestly slow progression in subgroups with elevated baseline oxidative stress. It may contribute — as part of a broader pattern that includes vitamin C, selenium, omega-3 fatty acids, magnesium, and a low-refined-carbohydrate diet — to vascular biology that is meaningfully different than no intervention at all. None of this constitutes a "vitamin E is proven to prevent heart disease" claim, but it also does not support the popular "vitamin E is useless or harmful" narrative.
Practical Dosing and Form
The contemporary, evidence-aware approach to vitamin E for cardiovascular health prioritizes food first, then carefully chosen supplement form if supplementation is desired, with attention to cofactors.
- Food sources – The highest practical food sources of vitamin E are sunflower seeds (approximately 35 mg of alpha-tocopherol per 100 g, mostly alpha), almonds (26 mg per 100 g, mostly alpha), hazelnuts (15 mg per 100 g), wheat germ oil (149 mg per 100 g, the densest natural source), and avocado (2.07 mg per 100 g, USDA). Common U.S. dietary patterns are gamma-tocopherol heavy due to soybean and corn oils. A small daily handful of mixed nuts and seeds will reliably provide 10 to 20 mg of mixed tocopherols in a natural matrix with fiber, magnesium, and the fats needed for absorption.
- Mixed tocopherols as a supplement form – The mechanistic argument and the modern surrogate-endpoint trials both favor mixed natural tocopherol preparations (containing alpha-, gamma-, and delta-tocopherol) over pure alpha-tocopherol. Such preparations are labeled "mixed tocopherols" and usually state the gamma-tocopherol content (typically 100 to 200 mg per dose). Synthetic dl-alpha-tocopherol on its own is the form the large null trials mostly tested.
- Tocotrienols as an add-on – Annatto-source delta- and gamma-tocotrienol preparations are sold at 125 to 300 mg per day for the bioactivities described above that tocopherols do not have (the pooled trials did not show lower total or low-density lipoprotein cholesterol). Because alpha-tocopherol can interfere with tocotrienol absorption, practitioners who use both describe taking them at different meals, 6 to 8 hours apart.
- Dose range – Supplement doses of 200 to 400 international units per day of mixed tocopherols (equivalent to roughly 134 to 268 mg of natural alpha-tocopherol) are common. The Miller 2005 meta-analysis placed its mortality signal at 400 international units per day or more (9 of 11 such trials showed more deaths with vitamin E, an extra 39 deaths per 10,000 people), and its dose-response analysis showed rising risk above 150 international units per day; the top of that common range is therefore inside the dose group the meta-analysis flagged. Doses above 400 international units per day of synthetic alpha-tocopherol have no demonstrated cardiovascular benefit and a small adverse signal.
- Absorption needs fat – Vitamin E is fat-soluble and requires dietary fat for absorption. A meal containing at least 5 to 10 g of fat is the figure commonly given for supplements; taken on an empty stomach, absorption is erratic and incomplete.
- Cofactor synergy – Selenium is required for the glutathione peroxidase enzymes that work alongside vitamin E to handle lipid hydroperoxides. Vitamin C in the aqueous phase regenerates oxidized vitamin E at the lipid-water interface. Adequate magnesium supports the overall antioxidant defense network. These nutrients work together rather than as individual supplements.
- Rationale against high-dose synthetic alpha – The accumulated evidence weighs strongly against high-dose (above 400 international units per day) synthetic dl-alpha-tocopherol monotherapy. This is the intervention that the major randomized controlled trials tested with null results and the meta-analysis flagged for a small mortality signal. There is no longer a serious mechanistic or empirical case for this specific regimen.
Cautions and Drug Interactions
- Warfarin and other anticoagulants – Vitamin E at doses above approximately 400 international units per day has antiplatelet activity and at higher doses appears to antagonize vitamin K-dependent clotting factor synthesis, potentiating the effect of warfarin. Food-pattern intake is generally not a problem; high-dose supplements are, and changes in supplement use can shift the international normalized ratio (INR, the blood-clotting test used to adjust warfarin). The Institute of Medicine's 2000 report notes that people on anticoagulant therapy are at increased risk of clotting problems with vitamin E supplements and that they were monitored when taking them.
- Antiplatelet drugs – The combination of high-dose vitamin E with aspirin, clopidogrel, prasugrel, or ticagrelor can additively increase bleeding risk. This is particularly relevant in elderly patients and in patients with prior gastrointestinal bleeding. The increment is small at 200 to 400 international units per day of mixed tocopherols but real.
- Surgery washout – Most surgical teams ask patients to stop vitamin E supplementation 2 weeks before elective surgery to reduce the risk of bleeding during and after the operation.
- Statin interaction – The interaction between vitamin E and statins is complex. An antioxidant cocktail containing vitamin E, added to simvastatin and niacin, blunted the high-density lipoprotein-raising effect of niacin in the HATS trial — an unexpected adverse signal that helped sour clinician opinion. Statins themselves slightly reduce plasma alpha-tocopherol; the mechanistic interaction goes both ways. No trial has shown that adding high-dose vitamin E gives extra benefit to people taking statins for established coronary disease.
- Vitamin K antagonism at high doses – At doses above approximately 1000 international units per day, alpha-tocopherol can interfere with vitamin K-dependent gamma-carboxylation, slightly increasing prothrombin time. This is a dose-dependent effect with no clinical consequence at standard mixed-tocopherol doses but a real concern at the pharmacologic doses (1200 to 2000 international units per day) that have been used in some clinical settings.
- Hemorrhagic stroke signal – The ATBC trial reported a statistically significant increase in hemorrhagic stroke in the alpha-tocopherol arm (small absolute numbers but real signal). The signal is most concerning in male smokers, in older patients with hypertension, and at doses above 400 international units per day. It is less concerning at food-pattern intake and at modest mixed-tocopherol supplementation. The research raises the greatest concern for people with a prior hemorrhagic stroke, uncontrolled high blood pressure, or cerebral amyloid angiopathy taking high-dose vitamin E.
- Stroke subtypes in the pooled trials – A 2010 meta-analysis in the BMJ of 9 randomized trials (118,765 people) found that vitamin E did not change the risk of stroke overall (relative risk 0.98), but raised the risk of hemorrhagic (bleeding) stroke by 22% (relative risk 1.22) and lowered the risk of ischemic (clot) stroke by 10% (relative risk 0.90). In absolute terms, that is about one extra bleeding stroke for every 1,250 people taking vitamin E, against one clot stroke prevented for every 476. The authors noted that bleeding strokes are generally the more severe kind.
- Mortality meta-analysis context – The Miller 2005 meta-analysis in Annals of Internal Medicine suggested a small increase in all-cause mortality at doses above 400 international units per day. The meta-analysis was dominated by trials in chronically ill populations on multiple medications, and subsequent analyses have suggested the signal may not generalize to healthier populations or to mixed-tocopherol preparations. Nonetheless, doses of 400 international units per day or more have no demonstrated cardiovascular benefit and carry a small possible harm in this analysis.
- The official upper limit – The Institute of Medicine's 2000 Dietary Reference Intakes set the Tolerable Upper Intake Level for adults at 1,000 mg a day of any form of supplemental alpha-tocopherol, based on an increased tendency to bleed.
This content is provided for informational purposes only and does not constitute medical advice. The bleeding interactions above matter most for people taking anticoagulant or antiplatelet medication and for people planning surgery.
Where the Official Guidance Stands Today
In 2022 the US Preventive Services Task Force, the US panel that reviews prevention evidence, concluded “with moderate certainty that there is no net benefit of supplementation with vitamin E for the prevention of cardiovascular disease or cancer.” It recommends against vitamin E supplements for that purpose (a grade D recommendation) for community-dwelling adults who are not pregnant. The statement covers prevention in the general adult population; it does not address vitamin E from food, or people with a diagnosed vitamin E deficiency.
Key Research Papers
The following are landmark and frequently cited peer-reviewed research papers underpinning the claims on this page. Links resolve to the publisher DOI or to PubMed.
- Yusuf S, Dagenais G, Pogue J, Bosch J, Sleight P (HOPE Investigators). Vitamin E supplementation and cardiovascular events in high-risk patients. New England Journal of Medicine. 2000;342(3):154-160. — doi:10.1056/NEJM200001203420302 · PubMed PMID: 10639540
- GISSI-Prevenzione Investigators. Dietary supplementation with n-3 polyunsaturated fatty acids and vitamin E after myocardial infarction: results of the GISSI-Prevenzione trial. Lancet. 1999;354(9177):447-455. — doi:10.1016/S0140-6736(99)07072-5 · PubMed PMID: 10465168
- The Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. New England Journal of Medicine. 1994;330(15):1029-1035. — doi:10.1056/NEJM199404143301501 · PubMed PMID: 8127329
- Stephens NG, Parsons A, Schofield PM, Kelly F, Cheeseman K, Mitchinson MJ. Randomised controlled trial of vitamin E in patients with coronary disease: Cambridge Heart Antioxidant Study (CHAOS). Lancet. 1996;347(9004):781-786. — doi:10.1016/S0140-6736(96)90866-1 · PubMed PMID: 8622332
- Lee IM, Cook NR, Gaziano JM, et al. Vitamin E in the primary prevention of cardiovascular disease and cancer: the Women's Health Study: a randomized controlled trial. JAMA. 2005;294(1):56-65. — doi:10.1001/jama.294.1.56 · PubMed PMID: 15998891
- Milman U, Blum S, Shapira C, et al. Vitamin E supplementation reduces cardiovascular events in a subgroup of middle-aged individuals with both type 2 diabetes mellitus and the haptoglobin 2-2 genotype: a prospective double-blinded clinical trial. Arteriosclerosis, Thrombosis, and Vascular Biology. 2008;28(2):341-347. — doi:10.1161/ATVBAHA.107.153965 · PubMed PMID: 18032779
- Levy AP, Gerstein HC, Miller-Lotan R, et al. The effect of vitamin E supplementation on cardiovascular risk in diabetic individuals with different haptoglobin phenotypes. Diabetes Care. 2004;27(11):2767. — doi:10.2337/diacare.27.11.2767 · PubMed PMID: 15505023
- Wagner KH, Kamal-Eldin A, Elmadfa I. Gamma-tocopherol — an underestimated vitamin? Annals of Nutrition and Metabolism. 2004;48(3):169-188. — doi:10.1159/000079555 · PubMed PMID: 15256801
- Jiang Q, Christen S, Shigenaga MK, Ames BN. Gamma-tocopherol, the major form of vitamin E in the US diet, deserves more attention. American Journal of Clinical Nutrition. 2001;74(6):714-722. — doi:10.1093/ajcn/74.6.714 · PubMed PMID: 11722951
- Sen CK, Khanna S, Roy S. Tocotrienols: vitamin E beyond tocopherols. Life Sciences. 2006;78(18):2088-2098. — doi:10.1016/j.lfs.2005.12.001 · PubMed PMID: 16458936
- Qureshi AA, Sami SA, Salser WA, Khan FA. Synergistic effect of tocotrienol-rich fraction (TRF(25)) of rice bran and lovastatin on lipid parameters in hypercholesterolemic humans. Journal of Nutritional Biochemistry. 2001;12(6):318-329. — doi:10.1016/s0955-2863(01)00144-9 · PubMed PMID: 11516635
- Miller ER 3rd, Pastor-Barriuso R, Dalal D, Riemersma RA, Appel LJ, Guallar E. Meta-analysis: high-dosage vitamin E supplementation may increase all-cause mortality. Annals of Internal Medicine. 2005;142(1):37-46. — doi:10.7326/0003-4819-142-1-200501040-00110 · PubMed PMID: 15537682
- Steinberg D, Parthasarathy S, Carew TE, Khoo JC, Witztum JL. Beyond cholesterol. Modifications of low-density lipoprotein that increase its atherogenicity. New England Journal of Medicine. 1989;320(14):915-924. — doi:10.1056/NEJM198904063201407 · PubMed PMID: 2648148
- Lonn E, Bosch J, Yusuf S, et al (HOPE and HOPE-TOO Trial Investigators). Effects of long-term vitamin E supplementation on cardiovascular events and cancer: a randomized controlled trial. JAMA. 2005;293(11):1338-1347. — doi:10.1001/jama.293.11.1338 · PubMed PMID: 15769967
- Cheung MC, Zhao XQ, Chait A, Albers JJ, Brown BG. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arteriosclerosis, Thrombosis, and Vascular Biology. 2001;21(8):1320-1326. — doi:10.1161/hq0801.095151 · PubMed PMID: 11498460
- Hodis HN, Mack WJ, LaBree L, et al (VEAPS Research Group). Alpha-tocopherol supplementation in healthy individuals reduces low-density lipoprotein oxidation but not atherosclerosis: the Vitamin E Atherosclerosis Prevention Study (VEAPS). Circulation. 2002;106(12):1453-1459. — doi:10.1161/01.cir.0000029092.99946.08 · PubMed PMID: 12234947
- Zuo S, Wang G, Han Q, et al. The effects of tocotrienol supplementation on lipid profile: A meta-analysis of randomized controlled trials. Complementary Therapies in Medicine. 2020;52:102450. — doi:10.1016/j.ctim.2020.102450 · PubMed PMID: 32951713
- Sesso HD, Buring JE, Christen WG, et al. Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomized controlled trial. JAMA. 2008;300(18):2123-2133. — doi:10.1001/jama.2008.600 · PubMed PMID: 18997197
- Schürks M, Glynn RJ, Rist PM, Tzourio C, Kurth T. Effects of vitamin E on stroke subtypes: meta-analysis of randomised controlled trials. BMJ. 2010;341:c5702. — doi:10.1136/bmj.c5702 · PubMed PMID: 21051774
- US Preventive Services Task Force; Mangione CM, Barry MJ, Nicholson WK, et al. Vitamin, Mineral, and Multivitamin Supplementation to Prevent Cardiovascular Disease and Cancer: US Preventive Services Task Force Recommendation Statement. JAMA. 2022;327(23):2326-2333. — doi:10.1001/jama.2022.8970 · PubMed PMID: 35727271
External Authoritative Resources
- NIH Office of Dietary Supplements — Vitamin E Fact Sheet for Health Professionals
- Linus Pauling Institute — Vitamin E
- Harvard T.H. Chan School of Public Health — The Nutrition Source: Vitamin E
- Institute of Medicine (2000). Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids — Vitamin E chapter (Tolerable Upper Intake Level)