Vitamin D3 for Bone Health & Fracture Prevention
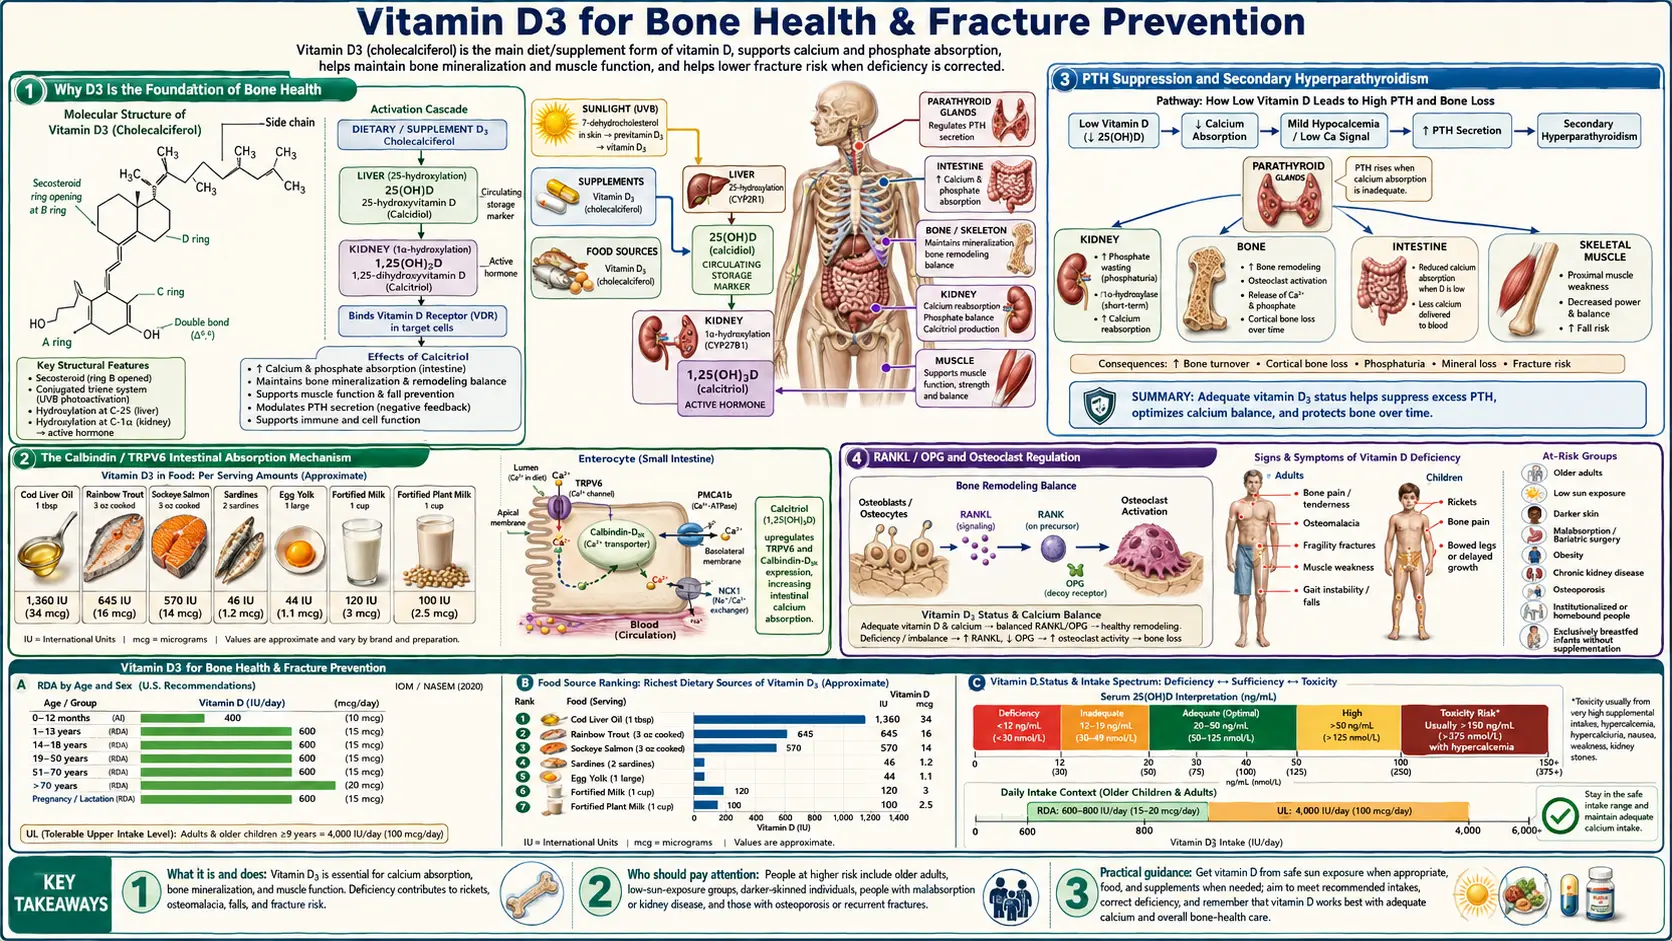
Bone health is the classical — and best-established — indication for vitamin D3. The fundamental mechanism is that calcitriol (the active hormonal form) drives the transcription of calbindin-D9k and TRPV6 in the intestinal brush border, which raises dietary calcium absorption from 10-15% to 30-40%. Without adequate D3, even abundant calcium intake cannot reach the bloodstream or be deposited into bone. But the picture is more nuanced than the mainstream "calcium + D" framing. Integrative practitioners describe vitamin K2, magnesium and vitamin A as cofactors of D3 and hold, as a mechanistic view, that D3 given without them can promote arterial calcification; in the trial evidence, the kidney-stone signal came from calcium plus D3 (a 17% higher risk of kidney stones in the Women's Health Initiative trial). The protocol these practitioners describe is a quartet: D3 + K2-MK7 + magnesium + adequate calcium from food, with a 25(OH)D target of 40-60 ng/mL for skeletal outcomes; no trial cited on this page tested the four together. This deep-dive walks through the Bischoff-Ferrari fracture meta-analyses, the large trials that did not find fewer fractures, the calbindin/TRPV6/PTH/RANKL-OPG mechanism stack, and the osteoporosis protocol described in integrative practice.
Table of Contents
- Why D3 Is the Foundation of Bone Health
- The Calbindin / TRPV6 Intestinal Absorption Mechanism
- Parathyroid Hormone Suppression and Secondary Hyperparathyroidism
- RANKL / OPG and Osteoclast Regulation
- The Bischoff-Ferrari Fracture Meta-Analyses
- Fall Prevention and Neuromuscular Function
- The Quartet Described in Integrative Practice: D3 + K2 + Magnesium + Calcium
- Why K2 Without D3 (or D3 Without K2) Is Incomplete
- 25(OH)D Target Levels for Skeletal Outcomes
- Osteoporosis Protocol Described in Integrative Practice
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Why D3 Is the Foundation of Bone Health
The skeletal system is in constant turnover — an adult human replaces approximately 10% of skeletal mass every year through the coordinated activity of osteoblasts (bone-forming cells) and osteoclasts (bone-resorbing cells). For osteoblasts to deposit hydroxyapatite crystals into the collagen matrix, two raw materials must be present in adequate concentrations in the extracellular fluid: calcium and phosphorus. Vitamin D3 is the master regulator of both.
Severe D3 deficiency in children produces rickets — bowed legs, widened wrists, frontal bossing of the skull, delayed fontanelle closure, dental defects. Severe deficiency in adults produces osteomalacia, the soft-bone equivalent that often presents as diffuse bone pain and proximal muscle weakness that is misdiagnosed as fibromyalgia. Modest D3 deficiency over decades produces osteoporosis — the progressive loss of bone mineral density that culminates in fragility fractures of the hip, spine, and wrist.
Hip fractures in particular are catastrophic events: roughly 20% of patients over 65 die within one year of a hip fracture, and a substantial fraction of survivors never regain prior mobility. Preventing the fracture in the first place is one of the highest-leverage interventions in geriatric medicine, and adequate vitamin D status is the most cost-effective component of that prevention.
For the broader clinical picture of bone disease, see our Osteoporosis page. For the synergistic partners, see Vitamin K and Magnesium.
The Calbindin / TRPV6 Intestinal Absorption Mechanism
Dietary calcium is absorbed in the small intestine through two parallel pathways:
- Paracellular (passive) absorption — calcium ions diffuse between enterocytes through tight junctions. This pathway accounts for absorption when dietary calcium is abundant but is unregulated — the gut absorbs only what passively diffuses.
- Transcellular (active) absorption — calcium enters enterocytes through the apical TRPV6 calcium channel, is shuttled across the cell bound to calbindin-D9k (which prevents toxic intracellular calcium accumulation), and is extruded across the basolateral membrane by the PMCA1b plasma membrane Ca-ATPase and the NCX1 Na/Ca exchanger. This pathway is the one that is upregulated by calcitriol.
Calcitriol binds its nuclear receptor (VDR), which heterodimerizes with the Retinoid X Receptor (RXR) and binds Vitamin D Response Elements (VDREs) in the promoter regions of the genes encoding calbindin-D9k, TRPV6, PMCA1b, and the basolateral exchanger. Within hours of vitamin D action, transcription of all four genes increases dramatically, and the intestinal absorption efficiency of dietary calcium rises from a baseline of roughly 10-15% (in vitamin D deficiency) to 30-40% (in repletion).
This is why "take more calcium" without addressing vitamin D status is largely futile. A 1,500 mg dietary calcium intake in a deficient individual delivers only 150-225 mg of absorbed calcium to the bloodstream. The same intake in a vitamin D-replete individual delivers 450-600 mg — a three- to four-fold increase from the identical diet, achieved entirely through gene-expression changes in the intestinal epithelium.
The phosphorus story is parallel: calcitriol upregulates the NaPi-IIb sodium-phosphate cotransporter in the intestinal brush border, improving phosphate absorption. Adequate serum phosphate is critical because hydroxyapatite, the mineral phase of bone, is calcium-phosphate.
Parathyroid Hormone Suppression and Secondary Hyperparathyroidism
The parathyroid glands continuously sample blood calcium and adjust the secretion of parathyroid hormone (PTH) to maintain serum calcium within a narrow range. When blood calcium falls (because dietary absorption is inadequate from D3 deficiency), parathyroid hormone rises — and parathyroid hormone mobilizes calcium from bone to restore blood levels.
This is a critical adaptive mechanism for acute calcium emergencies, but when it operates chronically — as in long-standing D3 deficiency — it produces secondary hyperparathyroidism, a state in which parathyroid hormone is chronically elevated and bone is steadily being decalcified to maintain blood calcium. This is one of the principal mechanisms by which vitamin D deficiency drives osteoporosis.
Vitamin D3 suppresses parathyroid hormone through two mechanisms: directly via VDR-mediated repression of the parathyroid hormone gene in parathyroid cells, and indirectly by raising blood calcium so the calcium-sensing receptor on parathyroid cells signals "calcium is adequate, stand down." Restoring 25(OH)D to the 30-50 ng/mL range typically brings parathyroid hormone from the elevated 80-150 pg/mL range (secondary hyperparathyroidism) down to the desirable 20-40 pg/mL range within 8-16 weeks.
Clinically, the response of parathyroid hormone to D3 repletion is one of the better biomarkers of "adequate" vitamin D status — when parathyroid hormone stops dropping with additional D3, the body is signaling that bone-relevant D3 sufficiency has been reached.
RANKL / OPG and Osteoclast Regulation
Bone turnover is governed by the balance between two cytokines produced by osteoblasts:
- RANKL (Receptor Activator of NF-κB Ligand) — activates osteoclasts, driving bone resorption
- OPG (osteoprotegerin) — a decoy receptor that binds RANKL and prevents it from activating osteoclasts, slowing bone resorption
The ratio of RANKL to OPG determines whether bone is in net resorption (RANKL dominant) or in net building (OPG dominant). Calcitriol has complex, context-dependent effects on this axis: in conditions of dietary calcium scarcity, calcitriol upregulates RANKL to mobilize calcium from bone (an evolved emergency mechanism). In conditions of calcium sufficiency, calcitriol shifts the ratio toward OPG, favoring bone preservation.
The clinical implication is that vitamin D supplementation produces the best bone outcomes when calcium intake is also adequate — isolated D3 supplementation in calcium-deficient individuals can theoretically accelerate bone loss through inappropriate RANKL upregulation. In the Women's Health Initiative (WHI) calcium-and-D trial, the combination raised hip bone density slightly but did not significantly reduce hip fracture (details below); D3 monotherapy is harder to interpret.
Practitioners describe this as one mechanism by which the calcium-K2-D3 combination could outperform calcium-D3 alone: K2 activates osteocalcin, which directs calcium into the hydroxyapatite matrix, biasing the system toward bone building rather than serum calcium maintenance.
What the largest calcium-plus-D trial found. In the Women's Health Initiative, 36,282 postmenopausal women aged 50 to 79 took 1,000 mg of calcium (as calcium carbonate) plus 400 international units of vitamin D3 daily, or placebo, for an average of 7 years. Hip bone density ended 1.06% higher with calcium plus D, but hip fractures were not significantly reduced (hazard ratio 0.88, 95% confidence interval 0.72 to 1.08), and the risk of kidney stones rose by 17% (hazard ratio 1.17). Among women who kept taking the pills, hip fractures were 29% lower (hazard ratio 0.71). The authors concluded that the supplements gave a small but significant improvement in hip bone density, did not significantly reduce hip fracture, and increased the risk of kidney stones (Jackson 2006).
The Bischoff-Ferrari Fracture Meta-Analyses
Heike Bischoff-Ferrari (Zurich) is the principal investigator who established the modern dose-response evidence for vitamin D in fracture prevention. Two pivotal meta-analyses anchor the literature:
Bischoff-Ferrari 2009 (Archives of Internal Medicine)
Pooled analysis of 12 double-blind randomized controlled trials (RCTs) of vitamin D supplementation for nonvertebral fracture prevention. The key finding was a clear dose-response: low-dose vitamin D (400 international units (IU)/day, the doses used in older trials) produced no significant fracture reduction. Higher-dose vitamin D (482-770 international units/day, with achieved 25(OH)D of approximately 30 ng/mL or higher) produced a 20% reduction in nonvertebral fractures and a 18% reduction in hip fractures.
This meta-analysis was clinically important because it explained the apparent contradiction in earlier literature: trials using inadequate doses (and not measuring achieved 25(OH)D levels) had produced null results that led clinicians to dismiss D3 supplementation, while adequate-dose trials consistently showed fracture reduction.
Bischoff-Ferrari 2012 (NEJM)
Individual-patient-data pooled analysis of 11 double-blind randomized controlled trials in people aged 65 or older (n = 31,022; mean age 76; 91% women). Simply being assigned to vitamin D, compared with placebo or calcium alone, gave a 10% reduction in hip fracture that was not statistically significant (hazard ratio 0.90, 95% confidence interval 0.80 to 1.01) and a 7% reduction in any nonvertebral fracture (hazard ratio 0.93). When people were grouped into quartiles by how much vitamin D they actually took, fracture reduction appeared only in the highest quartile (median 800 international units/day; range 792 to 2,000): a 30% reduction in hip fracture and a 14% reduction in any nonvertebral fracture compared with the control groups. The lower three quartiles showed no significant benefit. The authors concluded that 800 international units/day or more was "somewhat favorable" for preventing hip and nonvertebral fractures in people 65 and older — well above the conventional 400 international units recommendation.
Subsequent work has refined this further: achieved 25(OH)D of 30-44 ng/mL is associated with the lowest hip fracture risk, and the relationship plateaus above 44 ng/mL. This is the basis for the 40-60 ng/mL target range now used in integrative practice for bone outcomes.
The VITAL Trial (2022, NEJM)
In the VITAL trial, 25,871 U.S. adults (men aged 50 and over, women aged 55 and over) who were not chosen for low vitamin D, low bone mass or osteoporosis took 2,000 international units of vitamin D3 a day or placebo for a median of 5.3 years. Vitamin D3 did not lower total fractures (hazard ratio 0.98), nonvertebral fractures (hazard ratio 0.97) or hip fractures (hazard ratio 1.01) compared with placebo, and the result did not change with age, sex, race, body-mass index or starting blood 25-hydroxyvitamin D level (LeBoff 2022).
Fall Prevention and Neuromuscular Function
Hip fractures in the elderly are not purely a bone-fragility phenomenon — they require both fragile bone and a fall. Vitamin D contributes to fracture prevention through both mechanisms: it strengthens bone (the mechanism discussed above) and it reduces fall risk by improving neuromuscular function.
VDRs are expressed in skeletal muscle, and calcitriol directly regulates muscle protein synthesis and intramuscular calcium handling. Vitamin D deficiency produces proximal muscle weakness — difficulty rising from a chair, climbing stairs, or maintaining single-leg balance. These deficits are subtle, often attributed to aging, and reversible with D3 repletion.
A 2009 meta-analysis of 8 double-blind fall-prevention trials (2,426 older people, mean age 65 or older) found that vitamin D supplementation at 700-1000 international units/day reduced fall risk by 19% (relative risk 0.81); lower doses did not notably reduce falls. The effect is more pronounced in those starting from lower baseline 25(OH)D levels. The mechanism is improvement in lower-extremity strength, postural sway, and reaction time — all VDR-dependent in muscle.
The combined effect of fracture-reduction (bone strengthening) plus fall-reduction (muscle strengthening) is why vitamin D is one of the few single interventions that has reduced hip fracture in some randomized trials and pooled analyses, mainly of people 65 and older taking about 800 international units a day or more; in the VITAL trial of generally healthy midlife and older adults not selected for deficiency, 2,000 international units a day did not lower fractures.
The Quartet Described in Integrative Practice: D3 + K2 + Magnesium + Calcium
Integrative practitioners describe isolated vitamin D supplementation as incomplete and describe a bone-protective quartet; no trial cited on this page tested the four together. The doses below are the ones these practitioners describe:
| Nutrient | Role | Typical Dose |
|---|---|---|
| Vitamin D3 | Drives intestinal calcium absorption (calbindin/TRPV6), suppresses parathyroid hormone, supports muscle function | 2,000-5,000 international units/day |
| Vitamin K2 (menaquinone-7, MK-7) | Activates osteocalcin (directs calcium into bone) and matrix Gla protein (keeps calcium out of arteries) | 100-200 mcg/day |
| Magnesium | Cofactor for the enzymes that hydroxylate D3 to 25(OH)D and 1,25(OH)2D; cofactor for osteoblast function | 300-500 mg/day elemental (glycinate or citrate) |
| Calcium | Raw material for hydroxyapatite; ideally from food (dairy, leafy greens, sardines, almonds) | 1,000-1,200 mg/day total intake (food preferred over supplements) |
A fifth nutrient, boron, deserves mention — it influences vitamin D metabolism and bone matrix protein activity. Trace amounts (3-10 mg/day) from prunes, raisins, almonds, and avocados are typically sufficient; supplementation is rarely required.
Why K2 Without D3 (or D3 Without K2) Is Incomplete
Vitamin K2 (the menaquinone family, most studied as menaquinone-4 (MK-4) from animal foods and menaquinone-7 from fermented foods like natto) is the activator of two Gla-protein enzymes critical to bone and cardiovascular health:
- Osteocalcin — produced by osteoblasts; when K2-activated (carboxylated), it binds calcium and directs it into the hydroxyapatite matrix of bone
- Matrix Gla Protein (MGP) — produced by vascular smooth muscle cells; when K2-activated, it prevents calcium deposition in arterial walls
Both osteocalcin and MGP are produced at rates that depend on vitamin D — calcitriol upregulates their gene transcription — but they are activated by vitamin K2-dependent carboxylation. In K2 deficiency, osteocalcin and MGP are produced but remain inactive (uncarboxylated), so the calcium that D3 brought across the intestinal epithelium has nowhere to go: it accumulates in soft tissues and arterial walls rather than being deposited into bone.
Practitioners point to this mechanism to explain reports that isolated vitamin D supplementation, especially at high doses, may increase arterial calcification — a mechanistic view that the studies cited on this page do not test directly. The Rotterdam Study and other epidemiological data show that high K2 intake (especially menaquinone-7) is associated with significantly reduced cardiovascular mortality and reduced arterial calcification — effects that are likely synergistic with vitamin D rather than independent of it.
Integrative practitioners therefore pair high-dose D3 with K2-MK7. The ratio they describe is 100-200 mcg menaquinone-7 per 2,000-5,000 international units of D3; for very high D3 doses (10,000+ international units/day as used in the Coimbra autoimmune protocol), they describe scaling K2 up proportionally.
25(OH)D Target Levels for Skeletal Outcomes
| 25(OH)D Range | Bone-Relevant Interpretation |
|---|---|
| < 20 ng/mL (50 nmol/L) | Deficient. Risk of rickets in children, osteomalacia in adults, secondary hyperparathyroidism, accelerated bone loss. |
| 20-29 ng/mL (50-72 nmol/L) | Insufficient. Parathyroid hormone may still be inappropriately elevated; calcium absorption is suboptimal. |
| 30-39 ng/mL (75-97 nmol/L) | Conventional sufficiency. The 2011 Endocrine Society guideline (since replaced by the 2024 guideline, which set no target) and most fracture-prevention trials used this as the minimum target. |
| 40-60 ng/mL (100-150 nmol/L) | Optimal for skeletal outcomes in integrative practice (not an official target). Practitioners cite Bischoff-Ferrari data as showing that fracture risk plateaus in this range. Parathyroid hormone fully suppressed. Active calcium absorption maximal. |
| 60-100 ng/mL (150-250 nmol/L) | Higher than needed for bone alone; may be targeted for immune or autoimmune indications. Calcium is monitored in this range. |
| > 100 ng/mL (250 nmol/L) | Risk of hypercalcemia rises; doses are usually reduced unless under specialist supervision. |
The blood test that reflects vitamin D status is 25(OH)D; the 1,25(OH)2D test does not reflect vitamin D status and is essentially never appropriate for that purpose. The Vitamin D Test page covers ordering and interpretation.
The current Endocrine Society guideline (2024). The 2024 Endocrine Society guideline on vitamin D for disease prevention replaced the 2011 guideline. It found no clear evidence defining an optimal 25(OH)D target level for disease prevention and suggests against routine 25(OH)D testing in the populations it considered, including people with obesity or dark skin. It suggests vitamin D above the Dietary Reference Intakes for children and teenagers aged 1 to 18, adults over 75, pregnancy and high-risk prediabetes, and suggests against such extra vitamin D in healthy adults younger than 75. These recommendations do not apply to people with established reasons for vitamin D treatment or testing (Demay 2024). The 40-60 ng/mL range in the table is therefore an integrative-practice target, not a guideline target.
Osteoporosis Protocol Described in Integrative Practice
The protocol below is the one integrative practitioners describe. It has not been tested as a whole in a trial, and its 40-60 ng/mL target is higher than anything the 2024 Endocrine Society guideline endorses.
Assessment
- Baseline 25(OH)D level (target 40-60 ng/mL for bone)
- Parathyroid hormone level (target 20-40 pg/mL; elevated parathyroid hormone suggests vitamin D inadequacy even if 25(OH)D appears borderline-adequate)
- Serum calcium, phosphorus, magnesium
- DEXA scan for baseline bone mineral density (T-score)
- If T-score < -2.5: osteoporosis. If T-score -1.0 to -2.5: osteopenia.
Repletion phase (12-16 weeks)
- Vitamin D3: 5,000 international units/day (more if body mass index (BMI) > 30; 10,000 international units/day described for severe deficiency)
- Vitamin K2 (menaquinone-7): 200 mcg/day
- Magnesium glycinate or citrate: 400 mg elemental at bedtime
- Dietary calcium: 1,000-1,200 mg/day from sardines, dairy (if tolerated), almonds, leafy greens, calcium-set tofu
- 25(OH)D and parathyroid hormone re-tested at 12 weeks
Maintenance phase (indefinite)
- Vitamin D3: 2,000-4,000 international units/day to maintain 25(OH)D in 40-60 ng/mL range; periodic monitoring
- Vitamin K2 (menaquinone-7): 100-200 mcg/day indefinitely
- Magnesium: 300-400 mg/day elemental
- Continued calcium-rich diet
- Weight-bearing exercise (essential for the mechanical signaling that drives osteoblast activity); resistance training 2-3x/week
- Annual 25(OH)D and PTH; DEXA every 1-2 years to track BMD trajectory
Where pharmaceutical bone agents fit
Patients with established osteoporosis (T-score < -2.5), prior fragility fractures, or rapid bone loss are usually treated with a pharmaceutical agent (bisphosphonate, denosumab, teriparatide, or romosozumab depending on context), which practitioners combine with the quartet. Practitioners describe the quartet as complementary to these drugs, not a substitute — bisphosphonates work poorly in vitamin D-deficient patients, and many "bisphosphonate failures" are actually vitamin D failures.
Cautions
- Hypercalcemia at high doses — the principal toxicity of D3 supplementation. Typically requires sustained intake above 10,000-40,000 international units/day for weeks to months, but individual susceptibility varies. Practitioners check serum calcium periodically at doses above 5,000 international units/day; signs of hypercalcemia at any dose are nausea, polyuria (passing a lot of urine), polydipsia (strong thirst), confusion and kidney stones.
- Sarcoidosis and other granulomatous diseases — macrophages in granulomatous tissue express extrarenal 1α-hydroxylase and convert 25(OH)D to calcitriol without normal feedback regulation. These patients can develop hypercalcemia at modest D3 intakes, which is why supplementation in these conditions is usually done under specialist supervision with frequent calcium and 25(OH)D monitoring.
- Williams syndrome, idiopathic infantile hypercalcemia — rare genetic disorders causing exaggerated calcium response to D3. Standard pediatric D3 doses can be toxic.
- Drug interactions:
- Thiazide diuretics reduce calcium excretion — can predispose to hypercalcemia in D3-supplemented patients
- Glucocorticoids accelerate D3 catabolism (long-term steroid users typically need higher D3 doses)
- Anticonvulsants (phenytoin, phenobarbital, carbamazepine) induce hepatic CYP enzymes and accelerate D3 metabolism
- Rifampin similarly accelerates D3 metabolism
- Bile acid sequestrants (cholestyramine, colestipol) and orlistat reduce D3 absorption (separate dosing by 4+ hours)
- Cardiac glycosides (digoxin) interact with hypercalcemia — arrhythmia risk if D3-induced hypercalcemia develops in a digoxin patient
- Kidney disease — impaired renal 1α-hydroxylation may require calcitriol or its analogues (paricalcitol, doxercalciferol) rather than D3
- K2 caution with warfarin — vitamin K antagonizes warfarin's anticoagulant effect. Adding K2 lowers the international normalized ratio (INR) in people on warfarin, so the INR and the warfarin dose change; warfarin control depends on a steady vitamin K intake, so a K2 dose that goes up and down makes it harder
Key Research Papers
- Bischoff-Ferrari HA, Willett WC, Wong JB, et al. (2009). Prevention of nonvertebral fractures with oral vitamin D and dose dependency: a meta-analysis of randomized controlled trials. Archives of Internal Medicine. — PubMed PMID: 19307517
- Bischoff-Ferrari HA et al. (2012). A pooled analysis of vitamin D dose requirements for fracture prevention. NEJM 367:40-49. — PubMed PMID: 22762317
- Holick MF (2007). Vitamin D deficiency. NEJM 357:266-281. — PubMed PMID: 17634462
- Bouillon R, Marcocci C, Carmeliet G, et al. (2019). Skeletal and extraskeletal actions of vitamin D: current evidence and outstanding questions. Endocrine Reviews. — PubMed PMID: 30321335
- Christakos S, Dhawan P, Verstuyf A, Verlinden L, Carmeliet G (2016). Vitamin D: metabolism, molecular mechanism of action, and pleiotropic effects. Physiological Reviews. — PubMed PMID: 26681795
- Lips P, van Schoor NM (2011). The effect of vitamin D on bone and osteoporosis. Best Pract Res Clin Endocrinol Metab. — PubMed
- Knapen MHJ et al. Three-year low-dose menaquinone-7 (MK-7) supplementation helps decrease bone loss in healthy postmenopausal women. Osteoporosis International. — PubMed PMID: 23525894
- Schurgers LJ et al. Vitamin K-containing dietary supplements: comparison of synthetic vitamin K1 and natto-derived menaquinone-7. Blood. — PubMed
- Uwitonze AM, Razzaque MS (2018). Role of magnesium in vitamin D activation and function. J Am Osteopath Assoc. — PubMed PMID: 29480918
- Cranney A, Horsley T, O'Donnell S, et al. (2007). Effectiveness and safety of vitamin D in relation to bone health. AHRQ Evidence Report. — PubMed
- Holick MF, Binkley NC, Bischoff-Ferrari HA, et al. (2011). Evaluation, treatment, and prevention of vitamin D deficiency: Endocrine Society clinical practice guideline. J Clin Endocrinol Metab. — PubMed PMID: 21646368
- Bischoff-Ferrari HA et al. (2009). Fall prevention with supplemental and active forms of vitamin D: a meta-analysis of randomised controlled trials. BMJ. — PubMed PMID: 19797342
- Jackson RD, LaCroix AZ, Gass M, et al.; Women's Health Initiative Investigators (2006). Calcium plus vitamin D supplementation and the risk of fractures. NEJM 354:669-683. — PubMed PMID: 16481635
- LeBoff MS, Chou SH, Ratliff KA, et al. (2022). Supplemental Vitamin D and Incident Fractures in Midlife and Older Adults. NEJM 387:299-309. — PubMed PMID: 35939577
- Demay MB, Pittas AG, Bikle DD, et al. (2024). Vitamin D for the Prevention of Disease: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab 109:1907-1947. — PubMed PMID: 38828931