⚠ Evidence warning: Clinical trials or other evidence do not support the claims that multiple sclerosis risk falls in a graded, dose-response way with vitamin D level, that vitamin D is a disease-modifying add-on that reduces relapses and brain atrophy in multiple sclerosis, and that the antibody-reduction signal in Hashimoto's thyroiditis is consistent. This page keeps it as a report of what people, websites or other media say.
Vitamin D3 for Autoimmune Disease
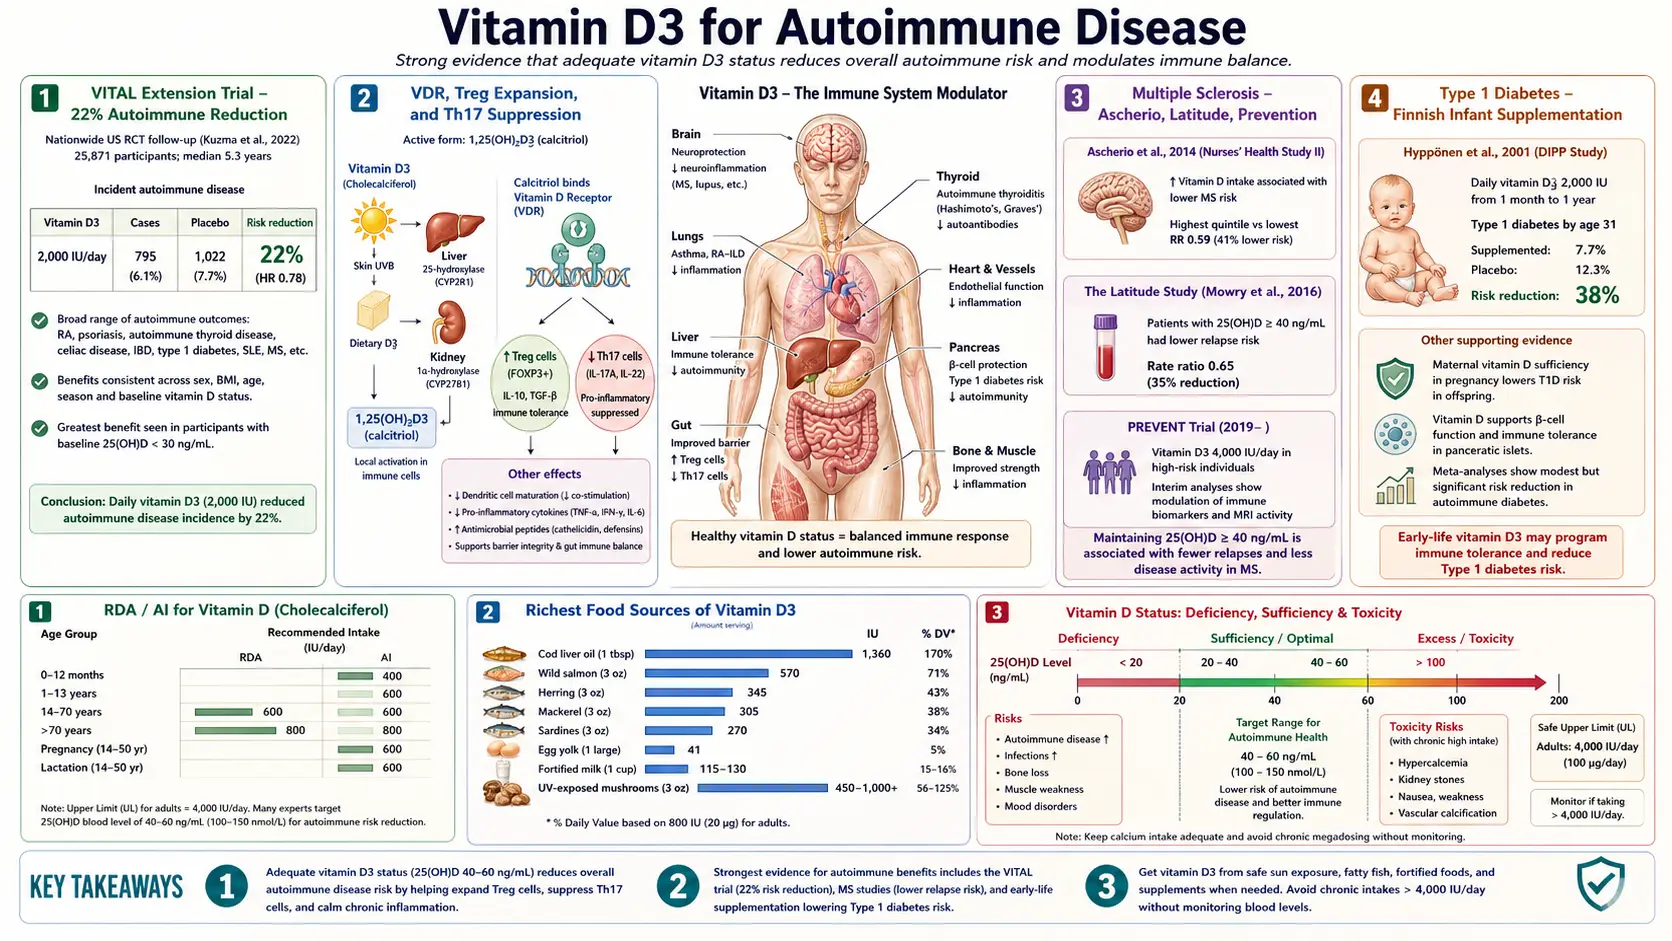
Vitamin D3 has emerged as one of the most important modifiable risk factors for autoimmune disease — the family of disorders in which the immune system attacks the body's own tissues. A 2022 report from the large VITAL trial found a 22% reduction in incident autoimmune disease in older adults randomized to 2,000 international units (IU)/day of vitamin D3 over a median of 5.3 years. Underlying this finding is a clear mechanism: calcitriol acts on naive T-cells and dendritic cells to suppress pathogenic Th17 differentiation, expand regulatory T-cell (Treg) populations via FoxP3 induction, and tilt the immune system toward tolerance rather than attack. The geographic latitude gradient seen in multiple sclerosis (and most other autoimmune conditions) mirrors the gradient in ultraviolet B-driven D3 synthesis. Specific evidence supports protective and therapeutic effects in multiple sclerosis (MS), type 1 diabetes (especially when supplemented in infancy), inflammatory bowel disease, Hashimoto's thyroiditis, psoriasis, lupus, and rheumatoid arthritis. At the most aggressive end of the dose spectrum, the Coimbra Protocol uses very-high-dose vitamin D under strict specialist supervision and calcium-restricted diet for treatment-resistant autoimmune conditions.
Table of Contents
- The VITAL Trial — 22% Autoimmune Reduction
- VDR, Treg Expansion, and Th17 Suppression
- Multiple Sclerosis — Ascherio, Latitude, Prevention
- Type 1 Diabetes — Finnish Infant Supplementation
- Inflammatory Bowel Disease (Crohn's, UC)
- Hashimoto's Thyroiditis
- Psoriasis (Topical and Systemic)
- Lupus and Rheumatoid Arthritis
- The Coimbra Protocol (High-Dose Supervised)
- Target 25(OH)D for Autoimmune Outcomes
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The VITAL Trial — 22% Autoimmune Reduction
The VITAL trial (VITamin D and OmegA-3 TriaL) was the largest randomized trial of vitamin D supplementation ever conducted. 25,871 American adults (12,786 men aged 50 or older and 13,085 women aged 55 or older) were randomized in a 2×2 factorial design to vitamin D3 2,000 international units/day vs placebo and to fish oil 1 gram/day vs placebo, with a median follow-up of 5.3 years. The primary outcomes were cancer and cardiovascular disease.
In 2022, Hahn and colleagues published the pre-specified autoimmune disease secondary analysis in BMJ. The result was striking:
- Everyone randomized to vitamin D3 (with or without fish oil): 22% reduction in incident autoimmune disease (hazard ratio (HR) 0.78, 95% confidence interval (CI) 0.61-0.99)
- Everyone randomized to fish oil (with or without vitamin D3): 15% reduction (HR 0.85, 0.67-1.08; not statistically significant)
- Compared with the double-placebo group: vitamin D3 + fish oil HR 0.69 (0.49-0.96), vitamin D3 only HR 0.68 (0.48-0.94), fish oil only HR 0.74 (0.54-1.03)
- The effect grew over time — protection became more pronounced after the first 2 years of supplementation, suggesting a cumulative effect of sustained vitamin D sufficiency
- The benefit was statistically significant for the composite autoimmune endpoint despite the relatively modest 2,000 international units/day dose (which only modestly raised 25(OH)D in many participants)
The autoimmune endpoints in VITAL included rheumatoid arthritis, psoriasis, autoimmune thyroid disease, polymyalgia rheumatica, and a smaller number of other conditions. The trial was not powered to detect effects within individual diseases, but the composite finding has substantial clinical implications: vitamin D supplementation at a modest dose of 2,000 international units/day, in a generally well-nourished older American population, prevented roughly 1 in 5 incident autoimmune diagnoses over 5 years.
Practitioners who use vitamin D for prevention read this result as support for routine supplementation, particularly in people with a family history of autoimmunity or with risk factors for vitamin D deficiency (high latitude, dark skin, obesity, indoor occupation).
VDR, Treg Expansion, and Th17 Suppression
The mechanistic basis for vitamin D's anti-autoimmune effect is now well-characterized at the molecular level. Calcitriol acts on three cell types in the autoimmune cascade:
Dendritic cells
Dendritic cells (DCs) are the antigen-presenting cells that determine whether a naive T-cell encountering a particular antigen will be activated (mount an immune response) or tolerized (learn to ignore it). Calcitriol shifts DCs toward a tolerogenic phenotype — reduced expression of MHC class II and costimulatory molecules (CD80, CD86), reduced IL-12 production, and increased interleukin-10 (IL-10) production. Tolerogenic DCs present self-antigens to T-cells in a way that promotes tolerance rather than autoreactive attack.
Naive T-cells — Th17 suppression
Th17 cells are the pathogenic T-cell subset that drives most autoimmune tissue damage. They produce IL-17, which recruits neutrophils, induces tissue inflammation, and damages target organs. Calcitriol directly suppresses Th17 differentiation by:
- Inhibiting RORγt, the master transcription factor for Th17 development
- Suppressing IL-17 production from already-differentiated Th17 cells
- Reducing the Th17-supporting cytokine environment (interleukin-6, IL-23)
Naive T-cells — Treg expansion
Regulatory T-cells (Tregs) are the immune system's brake pedal. They suppress effector T-cells, including autoreactive ones, and maintain peripheral tolerance. Calcitriol promotes Treg differentiation by:
- Inducing FoxP3 expression, the master transcription factor for Treg identity
- Promoting CD25 (IL-2 receptor) expression, which Tregs need to compete for IL-2
- Synergizing with TGF-β in driving Treg differentiation
The net effect of calcitriol on the adaptive immune system is therefore a coordinated shift: fewer pathogenic Th17 cells, more suppressive Tregs, and tolerogenic dendritic cells presenting self-antigens in a way that doesn't trigger autoreactive responses. This is exactly the immune phenotype seen in healthy individuals and lost in autoimmune patients.
The 22% autoimmune reduction in VITAL is consistent with this mechanism: vitamin D doesn't eliminate autoimmunity (the immune system can still mount autoreactive responses to strong genetic or environmental triggers), but it provides ongoing tonic support for the regulatory phenotype that suppresses incipient autoimmunity before it becomes clinically evident.
Multiple Sclerosis — Ascherio, Latitude, Prevention
Multiple sclerosis (MS) is the autoimmune disease with the strongest, most consistent evidence for a vitamin D connection. Three lines of evidence converge:
The latitude gradient
Multiple sclerosis incidence rises dramatically with distance from the equator. In the United States, multiple sclerosis is roughly 3-4 times more common in Minnesota than in Florida. In the Australasian region, multiple sclerosis is roughly 7 times more common in Tasmania than in Queensland. These gradients track ultraviolet B (UVB) intensity and therefore endogenous vitamin D synthesis, suggesting that childhood and young-adult vitamin D status (when multiple sclerosis is sown) is a major determinant of lifetime risk.
Migration studies reinforce the inference: individuals who migrate from a high-MS-risk to a low-MS-risk region before age 15 acquire the lower risk of their adopted region. Those who migrate after age 15 retain the higher risk of their birthplace. This suggests that childhood vitamin D status is the critical exposure.
The Ascherio prospective cohort data
Alberto Ascherio (Harvard) and colleagues used the Nurses Health Study cohorts to test the vitamin D-MS hypothesis prospectively. Higher dietary vitamin D intake (with or without supplements) was associated with approximately 40% lower multiple sclerosis risk.
A second study by the same group (Munger 2006, JAMA) used blood samples banked by the US military, which draws serial samples routinely, and compared 257 people later diagnosed with multiple sclerosis with matched controls. Among white participants, those in the highest fifth of serum 25(OH)D before the illness (above 99.1 nmol/L, about 40 ng/mL) had lower odds of multiple sclerosis than those in the lowest fifth (odds ratio 0.38, 95% CI 0.19-0.75); the odds ratios across the fifths were 0.57, 0.57, 0.74 and 0.38, and only the top fifth differed significantly. The link was strongest for levels measured before age 20. This was a graded, dose-response relationship. Among Black and Hispanic participants, no significant association was found.
Vitamin D in established Multiple Sclerosis
For patients with established multiple sclerosis, evidence supports vitamin D supplementation as a disease-modifying adjunct, though it does not replace standard multiple sclerosis therapies. For these patients, vitamin D is studied as an add-on to standard multiple sclerosis therapies, not a replacement. Two randomized trials added high-dose vitamin D3 to interferon beta-1a and neither met its primary endpoint. In SOLAR (229 patients, 14,007 IU/day for 48 weeks), the share of patients with no evidence of disease activity was 36.3% on vitamin D3 and 35.3% on placebo; exploratory MRI outcomes (new active lesions) favoured vitamin D3. In CHOLINE (181 patients, 100,000 IU every other week for 96 weeks), the relapse-rate primary endpoint was not met; among the 90 patients who completed two years, relapse rate, new lesions and disability progression favoured vitamin D3. Reports describe reduced relapse rates and slowed brain atrophy in multiple sclerosis patients given high-dose vitamin D, though effect sizes were modest. The Charcot Project and ongoing trials continue to refine optimal dosing.
The clinical takeaway for multiple sclerosis: aggressive 25(OH)D optimization (target 50-80 ng/mL minimum, with some specialists targeting higher) is now standard in integrative multiple sclerosis practice. Vitamin D is complementary to disease-modifying therapies, not a substitute. For prevention in those at risk (family history, female, northern latitude), maintaining 25(OH)D above 40-50 ng/mL throughout childhood and young adulthood is the most plausible intervention currently available.
Type 1 Diabetes — Finnish Infant Supplementation
Type 1 diabetes (T1D) is an autoimmune destruction of insulin-producing pancreatic beta cells, typically with onset in childhood or young adulthood. The classic vitamin D-T1D study is the Finnish birth cohort published by Hyppönen et al. in Lancet (2001).
In Finland during the 1960s, infants were routinely supplemented with cod liver oil (which provided approximately 2,000 international units/day of vitamin D3) during the first year of life. The Hyppönen team followed 10,366 of these infants for over 30 years and assessed T1D incidence.
- Infants given vitamin D regularly in their first year had a much lower rate of T1D by the end of 1997 than infants given none (rate ratio (RR) 0.12, 95% confidence interval 0.03-0.51; irregular supplementation RR 0.16, 0.04-0.74); 81 of the 10,366 children developed diabetes
- Children who regularly took the then-recommended 2,000 international units/day had RR 0.22 (0.05-0.89) compared with children who regularly took less than that
- Infants with suspected rickets (the marker of severe deficiency) had approximately 3-fold increased T1D risk
- The dose-response was clear: regular supplementation gave more protection than irregular supplementation, which gave more than none
This is an extraordinary effect size for a nutritional intervention — comparable in magnitude to the most effective vaccines. Other observational studies (EURODIAB case-control, Norwegian birth cohorts) have replicated the protective effect, though with more modest effect sizes (typically 25-50% reduction).
The mechanistic rationale: T1D arises when autoreactive T-cells destroy pancreatic beta cells. Vitamin D's Treg-promoting and Th17-suppressing effects directly oppose this autoimmune cascade. The first year of life is a critical window during which the developing immune system establishes tolerance toward self-antigens, and adequate vitamin D during this window may program lifelong protection against beta-cell autoimmunity.
These findings raise the possibility that vitamin D in infancy and early childhood lowers T1D risk, particularly in high-risk groups (family history, HLA-DR3/DR4 genotype). The standard pediatric recommendation is 400 international units/day for all breastfed infants; many natural-medicine pediatricians use 800-1,200 international units/day, and some practitioners also aim to raise 25(OH)D in pregnant women in high-risk pregnancies, on the theory that it supports fetal immune programming.
Inflammatory Bowel Disease (Crohn's, UC)
Crohn's disease and ulcerative colitis (collectively, inflammatory bowel disease, IBD) are autoimmune-inflammatory conditions of the intestinal tract. The vitamin D connection is multifaceted:
Epidemiology
- Inflammatory bowel disease incidence shows the same latitude gradient as multiple sclerosis — more common in northern populations
- Low 25(OH)D is highly prevalent in inflammatory bowel disease patients (often < 15 ng/mL even outside winter)
- Low 25(OH)D predicts worse disease course, more frequent flares, more steroid courses, more hospitalizations, and higher rates of surgery
Mechanism
Vitamin D's inflammatory bowel disease-relevant effects include:
- Treg expansion in gut-associated lymphoid tissue (suppressing the autoreactive responses that drive inflammatory bowel disease)
- Upregulation of intestinal tight-junction proteins (claudins, occludin, ZO-1), reducing the "leaky gut" that allows microbial antigens to drive inflammation
- Cathelicidin LL-37 induction in intestinal epithelium (improving antimicrobial defense)
- Modulation of the gut microbiome composition
- Direct anti-inflammatory effects on intestinal mucosa
Trial evidence
Multiple small randomized controlled trials (RCTs) have shown that vitamin D supplementation reduces inflammatory markers, improves quality of life, and lowers relapse rates in inflammatory bowel disease. In the best-known of these, a 2010 Danish trial in 94 people with Crohn's disease in remission, relapse over 12 months was 13% on 1,200 international units/day versus 29% on placebo, a difference that fell just short of statistical significance (P=0.06). Effect sizes are modest, but trial doses have generally been conservative (1,000-4,000 international units/day). Some integrative gastroenterologists use much higher doses (10,000-20,000 international units/day) for active inflammatory bowel disease with calcium and 25(OH)D monitoring.
Note that inflammatory bowel disease patients have increased risk of vitamin D toxicity at standard doses because intestinal inflammation can paradoxically increase calcitriol production (via inflammatory upregulation of 1α-hydroxylase). This is why practitioners using higher-dose D3 in inflammatory bowel disease check calcium and 25(OH)D.
Hashimoto's Thyroiditis
Hashimoto's thyroiditis is the most common cause of hypothyroidism in iodine-sufficient regions and is fundamentally an autoimmune destruction of the thyroid gland mediated by anti-TPO (thyroid peroxidase) and anti-thyroglobulin antibodies. Vitamin D's role in Hashimoto's:
- Low 25(OH)D is observed in 70-90% of Hashimoto's patients
- Lower 25(OH)D correlates with higher anti-TPO antibody titers in observational studies
- Two non-randomized studies found lower anti-TPO antibody levels after vitamin D: Mazokopakis et al. 2015 gave 1,200-4,000 international units/day for 4 months to 186 vitamin D-deficient patients on Crete, and anti-TPO fell by 20.3%; Krysiak et al. 2017 followed 34 levothyroxine-treated women with normal vitamin D status who chose whether to take 2,000 international units/day, and antibody titers fell over 6 months only in those who took it
- The autoimmune-modulating mechanism (Treg expansion, Th17 suppression) is the proposed driver
Whether antibody reduction translates into preservation of thyroid function over the long term is less clear — Hashimoto's typically progresses slowly, and trials long enough to detect levothyroxine-dose reduction or restoration of normal thyroid-stimulating hormone (TSH) have not been completed. But the antibody-reduction signal is consistent and the safety profile is excellent. Vitamin D optimization is nonetheless standard in integrative Hashimoto's management.
For Hashimoto's, integrative practitioners target 25(OH)D 60-80 ng/mL, combine it with selenium 200 mcg/day (which has also been reported to reduce anti-TPO antibodies), and aim for adequate iodine intake without excess. See the Hashimoto's page for the broader protocol.
Psoriasis (Topical and Systemic)
Psoriasis is the autoimmune condition where vitamin D's clinical role is most established — topical vitamin D analogues (calcipotriol, calcitriol, tacalcitol, maxacalcitol) are first-line treatments for plaque psoriasis.
Topical analogues
Topical calcipotriol (the most widely used) is applied directly to psoriatic plaques and works through three mechanisms: it normalizes keratinocyte differentiation (psoriatic keratinocytes are hyperproliferative and undifferentiated), it reduces local Th17 and IL-17 activity, and it activates local Tregs. Effect onset is typically 4-8 weeks; combination with topical corticosteroids accelerates response.
Systemic supplementation
Systemic vitamin D3 supplementation (separate from topical analogues) is also valuable. Psoriasis patients have lower 25(OH)D than controls, and supplementation reduces PASI (Psoriasis Area and Severity Index) scores in several randomized controlled trials. The systemic approach addresses the underlying immunoregulatory abnormality that drives flares, while topical analogues address the current visible lesions.
Coimbra protocol use
Psoriasis is one of the conditions where the Coimbra Protocol (very high-dose vitamin D, calcium-restricted diet) has been used most extensively. Many treatment-resistant patients report dramatic improvement or remission on the protocol, though it requires specialist supervision (see below).
Lupus and Rheumatoid Arthritis
Systemic Lupus Erythematosus (SLE)
Systemic lupus erythematosus patients almost universally have low 25(OH)D, partly because they are advised to avoid sun exposure (sun exposure triggers lupus flares) and partly because of the disease itself. Low 25(OH)D in systemic lupus erythematosus is associated with higher disease activity, more frequent flares, increased anti-dsDNA antibody titers, and worse cardiovascular outcomes.
Supplementation trials in systemic lupus erythematosus have generally shown improvements in fatigue scores and disease activity, but no large definitive trials have established disease-modifying effects. The strategy in integrative systemic lupus erythematosus management is to optimize 25(OH)D to 60-80 ng/mL using daily oral supplementation (since sun avoidance is mandatory), combined with standard immunosuppressive therapy.
Rheumatoid Arthritis (RA)
Rheumatoid arthritis shares much of the same biology — Th17-driven autoimmune attack on joint tissue. Vitamin D deficiency is common in rheumatoid arthritis, correlates with disease activity, and supplementation in several trials has shown modest reductions in tender joint counts, morning stiffness, and DAS28 (disease activity) scores.
Rheumatoid arthritis patients are also at elevated osteoporosis risk (from chronic inflammation, glucocorticoid use, and reduced activity), so the bone-protective effects of vitamin D add to its autoimmune-modulatory benefits. The quartet protocol (D3 + K2 + magnesium + calcium) is particularly important in rheumatoid arthritis patients.
The Coimbra Protocol (High-Dose Supervised)
The Coimbra Protocol is a treatment approach developed by Brazilian neurologist Cicero Galli Coimbra for severe autoimmune disease. It uses very-high-dose vitamin D (typically 40,000-200,000 international units/day, dose-titrated to suppress parathyroid hormone (PTH) to a low-normal range) combined with a strict calcium-restricted diet (essentially no dairy, low-calcium plant foods only) and daily hydration of 2.5+ liters of water.
The rationale is based on observations of vitamin D receptor polymorphisms in autoimmune patients — the Coimbra group hypothesizes that many autoimmune patients have reduced VDR sensitivity, requiring supraphysiologic 25(OH)D levels (often above 100 ng/mL, sometimes above 300 ng/mL) to achieve adequate VDR activation in immune cells. The calcium restriction and high water intake are protective measures to prevent hypercalcemia and kidney stones at these extreme doses.
Reported clinical experience (mostly published as case series) describes substantial improvements in multiple sclerosis, psoriasis, lupus, rheumatoid arthritis, inflammatory bowel disease, and other conditions, with high rates of disease stabilization or improvement. The protocol has spread internationally; certified Coimbra physicians practice in many countries.
Critical caveats:
- The Coimbra Protocol is not a self-administered intervention. The doses used (10-50 times typical supplementation) can cause severe hypercalcemia and kidney damage in inadequately monitored patients.
- Periodic 25(OH)D, calcium (serum and 24-hour urine), parathyroid hormone, kidney function, and DEXA monitoring are mandatory.
- The calcium-restricted diet is non-negotiable; even occasional dairy can trigger hypercalcemic episodes.
- Randomized trial evidence is limited; the protocol is supported by case series and clinician experience rather than definitive randomized controlled trials.
- The protocol is run by certified Coimbra Protocol practitioners; the doses involved are the range at which unmonitored use has caused the hypercalcemia and kidney damage described above.
For the typical autoimmune patient, integrative practitioners use conventional vitamin D supplementation (5,000-10,000 international units/day with K2 and magnesium, target 25(OH)D 60-100 ng/mL), which they regard as providing much of the benefit at far lower risk. The Coimbra Protocol is reserved for severe, treatment-resistant cases under specialist care.
Target 25(OH)D for Autoimmune Outcomes
The targets and doses below are those used by integrative and Coimbra Protocol practitioners; they are not official recommendations. The 2011 Institute of Medicine (now National Academies) report set the adult tolerable upper intake level at 4,000 international units/day.
| Indication | Target 25(OH)D | Typical D3 Dose |
|---|---|---|
| Autoimmune prevention (family history, no disease) | 50-70 ng/mL | 2,000-5,000 international units/day |
| Established autoimmune disease (stable, on conventional therapy) | 60-100 ng/mL | 5,000-10,000 international units/day |
| Active flare or treatment-resistant | 80-150 ng/mL (with monitoring) | 10,000-20,000 international units/day under specialist care |
| Coimbra Protocol | 100-300+ ng/mL (parathyroid hormone-suppressed) | 40,000-200,000 international units/day, certified Coimbra physician only |
In these protocols K2 and magnesium dosing scales with D3 dose. For 10,000 international units/day D3, practitioners use approximately 200 mcg menaquinone-7 (MK-7) and 400 mg elemental magnesium; at Coimbra-level doses, K2 and magnesium are scaled up substantially.
Cautions
- Hypercalcemia — the principal risk of higher-dose autoimmune protocols. Practitioners check serum calcium every 1-3 months at doses above 5,000 international units/day, more often above 10,000 international units/day, and at every visit on the Coimbra Protocol.
- Kidney stones and nephrocalcinosis — risk rises with hypercalciuria. Higher-dose protocols include periodic 24-hour urinary calcium checks.
- Sarcoidosis and granulomatous disease — absolute caution. Granuloma macrophages produce calcitriol without normal regulation. Even modest D3 doses can cause hypercalcemia in these conditions.
- Hypercalcemia of malignancy — some lymphomas and other tumors produce calcitriol, mimicking sarcoidosis biology. Persistent hypercalcemia in a person taking vitamin D can therefore have a cause other than the vitamin.
- Drug interactions in autoimmune patients — many autoimmune patients are on glucocorticoids (accelerate D3 catabolism, requiring higher doses), hydroxychloroquine (lupus — no significant D3 interaction), methotrexate (no significant interaction), and biologics (no significant interaction). Anticonvulsants used for autoimmune neurologic conditions accelerate D3 metabolism.
- Pregnancy and breastfeeding — vitamin D is safe and beneficial during pregnancy at 4,000-6,000 international units/day (Hollis randomized controlled trial, RCT). Very-high-dose Coimbra-style protocols have no safety data in pregnancy.
- Coimbra Protocol-specific cautions — absolute requirement for calcium-restricted diet, 2.5+ L daily water intake, frequent monitoring of calcium and kidney function. Coimbra practitioners exclude patients who cannot reliably keep to the calcium restriction.
- K2 with warfarin — K2 antagonizes warfarin's anticoagulant effect. Adding K2 can lower the international normalized ratio (INR) of a person on warfarin, and a K2 dose that goes up and down makes the INR swing.
Key Research Papers
- Hahn J, Cook NR, Alexander EK, et al. (2022). Vitamin D and marine omega-3 fatty acid supplementation and incident autoimmune disease: VITAL randomized controlled trial. BMJ 376:e066452. — PubMed PMID: 35082139
- Hyppönen E, Läärä E, Reunanen A, Järvelin MR, Virtanen SM (2001). Intake of vitamin D and risk of type 1 diabetes: a birth-cohort study. Lancet 358(9292):1500-1503. — PubMed PMID: 11705562
- Munger KL, Levin LI, Hollis BW, Howard NS, Ascherio A (2006). Serum 25-hydroxyvitamin D levels and risk of multiple sclerosis. JAMA 296:2832-2838. — PubMed PMID: 17179460
- Ascherio A, Munger KL, White R, et al. (2014). Vitamin D as an early predictor of multiple sclerosis activity and progression. JAMA Neurology 71(3):306-314. — PubMed PMID: 24445558
- Hupperts R, Smolders J, Vieth R, et al. (2019). Randomized trial of daily high-dose vitamin D3 in patients with RRMS receiving subcutaneous interferon β-1a (SOLAR). Neurology 93(20):e1906-e1916. — PubMed PMID: 31594857
- Camu W, Lehert P, Pierrot-Deseilligny C, et al. (2019). Cholecalciferol in relapsing-remitting MS: a randomized clinical trial (CHOLINE). Neurol Neuroimmunol Neuroinflamm 6(5):e597. — PubMed PMID: 31454777
- Mazokopakis EE, Papadomanolaki MG, Tsekouras KC, et al. (2015). Is vitamin D related to pathogenesis and treatment of Hashimoto's thyroiditis? Hell J Nucl Med 18(3):222-227. — PubMed PMID: 26637501
- Krysiak R, Szkróbka W, Okopień B (2017). The effect of vitamin D on thyroid autoimmunity in levothyroxine-treated women with Hashimoto's thyroiditis and normal vitamin D status. Exp Clin Endocrinol Diabetes 125(4):229-233. — PubMed PMID: 28073128
- Cantorna MT (2010). Mechanisms underlying the effect of vitamin D on the immune system. Proc Nutr Soc. — PubMed PMID: 20515520
- Joshi S, Pantalena LC, Liu XK, et al. (2011). 1,25-dihydroxyvitamin D3 ameliorates Th17 autoimmunity via transcriptional modulation of interleukin-17A. Mol Cell Biol. — PubMed PMID: 21746882
- Smolders J, Thewissen M, Peelen E, et al. (2009). Vitamin D status is positively correlated with regulatory T cell function in patients with multiple sclerosis. PLoS One. — PubMed PMID: 19675671
- Jorgensen SP, Agnholt J, Glerup H, et al. (2010). Clinical trial: vitamin D3 treatment in Crohn's disease — a randomized double-blind placebo-controlled study. Aliment Pharmacol Ther 32(3):377-383. — PubMed PMID: 20491740
- Amrein K, Scherkl M, Hoffmann M, et al. (2020). Vitamin D deficiency 2.0: an update on the current status worldwide. Eur J Clin Nutr. — PubMed PMID: 31959942
- Finamor DC, Sinigaglia-Coimbra R, Neves LCM, et al. (2013). A pilot study assessing the effect of prolonged administration of high daily doses of vitamin D on the clinical course of vitiligo and psoriasis. Dermatoendocrinol. (Early Coimbra protocol paper.) — PubMed PMID: 24494059
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin D3 Overview
- D3 Benefits Hub
- D3 for Bone Health
- D3 for Immune Function
- D3 for Mood & Depression
- Multiple Sclerosis
- Hashimoto's Thyroiditis
- Diabetes (Type 1)
- Inflammatory Bowel Disease
- Psoriasis
- Lupus (Systemic Lupus Erythematosus)
- Rheumatoid Arthritis
- Vitamin K2
- Vitamin A
- Magnesium
- Selenium
- Omega-3 Fatty Acids
- Vitamin D Test
- Calcium — the mineral whose absorption vitamin D governs; restricted on the Coimbra Protocol and monitored on every higher-dose D3 regimen.
- Deficiency
- Toxicity
- History
- Sources