Sleep Hygiene — Temperature and Mattress
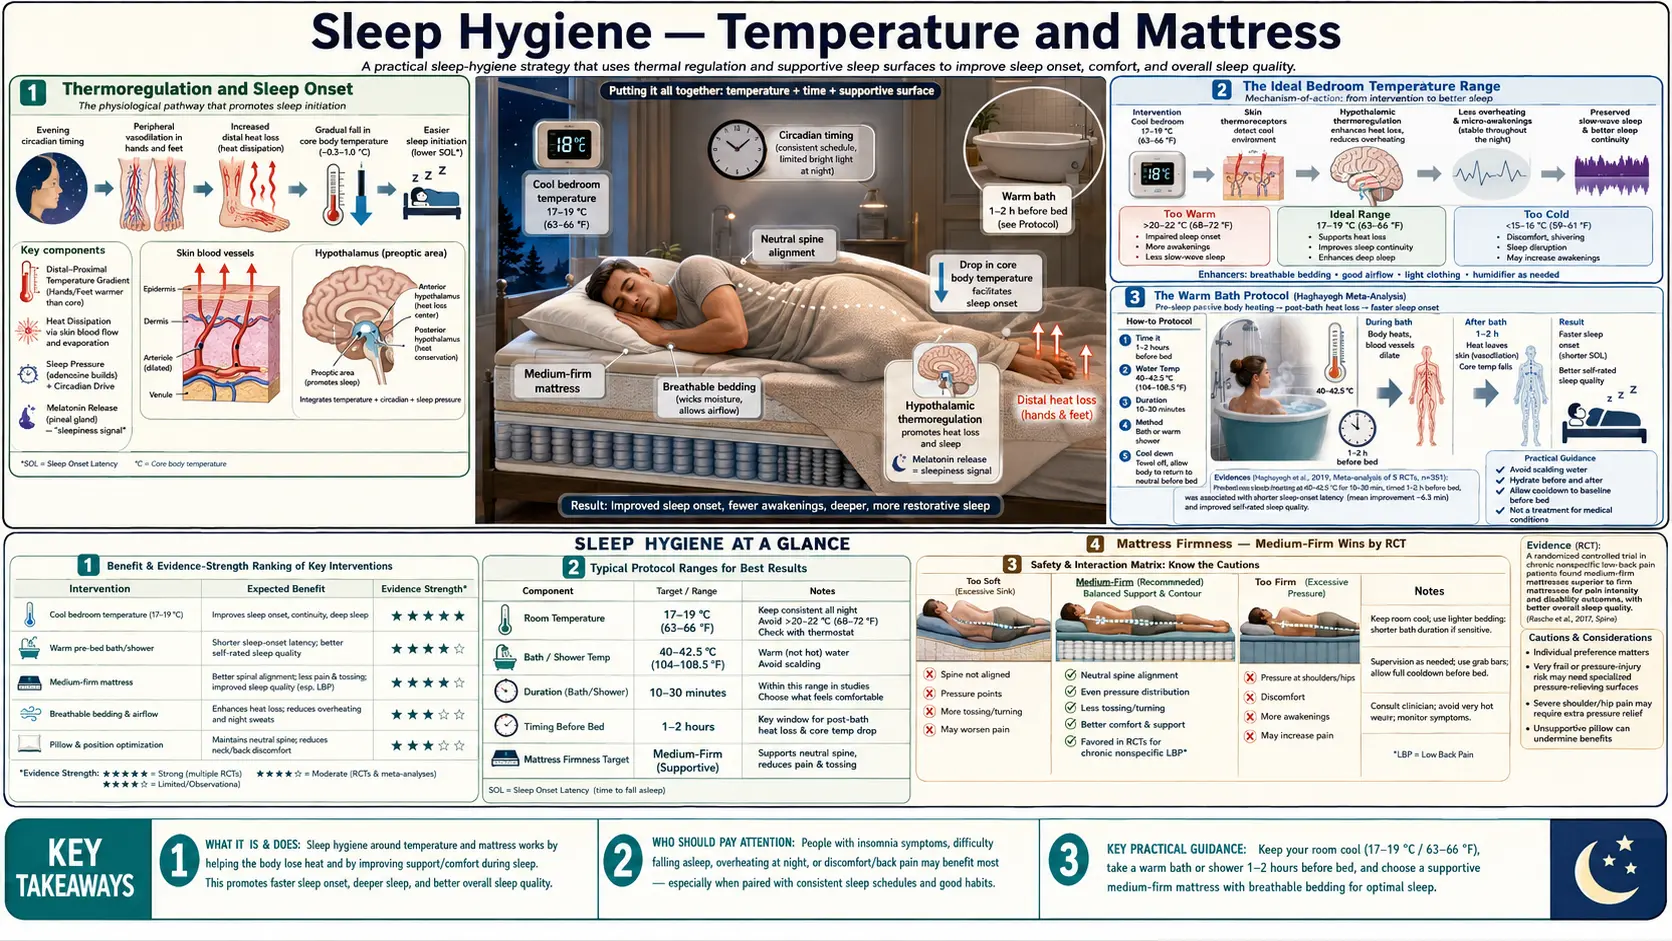
Sleep onset is gated by thermoregulation. The human core body temperature must drop by approximately 0.3°C from its daytime peak to initiate the slow-wave sleep cascade, and this drop is mediated by distal-skin vasodilation that radiates heat away from the body core. A bedroom temperature of 60–67°F (15.5–19.5°C), with a sweet spot around 65°F (18°C), is the range across which most healthy adults achieve this drop most efficiently. Two ancillary interventions help: a warm shower or bath 90 minutes before bed (the Haghayegh meta-analysis found it significantly shortened the time taken to fall asleep), and a medium-firm mattress with cervical-aligning pillow. This page covers the physiology in depth, then walks through the practical decisions on thermostats, mattresses, pillows, sheets, and cooling toppers.
Table of Contents
- Thermoregulation and Sleep Onset
- The Ideal Bedroom Temperature Range
- The Warm Bath Protocol (Haghayegh Meta-Analysis)
- Mattress Firmness — Medium-Firm Wins by Randomized Controlled Trial
- Mattress Types (Innerspring, Memory Foam, Latex, Hybrid)
- Pillow Loft and Cervical Alignment
- Sheets and Bedding (Fiber, Weave, Tog)
- Cooling Toppers and Active Climate Systems
- Night Sweats, Hot Flashes, and Hot Sleepers
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Thermoregulation and Sleep Onset
Core body temperature follows a robust circadian rhythm in healthy adults, peaking at roughly 99°F (37.2°C) in the late afternoon and reaching a nadir of approximately 97.5°F (36.4°C) about 2 hours before habitual wake time. This is not incidental — sleep onset is causally gated by the descending slope of body temperature in the evening. The thermal phase shift comes from the suprachiasmatic nucleus (SCN), the brain's master clock, through the suprachiasmatic-paraventricular projections that regulate the sympathetic nervous system.
The mechanism of temperature drop involves distal-skin vasodilation: blood vessels in the hands and feet open, allowing warm blood to radiate heat through the skin into the environment. This is why warm hands and feet are a reliable physiological marker of imminent sleep, and why cold hands and feet at bedtime (often caused by sympathetic activation from stress or low ambient temperature) predict difficulty falling asleep. Krauchi et al. (Nature 1999, PubMed PMID: 10485703) demonstrated that the ratio of distal-skin temperature to proximal-skin temperature (the "distal-proximal gradient") is the single best physiological predictor of sleep latency — warm feet and cool core predict rapid sleep onset.
Once asleep, body temperature continues to drop through the first half of the night, reaches its nadir in the second half, and begins to climb again roughly 2 hours before natural wake time. Cortisol surges in parallel with the temperature climb, producing the cortisol awakening response (CAR). Disruption of the temperature rhythm — from a too-warm bedroom, an insulating mattress, heavy bedding, or pre-bed alcohol — flattens the temperature curve and fragments sleep, particularly reducing slow-wave (deep) sleep in the first third of the night.
The Ideal Bedroom Temperature Range
Sleep researchers converge on 60–67°F (15.5–19.5°C) as the optimal bedroom temperature for most adults, with the sweet spot around 65°F (18°C). The range exists because individuals vary considerably in basal metabolic rate, body composition (more lean mass = more heat production), thyroid status, and bedding preferences.
A 2012 review by Okamoto-Mizuno & Mizuno (J Physiol Anthropol 2012, PMID 22738673) found that in real-life conditions, with bedding and clothing, heat exposure increases wakefulness and decreases slow-wave and rapid eye movement (REM) sleep, while cold exposure does not change sleep stages but does affect the heart's autonomic (nervous-system) response during sleep. The review gives no Fahrenheit bands; the bands below are commonly cited sleep-hygiene ranges:
- Below 60°F (15.5°C): The body must work harder to maintain core temperature. With bedding in use, sleep-lab studies of cold exposure found no change in sleep stages but a shift in the heart's autonomic response.
- 60–67°F (15.5–19.5°C): Optimal range. Slow-wave sleep is maximized; sleep onset latency is shortest; wake-after-sleep-onset (WASO) is lowest.
- 67–72°F (19.5–22°C): Generally tolerated but slow-wave sleep begins to drop and REM is preserved less well.
- Above 75°F (24°C): Substantial impairment of sleep architecture. Frequent micro-arousals, reduced slow-wave sleep, sweating-mediated dehydration.
Older adults often prefer warmer rooms by 2–5°F because of reduced basal metabolic rate and thinner skin (less efficient thermoregulation). Postmenopausal women experiencing hot flashes may need an even cooler room (60–63°F) with cooling sheets and possibly a bedside fan. Couples with mismatched preferences can use dual-zone water-circulating mattress pads.
The Warm Bath Protocol (Haghayegh Meta-Analysis)
The Haghayegh et al. systematic review and meta-analysis (Sleep Medicine Reviews 2019, PubMed PMID: 31102877) included 17 studies of pre-bed warm-water bathing or showering, 13 of which gave data that could be pooled. The headline finding: warm water at 40–42.5°C (104–108.5°F) was linked to better self-rated sleep quality and sleep efficiency, and when scheduled 1–2 hours before bedtime, for as little as 10 minutes, to a significant shortening of the time taken to fall asleep (sleep onset latency). The authors noted that research on the subject is still scarce.
The mechanism is counterintuitive. The warm water does not cool you down directly — it warms you up. But the warm bath causes massive distal-skin vasodilation, and when you step out of the bath and into cooler ambient air, the dilated peripheral vessels radiate heat away from the body core extremely efficiently. The net effect over the next 1–2 hours is a faster and deeper core-body-temperature drop than would occur naturally, accelerating the thermal trigger for sleep onset.
Practical protocol:
- Timing: 60–120 minutes before intended bedtime is optimal. Closer to bedtime fails because the temperature drop is incomplete; further away fails because the effect has dissipated.
- Temperature: 104–108°F (40–42°C). Hot enough to feel pleasantly warm but not scalding.
- Duration: 10–20 minutes. Long enough to warm the body core; short enough to be practical.
- Post-bath: Towel off, change into light cool pajamas, lower bedroom thermostat if possible.
- Footbath: A 2013 crossover trial by Liao et al. tested a 20-minute footbath at 40°C in 25 adults aged about 60 (good and poor sleepers). It warmed the feet, but sleep measured in the sleep lab and how well people felt they slept did not change in either group.
Magnesium-rich Epsom salt baths are popular but the magnesium contribution is largely irrelevant (transdermal absorption is minimal); the sleep benefit comes from the thermal effect alone.
Mattress Firmness — Medium-Firm Wins by Randomized Controlled Trial
The Kovacs et al. trial (Lancet 2003, PubMed PMID: 14630439) is the landmark randomized controlled trial (RCT) on mattress firmness. 313 adults with chronic non-specific low back pain were randomized to a firm mattress (H(s) 2.3 on the European scale, which runs from 1.0 firmest to 10.0 softest) or medium-firm (H(s) 5.6) for 90 days. At 90 days the medium-firm group did better for pain while lying in bed (odds ratio 2.36) and for disability (odds ratio 2.10); pain on rising (odds ratio 1.93) and daytime low back pain (p=0.059) also favoured medium-firm but fell just short of statistical significance. The authors' conclusion: a medium-firm mattress improves pain and disability in adults with chronic non-specific low back pain. Sleep quality was not one of the trial's outcomes.
In a 2010 study by Jacobson et al., 27 people with chronic back pain, referred by chiropractors, rated their back pain, stiffness and sleep quality for 21 days in their own beds, then for 12 weeks on medium-firm foam-and-latex mattresses chosen to suit their usual sleeping position. Back pain, stiffness and sleep quality all improved, progressively over the weeks, and the number of days a week with poor sleep and physical discomfort fell. The study had no control group. A common view in sleep-hygiene writing is that mattress age and condition matter more than brand. The average mattress useful lifespan is 7–10 years; visible sagging, body impressions deeper than 1.5 inches, or springs poking through indicate a worn-out mattress regardless of age.
Mattress firmness intersects with body weight: heavier individuals (over 230 lb / 105 kg) generally need firmer mattresses to prevent excessive sinking; lighter individuals (under 130 lb / 60 kg) often find very firm mattresses uncomfortable because they cannot compress the surface enough to relieve pressure points. Side sleepers benefit from slightly softer surfaces (pressure relief at hip and shoulder); back and stomach sleepers benefit from slightly firmer surfaces (lumbar support).
Mattress Types (Innerspring, Memory Foam, Latex, Hybrid)
The four major mattress categories each have characteristic profiles:
- Innerspring: Traditional coil-based construction. Excellent airflow (sleeps cool), good edge support, moderate pressure relief, moderate durability (5–8 years typical lifespan). Best for: hot sleepers, heavier individuals, those wanting traditional feel and bounce.
- Memory foam: Viscoelastic polyurethane foam. Excellent pressure relief and motion isolation; tends to sleep warm without phase-change materials or gel infusions; 7–10 year lifespan. Best for: side sleepers, couples (motion isolation), those with joint pain. Less suited to: hot sleepers (unless cooling formulation).
- Latex: Natural or synthetic rubber foam. Most durable category (10–15+ years for natural latex); excellent pressure relief with more bounce than memory foam; cooler than memory foam; expensive. Best for: those wanting longevity, allergy sufferers (natural latex is dust-mite resistant), eco-conscious buyers.
- Hybrid: Innerspring coil base + foam or latex comfort layers on top. Combines coil airflow and edge support with foam pressure relief; 7–10 year lifespan. Best for: most buyers seeking a versatile general-purpose mattress.
The choice of mattress type is highly individual — no single material is best for everyone. The most important tactic is buying from a vendor with a generous trial period (90–365 nights). The body takes 2–4 weeks to adapt to a new sleep surface; impressions in the first few nights are unreliable.
Pillow Loft and Cervical Alignment
The pillow's job is to keep the cervical spine in neutral alignment with the thoracic spine during sleep. Pillow height (loft) requirements differ dramatically by sleep position:
- Back sleepers: Low to medium loft (3–5 inches). The pillow should fill the space between the head and the mattress without tilting the head forward. A contoured cervical pillow with a depression for the head and a roll under the neck is often ideal.
- Side sleepers: Medium to high loft (5–7 inches). The pillow must fill the wider gap between the head and the mattress created by the shoulder. Broader-shouldered sleepers need taller pillows. The head should be level with the spine, not tilted up or down.
- Stomach sleepers: Very low loft or no pillow. Most pillows force the cervical spine into hyperextension when stomach sleeping. Stomach sleeping keeps the neck turned and extended for hours, a source of chronic neck strain; side sleeping does not carry this strain.
- Combination sleepers: Adjustable-loft pillows (shredded memory foam or buckwheat hulls) that can be added to or removed from a zippered shell are most flexible.
Pillow lifespan is 1–3 years for polyester, 3–5 years for memory foam, 5–10 years for latex or buckwheat. A flattened pillow that no longer springs back when folded is past its useful life. A leg pillow (small wedge between the knees for side sleepers; pillow under the knees for back sleepers) is a low-cost addition that often substantially reduces morning back pain.
Sheets and Bedding (Fiber, Weave, Tog)
Sheets and bedding contribute meaningfully to bed-surface temperature. Key variables:
- Fiber: Cotton (especially long-staple Egyptian or Pima) and linen are the most breathable. Linen actively wicks moisture and feels cool to the touch year-round. Bamboo lyocell is breathable and antimicrobial. Synthetic microfiber (polyester) traps heat and moisture — a drawback for hot sleepers.
- Weave: Percale (one-over-one-under) is crisp and cool; sateen (four-over-one-under) is silkier but warmer. For hot sleepers, percale beats sateen for the same fiber.
- Thread count: Quality matters more than thread count. Above 400–500 thread count, additional threads come from low-quality multi-ply yarns. Reputable 200–400 thread count single-ply long-staple cotton outperforms 1000-thread-count multi-ply.
- Comforter / duvet tog rating: Tog is a unit of thermal insulation. Light summer comforter: 4.5 tog or lower. All-season: 10.5 tog. Winter / cold-climate: 13.5 tog or higher. Mismatched tog is a frequent cause of sleep-disrupting overheating.
The Scandinavian "two-duvet" system — each partner under their own duvet rather than sharing — resolves mismatched-tog disputes and reduces sleep disruption from a partner's movements.
Cooling Toppers and Active Climate Systems
For chronic hot sleepers, passive cooling toppers (phase-change material, gel-infused memory foam, gel beads in pillows) provide modest cooling for the first 30–60 minutes after lying down, then equilibrate with body temperature. Helpful but limited.
Active climate-controlled mattress pads circulate water at user-set temperatures (55–110°F / 13–43°C) through tubes embedded in a topper. These can independently cool each side of the bed, programmable to drop temperature in the first half of the night and rise gently before wake. Cost: $1,500–$3,500. Users with menopausal hot flashes, postmenopausal night sweats, or who simply run hot generally report these pads as helpful.
A simpler, cheaper alternative is a bedside fan or ceiling fan on low, providing air circulation that aids evaporative cooling without dropping room temperature uncomfortably.
Night Sweats, Hot Flashes, and Hot Sleepers
Persistent night sweats severe enough to soak through pajamas or sheets have many possible causes. Common causes include perimenopause/menopause, hyperthyroidism, lymphoma (especially Hodgkin), tuberculosis, human immunodeficiency virus (HIV), gastroesophageal reflux disease (GERD), anxiety disorders, and medications (selective serotonin reuptake inhibitors (SSRIs), opioid withdrawal, certain antihypertensives). Unexplained new-onset drenching night sweats in an adult are a recognised sign of lymphoma and tuberculosis, both listed above.
For perimenopausal/postmenopausal hot flashes, in addition to bedroom cooling: layered breathable nightwear that can be quickly removed; avoidance of alcohol, spicy foods, and large meals in the evening (all triggers); cognitive behavioral therapy for menopause (cognitive behavioral therapy-Meno); selective serotonin reuptake inhibitor (SSRI)/serotonin-norepinephrine reuptake inhibitor (SNRI) pharmacotherapy if indicated; and discussion of menopause hormone therapy where appropriate.
Cautions
- Persistent back pain after mattress change: The body takes 2–4 weeks to adapt to a new sleep surface; pain that has not improved, or has worsened, after 4–6 weeks suggests the mattress does not suit that sleeper, and vendor trial periods allow a return or exchange.
- Pregnancy and side sleeping: Going to sleep on the back in late pregnancy is linked to stillbirth. A 2019 pooled analysis of five case-control studies (pregnancies of 28 weeks or more) found that going to sleep on the back carried about 2.6 times the odds of late stillbirth compared with the left side (adjusted odds ratio 2.63), while the right side carried the same odds as the left (adjusted odds ratio 1.04); the authors concluded that going to sleep on either side appears equally safe. They estimated that 5.8% of late stillbirths could be avoided if every woman at 28 weeks or more settled to sleep on her side. A pregnancy wedge pillow under the abdomen and between the knees adds comfort.
- Recent surgery, fractures, or severe arthritis: Sleeping positions and surfaces are often restricted after surgery or a fracture; adjustable beds are one option used in these cases.
- Severe hot flashes or night sweats: See above; not a sleep-hygiene problem alone, may indicate an underlying medical condition.
- Sleep apnea: Sleeping prone or supine can worsen positional obstructive sleep apnea (OSA); side sleeping may improve it. Loud snoring and witnessed pauses in breathing are recognised signs of sleep apnea, which a mattress change does not treat.
Key Research Papers
- Haghayegh S et al., Before-bedtime passive body heating by warm shower or bath to improve sleep: A systematic review and meta-analysis (Sleep Med Rev 2019) — PubMed PMID: 31102877
- Krauchi K et al., Warm feet promote the rapid onset of sleep (Nature 1999) — PubMed PMID: 10485703
- Okamoto-Mizuno K, Mizuno K, Effects of thermal environment on sleep and circadian rhythm (J Physiol Anthropol 2012) — PubMed PMID: 22738673
- Kovacs FM et al., Effect of firmness of mattress on chronic non-specific low-back pain: randomised, double-blind, controlled, multicentre trial (Lancet 2003) — PubMed PMID: 14630439
- Raymann RJ et al., Skin deep: enhanced sleep depth by cutaneous temperature manipulation (Brain 2008) — PubMed PMID: 18192289
- Lack LC et al., The relationship between insomnia and body temperatures (Sleep Med Rev 2008) — PubMed PMID: 18603220
- Liao WC, Wang L, Kuo CP, Lo C, Chiu MJ, Ting H, Effect of a warm footbath before bedtime on body temperature and sleep in older adults with good and poor sleep: an experimental crossover trial (Int J Nurs Stud 2013;50(12):1607-16) — PubMed PMID: 23669188
- Jacobson BH et al., Effect of prescribed sleep surfaces on back pain and sleep quality — PubMed PMID: 20579971
- Onen SH et al., Prevention and treatment of sleep disorders through regulation of sleeping habits — PubMed PMID: 8022726
- Van Someren EJ, More than a marker: interaction between the circadian regulation of temperature and sleep, age-related changes, and treatment possibilities — PubMed PMID: 10841209
- Murphy PJ, Campbell SS, Nighttime drop in body temperature: a physiological trigger for sleep onset? — PubMed PMID: 9322266 (Sleep 1997)
- Buman MP et al., Sitting and television viewing: novel risk factors for sleep disturbance and anxiety (Mental Health and Physical Activity) — PubMed: Buman sitting and sleep
- Cronin RS, Li M, Thompson JMD, Gordon A, Raynes-Greenow CH, Heazell AEP, Stacey T, Culling VM, Bowring V, Anderson NH, O'Brien LM, Mitchell EA, Askie LM, McCowan LME, An Individual Participant Data Meta-analysis of Maternal Going-to-Sleep Position, Interactions with Fetal Vulnerability, and the Risk of Late Stillbirth (EClinicalMedicine 2019;10:49-57) — PubMed PMID: 31193832