Sleep Hygiene — Circadian Light Exposure
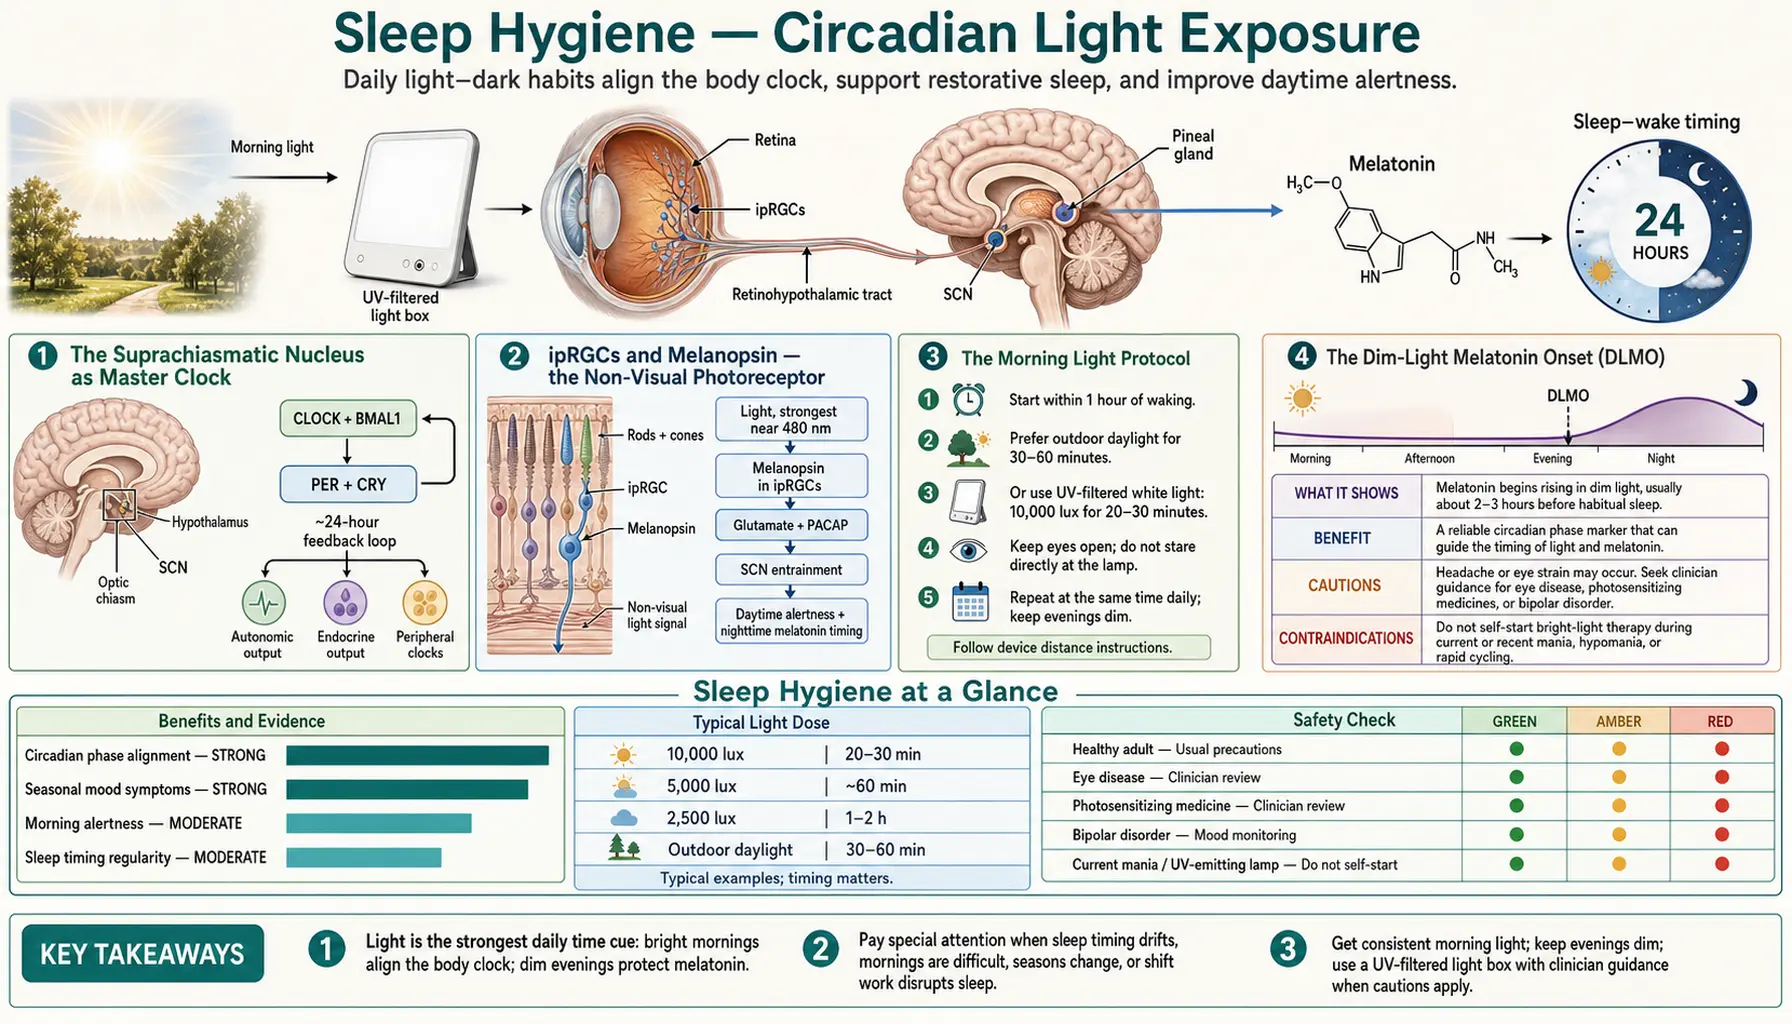
Light is the single most powerful zeitgeber ("time-giver") that the suprachiasmatic nucleus — the brain's master clock — uses to align internal biological time with the external 24-hour day. Bright morning light within 30 minutes of waking advances and stabilizes the circadian phase, suppresses daytime melatonin, increases alertness through serotonergic and cortisol pathways, and gates the evening release of melatonin roughly 14–16 hours later. Conversely, evening exposure to even modest amounts of blue-wavelength light (40–100 lux from screens, LEDs, and bright bathroom fixtures) suppresses melatonin secretion and delays sleep onset. This is not folk wisdom — it is the most rigorously characterized non-pharmacological lever in chronobiology, and it explains why sleep quality often improves dramatically with two specific habits: 10–30 minutes of outdoor light shortly after waking, and dim warm light for the last 2–3 hours before bed.
Table of Contents
- The Suprachiasmatic Nucleus as Master Clock
- ipRGCs and Melanopsin — the Non-Visual Photoreceptor
- The Morning Light Protocol
- The Dim-Light Melatonin Onset (DLMO)
- Blue Light, Screens, and Evening Melatonin Suppression
- Blackout Curtains, Eye Masks, and Bedroom Darkness
- Light Therapy for SAD and Shift Work
- Jet Lag and Phase-Shifting Protocols
- A Typical Daily Light Routine
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Suprachiasmatic Nucleus as Master Clock
The suprachiasmatic nucleus (SCN) is a pair of approximately 20,000-neuron clusters in the hypothalamus, sitting directly above the optic chiasm. It is the master pacemaker of mammalian circadian rhythm. Lesion the SCN in a rodent and all its circadian rhythms collapse — activity, body temperature, hormone secretion, feeding, sleep/wake — into a random pattern. Transplant SCN tissue from a hamster with a short-period mutation into a normal hamster, and the recipient takes on the donor's short period. The SCN is unambiguously the source.
The SCN's intrinsic rhythm is not exactly 24 hours — in humans it averages closer to 24.2 hours, with substantial individual variation. Without daily resetting, the clock would drift later by roughly 12 minutes per day. The resetting is accomplished by zeitgebers ("time-givers"), of which light is by far the most powerful. Other zeitgebers include feeding time, exercise, social cues, and ambient temperature, but their phase-shifting effects are an order of magnitude weaker than light.
Each cell in the SCN runs a transcription-translation feedback loop involving the genes BMAL1, CLOCK, PER1/2/3, and CRY1/2. The protein products of PER and CRY accumulate during the day, translocate to the nucleus at night, and repress their own transcription — an autoregulatory loop that takes approximately 24 hours to complete. Light signals reaching the SCN through the retinohypothalamic tract induce PER1/PER2 expression, which is how light resets the clock at the molecular level.
ipRGCs and Melanopsin — the Non-Visual Photoreceptor
For most of the 20th century, biologists assumed the rods and cones of the retina were the only photoreceptors in the eye. The discovery of a third class, the intrinsically photosensitive retinal ganglion cells (ipRGCs), by David Berson and colleagues (Science 2002, PubMed PMID: 11834835), reshaped the entire field of chronobiology. ipRGCs express a unique photopigment called melanopsin, with peak sensitivity at approximately 480 nm — the blue-cyan range. They project not to the visual cortex but to the SCN via the retinohypothalamic tract, the olivary pretectal nucleus (pupillary reflex), and the ventrolateral preoptic nucleus (sleep regulation).
Three practical implications follow:
- Wavelength matters more than total brightness. A blue-spectrum bulb at 200 lux can suppress melatonin more than a warm-white bulb at 500 lux. This is why amber/red night lights and "night mode" blue-light filters on devices are used as evening measures.
- Eyes-open exposure matters — not skin exposure. Vitamin D synthesis happens in the skin; circadian entrainment happens through the eyes. Light on the face or skin alone does not entrain the clock. Morning-light routines typically describe at least 10 minutes outdoors, looking around rather than directly at the sun.
- Even legally blind individuals with intact ipRGCs entrain normally. Conversely, patients with bilateral enucleation have no light entrainment and "free-run" with non-24-hour sleep-wake rhythm.
The Morning Light Protocol
The single most cost-effective intervention for sleep is morning bright-light exposure within 30–60 minutes of waking. The mechanism is simple: morning light hitting ipRGCs sends a phase-advancing signal to the SCN, which:
- Suppresses residual nocturnal melatonin, increasing daytime alertness
- Triggers the cortisol awakening response (CAR)
- Locks the phase of the evening melatonin onset 14–16 hours later
- Increases serotonin synthesis through bright-light pathways
- Sets the phase of body temperature, growth hormone, and hundreds of other circadian-regulated systems
Practical dosing: outdoor sunlight gives 10,000–100,000 lux even on overcast days; bright indoor lighting rarely exceeds 500 lux; a typical office is 200–500 lux. The order-of-magnitude difference between outdoor and indoor light is why so many people experience circadian disruption despite "spending time near a window." Behind a window, you lose a factor of 2–5 in intensity. Through clouds, you still receive 1,000–10,000 lux outside — vastly more than any indoor fixture.
The protocol commonly described: 10–30 minutes outdoors within an hour of waking. Where geography or season make this impractical, a 10,000-lux light therapy lamp at arm's length for 20–30 minutes is the validated substitute. Walking combines light exposure with low-intensity exercise (another circadian zeitgeber). Coffee, reading, or breakfast outdoors give the same light exposure.
The Dim-Light Melatonin Onset (DLMO)
The dim-light melatonin onset (DLMO) is the best single biomarker of circadian phase available outside of a sleep lab. It marks the moment in the evening when pineal melatonin secretion rises above approximately 3–4 pg/mL in serum (or 4 pg/mL in saliva). In a healthy adult with normal entrainment, DLMO occurs roughly 2–3 hours before habitual sleep onset.
DLMO can be measured in saliva at home using a commercial assay kit: collect saliva samples every 30 minutes from approximately 4 PM until 1 hour after habitual bedtime, in dim light (less than 30 lux, blue-filtered). The samples are mailed to a lab, and the result tells you precisely where your circadian phase sits. Phase-advanced individuals (DLMO earlier than 8 PM) are "morning larks"; phase-delayed individuals (DLMO later than 11 PM) are "night owls" and often have delayed sleep-wake phase disorder (DSWPD).
For most patients, formal DLMO testing is not necessary. The behavioral approximation is: track sleep onset for 2–4 weeks, subtract 2–3 hours, and you have an approximate DLMO. Combined with chronotype questionnaires (Morningness-Eveningness Questionnaire, Munich Chronotype Questionnaire), this is usually sufficient to plan timing of light exposure, exercise, meals, and supplementary melatonin.
Blue Light, Screens, and Evening Melatonin Suppression
The Chang et al. 2015 PNAS trial (PMID 25535358) is the cleanest demonstration of the screen-light effect on sleep. Participants spent 5 evenings reading a print book and 5 evenings reading from a light-emitting tablet eReader in dim ambient light. Compared to print, tablet reading:
- Suppressed evening melatonin secretion by 55%
- Delayed melatonin onset by approximately 1.5 hours
- Extended sleep latency by 10 minutes
- Reduced REM sleep duration
- Decreased morning alertness measurably for several hours after waking
The mechanism is melanopsin activation by 460–480 nm blue wavelengths emitted by white LED backlights. Mitigation strategies in approximate order of effectiveness:
- No bright screens for 1–2 hours before bed. The most effective measure is the simplest.
- Amber blue-blocker glasses (filtering 90%+ of light below 530 nm) for the 2–3 hours before bed, when screens are in use.
- A dim room. Overhead lighting on dim warm-white or amber bulbs (2700K or lower); bedside lamps with amber bulbs at minimum brightness.
- Night mode on phones/tablets/laptops (device night-mode and blue-light-filtering settings). Effective at the modest end — reduces blue but does not eliminate it.
- E-ink readers rather than LCD/OLED tablets. E-ink uses reflected ambient light, not backlight.
Blackout Curtains, Eye Masks, and Bedroom Darkness
The benchmark for a dark bedroom is a moonless night. Streetlight intrusion through thin curtains, the glow of charging electronics, or a partner's reading light can all elevate melatonin-suppressing ambient light above the 5–10 lux threshold at which biological effects begin. Common measures:
- Blackout curtains or roller shades rated for at least 99% light blocking. Side rails or a wraparound rod close the gap along the edge.
- A contoured sleep mask for travel or for partners on different schedules. Flat eye masks press on the eyelids, which is described as disrupting REM eye movement.
- Covered or removed glowing electronics. The blue LED on a charging laptop or the bright digital clock are both meaningful sources at night.
- Amber or red night lights for bathroom trips. A 1-2 watt amber LED night light provides enough illumination for safety without triggering melanopsin.
A 2023 study in the journal Sleep (Kim and colleagues, PubMed PMID: 35729737) measured light with a wrist-worn recorder for 7 days in 552 adults aged 63–84. Those with any light during the darkest 5 hours of the night had a higher prevalence of obesity, diabetes and hypertension (but not high cholesterol) than those with none, after adjusting for age, sex, race, season and sleep measures. The study looked at one point in time, so it shows an association, not cause. The mechanism is presumed to be circadian disruption through ipRGCs even with closed eyelids (eyelids transmit approximately 5–10% of incident light).
Light Therapy for SAD and Shift Work
Bright light therapy (BLT) is a first-line treatment for seasonal affective disorder (SAD) and a useful adjunct for non-seasonal major depression, delayed sleep-wake phase disorder, and shift work disorder. The standard prescription is a 10,000-lux full-spectrum white-light box, used 20–30 minutes immediately after waking, with the light at arm's length and the user's eyes open but not staring directly at the source.
Efficacy in SAD is comparable to fluoxetine in head-to-head trials, with a faster onset (1–2 weeks versus 4–6 weeks) and fewer side effects. Common minor side effects include mild eye strain, headache, and (rarely) hypomania induction in patients with bipolar disorder.
For shift workers on permanent night shifts, the protocol inverts: bright light during work hours to maintain alertness, dark sunglasses on the morning commute home, blackout bedroom for daytime sleep. Strategic light exposure can shift the circadian phase by 1–2 hours per day, which is the rate of natural phase shifting after transmeridian travel.
Jet Lag and Phase-Shifting Protocols
Jet lag is the symptomatic mismatch between an individual's internal circadian phase and the external time zone after rapid eastward or westward travel. The human SCN can naturally shift by approximately 1 hour per day after transmeridian travel, so a 6-hour eastward flight takes about 6 days to fully adapt without intervention. Strategic light exposure (and sometimes timed melatonin) can roughly double that rate.
General principle: eastward travel requires phase advance (the body clock moves earlier to match the destination), which means morning light in the destination time zone and no evening light. Westward travel requires phase delay (the body clock moves later), which means evening light and no morning light. Light-scheduling apps produce personalized light-exposure schedules from a travel itinerary.
Supplementary tools: low-dose melatonin (0.3–0.5 mg, not 3–10 mg) taken at the destination's bedtime for 3–5 nights can accelerate phase shifting. Other commonly described measures: no alcohol on the flight (alcohol suppresses REM sleep), plenty of fluids, and meals on the destination's schedule from day one.
A Typical Daily Light Routine
The everyday light-hygiene routine commonly described for an adult on a standard daytime schedule:
- Morning (within 60 min of waking): 10–30 minutes outdoors. Walk, coffee on a porch, or breakfast at a sunlit window when outdoors is impossible. No sunglasses for the first segment.
- Midday: Brief outdoor break (5–15 min) if possible. Reinforces the daytime light signal.
- 2–3 hours before sleep: Dim overhead lighting, warm-white bedside lamps, screen brightness at minimum.
- 1 hour before sleep: Phone night mode at maximum warmth; amber blue-blockers when screens are in use; no bright bathroom lights when brushing teeth.
- Sleep environment: Genuine darkness. Blackout curtains, no glowing electronics, amber night light only if needed for safety.
- Throughout the night: No phone checks; the phone face-down or in another room.
Cautions
- Staring directly at the sun damages the retina. Brief glances toward the sky are harmless; direct staring causes retinal damage (solar retinopathy). The same applies to 10,000-lux light boxes — the usual placement is 16–24 inches from the face, slightly above and to the side of the visual field.
- Bipolar disorder. Bright light therapy can trigger mania or rapid cycling in approximately 5–10% of bipolar patients.
- Retinal disease. Macular degeneration, diabetic retinopathy and other significant retinal disease are listed as cautions for bright light therapy, because a damaged retina may be more vulnerable to intense light.
- Drugs that increase photosensitivity — tetracyclines, fluoroquinolones, amiodarone, isotretinoin, St. John's wort — can increase the risk of light-induced eye damage during bright light therapy.
- Melatonin supplementation is unregulated and dosed wildly inconsistently across products. The low doses described for phase shifting are 0.3–0.5 mg, while drugstore tablets commonly contain 3–10 mg; the USP Verified mark means an independent laboratory checked that the product contains what its label states.
Key Research Papers
- Berson DM et al., Phototransduction by retinal ganglion cells that set the circadian clock (Science 2002) — PubMed PMID: 11834835
- Hattar S et al., Melanopsin-containing retinal ganglion cells: architecture, projections, and intrinsic photosensitivity (Science 2002) — PubMed PMID: 11834834
- Czeisler CA et al., Bright light induction of strong (type 0) resetting of the human circadian pacemaker (Science 1989) — PubMed PMID: 2734611
- Chang AM et al., Evening use of light-emitting eReaders negatively affects sleep, circadian timing, and next-morning alertness (PNAS 2015) — PubMed PMID: 25535358
- Brainard GC et al., Action spectrum for melatonin regulation in humans: evidence for a novel circadian photoreceptor (J Neurosci 2001) — PubMed PMID: 11487664
- Wright KP et al., Entrainment of the human circadian clock to the natural light-dark cycle (Curr Biol 2013) — PubMed PMID: 23910656
- Cajochen C et al., High sensitivity of human melatonin, alertness, thermoregulation, and heart rate to short wavelength light (J Clin Endocrinol Metab 2005) — PubMed PMID: 15585546
- Lewy AJ, The dim light melatonin onset, melatonin assays and biological rhythm research in humans (Biol Signals Recept 1999) — PubMed PMID: 10085467
- Burgess HJ et al., Human phase response curves to three days of daily melatonin: 0.5 mg versus 3.0 mg (J Clin Endocrinol Metab 2010) — PubMed PMID: 20410229
- Khalsa SBS et al., A phase response curve to single bright light pulses in human subjects (J Physiol 2003) — PubMed PMID: 12717008
- Eastman CI et al., Bright light treatment of winter depression: a placebo-controlled trial (Arch Gen Psychiatry 1998) — PubMed PMID: 9783558
- Pail G et al., Bright-light therapy in the treatment of mood disorders (Neuropsychobiology 2011) — PubMed PMID: 21811085
- Kim M et al., Light at night in older age is associated with obesity, diabetes, and hypertension (Sleep 2023) — PubMed PMID: 35729737