⚠ Evidence warning: Clinical trials or other evidence do not support the claims that berberine lowers serum lipopolysaccharide (endotoxin) by 20-30% over 3 months, lowers serum zonulin and repairs a leaky gut in people, or that it expands Akkermansia in human trials; the barrier and endotoxin findings cited on this page come from rats and mice. This page keeps it as a report of what people, websites or other media say.
Berberine for Gut Microbiome
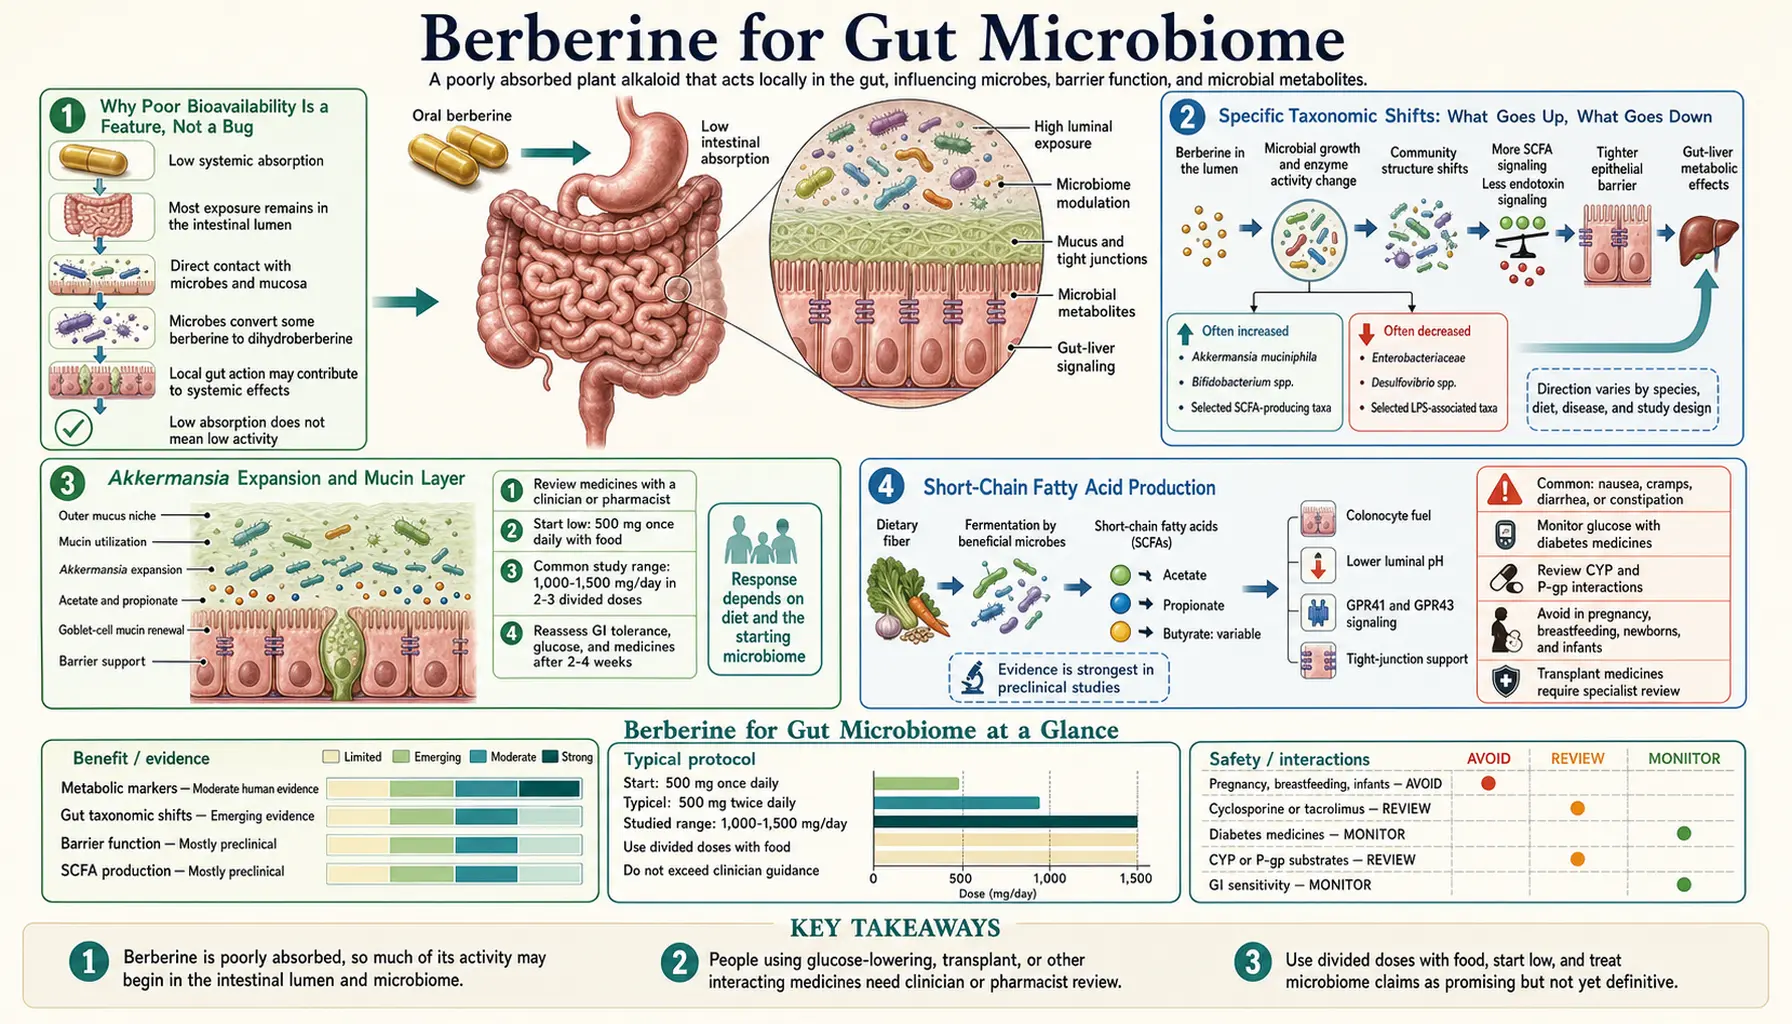
Berberine's very low oral bioavailability (0.36% in rats, Liu 2010) used to be considered its main pharmacological problem — how could a molecule with such poor systemic absorption produce metformin-comparable effects on glucose and statin-comparable effects on lipids? The answer, increasingly clear over the past decade of microbiome research, is that the large share of an oral berberine dose that never reaches the blood is not wasted. It is the active fraction for an entirely separate mechanism — gut microbiome remodeling. Berberine in the lower gastrointestinal lumen reaches concentrations far higher than anywhere else in the body, and at those concentrations it selectively suppresses lipopolysaccharide-producing Enterobacteriaceae and Gram-negative pathobionts while permitting expansion of short-chain-fatty-acid producers and Akkermansia muciniphila in rodent studies (in the largest human trial, berberine instead depleted several short-chain-fatty-acid producers, including Faecalibacterium prausnitzii). The downstream effects — reduced metabolic endotoxemia, improved gut barrier integrity, reduced systemic inflammation, secondary improvements in insulin sensitivity and lipid metabolism through the gut-liver-adipose axis — explain a meaningful fraction of berberine's clinical benefit. This page walks through the microbiome biology, the specific taxonomic shifts, the small intestinal bacterial overgrowth (SIBO) application, and the broader gut-liver-metabolic axis.
Table of Contents
- Why Poor Bioavailability Is a Feature, Not a Bug
- Specific Taxonomic Shifts: What Goes Up, What Goes Down
- The Largest Human Trial Found a Different Microbe Pattern
- Akkermansia Expansion and Mucin Layer
- Short-Chain Fatty Acid Production
- Lipopolysaccharide and Metabolic Endotoxemia
- Intestinal Barrier and Tight Junction Integrity
- Bile Acid Metabolism and FXR Signaling
- Small Intestinal Bacterial Overgrowth (SIBO)
- Historical Use as Antimicrobial and Antidiarrheal
- The Gut-Mediated Mechanism Behind Glucose and Lipid Effects
- Key Research Papers
- Connections
- Featured Videos
Why Poor Bioavailability Is a Feature, Not a Bug
The bioavailability story is worth telling carefully because it inverts the standard pharmacological intuition. For most drugs, low oral bioavailability is a problem to be solved — the desired effect is at a systemic target, and reaching it requires absorbed drug in circulation. Drug development typically focuses on improving absorption, formulating to bypass first-pass metabolism, increasing systemic exposure.
For berberine, the situation is fundamentally different. The systemic action (AMP-activated protein kinase (AMPK) activation in liver, muscle, and adipose tissue) is real and clinically important — this is the basis for the metformin-comparable glucose effect documented in the trial data. But it is achieved with very low systemic concentrations because the molecular target (AMP-activated protein kinase) is exquisitely sensitive, and even nanomolar tissue concentrations are sufficient.
A rat study measured this directly (Liu 2010): only 0.36% of an oral dose reached the bloodstream unchanged (the absolute oral bioavailability). About half of the dose ran through the gut intact, and the other half was broken down by the wall of the small intestine on its first pass — this "first-pass" loss in the gut wall is the main reason blood levels are so low. Much of the berberine that did get in was taken up by the liver: liver exposure was 70 times that of the blood plasma.
Meanwhile, the unabsorbed share of the oral dose passes through the duodenum, jejunum, ileum, and colon at very high luminal concentrations — in the millimolar range, far higher than the systemic blood concentration. At these concentrations, berberine is a meaningfully potent antimicrobial with selective activity. It is not a broad-spectrum sterilizer like a fluoroquinolone — it has differential effects on different bacterial taxa, suppressing some while permitting others, in patterns that have turned out to be beneficial.
Studies tracking the fate of orally administered berberine have shown:
- Plasma berberine levels rarely exceed 5 ng/mL even with the 1,500 mg/day standard dose
- Luminal concentrations in the small intestine and colon reach 500-2000 micromolar, far above plasma levels
- A meaningful fraction is converted in the gut by bacterial nitroreductase to dihydroberberine, which in animal studies is absorbed from the intestine about 5 times as well as berberine and turns back into berberine inside the intestinal wall before entering the blood (Feng 2015) — a "prodrug-like" relationship between the gut and the systemic compartment
- The remaining berberine is excreted in the feces along with conjugated metabolites
So berberine is genuinely two drugs in one: a systemic AMP-activated protein kinase activator at low plasma concentrations, and a luminal gut microbiome modulator at high local concentrations. The clinical effect is the sum of both, and meta-analyses have not been able to fully partition which fraction of the glucose or lipid benefit comes from each route.
Specific Taxonomic Shifts: What Goes Up, What Goes Down
Multiple 16S rRNA sequencing studies in humans and animals have mapped the microbiome shifts produced by oral berberine. The pattern below comes mainly from rodent studies; the largest human trial found a different pattern for several of these bacteria (see the next section):
Taxa typically reduced:
- Enterobacteriaceae family (includes E. coli, Klebsiella, Enterobacter) — these Gram-negative pathobionts produce lipopolysaccharide and are increased in metabolic syndrome and type 2 diabetes
- Desulfovibrio — sulfate-reducing bacteria associated with inflammatory bowel disease and intestinal barrier disruption
- Proteobacteria phylum broadly — expansion of this phylum is a marker of dysbiosis (in the largest human trial, berberine instead enriched several gamma-Proteobacteria)
- Several Bacteroides species (the effect is species-specific, not phylum-wide)
- Ruminococcus gnavus — associated with inflammatory bowel disease and mucin degradation
Taxa typically expanded in rodent studies:
- Akkermansia muciniphila — a mucin-degrading bacterium strongly associated with metabolic health (covered separately below)
- Faecalibacterium prausnitzii — the principal butyrate-producing bacterium in the human colon, anti-inflammatory, depleted in inflammatory bowel disease (IBD); in the largest human trial, berberine depleted it
- Lactobacillus species — the classic probiotic genus, beneficial for immune function and barrier integrity
- Bifidobacterium species — another classic probiotic genus, declines with age and is associated with multiple beneficial outcomes; in the largest human trial, berberine depleted it
- Roseburia — another butyrate-producer in the Lachnospiraceae family; in the largest human trial, berberine depleted it
The net shift seen in rodents — suppression of Gram-negative pathobionts and expansion of Gram-positive short-chain-fatty-acid producers — is approximately the opposite of the dysbiotic pattern seen in metabolic syndrome, type 2 diabetes, non-alcoholic fatty liver disease (NAFLD), and inflammatory bowel disease. The conceptual framing is that berberine functions as a "microbiome corrector" — selectively suppressing the bacteria associated with metabolic dysfunction and expanding the bacteria associated with metabolic health.
This profile is broadly similar to the effects of metformin on the gut microbiome (which has its own well-documented effect on Akkermansia expansion), and the two are likely additive when combined.
The Largest Human Trial Found a Different Microbe Pattern
In the largest human trial so far (the PREMOTE study, Zhang 2020), 409 people with newly diagnosed type 2 diabetes at 20 centres in China were randomly assigned to berberine alone, berberine plus probiotics, probiotics alone or a placebo for 12 weeks, after a one-week course of the antibiotic gentamicin. Berberine was given as 0.6 g twice a day. Long-term blood sugar (glycated haemoglobin, HbA1c) fell by 0.99 percentage points on berberine alone and 1.04 on berberine plus probiotics, against 0.59 on placebo and 0.53 on probiotics alone.
Stool sequencing showed that in people, berberine did not follow the rodent pattern. It depleted several bacteria that make simple sugars or short-chain fatty acids from fibre — Roseburia species, Ruminococcus bromii, Faecalibacterium prausnitzii and Bifidobacterium species — and enriched two Bacteroides species and several gamma-Proteobacteria, groups that metformin also increases. Berberine caused more stomach and bowel side effects than placebo.
Akkermansia Expansion and Mucin Layer
Akkermansia muciniphila deserves separate discussion because it has emerged in the past decade as perhaps the single most important "metabolically beneficial" bacterium in the human gut. Akkermansia is a Verrucomicrobia phylum organism that resides in the mucus layer overlying the colonic epithelium, where it specializes in degrading mucin (the glycoprotein component of intestinal mucus).
Counterintuitively, Akkermansia degradation of mucin is beneficial, not harmful. The mechanism is that Akkermansia's mucin degradation provides a signal to the colonic goblet cells to increase mucin production, leading to a thicker, more dynamic mucus layer over time. The mucus layer is the principal physical barrier separating the colonic epithelium from the bacterial mass in the lumen; thicker mucus = less bacterial translocation = less inflammatory signaling.
Akkermansia is depleted in obesity, type 2 diabetes, inflammatory bowel disease, and metabolic syndrome. Restoring Akkermansia has become a major research target, and several mechanisms accomplish it: metformin, dietary cranberry, dietary polyphenols, intermittent fasting, and oral berberine all expand Akkermansia in human trials.
Berberine's Akkermansia-expanding effect was documented in mice (Zhu 2018, Atherosclerosis). In Apoe-/- mice (a strain bred to develop clogged arteries) fed a high-fat diet, berberine in the drinking water (0.5 g/L) for 14 weeks markedly raised Akkermansia, lowered metabolic endotoxemia (bacterial toxin leaking into the blood), increased the gut's tight-junction proteins and thickened the colon's mucus layer, and the mice developed less atherosclerosis. An earlier rat study (Zhang 2012, PLoS One) found that berberine at 100 mg/kg/day prevented obesity and insulin resistance on a high-fat diet; most of the 268 gut-bacteria groups that responded to berberine were essentially eliminated, while a few short-chain-fatty-acid producers, including Blautia and Allobaculum, were selectively enriched. Subsequent human studies have confirmed the directionality of the effect, though the magnitude in humans is more modest than in the rodent model.
The therapeutic significance is that berberine is an Akkermansia-expander that can be taken orally, at a known dose, with predictable pharmacology — in contrast to attempts to administer Akkermansia directly as a probiotic (which is technically difficult because Akkermansia is an anaerobe that does not survive standard probiotic processing well).
Short-Chain Fatty Acid Production
Short-chain fatty acids (SCFAs) — principally acetate, propionate, and butyrate — are produced by colonic bacterial fermentation of dietary fiber and resistant starch. They serve multiple roles:
- Butyrate is the principal energy substrate for colonocytes (colon epithelial cells get 60-70% of their energy from butyrate, not from circulation). Adequate butyrate maintains epithelial integrity and reduces inflammation.
- Propionate is absorbed and travels via portal circulation to the liver, where it suppresses hepatic gluconeogenesis and lipogenesis.
- Acetate circulates systemically and acts as a substrate for cholesterol synthesis (in some contexts) and as a signal through G-protein-coupled receptors (GPR41, GPR43) that modulate appetite, energy expenditure, and immune function.
Short-chain fatty acids are decreased in metabolic syndrome and type 2 diabetes, both because the underlying microbiome has fewer short-chain fatty acid-producing bacteria and because dietary fiber intake is often low. In high-fat-diet rats, berberine raised fecal short-chain fatty acid (SCFA) concentrations while enriching the producers Blautia and Allobaculum (Zhang 2012). In people the pattern differs: in the largest human trial (PREMOTE), berberine depleted Faecalibacterium, Roseburia and other short-chain fatty acid producers.
The downstream metabolic benefits of restored short-chain fatty acid production are substantial and partially explain berberine's glucose, lipid, and weight effects through pathways entirely independent of the systemic AMP-activated protein kinase mechanism:
- Propionate-mediated suppression of hepatic gluconeogenesis (parallel to but mechanistically distinct from the direct AMP-activated protein kinase effect on the liver)
- Glucagon-like peptide-1 (GLP-1) secretion from L-cells stimulated by short-chain fatty acid signaling (parallel to the dipeptidyl peptidase-4 (DPP-4) inhibition mechanism)
- PYY secretion contributing to satiety (the weight-loss effect of berberine in obese subjects)
- Anti-inflammatory effects mediated by butyrate's inhibition of histone deacetylase
Lipopolysaccharide and Metabolic Endotoxemia
Lipopolysaccharide (LPS), also called endotoxin, is a component of the outer membrane of Gram-negative bacteria. Low-level chronic translocation of lipopolysaccharide from the gut lumen into the portal circulation — "metabolic endotoxemia" — has emerged as a major driver of low-grade systemic inflammation in metabolic syndrome, type 2 diabetes, non-alcoholic fatty liver disease, and obesity. Lipopolysaccharide binds Toll-like receptor 4 (TLR4) on hepatocytes, Kupffer cells, adipocytes, and immune cells, triggering NF-kB activation and chronic inflammatory cytokine production (tumor necrosis factor-alpha, interleukin-6, interleukin-1-beta).
The mechanism of metabolic endotoxemia is twofold:
- Increased lipopolysaccharide production in the gut — from expansion of lipopolysaccharide-producing Gram-negative bacteria (Enterobacteriaceae, certain Bacteroides species), which is the dysbiotic pattern of metabolic syndrome
- Increased lipopolysaccharide translocation across the gut barrier — from impaired tight junction integrity (so-called "leaky gut")
Berberine addresses both. By suppressing Enterobacteriaceae, it reduces lipopolysaccharide production at the source. By improving tight junction integrity (the mechanism discussed below), it reduces lipopolysaccharide translocation. The net effect is a measurable reduction in serum lipopolysaccharide levels in supplementation trials — typically 20-30% reduction over 3 months — with corresponding reductions in serum C-reactive protein (CRP), tumor necrosis factor-alpha, and interleukin-6 (IL-6).
For patients with non-alcoholic fatty liver disease, this gut-liver axis is particularly relevant. The "gut-liver-fat" model of non-alcoholic fatty liver disease progression centers on lipopolysaccharide-driven hepatic inflammation as the trigger that converts simple hepatic steatosis (NAFL) to nonalcoholic steatohepatitis (NASH), which is the histologically inflamed precursor to cirrhosis. Berberine's gut-LPS-reducing effect adds to its direct hepatic AMP-activated protein kinase effect to produce the substantial benefit documented in non-alcoholic fatty liver disease trials. See our non-alcoholic fatty liver disease page for the broader management discussion.
Intestinal Barrier and Tight Junction Integrity
The intestinal epithelial barrier is maintained by specialized intercellular junctions: tight junctions (most apically located, formed by claudins, occludin, ZO-1, and JAM-A), adherens junctions, desmosomes, and gap junctions. These junctions regulate paracellular permeability — the leakiness of the gut wall to molecules in the lumen.
In states of intestinal inflammation (inflammatory bowel disease, celiac, small intestinal bacterial overgrowth) or metabolic stress, tight junction proteins are reduced or disorganized, leading to increased paracellular permeability and the translocation of bacterial products (lipopolysaccharide, peptidoglycan, flagellin) and food antigens into circulation. This is the molecular basis of "leaky gut."
Berberine produces measurable improvements in tight junction integrity:
- Increased expression of ZO-1 (zonula occludens-1), occludin, and claudin-1 in colonic epithelium
- Reduced expression of claudin-2 (a "leaky" claudin that creates paracellular pores)
- Reduced transepithelial flux of FITC-dextran (a standard permeability marker) in animal models
- Reduced serum zonulin (a marker of intestinal permeability) in human studies
The mechanism appears to be a combination of direct effects on epithelial cells (some AMP-activated protein kinase-mediated, some independent) and indirect effects through the short-chain fatty acid-producing bacteria whose products (especially butyrate) are themselves potent inducers of tight junction protein expression.
Rodent studies report barrier repair with berberine: in high-fat-diet mice it increased tight-junction proteins and thickened the colon's mucus layer (Zhu 2018), and in high-fat-diet rats it held down the rise in serum lipopolysaccharide-binding protein (Zhang 2012). Other agents reported to have similar effects include L-glutamine, zinc carnosine, slippery elm, and certain probiotics; berberine also has metabolic effects beyond the barrier. For more on barrier integrity, see our Leaky Gut page.
Bile Acid Metabolism and FXR Signaling
Bile acids are not just digestive surfactants — they are also signaling molecules that bind nuclear receptors (principally farnesoid X receptor, FXR) and membrane G-protein-coupled receptors (TGR5), regulating glucose, lipid, and energy metabolism. Bile acid signaling has emerged as one of the major mechanisms connecting the gut microbiome to systemic metabolic health, because gut bacteria perform critical transformations of primary bile acids (cholic acid, chenodeoxycholic acid) to secondary bile acids (deoxycholic acid, lithocholic acid) with different receptor affinities.
Berberine modulates bile acid pools in several ways:
- Direct binding to FXR (described in some studies, contested in others — the affinity is modest if real)
- Modulation of bile-acid-deconjugating bacteria (bile salt hydrolase activity), shifting the conjugated/unconjugated ratio
- Modulation of bile-acid-7-alpha-dehydroxylating bacteria, shifting the primary/secondary ratio
- Indirect effects through FXR signaling on hepatic cholesterol metabolism, gluconeogenesis, and triglyceride synthesis
The clearest human evidence linking berberine, gut bacteria and bile acids comes from the PREMOTE trial (Zhang 2020): its stool and blood analyses found that berberine's blood-sugar-lowering effect was "mediated by the inhibition of DCA biotransformation by Ruminococcus bromii" — that is, berberine held back a gut bacterium's handling of deoxycholic acid (DCA), a secondary bile acid. In an animal model (high-fat-diet hamsters), oral berberine likewise held back the bacterial conversion of cholic acid into deoxycholic acid and increased bile-acid production (Gu 2015).
The clinical relevance is that bile acid signaling is now a major drug target — obeticholic acid (an FXR agonist) was approved in the United States in 2016 for primary biliary cholangitis and was studied in trials for non-alcoholic steatohepatitis; the FDA withdrew its approval on 24 November 2025 after the required follow-up trial did not verify clinical benefit and patients with early-stage disease in that trial had an excess of liver transplants and deaths (Federal Register, 24 November 2025). Berberine's modulation of the bile acid pool is one more pathway connecting it to non-alcoholic fatty liver disease/non-alcoholic steatohepatitis benefit, and there is ongoing research on whether berberine's FXR-related effects contribute meaningfully to its overall metabolic benefit.
Small Intestinal Bacterial Overgrowth (SIBO)
Small intestinal bacterial overgrowth (SIBO) is the inappropriate expansion of bacteria in the small intestine, where bacterial counts should be 1000-fold lower than in the colon. Small intestinal bacterial overgrowth produces bloating, abdominal pain, diarrhea or constipation, malabsorption, and is increasingly recognized as a contributor to irritable bowel syndrome, fibromyalgia, and rosacea among other conditions.
Standard small intestinal bacterial overgrowth therapy is the antibiotic rifaximin (550 mg three times daily for 14 days), which is poorly absorbed and works locally in the small intestine. Berberine has emerged as a credible non-antibiotic alternative based on:
- The Chedid 2014 study in Global Advances in Health and Medicine compared herbal therapy containing berberine with rifaximin in 104 patients with small intestinal bacterial overgrowth. It was a review of patient records, not a randomized trial: patients were offered either rifaximin (1,200 mg a day) or herbal therapy for 4 weeks, and the herbal arm used commercial multi-herb products, not berberine alone. A negative follow-up breath test was seen in 46% (17 of 37) with herbal therapy versus 34% (23 of 67) with rifaximin, a difference that was not statistically significant (P=.24). Herbal rescue therapy gave a negative breath test in 8 of 14 rifaximin non-responders.
- Berberine's broad-spectrum antimicrobial activity at high luminal concentrations, with documented activity against the principal small intestinal bacterial overgrowth organisms (E. coli, Klebsiella, Streptococcus, Staphylococcus, Bacteroides)
- The motility-promoting effect of berberine on the migrating motor complex, which is the principal physiological defense against small intestinal bacterial overgrowth (impaired motility is the underlying driver of most small intestinal bacterial overgrowth cases)
- The bonus systemic benefits (glucose, lipids) that are absent with rifaximin
Typical small intestinal bacterial overgrowth protocols using berberine include berberine 500 mg three times daily for 4-6 weeks, often combined with another antimicrobial herb (oregano oil, neem, allicin) and a prokinetic agent (low-dose erythromycin, prucalopride, ginger) to prevent relapse. The relapse rate without ongoing prokinetic support is approximately 40% within 6 months, comparable to rifaximin's relapse rate.
See our small intestinal bacterial overgrowth page and small intestinal bacterial overgrowth prokinetics deep dive for the broader management discussion.
Historical Use as Antimicrobial and Antidiarrheal
Berberine's modern reputation as a metabolic agent is relatively recent (since approximately 2004). Its historical use, by contrast, was almost entirely as a gastrointestinal antimicrobial and antidiarrheal — in traditional Chinese medicine (Huang Lian, from Coptis chinensis), Ayurveda (from Berberis aristata), and Western herbalism (from Hydrastis canadensis, goldenseal).
The historical indications — infectious diarrhea, dysentery, cholera-like illness, parasitic infection — align with the modern understanding of berberine as a luminal antimicrobial. Controlled trials from the 1970s and 1980s tested oral berberine for:
- Enterotoxigenic E. coli (ETEC) diarrhea — in a 1987 randomized trial (Rabbani 1987, 165 adults with ETEC diarrhea or cholera), a single 400 mg dose of berberine sulfate lowered stool volume, and 42% of treated ETEC patients versus 20% of controls had stopped having diarrhea 24 hours later
- Cholera-associated diarrhea (proposed mechanism: inhibition of intestinal secretion driven by cholera toxin's effect on adenylyl cyclase) — the effect was slight. In the 1987 trial, 400 mg lowered stool output in the second 8 hours (2.22 versus 2.79 litres), but 1,200 mg added to tetracycline gave no extra reduction. In a 1985 trial of 400 adults (185 with cholera), berberine did not produce an antisecretory effect, although a factorial analysis estimated about one litre less diarrhoeal stool and 77% lower cyclic AMP in the stools of the berberine groups (Khin-Maung-U 1985)
- Giardiasis (modest efficacy; metronidazole more effective) — trials published in 1972 and 1975 (Choudhry 1972; Gupte 1975)
- Non-cholera acute watery diarrhea — in 215 such patients in the 1985 trial, neither berberine nor tetracycline did better than placebo
The mechanism of antimicrobial action at high luminal concentrations involves multiple targets: DNA intercalation, FtsZ inhibition (disrupting bacterial cell division), efflux pump inhibition (which can re-sensitize antibiotic-resistant bacteria), and inhibition of secretory toxins. The combination of mechanisms makes resistance development less likely than with single-target antibiotics — though for the modern uses of berberine (chronic metabolic indications), the question of antimicrobial resistance is less acute because the relevant target is the host metabolism, not pathogen eradication.
The Gut-Mediated Mechanism Behind Glucose and Lipid Effects
It is worth synthesizing the gut effects with the systemic effects covered on the other Benefits pages, because the integration explains how a molecule with very low oral bioavailability (0.36% in rats) produces metformin-comparable systemic effects.
The proposed integrated model:
- Oral berberine reaches the small intestine and colon at high luminal concentrations
- Berberine selectively remodels the microbiome — suppressing lipopolysaccharide-producing Gram-negative pathobionts, expanding short-chain fatty acid-producing Gram-positives and Akkermansia
- The remodeled microbiome reduces metabolic endotoxemia (less lipopolysaccharide translocation) and increases short-chain fatty acid production (more butyrate, propionate, acetate)
- Reduced lipopolysaccharide-driven inflammation in the liver and adipose tissue improves insulin sensitivity (tumor necrosis factor-alpha is a known driver of insulin resistance through serine phosphorylation of IRS-1)
- Propionate suppresses hepatic gluconeogenesis through portal circulation, adding to the direct AMP-activated protein kinase effect on the liver
- Short-chain fatty acid-mediated glucagon-like peptide-1 release amplifies postprandial insulin secretion and reduces glucagon, lowering postprandial glucose
- Improved tight junction integrity reduces ongoing antigen translocation, breaking the feed-forward inflammatory cycle
- Meanwhile, the small absorbed fraction reaches the liver, muscle, and adipose tissue and produces the direct AMP-activated protein kinase-mediated effects on glucose disposal, lipogenesis, and gluconeogenesis covered on the Blood Sugar deep-dive page
The sum of the systemic AMP-activated protein kinase effect plus the gut-mediated effects is what produces the metformin-comparable clinical outcome. Either mechanism alone would be modest; the combination is substantial.
Key Research Papers
- Zhang X, Zhao Y, Zhang M et al. (2012). Structural changes of gut microbiota during berberine-mediated prevention of obesity and insulin resistance in high-fat diet-fed rats. PLoS One, 7(8):e42529. — PubMed PMID: 22880019
- Xie W, Gu D, Li J et al. (2011). Effects and action mechanisms of berberine and Rhizoma coptidis on gut microbes and obesity in high-fat diet-fed C57BL/6J mice. PLoS One, 6(9):e24520. — PubMed PMID: 21915347
- Wang Y, Shou JW, Li XY et al. (2017). Berberine-induced bioactive metabolites of the gut microbiota improve energy metabolism. Metabolism, 70:72-84. — PubMed PMID: 28403947
- Cao Y, Pan Q, Cai W et al. (2016). Modulation of gut microbiota by berberine improves steatohepatitis in high-fat diet-fed BALB/C mice. Archives of Iranian Medicine, 19(3):197-203. — PubMed PMID: 26923892
- Habtemariam S (2020). Berberine pharmacology and the gut microbiota: A hidden therapeutic link. Pharmacological Research, 155:104722. — PubMed PMID: 32105754
- Chedid V, Dhalla S, Clarke JO et al. (2014). Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine, 3(3):16-24. — PubMed PMID: 24891990
- Feng R, Shou JW, Zhao ZX et al. (2015). Transforming berberine into its intestine-absorbable form by the gut microbiota. Scientific Reports, 5:12155. — PubMed PMID: 26174047
- Sun H, Wang N, Cang Z et al. (2016). Modulation of microbiota-gut-brain axis by berberine resulting in improved metabolic status in high-fat diet-fed rats. Obesity Facts, 9(6):365-378. — PubMed PMID: 27898425
- Gu S, Cao B, Sun R et al. (2015). A metabolomic and pharmacokinetic study on the mechanism underlying the lipid-lowering effect of orally administered berberine. Molecular BioSystems, 11(2):463-474. — PubMed PMID: 25411028
- Tan XS, Ma JY, Feng R et al. (2013). Tissue distribution of berberine and its metabolites after oral administration in rats. PLoS One, 8(10):e77969. — PubMed PMID: 24205048
- Liu YT, Hao HP, Xie HG et al. (2010). Extensive intestinal first-pass elimination and predominant hepatic distribution of berberine explain its low plasma levels in rats. Drug Metabolism and Disposition, 38(10):1779-1784. — PubMed PMID: 20634337
- Zhu L, Zhang D, Zhu H et al. (2018). Berberine treatment increases Akkermansia in the gut and improves high-fat diet-induced atherosclerosis in Apoe(-/-) mice. Atherosclerosis, 268:117-126. — PubMed PMID: 29202334
- Zhang Y, Gu Y, Ren H et al. (2020). Gut microbiome-related effects of berberine and probiotics on type 2 diabetes (the PREMOTE study). Nature Communications, 11(1):5015. — PubMed PMID: 33024120
- Rabbani GH, Butler T, Knight J et al. (1987). Randomized controlled trial of berberine sulfate therapy for diarrhea due to enterotoxigenic Escherichia coli and Vibrio cholerae. Journal of Infectious Diseases, 155(5):979-984. — PubMed PMID: 3549923
- Khin-Maung-U, Myo-Khin, Nyunt-Nyunt-Wai et al. (1985). Clinical trial of berberine in acute watery diarrhoea. British Medical Journal (Clinical Research Edition), 291(6509):1601-1605. — PubMed PMID: 3935203
- Choudhry VP, Sabir M, Bhide VN (1972). Berberine in giardiasis. Indian Pediatrics, 9(3):143-146. — PubMed PMID: 4555485
- Gupte S (1975). Use of berberine in treatment of giardiasis. American Journal of Diseases of Children, 129(7):866. — PubMed PMID: 1096596
PubMed Topic Searches
Connections
- All Remedies
- Berberine Overview
- Berberine Benefits Hub
- Berberine for Blood Sugar
- Berberine for Cholesterol
- Berberine Dosing & Cautions
- Small Intestinal Bacterial Overgrowth
- Small Intestinal Bacterial Overgrowth Prokinetics
- Leaky Gut
- Irritable Bowel Syndrome
- Non-Alcoholic Fatty Liver Disease
- Oregano Oil
- Allicin
- Resistant Starch
- Probiotics