⚠ Evidence warning: Clinical trials or other evidence do not support the claims that berberine trended slightly better than metformin on hemoglobin A1c in Yin 2008 and that subsequent trials confirmed the size of the effect. This page keeps it as a report of what people, websites or other media say.
Berberine for Blood Sugar and Insulin Sensitivity
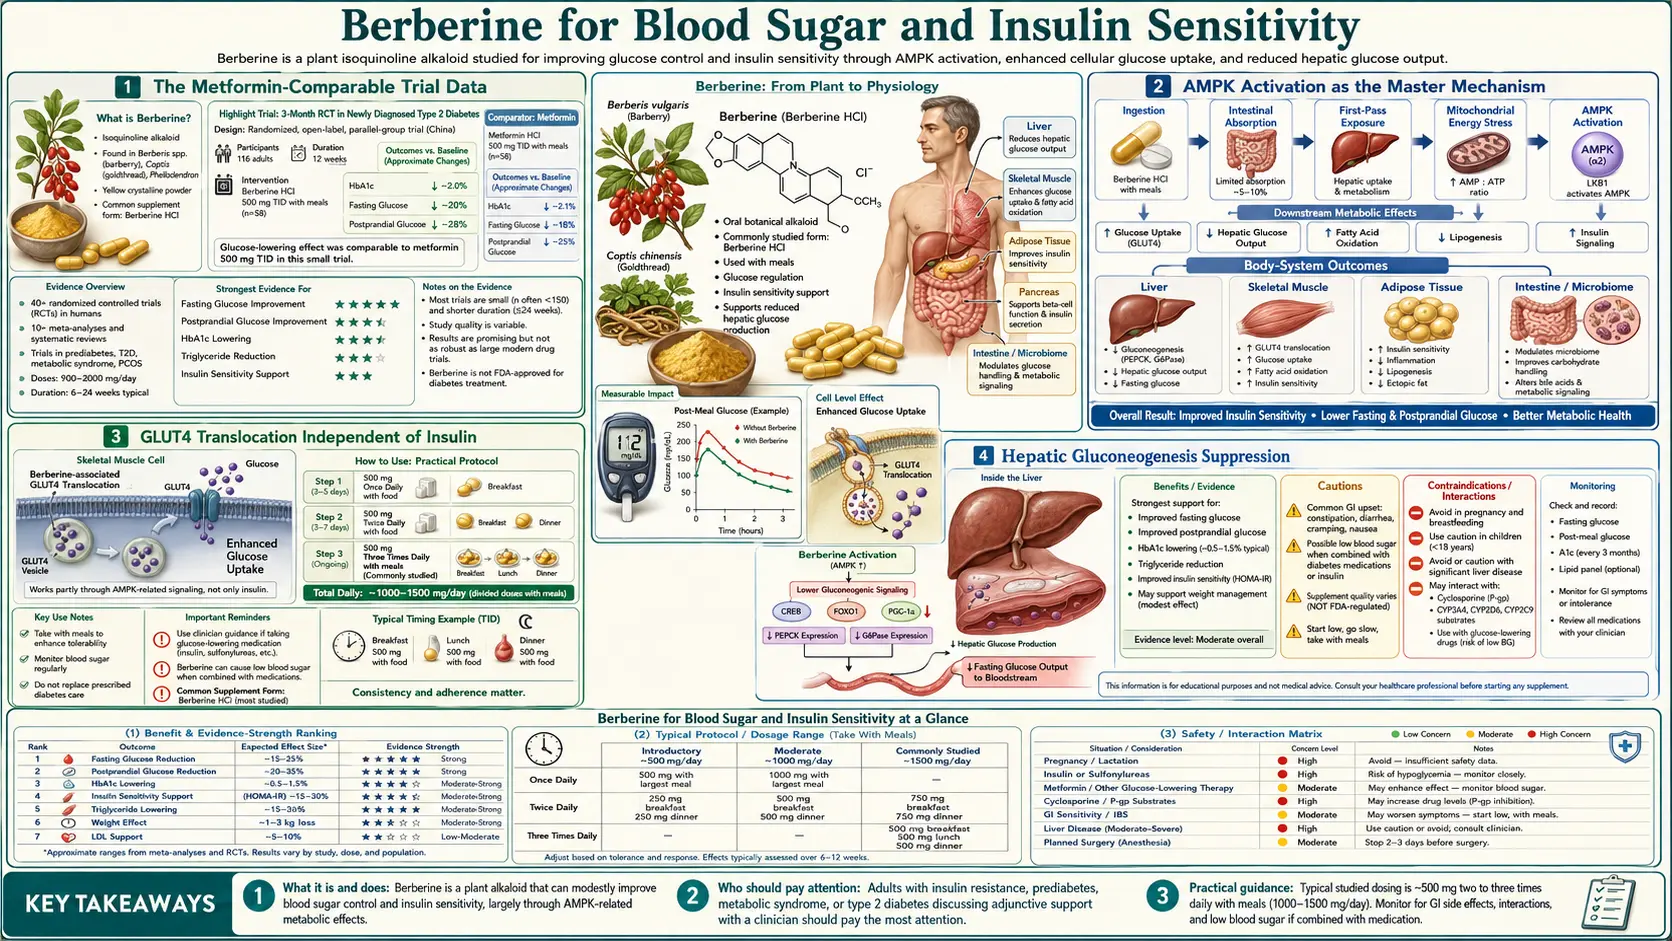
Berberine's claim to legitimacy as a metabolic agent rests on a single landmark trial: in 2008, Jun Yin and colleagues at the Chinese Academy of Sciences randomized 36 newly diagnosed type 2 diabetics to either berberine 500 mg three times daily or metformin 500 mg three times daily for three months — head to head, no other antidiabetic medication, no placebo arm. The result was that berberine produced a fasting glucose reduction (from 191 to 124 mg/dL), hemoglobin A1c (HbA1c) reduction (from 9.5% to 7.5%, a full 2.0% point drop), and insulin-resistance-index improvement (homeostatic model assessment of insulin resistance, HOMA-IR) that were statistically indistinguishable from metformin. Two pooled meta-analyses since (Dong 2012, with 14 trials and 1,068 patients; Lan 2015, with 27 trials and 2,569 patients) have reported a glucose-lowering effect, while rating the quality of the included trials as low (Dong) or limited (Lan). This is one of the very few plant compounds with rigorous head-to-head data against a first-line pharmaceutical, and it has reshaped the conversation about berberine from "another supplement" to "a legitimate AMP-activated protein kinase (AMPK) activator with the same final mechanism as metformin." This page walks through the mechanism, the trial data, the doses used, and the rationale practitioners give for combining berberine with metformin in difficult-to-control cases.
Table of Contents
- The Metformin-Comparable Trial Data
- AMP-Activated Protein Kinase Activation as the Master Mechanism
- GLUT4 Translocation Independent of Insulin
- Hepatic Gluconeogenesis Suppression
- Intestinal Effects: Alpha-Glucosidase and Dipeptidyl Peptidase-4
- Hemoglobin A1c Reduction in Pooled Meta-Analyses
- Polycystic Ovary Syndrome, Insulin Resistance, and Reproductive Endocrinology
- Metabolic Syndrome and Prediabetes
- Combining Berberine with Metformin
- Doses Used in Trials
- Key Research Papers
- Connections
- Featured Videos
The Metformin-Comparable Trial Data
The Yin 2008 paper in Metabolism is the cornerstone trial. Thirty-six patients with newly diagnosed type 2 diabetes were randomized to berberine 500 mg orally three times daily or metformin 500 mg orally three times daily for three months. Neither group received any other antidiabetic medication. The trial was open-label but used objective laboratory endpoints.
The results, summarized:
- Fasting plasma glucose — berberine reduced from 10.6 to 6.9 mmol/L (191 to 124 mg/dL). The paper reports that the glucose-lowering effect of berberine was similar to that of metformin.
- Hemoglobin A1c — berberine 9.5% to 7.5% (a 2.0 percentage-point reduction). The berberine arm trended slightly better.
- Postprandial 2-hour glucose — berberine 19.8 to 11.1 mmol/L.
- Homeostatic model assessment of insulin resistance (insulin resistance index) — reported in the paper's second study (below), where it fell by 44.7%.
- Triglycerides — fell in the berberine group from 1.13 to 0.89 mmol/L; the abstract reports no lipid comparison between the berberine and metformin arms. Low-density lipoprotein cholesterol (LDL-C) fell in the paper's second study (below). Blood fats are the focus of our cardiovascular page.
The same paper reported a second study of 48 adults with poorly controlled type 2 diabetes who were given berberine on top of their treatment for three months. Berberine lowered fasting and after-meal glucose from the first week to the end of the trial; hemoglobin A1c fell from 8.1% to 7.3% (P<.001), fasting insulin fell by 28.1% and the insulin resistance index by 44.7%, and total and LDL cholesterol also fell significantly. Across the paper, 20 patients (34.5%) had short-lived gastrointestinal side effects, and no liver or kidney damage was seen in any patient. The authors described the work as a pilot study. This is the basis for the "combine with metformin" strategy still used by many functional medicine and integrative practitioners.
Subsequent trials have confirmed the magnitude of the effect. Later meta-analyses pooled more trials. The Dong 2012 meta-analysis (14 trials, 1,068 patients) found that berberine did not give significantly better glucose control than metformin, glipizide or rosiglitazone, and rated the trials' methodological quality as generally low. The Lan 2015 meta-analysis (27 trials, 2,569 patients) found no statistically significant difference between berberine and oral diabetes drugs, and judged the quality of the included studies as limited.
AMP-Activated Protein Kinase Activation as the Master Mechanism
The molecular target that explains nearly all of berberine's glucose-lowering effect is AMP-activated protein kinase (AMPK). AMP-activated protein kinase is a heterotrimeric serine/threonine kinase that functions as the cell's low-energy sensor: when the AMP:ATP ratio rises (i.e., when the cell is energy-stressed), AMP-activated protein kinase is activated through allosteric binding of AMP and through phosphorylation by upstream kinases LKB1 and CaMKK-beta.
When AMP-activated protein kinase is activated, it coordinates a global shift away from energy-consuming anabolic processes and toward energy-producing catabolic processes:
- Anabolic processes turned OFF — fatty acid synthesis (acetyl-CoA carboxylase phosphorylation/inhibition), cholesterol synthesis (HMG-CoA reductase phosphorylation/inhibition), glycogen synthesis, protein synthesis (via mTORC1 inhibition), and gluconeogenesis
- Catabolic processes turned ON — fatty acid oxidation, glucose uptake (GLUT4 translocation), mitochondrial biogenesis (via PGC-1-alpha), autophagy, and glycolysis
This is the same final mechanism as metformin. Metformin activates AMP-activated protein kinase indirectly through inhibition of mitochondrial complex I, which raises the AMP:ATP ratio and turns on AMP-activated protein kinase. Berberine produces AMP-activated protein kinase activation through partially overlapping mechanisms: at higher concentrations berberine also inhibits complex I, and at lower concentrations there is evidence for more direct effects on the LKB1 upstream kinase and on AMP-activated protein kinase itself.
The pharmacological consequence is that berberine and metformin both produce the same broad downstream metabolic program: lower hepatic glucose output, higher peripheral glucose uptake, improved insulin sensitivity, lower lipogenesis, and improved mitochondrial efficiency. The differences are in the specific tissue-distribution kinetics, the side-effect profile (berberine's gastrointestinal (GI) effects are typically milder and more transient), and the additional gut-microbiome-mediated effects of berberine that metformin does not share to the same degree.
For a deeper discussion of how AMP-activated protein kinase fits into the broader picture of metabolic regulation, see our Insulin Resistance page.
GLUT4 Translocation Independent of Insulin
GLUT4 is the principal insulin-responsive glucose transporter in skeletal muscle and adipose tissue. Under fasting conditions, GLUT4 resides in intracellular vesicles. When insulin binds its receptor and activates the PI3K-Akt cascade, GLUT4 vesicles fuse with the plasma membrane, dramatically increasing glucose uptake. This is the principal mechanism by which postprandial insulin lowers blood glucose.
In insulin-resistant tissue, the insulin signal fails to fully translocate GLUT4, and glucose accumulates in circulation. Berberine, through AMP-activated protein kinase activation, induces GLUT4 translocation through a parallel pathway that does not require insulin. AMP-activated protein kinase phosphorylates and activates the AS160/TBC1D4 protein, which permits GLUT4 vesicle fusion with the membrane independent of the PI3K-Akt insulin signaling pathway.
The clinical consequence is that berberine can lower glucose even in patients with severe insulin resistance whose insulin signaling is profoundly impaired. This mechanism has been proposed as a reason berberine might work in patients who respond poorly to insulin sensitizers like pioglitazone (a hypothesis; no trial in such patients is cited here), and as a reason it is studied in conditions where insulin resistance is the dominant driver (polycystic ovary syndrome (PCOS), metabolic syndrome, hepatic steatosis with insulin resistance).
The same insulin-independent mechanism is shared with exercise, which also activates AMP-activated protein kinase and drives GLUT4 translocation. This is why exercise is so effective at lowering glucose acutely even in profoundly insulin-resistant patients — and conceptually, berberine produces a similar effect pharmacologically.
Hepatic Gluconeogenesis Suppression
The liver is the primary contributor to fasting hyperglycemia in type 2 diabetes. The liver synthesizes glucose de novo from pyruvate, lactate, glycerol, and amino acids through the gluconeogenesis pathway, mediated principally by the enzymes phosphoenolpyruvate carboxykinase (PEPCK) and glucose-6-phosphatase (G6Pase). In type 2 diabetes, hepatic gluconeogenesis is inappropriately high because the normal insulin-mediated suppression has failed.
Berberine suppresses hepatic gluconeogenesis through two mechanisms:
- AMP-activated protein kinase-mediated suppression of gluconeogenic gene transcription — activated AMP-activated protein kinase phosphorylates and inactivates the transcription factor CREB-regulated transcription coactivator 2 (CRTC2/TORC2), which normally drives transcription of PEPCK and G6Pase. With CRTC2 inactivated, gluconeogenic enzyme synthesis falls.
- Direct inhibition of mitochondrial complex I — at hepatocellular concentrations, berberine inhibits complex I, reducing adenosine triphosphate (ATP) synthesis. Gluconeogenesis is highly adenosine triphosphate-intensive (six adenosine triphosphate equivalents per glucose synthesized from pyruvate), so reduced hepatic adenosine triphosphate availability directly throttles glucose synthesis.
The clinical signature of effective gluconeogenesis suppression is a drop in fasting glucose — which is exactly what is seen in the berberine trials. The Yin 2008 trial showed fasting glucose reductions from 191 to 124 mg/dL, comparable to metformin. This is the principal mechanism behind the morning-glucose improvement that patients typically notice within 2-4 weeks of starting berberine.
Intestinal Effects: Alpha-Glucosidase and Dipeptidyl Peptidase-4
Because oral berberine has only 1-5% systemic bioavailability, most of an ingested dose stays in the gut lumen. This is not wasted — berberine produces clinically relevant effects on intestinal glucose handling that contribute to its glycemic benefit:
- Alpha-glucosidase inhibition — berberine competitively inhibits the brush-border alpha-glucosidase enzymes (sucrase, maltase, isomaltase) that cleave dietary disaccharides into absorbable monosaccharides. This delays carbohydrate absorption and blunts the postprandial glucose spike. The mechanism is similar to the prescription drug acarbose, although berberine's alpha-glucosidase inhibition is less potent.
- Dipeptidyl peptidase-4 (DPP-4) inhibition — dipeptidyl peptidase-4 is the enzyme that rapidly degrades the incretin hormones glucagon-like peptide-1 (GLP-1) and GIP. Berberine has been shown in animal models and small human studies to inhibit dipeptidyl peptidase-4, prolonging incretin half-life and amplifying the postprandial insulin response and glucagon suppression. The mechanism overlaps with the gliptin drug class (sitagliptin, linagliptin).
- Gut microbiome modulation — berberine remodels the gut microbiome in ways that reduce metabolic endotoxemia and improve systemic insulin sensitivity. This is covered in detail on our Gut Microbiome deep-dive.
The combined effect of these intestinal mechanisms is a meaningful blunting of the postprandial glucose excursion, which is studied as a risk marker separate from fasting glucose. The DECODE study (Lancet 1999), which followed 18,048 men and 7,316 women from 13 European cohorts for an average of 7.3 years, found that within each fasting-glucose category, death rates rose with higher glucose 2 hours after a glucose drink, and concluded that fasting glucose alone does not identify everyone at higher risk.
Hemoglobin A1c Reduction in Pooled Meta-Analyses
The most rigorous summary of berberine's glycemic effect comes from pooled meta-analyses. Four are summarized here:
- Dong et al. 2012 (Evidence-Based Complementary and Alternative Medicine) — 14 randomized controlled trials, 1,068 patients. Compared with lifestyle change with or without placebo, berberine plus lifestyle change lowered blood sugar and blood fats significantly; compared with metformin, glipizide or rosiglitazone, berberine did not give significantly better glucose control; berberine added to the same diabetes drugs gave better control than the drugs alone. No serious side effects were reported. Methodological quality was generally low, and the authors wrote that the evidence should be interpreted carefully.
- Lan et al. 2015 (Journal of Ethnopharmacology) — 27 randomized controlled trials, 2,569 patients with type 2 diabetes, hyperlipidemia, or hypertension. In type 2 diabetes, berberine with lifestyle change tended to lower fasting glucose, after-meal glucose and hemoglobin A1c more than lifestyle change alone or placebo, with no statistically significant difference between berberine and oral diabetes drugs. No serious side effects were reported; the authors noted the overall limited quality of the included studies.
- Liang et al. 2019 (Endocrine Journal) — 28 randomized controlled trials, 2,313 patients with type 2 diabetes. Compared with control groups, berberine lowered fasting glucose by 0.54 mmol/L, after-meal glucose by 0.94 mmol/L and hemoglobin A1c by 0.54 points (weighted mean differences), and berberine combined with diabetes drugs worked better than either alone. In subgroup analyses the glucose-lowering effect was no longer notable when treatment lasted more than 90 days, when the daily dose was above 2 g, and in patients older than 60 — so whether the effect holds with long-term use, at high doses and in older people is not established.
- Nazari et al. 2024 (Clinical Therapeutics) — an umbrella meta-analysis pooling earlier meta-analyses of randomized trials (searched up to April 2023). In adults with metabolic disorders, berberine lowered fasting blood glucose (pooled weighted mean difference −0.77 mmol/L), hemoglobin A1c (−0.57), the insulin resistance index (HOMA-IR) and insulin, and the inflammation markers interleukin-6 (IL-6), tumor necrosis factor-alpha (TNF-α) and C-reactive protein (CRP).
The pooled hemoglobin A1c reductions in the Liang 2019 and Nazari 2024 analyses were about 0.5-0.6 points. The UK Prospective Diabetes Study (UKPDS) established that each 1% reduction in hemoglobin A1c reduces microvascular complications by 37%, myocardial infarction by 14%, and all-cause diabetes-related death by 21%. Berberine's magnitude of effect is therefore not trivial — it is comparable to adding a first-line oral agent.
For comparison, metformin monotherapy typically reduces hemoglobin A1c by 1.0-1.5%, sulfonylureas by 1.0-1.5%, gliptins by 0.5-0.8%, and sodium-glucose cotransporter-2 (SGLT2) inhibitors by 0.6-1.0%. Berberine sits in the middle of this range and is competitive on a per-dose basis.
Polycystic Ovary Syndrome, Insulin Resistance, and Reproductive Endocrinology
Polycystic ovary syndrome (PCOS) is the most common endocrinopathy in women of reproductive age. Insulin resistance is the central metabolic driver: hyperinsulinemia stimulates ovarian theca cells to overproduce androgens, suppresses sex hormone binding globulin (SHBG) in the liver (raising free testosterone), and disrupts the normal hypothalamic-pituitary-ovarian axis. Metformin is widely used in polycystic ovary syndrome, particularly in patients with concurrent insulin resistance or obesity.
Berberine has been studied in polycystic ovary syndrome, including the Wei et al. 2012 trial in the European Journal of Endocrinology. 89 women with polycystic ovary syndrome and insulin resistance were randomized to berberine, metformin, or placebo, each together with compound cyproterone acetate (a hormonal drug), for 3 months. Berberine produced:
- Lower fasting glucose, fasting insulin and homeostatic model assessment of insulin resistance than placebo
- Greater reduction in waist circumference and waist-to-hip ratio than metformin (statistically significant)
- Larger falls in total cholesterol, triglycerides and low-density lipoprotein cholesterol, and larger rises in high-density lipoprotein cholesterol and sex hormone binding globulin, than metformin
For women trying to conceive, a second strand of evidence has explored berberine as a fertility intervention in polycystic ovary syndrome. The An et al. 2014 trial in Clinical Endocrinology randomized 150 infertile women with polycystic ovary syndrome undergoing in vitro fertilization (IVF) to berberine, metformin or placebo for 3 months before ovarian stimulation. Compared with placebo, both berberine and metformin lowered testosterone, fasting glucose, fasting insulin and insulin resistance and raised sex hormone binding globulin, increased the pregnancy rate and reduced severe ovarian hyperstimulation syndrome. Compared with metformin, berberine was associated with lower body mass index, blood fats and total follicle-stimulating hormone (FSH) requirement, more live births and fewer gastrointestinal side effects. The mechanism is presumably the combined insulin-sensitizing and androgen-lowering effects.
Some practitioners describe berberine 500 mg three times daily as an alternative for women with polycystic ovary syndrome who cannot tolerate metformin (typically due to gastrointestinal symptoms) or who prefer a non-prescription option; in the An 2014 trial berberine had fewer gastrointestinal side effects than metformin. For more on the management of polycystic ovary syndrome, see our polycystic ovary syndrome page.
Metabolic Syndrome and Prediabetes
Metabolic syndrome — the constellation of central adiposity, hypertension, dyslipidemia, and insulin resistance — is the precursor state to type 2 diabetes and a major risk factor for cardiovascular disease. The Zhang et al. 2008 trial in the Journal of Clinical Endocrinology and Metabolism randomized 116 people with type 2 diabetes and dyslipidemia (high blood fats) to berberine 1.0 g a day or placebo for 3 months. In the berberine group:
- Fasting plasma glucose fell from 7.0 to 5.6 mmol/L, and glucose after a glucose load from 12.0 to 8.9 mmol/L
- Hemoglobin A1c fell from 7.5% to 6.6%
- Triglycerides fell from 2.51 to 1.61 mmol/L
- Total cholesterol fell from 5.31 to 4.35 mmol/L
- Low-density lipoprotein cholesterol fell from 3.23 to 2.55 mmol/L
- All of these changes differed significantly from placebo. Insulin sensitivity (glucose disposal rate, measured with a clamp test) rose after berberine, but the difference from placebo was not significant (P = 0.063).
- Mild to moderate constipation was seen in five people taking berberine.
This is one of the better-documented examples of a single supplement improving blood sugar and blood fats at the same time. For prediabetes specifically (hemoglobin A1c 5.7-6.4% or fasting glucose 100-125 mg/dL), some practitioners describe berberine as a first-line non-prescription option, particularly when lifestyle change alone has not reached target values.
The Diabetes Prevention Program (3,234 people with raised blood sugar, average follow-up 2.8 years) found that metformin 850 mg twice daily reduced the incidence of type 2 diabetes by 31% compared with placebo, and the lifestyle program by 58%. There is no equivalent long-term outcome study for berberine — the question of whether berberine produces comparable diabetes-prevention benefit has not been answered definitively. Practitioners who use it in this setting point to the shared mechanism with metformin and the comparable short-term glycemic effects.
Combining Berberine with Metformin
Many integrative practitioners describe berberine in type 2 diabetes as a metformin add-on rather than a metformin replacement. The trial they point to is the Yin 2008 second study: 48 adults with poorly controlled type 2 diabetes were given berberine on top of their treatment (the abstract does not list which drugs they were taking). After 3 months:
- Hemoglobin A1c down from 8.1% to 7.3%
- Fasting insulin down by 28.1% and the insulin resistance index (HOMA-IR) down by 44.7%
- Total cholesterol and low-density lipoprotein cholesterol down significantly
- 20 patients (34.5%) in the paper had short-lived gastrointestinal side effects; no liver or kidney damage was seen
The combination is mechanistically rational. Both molecules activate AMP-activated protein kinase, but they reach AMP-activated protein kinase through partially distinct routes, and berberine adds the unique gut-microbiome-mediated effects that metformin produces less consistently. The combination also allows lower individual doses of each agent, often reducing the gastrointestinal side effects of each.
The practical regimen used by many integrative practitioners for difficult-to-control type 2 diabetes is metformin 500-1000 mg twice daily plus berberine 500 mg three times daily, with attention to:
- Hypoglycemia risk in patients also on sulfonylureas or insulin (additive glucose-lowering effect)
- Vitamin B12 monitoring (metformin depletes B12; berberine has not been shown to do so but the combination is on long-term use anyway)
- Renal function (metformin requires estimated glomerular filtration rate (eGFR) >30; berberine has no such restriction but is rarely used in advanced chronic kidney disease (CKD))
- Gastrointestinal tolerance — practitioners describe a slow build-up of berberine (500 mg once daily at first, rising to 500 mg three times daily over 2-4 weeks) to limit the initial transient diarrhea and cramping
For a discussion of the specific CYP450 interactions that berberine introduces (which matter more than metformin's), see our Dosing, Forms & Cautions page.
Doses Used in Trials
The dose used in the Yin 2008 trial is 500 mg three times daily (1,500 mg/day total), and practitioners describe taking it with meals; the Zhang 2008 trial used 1.0 g a day. Practitioners give this reason for the three-divided-dose schedule: berberine's half-life is approximately 4 hours, and the short half-life means that once-daily dosing produces inadequate steady-state concentrations and substantially weaker clinical effect. Three-times-daily with meals also maximizes the postprandial alpha-glucosidase and dipeptidyl peptidase-4 effects discussed above.
A titration schedule practitioners describe for new users:
- Week 1 — 500 mg once daily with dinner, while gastrointestinal tolerance is assessed.
- Week 2 — 500 mg twice daily (breakfast and dinner).
- Week 3 onward — 500 mg three times daily (breakfast, lunch, dinner).
Timeline of benefit as practitioners describe it:
- 2-4 weeks — first improvements in fasting glucose visible
- 8-12 weeks — meaningful hemoglobin A1c reduction (hemoglobin A1c reflects 8-12 weeks of average glucose, so changes take that long to manifest)
- 3-6 months — lipid effects fully developed
- 6-12 months — gut-microbiome and metabolic-syndrome benefits at peak
If standard berberine is not well tolerated due to gastrointestinal symptoms, or when higher systemic concentrations are sought, practitioners describe dihydroberberine at 200 mg twice daily as a higher-bioavailability alternative, covered in detail on the Dosing page.
Key Research Papers
- Yin J, Xing H, Ye J (2008). Efficacy of berberine in patients with type 2 diabetes mellitus. Metabolism, 57(5):712-717. — PubMed PMID: 18442638
- Lee YS, Kim WS, Kim KH et al. (2006). Berberine, a natural plant product, activates AMP-activated protein kinase. Diabetes, 55(8):2256-2264. — PubMed PMID: 16873688
- Dong H, Wang N, Zhao L, Lu F (2012). Berberine in the treatment of type 2 diabetes mellitus: a systematic review and meta-analysis. Evidence-Based Complementary and Alternative Medicine, 2012:591654. — PubMed PMID: 23118793
- Lan J, Zhao Y, Dong F et al. (2015). Meta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipidaemia and hypertension. Journal of Ethnopharmacology, 161:69-81. — PubMed PMID: 25498346
- Zhang Y, Li X, Zou D et al. (2008). Treatment of type 2 diabetes and dyslipidemia with the natural plant alkaloid berberine. Journal of Clinical Endocrinology and Metabolism, 93(7):2559-2565. — PubMed PMID: 18397984
- An Y, Sun Z, Zhang Y et al. (2014). The use of berberine for women with polycystic ovary syndrome undergoing IVF treatment. Clinical Endocrinology, 80(3):425-431. — PubMed PMID: 23869585
- Wei W, Zhao H, Wang A et al. (2012). A clinical study on the short-term effect of berberine in comparison to metformin on the metabolic characteristics of women with polycystic ovary syndrome. European Journal of Endocrinology, 166(1):99-105. — PubMed PMID: 22019891
- Yin J, Gao Z, Liu D et al. (2008). Berberine improves glucose metabolism through induction of glycolysis. American Journal of Physiology Endocrinology and Metabolism, 294(1):E148-156. — PubMed PMID: 17971514
- Liu Y, Zhang L, Song H, Ji G (2013). Update on berberine in nonalcoholic fatty liver disease. Evidence-Based Complementary and Alternative Medicine, 2013:308134. — PubMed PMID: 23843872
- Liang Y, Xu X, Yin M et al. (2019). Effects of berberine on blood glucose in patients with type 2 diabetes mellitus: a systematic literature review and a meta-analysis. Endocrine Journal, 66(1):51-63. — PubMed PMID: 30393248
- Nazari A, Ghotbabadi ZR, Kazemi KS et al. (2024). The effect of berberine supplementation on glycemic control and inflammatory biomarkers in metabolic disorders: an umbrella meta-analysis of randomized controlled trials. Clinical Therapeutics, 46(2):e64-e72. — PubMed PMID: 38016844
- Knowler WC, Barrett-Connor E, Fowler SE et al.; Diabetes Prevention Program Research Group (2002). Reduction in the incidence of type 2 diabetes with lifestyle intervention or metformin. New England Journal of Medicine, 346(6):393-403. — PubMed PMID: 11832527
- DECODE Study Group, European Diabetes Epidemiology Group (1999). Glucose tolerance and mortality: comparison of WHO and American Diabetes Association diagnostic criteria. Lancet, 354(9179):617-621. — PubMed PMID: 10466661
- Turner N, Li JY, Gosby A et al. (2008). Berberine and its more biologically available derivative, dihydroberberine, inhibit mitochondrial respiratory complex I. Diabetes, 57(5):1414-1418. — PubMed PMID: 18285556
- Zhang H, Wei J, Xue R et al. (2010). Berberine lowers blood glucose in type 2 diabetes mellitus patients through increasing insulin receptor expression. Metabolism, 59(2):285-292. — PubMed PMID: 19800084
PubMed Topic Searches
Connections
- All Remedies
- Berberine Overview
- Berberine Benefits Hub
- Berberine for Cholesterol
- Berberine for Gut Microbiome
- Berberine Dosing & Cautions
- Type 2 Diabetes
- Insulin Resistance
- Metabolic Syndrome
- Polycystic Ovary Syndrome
- Prediabetes
- Non-Alcoholic Fatty Liver Disease
- Chromium
- Magnesium
- Hemoglobin A1c Lab Test
- Metformin — the first-line drug berberine was measured against head-to-head in the Yin 2008 trial, and the usual add-on partner.