Boron for Cognitive Function
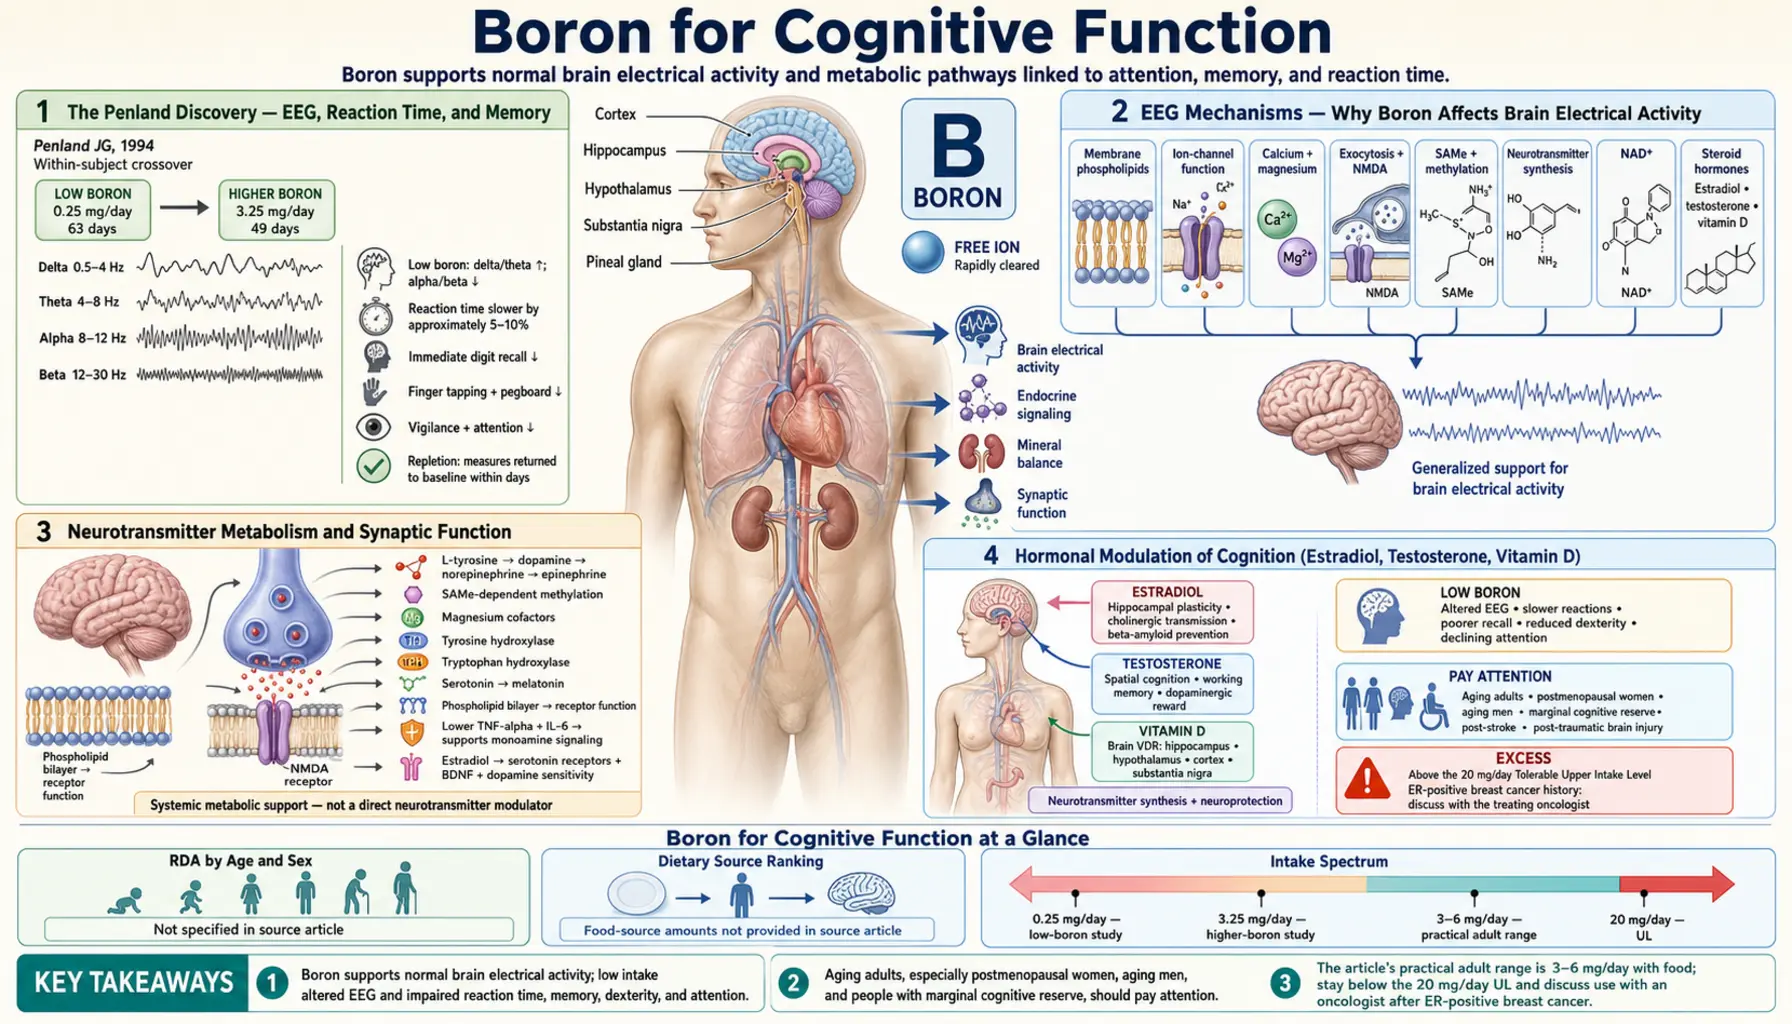
The connection between boron and brain function was almost entirely unsuspected until James G. Penland at the U.S. Department of Agriculture (USDA) Grand Forks Human Nutrition Research Center conducted a series of controlled-diet studies in the early 1990s. Penland fed adult subjects low-boron diets (0.25 mg/day) for prolonged periods and compared their electroencephalogram (EEG) patterns, reaction times, short-term memory performance, manual dexterity, and attention metrics against the same subjects after boron repletion (3 mg/day). The boron-deprived state was associated with more low-frequency and less higher-frequency (including alpha-wave) electroencephalogram activity — a pattern Penland noted is typical of drowsiness and often seen with general malnutrition and heavy metal toxicity — and with poorer performance on cognitive tasks than during the higher-boron period. This deep-dive walks through the Penland electroencephalogram studies, the proposed neural mechanisms, the implications for aging cognition and neurodegenerative disease prevention, and the practical role of boron in a brain-health nutritional protocol.
Table of Contents
- The Penland Discovery — Electroencephalogram, Reaction Time, and Memory
- Electroencephalogram Mechanisms — Why Boron Affects Brain Electrical Activity
- Neurotransmitter Metabolism and Synaptic Function
- Hormonal Modulation of Cognition (Estradiol, Testosterone, Vitamin D)
- Neuroinflammation Reduction
- Oxidative Stress and Neuroprotection
- Boron-Mediated Mineral Balance and Brain Function
- Aging Cognition and Mild Cognitive Impairment
- Alzheimer's Disease — Hypothesized Boron Connection
- Practical Brain-Health Protocol with Boron
- Cautions for Cognitive Use
- Key Research Papers
- Connections
- Featured Videos
The Penland Discovery — Electroencephalogram, Reaction Time, and Memory
James G. Penland published the seminal paper on dietary boron and brain function in Environmental Health Perspectives in 1994. The paper described three studies in healthy older men and women, all with within-subject designs and controlled diets. In the first, 13 postmenopausal women lived in a metabolic research unit and received boron or placebo in 42-day periods. In the other two, participants (15 recruited for each study: five men and ten postmenopausal women) lived at home, ate prepared meals, and were fed a low-boron diet (about 0.25 mg per 2,000 kcal a day, the background level of a diet low in fruits and vegetables) for 63 days, then a higher-boron diet (about 3.25 mg, achieved by adding boron supplementation back to the same base diet) for 49 days.
During each diet period, subjects underwent regular cognitive and electrophysiological testing:
- Electroencephalogram recording — resting-state electroencephalography with quantitative analysis of frequency bands (delta 0.5–4 Hz, theta 4–8 Hz, alpha 8–12 Hz, beta 12–30 Hz)
- Reaction time — simple and choice reaction time tasks
- Short-term memory — immediate digit recall, spatial memory tasks
- Manual dexterity — finger-tapping rates, pegboard tasks
- Vigilance and attention — sustained-attention tasks of 10–30 minute duration
- Psychomotor performance — coordinated hand-eye tasks
The key findings:
- Electroencephalogram changes — the low-boron diet was associated with increased proportion of low-frequency (delta and theta) activity and reduced proportion of high-frequency (alpha and beta) activity. This effect was seen in two of the three studies; Penland noted that the pattern is typical of drowsiness and reduced alertness, and is often seen with general malnutrition and heavy metal toxicity. Boron repletion shifted the electroencephalogram back toward higher alpha and beta activity, the pattern of alert, attentive cognition
- Slower responses — response times on cognitive and psychomotor tasks were poorer during the low-boron period; accuracy was not affected
- Short-term memory impairment — performance on encoding and short-term memory tasks was poorer during low-boron in all three studies
- Manual dexterity reduction — performance on tasks emphasizing manual dexterity, such as finger tapping, was poorer (studies II and III)
- Vigilance/attention impairment — performance on attention tasks was poorer in the low-boron state in all three studies
The pattern of effects is consistent with a mild but generalized impairment of cognitive performance, mediated through changes in brain electrical activity rather than through any specific localized cognitive deficit. The implication is that boron supports baseline brain electrical function in a relatively non-specific way, with detectable behavioral consequences when boron is deficient.
The Institute of Medicine's 2001 review noted that these findings come from studies in one laboratory and that these possible functions of boron “have yet to be studied and confirmed by other laboratories.” Penland's own conclusion was that boron may play a role in human brain function and cognitive performance. The effect is subtle in healthy adults with normal cognitive baseline, but it may be more clinically significant in populations with marginal cognitive reserve (aging adults, post-stroke, post-traumatic brain injury).
Electroencephalogram Mechanisms — Why Boron Affects Brain Electrical Activity
The proposed mechanisms for boron's effect on electroencephalogram are several and overlapping:
- Membrane phospholipid stabilization — boron binds to phosphatidylinositol and other inositol-containing membrane lipids, modulating membrane fluidity and the function of membrane-bound ion channels that govern neuronal excitability. The voltage-gated sodium, potassium, and calcium channels that generate action potentials and synaptic potentials are all membrane-protein complexes whose function depends on the surrounding lipid environment
- Calcium and magnesium homeostasis — boron-supported mineral balance keeps intracellular and extracellular calcium and magnesium concentrations stable, which is critical for normal neurotransmitter release (calcium-triggered exocytosis at synaptic terminals) and for N-methyl-D-aspartate-receptor function (magnesium blocks the N-methyl-D-aspartate (NMDA) channel at resting potential and is displaced by depolarization)
- S-adenosylmethionine (SAMe) and methylation — boron is required for normal S-adenosylmethionine (SAMe) metabolism, and S-adenosylmethionine is the universal methyl donor for hundreds of biochemical reactions including neurotransmitter metabolism (the conversion of norepinephrine to epinephrine), membrane phospholipid methylation, and DNA methylation
- Nicotinamide adenine dinucleotide (NAD+) and energy metabolism — boron influences nicotinamide adenine dinucleotide availability through interactions with the nicotinamide riboside metabolic pathway. Nicotinamide adenine dinucleotide is required for oxidative phosphorylation, sirtuin function, and DNA-repair enzyme activity — all critical for normal neuronal function and longevity
- Steroid hormone effects on brain — the boron-mediated elevation of estradiol, testosterone, and vitamin D (see the Hormone Balance deep-dive) has independent effects on brain function. Estradiol supports synaptic plasticity, neurotransmitter receptor expression, and brain-derived neurotrophic factor (BDNF) production. Testosterone supports dopaminergic function and spatial cognition. Vitamin D acts at the brain VDR to influence neurotransmitter synthesis and neuroprotection
The convergence of these mechanisms is why boron-induced electroencephalogram changes are generalized rather than localized to a single brain region or a single cognitive domain. Boron operates at the metabolic substrate level (membrane lipids, methylation, nicotinamide adenine dinucleotide, mineral balance, steroid hormones) that supports brain function as a whole.
Neurotransmitter Metabolism and Synaptic Function
Boron influences neurotransmitter metabolism through several indirect routes:
- S-adenosylmethionine-dependent methylation — in the synthesis of the catecholamines from L-tyrosine, one step uses S-adenosylmethionine: phenylethanolamine N-methyltransferase (PNMT) methylates norepinephrine to form epinephrine. Boron-supported S-adenosylmethionine metabolism therefore relates to that step. The breakdown of catecholamines by COMT-mediated O-methylation (COMT acts on catechols, which serotonin is not) and the conversion of serotonin to melatonin in the pineal gland also use S-adenosylmethionine
- Cofactor availability — tyrosine hydroxylase (the rate-limiting enzyme for dopamine synthesis) and tryptophan hydroxylase (the rate-limiting enzyme for serotonin synthesis) use iron and tetrahydrobiopterin (BH4) as cofactors rather than magnesium, so boron's effect on magnesium retention does not act on these two enzymes directly
- Membrane lipid composition — the function of every neurotransmitter receptor (which are transmembrane proteins) depends on the surrounding lipid bilayer composition. Boron-stabilized phospholipids support normal receptor function
- Inflammatory cytokine suppression — chronic neuroinflammation impairs neurotransmitter function (tumor necrosis factor-alpha and interleukin-6 (IL-6) disrupt monoamine signaling). Boron's anti-inflammatory effect indirectly supports normal neurotransmitter biology
- Steroid-mediated effects on receptor expression — estradiol increases serotonin receptor density in multiple brain regions, supports brain-derived neurotrophic factor production, and modulates dopamine receptor sensitivity. Boron-elevated estradiol in postmenopausal women therefore has downstream neurotransmitter consequences
The composite effect is that boron supplementation provides metabolic support for normal neurotransmitter function without being a direct neurotransmitter modulator itself. It does not cross the blood-brain barrier in significant concentrations as a free ion (boron is rapidly cleared) but its effects on systemic mineral balance, methylation status, and hormone concentrations translate into brain effects.
Hormonal Modulation of Cognition (Estradiol, Testosterone, Vitamin D)
The hormonal effects of boron documented in detail on the Hormone Balance page have direct cognitive consequences:
- Estradiol in postmenopausal women — estradiol supports hippocampal neuroplasticity, cholinergic neurotransmission, and prevention of beta-amyloid accumulation. Postmenopausal estradiol decline is implicated in the increased dementia risk in women relative to men of the same age. Boron-induced partial estradiol restoration may provide modest cognitive support, particularly for verbal memory and processing speed
- Testosterone in aging men — testosterone supports spatial cognition, working memory, and dopaminergic reward function. Age-related testosterone decline is associated with mild cognitive impairment risk. Boron-elevated free testosterone may provide modest cognitive support
- Vitamin D at the brain VDR — vitamin D receptors are widely expressed in the brain (hippocampus, hypothalamus, cortex, substantia nigra) and vitamin D-deficient individuals have measurably worse cognitive performance and higher dementia risk. Boron-supported vitamin D activation amplifies the cognitive-protective effect of vitamin D supplementation
- DHEA and adrenal steroids — DHEA has direct neurosteroid effects on gamma-aminobutyric acid-A and N-methyl-D-aspartate receptors, supports mood and energy. Boron-supported DHEA may contribute to general cognitive wellbeing
- Cortisol — chronically elevated cortisol is hippocampal-toxic and associated with cognitive impairment; in the Naghii trial (eight healthy men taking 10 mg of boron a day for one week), cortisol was elevated after the week of boron, not lowered
The integrated hormonal effects of boron are particularly relevant for aging populations whose cognitive decline is partly driven by hormonal changes. For aging women in particular, the combination of proposed bone-protective and cognition-protective effects is the rationale put forward for boron supplementation.
Neuroinflammation Reduction
Chronic low-grade neuroinflammation is increasingly recognized as a central feature of aging brain dysfunction and a contributor to neurodegenerative diseases including Alzheimer's disease, Parkinson's disease, and vascular cognitive impairment. The activated microglia and astrocytes that produce pro-inflammatory cytokines (interleukin-1-beta, interleukin-6, tumor necrosis factor-alpha) in chronic neuroinflammation impair synaptic plasticity, neurotransmitter function, and (in extreme cases) drive neuronal death.
The systemic anti-inflammatory effect of boron documented in the Naghii trial (eight healthy men, one week of 10 mg/day; as reported in a 2015 review, high-sensitivity C-reactive protein (CRP) fell from 1,460 to 795 ng/mL, tumor necrosis factor-alpha from 12.32 to 9.97 pg/mL, and interleukin-6 from 1.55 to 0.87 pg/mL) is proposed to reduce central inflammation through several mechanisms:
- Reduced peripheral cytokine exposure — the brain is partially exposed to circulating cytokines through the circumventricular organs, where the blood-brain barrier is incomplete. Lower peripheral inflammation means less central exposure
- Reduced gut inflammation — the gut-brain axis transmits inflammatory signals from intestinal dysbiosis and leaky gut to the brain via vagal afferents and circulating mediators. Boron's general anti-inflammatory effect reduces this signaling
- Direct microglial effects — proposed, not demonstrated: boron compounds might directly suppress microglial activation through NF-kB pathway inhibition
- Improved endothelial function — cerebrovascular endothelial inflammation contributes to blood-brain-barrier disruption and to vascular cognitive impairment. Reduced systemic inflammation supports endothelial integrity
The combination of anti-inflammatory and hormone-supportive effects positions boron as a foundational nutritional intervention for cognitive aging, alongside other established neuroprotective nutrients (omega-3 fatty acids, vitamin D, B-vitamins for homocysteine management, magnesium, lithium orotate in low dose).
Oxidative Stress and Neuroprotection
The brain is uniquely vulnerable to oxidative stress because of its high oxygen consumption (20% of resting energy expenditure for 2% of body mass), its high content of oxidation-prone polyunsaturated fatty acids in membrane phospholipids, and its limited regenerative capacity (most neurons are postmitotic and cannot be replaced). Antioxidant defenses are correspondingly important for long-term brain health.
Boron does not function as a direct antioxidant (it does not have a redox-active electron) but supports the endogenous antioxidant systems through several pathways:
- Glutathione metabolism — boron-supported magnesium retention supports glutamate-cysteine ligase (the rate-limiting enzyme for glutathione synthesis). Glutathione is the brain's dominant intracellular antioxidant
- Vitamin D and antioxidant gene expression — vitamin D upregulates antioxidant enzyme expression (superoxide dismutase, glutathione peroxidase, catalase). Boron-supported vitamin D activation amplifies this effect
- Sex steroid neuroprotection — estradiol and testosterone both have neuroprotective effects against oxidative stress, partly through direct antioxidant chemistry and partly through antioxidant gene expression
- Membrane stabilization — boron-stabilized membrane phospholipids are less susceptible to lipid peroxidation, reducing the propagation of oxidative damage through the membrane
The neuroprotective effects of boron are subtle compared to dedicated antioxidant nutrients (alpha-lipoic acid, N-acetylcysteine (NAC), vitamin E, vitamin C). Boron is better described as a supportive nutrient proposed to amplify the effect of dedicated antioxidants, not as an antioxidant in its own right.
For dedicated antioxidant approaches, see our Alpha Lipoic Acid page and N-acetylcysteine page.
Boron-Mediated Mineral Balance and Brain Function
The mineral-balance effects of boron documented in detail on the Bone Density page have direct brain implications:
- Magnesium retention — magnesium deficiency is associated with increased anxiety, depression, headache, and cognitive impairment. Boron-supported magnesium retention preserves the calming, N-methyl-D-aspartate-modulating effects of adequate brain magnesium
- Calcium balance — both hypercalcemia and hypocalcemia produce neurological symptoms. Boron-mediated calcium balance helps maintain the narrow normal range required for normal neuronal excitability
- Phosphorus balance — phosphate is required for adenosine triphosphate (ATP), phospholipids, and DNA. Boron-supported phosphorus retention contributes to brain energy metabolism
- Sodium and potassium — the resting membrane potential of neurons depends on the sodium-potassium ATPase pump (which requires magnesium as cofactor) and on potassium gradients (which are influenced by acid-base balance, itself affected by mineral homeostasis)
The composite picture: boron acts as a metabolic regulator that keeps the brain's mineral and hormonal milieu in a state that supports optimal function. The effect is not dramatic in any single dimension but is real across many dimensions simultaneously.
Aging Cognition and Mild Cognitive Impairment
Cognitive decline with normal aging is multifactorial. Synaptic loss, neurotransmitter receptor decline, reduced cerebral blood flow, accumulated oxidative damage, declining hormonal milieu (estradiol in women, testosterone in men, DHEA in both, vitamin D in both), and increasing neuroinflammation all contribute. Mild cognitive impairment (MCI) is the clinical syndrome characterized by measurable cognitive decline beyond normal aging but not yet meeting dementia criteria; approximately 15% of MCI patients progress to dementia annually.
Boron supplementation in aging populations has not been specifically tested as an MCI intervention in any large trial, but the proposed mechanistic rationale includes:
- Improved electroencephalogram patterns documented by Penland in adults, presumably also operative in older adults
- Modest hormonal restoration in postmenopausal women and aging men
- Anti-inflammatory effects consistent with reduced neuroinflammation
- Vitamin D activation support with downstream cognitive consequences
- Bone-cognitive protection (the same supplementation that protects bone also protects cognition, addressing the two leading aging concerns simultaneously)
The intervention is low-cost (a year of 3–6 mg/day boron costs $10–30), low-risk (well below the 20 mg/day Tolerable Upper Intake Level), and produces measurable changes in objective biomarkers within weeks. That is the case made for boron supplementation in aging populations, in the absence of dedicated MCI trial data.
For comprehensive cognitive aging approaches, see the mild cognitive impairment section above, our Dementia page, and our Brain Health page.
Alzheimer's Disease — Hypothesized Boron Connection
The role of boron in Alzheimer's disease prevention or treatment is speculative but rests on a coherent hypothesis. The proposed pathways are:
- Beta-amyloid clearance — estradiol supports the activity of insulin-degrading enzyme and neprilysin, the proteases that catabolize beta-amyloid. Boron-induced estradiol restoration in postmenopausal women may modestly improve beta-amyloid clearance
- Tau phosphorylation — glycogen synthase kinase-3-beta (GSK-3-beta), the enzyme primarily responsible for pathological tau hyperphosphorylation, is inhibited by lithium and may be modulated by other trace elements including boron
- Neuroinflammation — the central role of microglial activation in Alzheimer's pathogenesis means that any anti-inflammatory intervention is theoretically relevant. The Naghii data on systemic C-reactive protein, tumor necrosis factor-alpha, and interleukin-6 reduction are encouraging
- Vitamin D status — vitamin D deficiency is consistently associated with higher Alzheimer's risk in observational studies. Boron-supported vitamin D activation amplifies the protective effect of vitamin D supplementation
- Insulin sensitivity — type 2 diabetes and insulin resistance are major risk factors for Alzheimer's disease (sometimes called "type 3 diabetes"). Boron's effects on insulin sensitivity (modest but real) may be protective
- S-adenosylmethionine and methylation — impaired methylation is implicated in Alzheimer's pathogenesis, and S-adenosylmethionine supplementation has shown modest cognitive benefit in some studies. Boron-supported S-adenosylmethionine metabolism is potentially relevant
No randomized controlled trial has yet tested boron supplementation as Alzheimer's prevention. The case made for its use in at-risk groups (positive family history, ApoE4 carriers, individuals with MCI) without trial-level evidence rests on its low risk and low cost. It is usually described alongside other nutritional approaches studied for Alzheimer's protection: Mediterranean diet, omega-3 fatty acids, B-vitamins for homocysteine management, vitamin D, magnesium, and regular exercise.
For comprehensive Alzheimer's information, see our Alzheimer's Disease page.
Practical Brain-Health Protocol with Boron
Boron does not function as a stand-alone cognitive intervention but as one component of a comprehensive brain-health nutritional protocol. A protocol of the kind described in integrative-nutrition practice for adults with cognitive aging concerns, with doses as commonly listed:
- Boron citrate or glycinate 3–6 mg/day with food
- Vitamin D3 2000–5000 international units (IU)/day to a serum 25(OH)D level of 40–80 ng/mL (the Institute of Medicine's upper limit for everyone aged 9 and over, adults included, is 4,000 IU a day)
- Magnesium glycinate or L-threonate 300–400 mg/day (L-threonate has documented brain penetration); the Institute of Medicine's upper limit for magnesium from supplements is 350 mg a day, diarrhea is the first sign of too much, and magnesium building up in the blood is seen mostly in people with weak kidneys taking magnesium from non-food sources
- Omega-3 fatty acids (eicosapentaenoic acid (EPA) + docosahexaenoic acid (DHA)) 2–3 g/day, particularly docosahexaenoic acid for brain structure
- B-vitamin complex with adequate B12 (1000 mcg methylcobalamin), folate (400–800 mcg methylfolate), B6 (50 mg pyridoxal-5-phosphate) to keep homocysteine below 8 micromoles/L
- Vitamin K2 menaquinone-7 (MK-7) 180–360 mcg/day for cerebrovascular calcium handling
- Vitamin E 400 international units/day as mixed tocopherols (in the Physicians' Health Study II, 400 IU of vitamin E every other day was associated with an increased risk of bleeding stroke, called hemorrhagic stroke)
- Curcumin 500–1500 mg/day (an enhanced-absorption form, such as curcumin combined with turmeric oils or bound to phospholipids) for anti-inflammatory effect
- Alpha-lipoic acid 600 mg/day or N-acetylcysteine 600–1200 mg/day for antioxidant support
- Lion's Mane mushroom 1–3 g/day for NGF-mimetic effect
The full protocol addresses multiple cognitive-aging pathways simultaneously. Boron at 3–6 mg/day is one foundational element among many. Combined with regular aerobic exercise (which independently supports brain-derived neurotrophic factor, vascular function, and cognitive performance), Mediterranean-style diet, social engagement, and cognitive challenge (the "use it or lose it" principle of cognitive reserve), the regimen represents a comprehensive approach to cognitive aging.
Cautions for Cognitive Use
- Not a treatment for established dementia — once Alzheimer's or other dementia is clinically established, boron supplementation is unlikely to produce noticeable functional improvement. The intervention is best framed as prevention or as adjunct to early-stage management
- Drug interactions — boron has minimal interaction with cognitive-enhancing pharmaceuticals (donepezil, memantine, rivastigmine). Generally compatible
- Hormone-dependent cancers — estrogen-receptor-positive breast cancer is the type whose growth is driven by estrogen, and its treatments work by blocking or lowering estrogen; for women with that history, the modest estradiol-elevating effect of boron reported in postmenopausal women runs in the opposite direction
- Other cognition-related cautions — as covered in the Hormone Balance Cautions section and the Bone Density Cautions section, the general boron supplementation safety profile is excellent at typical doses
Key Research Papers
- Penland JG (1994). Dietary boron, brain function, and cognitive performance. Environmental Health Perspectives. — PubMed PMID: 7889884
- Penland JG (1998). The importance of boron nutrition for brain and psychological function. Biological Trace Element Research. — PubMed PMID: 10050926
- Nielsen FH, Penland JG (1999). Boron supplementation of peri-menopausal women affects boron metabolism and indices associated with macromineral metabolism, hormonal status and immune function. Journal of Trace Elements in Experimental Medicine. — PubMed
- Nielsen FH (2008). Is boron nutritionally relevant? Nutrition Reviews. — PubMed
- Pizzorno L (2015). Nothing boring about boron. Integrative Medicine (Encinitas). — PubMed PMID: 26770156
- Naghii MR, Mofid M, Asgari AR, Hedayati M, Daneshpour MS (2011). Comparative effects of daily and weekly boron supplementation on plasma steroid hormones and proinflammatory cytokines. Journal of Trace Elements in Medicine and Biology. — PubMed PMID: 21129941
- Eyles DW, Burne TH, McGrath JJ (2013). Vitamin D, effects on brain development, adult brain function and the links between low levels of vitamin D and neuropsychiatric disease. Frontiers in Neuroendocrinology. — PubMed PMID: 22796576
- Henderson VW (2014). Alzheimer's disease: review of hormone therapy trials and implications for treatment and prevention after menopause. Journal of Steroid Biochemistry and Molecular Biology. — PubMed PMID: 23727128
- Slutsky I et al. (2010). Enhancement of learning and memory by elevating brain magnesium. Neuron. — PubMed PMID: 20152124
- Cherbuin N, Sachdev P, Anstey KJ (2012). Higher normal fasting plasma glucose is associated with hippocampal atrophy: the PATH Study. Neurology. — PubMed PMID: 22946113
- Smith AD et al. (2010). Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment. PLoS ONE. — PubMed PMID: 20838622
- Sesso HD, Buring JE, Christen WG, et al. (2008). Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomized controlled trial. JAMA. — PubMed PMID: 18997197
PubMed Topic Searches
Connections
- All Minerals
- Boron Overview
- Boron Benefits Hub
- Boron for Bone Density
- Boron for Hormone Balance
- Boron for Arthritis & Joints
- Alzheimer's Disease
- Dementia
- Magnesium
- Vitamin D3
- Vitamin B12
- Folate
- N-Acetylcysteine
- Alpha Lipoic Acid
- Omega-3 Fatty Acids
- Estradiol
- Testosterone
- Vitamin D Test
- Homocysteine
- Lion's Mane Mushroom
- Deficiency
- Toxicity
- History