⚠ Evidence warning: Clinical trials or other evidence do not support the claims that shilajit boosts cell energy in people, improves mineral absorption, works together with coenzyme Q10 and helps chronic fatigue, long COVID, fibromyalgia, heart failure and neurodegenerative disease. This page keeps it as a report of what people, websites or other media say.
Shilajit for Mitochondrial Function and Bioenergetics
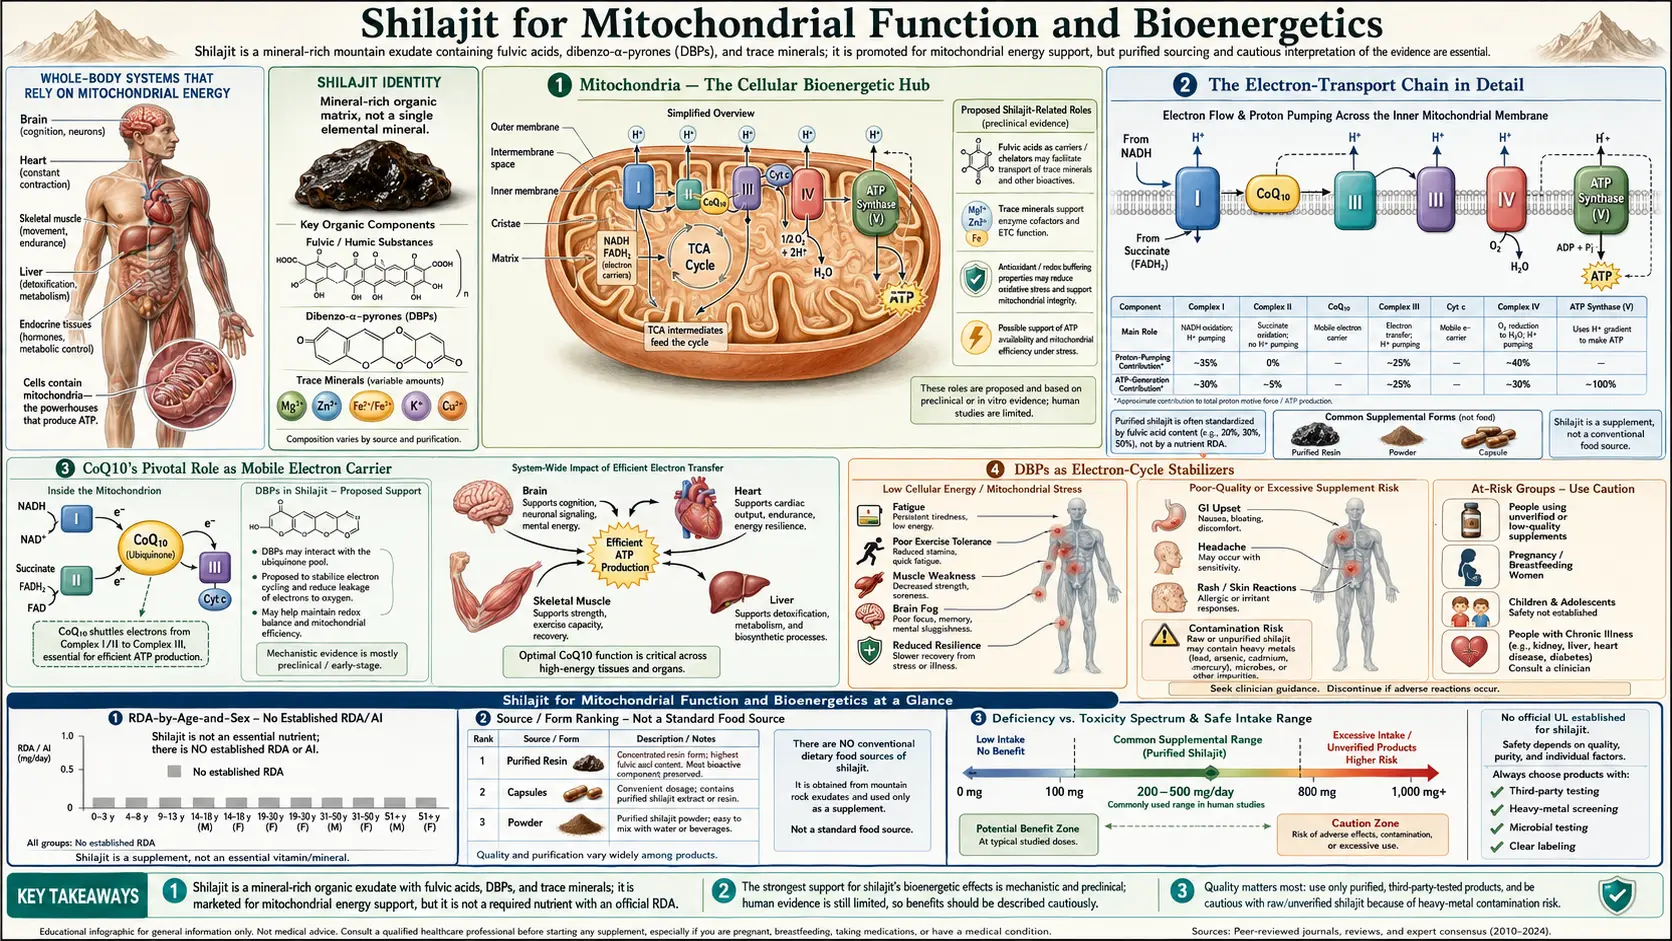
Mitochondrial bioenergetics is arguably the single most-studied mechanism of shilajit's effects. The framework that has emerged over the past two decades centers on two complementary actions: shilajit's dibenzo-alpha-pyrones (DBPs) function as electron-cycle stabilizers that prevent the oxidation of Coenzyme Q10 in the electron-transport chain, and its fulvic acid matrix delivers a broad spectrum of mineral cofactors to mitochondrial enzymes in highly bioavailable form. DBPs have been described as "mitochondria-targeted antioxidants," and a shilajit + coenzyme Q10 (CoQ10) combination has been reported to raise adenosine triphosphate (ATP) in animal tissue more than either substance alone; the original report of that combination could not be found for this page. The Surapaneni 2012 chronic-fatigue rat model found that shilajit, given for 21 days before the stress, kept brain mitochondrial complex enzyme activities stable. This page walks through the proposed bioenergetic mechanism in detail and the reasons given for using shilajit to support mitochondrial function in aging and chronic illness.
Table of Contents
- Mitochondria — The Cellular Bioenergetic Hub
- The Electron-Transport Chain in Detail
- Coenzyme Q10's Pivotal Role as Mobile Electron Carrier
- DBPs as Electron-Cycle Stabilizers
- The Reported Shilajit and Coenzyme Q10 Synergy
- The Surapaneni 2012 Bioenergetic Protection Data
- Fulvic Acid and Cofactor Delivery to Mitochondria
- Mitochondrial Aging and Why Support Matters
- Oxidative-Stress Protection of the Mitochondrial Membrane
- Clinical Applications and Specific Conditions
- Stacking Shilajit with Other Mitochondrial Cofactors
- Key Research Papers
- Connections
- Featured Videos
Mitochondria — The Cellular Bioenergetic Hub
Mitochondria are membrane-bound organelles present in nearly every nucleated cell of the human body, with numbers per cell ranging from a few hundred in lymphocytes to tens of thousands in cardiac muscle cells. They are the primary site of oxidative phosphorylation, the metabolic process that couples the oxidation of food-derived substrates (glucose, fatty acids, amino acids) to the synthesis of adenosine triphosphate, the universal cellular energy currency. The human body produces and consumes its body weight in adenosine triphosphate every day, almost all of which is synthesized by mitochondrial oxidative phosphorylation.
Each mitochondrion has a double-membrane structure: a smooth outer membrane that is relatively permeable to small molecules, and an extensively folded inner membrane (the cristae) that is the site of the electron-transport chain and adenosine triphosphate synthase. The folding of the inner membrane multiplies its surface area, allowing dense packing of the protein complexes that carry out oxidative phosphorylation. The matrix space enclosed by the inner membrane contains the enzymes of the citric acid cycle, fatty-acid beta-oxidation, urea cycle, and parts of heme biosynthesis.
Mitochondria carry their own small circular DNA genome (mtDNA), inherited essentially exclusively from the maternal lineage, that encodes 13 of the protein subunits of the electron-transport chain plus the tRNAs and rRNAs needed for mitochondrial protein synthesis. The remaining ~1500 mitochondrial proteins are encoded by the nuclear genome, synthesized in the cytoplasm, and imported into the mitochondrion via specialized translocase complexes. This division of labor between the two genomes makes mitochondrial biogenesis a coordinated process requiring intact nuclear-mitochondrial communication.
Mitochondria are also central to apoptosis (programmed cell death), calcium homeostasis, heme biosynthesis, steroid hormone synthesis, and the regulation of cellular redox state. They are not simply "powerhouses" but multifunctional signaling hubs whose dysfunction reverberates across the entire cellular phenotype.
The Electron-Transport Chain in Detail
The electron-transport chain (ETC) is the series of four protein complexes (Complex I, II, III, IV) embedded in the inner mitochondrial membrane that carry electrons from reduced cofactors (reduced nicotinamide adenine dinucleotide (NADH) and reduced flavin adenine dinucleotide (FADH2) generated by the citric acid cycle and beta-oxidation) to molecular oxygen, ultimately producing water. The electron transfer is coupled to the pumping of protons (H+) from the matrix into the intermembrane space, creating an electrochemical gradient (the proton-motive force) that drives adenosine triphosphate synthesis by Complex V (adenosine triphosphate synthase).
The four complexes:
- Complex I (reduced nicotinamide adenine dinucleotide:ubiquinone oxidoreductase) — accepts electrons from reduced nicotinamide adenine dinucleotide and passes them to ubiquinone (coenzyme Q10). Pumps 4 H+ per pair of electrons. Contains 45 subunits and multiple iron-sulfur clusters and a flavin mononucleotide (FMN) cofactor. The largest and most complex of the ETC complexes.
- Complex II (succinate dehydrogenase) — accepts electrons from FADH2 generated during the oxidation of succinate to fumarate in the citric acid cycle, and passes them to ubiquinone. Does not pump protons. Contains flavin adenine dinucleotide (FAD) and iron-sulfur clusters.
- Complex III (cytochrome bc1 complex) — accepts electrons from ubiquinol (reduced ubiquinone) and passes them to cytochrome c. Pumps 4 H+ per pair of electrons via the Q-cycle. Contains heme groups and a Rieske iron-sulfur protein.
- Complex IV (cytochrome c oxidase) — accepts electrons from cytochrome c and passes them to molecular oxygen, reducing it to water. Pumps 2 H+ per pair of electrons. Contains heme a and heme a3, plus two copper centers (CuA and CuB).
- Complex V (adenosine triphosphate synthase) — uses the proton gradient established by Complexes I, III, and IV to drive the phosphorylation of adenosine diphosphate (ADP) to adenosine triphosphate. Pumps protons back into the matrix through the F0 channel, with the F1 head catalyzing adenosine triphosphate synthesis.
Two mobile carriers shuttle electrons between the fixed complexes: coenzyme Q10 (ubiquinone) moves electrons between Complexes I/II and Complex III, and cytochrome c moves electrons between Complex III and Complex IV. Both mobile carriers are rate-limiting under various conditions, and dysfunction or depletion of either can throttle the entire ETC.
The relevance of all this detail for shilajit is that coenzyme Q10 sits at the central node of the electron-transport chain — it is the single mobile carrier through which electrons from both reduced nicotinamide adenine dinucleotide (via Complex I) and FADH2 (via Complex II) must pass. Anything that stabilizes coenzyme Q10 or augments its function has disproportionate effects on overall ETC throughput.
Coenzyme Q10's Pivotal Role as Mobile Electron Carrier
Coenzyme Q10 (also called ubiquinone, ubiquinol when reduced) is a small lipid-soluble benzoquinone with a long isoprenoid tail (10 isoprene units in the human form, hence Q10) that anchors it in the inner mitochondrial membrane. Coenzyme Q10 exists in three redox states:
- Ubiquinone (oxidized, Q) — the fully oxidized form, ready to accept electrons from Complex I or Complex II
- Ubisemiquinone (one-electron-reduced, QH-) — the intermediate radical form, generated transiently during the Q-cycle at Complex III
- Ubiquinol (fully reduced, QH2) — the fully reduced form, ready to donate electrons to Complex III
Ubiquinol additionally functions as a potent membrane antioxidant, protecting membrane lipids from peroxidation by donating electrons to lipid radicals and regenerating reduced vitamin E (alpha-tocopherol). The mitochondrial membrane has an extraordinarily high content of polyunsaturated phospholipids (cardiolipin in particular, which is found nowhere else in the cell) that are vulnerable to oxidative damage; ubiquinol is the primary defense against this damage.
Cellular coenzyme Q10 levels decline with age, in part because of reduced biosynthesis (the mevalonate pathway shared with cholesterol biosynthesis) and in part because of increased oxidative consumption. Statin drugs, which inhibit 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase in the mevalonate pathway, further reduce coenzyme Q10 biosynthesis as an off-target effect — the proposed mechanism behind the muscle-pain and fatigue side effects of statin therapy in a subset of patients.
The cellular balance between ubiquinone and ubiquinol forms is dynamically regulated. Under high metabolic demand or oxidative stress, ubiquinol gets oxidized faster than the ETC can re-reduce it, shifting the balance toward the inactive ubiquinone form. The hypothesis proposed for shilajit is that its DBPs act precisely at this point of regulation: they stabilize ubiquinol against premature oxidation, keeping more of the cellular coenzyme Q10 pool in the active form.
DBPs as Electron-Cycle Stabilizers
The dibenzo-alpha-pyrone family of molecules in shilajit shares key structural features with ubiquinone: both are small aromatic molecules with redox-active functional groups capable of accepting and donating electrons in pairs. The proposed mechanism by which DBPs stabilize the ubiquinone/ubiquinol cycle:
- DBPs act as auxiliary electron carriers at the inner mitochondrial membrane, accepting electrons from upstream cofactors and shuttling them to Complex III in parallel with native coenzyme Q10. This effectively expands the pool of mobile electron carriers and reduces the rate-limiting bottleneck of coenzyme Q10 turnover.
- DBPs preferentially reduce oxidized ubiquinone back to ubiquinol, keeping more of the native coenzyme Q10 pool in the active reduced form even under conditions of high metabolic demand.
- DBPs quench reactive oxygen species generated at Complexes I and III, protecting the surrounding membrane and reducing the oxidative consumption of ubiquinol that occurs when reactive oxygen species (ROS) production exceeds antioxidant defense capacity.
- DBPs may protect the iron-sulfur clusters of Complex I against oxidative damage, preserving the structural integrity of the most damage-vulnerable of the ETC complexes.
The net effect of these four actions is increased adenosine triphosphate synthesis per unit of substrate oxidized, reduced reactive-oxygen-species leak, and preserved coenzyme Q10 functionality under conditions of metabolic stress. This is qualitatively different from being a simple antioxidant — the proposed mechanism is specifically integrated with the electron-transport chain rather than passively scavenging free radicals from outside the system.
The description of DBPs as "mitochondria-targeted antioxidants" was meant to capture this integration. The phrase has since been picked up by the wider supplement-industry literature, sometimes inaccurately. The precise claim is more subtle: DBPs do not simply soak up reactive oxygen species that wander into the mitochondrion; they participate functionally in electron transport in a way that reduces reactive oxygen species leak at its source.
The Reported Shilajit and Coenzyme Q10 Synergy
A synergy between shilajit's DBPs and coenzyme Q10 is widely reported in the shilajit literature: the combination is said to raise adenosine triphosphate in the brain and muscle of rats, and to improve endurance, by more than either substance alone. The report usually cited for it is a 2009 paper in Pharmacologyonline, a journal not indexed in PubMed; it could not be found in PubMed, Europe PMC, Crossref or OpenAlex for this page, so its design and figures are not repeated here. A 2014 review of shilajit's safety and efficacy (Stohs) states more generally that animal and human data support its use as a “revitalizer”, relieving fatigue with enhanced production of ATP; its abstract does not mention coenzyme Q10.
The mechanistic interpretation offered for the reported synergy is that shilajit's DBPs prevent the oxidation of administered coenzyme Q10 to the inactive ubiquinone form, allowing far more of the exogenous coenzyme Q10 to remain in the active ubiquinol form where it can participate in electron transport. In this view, without DBP co-administration, much of the supplemented coenzyme Q10 is rapidly oxidized to ubiquinone and provides only modest functional benefit.
Proponents draw implications beyond shilajit: they suggest that the disappointing clinical-trial track record of coenzyme Q10 monotherapy (which has shown signal in some conditions but failed to deliver convincing benefit in others) may reflect not a failure of the mitochondrial-bioenergetic hypothesis but a delivery problem — the supplemented coenzyme Q10 being oxidized before it could be functionally incorporated — and that co-administration with DBPs may rescue this delivery failure.
Caveat: no study that could be read for this page confirms the synergy or its size, and no trial has tested shilajit with coenzyme Q10 in people.
The Surapaneni 2012 Bioenergetic Protection Data
The Surapaneni et al. 2012 chronic-fatigue-syndrome rat study (Journal of Ethnopharmacology, 143(1):91-99) is also highly relevant to the mitochondrial-function indication. While the paper's headline framing was on chronic fatigue syndrome, its mitochondrial measurements in the front part of the brain (prefrontal cortex) provide animal evidence for shilajit's bioenergetic mechanism. No muscle tissue was measured.
The shilajit used was a processed extract standardised to 0.43% dibenzo-alpha-pyrones, 20.45% DBP-chromoproteins and 56.75% fulvic acids. Rats were given 25, 50 or 100 mg/kg for 21 days before the stress procedure, in which they were forced to swim for 15 minutes a day for 21 consecutive days to produce a chronic-fatigue-like state. Shilajit reversed the stress-induced rise in immobility and fall in climbing, reduced anxiety on a maze test, and reversed the fall in blood corticosterone and the loss of adrenal-gland weight — signs that it steadied the stress-hormone (hypothalamic-pituitary-adrenal) axis.
Key mitochondrial findings:
- The activities of mitochondrial Complexes I, II, IV and V and the mitochondrial membrane potential were measured in the prefrontal cortex
- Shilajit prevented the stress-induced mitochondrial dysfunction by keeping the complex enzyme activities stable
- Mitochondrial membrane potential was preserved
- Stress-induced mitochondrial oxidative stress was reversed, measured as nitric oxide, lipid peroxidation, and the activities of the antioxidant enzymes superoxide dismutase (SOD) and catalase
This profile is consistent with the broader DBP-as-mitochondrial-protector mechanism: shilajit, given before the stress, preserved both the structural integrity (membrane potential) and the functional capacity (complex enzyme activities) of brain mitochondria under stress. The abstract does not report how the effect differed across the three doses.
For chronic-fatigue indications specifically, the Surapaneni model is one of the more directly relevant animal-model systems because it combines hypothalamic-pituitary-adrenal-axis stress, mitochondrial dysfunction, oxidative stress, and behavioral fatigue endpoints — the same combination that characterizes human chronic fatigue syndrome, post-viral fatigue, and burnout-related exhaustion.
Fulvic Acid and Cofactor Delivery to Mitochondria
The DBP electron-stabilizer story is the most distinctive part of the shilajit mitochondrial mechanism, but it is complemented by the fulvic-acid mineral-delivery effect. Mitochondrial function depends on a long list of mineral cofactors, several of which deserve specific mention:
- Iron — required for the iron-sulfur clusters in Complexes I, II, and III, and for the heme groups in Complexes III and IV. Iron deficiency directly impairs ETC throughput regardless of any other intervention.
- Copper — required for Complex IV (cytochrome c oxidase). Copper deficiency, often subclinical in patients with chronic illness, can be a significant rate-limiter on mitochondrial respiration. See Copper.
- Magnesium — required as a structural cofactor for adenosine triphosphate synthase (the enzyme actually makes Mg-ATP, not adenosine triphosphate per se) and dozens of other mitochondrial enzymes. Subclinical magnesium deficiency is common.
- Manganese — required for mitochondrial superoxide dismutase (MnSOD), the primary antioxidant defense within the mitochondrial matrix.
- Zinc — structural cofactor for many mitochondrial dehydrogenases and a co-regulator of mitochondrial biogenesis.
- Selenium — required for glutathione peroxidase 4 (GPx4), the only enzyme capable of reducing phospholipid hydroperoxides directly in the membrane.
Shilajit's fulvic acid is said, in the supplement literature, to carry all of these in ionic form and to improve their absorption compared to inorganic salt forms. Proponents argue that for people with broad-spectrum subclinical mineral deficiency, this comprehensive delivery may matter more than any individual single-mineral supplement.
The mitochondria also depend on adequate availability of several B-vitamin-derived cofactors: thiamine pyrophosphate (B1) for pyruvate dehydrogenase and alpha-ketoglutarate dehydrogenase, riboflavin (B2) for flavin adenine dinucleotide (FAD) and flavin mononucleotide (FMN) in Complexes I and II, niacin (B3) for nicotinamide adenine dinucleotide (NAD+)/reduced nicotinamide adenine dinucleotide, pantothenic acid (B5) for CoA, and biotin (B7) for pyruvate carboxylase. Shilajit does not directly provide these B vitamins; mitochondrial-support protocols described by practitioners typically pair it with a B-complex supplement.
Mitochondrial Aging and Why Support Matters
Mitochondrial dysfunction is one of the recognized "hallmarks of aging" (per the influential Lopez-Otin 2013 Cell review) and is causally implicated in age-related decline across virtually every organ system. The aging mitochondrial phenotype includes:
- Accumulation of mtDNA point mutations and large deletions
- Reduced biogenesis of new mitochondria (decreased expression of peroxisome proliferator-activated receptor gamma coactivator 1-alpha, PGC-1-alpha)
- Impaired mitophagy (selective autophagy of damaged mitochondria)
- Accumulation of dysfunctional senescent mitochondria within cells
- Reduced cardiolipin content and altered inner-membrane structure
- Increased reactive-oxygen-species leak at Complexes I and III
- Decreased adenosine triphosphate production per oxygen consumed (reduced coupling efficiency)
- Reduced mitochondrial calcium-handling capacity
Each of these contributes to the gradual reduction in cellular adenosine triphosphate availability that drives the overall decline in tissue function with age. Tissues with the highest mitochondrial density and energy demand — brain, heart, skeletal muscle, kidney, liver — are most vulnerable.
The therapeutic interest in mitochondrial-support interventions like shilajit, nicotinamide adenine dinucleotide precursors (nicotinamide riboside, nicotinamide mononucleotide), urolithin A, methylene blue, mitoquinone (a mitochondria-targeted coenzyme Q10 analogue), and elamipretide (SS-31, a mitochondria-targeting peptide) reflects the recognition that addressing mitochondrial decline may be one of the most leverage-rich interventions for healthy aging. None of these substances has been definitively shown to extend human lifespan, but the mechanistic case is strong and the clinical-trial literature is rapidly expanding.
Shilajit's positioning in this landscape is as a multi-target intervention that addresses electron-transport-chain efficiency (DBP mechanism), antioxidant defense (induction of endogenous superoxide dismutase (SOD)/catalase/GPx), and mineral cofactor delivery (fulvic-acid chelation) simultaneously. It is unlikely to be a single "magic bullet," but as a component of a broader healthy-aging protocol it has both mechanistic plausibility and a multi-millennial track record of safe traditional use.
Oxidative-Stress Protection of the Mitochondrial Membrane
The inner mitochondrial membrane has an unusually high content of cardiolipin, a phospholipid with four fatty-acid tails (most lipids have two) that is essential for the structural organization and functional efficiency of Complexes III and IV and the ADP/ATP translocase. Cardiolipin is enriched in polyunsaturated fatty acids (linoleic acid in particular) which makes it extraordinarily vulnerable to oxidative damage.
Cardiolipin oxidation has cascading consequences: oxidized cardiolipin releases cytochrome c from its binding site on Complex III, which both impairs electron transport and primes the cell for apoptosis (because cytoplasmic cytochrome c activates the caspase cascade). Loss of cardiolipin also disrupts the assembly of ETC supercomplexes (the higher-order assemblies of Complexes I, III, and IV that increase respiratory efficiency), further degrading adenosine triphosphate production.
The protection of cardiolipin against oxidative damage is therefore a high-leverage mitochondrial intervention. The defenses include:
- Membrane-bound antioxidants (ubiquinol, vitamin E)
- The glutathione peroxidase 4 (GPx4) enzyme that specifically reduces phospholipid hydroperoxides
- Mitochondria-targeted antioxidant interventions such as mitoquinone and (in the present argument) shilajit DBPs
The description of shilajit DBPs as "mitochondria-targeted antioxidants" maps directly onto this proposed cardiolipin-protection role. In this proposal, by scavenging the reactive oxygen species generated at Complexes I and III before they damage cardiolipin, DBPs help preserve the structural integrity of the inner-membrane phospholipid environment that the ETC depends on.
Clinical Applications and Specific Conditions
Conditions in which mitochondrial dysfunction is a recognized component, and where shilajit's bioenergetic profile may have particular relevance:
- Myalgic encephalomyelitis / chronic fatigue syndrome (ME/CFS) — mitochondrial dysfunction is one of the more reproducible biochemical findings in chronic fatigue syndrome (CFS), and the Surapaneni 2012 rat model directly tested shilajit in this context with positive results
- Long-COVID / post-viral fatigue — emerging research suggests substantial mitochondrial dysfunction in long-COVID patients; shilajit has not been formally trialed but the mechanistic case parallels chronic fatigue syndrome
- Fibromyalgia — mitochondrial dysfunction has been documented in muscle biopsies from fibromyalgia patients
- Statin-associated myopathy — the statin-induced coenzyme Q10 deficiency mechanism is the rationale for coenzyme Q10 supplementation in statin-intolerant patients; the proposed coenzyme Q10-stabilizing effect of shilajit has been put forward as a way to amplify the benefit of co-administered coenzyme Q10, though no trial has tested shilajit with coenzyme Q10 in people
- Heart failure — cardiac mitochondrial dysfunction is central to heart-failure pathophysiology, and coenzyme Q10 supplementation has shown signal in the Q-SYMBIO trial: 420 people with moderate to severe heart failure took coenzyme Q10 100 mg three times daily or placebo alongside standard treatment for two years. Short-term measures at 16 weeks did not change, but major adverse cardiovascular events occurred in 15% on coenzyme Q10 versus 26% on placebo, with lower cardiovascular death (9% vs 16%) and death from any cause (10% vs 18%). Shilajit plus coenzyme Q10 is a proposed extension; no trial has tested shilajit with coenzyme Q10 in people
- Age-related sarcopenia — skeletal-muscle mitochondrial decline contributes to the loss of muscle mass and strength with age; the Keller 2019 trial studied 63 recreationally active young men (average age 21), not older adults: 500 mg/day of shilajit for 8 weeks lessened the strength loss after a fatiguing exercise test only in the stronger half of participants (8.9% decline versus 16.0% on placebo), while 250 mg/day made no difference. Whether this applies to age-related muscle loss has not been tested
- Neurodegenerative disease — mitochondrial dysfunction is implicated in Alzheimer's, Parkinson's, amyotrophic lateral sclerosis (ALS), and Huntington's disease; shilajit has been investigated in animal models with positive results, though human-trial data are limited
A human study that took muscle samples (Das 2016) gave overweight or mildly obese adults 250 mg of shilajit twice a day for 8 weeks, then 4 more weeks combined with exercise. Blood sugar, blood fats, creatine kinase and myoglobin did not change. What changed in the muscle after 8 weeks was a cluster of 17 connective-tissue (extracellular-matrix) gene probes, including collagen, elastin, fibrillin 1 and fibronectin 1. The abstract reports no mitochondrial change, so direct human evidence of a mitochondrial effect is still missing.
Important caveat: none of these conditions has a well-powered randomized controlled trial of shilajit specifically as a primary intervention. The mechanistic case is strong, but clinical-trial evidence remains preliminary. No study has tested shilajit as a replacement for standard medical treatment of any of these conditions.
Stacking Shilajit with Other Mitochondrial Cofactors
Protocols that practitioners and supplement users describe for mitochondrial function typically combine shilajit with several other substances; the doses below are the ranges these protocols describe:
- Coenzyme Q10 (often as ubiquinol) — 100-300 mg/day. The reported shilajit–coenzyme Q10 synergy (see above) is the usual justification for this combination. Ubiquinol is the active reduced form and is described as better absorbed than the standard ubiquinone form.
- B-complex — a multivitamin with all B vitamins (especially B1 thiamine, B2 riboflavin, B3 niacin/niacinamide, B5 pantothenic acid, B7 biotin)
- Magnesium glycinate or magnesium malate — 200-400 mg elemental magnesium daily. The glycinate form is well-absorbed and gentle on the gastrointestinal (GI) tract; malate is particularly favored for mitochondrial applications because malate is a citric-acid-cycle intermediate.
- L-carnitine (acetyl-L-carnitine or L-carnitine tartrate) — 500-2000 mg/day. Carnitine shuttles long-chain fatty acids into the mitochondrial matrix for beta-oxidation; carnitine deficiency directly impairs fatty-acid energy metabolism.
- Alpha-lipoic acid (often the R-form) — 200-600 mg/day. Alpha-lipoic acid (ALA) is a mitochondrial cofactor for pyruvate dehydrogenase and alpha-ketoglutarate dehydrogenase and also functions as an antioxidant that recycles vitamin E and glutathione.
- Nicotinamide adenine dinucleotide precursors — nicotinamide riboside (NR) or nicotinamide mononucleotide (NMN), 250-1000 mg/day. These raise tissue nicotinamide adenine dinucleotide levels, which decline with age and are required for ETC function and for sirtuin enzyme activity.
- Creatine monohydrate — 3-5 g/day. Creatine acts as a high-energy phosphate buffer that smooths adenosine triphosphate availability across periods of high demand.
This kind of multi-component "mitochondrial cocktail" approach is the working framework used in mitochondrial-medicine specialty clinics. The synergies between components are not all formally proven in randomized controlled trials, but the mechanistic logic is coherent and the safety profile of well-sourced versions of each component is benign.
Key Research Papers
- Surapaneni DK, Adapa SR, Preeti K, Teja GR, Veeraragavan M, Krishnamurthy S (2012). Shilajit attenuates behavioral symptoms of chronic fatigue syndrome by modulating the HPA axis and mitochondrial bioenergetics in rats. Journal of Ethnopharmacology. — PubMed PMID: 22771318
- Visser SA (1987). Effect of humic substances on mitochondrial respiration and oxidative phosphorylation. Science of the Total Environment. — PubMed PMID: 2953069
- Stohs SJ (2014). Safety and efficacy of shilajit (mumie, moomiyo). Phytotherapy Research. — PubMed PMID: 23733436
- Keller JL, Housh TJ, Hill EC, et al. (2019). The effects of Shilajit supplementation on fatigue-induced decreases in muscular strength and serum hydroxyproline levels. Journal of the International Society of Sports Nutrition. — PubMed PMID: 30728074
- Das A, Datta S, Rhea B, et al. (2016). The human skeletal muscle transcriptome in response to oral shilajit supplementation. Journal of Medicinal Food. — PubMed PMID: 27414521
- Ghosal S, Singh SK, Kumar Y, Srivastava R (1988). Antiulcerogenic activity of fulvic acids and 4-methoxy-6-carbomethoxybiphenyl isolated from Shilajit. Phytotherapy Research. — PubMed
- Lopez-Otin C, Blasco MA, Partridge L, Serrano M, Kroemer G (2013). The hallmarks of aging. Cell. — PubMed PMID: 23746838
- Lesnefsky EJ, Hoppel CL (2006). Oxidative phosphorylation and aging. Ageing Research Reviews. — PubMed PMID: 16831573
- Wallace DC (2005). A mitochondrial paradigm of metabolic and degenerative diseases, aging, and cancer. Annual Review of Genetics. — PubMed PMID: 16285865
- Mortensen SA, Rosenfeldt F, Kumar A, et al. (2014). The effect of coenzyme Q10 on morbidity and mortality in chronic heart failure: results from Q-SYMBIO: a randomized double-blind trial. JACC: Heart Failure. — PubMed PMID: 25282031
- Schepetkin I, Khlebnikov A, Kwon BS (2002). Medical drugs from humus matter: focus on mumie. Drug Development Research. — PubMed
- Carrasco-Gallardo C, Guzman L, Maccioni RB (2012). Shilajit: a natural phytocomplex with potential procognitive activity. International Journal of Alzheimer's Disease. — PubMed PMID: 22482077