⚠ Evidence warning: Clinical trials or other evidence do not support the claims that tart cherry relieves fibromyalgia, post-surgical pain and inflammatory arthritis. This page keeps it as a report of what people, websites or other media say.
Tart Cherry for Inflammation & Athletic Recovery
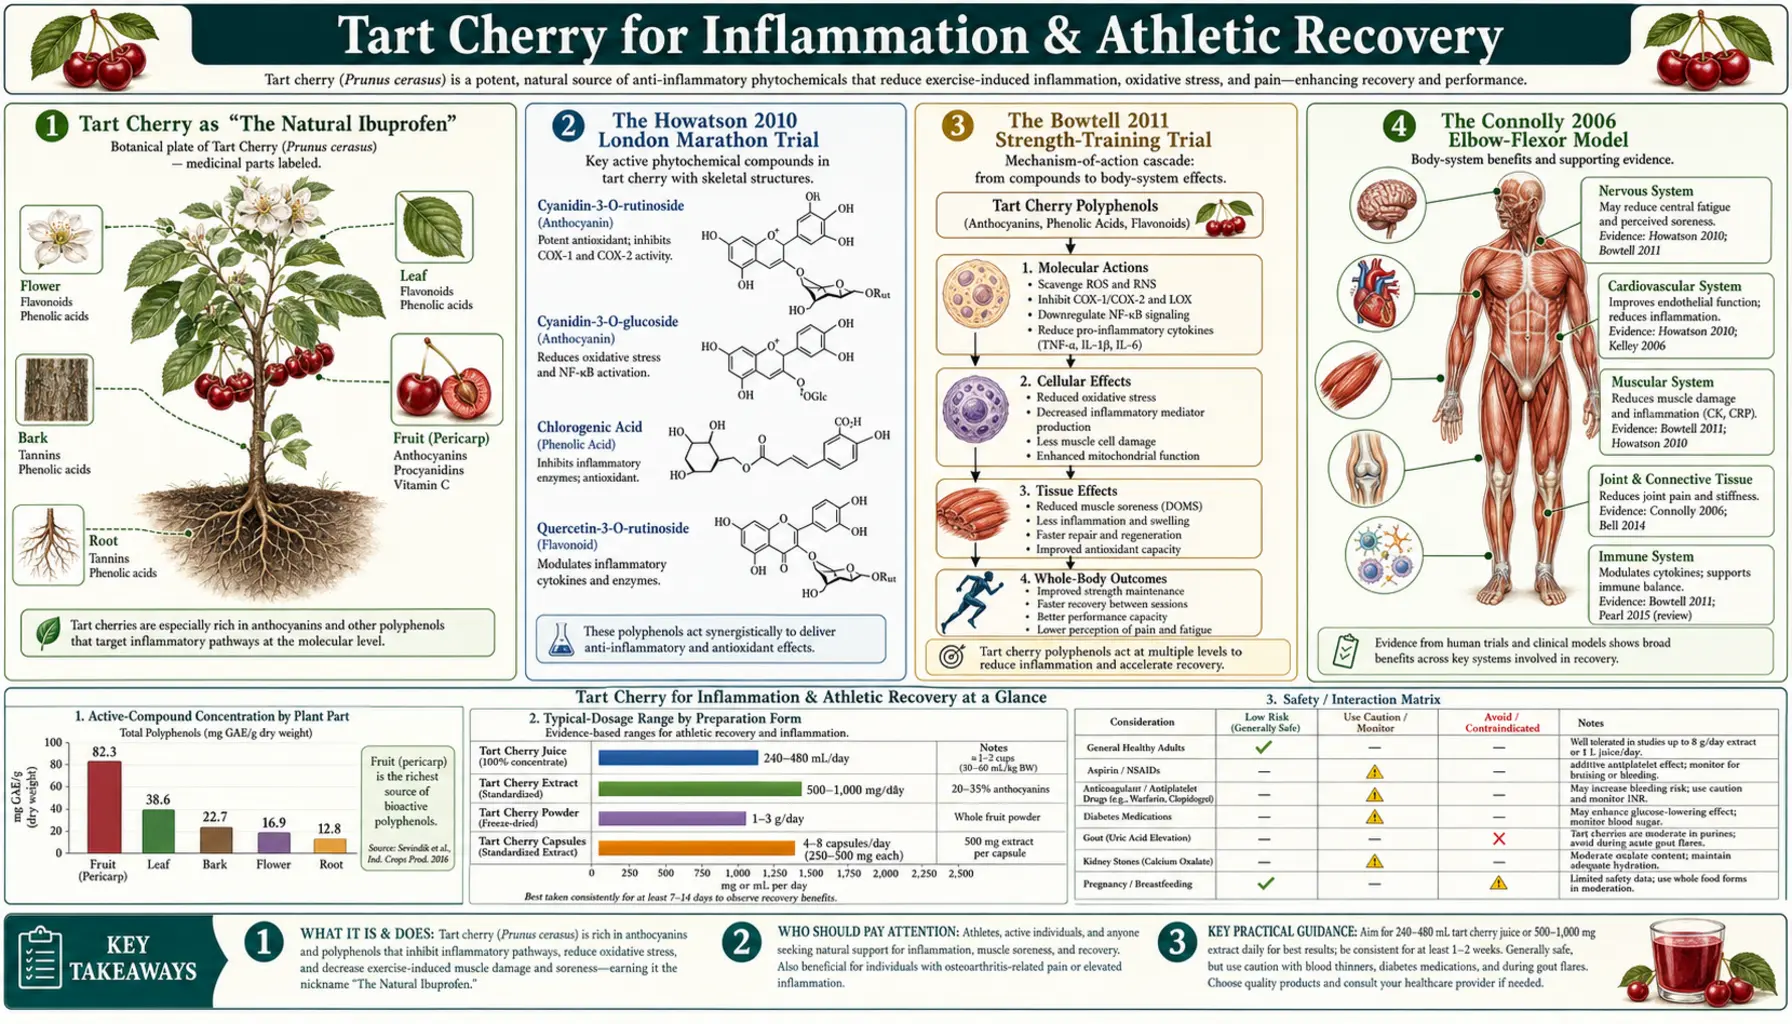
Tart cherry has earned the nickname "the natural ibuprofen" among sports-medicine researchers. The evidence behind that name is real but narrower than the nickname suggests: it sits almost entirely in short recovery trials after a single hard bout, and several trials of resting inflammation in ordinary adults have been flatly negative. A series of well-designed randomized trials between 2006 and 2015 documented that Montmorency tart cherry juice or freeze-dried capsule supplementation around endurance and resistance exercise reduces post-event delayed-onset muscle soreness (DOMS), preserves isometric strength recovery, lowers post-event serum C-reactive protein (CRP) and interleukin-6 (IL-6), blunts oxidative-stress markers, and accelerates the return to baseline performance metrics. The Howatson 2010 London Marathon trial and the Bowtell 2011 strength-training trial are the most cited, but the body of evidence now includes elbow-flexor models, cycling protocols, and team-sport recovery trials. The clinical translation matters because the conventional alternative — nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, aspirin) taken around exercise — carries underappreciated downsides: gastrointestinal (GI) bleeding risk, renal dysfunction in dehydrated athletes, and, in some trials, inhibition of the anabolic muscle-adaptation signaling that exercise is supposed to produce. No trial has compared tart cherry with these drugs head to head, and a 2026 meta-analysis of 19 trials in athletes found no pooled effect on muscle soreness; its pooled benefits were faster strength recovery and lower CRP. This article walks through the trials, the molecular mechanism (anthocyanin-mediated COX modulation and antioxidant defense), the loading and maintenance schedules used in the trials and in sports practice, and the head-to-head comparison with nonsteroidal anti-inflammatory drug (NSAID) strategies.
Table of Contents
- Tart Cherry as "The Natural Ibuprofen"
- The Howatson 2010 London Marathon Trial
- The Bowtell 2011 Strength-Training Trial
- The Connolly 2006 Elbow-Flexor Model
- Mechanism: Anthocyanins, Cyclooxygenase-2, and Oxidative Stress
- C-Reactive Protein, Interleukin-6, and Tumor Necrosis Factor-Alpha Reduction
- Comparison: Tart Cherry vs Ibuprofen / Naproxen / Aspirin
- The Nonsteroidal Anti-Inflammatory Drug Anti-Adaptive Muscle-Recovery Problem
- Loading, Maintenance, and Post-Event Protocols
- Beyond Sports: Chronic Inflammatory Conditions
- Cautions, Interactions, and Patient Selection
- Key Research Papers
- Connections
- Featured Videos
Tart Cherry as "The Natural Ibuprofen"
The phrase "natural ibuprofen" is informal but apt. Like ibuprofen, tart cherry anthocyanins inhibit cyclooxygenase (COX) enzymes, reducing prostaglandin production at the site of tissue injury and inflammation. Unlike ibuprofen, the inhibition is modest, broad-spectrum across cyclooxygenase-1 (COX-1) and cyclooxygenase-2 (COX-2), and accompanied by direct antioxidant scavenging of reactive oxygen species, plus a separate set of anti-inflammatory effects on NF-kB signaling, interleukin-6 transcription, and tumor necrosis factor-alpha release.
The earliest mechanistic demonstration was Wang et al. (1999) at Michigan State University, who isolated anthocyanins and their sugar-free core (aglycone), cyanidin, from tart cherries. In test-tube assays they reported antioxidant and anti-inflammatory activities “comparable to commercial products”; the cyclooxygenase-1 and cyclooxygenase-2 inhibition figures (IC50 values, printed in the abstract as 90 and 60 mM) were reported for cyanidin only, not for the anthocyanins. This established that the molecular machinery was at least theoretically capable of producing a nonsteroidal anti-inflammatory drug-like effect, and motivated the human trials that followed.
The translational question was always whether a dietary dose of cherries or cherry juice would deliver enough anthocyanin to the bloodstream and the relevant tissues to produce a clinically meaningful effect. The answer, established by the trials below, is yes — for the specific clinical context of post-exercise muscle damage and inflammation, where the cumulative effect of dietary anthocyanin loading produces measurable reductions in markers of muscle damage, inflammation, and subjective soreness.
The Howatson 2010 London Marathon Trial
The most cited and most clinically interpretable tart cherry sports-medicine trial is Howatson, McHugh, and colleagues published in Scandinavian Journal of Medicine & Science in Sports in 2010. The design was a parallel-group randomized trial in 20 recreational marathon runners (10 cherry, 10 placebo) preparing for and running the 2008 London Marathon. The intervention was 8 oz of Montmorency tart cherry juice twice daily for 5 days before the race, on race day, and for 48 hours after — total 8 days of loading.
Outcomes were measured at baseline, immediately post-race, 24 hours, and 48 hours post-race:
- Isometric strength recovery — the cherry group recovered isometric quadriceps strength significantly faster than placebo, returning to near-baseline values by 48 hours while the placebo group was still substantially impaired
- Inflammation markers — serum interleukin-6 (IL-6) and high-sensitivity C-reactive protein (CRP) were lower in the cherry group at 24 and 48 hours post-race
- Oxidative stress — total antioxidant status was about 10% higher in the cherry group, and lipid peroxidation (thiobarbituric acid reactive substances, TBARS) was lower at 48 hours; protein carbonyls did not differ between groups
- Muscle damage — creatine kinase tended lower in the cherry group, though the difference did not reach significance
- Subjective soreness — muscle soreness did not differ significantly between the groups
The Howatson 2010 trial was the first to show that a dietary intervention could meaningfully shift the marathon-recovery time course. The magnitude of the strength-recovery effect was large enough to be relevant to professional athletes with tight competition calendars where 24-48 hours faster recovery has direct competitive implications.
The Bowtell 2011 Strength-Training Trial
Bowtell and colleagues at the University of Brighton published the complementary strength-training trial in Medicine & Science in Sports & Exercise in 2011. The design was a randomized double-blind crossover in 10 well-trained men (mean age 27, regular strength trainers) performing 10 sets of 10 single-leg knee extensions at 80% of one-repetition maximum, with the two trials 2 weeks apart and the other leg used in the second trial. Subjects consumed 30 ml Montmorency tart cherry juice concentrate (diluted in 100 ml water) twice daily for 7 days before exercise, on the day of exercise, and for 48 hours after — or a non-cherry placebo of similar appearance.
The principal outcome was recovery of maximal voluntary isometric contraction (MVIC), a sensitive measure of muscle-damage recovery, alongside markers of inflammation and oxidative stress:
- MVIC recovery — strength recovered significantly faster after cherry: 90.9% of initial strength at 24 hours versus 84.9% after placebo, and 92.9% versus 88.5% at 48 hours.
- Oxidative damage — protein carbonyls (a marker of oxidative damage to proteins) rose 23.8% at 24 hours after cherry versus 82.7% after placebo (P = 0.013).
- Muscle damage — the rise in creatine kinase was the same in both trials.
The Bowtell trial extended the Howatson finding from the endurance-exercise context (marathon) to the strength-training context (eccentric resistance exercise). The same intervention, in roughly the same protocol, again produced faster recovery of strength. The convergence across two different exercise paradigms strengthens the evidence base substantially — this is not a quirk of one specific protocol.
The Connolly 2006 Elbow-Flexor Model
The earliest of the modern tart cherry exercise trials was Connolly and colleagues, published in the British Journal of Sports Medicine in 2006. The design used the classic eccentric elbow-flexor (biceps) protocol that has been a workhorse model in DOMS research for decades — subjects perform 2 sets of 20 maximal eccentric elbow flexions on an isokinetic dynamometer, which reliably produces measurable strength loss, swelling, soreness, and recovery curves over 4-5 days. The subjects were 14 college-age males. The intervention was 12 oz of tart cherry juice blend or a placebo twice daily for 8 consecutive days, in a randomized crossover design: two weeks later each subject repeated the protocol on the other drink, using the opposite arm for the second bout of exercise.
Key results:
- Pain scores — subjects reported significantly less elbow-flexor pain on the cherry arm at days 3 and 4 post-exercise
- Strength loss — isometric elbow-flexor strength loss averaged over the four days after exercise was 22% on placebo vs 4% on cherry
- Within-subject design — because each subject served as their own control, taking cherry in one bout and placebo in the other, the protocol was particularly rigorous against between-subject variability confounders
The Connolly trial was the original proof of principle that motivated the larger Howatson and Bowtell trials that followed. Its within-subject design remains a methodologic strength in a literature otherwise dominated by parallel-group trials.
Mechanism: Anthocyanins, Cyclooxygenase-2, and Oxidative Stress
The molecular mechanism of tart cherry's anti-inflammatory effect operates through at least four distinct pathways:
- Direct antioxidant scavenging — the cyanidin-3-glucoside structure has a catechol B-ring that donates hydrogen to peroxyl, hydroxyl, and superoxide radicals, neutralizing them before they can damage cell membranes (lipid peroxidation), proteins (carbonyl formation), or DNA (8-oxoguanine adducts). In exercise contexts, the principal source of oxidative damage is mitochondrial reactive oxygen species (ROS) leak during high-intensity contraction; anthocyanins reach concentrations in plasma sufficient to provide measurable scavenging
- Cyclooxygenase-1 and cyclooxygenase-2 inhibition — the Wang 1999 in vitro work reported inhibition of both cyclooxygenase isoforms by cyanidin, the aglycone of the tart cherry anthocyanins (IC50 values printed as 90 and 60 mM for COX-1 and COX-2); the effect is modest per molecule, but the cumulative anthocyanin load from concentrated supplementation produces measurable downstream prostaglandin reduction
- NF-kB transcription factor inhibition — anthocyanins reduce nuclear translocation of the NF-kB heterodimer, which is the master regulator of inflammatory gene expression. Downstream consequences include reduced transcription of interleukin-1 (IL-1), interleukin-6, IL-8, tumor necrosis factor-alpha, cyclooxygenase-2, and inducible nitric oxide synthase (iNOS)
- Nrf2 antioxidant defense activation — anthocyanins (and related polyphenols) activate the Nrf2 / Keap1 / ARE pathway, the master regulator of endogenous antioxidant defense. Activation upregulates glutathione synthesis enzymes, superoxide dismutase, catalase, and a suite of phase-II detoxification enzymes — producing a longer-lasting "indirect antioxidant" effect that outlasts the direct scavenging by hours to days
The multi-mechanism profile is what distinguishes tart cherry from a single-pathway pharmacologic intervention. Nonsteroidal anti-inflammatory drugs hit one mechanism hard (COX inhibition) but produce no Nrf2 activation, no direct radical scavenging, and no transcriptional anti-inflammatory effect. Tart cherry hits multiple mechanisms modestly — the dietary intervention pattern.
C-Reactive Protein, Interleukin-6, and Tumor Necrosis Factor-Alpha Reduction
The serum inflammatory marker reductions documented across the tart cherry trials are clinically meaningful in their own right, beyond the sports-medicine context. The Howatson 2010 marathon trial reported lower C-reactive protein (CRP) in the cherry group after the race (P<0.01). Interleukin-6, the most exercise-responsive cytokine, was also reduced (P<0.001). Tumor necrosis factor-alpha was not measured in that trial.
These changes are mechanistically relevant to chronic disease prevention. Elevated high-sensitivity C-reactive protein is an independent risk factor for cardiovascular events; elevated interleukin-6 is implicated in insulin resistance, depression, and accelerated brain aging; tumor necrosis factor-alpha drives a wide range of autoimmune and inflammatory conditions. The fact that a dietary intervention can measurably reduce CRP and interleukin-6 after exercise has drawn interest for people with chronically elevated inflammatory markers. For people with documented elevated high-sensitivity C-reactive protein (hs-CRP) on routine lipid screening, see our Inflammatory Markers page for the broader workup.
The magnitude of the cherry effect on chronic inflammatory markers in non-exercise contexts has been studied less extensively. Trials at rest have mostly been negative. In Lear and colleagues (2019), 4 weeks of tart cherry concentrate in 28 adults aged 40-60 left serum interleukin-6 and CRP unchanged. In Hillman and Chrismas (2021), 30 days of concentrate or freeze-dried capsules in 58 healthy adults did not change inflammation, by the authors' conclusion (markers measured: tumor necrosis factor-alpha, uric acid, CRP and erythrocyte sedimentation rate). The one positive is Schumacher (2013), in which high-sensitivity CRP fell during 6 weeks of tart cherry juice compared with placebo in people with knee osteoarthritis. One explanation offered is the underlying biology — the acute exercise stimulus produces a large inflammatory perturbation that the cherry intervention modulates, while chronic baseline inflammation is a smaller, slower target.
A 2026 meta-analysis of 19 trials in trained athletes (Daab and colleagues, Sports Medicine – Open) found that tart cherry juice sped the return of muscle strength (maximal voluntary contraction) and lowered CRP for up to 48 hours after muscle-damaging exercise, but found no pooled effect on muscle soreness, creatine kinase, interleukin-6 or tumor necrosis factor-alpha. Results varied widely between trials, and the certainty of the evidence ranged from very low to moderate.
Comparison: Tart Cherry vs Ibuprofen / Naproxen / Aspirin
The natural question in any "natural alternative to nonsteroidal anti-inflammatory drugs" discussion is whether the natural intervention is actually competitive with the pharmacologic option in terms of efficacy, safety, and convenience.
| Parameter | Tart Cherry | Ibuprofen / Naproxen |
|---|---|---|
| DOMS / post-exercise pain reduction | Reported in some randomized controlled trials (RCTs); no pooled effect on soreness in a 2026 meta-analysis of 19 trials | Moderate to large for acute pain; mixed for DOMS specifically |
| Onset of action | Hours, with loading days preferable | 30-60 minutes |
| Gastrointestinal bleeding risk | Negligible at dietary doses | Significant, dose-dependent; ~1%/year on chronic nonsteroidal anti-inflammatory drug |
| Renal effect in dehydrated athletes | None documented | Acute kidney injury risk; multiple case series in marathon runners |
| Cardiovascular risk | None documented (likely cardioprotective via antioxidant effect) | Elevated heart attack (myocardial infarction, MI) and stroke risk with chronic use (U.S. Food and Drug Administration (FDA) black box) |
| Anti-anabolic muscle effect | None documented | Reduced post-exercise muscle protein synthesis in one trial; mixed results on muscle growth over weeks of training (see next section) |
| Cost per effective dose | $0.50-1.00 (concentrate) or $0.30-0.60 (capsule) | $0.10-0.20 |
| Drug interactions | Minor (mild platelet effect; relevant with anticoagulants) | Many (anticoagulants, antiplatelet, angiotensin-converting enzyme (ACE) inhibitors, lithium, methotrexate) |
The bottom line: nonsteroidal anti-inflammatory drugs are faster-acting and cheaper for acute injury pain (a turned ankle, a tweaked back), where short-duration use carries acceptable risk. Tart cherry's case rests on regular post-exercise use, where cumulative nonsteroidal anti-inflammatory drug exposure adds up over months and years — and where the anti-adaptive muscle-recovery question (next section) arises. See also our Aspirin Side Effects page for the longer nonsteroidal anti-inflammatory drug-class safety discussion.
The Nonsteroidal Anti-Inflammatory Drug Anti-Adaptive Muscle-Recovery Problem
The most underappreciated reason that competitive and recreational athletes have been switching from prophylactic nonsteroidal anti-inflammatory drugs to tart cherry juice is the finding, in some trials, that nonsteroidal anti-inflammatory drug use around training blunts the muscle-adaptation signal that training is supposed to produce. In a 2002 single-session study by Trappe and colleagues, 24 young men did a hard eccentric knee-extensor workout; muscle protein synthesis rose 76% over the next 24 hours on placebo but did not rise significantly on the maximum over-the-counter doses of ibuprofen (1,200 mg/day) or acetaminophen (4,000 mg/day). That study measured one bout, not muscle growth over weeks of training. Lilja et al. (2018) ran an 8-week strength-training trial in adults aged 18-35: quadriceps muscle volume grew 3.7% on high-dose ibuprofen (1,200 mg/day) versus 7.5% on low-dose aspirin (acetylsalicylic acid, 75 mg/day). Strength gains were similar (11-20%) in the leg trained on conventional weight-stack equipment, and generally greater with aspirin in the leg trained on a flywheel machine.
The picture is mixed by age. In a 12-week training trial in adults in their 60s, Trappe and colleagues (2011, Ball State University) found the opposite: daily acetaminophen (4 g) or ibuprofen (1.2 g) was followed by more muscle growth than placebo (12.5% and 10.9% versus 8.6%) and larger strength gains. In the authors' words, these over-the-counter doses “do not inhibit and appear to enhance muscle hypertrophy and strength gains in older adults”.
The mechanism is the prostaglandin-mediated signaling that normally couples mechanical loading to muscle protein synthesis. Nonsteroidal anti-inflammatory drugs block cyclooxygenase-2-derived PGF2-alpha that activates p38 MAPK and downstream mechanistic target of rapamycin (mTOR) signaling in muscle satellite cells. Without PGF2-alpha, the muscle does not "know" it was loaded and does not initiate the adaptive hypertrophy program.
Whether tart cherry does the same thing to adaptation has not actually been tested, and this page previously implied otherwise. The trials usually offered in support do not carry a training-adaptation endpoint: Howatson (2010) followed marathon runners for 48 hours, Bowtell (2011) measured recovery from a single bout of strength exercise, and Levers (2015) likewise studied one acute bout. None of them ran a training block and measured hypertrophy or strength gain, so none of them can show that gains “continue normally” on cherry. No trial has.
There is a specific reason not to assume the answer is favourable. The concern with nonsteroidal anti-inflammatory drugs is that suppressing the post-exercise signal suppresses the adaptation it triggers, and the same logic has been demonstrated for antioxidant supplements: Paulsen et al. (2014), in a double-blind randomized trial in The Journal of Physiology, found that vitamin C and E supplementation hampered cellular adaptation to endurance training. Tart cherry is being taken for its antioxidant and anti-inflammatory activity, which is exactly the activity implicated. A 2020 Sports Medicine review of dietary supplements and endurance-training adaptation places polyphenol supplements squarely inside this open question.
The honest position: cherry's COX effect is milder than a therapeutic nonsteroidal anti-inflammatory drug dose, which is a reasonable basis for expecting less interference — but expecting is not knowing. For people whose goal is maximum adaptation from a training block, the cautious approach described by many sports dietitians for antioxidants applies to cherry too: taking it around competition and in-season congestion, when recovery speed is what matters, rather than continuously through a hypertrophy or base-building block. That is a judgement call made under uncertainty.
Loading, Maintenance, and Post-Event Protocols
In the trials, Howatson's runners drank the juice for 5 days before the race, on race day and for 48 hours after; Bowtell's athletes took the concentrate for 7 days before and 48 hours after exercise; Connolly's students drank the juice blend twice a day for 8 consecutive days. The schedules described in sports practice follow the same loading-and-maintenance pattern:
- Loading phase (4-7 days before target event) — 30 ml Montmorency tart cherry juice concentrate twice daily, or 480 mg freeze-dried capsule equivalent twice daily, or 8 oz ready-to-drink tart cherry juice twice daily. This is intended to build plasma anthocyanin levels and Nrf2-mediated antioxidant defense capacity
- Event day — the twice-daily dose continues, with one dose 1-2 hours before the event
- Recovery phase (48 hours post-event) — the twice-daily dose continues for 48 hours, as in the trials; 5-7 days is described for high-intensity events with substantial muscle damage
- Chronic maintenance (training season) — 30 ml concentrate once daily (typically with breakfast) is described for heavy training blocks; the trials at rest found no change in inflammatory markers (see below)
Applications described in sports practice (not tested as separate trials):
- Marathon and ultramarathon runners — loading 5-7 days before a race and continuing 48 hours after; Howatson's trial schedule was 5 days before, race day and 48 hours after
- Triathletes — a schedule similar to the marathon one, described particularly for Olympic-distance races spaced 7-14 days apart in racing season
- Strength athletes — chronic 30 ml/day during heavy training blocks; full 7-day loading around competition or tested one-repetition maximum (1RM) days
- High-intensity functional training — chronic 30 ml/day; full loading around competition
- Cyclists in stage races — continuous twice-daily dosing throughout the race period, with the aim of limiting cumulative inflammation across consecutive race days
- Football / rugby / contact sports — chronic 30 ml/day during season; particularly relevant given the broader concussion / brain-inflammation literature where antioxidant cherry effect may have value
- Recreational weekend warriors — a single 30 ml dose the evening before and morning of an unaccustomed exercise event (a hike, a basketball game, a ski day) is a simplified schedule some people use
Beyond Sports: Chronic Inflammatory Conditions
The anti-inflammatory mechanism that helps athletic recovery also has applications in chronic inflammatory disease management:
- Osteoarthritis — in Schumacher 2013, a crossover trial in 58 people with knee osteoarthritis, scores on the Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC) fell significantly during 6 weeks of tart cherry juice, but the improvement was not significantly greater than with placebo (P = 0.16); high-sensitivity CRP fell compared with placebo. See our Arthritis page for the broader management context.
- Inflammatory arthritis (rheumatoid arthritis, psoriatic arthritis) — tart cherry is an adjunct rather than primary therapy; the underlying autoimmune mechanism requires immunomodulatory drugs (methotrexate, biologics). Cherry is described as an add-on for symptomatic relief.
- Fibromyalgia — small open-label studies suggest improvement in pain and sleep quality (the latter via the melatonin route; see the Sleep deep-dive).
- Metabolic syndrome / chronic low-grade inflammation — modest high-sensitivity C-reactive protein and interleukin-6 reductions have been documented; cherry is one component of a broader anti-inflammatory diet
- Post-surgical recovery — emerging evidence (small trials) suggests that perioperative tart cherry supplementation may reduce postoperative pain scores and opioid requirements. Currently best considered exploratory.
- Chronic tendinopathy (Achilles, patellar, lateral epicondylitis) — the chronic-inflammatory component of tendinopathy is theoretically responsive to anti-inflammatory dietary intervention; evidence is largely mechanistic rather than clinical at this point
Cautions, Interactions, and Patient Selection
- Glycemic load — cherry juice concentrate contains substantial fructose. Freeze-dried capsule forms avoid most of that sugar. A continuous glucose monitor (CGM) shows an individual's own glucose response
- Anticoagulant interaction — the modest platelet-modulating effect of cherry anthocyanins may add to warfarin, apixaban, rivaroxaban, or dabigatran. For warfarin users, the international normalized ratio (INR) blood test is what would show such an effect; the magnitude is described as small
- Aspirin interaction — theoretical additive antiplatelet effect; clinically negligible at dietary doses. See our Aspirin page
- Athletes subject to anti-doping testing — tart cherry juice and freeze-dried cherry are not banned substances under WADA or NCAA rules. Contamination of sports supplements with unlabeled stimulants or anabolic agents is a recognised risk, and third-party testing programmes exist to screen products for it
- Iron supplementation — anthocyanins mildly bind (chelate) non-heme iron, which is why a 2-hour gap between the two is sometimes described
- Concurrent nonsteroidal anti-inflammatory drug use — no specific interaction is described for short-term combined use; when cherry is taken to reduce nonsteroidal anti-inflammatory drug exposure, continuing both indefinitely does not reduce that exposure
- Pregnancy and lactation — whole-food cherry is an ordinary food; there are no safety studies of supplement-form anti-inflammatory doses in pregnancy or breastfeeding
- Liver disease — no specific contraindication; cherry has been documented to be hepatoprotective in animal models of chemical liver injury, but no human hepatic dosing data exist
Key Research Papers
- Howatson G et al. (2010). Influence of tart cherry juice on indices of recovery following marathon running. Scandinavian Journal of Medicine & Science in Sports, 20(6):843-852. — PubMed PMID: 19883392
- Bowtell JL et al. (2011). Montmorency cherry juice reduces muscle damage caused by intensive strength exercise. Medicine & Science in Sports & Exercise, 43(8):1544-1551. — PubMed PMID: 21233776
- Connolly DA et al. (2006). Efficacy of a tart cherry juice blend in preventing the symptoms of muscle damage. British Journal of Sports Medicine, 40(8):679-683. — PubMed PMID: 16790484
- Wang H et al. (1999). Antioxidant and antiinflammatory activities of anthocyanins and their aglycon, cyanidin, from tart cherries. Journal of Natural Products 62(2):294-296. In vitro. — PubMed PMID: 10075763
- Levers K et al. (2015). Effects of powdered Montmorency tart cherry supplementation on an acute bout of intense lower body strength exercise in resistance trained males. Journal of the International Society of Sports Nutrition, 12:41. — PubMed PMID: 26578852
- Kuehl KS et al. (2010). Efficacy of tart cherry juice in reducing muscle pain during running: a randomized controlled trial. Journal of the International Society of Sports Nutrition, 7:17. — PubMed PMID: 20459662
- Schumacher HR et al. (2013). Randomized double-blind crossover study of the efficacy of a tart cherry juice blend in treatment of osteoarthritis (OA) of the knee. Osteoarthritis and Cartilage, 21(8):1035-1041. — PubMed PMID: 23727631
- Kuehl KS (2012). Cherry juice targets antioxidant potential and pain relief. Medicine and Sport Science 59:86-93. (A 2012 Kuehl osteoarthritis trial is often cited alongside this one; it appeared in a journal PubMed does not index and could not be verified, so it is not relied on here.) — PubMed PMID: 23075558
- Trappe TA et al. (2002). Effect of ibuprofen and acetaminophen on postexercise muscle protein synthesis. American Journal of Physiology — Endocrinology and Metabolism 282(3):E551-E556. — PubMed PMID: 11832356
- Trappe TA, Carroll CC, Dickinson JM, LeMoine JK, Haus JM, Sullivan BE, Lee JD, Jemiolo B, Weinheimer EM, Hollon CJ (2011). Influence of acetaminophen and ibuprofen on skeletal muscle adaptations to resistance exercise in older adults. American Journal of Physiology — Regulatory, Integrative and Comparative Physiology 300(3):R655-R662. — PubMed PMID: 21160058
- Lilja M et al. (2018). High doses of anti-inflammatory drugs compromise muscle strength and hypertrophic adaptations to resistance training in young adults. Acta Physiologica, 222(2). — PubMed PMID: 28834248
- Paulsen G, Cumming KT, Holden G, et al. (2014). Vitamin C and E supplementation hampers cellular adaptation to endurance training in humans: a double-blind, randomised, controlled trial. The Journal of Physiology 592(8):1887-1901. — PubMed PMID: 24492839
- Rothschild JA, Bishop DJ (2020). Effects of dietary supplements on adaptations to endurance training. Sports Medicine 50(1):25-53. — PubMed PMID: 31531769
- Hillman AR, Uhranowsky K (2021). Acute ingestion of Montmorency tart cherry reduces serum uric acid but has no impact on high-sensitivity C-reactive protein or oxidative capacity. Plant Foods for Human Nutrition 76(1):83-89. Human RCT — null on the inflammatory marker. — PubMed PMID: 33506357
- Hillman AR, Chrismas BCR (2021). Thirty days of Montmorency tart cherry supplementation has no effect on gut microbiome composition, inflammation, or glycemic control in healthy adults. Frontiers in Nutrition 8:733057. Human RCT — negative. — PubMed PMID: 34604282
- Lear R, O'Leary M, O'Brien Andersen L, et al. (2019). Tart cherry concentrate does not alter the gut microbiome, glycaemic control or systemic inflammation in a middle-aged population. Nutrients 11(5):1063. Human RCT — negative. — PubMed PMID: 31085979
- Bell PG, Walshe IH, Davison GW, Stevenson EJ, Howatson G (2015). Recovery facilitation with Montmorency cherries following high-intensity, metabolically challenging exercise. Applied Physiology, Nutrition, and Metabolism 40(4):414-423. — PubMed PMID: 25794236
- Daab W, Bouzid MA, Nassis GP, Arumugam A, Ammar A, Pojskić H, Abaïdia AE (2026). Effects of tart cherry juice supplementation on recovery from exercise-induced muscle damage in athletes: a systematic review and meta-analysis. Sports Medicine – Open 12(1):40. — PubMed PMID: 41945263
PubMed Topic Searches
Connections
- All Herbs
- Tart Cherry Overview
- Tart Cherry Benefits Hub
- Tart Cherry for Sleep & Melatonin
- Tart Cherry for Antioxidant & Brain Health
- Tart Cherry for Uric Acid & Gout
- Arthritis
- Joint Pain
- Fibromyalgia
- Inflammatory Markers (C-Reactive Protein, Interleukin-6)
- Anti-Inflammatory Diet
- Aspirin Side Effects (Nonsteroidal Anti-Inflammatory Drug Risks)
- Turmeric / Curcumin
- Willow Bark
- Quercetin
- History