⚠ Evidence warning: Clinical trials or other evidence do not support the claims that manuka honey clears acne, reduces surgical scars, eases rosacea and psoriasis, and spares steroids in eczema. This page keeps it as a report of what people, websites or other media say.
Manuka Honey for Skin Conditions and Acne
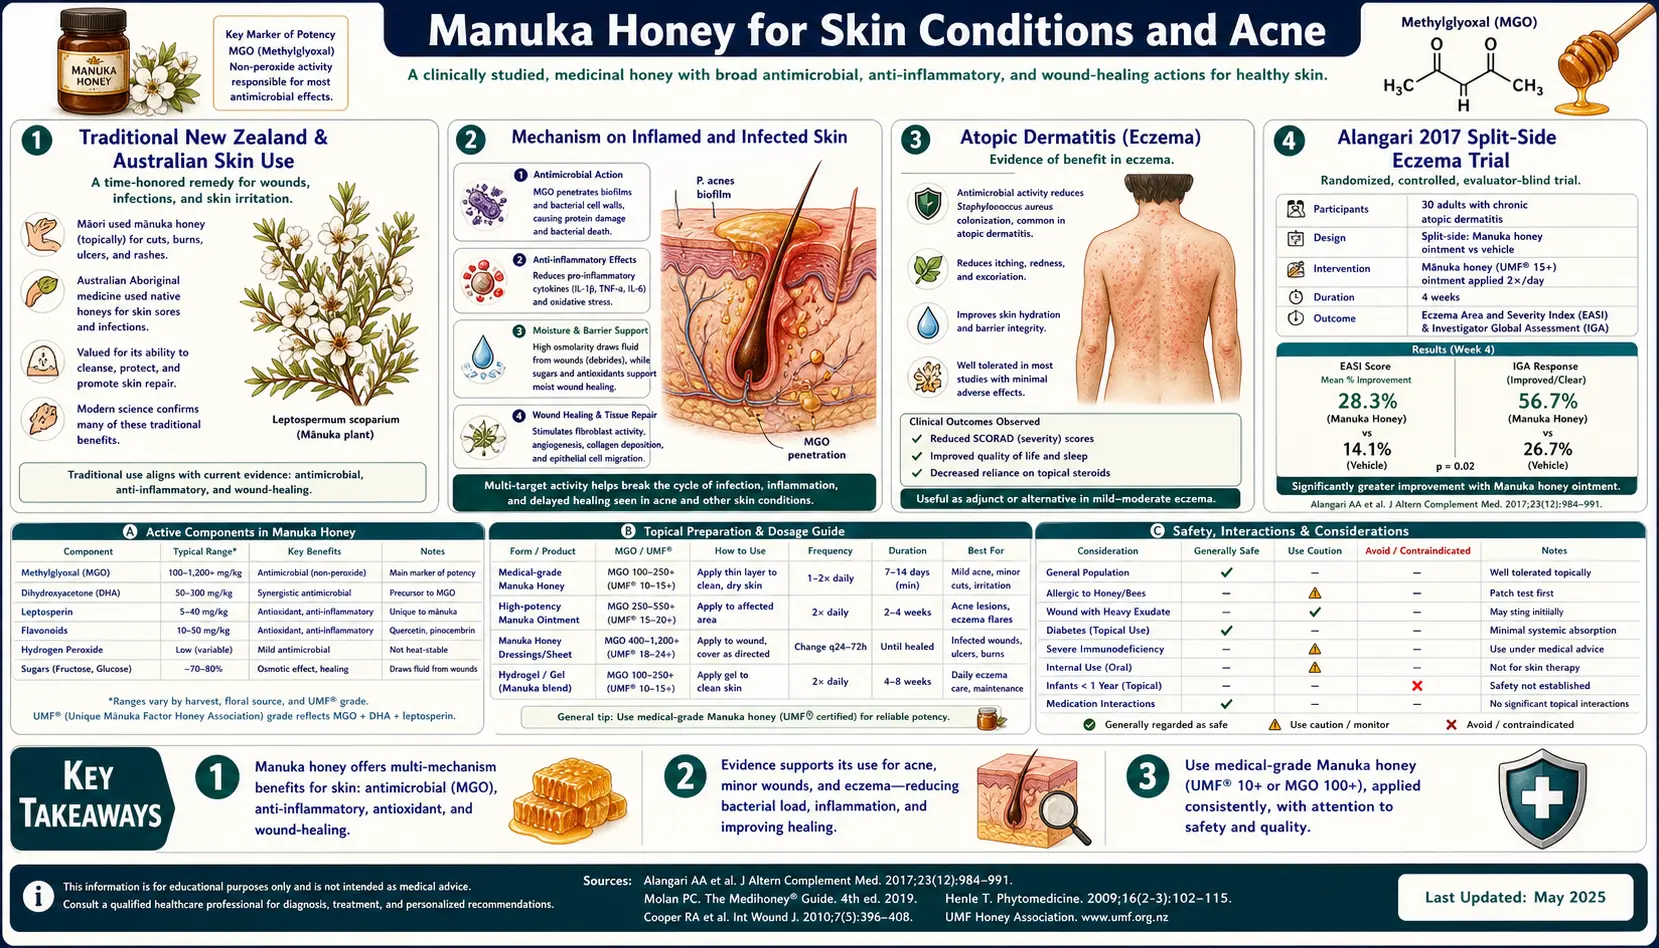
Beyond formal wound-care indications, manuka honey is used topically for inflammatory and infectious skin conditions. A 2017 open-label pilot study (Alangari) reported improvement on a lesion score in atopic dermatitis with manuka honey applied overnight under gauze. Topical manuka has been investigated for acne vulgaris as adjunctive antibacterial-and-anti-inflammatory therapy targeting Cutibacterium acnes. Practitioners apply it to post-surgical scars to limit hypertrophic scar formation and pigmentation, though two randomized trials of manuka found no difference on scar scales. Traditional New Zealand and Australian use of the manuka plant for skin complaints predates European contact; honey use came after European honeybees reached New Zealand in 1839. Practitioners describe the combined antibacterial-osmotic-low-pH-anti-inflammatory mechanism as making manuka honey one of the most versatile non-prescription topical agents for inflammatory dermatology. This deep-dive walks through atopic dermatitis trials, acne applications, surgical scar treatment, rosacea, traditional use, application techniques, and the practical limitations.
Table of Contents
- Traditional New Zealand & Australian Skin Use
- Mechanism on Inflamed and Infected Skin
- Atopic Dermatitis (Eczema)
- Alangari 2017 — Split-Side Eczema Pilot Study
- Acne Vulgaris
- Post-Surgical Scar Treatment
- Rosacea and Inflammatory Facial Conditions
- Herpes Simplex (Cold Sores)
- Psoriasis — Limited Evidence
- Application Practices (Overnight Occlusive vs Rinse-Off)
- Cautions and Limitations
- Key Research Papers
- Connections
- Featured Videos
Traditional New Zealand & Australian Skin Use
The Māori traditional pharmacopeia included mānuka (Leptospermum scoparium) for a range of skin and wound conditions. The leaves were boiled to produce decoctions used as wound washes and as compresses for inflamed skin. The bark was used for skin sores and as an antiseptic for wounds. The seeds and seed capsules were chewed and applied topically for boils. These pre-honey applications of the plant itself were focused on the volatile-oil and tannin content of Leptospermum, distinct from the methylglyoxal (MGO) mechanism that emerged later with honey production.
The closely related Australian tea-tree species (Melaleuca alternifolia) and the broader Leptospermum genus (including manuka in Australia) have a parallel Aboriginal Australian medicinal tradition, also focused on volatile-oil-rich topical applications for skin complaints. The shared family of antimicrobial volatile oils across these related Australasian myrtaceous species made them the regional first-line topical antiseptics for centuries.
The transition from plant decoctions and topical leaf applications to honey-based applications followed the introduction of European honeybees to New Zealand in 1839. By the late 19th century, both indigenous Māori healers and European settlers were using manuka honey topically for the same skin and wound applications previously addressed by leaf and bark preparations. The traditional knowledge essentially identified the right plant for these applications a century before the methylglyoxal mechanism was characterized.
Mechanism on Inflamed and Infected Skin
Manuka honey's proposed topical action on inflamed skin combines several mechanisms. Most of this list comes from laboratory work and from wound care, not from measurements on inflamed human skin:
- Antibacterial action against skin commensals and pathogens — including Staphylococcus aureus (the dominant skin colonizer in atopic dermatitis), Cutibacterium acnes (the bacterium implicated in acne), and the common pyogenic skin pathogens (Streptococcus pyogenes, methicillin-resistant Staphylococcus aureus (MRSA)). The MGO mechanism is the same as in wound applications, applied to intact or barrier-disrupted skin.
- Effects on inflammatory signals — honey contains polyphenols and flavonoids proposed to act against inflammation, but laboratory results go both ways and no skin study was found. Manuka, pasture and jelly bush honey all raised release of tumor necrosis factor-alpha, interleukin-1 beta (IL-1beta) and interleukin-6 (IL-6) from monocytes (Tonks 2003), and a dermatology review lists “the induction of cytokines” among honey's actions (Burlando 2013). In other cell work, manuka lowered interleukin-4-induced CCL26 release from cultured skin cells and reduced mast cell degranulation (Alangari 2017), whose authors note honey may act pro-inflammatory in the absence of active inflammation.
- Osmotic action on edematous skin — honey draws water out of edematous tissue, reducing swelling. This is the same mechanism that reduces wound edema; in inflammatory skin conditions, it reduces the dependent pitting edema of severe eczema flares and the diffuse facial swelling of acute rosacea.
- Barrier repair support — honey at applied concentration maintains a moist wound-healing environment that supports re-epithelialization. For barrier-disrupted skin (eczema, acne lesions, surgical incisions), this accelerates restoration of normal stratum corneum function. The natural emollient effect of honey's viscous coating is additive.
- Low pH effect — healthy skin has a slightly acidic surface pH (4.5-5.5) maintained by the "acid mantle" of sweat and sebum acids. Inflammatory and infected skin frequently has elevated pH (6.0-7.0) that supports pathogen colonization. Honey's pH (3.2-4.5) restores acidic surface conditions that disfavor pathogen growth.
- Pigmentation modulation — topical honey appears to reduce post-inflammatory hyperpigmentation, possibly through reduced melanocyte stimulation by the lower inflammatory cytokine environment, or through direct effects on melanocyte tyrosinase activity. This is relevant for darker skin types where post-inflammatory hyperpigmentation often becomes the lasting cosmetic concern after acne or eczema resolves.
The combined mechanism is the reason practitioners give for using manuka honey across such a wide range of skin conditions — it is not a specific antibiotic targeting one pathogen, nor a specific anti-inflammatory targeting one cytokine, but a multi-action topical agent that addresses several of the dysfunctional pathways in inflammatory skin disease simultaneously.
Atopic Dermatitis (Eczema)
Atopic dermatitis (AD, eczema) affects approximately 10-20% of children and 2-10% of adults globally. The disease is characterized by impaired skin barrier function (genetic and acquired), type 2 helper T cell (Th2)-skewed adaptive immunity (elevated interleukins IL-4, IL-13 and IL-31), and abnormal skin microbiome dominated by Staphylococcus aureus. S. aureus colonizes the skin of 70-90% of people with AD against about 5% of the normal population, by the Alangari paper's account; a pooling of 26 studies in children found 55.0% on eczematous skin (38.3-71.7) and 23.3% on non-lesional skin. It produces toxins (superantigens, alpha-toxin) that exacerbate the inflammatory cascade. Approaches used against S. aureus colonization include dilute bleach baths, mupirocin, and topical antiseptics, but a 2019 Cochrane review of 41 studies states: “There is no standard intervention to reduce S. aureus burden in eczema.” It found “insufficient evidence on the effects of anti-staphylococcal treatments,” and reports that bleach baths may make no difference compared with placebo.
Manuka honey's proposed antibacterial (S. aureus) and anti-inflammatory actions make it a mechanistically attractive intervention for AD. The Alangari et al. (2017) split-side pilot study (discussed in detail below) reported improvement on a lesion score with topical manuka in adults with AD.
A small randomized trial points the other way, for a different honey. Fingleton and colleagues (2014) treated matched lesions in 15 adults with kanuka honey on one side and aqueous cream on the other, nightly for 2 weeks. A blinded assessor found no difference in lesion score (-0.1, 95% confidence interval -1.5 to 1.4), and itch scores were similar. One participant reported more itch with honey.
Practitioner practice for AD, with no trial behind this schedule: clean medical-grade manuka honey (10+ to 18+ on a manuka grading scale for antibacterial activity) applied as a thin film to lesional skin overnight under occlusive wet-wrap dressing, followed by a morning rinse with lukewarm water and no soap, which practitioners say strips the natural skin barrier. It is repeated nightly for 7-14 days, then 2-3 times per week for maintenance. Practitioners say the wet-wrap occlusion maintains the honey-skin contact and amplifies the penetration of MGO and polyphenols into the epidermis. The one manuka study used gauze and tape for 7 nights.
For severe or recalcitrant AD, manuka honey is an adjunct to standard care (topical corticosteroids, calcineurin inhibitors, dupilumab) rather than a replacement. Practitioners make their strongest case for manuka in AD as a steroid-sparing maintenance therapy for people who cycle between flares and corticosteroid courses, to reduce cumulative steroid exposure; no manuka trial has tested this.
See our Eczema page for the broader management approach.
Alangari 2017 — Split-Side Eczema Pilot Study
Alangari et al. (2017) in Immunity, Inflammation and Disease conducted a proof-of-concept, open-label pilot study of topical manuka honey in adults with bilateral atopic dermatitis lesions. It was not randomized: where the two sides differed, the slightly more severe site received the honey, covered with gauze and tape overnight for 7 nights, and the other site was left untreated, with moisturizers allowed on both. Sixteen people were recruited, two withdrew within two days for worsening symptoms, and 14 completed it. The measure was the Three Item Severity score (0-9). Results:
- Honey site: -2 points (95% confidence interval -2.75 to -1.25), p<0.001, before against after
- Control site: -0.7 points (-1.71 to 0.28), p=0.15; two people used a steroid on the control site for intolerable symptoms
- No significant change in skin staphylococci by day 7, with or without honey
- In cultured cells, not in the patients: honey lowered interleukin-4-induced CCL26 from HaCaT keratinocytes and reduced mast cell degranulation
The split-side comparison limits differences between people, but the study was small, unblinded and not randomized. Its authors note that the score is validated yet not the gold standard for AD, and that the results need “randomized and controlled clinical trials.” What is not known: whether the effect holds under blinding, and how long it lasts. A one-year telephone follow-up gave only anecdotes: three people reported overall improvement without using honey.
An earlier, partly controlled study (Al-Waili 2003) tested a mixture of honey, beeswax and olive oil, not manuka: 8 of 10 people with dermatitis showed significant improvement after 2 weeks.
Acne Vulgaris
Acne vulgaris affects approximately 85% of adolescents and an estimated 50% of adults at some point in life. The pathogenesis is multifactorial: excess sebum production from sebaceous glands under androgen stimulation, follicular hyperkeratosis blocking the follicular opening, colonization by Cutibacterium acnes (formerly Propionibacterium acnes) in the obstructed follicle, and resulting inflammation that produces the visible papules, pustules, and nodules.
Topical manuka honey is proposed to address two of these mechanisms: the C. acnes colonization (antibacterial action of MGO) and the inflammation (anti-inflammatory polyphenols and cytokine reduction). It does not directly address sebum production or follicular keratinization — for those, conventional acne therapies (topical retinoids, isotretinoin, hormonal therapy in women) remain the established interventions.
The case made for manuka honey in acne is therefore as an adjunctive antibacterial-and-anti-inflammatory agent. No acne trial of manuka was found. The one controlled honey trial in acne was negative: in 136 people aged 16-40, adding 90% kanuka honey to antibacterial soap for 12 weeks gave a 2-point improvement in 4 of 53 against 1 of 53 with soap alone (p=0.17). In the laboratory, honey stopped acne bacteria at a 50% concentration (Julianti 2017). Practices people and practitioners describe:
- Spot treatment — small dab of grade 15+ manuka honey applied to individual papules and pustules at bedtime, left overnight. Users describe less redness and smaller pustules by morning; no study has measured this.
- Face mask — thin film of grade 10+ to 15+ manuka honey applied to the entire affected area for 20-30 minutes, then rinsed off with lukewarm water. Done 2-3 times per week. Described for moderate diffuse inflammatory acne.
- Combination with topical retinoid — manuka honey at bedtime, topical retinoid (tretinoin, adapalene) in the morning. Described as a complementary mechanism without skin-irritation interaction, and as steroid-free, antibiotic-sparing inflammatory control.
The advantage practitioners claim for manuka over conventional topical antibiotics (clindamycin gel, erythromycin gel) concerns resistance — topical antibiotic resistance in C. acnes has reached approximately 50% globally and is reducing the effectiveness of long-term topical antibiotic acne therapy. Laboratory work on honey resistance is mixed, and none tested C. acnes or long-term skin use. Cooper 2010 found reduced susceptibility during stepwise training that was not permanent, with no resistant mutants, and judged the risk low “if high concentrations are maintained clinically.” Bischofberger 2021 found small honey resistance in E. coli (at most twofold) for 2 of 4 honey products, through mutations in genes that detoxify methylglyoxal. Mokhtar 2020 found that repeated low-dose exposure to a manuka wound gel changed antibiotic sensitivity and raised virulence in 4 of 8 bacteria.
The limitation of manuka honey in acne is that it does not address the follicular hyperkeratinization that drives comedone (whitehead/blackhead) formation. For comedonal-predominant acne, topical retinoids remain superior. For inflammatory-predominant (papulopustular) acne, practitioners describe manuka honey as a monotherapy or adjunct.
See our Acne page for the broader management context.
Post-Surgical Scar Treatment
Post-surgical and post-traumatic scars vary enormously in cosmetic outcome based on healing dynamics. The key determinants are: tension across the wound (high tension → widened scars and stretch marks), inflammation during healing (excess inflammation → hypertrophic scarring and keloid formation), pigmentation (post-inflammatory hyperpigmentation in darker skin types), and time (scars naturally remodel for 6-12 months post-injury). Conventional scar-prevention modalities include silicone sheeting, pressure dressings, topical onion-extract gels, corticosteroid injections (for keloids), and laser therapy.
Manuka honey has been used as a topical scar-prevention agent following its widespread acceptance in primary wound care. The proposed mechanism for scar benefit overlaps with the anti-inflammatory and barrier-repair actions:
- Reduced inflammation during the proliferative healing phase → less hypertrophic collagen deposition
- Antibacterial action preventing subclinical wound contamination → cleaner healing trajectory
- Maintained moist healing environment → faster re-epithelialization, less scar tissue formation
- Possible reduction in post-inflammatory hyperpigmentation through lower inflammatory cytokine environment
Practitioners describe applying medical-grade manuka honey to closed incisions, including after cesarean section, thyroidectomy and abdominal surgery, to limit scar thickening. Randomized trials of manuka itself found no scar benefit on validated scales. In eyelid surgery (55 randomized, 46 analysed), scar scales showed no difference at 4 months, though patients reported less scar pain on the honey side (0.48 against 1.9, p=0.005). After thyroidectomy (21 completed), there was no difference at 8 weeks. No manuka study of cesarean scars was found; a 2024 meta-analysis of honey of any type on obstetric wounds (5 trials, 353 women) found no difference in final wound healing (mean difference -0.34, 95% confidence interval -1.13 to 0.44) and less pain.
Practitioner routine, with no trial behind it: starting at 2-3 weeks post-op (after sutures are removed and the wound has fully closed), a thin film of grade 12+ manuka honey on the scar twice daily, covered with a thin silicone sheet or breathable bandage, for 4-12 weeks. For established hypertrophic scars or keloids, manuka honey is less effective and conventional intervention (intralesional corticosteroid, cryotherapy, surgical revision) may be required.
Rosacea and Inflammatory Facial Conditions
Rosacea is a chronic inflammatory facial dermatosis characterized by central facial erythema, telangiectasia, papules, pustules, and (in some patients) phymatous changes. The pathophysiology involves cathelicidin LL-37 dysregulation, kallikrein-5 hyperactivity, neurovascular dysregulation, and altered skin microbiome including Demodex folliculorum overgrowth. Conventional treatment includes topical metronidazole, ivermectin, azelaic acid, brimonidine, and oral doxycycline.
Topical manuka honey for rosacea has limited formal trial evidence but a growing case-report and patient-reported literature. The mechanism would be the anti-inflammatory and antibacterial action, potentially reducing the bacterial component of inflammatory papulopustular rosacea. The osmotic action could reduce facial edema in erythematotelangiectatic rosacea, though this effect is short-lived.
The closest trial is of a different honey. In 138 adults, 90% kanuka honey with glycerine was tested against a control cream for 8 weeks: 24 of 68 improved by 2 points or more on a severity score, against 12 of 69 (relative risk 2.03, 95% confidence interval 1.11-3.72). Manuka was not tested.
Practitioner routine: grade 12+ manuka honey applied as a thin film to affected facial areas at bedtime, left overnight, gently rinsed off in the morning, 3-4 nights per week at first and less often if irritation develops, alongside conventional rosacea therapy and not in place of it.
Limitations: rosacea is highly variable in response to topical therapies in general, and what helps one patient frequently does nothing for another. Practitioners describe manuka honey for mild-to-moderate papulopustular rosacea; for moderate-to-severe disease the concern is delay of conventional therapy.
Herpes Simplex (Cold Sores)
The strongest evidence for honey in herpes simplex labialis (cold sores, herpes simplex virus type 1 (HSV-1) facial recurrences) comes from kanuka honey rather than manuka. Kanuka (Kunzea ericoides) is a closely related New Zealand myrtaceous species producing honey with distinct chemical profile — lacking the high MGO of manuka but containing other antimicrobial compounds including arabinogalactan proteins.
Semprini et al. (2019) in BMJ Open conducted a head-to-head randomized controlled trial (RCT) of a 90% kanuka honey cream versus topical aciclovir (acyclovir cream) in 952 people aged 16 and over with herpes labialis, both applied five times daily. Results:
- Median time to normal skin: aciclovir 8 days (8 to 9), kanuka 9 days (8 to 9); hazard ratio 1.06 (0.92 to 1.22), p=0.56
- Maximal pain: median 3 in both groups
- No statistically significant differences on any secondary outcome, including time to pain resolution and acceptability
- Nine people withdrew for adverse events (three aciclovir, six honey)
- No related serious adverse events
The authors found “no evidence of a difference in efficacy.” It was an open-label superiority trial with no non-inferiority margin set for formal testing, though the authors consider the intervals consistent with non-inferiority, and it was funded by the honey's maker. An early pilot explains why it was run: in 16 adults, honey had beaten acyclovir on healing time (Al-Waili 2004), a result not reproduced in 952 people. Manuka honey has not been formally tested at this scale for HSV-1, but smaller in-vitro studies suggest similar antiviral activity. The trial result applies to the kanuka cream, not to manuka.
Practitioner routine: a dab of grade 12+ manuka honey (or kanuka honey product) applied to the prodromal tingle as soon as symptoms begin, reapplied every 2-3 hours during waking hours for the first 3-4 days, and as desired during scab formation and resolution. Worsening redness, purulent discharge or an expanding lesion are signs of bacterial superinfection.
Psoriasis — Limited Evidence
Psoriasis is mechanistically distinct from atopic dermatitis — it is a T helper 17 and 22 (Th17/Th22)-driven hyperproliferative dermatosis rather than the Th2-driven barrier-impairment disease of AD. The role of skin microbiome (and therefore antibacterial therapy) in psoriasis is less established. Conventional first-line therapy is topical corticosteroids and Vitamin D analogs (calcipotriol); moderate-to-severe disease is treated with phototherapy or biologics targeting IL-17 (secukinumab, ixekizumab) or IL-23 (guselkumab, risankizumab).
Topical manuka honey for psoriasis has minimal formal trial evidence. Small case reports describe modest benefit for plaque psoriasis with overnight occlusive application, but no controlled trial of manuka was found. Trials of other honey exist: Fingleton 2014 randomized matched lesions in 15 adults to kanuka honey or aqueous cream, with no significant difference after two weeks, and in Al-Waili 2003, 5 of 8 people responded to a honey, beeswax and olive oil mixture. The mechanistic argument is weaker than for atopic dermatitis because the bacterial colonization that manuka would address is not a primary pathogenic driver in psoriasis the way S. aureus is in AD.
For inverse psoriasis (intertriginous areas with secondary bacterial or candidal colonization), the antibacterial and antifungal activity of manuka may be more relevant. Small open-label experiences suggest benefit, but conventional therapy (low-potency topical steroid plus topical antifungal) remains first-line.
For scalp psoriasis with overlying seborrheic dermatitis, manuka honey shampoo or dilute (50% honey + 50% water) leave-in treatment for 30 minutes prior to rinsing has been described, though again without rigorous trial data. The study found on the scalp used a different routine and a different condition: 90% crude honey, not manuka, for 3 hours every other day in 30 people with seborrheic dermatitis, without a control group during treatment (Al-Waili 2001).
Application Practices (Overnight Occlusive vs Rinse-Off)
These are practitioner routines, not trial-tested schedules. The choice between overnight occlusive application versus shorter rinse-off application depends on the condition and the practical tolerability:
- Overnight occlusive (8-12 hour contact) — described as giving maximum penetration of MGO and polyphenols into the epidermis. Used for severe inflammatory conditions (severe atopic dermatitis flare, large or deep wound, post-surgical scar prevention). Practical issues: messy bedding, requires occlusive wrap or older clothing, may be unsuitable for facial conditions where moisture pooling can cause maceration.
- Several-hour mask (2-4 hours) — intermediate contact time. Used for facial applications where overnight occlusion is impractical. Honey is applied, covered with cling film or moist towel for the duration, then rinsed off with lukewarm water, 3-4 times per week.
- Short mask (20-30 minutes, rinse off) — for routine facial use as cosmetic-acne mask. Less penetration but cosmetically acceptable for daily or alternate-day use. Described for mild inflammatory conditions and as adjunct to other therapy.
- Spot treatment (apply, leave indefinitely, reapply as needed) — for small lesions (single papules, cold sores, small wounds, focal eczema patches). Provides continuous contact without the practical limitations of larger-area occlusion.
- Cleansing wash — diluted manuka honey (1:1 with warm water) is used as a gentle face wash, massaged onto wet skin for 30-60 seconds and rinsed. Described as mild antibacterial action and gentle cleansing without disrupting the skin barrier the way detergent-based cleansers do.
Practical notes from the same practice: rinsing is with lukewarm (not hot, not cold) water — hot water is said to dissolve honey too aggressively and remove it before therapeutic contact is complete; cold water doesn't dissolve well and leaves sticky residue. Soap or detergent face wash straight after honey treatment is said to strip the residual honey film and the natural skin barrier together. A gentle splash of lukewarm water is described as sufficient.
Cautions and Limitations
- Infant botulism — absolute contraindication for infants under 12 months. Raw honey of any kind, including manuka, is treated as off limits on broken skin of infants under 1 year due to risk of Clostridium botulinum spore exposure. The risk is greatest from oral ingestion but applies in principle to wound applications too. Over 12 months this particular concern no longer applies.
- Honey allergy / bee allergy — rare but documented. Practitioners patch test on a small skin area before extensive application in people with known bee venom allergy, severe pollen allergies, or unexplained urticaria. Contact dermatitis to honey itself is uncommon but possible.
- Stinging — common in the first 5-10 minutes of application, particularly on inflamed or wounded skin. Usually subsides spontaneously. Severe or persistent stinging suggests intolerance.
- Sticky residue — the practical limitation of honey use on facial skin. Many patients find the residual stickiness uncomfortable and abandon treatment. Wet-wrap or covered application reduces this; rinse-off application is more tolerable for daily facial use.
- Pillow staining — honey will stain bedding amber. Use older pillowcases for overnight facial honey treatments, or sleep on a towel.
- Discoloration of skin — honey will temporarily stain skin amber-yellow. This is cosmetic and resolves with rinsing.
- Counterfeit product — as with other applications, graded or independently MGO-assayed products state their strength. Buyers and practitioners report that low-priced "manuka" honey is often counterfeit or low-MGO.
- Not a substitute for established therapy — for moderate-to-severe atopic dermatitis, manuka is an adjunct to topical corticosteroids, calcineurin inhibitors, or dupilumab. For moderate-to-severe acne, manuka is an adjunct to topical retinoids and/or systemic isotretinoin or hormonal therapy. For rosacea, manuka is an adjunct to topical metronidazole/ivermectin/azelaic acid. For psoriasis, manuka is rarely a primary or even adjunctive choice. The concern with honey alone in moderate-to-severe disease is delay of conventional therapy.
- Dental caries — not directly relevant for skin applications, but a consideration for patients who also use manuka honey orally for throat or H. pylori indications — rinsing the mouth after oral use reduces dental exposure.
Key Research Papers
- Alangari AA, Morris K, Lwaleed BA, Lau L, Jones K, Cooper R, Jenkins R (2017). Honey is potentially effective in the treatment of atopic dermatitis: clinical and mechanistic studies. Immun Inflamm Dis, 5(2): 190-199. — PubMed PMID: 28474502
- Semprini A et al. (2019). Kanuka honey versus aciclovir for the topical treatment of herpes simplex labialis: a randomised controlled trial. BMJ Open, 9(5): e026201. — PubMed PMID: 31092654
- Al-Waili NS (2003). Topical application of natural honey, beeswax and olive oil mixture for atopic dermatitis or psoriasis: partially controlled, single-blinded study. Complement Ther Med, 11(4): 226-34. — PubMed PMID: 15022655
- Burlando B, Cornara L (2013). Honey in dermatology and skin care: a review. J Cosmet Dermatol, 12(4): 306-13. — PubMed PMID: 24305429
- McLoone P, Warnock M, Fyfe L (2016). Honey: a realistic antimicrobial for disorders of the skin. J Microbiol Immunol Infect, 49(2): 161-7. — PubMed PMID: 25732699
- Maddocks SE, Lopez MS, Rowlands RS, Cooper RA (2012). Manuka honey inhibits the development of Streptococcus pyogenes biofilms and causes reduced expression of two fibronectin binding proteins. Microbiology, 158(Pt 3): 781-790. — PubMed PMID: 22294681
- Sindi A et al. (2019). Anti-biofilm effects and characterisation of the hydrogen peroxide activity of a range of Western Australian honeys compared to Manuka and multifloral honeys. Sci Rep. — PubMed PMID: 31776432
- Eteraf-Oskouei T, Najafi M (2013). Traditional and modern uses of natural honey in human diseases: a review. Iran J Basic Med Sci, 16(6): 731-42. — PubMed PMID: 23997898
- Israili ZH (2014). Antimicrobial properties of honey. Am J Ther, 21(4): 304-23. — PubMed PMID: 23782759
- Julianti E, Rajah KK, Fidrianny I (2017). Antibacterial activity of ethanolic extract of cinnamon bark, honey, and their combination effects against acne-causing bacteria. Sci Pharm, 85(2): 19. — PubMed PMID: 28398231
- Visavadia BG, Honeysett J, Danford MH (2008). Manuka honey dressing: an effective treatment for chronic wound infections. Br J Oral Maxillofac Surg, 46(1): 55-6. — PubMed PMID: 17113690
- Saikaly SK, Khachemoune A (2017). Honey and wound healing: an update. Am J Clin Dermatol, 18(2): 237-251. — PubMed PMID: 28063093
- Braithwaite I, Hunt A, Riley J, et al. (2015). Randomised controlled trial of topical kanuka honey for the treatment of rosacea. BMJ Open, 5(6): e007651. — PubMed PMID: 26109117
- Semprini A, Braithwaite I, Corin A, et al. (2016). Randomised controlled trial of topical kanuka honey for the treatment of acne. BMJ Open, 6(2): e009448. — PubMed PMID: 26832428
- Fingleton J, Helm C, Tofield C, Weatherall M, Beasley R (2014). A randomised controlled trial of topical Kanuka honey for the treatment of eczema. JRSM Open, 5(1): 2042533313509263. — PubMed PMID: 25057363
- Fingleton J, Sheahan D, Corin A, Weatherall M, Beasley R (2014). A randomised controlled trial of topical Kanuka honey for the treatment of psoriasis. JRSM Open, 5(3): 2042533313518913. — PubMed PMID: 25057377
- Malhotra R, Ziahosseini K, Poitelea C, Litwin A, Sagili S (2017). Effect of Manuka honey on eyelid wound healing: a randomized controlled trial. Ophthalmic Plast Reconstr Surg, 33(4): 268-272. — PubMed PMID: 27429228
- Thamboo A, Mulholland G, Matthews K, Ayoub N, Anderson D (2016). Objective and subjective scar aesthetics with topical Manuka honey post-thyroidectomy: a randomized control study. World J Otorhinolaryngol Head Neck Surg, 2(4): 203-207. — PubMed PMID: 29204567
- Ferraz Barbosa B, de Moraes FCA, Araujo Alves da Silva B, et al. (2024). The use of honey for cicatrization and pain control of obstetric wounds: a systematic review and meta-analysis of randomized controlled trials. Nutrients, 16(2). — PubMed PMID: 38257078
- Cooper RA, Jenkins L, Henriques AF, Duggan RS, Burton NF (2010). Absence of bacterial resistance to medical-grade manuka honey. Eur J Clin Microbiol Infect Dis, 29(10): 1237-41. — PubMed PMID: 20549529
- Bischofberger AM, Pfrunder Cardozo KR, Baumgartner M, Hall AR (2021). Evolution of honey resistance in experimental populations of bacteria depends on the type of honey and has no major side effects for antibiotic susceptibility. Evol Appl, 14(5): 1314-1327. — PubMed PMID: 34025770
- Mokhtar JA, McBain AJ, Ledder RG, Binsuwaidan R, Rimmer V, Humphreys GJ (2020). Exposure to a manuka honey wound gel is associated with changes in bacterial virulence and antimicrobial susceptibility. Front Microbiol, 11: 2036. — PubMed PMID: 32973735
- Tonks AJ, Cooper RA, Jones KP, Blair S, Parton J, Tonks A (2003). Honey stimulates inflammatory cytokine production from monocytes. Cytokine, 21(5): 242-7. — PubMed PMID: 12824009
- Sangaphunchai P, Kritsanaviparkporn C, Treesirichod A (2023). Association between Staphylococcus aureus colonization and pediatric atopic dermatitis: a systematic review and meta-analysis. Indian J Dermatol, 68(6): 619-627. — PubMed PMID: 38371569
- George SM, Karanovic S, Harrison DA, et al. (2019). Interventions to reduce Staphylococcus aureus in the management of eczema. Cochrane Database Syst Rev, 2019(10). — PubMed PMID: 31684694
- Al-Waili NS (2001). Therapeutic and prophylactic effects of crude honey on chronic seborrheic dermatitis and dandruff. Eur J Med Res, 6(7): 306-8. — PubMed PMID: 11485891
- Al-Waili NS (2004). Topical honey application vs. acyclovir for the treatment of recurrent herpes simplex lesions. Med Sci Monit, 10(8): MT94-8. — PubMed PMID: 15278008