Manuka Honey for Digestive Health and Sore Throat
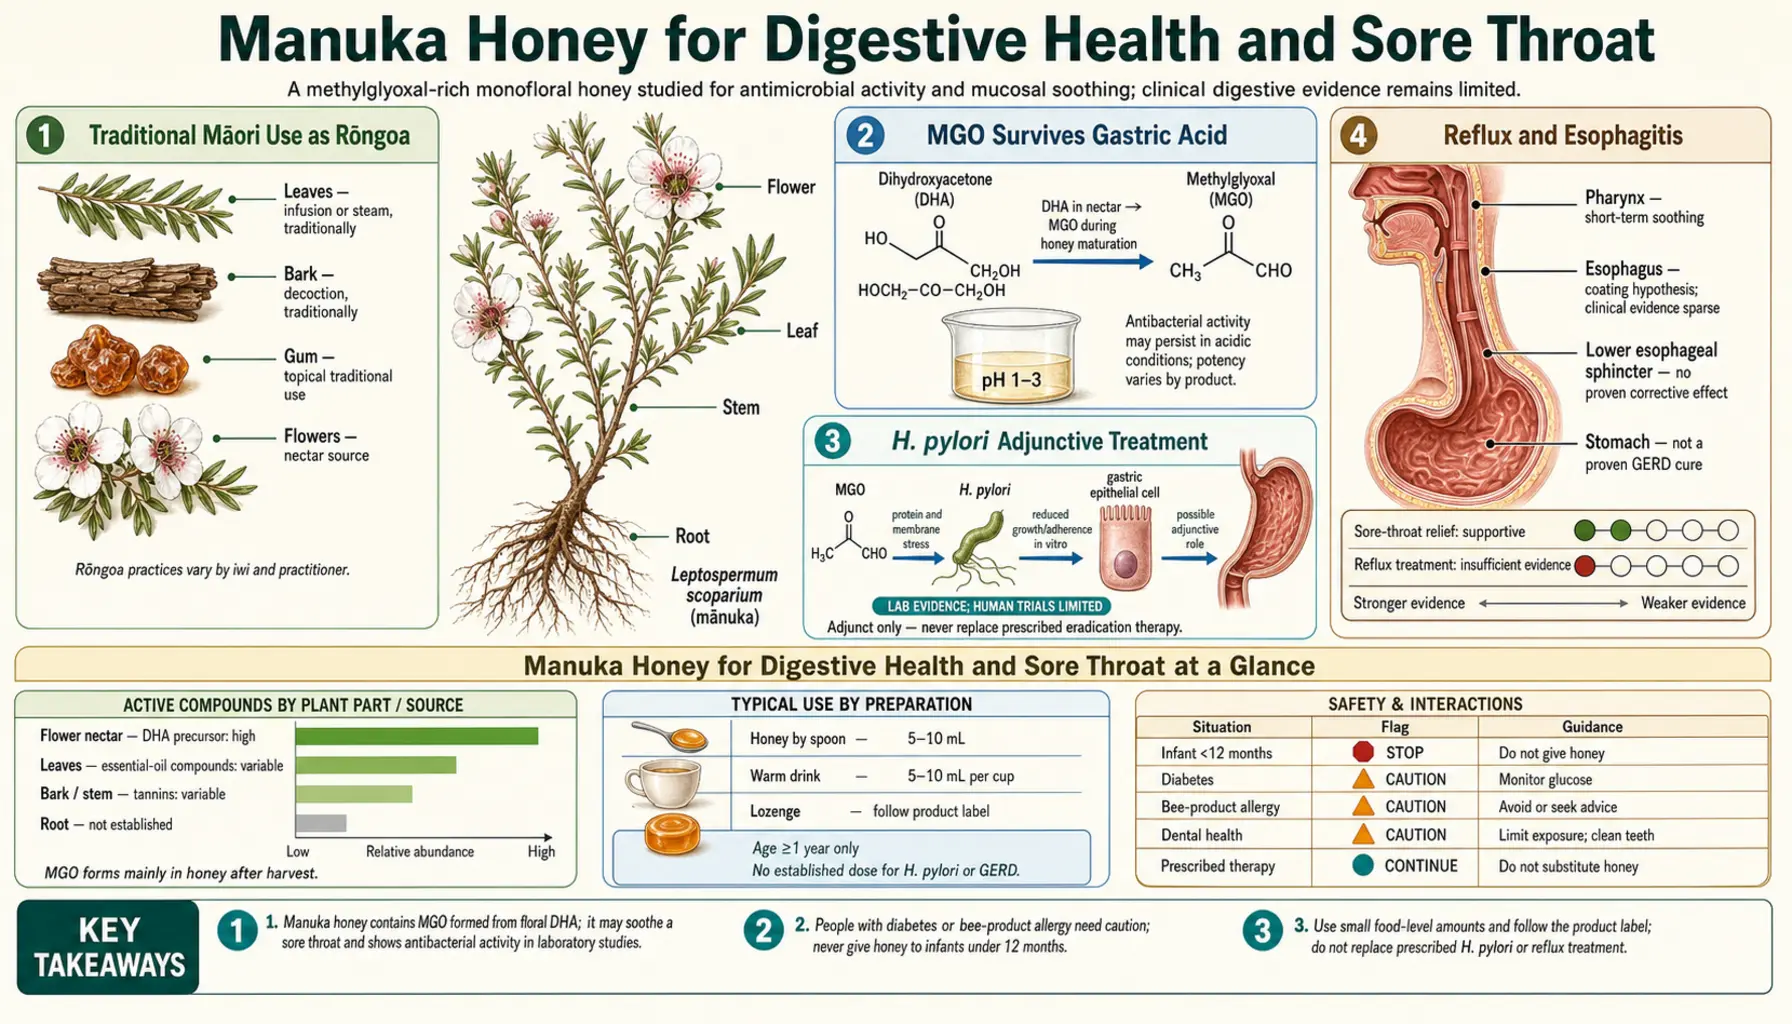
Beyond wound care, manuka honey is used and studied for upper-aerodigestive applications — sore throat, pharyngitis, post-tonsillectomy pain, radiation-induced oral mucositis, and as adjunctive therapy for Helicobacter pylori infection. The methylglyoxal (MGO) survives gastric acid intact, which means orally consumed manuka honey reaches the gastric mucosa with its antibacterial activity preserved — an unusual property among ingested antimicrobials. The best-known trial is Bardy 2012's double-blind randomized controlled trial (RCT) of active manuka honey for radiation mucositis in head-and-neck cancer patients, which found no significant difference between manuka honey and a golden-syrup placebo. Manuka honey lozenges are also used for throat comfort after tonsillectomy, a reported use. Traditional Māori use as rōngoa (medicine) for digestive complaints predates the European arrival in New Zealand. This deep-dive walks through the gastric H. pylori evidence, the mucositis trials, the lozenge use, the practical question of swallowing versus dissolving, and the broader gut-soothing applications.
Table of Contents
- Traditional Māori Use as Rōngoa
- MGO Survives Gastric Acid
- H. pylori Adjunctive Treatment
- Reflux and Esophagitis
- Sore Throat and Pharyngitis
- Bardy 2012 — Radiation Oral Mucositis Trial
- Post-Tonsillectomy Lozenges
- Cough — Cochrane Evidence in Children
- Swallow vs Dissolve — Practical Application
- Small Intestinal Bacterial Overgrowth, Irritable Bowel Syndrome, and Gut Microbiome Considerations
- Cautions — Including the Infant Botulism Warning
- Key Research Papers
- Connections
- Featured Videos
Traditional Māori Use as Rōngoa
The Māori people of New Zealand have used mānuka (their name for Leptospermum scoparium) as rōngoa (traditional medicine) for centuries before European contact. The plant's leaves were boiled to make decoctions for fevers, urinary complaints, and reduction of inflammation; the bark was used for diarrhea; vapor from the leaves was inhaled for head colds; and the seed capsules were chewed for sore throat. Honey-producing bees were introduced to New Zealand only in 1839 by Mary Bumby, an English missionary's sister, so the honey itself is post-contact — but the rapid Māori adoption of manuka honey for the same medicinal indications previously addressed by the plant's leaves and bark is well-documented in early 19th-century missionary accounts.
The traditional indications align remarkably well with the conditions for which modern clinical evidence has subsequently accumulated: wound care, sore throat, digestive complaints, skin conditions. The traditional knowledge essentially identified the right applications a century before the methylglyoxal mechanism was discovered. This is a recurring pattern in ethnobotany — experiential clinical observation often correctly identifies effective plant medicines, and modern science later catches up to explain the mechanism.
In modern New Zealand, manuka honey holds a particular cultural and economic significance for Māori communities. Many of the highest-quality manuka-producing land areas are on Māori-owned land (whenua Māori), and partnerships between traditional landowners and modern honey producers have made manuka honey a significant economic asset for several iwi (tribes). The 2018 ruling by the New Zealand Ministry for Primary Industries that only honey produced in New Zealand from Leptospermum scoparium can be exported as "manuka honey" was partly a recognition of the cultural and intellectual property dimensions of the Māori connection.
MGO Survives Gastric Acid
An unusual property of methylglyoxal that distinguishes manuka honey from most ingested antibacterial agents is its stability in gastric acid. Most plant-derived antibacterial compounds (allicin from garlic, curcumin, berberine, oregano carvacrol) are degraded, isomerized, or partially neutralized by stomach acid before they can reach the gastric mucosa or duodenum. Conventional antibiotics like penicillin V and ampicillin can be partially degraded; macrolides are typically formulated as enteric-coated to escape gastric inactivation.
MGO, by contrast, is stable at the acidic gastric pH (1.5-3.5) for the typical 1-3 hour gastric residence time of consumed honey. It exits the stomach in chemically intact form, contacts the gastric mucosa directly during its transit, and then enters the duodenum where the alkaline pH of pancreatic secretions slowly neutralizes it. This gives manuka honey three distinct points of antibacterial action in the upper gastrointestinal (GI) tract:
- Esophagus — if the honey is held in the mouth and then slowly swallowed (rather than gulped), it coats the esophageal mucosa and exerts local antibacterial and anti-inflammatory activity on its way to the stomach. This is the mechanism for radiation esophagitis applications.
- Stomach (gastric mucosa) — MGO survives gastric acid and reaches the gastric mucosal layer where H. pylori resides. This is the mechanism for H. pylori adjunctive treatment.
- Duodenum — partially neutralized MGO continues to have activity against duodenal pathogens before alkaline pancreatic secretions complete the inactivation. The clinical significance of this duodenal exposure is less well-characterized.
Beyond the duodenum, MGO has been largely inactivated by pancreatic secretions. Manuka honey does not reach the small intestine or colon in chemically active form — oral manuka honey is not a treatment for small intestinal bacterial overgrowth (SIBO), C. difficile, or any colonic infection. (For small intestinal bacterial overgrowth and diarrhea-predominant irritable bowel syndrome (IBS-D), see our small intestinal bacterial overgrowth page and related deep-dive sub-articles.)
H. pylori Adjunctive Treatment
The most-studied gastric application of manuka honey is as an adjunct in Helicobacter pylori eradication therapy. Standard "triple therapy" is a proton pump inhibitor (omeprazole, lansoprazole, etc.) plus clarithromycin plus amoxicillin or metronidazole for 14 days. Global eradication rates with first-line triple therapy have fallen from 85-90% in the 1990s to 70-75% in 2020s due to rising clarithromycin and metronidazole resistance. "Quadruple therapy" with bismuth subsalicylate and tetracycline is the rescue regimen but is more burdensome.
Al Somal et al. (1994) first demonstrated in the laboratory that manuka honey at 5% v/v completely stopped the growth of all seven H. pylori isolates tested, taken from gastric-ulcer biopsies. Taking manuka honey by mouth alongside standard triple therapy is a reported adjunct use.
The proposed mechanism is direct topical action on H. pylori in the gastric mucus layer — the honey coats the mucosal surface, and the MGO penetrates the mucus to reach the spiral organism. The osmotic action also disrupts the mucus layer that H. pylori uses to shelter itself from gastric acid, exposing it to additional acid-mediated stress.
The adjunct use as it is described:
- a high-grade manuka honey (UMF 15+ or MGO 514+ on the grading scales)
- 1 tablespoon (about 21 g, the USDA weight for a tablespoon of honey) on an empty stomach 30 minutes before breakfast
- 1 tablespoon at bedtime, at least 2 hours after the last meal
- held in the mouth briefly to coat the esophagus, then swallowed
- taken for the length of the triple-therapy course (typically 14 days) and 2 weeks beyond
- whether the infection has cleared is checked with a urea breath test, done at least 4 weeks after finishing therapy
Manuka honey alone is not adequate primary treatment for H. pylori. It is an adjunct, not a replacement for the systemic antibacterial therapy.
See our Helicobacter pylori page for the broader management approach.
Reflux and Esophagitis
For gastroesophageal reflux disease (GERD) and erosive esophagitis, manuka honey is sometimes used as a topical demulcent — a coating agent that physically protects the inflamed esophageal mucosa from acid and pepsin contact. The viscous honey coats the esophagus on its way down, providing temporary mechanical barrier protection plus the antibacterial activity that reduces H. pylori-associated inflammation contributing to reflux.
This is a folk-medicine use with limited formal trial evidence in gastroesophageal reflux disease specifically. The use reported for mild-to-moderate reflux symptoms is 1 teaspoon of manuka honey 30 minutes before meals and at bedtime. Proton pump inhibitor (PPI) therapy remains the first-line medical treatment for symptomatic and biopsy-confirmed reflux disease.
For radiation-induced esophagitis (a complication of chest or upper-GI radiation therapy), manuka honey has been investigated as a coating agent to reduce mucosal pain and inflammation during therapy. The application is similar to the radiation oral mucositis application discussed below — the honey is held in the mouth, then slowly swallowed to coat the esophagus on its way down. Evidence is preliminary; supportive care for radiation esophagitis remains primarily proton pump inhibitor therapy plus analgesics.
Sore Throat and Pharyngitis
The traditional use of honey for sore throat goes back millennia — ancient Egyptian, Greek, and Roman medical texts all reference honey for throat conditions. The modern question is whether manuka honey offers any specific advantage over conventional honey or over commercial throat lozenges and demulcents.
The mechanism for sore throat benefit is partly antibacterial (against bacterial pharyngitis, particularly group A streptococcus) but primarily demulcent and anti-inflammatory. The viscous honey coats the inflamed pharyngeal mucosa, providing mechanical buffering against the irritation of swallowing and breathing. The osmotic action draws fluid out of the inflamed tissue, reducing edema. The MGO provides direct antibacterial activity against the surface bacterial colonization that contributes to ongoing inflammation.
For viral pharyngitis (the cause of 80-90% of acute sore throat in adults), the antibacterial action is not the primary mechanism — the demulcent and anti-inflammatory effects are. Manuka honey is reasonably substitutable with conventional honey in this application; the MGO is helpful but not essential for the demulcent effect. The advantage of manuka is the established antibacterial activity if bacterial pharyngitis is suspected, the standardization (UMF/MGO ratings), and the more potent overall therapeutic effect.
For streptococcal pharyngitis (strep throat, group A strep), manuka honey is an adjunct only — it does not replace antibiotic therapy (penicillin VK or amoxicillin) because strep throat requires systemic antibiotic to prevent rheumatic fever and other delayed sequelae. The role of manuka is symptomatic comfort and adjunctive antibacterial action.
Bardy 2012 — Radiation Oral Mucositis Trial
A double-blind, placebo-controlled mucositis trial of manuka honey was published by Bardy et al. (2012) in the British Journal of Oral and Maxillofacial Surgery. 131 patients with head and neck cancer having radiotherapy to the mouth or throat area were randomized to active manuka honey or a placebo of golden syrup, 20 ml four times daily for 6 weeks, and mucositis was graded on the Radiation Therapy Oncology Group (RTOG) scale. Results:
- No significant difference between honey and golden syrup in their effects on mucositis
- Both the honey and the syrup seemed to be associated with fewer bacterial infections
- Compliance was a problem once mucositis began, which the authors say may have affected the findings
The authors concluded that active manuka honey did not improve mucositis. A 2014 Canadian trial (Hawley and colleagues) randomized 106 head and neck cancer patients to swish, hold and swallow 5 ml of manuka honey or a placebo gel four times a day throughout radiation treatment and for seven days after. It found no statistically significant difference between honey and placebo in any of the outcomes measured, which included symptom severity and quality of life; the authors reported that manuka honey was not tolerated well, with dropouts (57% on honey, 52% on placebo) mostly due to nausea.
The swish, hold and swallow method used in the Hawley trial is also described for other settings (chemotherapy mucositis, esophagitis, radiation laryngitis).
Post-Tonsillectomy Lozenges
Manuka honey lozenges are used during recovery from tonsillectomy, alongside pain medicines, for the long tail of throat pain that follows the operation. This is a reported use. The lozenge format gives longer contact with the throat lining (mucosa), which is described as mattering more than the total honey dose.
The same lozenge use is described for recovery from other upper aerodigestive surgical procedures (uvulopalatopharyngoplasty for sleep apnea, adenotonsillectomy in children, oropharyngeal cancer resection) and for acute viral pharyngitis, at 1 lozenge every 2-4 hours as needed.
Cough — Cochrane Evidence in Children
Honey (not specifically manuka, but honey in general) has the strongest pediatric evidence of any cough remedy. The Cochrane 2018 review (Oduwole et al.) of honey for acute cough in children pooled 6 randomized controlled trials (RCTs) in 899 children, comparing honey to over-the-counter cough medicines (dextromethorphan, diphenhydramine), no treatment, or placebo. Results:
- Honey reduced cough symptom severity and frequency more than no treatment
- Honey may have a similar effect to dextromethorphan in reducing cough frequency (low-certainty evidence)
- Honey may be better than diphenhydramine (low-certainty evidence)
- Honey improved children's and parents' sleep quality
- No difference in the occurrence of adverse events between the honey and comparison groups overall; nervousness, insomnia and hyperactivity were reported in 9.3% of children given honey and 2.7% given dextromethorphan, and stomach or bowel complaints in 12% on honey and 11% on placebo
The Cochrane review specifically excluded children under 12 months due to infant botulism risk. The standard dose used across the trials was 1.5-5 mL (approximately half to one teaspoon) of honey given 30 minutes before bedtime.
The AAP and WHO both endorse honey as a first-line cough remedy in children over 12 months and explicitly recommend it in preference to over-the-counter cough medicines, which have been demonstrated to be no more effective than placebo and to carry pediatric safety concerns. Manuka honey is reasonable to use in this application, though the more expensive medical-grade product is not necessary — ordinary culinary honey works equally well for cough symptom relief, where the demulcent effect predominates over antibacterial activity.
Swallow vs Dissolve — Practical Application
The application technique matters for the desired clinical effect:
- Slow dissolution in the mouth — for sore throat, pharyngitis, post-tonsillectomy pain, oral mucositis. 1 teaspoon (approximately 5 g) of manuka honey is allowed to dissolve slowly in the mouth and swished around the mouth and throat. In the method described, no water is drunk straight afterwards, so the honey coats the mucosa for at least 10-15 minutes, and it is repeated every 2-4 hours.
- Lozenge form — commercial manuka honey lozenges provide extended mucosal contact time and convenient dosing. Useful for prolonged or repeated daily use.
- Hold in mouth, then swallow — for combined upper-respiratory + esophageal applications. The honey coats the throat, then continues down to coat the esophagus.
- Direct ingestion on empty stomach — for H. pylori adjunctive treatment. 1 tablespoon (21 g) on an empty stomach 30 minutes before breakfast, again at bedtime. The honey passes quickly through the esophagus and coats the gastric mucosa.
- Gargle/swish — for oropharyngeal applications (post-tonsillectomy, periodontitis, oral thrush). 1 tablespoon held in the mouth, swished for 30 seconds, can be either swallowed or spit out depending on the indication.
- In warm (not hot) water or tea — for general sore-throat and cough comfort. Boiling water degrades both the MGO (though slowly) and the enzymes responsible for the residual hydrogen peroxide activity; warm water (under 60°C / 140°F) preserves activity.
The "swallow versus dissolve" question depends on the target site of action. For pharyngeal and oral pathology, slow dissolution is the method used. For gastric pathology (H. pylori, gastric ulcer), direct ingestion with brief mouth holding is the method used. For combined applications, hold-and-swallow technique addresses both.
Small Intestinal Bacterial Overgrowth, Irritable Bowel Syndrome, and Gut Microbiome Considerations
Several patient questions arise about whether manuka honey's antibacterial activity translates to benefit for small intestinal bacterial overgrowth (SIBO), irritable bowel syndrome (IBS), or other gut microbiome conditions. The mechanistic answer is: probably not, with caveats.
As discussed above, MGO is largely inactivated by pancreatic secretions in the duodenum. Oral manuka honey does not deliver clinically meaningful antibacterial concentrations to the small intestine, colon, or beyond. Small intestinal bacterial overgrowth, C. difficile colitis, ulcerative colitis flares, and other distal gut conditions are not addressed by oral manuka honey at any practical dose.
Conversely, the sugar load of honey (approximately 80% sugar, primarily fructose and glucose) can worsen small intestinal bacterial overgrowth symptoms in susceptible individuals — fructose is a known small intestinal bacterial overgrowth trigger food. Patients with small intestinal bacterial overgrowth who try manuka honey for any reason often experience bloating, gas, and increased symptoms within hours. For small intestinal bacterial overgrowth patients, manuka honey's antibacterial activity does not outweigh its fermentable sugar burden in the small intestine.
For diarrhea-predominant irritable bowel syndrome (IBS-D), the honey's osmotic effect can worsen diarrhea. For constipation-predominant irritable bowel syndrome (IBS-C), honey's mild laxative effect (from fructose malabsorption) may be helpful or counterproductive depending on the individual.
The exception is the use of manuka honey for upper-GI symptoms in irritable bowel syndrome patients — sore throat from acid reflux, mild esophagitis, gastric discomfort. In these specific indications, the local action on the esophagus and stomach can be beneficial without the fermentable-sugar concerns of lower gut delivery.
For comprehensive small intestinal bacterial overgrowth management see our small intestinal bacterial overgrowth overview and small intestinal bacterial overgrowth root causes deep-dive.
Cautions — Including the Infant Botulism Warning
- Infants under 12 months — absolute contraindication. Raw honey of any kind, including manuka, can contain Clostridium botulinum spores. In the immature infant gut (incomplete gastric acid production, immature gut microbiome), these spores can germinate and produce botulinum toxin, causing infant botulism — a life-threatening condition that typically presents as constipation, weakness, poor feeding, and progresses to respiratory failure. No honey of any type by any route for any infant under 1 year of age. This applies to even the smallest taste; the threshold for botulism spore exposure can be quite low. After 12 months of age, the maturing gut microbiome and gastric acidity prevent spore germination and honey is safe.
- Honey allergy / bee allergy — rare but documented. Onset can be immediate (anaphylaxis to honey traces of bee venom or pollen) or delayed (oral allergy syndrome from pollen cross-reactivity). A small first amount before regular use is the usual precaution for people with bee venom allergy or severe environmental pollen allergies.
- Diabetes (oral consumption) — manuka honey is approximately 80% sugar. For diabetic patients consuming honey orally, the carbohydrate load counts toward daily intake: USDA FoodData Central gives 1 tablespoon of honey as 21 g, carrying about 17 g of carbohydrate (82.4 g per 100 g). The glycemic index of manuka honey is moderate (50-60); the high fructose content moderates the glucose spike but contributes to hepatic fructose metabolism.
- Dental caries — honey is highly cariogenic. With frequent oral dissolution of manuka honey for sore-throat or mucositis applications, rinsing the mouth with water afterwards reduces dental surface exposure; for people with extensive dental restorations or active caries, this is the main drawback of honey as a demulcent.
- Counterfeit product — the global manuka honey market is approximately five times the size of New Zealand's actual production. Counterfeit and adulterated products are widespread. UMF and MGO are grading systems printed on the jar: an MGO number states the methylglyoxal content, and a UMF grade rates methylglyoxal together with other marker compounds, with a UMF logo and licence number on graded jars. Sub-$20 "manuka" honey on supermarket shelves is almost always either fake or low-MGO product with no therapeutic activity.
- Drug interactions — clinically significant interactions are uncommon. Topical and brief oral use have no documented major interactions. For daily large-volume oral use, the points raised are a theoretical, not well-established interaction with warfarin; the glucose load for people on insulin or sulfonylureas; and a theoretical osmotic effect on lithium clearance.
- Not a substitute for antibiotic therapy — for established H. pylori infection, manuka honey is an adjunct, not a replacement for standard triple therapy. For streptococcal pharyngitis, manuka is symptomatic only; antibiotic is required to prevent rheumatic fever. For systemic infection, manuka has no role beyond topical adjunctive support.
Key Research Papers
- Al Somal N, Coley KE, Molan PC, Hancock BM (1994). Susceptibility of Helicobacter pylori to the antibacterial activity of manuka honey. J R Soc Med, 87(1): 9-12. — PubMed PMID: 8308841
- McGovern DP, Abbas SZ, Vivian G, Dalton HR (1999). Manuka honey against Helicobacter pylori. J R Soc Med, 92(8): 439. (Letter.) — PubMed PMID: 10656024
- Bardy J, Slevin NJ, Mais KL, Molassiotis A (2008). A systematic review of honey uses and its potential value within oncology care. J Clin Nurs, 17(19): 2604-23. — PubMed PMID: 18808626
- Bardy J, Molassiotis A, Ryder WD, Mais K, Sykes A, Yap B, Lee L, Kaczmarski E, Slevin N (2012). A double-blind, placebo-controlled, randomised trial of active manuka honey and standard oral care for radiation-induced oral mucositis. Br J Oral Maxillofac Surg, 50(3): 221-6. — PubMed PMID: 21636188
- Oduwole O, Udoh EE, Oyo-Ita A, Meremikwu MM (2018). Honey for acute cough in children. Cochrane Database Syst Rev, 4: CD007094. — PubMed PMID: 29633783
- Paul IM, Beiler J, McMonagle A, Shaffer ML, Duda L, Berlin CM (2007). Effect of honey, dextromethorphan, and no treatment on nocturnal cough and sleep quality for coughing children and their parents. Arch Pediatr Adolesc Med. — PubMed PMID: 18056558
- Khanal B, Baliga M, Uppal N (2010). Effect of topical honey on limitation of radiation-induced oral mucositis: an intervention study. Int J Oral Maxillofac Surg. — PubMed PMID: 20832243
- Hawley P, Hovan A, McGahan CE, Saunders D (2014). A randomized placebo-controlled trial of manuka honey for radiation-induced oral mucositis. Support Care Cancer, 22(3): 751-61. — PubMed PMID: 24221577
- Manyi-Loh CE, Clarke AM, Munzhelele T, Green E, Mkwetshana NF, Ndip RN (2010). Selected South African honeys and their extracts possess in vitro anti-Helicobacter pylori activity. Arch Med Res. — PubMed PMID: 20851288
- Maddocks SE, Lopez MS, Rowlands RS, Cooper RA (2012). Manuka honey inhibits the development of Streptococcus pyogenes biofilms and causes reduced expression of two fibronectin binding proteins. Microbiology. — PubMed PMID: 22294681
- Brudzynski K (2006). Effect of hydrogen peroxide on antibacterial activities of Canadian honeys. Can J Microbiol. — PubMed PMID: 17473892
PubMed Topic Searches
Connections
- All Herbs
- Manuka Honey Overview
- Manuka Honey Benefits Hub
- Wound Healing
- Antimicrobial Spectrum
- Skin Conditions & Acne
- Helicobacter pylori
- Gastroesophageal Reflux Disease (Acid Reflux)
- Small Intestinal Bacterial Overgrowth
- Pharyngitis
- Cold & Flu Treatments
- Slippery Elm
- Marshmallow Root
- Licorice Root (DGL)
- Honey (Conventional)
- History