⚠ Evidence warning: Clinical trials or other evidence do not support the claim that cat's claw benefits inflammatory bowel disease, psoriasis, asthma, atherosclerosis and post-viral fatigue, spares the gut microbiome, and allows steroid or biologic dose reduction. This page keeps it as a report of what people, websites or other media say.
Cat's Claw Anti-Inflammatory (NF-kB & Tumor Necrosis Factor-alpha)
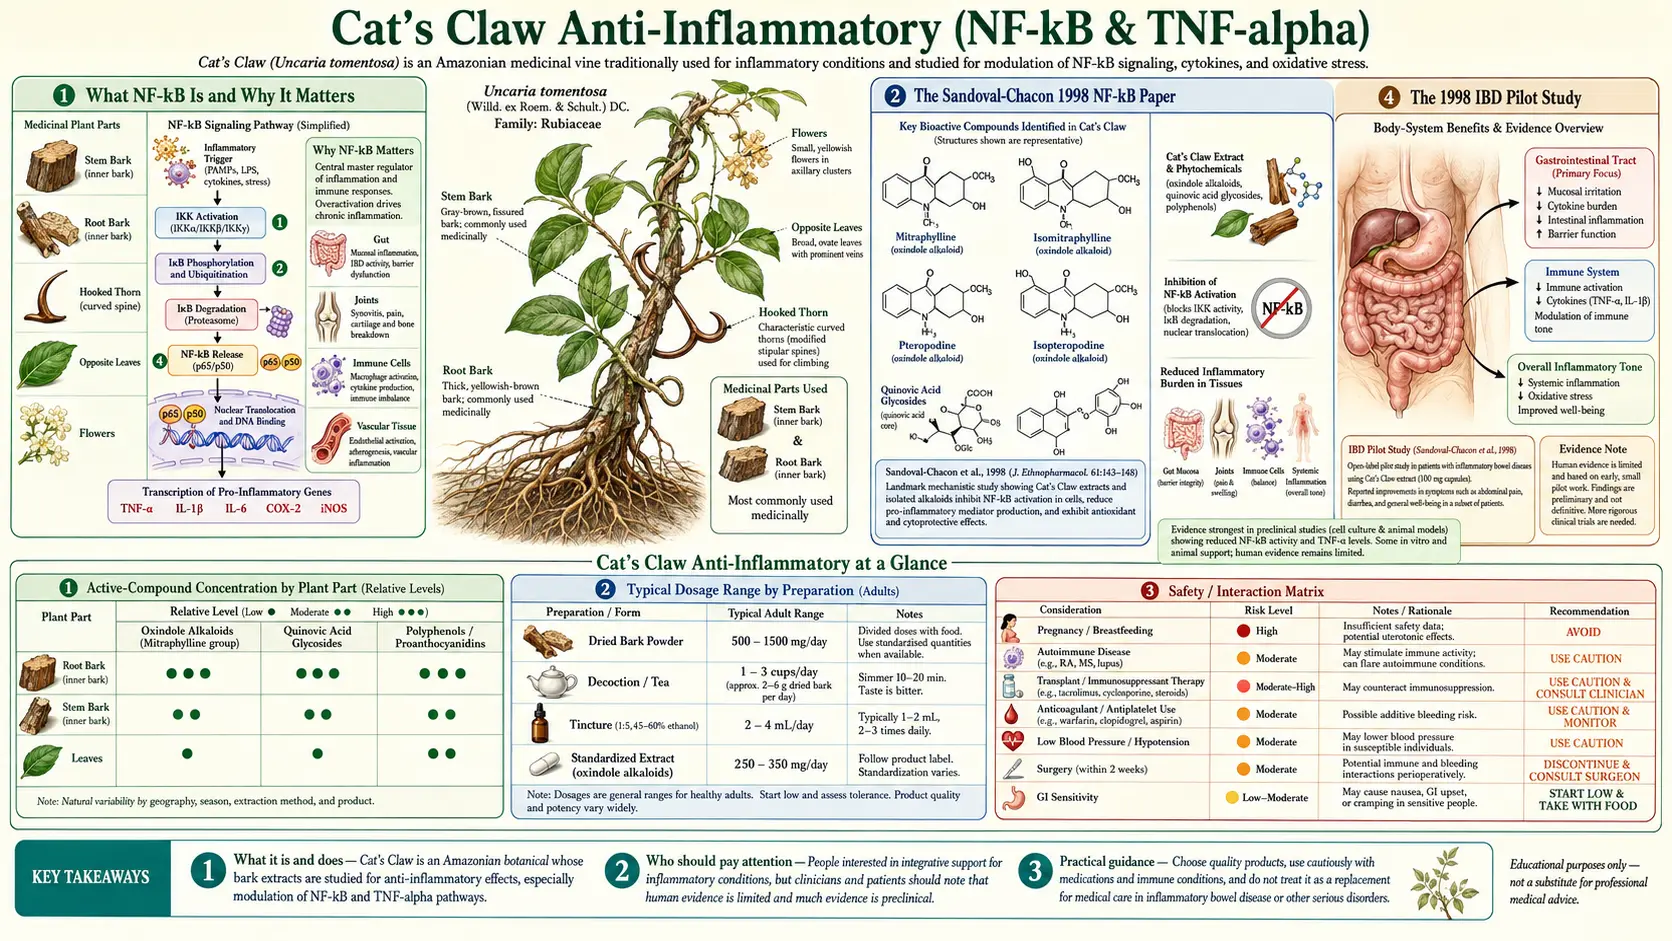
The anti-inflammatory action of Cat's Claw is one of the cleanest mechanism-to-clinical-effect stories in plant medicine. The active fraction (a combination of pentacyclic oxindole alkaloids (POA), quinovic acid glycosides, and triterpenoids) is described as blocking the activation of NF-kB; in a 2000 study in mouse macrophage cells in a dish, a cat's claw water extract suppressed tumor necrosis factor-alpha production by approximately 65–85%. The downstream consequence is suppression of tumor necrosis factor-alpha, interleukin-1 (IL-1), interleukin-6 (IL-6), cyclooxygenase-2 (COX-2), and matrix metalloproteinases — the entire inflammatory cascade dampened simultaneously rather than blocked at any single effector. Sandoval-Chacon et al. reported in 1998 that cat's claw blocked NF-kB activation in cells in a dish and reduced indomethacin-induced inflammation of the small intestine (enteritis) in rats. The mechanism explains why Cat's Claw produces parallel effects in conditions as different as rheumatoid arthritis, osteoarthritis, inflammatory bowel disease (IBD), and chronic neuroinflammatory states — all share NF-kB-driven inflammatory loops as a common pathway.
Table of Contents
- What NF-kB Is and Why It Matters
- The Sandoval-Chacon 1998 NF-kB Paper
- Tumor Necrosis Factor-alpha Reduction In Vitro and In Vivo
- Cat's Claw and Inflammatory Bowel Disease: Reported Use
- Cat's Claw vs Sulfasalazine
- Cat's Claw vs Nonsteroidal Anti-Inflammatory Drugs and Cyclooxygenase-2 Inhibitors
- Cat's Claw vs Corticosteroids
- Cat's Claw vs Tumor Necrosis Factor-alpha Inhibitor Biologics
- Other NF-kB-Driven Inflammatory Conditions
- Dosing, Standardization, and Form Selection
- What Rheumatology Reviewers Concluded in 2026
- Key Research Papers
- Connections
- Featured Videos
What NF-kB Is and Why It Matters
Nuclear factor kappa-B (NF-kB) is a family of transcription factors central to the regulation of inflammation, immune response, cell proliferation, and cell survival. In its inactive state, NF-kB exists as a dimer (most commonly the p50/p65 heterodimer) sequestered in the cytoplasm by its inhibitor protein IkB-alpha. The IkB-alpha "covers" the nuclear localization signal of NF-kB, preventing it from entering the nucleus to bind DNA.
Activating signals reach the cell through a wide variety of receptors:
- Cytokine receptors (tumor necrosis factor receptor 1 (TNFR1) bound by tumor necrosis factor-alpha, interleukin-1 receptor (IL-1R) bound by interleukin-1 (IL-1))
- Toll-like receptors (TLR4 bound by bacterial lipopolysaccharide, TLR2 by Gram-positive cell wall components, TLR3 by viral double-stranded RNA, etc.)
- Antigen receptors (T-cell receptor, B-cell receptor)
- Stress signals (ultraviolet (UV) radiation, oxidative stress, DNA damage)
All of these signals converge on activation of the IkB kinase (IKK) complex (IKK-alpha, IKK-beta, and NF-kB essential modulator (NEMO)), which phosphorylates IkB-alpha. Phosphorylated IkB-alpha is rapidly ubiquitinated and degraded by the proteasome, releasing NF-kB to translocate into the nucleus, where it binds to NF-kB response elements in the promoter regions of target genes and drives their transcription.
The target genes activated by NF-kB read like a catalog of inflammation:
- Pro-inflammatory cytokines: tumor necrosis factor-alpha (creating a positive-feedback loop where tumor necrosis factor-alpha activates NF-kB which produces more tumor necrosis factor-alpha), interleukin-1-beta, interleukin-6, interleukin-8 (IL-8), interleukin-12 (IL-12)
- Chemokines: monocyte chemoattractant protein-1 (MCP-1), RANTES (regulated on activation, normal T cell expressed and secreted), eotaxin (recruiting additional immune cells to the inflammatory site)
- Adhesion molecules: intercellular adhesion molecule-1 (ICAM-1), vascular cell adhesion molecule-1 (VCAM-1), E-selectin (allowing recruited leukocytes to bind and transmigrate the vascular endothelium)
- Inflammatory enzymes: cyclooxygenase-2 (producing inflammatory prostaglandins), inducible nitric oxide synthase (iNOS, producing nitric oxide), and matrix metalloproteinases (MMP) including MMP-1, MMP-3, MMP-9 (which destroy extracellular matrix and cartilage)
- Anti-apoptotic proteins: Bcl-2, Bcl-xL, IAPs (extending the survival of activated inflammatory cells)
- Cell-cycle regulators: Cyclin D1 (promoting cellular proliferation)
The clinical relevance: persistent NF-kB activation is the molecular signature of essentially every chronic inflammatory and autoimmune disease — rheumatoid arthritis, inflammatory bowel disease, psoriasis, atherosclerosis, asthma, neuroinflammation, and most cancers. Targeting NF-kB therapeutically is correspondingly one of the most attractive but technically difficult goals in pharmacology, because NF-kB is also required for normal immune defense against infection. Complete NF-kB blockade is incompatible with life. Therapeutic NF-kB modulation needs to be partial and selective — which is what Cat's Claw extracts are proposed to produce.
The Sandoval-Chacon 1998 NF-kB Paper
The Sandoval-Chacon, Thompson, Zhang et al. paper published in Alimentary Pharmacology and Therapeutics in 1998 is the foundational mechanistic study establishing Cat's Claw as an NF-kB inhibitor. The work combined cells in a dish with a rat model. It was not a human study, and it included no comparison with any drug.
Design. In the cell tests, two cell lines — RAW 264.7 mouse macrophages and HT29 epithelial cells — were exposed to the oxidant peroxynitrite, and the activation of NF-kB was measured in RAW 264.7 cells. In the animal part, chronic intestinal inflammation was induced in rats with indomethacin (7.5 mg/kg), and cat's claw was given by mouth in the drinking water (5 mg/mL). The result was inflammation of the small intestine (indomethacin-enteritis), not of the colon.
Findings.
- In the cells, cat's claw (100 microg/mL) reduced peroxynitrite-induced cell death (apoptosis) in both HT29 and RAW 264.7 cells, and it blocked the activation of NF-kB.
- In the rats, cat's claw markedly reduced the indomethacin-enteritis, as shown by lower myeloperoxidase activity, less measured tissue damage (morphometric damage) and lower liver metallothionein expression.
What the authors concluded. The authors concluded that cat's claw protects cells against oxidative stress and negated the activation of NF-kB, and that their studies provide mechanistic evidence for the widely held belief that cat's claw is an effective anti-inflammatory agent. One proposed explanation for how it blocks NF-kB is direct interference with the IKK-IkB-NF-kB signaling axis, possibly through inhibition of IKK activity or through stabilization of IkB-alpha; the paper's abstract does not test this.
The paper became the foundational reference for the next two decades of Cat's Claw inflammation research. Every subsequent study examining Cat's Claw in inflammatory disease has built on the NF-kB mechanism documented here.
Tumor Necrosis Factor-alpha Reduction In Vitro and In Vivo
Tumor necrosis factor-alpha is one of the most studied pro-inflammatory cytokines because it sits at the apex of many inflammatory disease cascades. Originally identified for its ability to induce tumor necrosis (hence the name), it is now recognized as the central driver of inflammation in rheumatoid arthritis, Crohn's disease, ulcerative colitis, psoriasis, and ankylosing spondylitis — conditions whose modern blockbuster treatment is the class of tumor necrosis factor-alpha inhibitor biologic drugs (adalimumab, etanercept, infliximab, golimumab, certolizumab pegol).
Cat's Claw's tumor necrosis factor-alpha-reducing activity has been documented in three complementary lines of evidence:
- In vitro macrophage models. Sandoval, Charbonnet, Okuhama et al. (Free Radical Biology and Medicine 2000) exposed RAW 264.7 mouse macrophages in a dish to bacterial lipopolysaccharide (LPS) in the presence or absence of Cat's Claw extract, a water decoction of the bark. Lipopolysaccharide is a potent NF-kB activator and drives high tumor necrosis factor-alpha output: here it raised tumor necrosis factor-alpha from 3 to 97 ng/ml. Cat's Claw suppressed tumor necrosis factor-alpha production by approximately 65–85%, with a half-maximal effect (EC50) at 1.2 ng/ml for the freeze-dried concentrate and 28 ng/ml for micropulverized bark. A separate 2007 study (Allen-Hall et al.) used human THP-1 monocytic cells.
- In vivo rodent models. In the 2002 Sandoval study, 3 days of oral pretreatment with Uncaria tomentosa protected against indomethacin-induced gastritis in an animal model and prevented tumor necrosis factor-alpha mRNA expression and apoptosis. Other studies in rodent models of carrageenan paw edema, adjuvant-induced arthritis, and lipopolysaccharide-induced septic shock have demonstrated reduced circulating tumor necrosis factor-alpha levels following Cat's Claw administration.
- Human clinical data. The Piscoya 2001 knee osteoarthritis trial had 45 patients: 30 took freeze-dried Uncaria guianensis (a related cat's claw species) and 15 took placebo, for four weeks. Pain with activity and the medical and patient assessment scores fell significantly, with benefits within the first week; knee pain at rest or at night and knee circumference were not significantly reduced. The trial's tumor necrosis factor-alpha measurements were made in RAW 264.7 mouse cells in a dish, not in the patients. The Mur 2002 rheumatoid arthritis trial had 40 patients already taking sulfasalazine or hydroxychloroquine: 24 weeks of a pentacyclic-chemotype Uncaria tomentosa extract reduced the number of painful joints compared with placebo (by 53.2% vs 24.1%; p = 0.044), which the authors described as a modest benefit to the tender joint count. It did not directly measure the cytokine.
The tumor necrosis factor-alpha-reducing effect is mechanistically downstream of the NF-kB inhibition. NF-kB drives transcription of the tumor necrosis factor-alpha gene, so reducing NF-kB activity reduces tumor necrosis factor-alpha production proportionally. Tumor necrosis factor-alpha has multiple input drivers, only some of which are NF-kB-mediated. The tumor necrosis factor-alpha figures above come from mouse cells in a dish.
Cat's Claw and Inflammatory Bowel Disease: Reported Use
Cat's claw (uña de gato) is used in traditional Peruvian medicine for a wide range of health problems, particularly digestive complaints and arthritis, as the 1998 Sandoval-Chacon paper notes. Practitioners also use it in inflammatory bowel disease (Crohn's disease and ulcerative colitis), usually alongside a person's existing inflammatory bowel disease medicines, and people who take it describe easing of symptoms such as abdominal pain, stool frequency and blood in stool.
The published research behind this use is the cell and rat work described above: the 1998 study induced inflammation of the small intestine with indomethacin, and the 2002 study used an indomethacin gastritis model. No published trial of cat's claw in people with inflammatory bowel disease was found in PubMed. Larger randomized controlled trials have not been done — partly because Cat's Claw cannot be patented as a drug and the financial incentive for industry-funded trials is absent.
Practitioners describe Cat's Claw as an add-on for people whose disease stays active despite conventional therapy (mesalamine, azathioprine, biologics), not as a substitute for established inflammatory bowel disease therapy. Supporters of pentacyclic-chemotype products hold that only POA-standardized extracts count; the 2002 Sandoval study found that the alkaloids did not influence the anti-inflammatory activity (see Dosing, Standardization, and Form Selection).
Cat's Claw vs Sulfasalazine
Sulfasalazine is the prototypical first-generation drug for both inflammatory bowel disease (specifically ulcerative colitis) and rheumatoid arthritis. It is a sulfonamide-salicylate conjugate that is cleaved by colonic bacteria into two active metabolites:
- 5-aminosalicylic acid (5-ASA, mesalamine) — acts locally in the colon as an anti-inflammatory, with NF-kB inhibition as part of the mechanism. This is the part that drives the inflammatory bowel disease effect.
- Sulfapyridine — absorbed systemically, contributes to the rheumatoid arthritis effect but is also the source of most of the side effects (hypersensitivity, hematologic toxicity, hepatotoxicity, gastrointestinal (GI) upset, male reversible oligospermia).
Comparison with Cat's Claw on multiple dimensions:
- NF-kB inhibition endpoint. The 1998 Sandoval-Chacon study had no sulfasalazine comparison. In the 2002 Mur rheumatoid arthritis trial, the patients were already taking sulfasalazine or hydroxychloroquine, and cat's claw extract or placebo was added on top.
- Microbiome effects. Sulfasalazine requires colonic bacterial cleavage and shifts the gut microbiome composition. Cat's Claw does not appreciably alter microbiome composition — an advantage for patients with concurrent dysbiosis or small intestinal bacterial overgrowth (SIBO).
- Sulfa allergy. Sulfasalazine is contraindicated in patients with sulfa allergy (a not-uncommon contraindication). Cat's Claw has no sulfa group and is not subject to this contraindication.
- Hematologic toxicity. Sulfasalazine can cause leukopenia, agranulocytosis, hemolytic anemia, and aplastic anemia, requiring complete blood count (CBC) monitoring every 3 months in chronic users. Cat's Claw has no documented hematologic toxicity.
- Hepatotoxicity. Sulfasalazine can cause hepatocellular injury requiring transaminase monitoring. Cat's Claw has no documented hepatotoxicity at conventional doses.
- Folate depletion. Sulfasalazine inhibits intestinal folate absorption and depletes folate stores. Cat's Claw does not affect folate metabolism.
- Male reproductive effects. Sulfasalazine causes reversible oligospermia in approximately 80% of male users. Cat's Claw has no documented effect on spermatogenesis.
- Cost and access. Sulfasalazine is generic, inexpensive, and prescription-only. Cat's Claw is over-the-counter, modestly priced (POA-standardized products typically $30–$60/month). Insurance covers sulfasalazine; not Cat's Claw.
- Evidence quality. Sulfasalazine has decades of large randomized controlled trials with hard endpoints (mucosal healing in inflammatory bowel disease, radiographic progression in rheumatoid arthritis (RA)). Cat's Claw has the Mur rheumatoid arthritis trial, the Piscoya knee osteoarthritis trial, and the Sandoval-Chacon mechanistic foundation in cells and rats. The two are not in the same evidence-base weight class.
In ulcerative colitis or rheumatoid arthritis, sulfasalazine has the larger evidence base. Practitioners describe Cat's Claw as an option for people who cannot tolerate sulfasalazine (sulfa allergy, hematologic effects, hepatic effects, persistent gastrointestinal intolerance) or who want an additional anti-inflammatory layer on top of existing therapy.
Cat's Claw vs Nonsteroidal Anti-Inflammatory Drugs and Cyclooxygenase-2 Inhibitors
Nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, diclofenac, indomethacin, meloxicam) and cyclooxygenase-2-selective inhibitors (celecoxib, rofecoxib historically, etoricoxib in some markets) work by inhibiting cyclooxygenase enzymes that convert arachidonic acid to inflammatory prostaglandins (prostaglandin E2 (PGE2) in particular). The COX inhibition reduces pain, fever, and acute inflammation but does nothing about the upstream NF-kB signaling, the cytokine cascade, or the matrix-destroying enzymes that drive chronic inflammatory disease progression.
Mechanism comparison:
- Nonsteroidal anti-inflammatory drugs (NSAIDs) block cyclooxygenase-1 (COX-1) (constitutive, present in gastric mucosa and platelets) and cyclooxygenase-2 (inducible, upregulated during inflammation). The cyclooxygenase-1 inhibition is responsible for most of the gastrointestinal ulceration and the antiplatelet effects. Cyclooxygenase-2 selective inhibitors spare cyclooxygenase-1 but at the cost of cardiovascular risk (rofecoxib was withdrawn from the market for this reason; celecoxib carries a black-box warning).
- Cat's Claw acts upstream of the COX pathway. In the Piscoya group's tests in RAW 264.7 mouse cells, Cat's Claw (10 microg/ml) had no effect on basal PGE2 production but reduced LPS-induced PGE2 release, at higher concentrations than those needed to inhibit tumor necrosis factor-alpha. The authors concluded that its anti-inflammatory properties may result from inhibiting tumor necrosis factor-alpha and, to a lesser extent, PGE2 production. This profile is proposed as the reason Cat's Claw is not linked to nonsteroidal anti-inflammatory drug (NSAID)-like gastric ulceration or antiplatelet effects.
Clinical comparison:
- Speed of effect. Nonsteroidal anti-inflammatory drugs produce noticeable analgesic effect within hours of dosing. Cat's Claw clinical effects emerge over weeks (the Mur trial primary endpoint was at 24 weeks). Because of that speed, nonsteroidal anti-inflammatory drugs are used for acute symptom flares; Cat's Claw is used as a maintenance therapy.
- Gastrointestinal toxicity. Chronic nonsteroidal anti-inflammatory drug use causes gastric ulceration in 15–30% of users and significantly elevated risk of upper gastrointestinal bleeding requiring proton pump inhibitor coverage. Cat's Claw has no documented gastrointestinal ulcerogenic effect.
- Kidney effects. Nonsteroidal anti-inflammatory drugs reduce renal blood flow through prostaglandin inhibition and can cause acute kidney injury, particularly in patients with reduced baseline kidney function, dehydration, or concurrent angiotensin-converting enzyme inhibitors (ACE inhibitors) / angiotensin receptor blockers (ARBs) / diuretics. For Cat's Claw, a 2022 case report described a person on a strict ketogenic diet, using over-the-counter diet shakes containing cat's claw (Uncaria tomentosa), who developed acute kidney injury with a serum creatinine of 3.6 mg/dL, up from a baseline of 0.7 mg/dL. A kidney biopsy showed sudden inflammation of the kidney tissue (acute interstitial nephritis). After the shake was stopped and corticosteroid treatment was given, kidney function improved to near baseline. The authors describe it, to their knowledge, as the only biopsy-proven case of acute interstitial nephritis in the setting of cat's claw use.
- Cardiovascular effects. Both non-selective nonsteroidal anti-inflammatory drugs and cyclooxygenase-2 selective inhibitors carry cardiovascular event risk, particularly in patients with established cardiovascular disease. Cat's Claw has not been associated with cardiovascular events; if anything, the mild blood-pressure-lowering effect may be slightly cardioprotective.
- Disease modification. Neither nonsteroidal anti-inflammatory drugs nor Cat's Claw modify long-term radiographic disease progression in rheumatoid arthritis. Both are symptomatic therapies in that disease context.
The adjunctive approach practitioners describe: for people with chronic inflammatory pain who take ongoing analgesic therapy, Cat's Claw (NF-kB modulation, slow onset, broad anti-inflammatory) plus as-needed low-dose nonsteroidal anti-inflammatory drugs for breakthrough symptoms, with the aim of lower nonsteroidal anti-inflammatory drug exposure and less of its gastrointestinal / renal / cardiovascular risk.
Cat's Claw vs Corticosteroids
Corticosteroids (prednisone, prednisolone, methylprednisolone, dexamethasone, hydrocortisone) are the most powerful broad-spectrum anti-inflammatory drugs in clinical use. They work through binding to the cytoplasmic glucocorticoid receptor and translocating into the nucleus, where they directly transrepress NF-kB (and AP-1) target genes at the transcriptional level — a mechanism that overlaps substantially with the Cat's Claw NF-kB inhibition mechanism, except corticosteroids work much more powerfully.
The clinical use case for corticosteroids in chronic inflammatory disease is generally as bridge therapy or as flare control, not as long-term maintenance, because of the side-effect profile:
- Osteoporosis with chronic use (significant by 3 months of low-dose oral steroid, severe by years)
- Steroid-induced diabetes / glucose intolerance
- Weight gain, central obesity, moon face, buffalo hump (Cushingoid features)
- Skin thinning, easy bruising, slow wound healing
- Adrenal axis suppression with chronic use, requiring slow tapering on discontinuation
- Mood disturbance (insomnia, irritability, depression, occasional psychosis)
- Cataracts and glaucoma with chronic use
- Avascular necrosis of femoral head at higher doses
- Immunosuppression with elevated risk of opportunistic infection
Cat's Claw has none of these adverse effects at conventional doses. The trade-off is that Cat's Claw is also dramatically less powerful — a 5 mg/day dose of prednisone produces broad anti-inflammatory effects that no botanical preparation can match.
In chronic inflammatory disease, where low-dose maintenance corticosteroids are used for symptom control on top of disease-modifying antirheumatic drug (DMARD) therapy (a common scenario in long-standing rheumatoid arthritis), practitioners describe adding Cat's Claw as an adjunct with the goal of potentially permitting steroid dose reduction. The Mur trial added the extract or placebo to sulfasalazine or hydroxychloroquine treatment. Chronic steroid use suppresses the adrenal axis (see the list above), which is why steroid doses are reduced by slow tapering, with disease activity markers and adrenal axis function tracked along the way.
Cat's Claw vs Tumor Necrosis Factor-alpha Inhibitor Biologics
Tumor necrosis factor-alpha inhibitor biologics (adalimumab, etanercept, infliximab, golimumab, certolizumab pegol) are large-molecule drugs that directly bind and neutralize circulating tumor necrosis factor-alpha or block the TNFR1 receptor. They are highly effective in rheumatoid arthritis, ankylosing spondylitis, psoriatic arthritis, Crohn's disease, ulcerative colitis, and psoriasis. They are also expensive ($20,000–$60,000/year retail in the US), require subcutaneous or intravenous injection, and carry serious risks including reactivation of latent tuberculosis, opportunistic fungal infections, hepatitis B reactivation, and rare but serious heart-failure exacerbation and lymphoma.
Mechanism comparison:
- Tumor necrosis factor (TNF) inhibitors directly bind extracellular tumor necrosis factor-alpha or its receptor, dropping circulating tumor necrosis factor-alpha activity to near zero.
- Cat's Claw reduced tumor necrosis factor-alpha production by approximately 65–85% in mouse macrophage cells in a dish; the proposed route is upstream NF-kB inhibition.
The magnitudes are not comparable. A patient on adalimumab effectively has tumor necrosis factor-alpha neutralized as a clinically relevant cytokine. A patient on Cat's Claw has tumor necrosis factor-alpha output modestly reduced.
How practitioners position it:
- In a patient with mild-to-moderate inflammatory disease, conventional therapy + Cat's Claw may produce sufficient control without escalating to biologics — an attractive outcome given the cost, route of administration, and side-effect profile of biologics.
- In a patient who already requires biologic therapy for adequate disease control, adding Cat's Claw is not contraindicated. The theoretical risk of additive infection susceptibility is present; the practical clinical experience is limited.
- Cat's Claw has not been studied as a substitute for biologic therapy in patients with severe or rapidly progressive disease where biologics are indicated.
Other NF-kB-Driven Inflammatory Conditions
Because NF-kB is the common transcriptional engine of essentially every chronic inflammatory disease, the Cat's Claw mechanism translates — with varying levels of clinical evidence — to multiple non-arthritis indications:
- Inflammatory bowel disease — Crohn's disease and ulcerative colitis. Mechanism: NF-kB inhibition at the inflamed mucosa, proposed from the 1998 Sandoval-Chacon cell and rat study (indomethacin-induced inflammation of the small intestine). Practitioners describe adjunctive use alongside established inflammatory bowel disease therapy, not in place of it.
- Psoriasis — an NF-kB and tumor necrosis factor-alpha-driven autoimmune skin disease. No formal Cat's Claw trials in psoriasis but the mechanism predicts benefit. Practitioners describe adjunctive use alongside conventional topical / phototherapy / biologic therapy.
- Atherosclerosis — chronic vascular inflammation with NF-kB-driven endothelial activation and macrophage activation in arterial plaques. Cat's Claw mechanistic profile is consistent with possible anti-atherogenic effect; no clinical outcome data.
- Neuroinflammation and neurodegeneration — microglial NF-kB activation is implicated in Alzheimer's disease, Parkinson's disease, and chronic neuroinflammatory states. In the Snow et al. 2019 study, a Cat's Claw extract and its proanthocyanidin constituents prevented the formation of, and broke up, beta-amyloid fibrils (the main component of plaques) and tau protein fibrils (the main component of tangles) in laboratory tests. In transgenic mice that develop brain plaques, the isolated constituent proanthocyanidin B2 markedly reduced brain plaque load and improved short-term memory.
- Chronic post-viral inflammation — including the immune-dysregulation states grouped under myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and the post-acute sequelae of viral infection. The combination of NF-kB modulation, immune support, and DNA-repair enhancement is mechanistically attractive; clinical evidence is anecdotal.
- Allergy / asthma — NF-kB drives much of the airway inflammation in chronic asthma. Cat's Claw has not been formally studied in asthma but the mechanism predicts benefit. It has not been compared with inhaled corticosteroid / long-acting bronchodilator therapy.
Dosing, Standardization, and Form Selection
Supporters of pentacyclic-chemotype products apply the same dosing and product-selection logic to anti-inflammatory use as to immune modulation: in their view chemotype certification matters more than dose, and a POA-standardized extract at moderate dose outperforms a non-standardized bulk product at high dose.
The research group that first studied cat's claw for inflammation reported a different result in 2002. In the Sandoval study, the presence of oxindole or pentacyclic alkaloids did not influence the anti-inflammatory and antioxidant activity of cat's claw. Extract fractions without alkaloids lowered LPS-induced tumor necrosis factor-alpha and nitrite production in RAW 264.7 mouse cells at a concentration range comparable to the whole plant. The total oxindole and pentacyclic alkaloid content of Uncaria tomentosa was 35-fold greater than that of the related species Uncaria guianensis, yet U. guianensis was the more potent of the two.
The dosing landmarks used in practice and in trials:
- POA-standardized extract: 60 mg/day (the Mur rheumatoid arthritis trial dose) to 350 mg/day (the dose used in trials of a water-soluble cat's claw extract), depending on product standardization. Supporters of standardization point to the certificate of analysis, where the parameter they track is total POA content per capsule, not bark mass.
- Non-standardized bark capsules (not chemotype-certified): 500–1000 mg two to three times daily, but with no guarantee of clinical activity.
- Tincture (1:5 in 45–60% ethanol): 1–2 mL two to three times daily. Some tinctures specify pentacyclic alkaloid chemotype; others do not.
- Tea/decoction: Traditional preparation; alkaloid extraction is incomplete with water alone. The 2000 Sandoval cell study that found approximately 65–85% suppression of tumor necrosis factor-alpha used a water decoction of the bark.
Time to clinical effect for anti-inflammatory indications is typically 4–12 weeks. Because its effects build over weeks, Cat's Claw is used as a maintenance and adjunctive therapy rather than for acute inflammatory flares, which are treated with conventional therapy (steroids, nonsteroidal anti-inflammatory drugs, biologics depending on disease).
For the disease-specific clinical evidence in rheumatoid arthritis, see the rheumatoid arthritis deep-dive. For the immune-modulation framework underlying the broader effects, see the immune modulation deep-dive. For the application to chronic Lyme disease and tick-borne co-infections (where NF-kB modulation of neuroinflammation is a key adjunctive role), see the Lyme-disease deep-dive.
What Rheumatology Reviewers Concluded in 2026
In 2026 a committee of the German Society for Rheumatology and Clinical Immunology (DGRh) published its review of 13 more herbal preparations frequently used in rheumatology, mostly as self-medication; cat's claw (Uncaria tomentosa) was one of them. For all the plant substances investigated, the committee found reports of anti-inflammatory or immune effects in cells and/or in animal models, but “the evidence for a clinically relevant benefit is very limited”. It concluded that none of the investigated preparations can be recommended for use in inflammatory joint diseases.
Key Research Papers
- Sandoval-Chacón M, Thompson JH, Zhang XJ, et al. (1998). Antiinflammatory actions of cat's claw: the role of NF-kappaB. Alimentary Pharmacology & Therapeutics 12(12): 1279–1289. — PubMed PMID: 9882039
- Sandoval M, Charbonnet RM, Okuhama NN, et al. (2000). Cat's claw inhibits TNF-alpha production and scavenges free radicals: role in cytoprotection. Free Radical Biology and Medicine 29(1): 71–78. — PubMed PMID: 10962207
- Sandoval M, Okuhama NN, Zhang XJ, et al. (2002). Anti-inflammatory and antioxidant activities of cat's claw (Uncaria tomentosa and Uncaria guianensis) are independent of their alkaloid content. Phytomedicine 9(4): 325–337. — PubMed PMID: 12120814
- Aguilar JL, Rojas P, Marcelo A, et al. (2002). Anti-inflammatory activity of two different extracts of Uncaria tomentosa (Rubiaceae). Journal of Ethnopharmacology 81(2): 271–276. — PubMed PMID: 12065162
- Allen-Hall L, Cano P, Arnason JT, et al. (2007). Treatment of THP-1 cells with Uncaria tomentosa extracts differentially regulates the expression of IL-1beta and TNF-alpha. Journal of Ethnopharmacology 109(2): 312–317. — PubMed PMID: 16959454
- Åkesson C, Lindgren H, Pero RW, et al. (2003). An extract of Uncaria tomentosa inhibiting cell division and NF-kappaB activity without inducing cell death. International Immunopharmacology 3(13–14): 1889–1900. — PubMed PMID: 14636838
- Mur E, Hartig F, Eibl G, Schirmer M (2002). Randomized double blind trial of an extract from the pentacyclic alkaloid-chemotype of Uncaria tomentosa for the treatment of rheumatoid arthritis. Journal of Rheumatology 29(4): 678–681. — PubMed PMID: 11950006
- Piscoya J, Rodriguez Z, Bustamante SA, et al. (2001). Efficacy and safety of freeze-dried cat's claw in osteoarthritis of the knee: mechanisms of action of the species Uncaria guianensis. Inflammation Research 50(9): 442–448. — PubMed PMID: 11603848
- Karin M, Greten FR (2005). NF-kappaB: linking inflammation and immunity to cancer development and progression. Nature Reviews Immunology 5(10): 749–759. — PubMed PMID: 16175180
- Lawrence T (2009). The nuclear factor NF-kappaB pathway in inflammation. Cold Spring Harbor Perspectives in Biology 1(6): a001651. — PubMed PMID: 20457564
- Snow AD, Castillo GM, Nguyen BP, et al. (2019). The Amazon rain forest plant Uncaria tomentosa (cat's claw) and its specific proanthocyanidin constituents are potent inhibitors and reducers of both brain plaques and tangles. Scientific Reports 9: 561. — PubMed PMID: 30728442
- Bhardwaj A, Aggarwal BB (2003). Receptor-mediated choreography of life and death. Journal of Clinical Immunology 23(5): 317–332. — PubMed PMID: 14601641 — a review of tumor necrosis factor-alpha and NF-kB signaling.
- Portalatin G, Shettigar S, Carrion-Rodriguez A, Medikayala S, Herlitz L, Sandy D, Gebreselassie SK, Bobart SA (2022). Ketogenic-Diet Shake Containing Uncaria tomentosa-Associated Acute Interstitial Nephritis. Case Reports in Nephrology and Dialysis 12(3): 219–225. — PubMed PMID: 36465572
- Keyßer G, Sander O, Frohne I, Pfeil A, Michalsen A, Schultz O, Reuß-Borst M, Seifert O; DGRh-Kommission für Komplementäre Heilverfahren und Ernährung (2026). Recommendations of the German Society for Rheumatology committee for complementary treatment and nutrition on phytotherapy: Supplement on the use of selected phytotherapeutic agents and herbal preparations in rheumatology: extension to include 13 medicinal plants [article in German]. Zeitschrift für Rheumatologie 85(8): 655–672. — PubMed PMID: 42448806
PubMed Topic Searches
Connections
- All Herbs
- Cat's Claw Overview
- Cat's Claw Benefits Hub
- Cat's Claw for Immune Modulation
- Cat's Claw for Rheumatoid Arthritis
- Cat's Claw for Lyme Disease
- Turmeric (Curcumin, NF-kB Inhibitor)
- Boswellia (5-LOX Inhibitor)
- Ginger (Anti-Inflammatory)
- Omega-3 Fatty Acids (SPM Pathway)
- Crohn's Disease
- Rheumatoid Arthritis
- Gut Healing
- Elimination Diet
- Vitamin D3 (Anti-Inflammatory)
- History