⚠ Evidence warning: Clinical trials or other evidence do not support the claim that blocking sweet taste with gymnema makes sugar cravings evaporate almost immediately, that repeated use can erode the sugar habit even without the herb, or that it works like a drug treatment for addiction during the first weeks of a diet change. This page keeps it as a report of what people, websites or other media say.
Gymnema for Sugar Cravings — The T1R2/T1R3 Sweet-Taste Blockade and Its Behavioral Applications
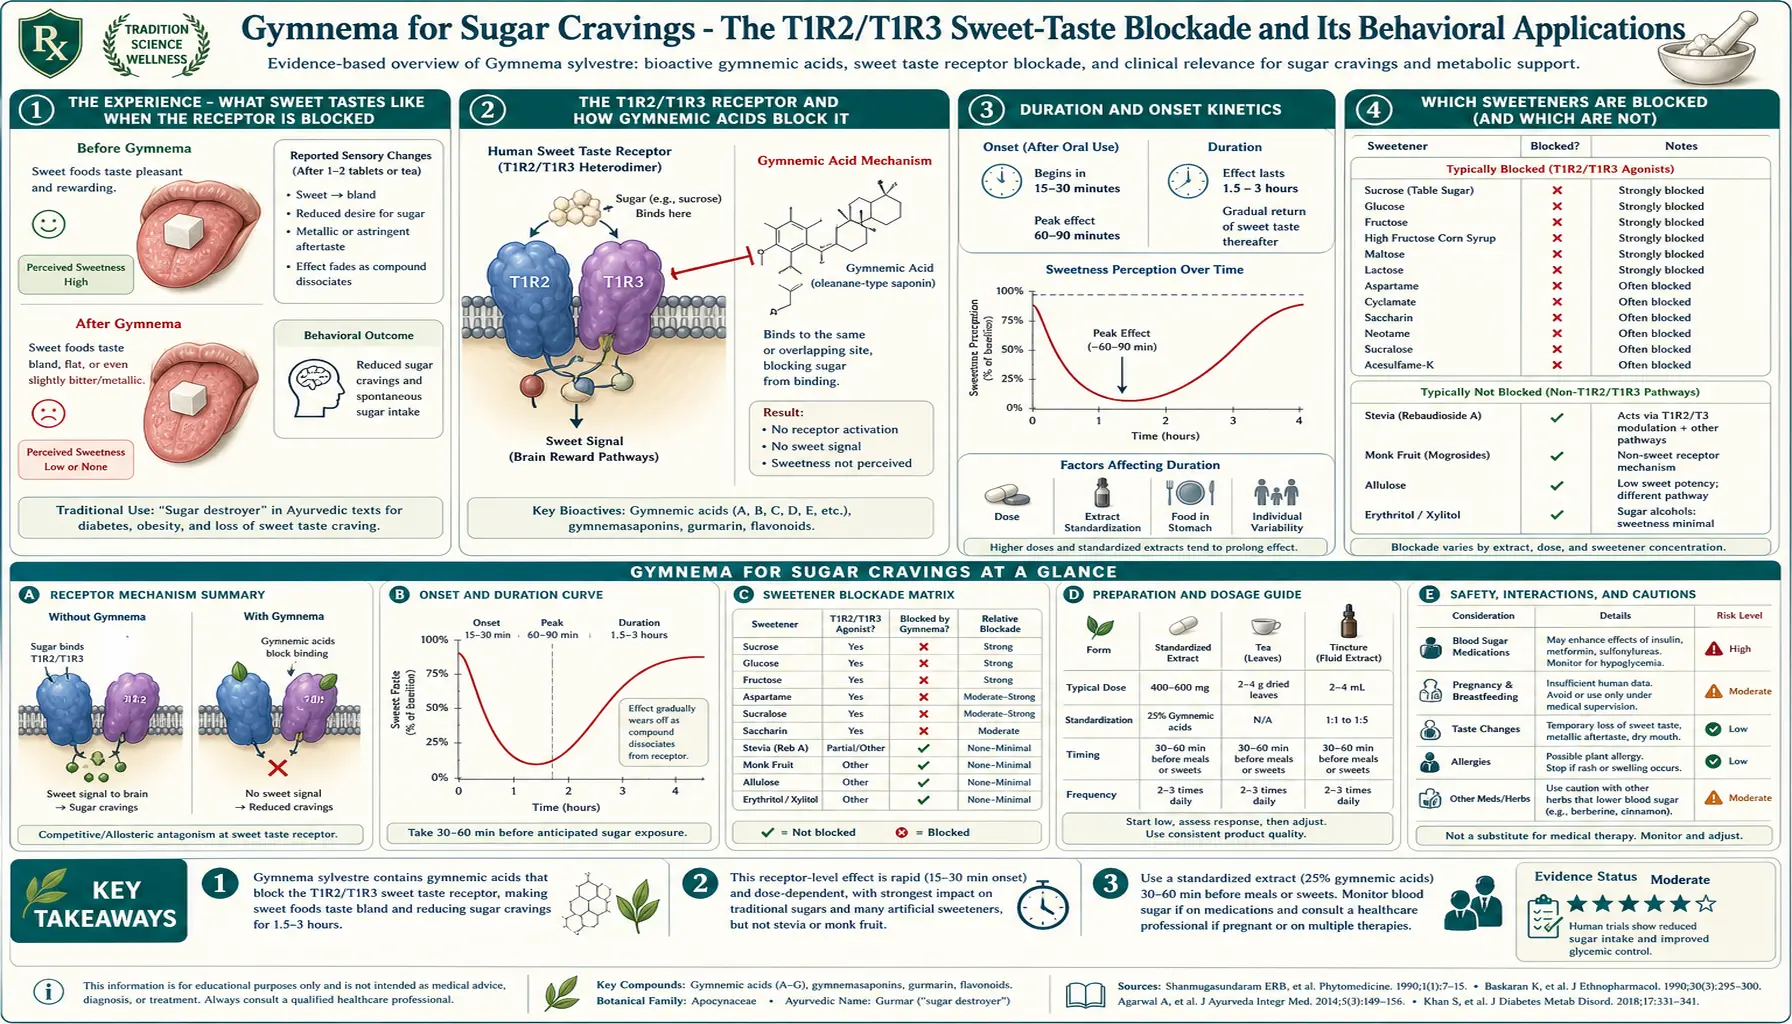
Few plant compounds produce the gymnemic acid effect (ziziphin from jujuba leaves is another): when a fresh Gymnema sylvestre leaf is chewed or a gymnema lozenge is held in the mouth for one minute, anything sweet tasted afterwards — sugar in coffee, a piece of chocolate, fresh fruit, even artificial sweeteners like aspartame and sucralose — loses most of its sweetness. In a taste-rating study, a gymnemic acid rinse cut the sweetness of sugar and aspartame to about one-seventh (14%) of normal. The food still has its other tastes (bitter, salty, sour, savory), but the sweetness channel is strongly muted, and in that study sweetness had climbed back to 63% of normal within 30 minutes. The molecular mechanism is a block of the T1R2/T1R3 sweet-taste receptor on type II taste-bud cells: gymnemic acids lodge in the part of its T1R3 subunit that sits inside the cell membrane. This curiosity has serious applications: it can be deployed as a willpower amplifier to interrupt sugar-craving episodes, has been extensively studied in the development of orexigenic-blocker drug candidates by major pharmaceutical companies, and provides a uniquely satisfying sensory demonstration to patients of how reflexive sugar consumption can be disrupted at the receptor level.
Table of Contents
- The Experience — What Sweet Tastes Like When the Receptor Is Blocked
- The T1R2/T1R3 Receptor and How Gymnemic Acids Block It
- Duration and Onset Kinetics
- Which Sweeteners Are Blocked (and Which Are Not)
- Behavioral Application — The Willpower Amplifier
- Controlled Trials of the Gymnema Mint
- Sugar Addiction and the Reward-Circuit Framework
- Big Pharma History — Sweet-Receptor Antagonist Drug Programs
- Practical Preparations — Leaves, Lozenges, Tea
- Combining Tongue Application with Systemic Dosing
- Cautions and Edge Cases
- Key Research Papers
- Connections
- Featured Videos
The Experience — What Sweet Tastes Like When the Receptor Is Blocked
The most informative way to understand gymnemic acid is to taste it work. The test people describe takes about 60 seconds: a gymnema lozenge or 1-2 g of leaf powder is chewed or held in the mouth, spread across the tongue, for one minute, then spat out or swallowed; after a further 60 seconds, a single granule of table sugar (or a small piece of chocolate, or a sip of orange juice) goes on the tongue.
People describe the result as startling. Sugar tastes like a coarse grain of sand — its texture, its slight cooling effect as it dissolves, perhaps a faint trace of mineral character come through, but very little sweetness: in a taste-rating study, a gymnemic acid rinse cut the sweetness of sugar (sucrose) and aspartame to 14% of what it had been before the rinse (Gent 1999). Chocolate becomes a flat, bitter, fatty paste. Orange juice tastes like watered-down lemon juice with no sugar to balance the acidity. Fruit becomes vegetable-like — the apple still tastes "appley" in some non-sweet way but is no more pleasant than chewing on celery.
The bitter and salty receptors are unaffected, so coffee still tastes like coffee, beer still tastes like beer, and pickles still taste like pickles. The sour and savory (umami) channels are also untouched. Only sweet is blocked. Artificial sweeteners are blocked just as effectively as table sugar — aspartame, sucralose, stevia, monk fruit, all lose most of their sweetness. Sugar alcohols like erythritol and xylitol, which work through the same T1R2/T1R3 receptor, are similarly silenced.
The blockade fades as the compound washes off the receptor. In the human taste-rating study, sweetness climbed back steadily and had reached 63% of its pre-rinse level within 30 minutes (Gent 1999); in chimpanzees, taste-nerve responses to sweeteners had recovered completely or nearly completely after one and a half hours (Hellekant 1985). People describe the return as starting with intensely sweet stimuli (sugar in solution) and gradually broadening back to subtle sweetness (mild fruit).
For most people, the single experience of this effect provides a more visceral understanding of how reflexive sugar consumption is than any amount of reading about it. Sugar tastes good. People describe the craving evaporating almost immediately when sugar does not taste good. This is the basis of the behavioral application discussed below.
The T1R2/T1R3 Receptor and How Gymnemic Acids Block It
The molecular machinery of sweet-taste perception was characterized in the early 2000s. The sweet-taste receptor is a heterodimer of two G-protein-coupled receptors: T1R2 (encoded by the TAS1R2 gene) and T1R3 (encoded by TAS1R3). Both subunits must be expressed for sweet taste to function. T1R3 also dimerizes with T1R1 to form the umami (savory) receptor, but the T1R2-containing dimer is exclusively sweet-specific.
The T1R2/T1R3 receptor sits on the surface membrane of type II taste-bud cells, which are clustered in the fungiform papillae on the front of the tongue, the foliate papillae on the sides, and the circumvallate papillae at the back. Binding of a sweetener to either subunit triggers G-protein-coupled signaling through the gustducin pathway, leading to depolarization of the type II cell, release of adenosine triphosphate (ATP) as a neurotransmitter onto the gustatory nerve fibers, and central perception of sweetness.
The receptor has an unusually large binding pocket that accommodates a remarkable variety of ligand structures: simple sugars (glucose, fructose, sucrose), sugar alcohols (sorbitol, mannitol, xylitol, erythritol), amino acids (glycine, alanine, in mild sweetness), sweet proteins (thaumatin, brazzein, monellin — some of the most intensely sweet substances known), and dozens of synthetic non-caloric sweeteners (saccharin, aspartame, acesulfame K, sucralose, neotame, advantame, steviol glycosides, mogrosides from monk fruit). All of these activate signaling by binding the same receptor complex.
Gymnemic acids block the receptor from inside its T1R3 subunit. A 2014 study used human kidney cells grown in the laboratory and engineered to carry the human sweet receptor (Sanematsu 2014). Gymnemic acids stopped these receptors from responding to sweet compounds. By swapping human and mouse receptor parts, the researchers found that the part of T1R3 that sits inside the cell membrane (its transmembrane domain) was mainly required for the effect. Changing single building blocks (amino acids) in that region showed that gymnemic acids act at the same spot as lactisole, another sweet blocker used by the food industry, and computer models placed gymnemic acids in a binding pocket within that membrane domain. Glucuronic acid, the building block that all gymnemic acids share, also reduced sweet responses on its own. The same compounds blocked the human receptor but not the mouse receptor, which matches the observation that gymnemic acids suppress sweet taste in people but not in mice.
The binding is not permanent. In the same cell study, the effect disappeared quickly when the cells were rinsed with gamma-cyclodextrin, and rinsing the human tongue with gamma-cyclodextrin also weakens the effect (Sanematsu 2014). Without such a rinse, the effect fades as the compound washes off the receptor, and sweetness perception returns.
The specificity for sweet over other taste modalities reflects the fact that bitter, salty, sour, and umami all use entirely different molecular machinery (the bitter receptors are a separate family of approximately 25 T2R G-protein-coupled receptors; salt and sour involve ion channels; umami uses the T1R1/T1R3 heterodimer). Gymnemic acids do not bind any of these, so non-sweet tastes are entirely preserved.
Duration and Onset Kinetics
What has been measured about the timing of the topical taste-blocking effect:
- Onset — users describe the effect appearing within about a minute of the compound touching the tongue.
- Strength — in a human taste-rating study, a gymnemic acid rinse cut the sweetness of sugar (sucrose) and aspartame to 14% of their pre-rinse level (Gent 1999). It is a strong reduction, not a total loss of sweetness.
- Decay — in the same study, sweetness climbed back in a straight line over the next 30 minutes, reaching 63% of the pre-rinse level (Gent 1999). The effect fades as the compound washes off the receptor; rinsing with gamma-cyclodextrin removes it quickly (Sanematsu 2014).
- Complete recovery — in chimpanzees, taste-nerve responses to sweeteners had recovered completely or nearly completely after one and a half hours (Hellekant 1985).
- Dose in the trials — the gymnema mint used in the controlled human trials held 4 mg of gymnemic acids per mint (Turner 2020).
- Repeated use — in a 14-day trial, the gymnema group ate fewer chocolates than the placebo group after the first dose (2.65 vs 3.15 bars), but after 14 days of daily use the two groups ate the same amount after dosing (2.77 vs 2.78 bars); the authors also reported no habituation to the mint over the 14 days (Turner 2022).
Practitioners describe extending the effect for a known temptation window (a long dinner with desserts, a holiday party with cake) by redosing at the 30-45 minute mark with a second lozenge or chewed leaf rather than taking a larger single dose at the outset. They describe the blockade as dose-dependent in intensity (a larger single dose producing a more complete and longer-lasting blockade), with little extra effect beyond one full standardized lozenge.
Which Sweeteners Are Blocked (and Which Are Not)
Effectively blocked (all activate T1R2/T1R3):
- Caloric sugars — sucrose (table sugar), glucose, fructose, lactose, maltose
- Sugar alcohols — sorbitol, mannitol, xylitol, erythritol, isomalt
- Synthetic non-caloric sweeteners — saccharin, aspartame, acesulfame potassium, sucralose, neotame, advantame
- Plant-derived non-caloric sweeteners — stevia (steviol glycosides), monk fruit (mogrosides), thaumatin
- Naturally sweet amino acids — glycine, D-alanine
- Sweet proteins — brazzein, monellin (miraculin is not a sweet protein: it is a taste-modifying protein that makes sour foods taste sweet, listed below)
Not blocked (do not act primarily through T1R2/T1R3):
- The miraculin effect itself — miraculin from miracle berry converts sourness to sweetness through a separate mechanism and is partially affected but not abolished
- Sweet sensations not mediated by T1R2/T1R3 — certain glycosides that activate the receptor through different binding modes may show partial preservation
- The "perceived sweetness" of foods with strong umami — some foods that are described as sweet partly through umami pathway interactions retain some pleasurable character
Other taste modalities are entirely preserved:
- Bitter — T2R family receptors, unaffected. Coffee tastes like coffee, dark chocolate tastes like bitter chocolate, beer tastes like beer.
- Salty — ion channels (ENaC), unaffected. Crisps, pretzels, soy sauce, all unchanged.
- Sour — ion channel mediated, unaffected. Lemon, vinegar, fermented foods unchanged.
- Umami — T1R1/T1R3, unaffected. Mushrooms, parmesan, broths, glutamate-containing foods unchanged.
- Pungent/spicy — TRPV1 and related channels, unaffected. Chili, ginger, mustard unchanged.
- Cool/menthol — TRPM8, unaffected. Mint chewing gum still tastes minty (though if it's a sweetened gum, the sweet component will be absent).
The result is that during gymnemic acid blockade, foods become more "naked" in their non-sweet character. A piece of milk chocolate becomes a bitter waxy fat. A piece of fruit becomes a fibrous source of organic acids. A glass of orange juice becomes acidic dishwater. This is precisely why the effect is so behaviorally useful: the foods that you might otherwise overconsume due to their sweetness become genuinely unappealing, not because of a willpower override but because the brain is simply not receiving the reward signal.
Behavioral Application — The Willpower Amplifier
The most practical use of the taste-blockade is what behavioral nutritionists call the "willpower amplifier" approach. Practitioners describe it in four steps:
- The temptation moments — the predictable times of day or social situations when sugar consumption tends to derail a dietary plan. Common patterns: the 3 PM office afternoon slump and the candy bowl, the post-dinner dessert craving, the office cake at colleagues' birthdays, the dessert menu after restaurant dinners, the children's leftover Halloween candy.
- A gymnema dose 5-15 minutes before exposure — a chewed leaf, a dissolved lozenge, or a 1-2 g leaf-powder dose held in the mouth for a minute
- The temptation itself — the foods are still physically present, but they now taste flat and unappealing rather than reward-triggering. The decision to skip them becomes trivial rather than effortful.
- The temptation window — practitioners describe the blockade as typically long enough to ride past the acute craving phase, and report that once the moment has passed, the craving for that specific food typically does not return that day.
The mechanism works because most non-clinical sugar cravings are reward-driven rather than nutritional. The brain's dopaminergic reward circuit (ventral tegmental area, nucleus accumbens) is strongly activated by sweetness signals from the tongue, and this activation drives the conscious experience of "craving" and the motor program of reaching for the food. When the sweetness signal does not arrive (because the receptor is blocked), the reward circuit gets no payoff for sugar consumption, and the behavior naturally extinguishes within the blockade window.
Practitioners propose that long-term, repeated use of this approach can produce conditioning effects. In their account, if gymnema blockade is consistently deployed at the 3 PM office candy bowl over several weeks, the associative learning that "reaching for office candy now produces no reward" can erode the habit even without the herb — the candy bowl stops being a salient stimulus. They describe this as consistent with the general principles of cue-extinction in addiction research.
Controlled Trials of the Gymnema Mint
Two controlled studies from New Zealand tested a gymnema mint (a tablet that dissolves in the mouth) holding 4 mg of gymnemic acids.
- Single-session study (2020) — in a single-blind crossover study of 56 healthy young men and women, eating the gymnema mint instead of a placebo mint cut the amount of chocolate eaten in the next 15 minutes by 0.48 bars (21.3%). People rated the chocolate as less pleasant and wanted less of it, and the drop in pleasantness and desire after the first serving was larger in people who said they had a "sweet tooth" (Turner 2020).
- 14-day study (2022) — in a randomized trial in 58 healthy adults, one group took the gymnema mint with a fiber and vitamin supplement and a healthy-eating guide for 14 days; the other group followed the same plan with a placebo mint. After the first dose (day 0), the gymnema group ate fewer chocolates than the placebo group (2.65 vs 3.15 bars). After the 14 days (day 15), the two groups ate the same amount (2.77 vs 2.78 bars), and food-frequency questionnaires showed no difference between the groups in the intake of 9 food categories at any time point (Turner 2022). The authors wrote that further research is needed to assess how long any effect of the 14-day plan lasts.
Sugar Addiction and the Reward-Circuit Framework
The framing of "sugar addiction" is contested in the academic literature — some researchers argue that sugar consumption meets formal addiction criteria (tolerance, withdrawal, compulsive use despite consequences, neuroadaptation in reward circuits), while others argue that the parallels to substances of abuse like alcohol or opioids are oversold and the phenomenology is better characterized as habit-driven hedonic consumption rather than true addiction.
For practical purposes, the distinction matters less than the observation that for some individuals, sugar consumption shows compulsive features: an inability to consume "just one cookie," a sustained pattern of consuming more than intended, return-to-baseline weight gain after diet attempts, and significant distress at the prospect of permanent abstinence. These patterns are particularly visible in patients with binge eating disorder, with reactive hypoglycemia, and with depressive disorders where sugar is being used as a self-medication strategy.
For these subgroups, gymnema provides a unique tool. Unlike most behavioral interventions (which require sustained conscious effort to deploy), gymnema works on the receptor level — the patient takes the lozenge, the receptor is blocked, the trigger food no longer tastes good, and the consumption decision becomes structurally different. Practitioners describe this as closer to the model of pharmacological addiction treatments (naltrexone for opioid use disorder, disulfiram for alcohol use disorder) than to most "willpower" interventions.
Clinical experience suggests gymnema is most useful for sugar-craving patients during the first 2-8 weeks of a dietary change, when willpower reserves are most challenged. After the initial habituation period, many patients can taper off active gymnema use as their cravings naturally diminish on lower-carbohydrate intake.
In a 2025 randomized crossover study of 32 healthy adults who described themselves as having a "sweet tooth" (high sweet-food eaters), using gymnema mints whenever they chose (up to 6 a day) for 14 days cut daily intake of sugar-sweetened drinks by 42% and overall sugar cravings by 28% compared with a placebo mint. Taking the mints at 3 fixed times a day and taking them as needed both lowered how pleasant people found chocolate and how much more of it they wanted; the drink and craving results were reported for the as-needed schedule (Hsiao 2025).
For the broader framing of metabolic and behavioral approaches to weight loss, see our Weight Loss deep-dive.
Big Pharma History — Sweet-Receptor Antagonist Drug Programs
The pharmaceutical industry has periodically explored sweet-receptor antagonists as candidate anti-obesity drugs, with gymnemic acids serving as both an inspiration and a chemical starting point. The logic: if dietary sugar overconsumption drives obesity, and if a molecule could selectively block sweet-taste perception (rendering sugars unappealing without affecting the overall food experience), patients might naturally reduce sugar intake and lose weight without the conscious effort of dietary restriction.
The programs that have been publicly described:
- Lactisole — a non-gymnemic acid sweet-receptor antagonist, originally discovered in coffee and developed as a food-industry sweetness-modulating ingredient (used at low doses to suppress unwanted sweetness in formulations). Has been studied as a research tool for sweet-receptor pharmacology but never advanced to clinical use for obesity.
- Flavor-company sweetness programs — in the early 2000s, biotechnology flavor companies developed sweetness enhancers (which lower the required sugar dose for a target perceived sweetness) and sweetness modulators including potential antagonists. Most of the clinical-grade work in this area was directed at sweetness enhancement (allowing food manufacturers to reduce sugar content without taste loss) rather than blockade.
- Various Big Pharma orexigenic-blocker programs — through the 2000s and 2010s, several major pharmaceutical companies explored sweet-receptor antagonists as candidate appetite suppressants. None have advanced to U.S. Food and Drug Administration (FDA) approval. The general challenges have included: poor oral bioavailability of compounds that work topically on the tongue, the difficulty of designing a molecule that blocks taste receptors but does not also block the same receptors expressed in the gut (where sweet-taste signaling regulates glucagon-like peptide-1 (GLP-1) secretion and other endocrine functions), and the conceptual problem that food-reward pathways involve multiple parallel inputs beyond sweetness alone.
- The arrival of glucagon-like peptide-1 agonists (semaglutide, tirzepatide) in the 2020s has substantially reduced the perceived market opportunity for sweet-receptor antagonists, since the glucagon-like peptide-1 class produces large weight losses (15-20% body weight) through a completely different mechanism and has demonstrated commercial viability.
The pharmaceutical interest has not resulted in marketed drugs, but the academic research generated by these programs has substantially clarified our understanding of how sweet-taste receptors work — including the detailed structural mapping of the T1R2/T1R3 receptor and the development of selective small-molecule antagonists used as research tools. Gymnemic acids remain the prototypical natural-product example and the only widely available sweet-receptor blocker in over-the-counter form.
Practical Preparations — Leaves, Lozenges, Tea
For the topical taste-blocking effect (as opposed to the systemic glycemic effect), several preparations work:
- Fresh or dried whole leaves — the most traditional preparation. One or two small leaves (approximately 1-2 g of leaf material) are chewed for 60 seconds, spread across the tongue, then spat out or swallowed. The leaves have a mildly bitter, vegetal taste that some find unpleasant. Fresh leaves are nearly impossible to obtain in the West; dried leaves can be sourced from Ayurvedic herb suppliers.
- Chewable lozenges (gymnema sucrosa / gymnema chews) — the most convenient and widely available form. Several manufacturers produce standardized lozenges containing 50-200 mg of standardized gymnema extract (25% gymnemic acids), often in a slightly minty base to mask the herbal flavor. They are held in the mouth for 1-2 minutes, then chewed or swallowed. The mint used in the controlled trials held 4 mg of gymnemic acids (Turner 2020).
- Standardized extract powder — a heaping pinch (approximately 200-500 mg) placed under the tongue and held for 60-90 seconds. Effective but less convenient than lozenges.
- Gymnema tea — brewed from dried leaves at approximately 1-2 g per cup for 10 minutes. The hot tea contacts the tongue and produces the taste-blocking effect, but the dilute concentration limits intensity compared to direct leaf or extract application. Useful as a pleasant gentle pre-meal beverage.
- Tinctures — less effective than direct leaf or extract application because the alcohol vehicle washes off the tongue quickly, limiting contact time. Generally described as the weakest form for the topical effect.
Cost considerations: a 30-day supply of chewable lozenges typically runs $15-25 USD, which is affordable for daily use through a difficult dietary transition. Standardized extract capsules used for the systemic glycemic effect can be opened and the powder used sublingually if the user wants both effects from a single product.
Combining Tongue Application with Systemic Dosing
The two clinical applications of gymnema — the topical taste-blockade and the systemic glycemic effect — can be combined without conflict. A typical protocol for a patient with type 2 diabetes who also struggles with sugar cravings:
- Twice daily — standardized GS4 extract 400 mg with breakfast and dinner, swallowed as a capsule, for the systemic glycemic effect (see the Blood Sugar deep-dive for the full dosing rationale)
- As needed — a gymnema chewable lozenge held in the mouth 5-15 minutes before any expected sugar-craving moment, for the topical taste-blockade
The systemic capsule does not produce the topical taste effect (it passes through the mouth too quickly and in the wrong vehicle), so the lozenge component is genuinely additive. The total daily gymnemic acid exposure remains well below safety thresholds even with frequent topical use, because the topical doses are small.
One important caveat: each topical dose contributes a small additional systemic absorption of gymnemic acid through the oral mucosa and (if swallowed) through the gastrointestinal (GI) tract. For patients on insulin or sulfonylureas, frequent topical use adds to total daily gymnema exposure, and gymnema adds to the glucose-lowering effect of these drugs, which can push blood sugar too low (see the hypoglycemia cautions in the Blood Sugar deep-dive).
Cautions and Edge Cases
- Hypoglycemia risk in patients on insulin or sulfonylureas — even topical gymnemic acid use contributes some systemic absorption. Gymnema adds to the glucose-lowering effect of insulin and sulfonylureas, which can cause low blood sugar (hypoglycemia); the hypoglycemia cautions are set out in the Blood Sugar deep-dive.
- Pregnancy and lactation — there is no good safety data on use in pregnancy or breastfeeding, including occasional use.
- Persistent taste disturbance — very rare reports describe taste alteration lasting beyond the usual hour or two, usually resolving within 24 hours. A taste change (dysgeusia) lasting longer than that is not a described effect of gymnema.
- Inadvertent dietary effects — some patients report unintentionally reduced food enjoyment for foods they had not intended to reduce (such as fruit or whole grains). The blockade is non-selective for sweetness source. Users describe timing the lozenge dose to the temptation window rather than across a healthy meal.
- Effect on the social experience of food — using gymnema at a birthday party or family dinner where dessert is offered may produce awkward social moments if the host has prepared something they hoped the guest would enjoy. Users describe needing some tact in these settings.
- Eating disorders — for patients with anorexia nervosa or restrictive eating disorders, gymnema is generally contraindicated because it can reinforce avoidance patterns rather than addressing the underlying disorder. For binge eating disorder, careful use under therapy supervision can be appropriate.
- Children — there is no good safety data on use in children.
- Drug interactions — theoretical interaction with any medication absorbed through buccal mucosa, though clinically reported interactions are minimal.
Key Research Papers
- Imoto T, Miyasaka A, Ishima R, Akasaka K (1991). A novel peptide isolated from the leaves of Gymnema sylvestre — I. Characterization and its suppressive effect on the neural responses to sweet taste stimuli in the rat. Comparative Biochemistry and Physiology A, Comparative Physiology 100(2): 309–314. Identified gurmarin as a second sweet-suppressing principle. — PubMed PMID: 1685952
- Sigoillot M, Brockhoff A, Meyerhof W, Briand L (2012). Sweet-taste-suppressing compounds: current knowledge and perspectives of application. Applied Microbiology and Biotechnology 96(3): 619–630. Comprehensive review of gymnemic acids and other sweet-receptor antagonists. — PubMed PMID: 22983596
- Hellfritsch C, Brockhoff A, Stähler F, Meyerhof W, Hofmann T (2012). Human psychometric and taste receptor responses to steviol glycosides. Journal of Agricultural and Food Chemistry 60(27): 6782–6793. Provides the T1R2/T1R3 mechanistic framework used to interpret gymnemic acid antagonism. — PubMed PMID: 22616809
- Suttisri R et al. (1995). Plant-derived triterpenoid sweetness inhibitors. Journal of Ethnopharmacology. Classification of gymnema-related saponins. — PubMed PMID: 7564423
- Gent JF, Hettinger TP, Frank ME, Marks LE (1999). Taste confusions following gymnemic acid rinse. Chemical Senses 24(4): 393–403. Human taste ratings: sweetness of sucrose and aspartame fell to 14% after the rinse and recovered to 63% within 30 minutes. — PubMed PMID: 10480675
- Kurihara Y (1992). Characteristics of antisweet substances, sweet proteins, and sweetness-inducing proteins. Critical Reviews in Food Science and Nutrition. Classic review covering gymnemic acids alongside other taste modulators. — PubMed PMID: 1418601
- Ye W, Liu X, Zhang Q, Che CT, Zhao S (2001). Antisweet saponins from Gymnema sylvestre. Journal of Natural Products 64(2): 232–235. Structural analysis of new members of the gymnemic acid family. — PubMed PMID: 11430009
- Nelson G et al. (2001). Mammalian sweet taste receptors. Cell. The foundational paper identifying T1R2/T1R3 as the mammalian sweet-taste receptor. — PubMed PMID: 11509186
- Margolskee RF (2002). Molecular mechanisms of bitter and sweet taste transduction. Journal of Biological Chemistry. Reviews the gustducin signaling cascade that gymnemic acids interrupt. — PubMed PMID: 11696554
- Sanematsu K et al. (2014). Molecular mechanisms for sweet-suppressing effect of gymnemic acids. Journal of Biological Chemistry. Detailed structural and mutational analysis of the gymnemic acid binding site on T1R2/T1R3. — PubMed PMID: 25056955
- Hellekant G, af Segerstad CH, Roberts T, van der Wel H, Brouwer JN, Glaser D, Haynes R, Eichberg JW (1985). Effects of gymnemic acid on the chorda tympani proper nerve responses to sweet, sour, salty and bitter taste stimuli in the chimpanzee. Acta Physiologica Scandinavica 124(3): 399–408. Taste-nerve recordings in the chimpanzee. — PubMed PMID: 4050473
- Turner S, Diako C, Kruger R, Wong M, Wood W, Rutherfurd-Markwick K, Ali A (2020). Consuming Gymnema sylvestre Reduces the Desire for High-Sugar Sweet Foods. Nutrients 12(4): 1046. Crossover study of a 4 mg gymnemic acid mint in 56 young adults. — PubMed PMID: 32290122
- Turner S, Diako C, Kruger R, Wong M, Wood W, Rutherfurd-Markwick K, Stice E, Ali A (2022). The Effect of a 14-Day Gymnema sylvestre Intervention to Reduce Sugar Cravings in Adults. Nutrients 14(24): 5287. Randomized 14-day trial in 58 adults. — PubMed PMID: 36558446
- Hsiao WH, Kruger R, Diako C, Nelson I, Stice E, Ali A (2025). The effect of a 14-day Gymnema sylvestre intervention to reduce sugar intake in people self-identifying with a sweet tooth. Appetite 207: 107871. Randomized crossover study in 32 adults. — PubMed PMID: 39855349