Gymnema for Blood Sugar — Type 1 & Type 2 Diabetes, the GS4 Extract, and the Shanmugasundaram Trials
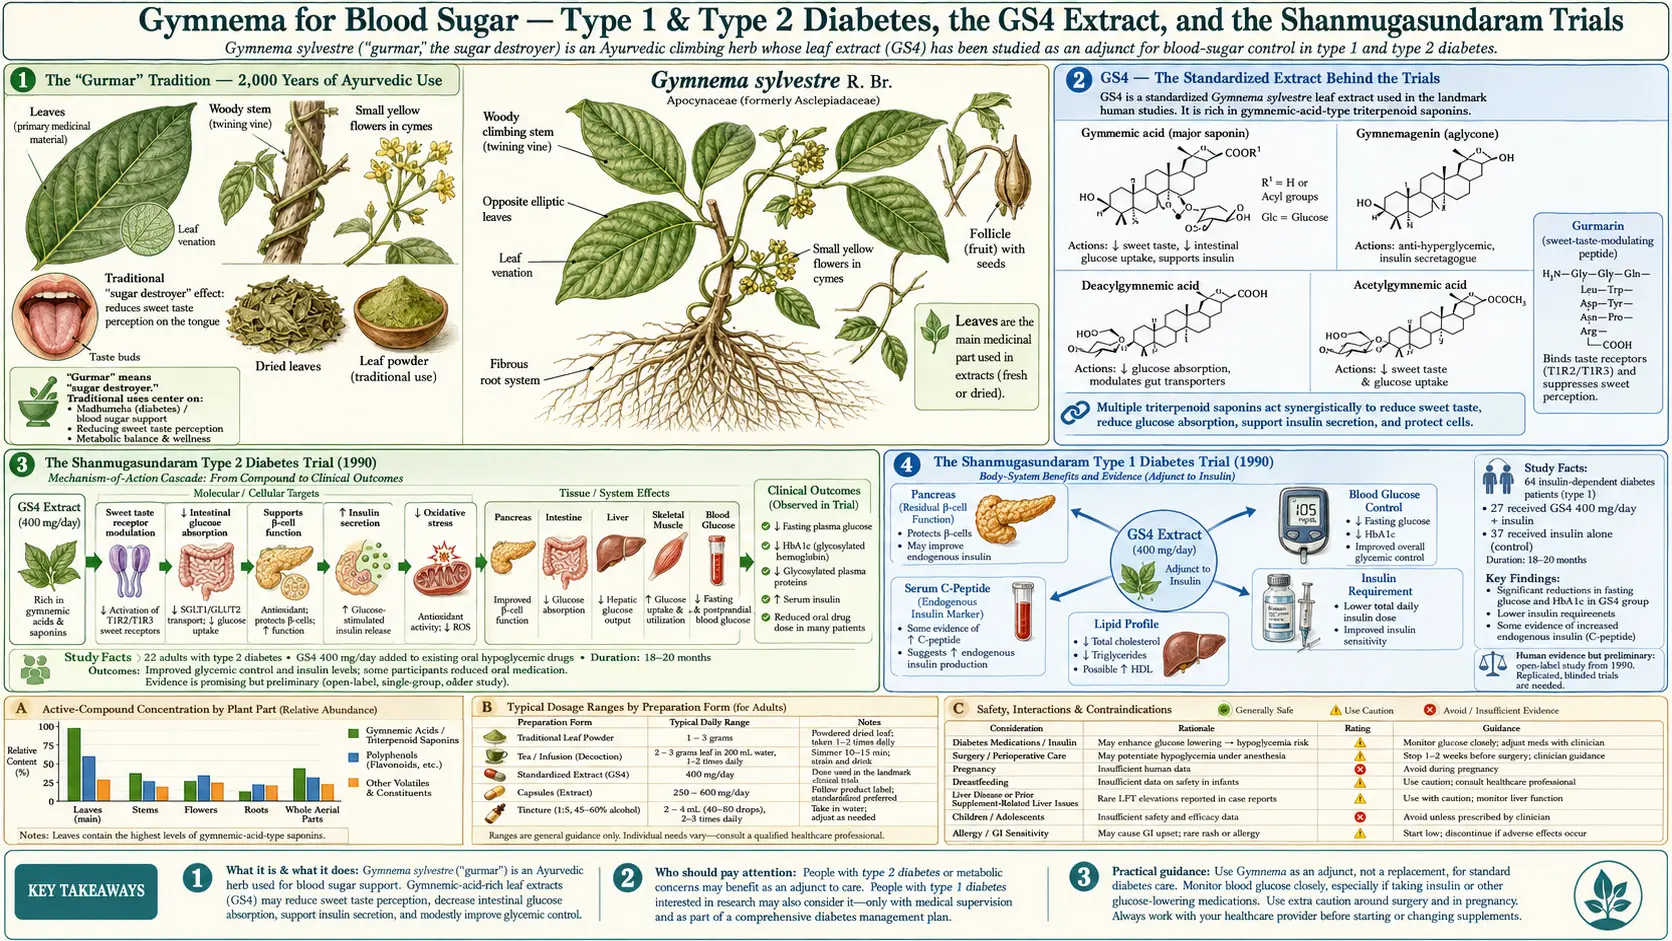
Of all the antidiabetic herbs in the global pharmacopoeia, Gymnema sylvestre — the Indian "gurmar" or "sugar destroyer" — has the deepest traditional lineage (more than 2,000 years of documented Ayurvedic use for madhumeha, "honey urine") and one of the most credible modern clinical evidence bases. The two pivotal Shanmugasundaram trials in 1990 established that the standardized GS4 extract (25% gymnemic acids) reduced hemoglobin A1c (HbA1c), fasting glucose, and insulin requirements in both type 1 and type 2 diabetics. This deep-dive walks through the trials, the four mechanisms of action (sweet-receptor mimicry, intestinal glucose absorption inhibition, insulin secretion enhancement, and possible beta-cell regeneration), the doses used in trials and practice, and the low-blood-sugar risks for people already on insulin or sulfonylureas.
Table of Contents
- The "Gurmar" Tradition — 2,000 Years of Ayurvedic Use
- GS4 — The Standardized Extract Behind the Trials
- The Shanmugasundaram Type 2 Diabetes Trial (1990)
- The Shanmugasundaram Type 1 Diabetes Trial (1990)
- The Four-Mechanism Model
- How Gymnema and Glipizide Differ
- Stacking with Metformin & Other Antidiabetics
- Hemoglobin A1c Changes Reported in Studies
- Doses Used in Trials and Practice
- Low-Blood-Sugar and Liver Risks
- Key Research Papers
- Connections
- Featured Videos
The "Gurmar" Tradition — 2,000 Years of Ayurvedic Use
The Hindi name gurmar translates literally to "sugar destroyer," and the Sanskrit Ayurvedic texts use the synonym meshashringi (literally "ram's horn," after the shape of the seed pods). The herb appears in the Sushruta Samhita and Charaka Samhita — two foundational Ayurvedic texts dated approximately 600 BCE to 200 CE — under the indication madhumeha, literally "honey urine," which is the same disease modern medicine calls diabetes mellitus. Sushruta and Charaka described madhumeha with such accuracy that the descriptions are still clinically recognizable: polyuria, polydipsia, weight loss, slow wound healing, susceptibility to skin infections, and the sweet smell of the urine that attracted ants.
Classical Ayurveda divided madhumeha into approximately twenty subtypes, which modern interpreters have mapped onto type 1 diabetes (thin, young, rapid onset) and type 2 diabetes (overweight, older, gradual onset). Gymnema was indicated for both. The traditional preparation was a powder of dried leaves or a decoction made by boiling the leaves in water for approximately ten minutes, with typical doses described as the weight of one to four small coins (roughly 2-8 grams) once or twice daily.
The traditional usage included a key behavioral observation: physicians noted that chewing the fresh leaf abolished the perception of sweetness on the tongue for approximately one hour, and used this as both a diagnostic confirmation of the plant's identity and a practical intervention for patients who could not control their cravings for sweets. This is the same mechanism that modern researchers later traced to the gymnemic acid blockade of the T1R2/T1R3 sweet-taste receptor — see the Sugar Cravings deep-dive for the full molecular explanation.
Western scientific interest dates to the late 19th century, when British colonial physicians in India observed Ayurvedic practitioners using gymnema with apparent clinical success in diabetic patients. The first English-language pharmacological investigation was published by Edgeworth in 1852, and the first chemical isolation of gymnemic acid was reported by Hooper in 1887. Sustained modern research, however, did not begin until the Shanmugasundaram group at the University of Madras (now Anna University) launched the systematic clinical trials in the 1980s that established the modern evidence base.
GS4 — The Standardized Extract Behind the Trials
The standardized extract used in essentially all of the modern clinical evidence is called GS4, developed by the Shanmugasundaram research group and later sold by commercial manufacturers. GS4 is a hydroalcoholic extract of Gymnema sylvestre leaf, standardized to contain at least 25% gymnemic acids by weight (the gymnemic acid content of unprocessed dried leaf is typically 3-6%, so GS4 represents an approximately 4-8× enrichment).
The 25% gymnemic acid figure was chosen because it produced consistent clinical effects at a manageable daily dose (400 mg twice daily, or 800 mg/day total). Lower concentrations of gymnemic acids required impractically large doses; higher concentrations produced no additional benefit beyond plateau. Most contemporary "gymnema 400 mg" supplements on the market are either GS4 itself or a similar standardized extract with the same 25% gymnemic acid label claim.
The important practical implication: unstandardized whole-leaf gymnema is not pharmacologically equivalent to GS4. A 400 mg capsule of whole-leaf powder contains only 12-24 mg of gymnemic acids, while a 400 mg capsule of GS4 contains 100 mg. The trials used the standardized extract, not whole leaf. Whole-leaf preparations are described as needing 4-12 g/day to deliver an equivalent gymnemic acid dose.
Beyond GS4, several other standardized extracts have appeared in more recent trials, including a branded high-molecular-weight gymnema extract (tested at 1 g/day for 60 days in a small group of people with type 2 diabetes) and various proprietary blends combining gymnema with chromium, cinnamon, berberine, or bitter melon. The clinical evidence for these newer formulations is generally less mature than for GS4, though the underlying gymnemic acid pharmacology is the same.
The Shanmugasundaram Type 2 Diabetes Trial (1990)
The landmark study for gymnema in type 2 diabetes is Baskaran K, Kizar Ahamath B, Radha Shanmugasundaram K, Shanmugasundaram ER (1990). Antidiabetic effect of a leaf extract from Gymnema sylvestre in non-insulin-dependent diabetes mellitus patients. Journal of Ethnopharmacology 30(3):295-300.
Design: 22 type 2 diabetic patients already on conventional oral hypoglycemic medication (sulfonylureas) received GS4 400 mg/day in addition to their existing regimen for 18-20 months. A control group of 25 type 2 diabetics on conventional medication alone was followed for comparison.
Results in the GS4 group:
- Fasting blood glucose decreased significantly from baseline
- Hemoglobin A1c (glycosylated haemoglobin) and glycosylated plasma proteins decreased significantly
- Serum lipids (total cholesterol, triglycerides, low-density lipoprotein, LDL) improved
- 5 of the 22 patients were able to discontinue conventional medication entirely and maintain glycemic control on GS4 monotherapy
- Conventional drug doses could be decreased during GS4 use
- Serum insulin levels increased, suggesting either preserved beta-cell function or actual regeneration
The control group on conventional medication alone showed no significant change in hemoglobin A1c over the same time period, providing a within-trial comparator that ruled out simple regression to the mean or placebo effects.
This trial has been criticized for its open-label design and small sample size, but the magnitude of the effects observed — particularly the medication discontinuation in 23% of subjects — combined with the long 18-20 month follow-up represent compelling preliminary evidence. Subsequent smaller trials and case series have largely replicated the findings, though no large randomized controlled trial of GS4 in type 2 diabetes has been completed to the standards required for U.S. Food and Drug Administration (FDA) drug approval. A 2009 review in Canadian Family Physician summed up the human evidence this way: gymnema lowered hemoglobin A1c in 2 small open-label trials (trials where patients and researchers knew who got the herb), and no trial of gymnema or any other complementary or alternative medicine (CAM) remedy had looked at diabetes complications such as eye, kidney, nerve or heart disease.
The Shanmugasundaram Type 1 Diabetes Trial (1990)
The companion trial in type 1 diabetics is Shanmugasundaram ER, Rajeswari G, Baskaran K, Kumar BR, Shanmugasundaram KR, Ahmath BK (1990). Use of Gymnema sylvestre leaf extract in the control of blood glucose in insulin-dependent diabetes mellitus. Journal of Ethnopharmacology 30(3):281-294.
Design: 27 type 1 diabetic patients on insulin therapy received GS4 400 mg/day in addition to their insulin regimen for 6-30 months (mean approximately 18 months). A control group of 37 type 1 diabetics on insulin alone was followed for comparison.
Results in the GS4 group:
- Insulin requirements came down
- Fasting blood glucose decreased
- Hemoglobin A1c decreased, but it and glycosylated plasma protein levels stayed higher than in people without diabetes
- Serum lipids improved
- Serum C-peptide increased — a critical finding because C-peptide is a marker of endogenous (pancreatic) insulin production, and rising C-peptide in established type 1 diabetics suggests either preservation of remaining beta-cell mass or actual regeneration of new beta cells. The control group on insulin alone showed no C-peptide change.
The C-peptide finding is the basis for the (still preliminary) claim that gymnema may stimulate beta-cell regeneration in type 1 diabetes — an effect not observed with any conventional pharmaceutical antidiabetic. This finding has not been definitively replicated in subsequent trials with the rigor required to establish causation, but the mechanism has been demonstrated in rodent models of streptozotocin-induced diabetes, where GS4 administration partially restored islet histology after beta-cell destruction.
In this trial GS4 was added to insulin, never used in place of it; insulin doses came down as blood sugar fell, which is why glucose was checked closely. In type 1 diabetes the body makes almost no insulin of its own, so stopping insulin leads to diabetic ketoacidosis, which can kill within days; gymnema has never been tested as a replacement for insulin.
The Four-Mechanism Model
Modern pharmacology has identified four distinct molecular mechanisms by which gymnemic acids reduce blood glucose. Unlike most antidiabetic drugs, which work through a single mechanism (metformin: hepatic gluconeogenesis suppression; sulfonylureas: beta-cell adenosine triphosphate-sensitive potassium channel blockade; sodium-glucose cotransporter-2 (SGLT2) inhibitors: renal glucose reabsorption inhibition), gymnema appears to combine effects across the entire glucose-handling axis.
- Sweet-receptor mimicry blocking intestinal glucose absorption — gymnemic acids share enough geometric similarity with glucose that they competitively inhibit the SGLT1 sodium-glucose cotransporter in the small-intestinal brush border. The result is reduced glucose absorption from the meal and a flatter postprandial glucose curve. This effect kicks in within 30-60 minutes of an oral dose taken with food.
- Insulin secretion enhancement — in isolated pancreatic islet preparations and in vivo, gymnema extracts increase glucose-stimulated insulin secretion. The mechanism is incompletely characterized but appears to involve direct membrane effects on the beta cell. This is part of why fasting and postprandial insulin levels rise in subjects on chronic GS4. A 1999 lab study (rat islets and beta-cell lines) found that GS4 released insulin by making beta-cell membranes leaky — the cells took up more trypan-blue dye, a sign of damaged membranes — “rather than by stimulating exocytosis by regulated pathways” (the normal, controlled way beta cells release insulin). Whether this leakiness matters for safety in people is an open question. A 2010 study of a newer high-molecular-weight extract found real stimulation of insulin secretion from isolated human islets, and higher insulin and C-peptide with lower fasting and after-meal glucose in a small group of people with type 2 diabetes taking 1 g/day for 60 days.
- Inhibition of hepatic gluconeogenesis — preliminary evidence suggests gymnemic acid effects on glucose-6-phosphatase, the rate-limiting enzyme in the final step of hepatic glucose production. This effect is smaller than that of metformin but contributes to the reduced fasting glucose observed in chronic gymnema use.
- Possible beta-cell preservation or regeneration — the most striking and most preliminary mechanism, supported primarily by the rising C-peptide observed in the Shanmugasundaram type 1 trial and by histological evidence of partial islet restoration in rodent streptozotocin models. The molecular mechanism is hypothesized to involve modulation of beta-cell apoptosis pathways and possibly stimulation of pancreatic stem-cell differentiation, but this is incompletely characterized.
The combined effect of these four mechanisms is the approximately 0.5-1.0 percentage point hemoglobin A1c reduction observed in controlled trials — a magnitude comparable to a low-dose metformin or sulfonylurea, but achieved by a plant. The multi-mechanism profile also helps explain why gymnema combines well with other antidiabetics: its mechanisms are largely orthogonal to those of metformin (hepatic gluconeogenesis), sulfonylureas (different beta-cell mechanism), and sodium-glucose cotransporter-2 inhibitors (renal rather than intestinal SGLT).
How Gymnema and Glipizide Differ
Glipizide is a second-generation sulfonylurea drug for type 2 diabetes. The differences described between the two agents:
- Hypoglycemia risk — glipizide is well-documented to cause hypoglycemia, particularly in patients who skip meals or exercise unexpectedly. Gymnema produces hypoglycemia far less reliably on its own (the magnitude of glucose lowering is smaller and slower-onset), but combines additively with sulfonylureas if both are used together.
- Weight effects — glipizide promotes modest weight gain (the insulin secretion increases drive lipogenesis). Gymnema is weight-neutral or modestly weight-reducing (see the Weight Loss deep-dive).
- Beta-cell trajectory — long-term sulfonylurea use accelerates beta-cell exhaustion in type 2 diabetes, contributing to the progressive insulin requirement seen in most type 2 diabetics over years. Gymnema may have the opposite effect (the C-peptide-preserving finding from the Shanmugasundaram trials), though this requires confirmation in larger studies.
- Cardiovascular effects — sulfonylureas have a checkered cardiovascular safety record (the UGDP trial in 1970 raised concerns about increased CV mortality with tolbutamide that were never fully resolved). Gymnema has no documented adverse cardiovascular signal and may produce modest favorable lipid effects.
Gymnema is described as a weaker glucose-lowering agent than glipizide with a milder side-effect profile, and the C-peptide findings raise the possibility of longer-term benefits on beta-cell health that sulfonylureas do not have; no trial has compared the two directly.
Stacking with Metformin & Other Antidiabetics
Gymnema combines well with metformin because their mechanisms are largely orthogonal. Metformin's primary effect is on hepatic gluconeogenesis; gymnema's primary effects are on intestinal glucose absorption and beta-cell insulin secretion.
Other compatible combinations:
- Gymnema + chromium (200-1000 mcg/day) — chromium enhances insulin receptor signaling. The combination shows additive effects in pilot trials. See Chromium.
- Gymnema + cinnamon (1-6 g/day) — cinnamon has its own modest insulin-sensitizing effects via cinnamaldehyde and proanthocyanidins. The combination is mild and well-tolerated. See Cinnamon.
- Gymnema + berberine (500 mg 2-3×/day) — the most potent combination. Berberine is the most metformin-like of the herbal antidiabetics, working through AMP-activated protein kinase (AMPK) activation. Both lower blood sugar, so together with insulin or sulfonylureas the risk of low blood sugar adds up. See Berberine.
- Gymnema + bitter melon (Momordica charantia) — both have insulin-secreting and insulin-mimetic effects; the combination is used in traditional Indian medicine. See Bitter Melon.
- Gymnema + fenugreek — fenugreek's soluble fiber slows carbohydrate absorption, complementing gymnema's direct glucose absorption inhibition. See Fenugreek.
Hemoglobin A1c Changes Reported in Studies
Figures described from the published evidence and from practice:
- Gymnema GS4 400-800 mg/day, monotherapy — hemoglobin A1c reduction of approximately 0.5-1.0 percentage points over 3-6 months in type 2 diabetics with baseline hemoglobin A1c 7.5-9.0%
- Gymnema as add-on to insulin (type 1 or type 2) — insulin requirement reduction of 10-30% over 6-18 months, with maintained or improved glycemic control
- Time to effect — partial effects evident within 4-6 weeks; full effects develop over 12-24 weeks
- Subjects unlikely to respond — advanced type 2 diabetics with near-complete beta-cell failure (very low C-peptide, requiring high-dose insulin) may see minimal effects, since two of gymnema's four mechanisms depend on residual beta-cell function
Why hemoglobin A1c matters: in the UK Prospective Diabetes Study (UKPDS 35), an observational analysis of 3,642 people with type 2 diabetes, each 1 percentage point lower hemoglobin A1c was associated with about 37% fewer microvascular complications (damage to the small blood vessels of the eyes, kidneys and nerves; 95% range 33-41%). This is an association in people followed over time, not a tested effect of any one treatment, and no gymnema trial has measured complications.
Two meta-analyses (studies that pool earlier studies) give the wider picture:
- 2021, 10 studies, 419 people with type 2 diabetes — gymnema lowered fasting blood sugar, after-meal blood sugar, hemoglobin A1c, triglycerides and total cholesterol compared with the start of each study. The results differed a great deal between studies (I², a measure of disagreement between studies, up to 99%), and the comparison was before-and-after, not against a placebo.
- 2023, randomized trials only (6 trials) — gymnema lowered triglycerides, total cholesterol, LDL cholesterol, fasting blood sugar and diastolic blood pressure. The authors point to large differences between studies, low study quality and little diversity among the people studied, and call for larger, longer, high-quality trials.
For patients monitoring their progress, see our hemoglobin A1c page and Fasting Insulin page for the lab interpretation framework.
Doses Used in Trials and Practice
The doses described in clinical practice and in the trials (the 1990 trials used GS4 400 mg/day):
- Standard adult dose, type 2 diabetes — GS4 400 mg twice daily with the largest two meals of the day. Total 800 mg/day. Onset of full effect 12-24 weeks.
- Maintenance / mild dysglycemia — GS4 200-400 mg once or twice daily, depending on baseline glucose control. Used for pre-diabetes (hemoglobin A1c 5.7-6.4%) or for type 2 diabetics in good control who want additional support.
- Type 1 diabetes adjunct — GS4 200-400 mg twice daily, described as started at the lower dose and raised over 4-8 weeks, with frequent glucose checks and insulin doses lowered ahead of time; in the 1990 type 1 trial it was added to insulin under the study team's care.
- Whole-leaf preparation — 4-12 g/day of dried leaf in capsules or as tea (10-minute steep) provides an approximate equivalent dose, though clinical effects are typically more variable.
- Timing relative to meals — described as taken with the meal or 15-30 minutes before, so peak gymnemic acid levels in the gut coincide with the postprandial glucose absorption window.
- Duration of treatment — no defined maximum. The Shanmugasundaram trials ran 18-30 months and reported no safety concerns. Practitioners describe long-term use, with periodic reassessment of glycemic control and medication adjustment.
- Combining with the sweet-taste-blocking application — for the craving-interruption effect, a chewable lozenge or 1-2 g of leaf powder held in the mouth 1-2 minutes before exposure to a sweet temptation is described as providing the taste blockade without affecting the chronic glycemic effect of the systemic dose. See the Sugar Cravings deep-dive.
Low-Blood-Sugar and Liver Risks
Gymnema lowers blood glucose. This is the desired effect. It can also become a dangerous effect when combined with other glucose-lowering treatments without dose adjustment.
- Insulin — type 1 or type 2 diabetics on insulin who start gymnema will, over weeks to months, see their glucose drift downward. Without prospective insulin dose reduction, this manifests as increasingly frequent hypoglycemic events — some of which can be severe (loss of consciousness, seizures, falls in elderly patients). Signs of low blood sugar include shaking, sweating, a fast heartbeat, confusion and hunger; severe low blood sugar (fainting, seizures) is treated by hospitals as an emergency. The safeguards described for this combination are closer glucose checks (a continuous glucose monitor or 4-6 fingersticks daily), insulin doses lowered according to glucose trends, and a glucagon emergency kit at hand.
- Sulfonylureas (glipizide, glyburide, glimepiride) — the additive hypoglycemia risk is comparable to insulin. The same monitoring and dose-adjustment plan applies. Practitioners describe lowering the sulfonylurea dose by 25-50% over the first 8-12 weeks.
- Meglitinides (repaglinide, nateglinide) — similar mechanism to sulfonylureas, similar additive risk.
- Glucagon-like peptide-1 (GLP-1) receptor agonists (semaglutide, liraglutide) and the dual GIP (glucose-dependent insulinotropic polypeptide) and GLP-1 receptor agonist tirzepatide — do not typically cause hypoglycemia on their own, but combined with insulin or sulfonylureas can. The same monitoring applies.
- Sodium-glucose cotransporter-2 inhibitors (empagliflozin, dapagliflozin) — low intrinsic hypoglycemia risk, but the diuretic and ketoacidosis risks combine unfavorably with poorly-controlled diet. Gymnema combination is described as carrying low hypoglycemia risk with standard monitoring.
- Metformin alone — very low intrinsic hypoglycemia risk. The combination with gymnema is described as low-risk for hypoglycemia, with routine hemoglobin A1c follow-up.
- Reactive hypoglycemia, post-bariatric dumping syndrome — gymnema can worsen these conditions by accelerating beta-cell insulin release.
- Surgery — practitioners describe stopping gymnema at least one week before scheduled surgery, because of the risk of unstable glucose during the operation.
- Pregnancy and lactation — there is no good safety data.
- Liver — doctors in Israel reported drug-induced toxic hepatitis (liver inflammation) in a patient taking Gymnema sylvestre for type 2 diabetes (2010), the first such report they could find. In 2022 doctors in India described two fatal cases of hepatitis-associated aplastic anaemia (liver inflammation followed by bone-marrow failure) after Ayurvedic herbal (gymnema) and homeopathic remedies were used. Yellowing of the skin or eyes and dark urine are signs of liver injury that hospitals treat as urgent.
The general principle: for people treating diabetes with insulin or any oral medication that can cause hypoglycemia, adding gymnema lowers glucose further, and the low-blood-sugar episodes described above happen when medication doses are not lowered ahead of time.
Key Research Papers
- Baskaran K et al. (1990). Antidiabetic effect of a leaf extract from Gymnema sylvestre in non-insulin-dependent diabetes mellitus patients. Journal of Ethnopharmacology. The landmark T2DM trial. — PubMed PMID: 2259217
- Shanmugasundaram ER et al. (1990). Use of Gymnema sylvestre leaf extract in the control of blood glucose in insulin-dependent diabetes mellitus. Journal of Ethnopharmacology. The landmark T1DM trial showing C-peptide rise. — PubMed PMID: 2259216
- Shanmugasundaram ER et al. (1990). Possible regeneration of the islets of Langerhans in streptozotocin-diabetic rats given Gymnema sylvestre leaf extracts. Journal of Ethnopharmacology. The mechanistic rodent study supporting beta-cell regeneration. — PubMed PMID: 2259215
- Tiwari P, Ahmad K, Baig MH (2017). Gymnema sylvestre for Diabetes: From Traditional Herb to Future's Therapeutic. Current Pharmaceutical Design 23(11):1667-1676. Modern comprehensive review. — PubMed PMID: 27834124
- Leach MJ (2007). Gymnema sylvestre for diabetes mellitus: a systematic review. Journal of Alternative and Complementary Medicine. Systematic review pooling earlier trials. — PubMed PMID: 18047444
- Kanetkar P, Singhal R, Kamat M (2007). Gymnema sylvestre: A Memoir. Journal of Clinical Biochemistry and Nutrition. Pharmacology and historical review. — PubMed PMID: 18193099
- Nahas R, Moher M (2009). Complementary and alternative medicine for the treatment of type 2 diabetes. Canadian Family Physician. Practice-oriented review including gymnema. — PubMed PMID: 19509199
- Persaud SJ et al. (1999). Gymnema sylvestre stimulates insulin release in vitro by increased membrane permeability. Journal of Endocrinology. Beta-cell insulin secretion mechanism. — PubMed PMID: 10556769
- Yeh GY et al. (2003). Systematic review of herbs and dietary supplements for glycemic control in diabetes. Diabetes Care. Includes gymnema among the herbs with credible evidence. — PubMed PMID: 12663610
- Pothuraju R et al. (2014). A systematic review of Gymnema sylvestre in obesity and diabetes management. Journal of the Science of Food and Agriculture. — PubMed PMID: 24166097
- Al-Romaiyan A et al. (2010). A novel Gymnema sylvestre extract stimulates insulin secretion from human islets in vivo and in vitro. Phytotherapy Research. Human islet preparation evidence for the insulin-secretion mechanism. — PubMed PMID: 20812281
- Stratton IM, Adler AI, Neil HA, Matthews DR, Manley SE, Cull CA, Hadden D, Turner RC, Holman RR (2000). Association of glycaemia with macrovascular and microvascular complications of type 2 diabetes (UKPDS 35): prospective observational study. BMJ 321(7258):405-412. — PubMed PMID: 10938048
- Devangan S, Varghese B, Johny E, Gurram S, Adela R (2021). The effect of Gymnema sylvestre supplementation on glycemic control in type 2 diabetes patients: A systematic review and meta-analysis. Phytotherapy Research 35(12):6802-6812. — PubMed PMID: 34467577
- Zamani M, Ashtary-Larky D, Nosratabadi S, Bagheri R, Wong A, Rafiei MM, Asiabar MM, Khalili P, Asbaghi O, Davoodi SH (2023). The effects of Gymnema Sylvestre supplementation on lipid profile, glycemic control, blood pressure, and anthropometric indices in adults: A systematic review and meta-analysis. Phytotherapy Research 37(3):949-964. — PubMed PMID: 36580574
- Shiyovich A, Sztarkier I, Nesher L (2010). Toxic hepatitis induced by Gymnema sylvestre, a natural remedy for type 2 diabetes mellitus. American Journal of the Medical Sciences 340(6):514-517. — PubMed PMID: 20856101
- Philips CA, Theruvath AH, Ravindran R (2022). Toxic hepatitis-associated aplastic anaemia after dual homeopathic remedies and Gymnema sylvestre use. BMJ Case Reports 15(3):e247867. — PubMed PMID: 35318201
PubMed Topic Searches
Connections
- All Herbs
- Gymnema Overview
- Gymnema Benefits Hub
- Gymnema for Sugar Cravings
- Gymnema for Weight Loss
- Gymnema for Cholesterol
- Berberine
- Cinnamon
- Bitter Melon
- Fenugreek
- Chromium
- Diabetes
- Insulin Resistance
- Hemoglobin A1c
- Fasting Insulin
- Blood Sugar Control
- Metformin — the first-line antidiabetic gymnema is most often stacked with, since their mechanisms are largely orthogonal.
- History