Betel Nut (Areca Nut) — What the Evidence Shows
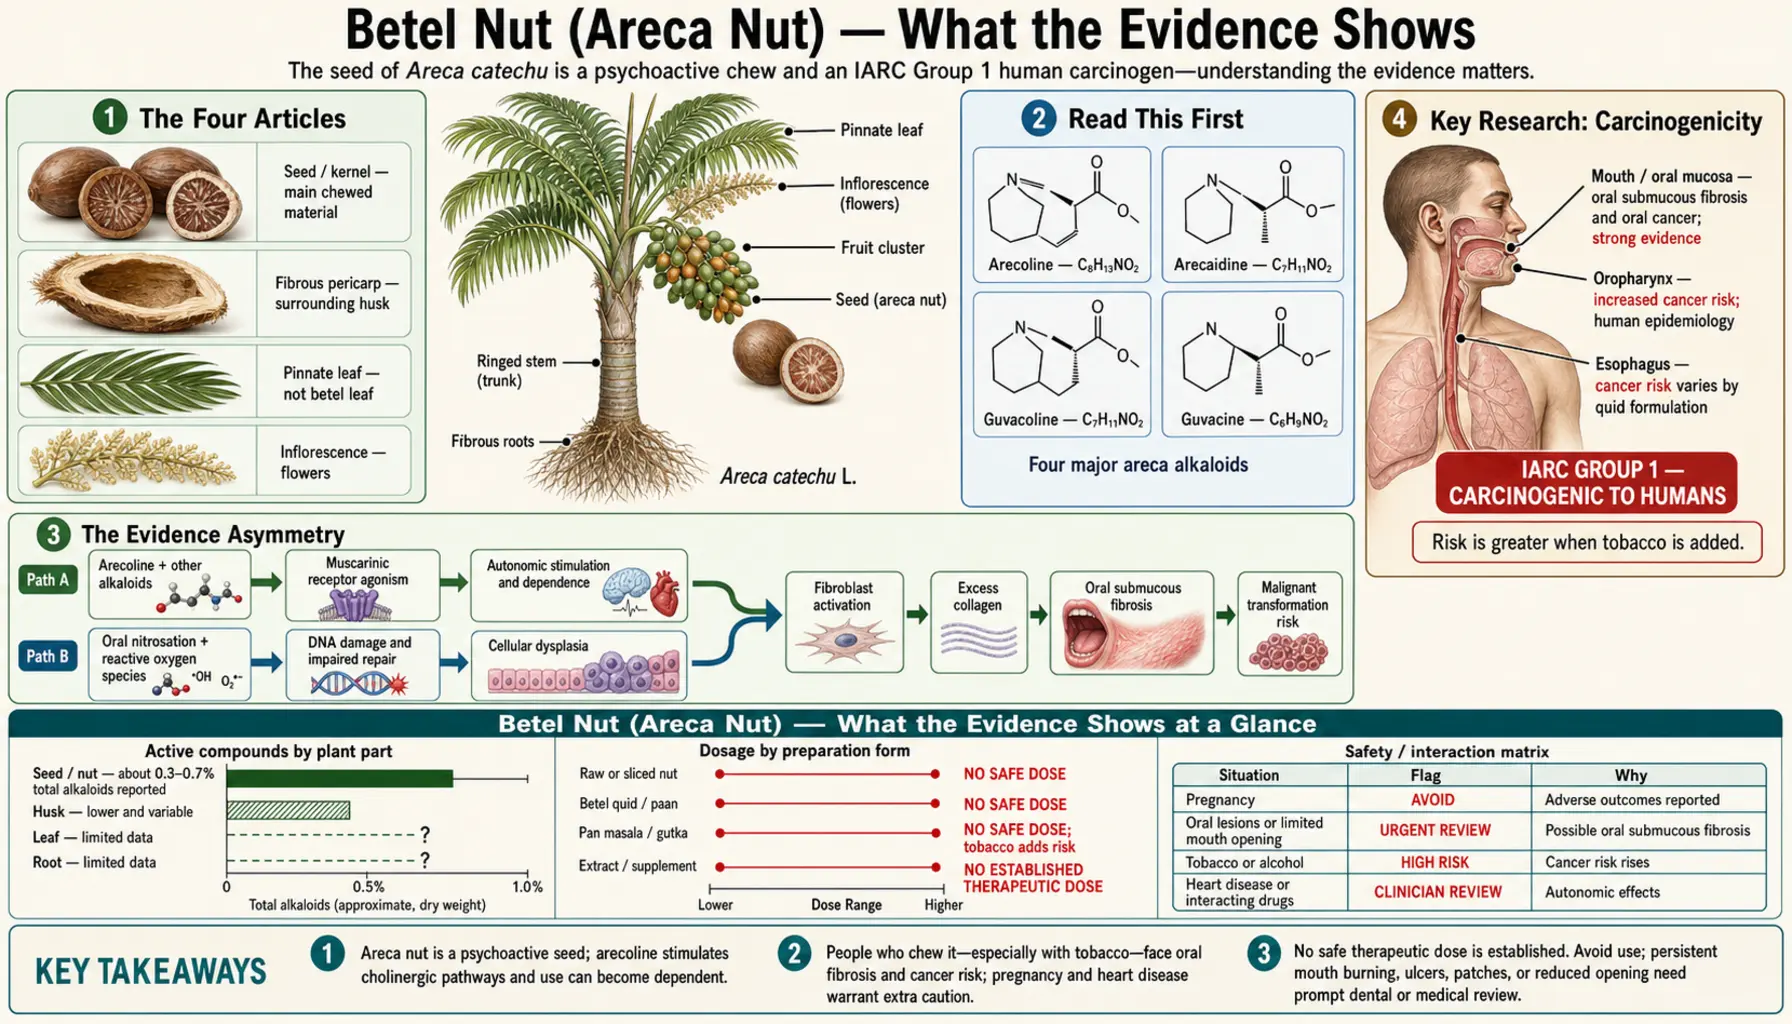
Areca nut — the seed of the palm Areca catechu, almost always called betel nut in English — is classified by the International Agency for Research on Cancer as a Group 1 human carcinogen: carcinogenic to humans. That classification applies to areca nut on its own, to betel quid without added tobacco, and to betel quid with tobacco, each evaluated separately and each placed in the same category as tobacco smoking and asbestos. This section is therefore not a benefits deep dive, and it is not headed as one, because calling it that would misrepresent what the evidence says.
What it is instead: an honest account for the reader who chews, or whose family chews. Areca nut is used every day by several hundred million people — estimates in the literature run from roughly 300 to 600 million, and all of them are estimates — which makes it one of the most widely used psychoactive substances on earth. It carries deep ceremonial and social meaning at weddings, in temples, and as an offering to a guest across South Asia, Southeast Asia and the Pacific. The alertness people describe from chewing is real pharmacology, not suggestion. None of that changes the biology, and none of it is a reason to be written at as though normal cultural practice were ignorance.
So these four articles document what areca nut is claimed to do, state the established harm alongside every claim, and put the genuinely useful material — how to recognise trouble early, and how to stop — where it can be found. The evidence is deliberately asymmetric and the asymmetry is stated on every page: the harm sits in the strongest tier there is, established human epidemiology, while the benefit side consists of traditional use plus the pharmacology of a short-acting stimulant. Those are not comparable categories.
One piece of terminology, because the confusion is pervasive and matters medically. Areca nut is not betel leaf. Betel leaf is Piper betle, a pepper vine used as the wrapper, and it is covered separately under betel leaf and its benefits leg. A betel quid or paan is the assembled preparation: areca nut, slaked lime, usually a betel leaf, and very often tobacco. Gutka, mawa and pan masala are commercial areca-based mixtures, the first two containing tobacco. Chewing plain areca nut with no leaf and no tobacco is not an exemption from anything here.
The Four Articles
Areca Nut and Oral Cancer: The Established Harm
The International Agency for Research on Cancer (IARC) Group 1 classification and where it comes from — Monographs Volume 85 and Volume 100E. The human epidemiology for oral cavity, pharynx and oesophagus; the risk that persists in people who have never used tobacco, which is what isolates areca's own contribution; the dose-response gradient in quids per day, years chewed and retention time; and the mechanisms, from arecoline and arecaidine genotoxicity through nitrosamines formed in the mouth during chewing to the reactive oxygen species driven by slaked lime. Also which beliefs about safer chewing hold up, and which do not.
Read the deep dive →Oral Submucous Fibrosis: The Mouth-Scarring Condition in Chewers
The condition to recognise early, because early detection is the one thing that changes outcomes. Burning on spicy food is the first sign and is almost always dismissed for years. Covers blanching, palpable fibrous bands, progressive trismus and how mouth opening is measured and tracked; why the scarring is progressive and largely irreversible; its recognised premalignant status and what is honestly known about the transformation rate; why it now appears in teenagers after only a few years of sachet products; and the weak state of the treatment evidence.
Read the deep dive →Arecoline: Why Areca Nut Is Habit-Forming
Why “just stop” fails as advice. Arecoline is a muscarinic agonist with additional nicotinic-receptor activity, and areca use produces tolerance, craving and a withdrawal syndrome of irritability, low mood and disturbed sleep — documented in chewers who use no tobacco at all. Also the harms that are not cancer and are rarely mentioned: metabolic syndrome and type 2 diabetes, cardiovascular disease and mortality, worsened asthma through direct bronchoconstriction, pregnancy associations including reduced birthweight, and medication interactions.
Read the deep dive →Areca Nut: Traditional Claims, and Help With Quitting
What areca nut is claimed to do, each claim labelled by evidence tier — the after-meal digestive use, the alertness and stamina effect (which is real), the obsolete anthelmintic action, and the ceremonial roles at weddings and religious occasions. Then the most practical material on the site about areca: what quitting achieves and how fast, a step-by-step quit plan, handling withdrawal, substitutes chewers actually use, how to decline a quid without insulting the person offering it, and what to ask a dentist to examine and measure.
Read the deep dive →Table of Contents
Read This First
Four things that decide most of what a reader needs from this section:
- There is no established safe amount, and no safer preparation. Omitting tobacco, using a betel leaf, choosing fresh nut over cured, or buying a branded “tobacco-free” sachet do not remove the classification. Areca nut alone is Group 1.
- Risk is graded, which means reduction is not futile. Fewer quids, shorter retention, and never holding a quid overnight all move a chewer down a real dose-response gradient. Stopping moves them furthest.
- Early detection is the intervention available today. A two-minute soft-tissue examination of the mouth, with mouth opening measured in millimetres and written down, is cheap, quick, and the thing most likely to change what happens. Burning on spicy food is, on its own, the first sign of oral submucous fibrosis.
- Stopping is hard for pharmacological reasons. Dependence with tolerance, craving and withdrawal is documented, including in chewers who use no tobacco. Advice that treats chewing as a mere habit fails, and the failure is not the chewer's.
The Evidence Asymmetry
Every claim in this section carries an evidence tier. On this topic the tiers fall almost entirely on one side, and stating that openly is more useful than a balanced-sounding summary would be.
- Established human epidemiology — the strongest tier. Areca nut causes cancer of the oral cavity, pharynx and oesophagus. Consistent across independent populations, with dose-response, and present in never-tobacco-users. International Agency for Research on Cancer Group 1, evaluated in 2004 and reaffirmed in 2012. In numbers, from a 2014 meta-analysis of 50 publications (Guha and colleagues): betel quid without tobacco multiplied the risk of mouth and throat (oral/oropharyngeal) cancer by 2.56 in the Indian subcontinent and by 10.98 in Taiwan; quid with tobacco multiplied it by 7.74 in the Indian subcontinent, and by 14.56 in women there. The risk rose with the amount chewed each day and the number of years, and roughly half of oral cancers in these countries (49.5% to 53.7%) could be prevented if betel quid were no longer chewed.
- Established clinical observation. Oral submucous fibrosis is caused by areca chewing, is progressive, is largely irreversible once established, and is a recognised oral potentially malignant disorder.
- Well supported. Dependence with tolerance, craving and withdrawal. Bronchoconstriction and worsening of asthma, which follows directly from muscarinic agonism.
- Consistent observational evidence. Metabolic syndrome and type 2 diabetes; cardiovascular disease and all-cause mortality; reduced birthweight and adverse pregnancy outcomes; periodontal disease and tooth loss.
- Established pharmacology, presented as fact rather than benefit. The stimulant and alertness effect of arecoline is real and measurable. So is the increase in salivation and gut motility behind the after-meal use. The historical veterinary anthelmintic action of arecoline salts is also real, and obsolete.
- Traditional use, no clinical evidence. Digestive and dyspepsia use, appetite suppression, nausea, mood, toothache.
- Documented cultural practice, not a health claim. The ceremonial, marital, religious and hospitality roles — historical and ethnographic fact, and the reason messaging that talks down to chewers does not work.
- Contradicted by the evidence. That chewing cleans the teeth. That tobacco-free areca is safe.
- Thin evidence base, stated as such. Areca-specific cessation research; the time course of withdrawal; every medical treatment for submucous fibrosis; and any pharmacotherapy for areca dependence, of which none is established.
Nothing on the claim side is supported by a clinical trial showing benefit in a defined condition. A real stimulant effect does not offset a Group 1 classification, and this section does not present it as though it might.
Key Research: Carcinogenicity
Each citation below links to its own PubMed record.
- IARC Working Group. Betel-quid and Areca-nut Chewing and Some Areca-nut-derived Nitrosamines. IARC Monographs, Volume 85, 2004. PubMed PMID: 15635762. The foundational evaluation, and the source of the three separate Group 1 classifications.
- IARC Working Group. Personal Habits and Indoor Combustions. IARC Monographs, Volume 100E, 2012. PubMed PMID: 23193840. The re-evaluation that reaffirmed all three.
- Secretan B, Straif K, Baan R, et al. “A review of human carcinogens — Part E: tobacco, areca nut, alcohol, coal smoke, and salted fish.” The Lancet Oncology, 2009;10(11):1033-4. PubMed PMID: 19891056.
- Guha N, Warnakulasuriya S, Vlaanderen J, Straif K. “Betel quid chewing and the risk of oral and oropharyngeal cancers: a meta-analysis with implications for cancer control.” International Journal of Cancer, 2014;135(6):1433-43. PubMed PMID: 24302487. Pooled risk, separating quid with and without tobacco.
- Warnakulasuriya S, Trivedy C, Peters TJ. “Areca nut use: an independent risk factor for oral cancer.” BMJ, 2002;324(7341):799-800. PubMed PMID: 11934759.
- Jeng JH, Chang MC, Hahn LJ. “Role of areca nut in betel quid-associated chemical carcinogenesis: current awareness and future perspectives.” Oral Oncology, 2001;37(6):477-92. PubMed PMID: 11435174. The mechanistic review.
- Znaor A, Brennan P, Gajalakshmi V, et al. “Independent and combined effects of tobacco smoking, chewing and alcohol drinking on the risk of oral, pharyngeal and esophageal cancers in Indian men.” International Journal of Cancer, 2003;105(5):681-6. PubMed PMID: 12740918.
- Nair U, Bartsch H, Nair J. “Alert for an epidemic of oral cancer due to use of the betel quid substitutes gutkha and pan masala: a review of agents and causative mechanisms.” Mutagenesis, 2004;19(4):251-62. PubMed PMID: 15215323. On the commercial sachet products.
- Thomas SJ, MacLennan R. “Slaked lime and betel nut cancer in Papua New Guinea.” The Lancet, 1992;340(8819):577-8. PubMed PMID: 1355157.
Key Research: Submucous Fibrosis
- Pindborg JJ, Sirsat SM. “Oral submucous fibrosis.” Oral Surgery, Oral Medicine, Oral Pathology, 1966;22(6):764-79. PubMed PMID: 5224185. The reference clinical and histological description.
- Murti PR, Bhonsle RB, Pindborg JJ, et al. “Malignant transformation rate in oral submucous fibrosis over a 17-year period.” Community Dentistry and Oral Epidemiology, 1985;13(6):340-1. PubMed PMID: 3866655. The most-cited transformation figure.
- Tilakaratne WM, Klinikowski MF, Saku T, Peters TJ, Warnakulasuriya S. “Oral submucous fibrosis: review on aetiology and pathogenesis.” Oral Oncology, 2006;42(6):561-8. PubMed PMID: 16311067.
- Rajendran R. “Oral submucous fibrosis: etiology, pathogenesis, and future research.” Bulletin of the World Health Organization, 1994;72(6):985-96. PubMed PMID: 7867145.
- Warnakulasuriya S, Johnson NW, van der Waal I. “Nomenclature and classification of potentially malignant disorders of the oral mucosa.” Journal of Oral Pathology & Medicine, 2007;36(10):575-80. PubMed PMID: 17944749. Where the premalignant terminology comes from.
- Warnakulasuriya S, Kujan O, Aguirre-Urizar JM, Bagan JV, González-Moles MÁ, Kerr AR, Lodi G, Mello FW, Monteiro L, Ogden GR, Sloan P, Johnson NW. “Oral potentially malignant disorders: a consensus report from an international seminar on nomenclature and classification, convened by the WHO Collaborating Centre for Oral Cancer.” Oral Diseases, 2021;27(8):1862-1880. PubMed PMID: 33128420. The current classification, updating the 2007 paper above. Oral submucous fibrosis stays on the list of oral potentially malignant disorders; oral lichenoid lesions and the mouth changes of chronic graft-versus-host disease were added to it.
- Trivedy C, Baldwin D, Warnakulasuriya S, Johnson N, Peters T. “Copper content in Areca catechu (betel nut) products and oral submucous fibrosis.” The Lancet, 1997;349(9063):1447. PubMed PMID: 9164320. The copper and lysyl oxidase mechanism.
- Kerr AR, Warnakulasuriya S, Mighell AJ, et al. “A systematic review of medical interventions for oral submucous fibrosis and future research opportunities.” Oral Diseases, 2011;17 Suppl 1:42-57. PubMed PMID: 21382138. Why the treatment evidence is called weak.
- Jones A, Veale B, Li T, Aggarwal VR, Twigg J. “Interventions for managing oral submucous fibrosis.” Cochrane Database of Systematic Reviews, 2024;2(2):CD007156. PubMed PMID: 38415846. The newest review of treatments: 30 randomised trials with 2,176 people, most of whom were also helped to stop chewing. Moderate-certainty evidence found that antioxidants given as whole-body (systemic) treatment probably widen mouth opening slightly at three to six months (by about 8.8 mm on average) and reduce burning pain. Every other treatment — including steroid (dexamethasone) injections into the lesion, pentoxifylline, hydrocortisone with hyaluronidase, and jaw exercises (physiotherapy) — had only low or very low certainty evidence. The reviewers note that all the gains in mouth opening were under 10 mm, which may be the smallest change a person with the condition would notice.
- Hazarey VK, Erlewad DM, Mundhe KA, Ughade SN. “Oral submucous fibrosis: study of 1000 cases from central India.” Journal of Oral Pathology & Medicine, 2007;36(1):12-7. PubMed PMID: 17181736. A large clinical series, useful for the shift to younger ages.
Key Research: Dependence and Pharmacology
- Winstock A. “Areca nut — abuse liability, dependence and public health.” Addiction Biology, 2002;7(1):133-8. PubMed PMID: 11900633.
- Benegal V, Rajkumar RP, Muralidharan K. “Does areca nut use lead to dependence?” Drug and Alcohol Dependence, 2008;97(1-2):114-21. PubMed PMID: 18490113.
- Bhat SJ, Blank MD, Balster RL, Nichter M, Nichter M. “Areca nut dependence among chewers in a South Indian community who do not also use tobacco.” Addiction, 2010;105(7):1303-10. PubMed PMID: 20642513. Dependence without the tobacco confounder.
- Ko AM, Wu PW, Lin WT, Lee CH. “Betel-quid addictive use disorders and oral potentially malignant disorders and oral cancer in south, southeast, and East Asia: a systematic review and meta-analysis.” Oral Diseases, 2025;31(5):1517-1530. PubMed PMID: 39164987. Among betel-quid chewers in these regions, 55.2% to 99.3% met the criteria for betel-quid use disorder (addiction). Oral-cancer risk was 8.5 times higher with mild, 8.2 times with moderate and 42.3 times with severe use disorder. The authors conclude that treating the addiction itself, going “beyond simple cessation efforts”, is part of preventing oral cancer.
- Papke RL, Horenstein NA, Stokes C. “Nicotinic activity of arecoline, the psychoactive element of ‘betel nuts’, suggests a basis for habitual use and anti-inflammatory activity.” PLoS One, 2015;10(10):e0140907. PubMed PMID: 26488401.
- Chu NS. “Effects of betel chewing on the central and autonomic nervous systems.” Journal of Biomedical Science, 2001;8(3):229-36. PubMed PMID: 11385294. Where the alertness effect is measured.
- Chu NS. “Neurological aspects of areca and betel chewing.” Addiction Biology, 2002;7(1):111-4. PubMed PMID: 11900630.
- Trivedy CR, Craig G, Warnakulasuriya S. “The oral health consequences of chewing areca nut.” Addiction Biology, 2002;7(1):115-25. PubMed PMID: 11900631. Staining, wear, periodontal disease and tooth loss.
Key Research: Metabolic, Cardiac and Pregnancy
- Yen AM, Chiu YH, Chen LS, et al. “A population-based study of the association between betel-quid chewing and the metabolic syndrome in men.” American Journal of Clinical Nutrition, 2006;83(5):1153-60. PubMed PMID: 16685060.
- Tung TH, Chiu YH, Chen LS, et al. “A population-based study of the association between areca nut chewing and type 2 diabetes mellitus in men.” Diabetologia, 2004;47(10):1776-81. PubMed PMID: 15517150.
- Boucher BJ, Mannan N. “Metabolic effects of the consumption of Areca catechu.” Addiction Biology, 2002;7(1):103-10. PubMed PMID: 11900629.
- Lin WY, Chiu TY, Lee LT, et al. “Betel nut chewing is associated with increased risk of cardiovascular disease and all-cause mortality in Taiwanese men.” American Journal of Clinical Nutrition, 2008;87(5):1204-11. PubMed PMID: 18469240.
- Taylor RF, Al-Jarad N, John LM, Conroy DM, Barnes NC. “Betel-nut chewing and asthma.” The Lancet, 1992;339(8802):1134-6. PubMed PMID: 1349367. The airway effect, mechanistically direct.
- Senn M, Baiwog F, Winmai J, Mueller I, Rogerson S, Senn N. “Betel nut chewing during pregnancy, Madang province, Papua New Guinea.” Drug and Alcohol Dependence, 2009;105(1-2):126-31. PubMed PMID: 19665325.
- Deahl M. “Betel nut-induced extrapyramidal syndrome: an unusual drug interaction.” Movement Disorders, 1989;4(4):330-2. PubMed PMID: 2572964. Case-report level, on the antipsychotic interaction.
Key Research: Cessation and Screening
- Sankaranarayanan R, Ramadas K, Thomas G, et al. “Effect of screening on oral cancer mortality in Kerala, India: a cluster-randomised controlled trial.” The Lancet, 2005;365(9475):1927-33. PubMed PMID: 15936419. The strongest evidence that visual oral screening reduces mortality in high-risk users. About 96,500 people were in the screened group and 95,400 in the comparison group. Across everyone, the fall in oral-cancer deaths was not statistically clear (77 deaths versus 87; mortality rate ratio 0.79, 95% confidence interval 0.51–1.22). Among users of tobacco or alcohol it was: 70 deaths versus 85 (0.66, 0.45–0.95), and 0.57 (0.35–0.93) in male users. The trial defined high risk by tobacco and alcohol use, not by areca chewing.
- Gupta PC, Mehta FS, Pindborg JJ, et al. “Primary prevention trial of oral cancer in India: a 10-year follow-up study.” Journal of Oral Pathology & Medicine, 1992;21(10):433-9. PubMed PMID: 1460581. A 10-year study in Ernakulam district, Kerala, of 12,212 tobacco users (chewers and smokers) given intensive education against tobacco use: more of them stopped using tobacco, and fewer developed leukoplakia (white patches that can precede cancer), than in a comparison group of 6,075 tobacco users. The trial was about tobacco, not areca nut on its own.
- Gupta PC, Warnakulasuriya S. “Global epidemiology of areca nut usage.” Addiction Biology, 2002;7(1):77-83. PubMed PMID: 11900626. Prevalence and patterns, with the limits of the estimates stated.
- Sharan RN, Mehrotra R, Choudhury Y, Asotra K. “Association of betel nut with carcinogenesis: revisit with a clinical perspective.” PLoS One, 2012;7(8):e42759. PubMed PMID: 22912735. A clinically framed synthesis, useful for what to tell a patient.
- Gupta R, Nethan ST, Sinha DN, Gupta S, Singh S. “Systematic review of determinants and interventions of areca nut cessation: curbing a public health menace.” Journal of Public Health (Oxford), 2023;45(1):145-153. PubMed PMID: 35094090. Only 16 studies on quitting areca nut were found (1990 to March 2021). The habit’s social and cultural place, its addictive nature and withdrawal symptoms were barriers to quitting; knowing the health harms, not also drinking or smoking, and family pressure went with quitting. Almost every intervention tested was behavioural; one study used antidepressants. The authors call for research into more behavioural and drug treatments.
- Gupta R, Mariano LC, Nethan ST, Kedar A, Sinha DN, Warnakulasuriya S, Monteiro L, Sharma S, Gupta S, Singh S, Straif K. “Risk reversal of oral, pharyngeal and oesophageal cancers after cessation of betel quid users: a systematic review and meta-analysis.” Annals of Global Health, 2022;88(1):5. PubMed PMID: 35087705. What quitting does to cancer risk, from 14 studies. For betel quid without tobacco, oral-cancer risk was lower in people who had stopped (relative risk 5.61 compared with non-chewers) than in people still chewing (7.89) — a 28.9% risk reversal. For throat (pharyngeal) cancer the risk fell by 48% (2.50 in former chewers versus 4.81 in current chewers). For oesophageal cancer no clear difference was seen. For quid with tobacco, oral-cancer risk was lower only in people who had quit more than 10 years earlier (0.72 compared with current chewers); in those who quit less than 10 years earlier it was not lower (1.21).
External Resources
- International Agency for Research on Cancer Monographs on the Identification of Carcinogenic Hazards to Humans — the primary source for the Group 1 classifications of areca nut and betel quid, with or without tobacco.
- World Health Organization, South-East Asia Region: tobacco and smokeless tobacco — regional context, since areca use overlaps heavily with smokeless tobacco.
- National Cancer Institute: head and neck cancers — symptoms, screening, staging and treatment for the cancers most associated with chewing.
- National Institute of Dental and Craniofacial Research — oral health information, including oral cancer and mouth lesions.
- World Health Organization: oral health — global oral disease burden and prevention policy, including areca and tobacco control.
- PubMed: all areca nut literature — the unfiltered search, if you would rather read the primary sources yourself.
Connections
- All Herbs
- Areca Nut and Oral Cancer — the International Agency for Research on Cancer Group 1 evidence, dose-response and mechanisms.
- Oral Submucous Fibrosis — the premalignant condition to recognise early.
- Arecoline and Dependence — why chewing is habit-forming, plus the non-cancer harms.
- Traditional Claims and Quitting — the claims, labelled, and the practical quit material.
- Betel Nut (Areca catechu) — the main topic page: botany, names, compounds, forms and cautions.
- Betel Leaf (Piper betle) — the other plant, the wrapper, and a different risk profile entirely.
- Betel Leaf — Benefits — the leaf's evidence review, where the two-plant distinction is set out.
- Betel Leaf vs Betel Quid: Cancer Risk — the same question approached from the leaf's side.
- Oral Cancer — presentation, staging, treatment and prognosis.
- Head and Neck Cancer — the wider category including oropharyngeal sites.
- Esophageal Cancer — the third site with sufficient evidence.
- Oncology — the full cancer section.
- Dentistry — oral examination and the conditions found on it.
- Periodontitis — gum disease and tooth loss, both more common in chewers.
- Metabolic Syndrome — associated with chewing in population studies.
- Type 2 Diabetes — associated with areca chewing in population studies of men.
- Asthma — worsened by chewing through direct bronchoconstriction.
- Addiction — how dependence is defined and treated generally.
- Nitrates and Nitrites — the chemistry of the nitrosamines formed during chewing.
- Secondhand Smoke — relevant because chewing and smoking coexist and their risks multiply.
A real safety statement, not a disclaimer. Nothing in this section recommends areca nut, and nothing in it is a reason to start or continue chewing. For people who chew, the research points to two things that change outcomes: stopping (cancer risk falls after quitting, as above) and having the mouth examined (in the Kerala trial, visual mouth examination lowered oral-cancer deaths among high-risk tobacco and alcohol users). A mouth examination covers the cheeks, gums, palate, tongue and the floor of the mouth, and records how much areca is used and for how many years; mouth opening is measured in millimetres and written down so later changes can be compared. Food that has begun to burn, a patch or ulcer that has not healed in three weeks, and a mouth that no longer opens as far as it used to are warning signs that dentists and doctors treat as needing prompt examination, not a routine visit.