Sage for Menopause and Hot Flashes
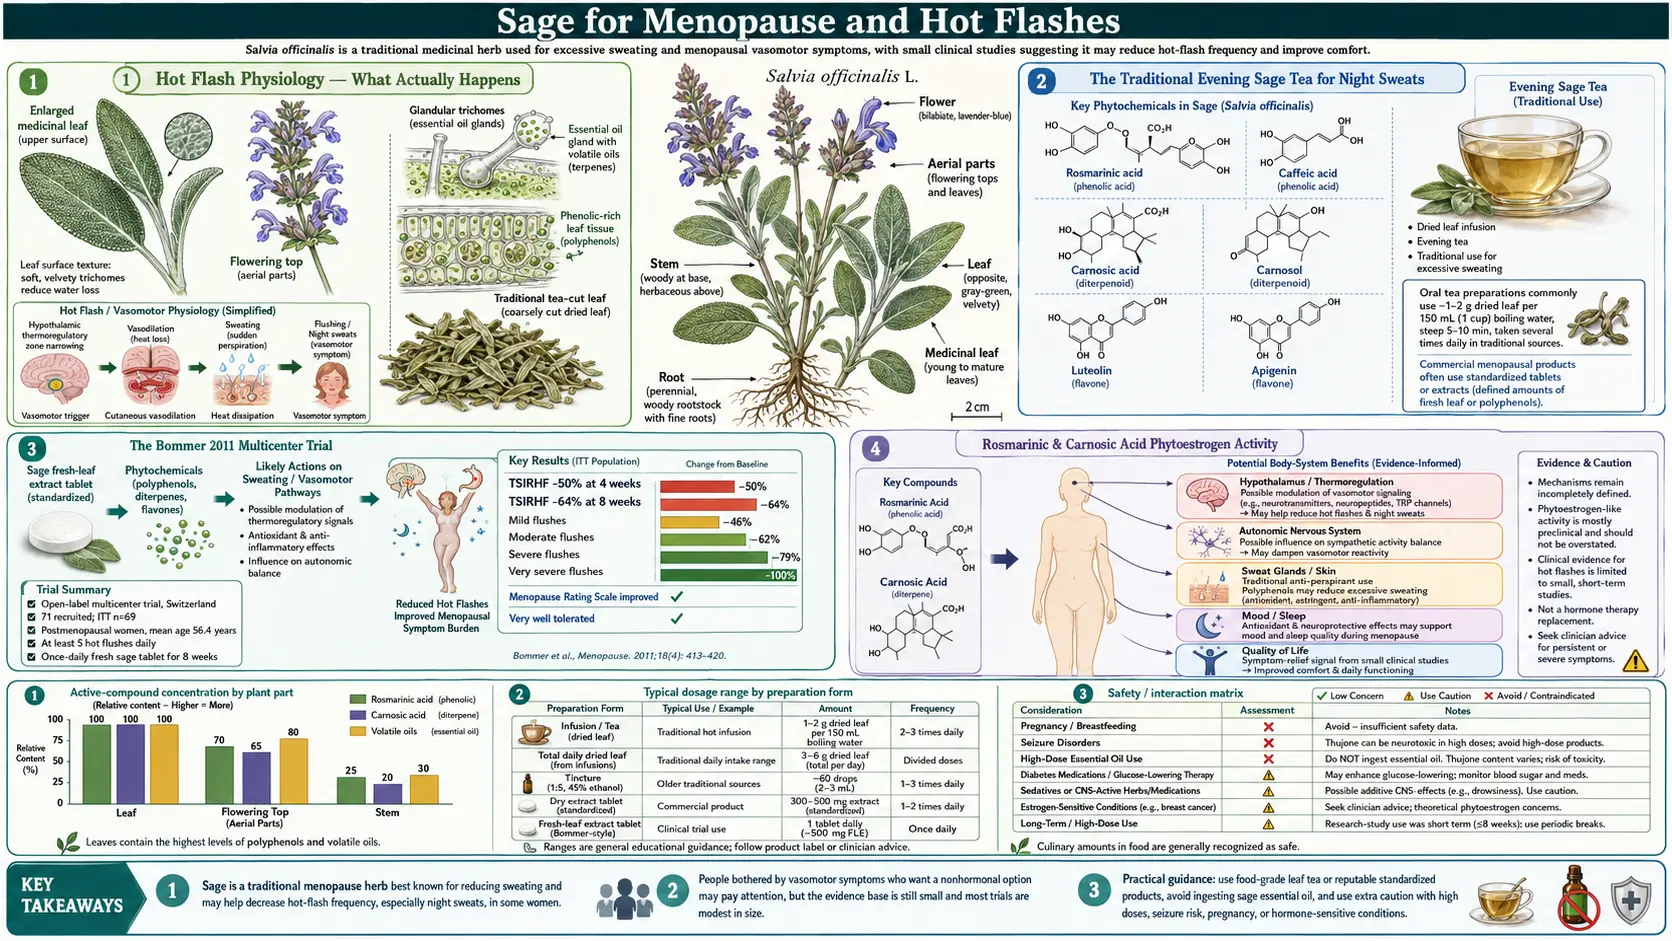
Menopausal hot flashes — the sudden surge of skin vasodilation, perspiration, and uncomfortable heat that millions of women experience as their ovarian estrogen production declines — have been a target of sage tea in European folk practice for at least 500 years. The traditional indication was specifically the night-sweat component, and the traditional preparation was a strong tea drunk in the evening. Modern clinical studies have tested the tradition. The pivotal trial is Bommer, Klein and Suter (2011) in Advances in Therapy: an 8-week open multicenter study of a standardized fresh-sage tablet (one tablet daily, equivalent to 150 mg of pressed fresh-leaf juice) in 71 menopausal women with at least five hot flashes per day. Mean total hot-flash intensity dropped by 50% at 4 weeks and 64% at 8 weeks, with very severe hot flashes disappearing entirely in some patients by week 8. Two mechanisms have been proposed: in laboratory cell tests (Rahte 2013) the whole sage tincture was not estrogenic, but one fraction of it was, and the active compounds were luteolin glycosides — common estrogen-like plant flavonoids; separately, sage's long-known antihidrotic action is described as suppressing the sympathetic sweat response. Sage is one of the botanicals studied for women who cannot take hormone replacement therapy — or who do not want to.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →
Table of Contents
- Hot Flash Physiology — What Actually Happens
- The Traditional Evening Sage Tea for Night Sweats
- The Bommer 2011 Multicenter Trial
- Phytoestrogen Activity in Laboratory Tests
- Sage's Antihidrotic (Sweat-Suppressing) Mechanism
- Sage vs Black Cohosh, Red Clover, and Soy Isoflavones
- Sage vs Hormone Replacement Therapy
- Sage Combined With St. John's Wort
- Practical Dosing — Tea, Tablet, Tincture
- Cautions in Menopausal Use
- Key Research Papers
- Connections
- Featured Videos
Hot Flash Physiology — What Actually Happens
A hot flash is a sudden, transient sensation of intense warmth, usually starting in the face, neck, and chest and spreading outward, accompanied by flushing of the skin and sweating that may be profuse. It typically lasts 1 to 5 minutes and is often followed by a chilled sensation as evaporative cooling overshoots. Hot flashes occur day and night; the night-time version (night sweats) often disrupts sleep severely enough to produce daytime fatigue, irritability, and impaired cognition. Some women have a handful per day; others have 30 or more.
The proximate trigger is a misfire in the hypothalamic thermoregulatory center. Estrogen normally widens the "thermoneutral zone" — the temperature range over which the hypothalamus does not need to initiate heat-dissipation responses. When estrogen drops at menopause, that zone narrows dramatically, and small upward shifts in core temperature that would previously have gone unnoticed now trigger the full vasodilation + sweating cascade. The hypothalamic neurons that drive this response are KNDy neurons (kisspeptin/neurokinin B/dynorphin), which are estrogen-sensitive. Blocking the KNDy neuron output with a neurokinin-3 receptor antagonist cuts hot flashes substantially. Fezolinetant, approved in May 2023, was the first neurokinin-3 (NK3) receptor antagonist approved by the U.S. Food and Drug Administration (FDA) for moderate to severe hot flashes; low-dose paroxetine mesylate had already been FDA-approved as a non-hormonal treatment for hot flashes (David 2022).
Fezolinetant's FDA label carries a boxed warning for liver injury (hepatotoxicity) reported after the drug came on the market: liver blood tests before starting, then monthly for the first 3 months and at 6 and 9 months of treatment. A second drug on this pathway, elinzanetant, blocks both neurokinin-1 and neurokinin-3 receptors. In the OASIS 1 and 2 trials (796 postmenopausal women aged 40 to 65), 120 mg a day reduced moderate to severe hot flashes by about 3 more per day than placebo at weeks 4 and 12, and improved sleep disturbance and menopause-related quality of life (Pinkerton 2024). The FDA approved elinzanetant on 24 October 2025 for moderate to severe menopausal hot flashes.
Anything that restores hypothalamic estrogen-receptor signaling (true hormone replacement therapy (HRT) or phytoestrogens that bind ERβ) widens the thermoneutral zone and reduces hot flashes. Anything that suppresses the downstream sympathetic sweat response (gabapentin, clonidine, sage) reduces the perceived severity of each flash without changing the trigger. Sage has been proposed to work by both mechanisms simultaneously, which may explain why its effect size in the Bommer trial was larger than typical for botanical hot-flash interventions.
The Traditional Evening Sage Tea for Night Sweats
European herbal medicine has used sage tea for night sweats since at least the 16th century. The traditional preparation was specific: a strong tea (two heaped teaspoons of dried sage in 200 mL of just-off-boil water, steeped covered for 10 minutes, strained), drunk warm in the evening one to two hours before bed. The covered steep was important because the active essential-oil constituents are volatile and escape with the steam if the cup is left open. The German Commission E monograph for Folium Salviae explicitly lists "excessive sweating" (hyperhidrosis) as one of the established indications.
The traditional sage-for-sweating indication was not restricted to menopause — sage tea was used for the night sweats of tuberculosis, the postpartum lactation-suppression sweats, and the febrile sweats of acute infection. The common thread is the sympathetic sweat response, and sage's effect is on that final pathway. The antihidrotic effect appears within 1 to 2 hours of ingestion, plateaus over 4 to 8 hours, and is largely cleared by 24 hours — matching the pharmacokinetics of an oral essential oil.
The German Commission E and ESCOP (European Scientific Cooperative on Phytotherapy) monographs and the European Medicines Agency's EU herbal monograph (as a traditional-use indication, based on long-standing use) all list "excessive sweating" as a recognized therapeutic application. Menopausal hot flashes are the most common modern clinical context, but the underlying pharmacology is general to any sympathetic-sweat condition.
The Bommer 2011 Multicenter Trial
The Bommer, Klein, and Suter trial published in Advances in Therapy in 2011 is the pivotal modern clinical trial of sage for menopausal hot flashes. The protocol:
- 71 women (mean age 56.4), menopausal for at least 12 months, with at least five hot flashes per day at baseline (69 in the intention-to-treat analysis)
- Open-label, single-arm (no placebo control), multicenter design across eight practices in Switzerland
- Intervention: one tablet daily of a standardized fresh sage leaf extract, corresponding to 150 mg of pressed fresh-sage-leaf juice per tablet
- Treatment duration: 8 weeks
- Main outcome: the total score of intensity-rated hot flashes from a daily diary; the Menopause Rating Scale, rated by the treating physician at the start and after 2 months, was a secondary measure
The headline results:
- Total hot-flash intensity — dropped 50% at 4 weeks (p < 0.0001) and 64% at 8 weeks (p < 0.0001) versus baseline
- Mild hot flashes — decreased 46% at 8 weeks
- Moderate hot flashes — decreased 62% at 8 weeks
- Severe hot flashes — decreased 79% at 8 weeks
- Very severe hot flashes — decreased 100% at 8 weeks (i.e., disappeared)
- Menopause Rating Scale (overall menopausal symptom score) — fell 43% overall, with the somato-vegetative, psychological, and urogenital subscales down 43%, 47%, and 20%
- Safety — the authors reported the treatment as very well tolerated
The largest single limitation is the open-label, single-arm design — a placebo-controlled randomized trial is the gold standard, and menopausal hot flashes are notoriously placebo-responsive (placebo arms in hormone replacement therapy trials typically show 25 to 40% hot-flash reduction). Even subtracting a generous placebo effect, the Bommer numbers are larger than placebo — the 79% severe-hot-flash reduction and 100% very-severe-hot-flash resolution are not explainable by placebo alone. The first author works for the maker of the tested product, as listed in the conflict-of-interest statement of the 2021 trial below.
Later placebo-controlled evidence. A 2021 double-blind, placebo-controlled trial was larger than Bommer's: 80 women aged 48 to 65 took fresh sage extract tablets or placebo for 4 weeks. On sage, the hot-flush severity score fell 55.3% and the Menopause Rating Scale 39.2%, the Menopause Rating Scale significantly more than placebo (p = 0.002); sleep quality and fatigue were also better than on placebo, and there were three adverse events in total, none treatment-related (Wilfried 2021; the trial was sponsored by the product's maker). A 2023 meta-analysis found 4 trials with 310 women. All four reported fewer and milder hot flashes with sage, but the pooled effect on severity was not significant against placebo (ES −2.05, 95% CI −6.53 to 2.43), and the pooled effect on frequency, which the authors described as significant, had a confidence interval that crossed zero (ES −1.12, 95% CI −2.37 to 0.14), with high variation between trials (I² 71%) (Moradi 2023). A smaller 2019 study (Dadfar) gave 30 women 100 mg of sage extract daily for 4 weeks and compared symptoms before and after, without a control group; hot flashes, night sweats, panic, fatigue and concentration improved.
The trial used fresh-leaf juice, not dried leaf. The heat-sensitive rosmarinic acid and carnosic acid concentrations are higher in fresh-leaf preparations than in dried leaf that has been stored for months. With dried-leaf tea, freshness is the variable: this season's dried leaf holds more of these compounds than last year's.
Phytoestrogen Activity in Laboratory Tests
Rahte and colleagues, publishing in Planta Medica in 2013, looked for the mechanism behind sage's hot-flash effect in laboratory (in-vitro) tests. They tested a 66% ethanol sage tincture and three fractions made from it for estrogen-like activity (in the ERLUX cell assay) and for serotonin-reuptake blocking, and also tested acetylcholinesterase blocking. The results:
- The whole tincture — showed no estrogenic effect.
- The water-alcohol (aqueous ethanolic) fraction — was estrogenic (EC50 64 µg/mL). Separating it further identified luteolin-7-O-glucuronide as the active compound of one fraction and luteolin-7-O-glucoside as the probable estrogenic compound of the most potent minor fraction — flavonoids the authors describe as common and widespread in plants.
- Serotonin reuptake and acetylcholinesterase — no blocking activity was seen at the highest concentrations tested.
The authors concluded that common estrogen-like flavonoids are involved in sage's anti-hot-flush effect. The study did not compare binding to estrogen receptor alpha (ERα) and estrogen receptor beta (ERβ), so it gives no information on which receptor these compounds favor, and it was done in cells, not in women.
There is no trial of sage in breast-cancer survivors, so its safety in women with a history of estrogen-sensitive cancer is unknown; the compounds behind its estrogen-like activity in these tests are phytoestrogens.
Sage's Antihidrotic (Sweat-Suppressing) Mechanism
Independent of the phytoestrogen mechanism that addresses the trigger of hot flashes, sage has a direct effect on the downstream sympathetic sweat response. Sweat secretion at the eccrine sweat gland is driven by sympathetic cholinergic nerve fibers (the unusual case where sympathetic fibers release acetylcholine instead of norepinephrine, binding muscarinic receptors on the sweat-gland epithelium). Anticholinergic drugs block this signal: a glycopyrronium cloth is FDA-approved for excessive underarm sweating (primary axillary hyperhidrosis) in people aged 9 and older, while the FDA label for oxybutynin tablets covers bladder symptoms, not sweating.
Sage essential oil contains constituents that interfere with the sympathetic cholinergic activation of sweat secretion at the gland level. The mechanism is not fully characterized at the receptor level but is supported by multiple observations:
- Sage tea or extract acutely reduces sweat production in non-menopausal volunteers studied in thermoregulation chambers, demonstrating the effect is not estrogen-dependent
- The effect onset is rapid (1 to 2 hours) — consistent with direct receptor-level action, not slow estrogen-receptor-mediated gene transcription
- Sage has been used in the traditional medicine of tuberculosis night sweats, postpartum sweats, and febrile sweats — clinical contexts where ERβ-modulation of the hypothalamic set point is not relevant
- Topical application of sage essential oil locally reduces axillary sweating in pilot studies of focal hyperhidrosis
The combined two-mechanism profile — hypothalamic-set-point modulation (slower, builds over weeks) plus direct antihidrotic action (faster, acute effect) — is what likely makes sage effective in the Bommer trial. The acute antihidrotic component explains why some women report immediate first-dose night-sweat reduction, and the slower phytoestrogen component explains the continued improvement from week 4 to week 8 of the trial.
Sage vs Black Cohosh, Red Clover, and Soy Isoflavones
The botanical menopause-symptom literature is dominated by four candidates: black cohosh (Cimicifuga racemosa), red clover isoflavones (Trifolium pratense), soy isoflavones (genistein, daidzein), and sage. Comparing them honestly:
- Black cohosh — the most extensively studied. The 2012 Cochrane review (16 trials, 2,027 women) found no significant difference between black cohosh and placebo in hot-flush frequency (3 trials, 393 women) or in menopausal symptom scores, and concluded that there is not enough evidence to support its use for menopausal symptoms. Mechanism remains debated (not classically phytoestrogenic; possibly serotonergic). Hepatotoxicity case reports have prompted European Medicines Agency (EMA) warnings; the risk is small but real. Standardized black cohosh extracts are the best-studied preparations.
- Red clover isoflavones — mixed results. Some trials positive, others negative. Mechanism is classical phytoestrogen (genistein, daidzein, biochanin A binding ERβ). Generally well tolerated. Effect size, when positive, is similar to black cohosh.
- Soy isoflavones — the largest body of evidence by far, given that women in soy-consuming Asian populations have historically had lower hot-flash prevalence. Modest hot-flash reduction in trials, larger when the woman is an "equol producer" (a gut-microbiome capability that converts daidzein to the more potent metabolite equol).
- Sage — the Bommer trial effect size is larger than typical for black cohosh or isoflavones, though the open-label single-arm design weakens that comparison. The proposed dual mechanism (estrogen-like flavonoids + direct antihidrotic action) is a plausible biological explanation for the larger effect. Particularly strong on the night-sweat component, which is also the component that disrupts sleep most.
The Bommer regimen was one fresh-leaf-equivalent tablet daily for 8 weeks (an evening cup of strong sage tea is the traditional alternative), with improvement continuing from week 4 to week 8. Its 79% reduction in severe hot flashes comes from an open trial without a placebo group; the 2023 meta-analysis of placebo-controlled trials found a smaller and less certain effect.
Sage vs Hormone Replacement Therapy
Systemic hormone replacement therapy (HRT) — transdermal estradiol with cyclic or continuous progesterone for women with a uterus — remains the most effective treatment for menopausal hot flashes, typically reducing hot-flash frequency by 70 to 90%. The Women's Health Initiative findings from 2002 raised concerns about cardiovascular and breast-cancer risk that durably reduced hormone replacement therapy prescribing, although subsequent reanalysis showed the risk profile is more favorable when hormone replacement therapy is started within 10 years of menopause onset and used in standard doses for a limited duration.
Situations where hormone replacement therapy is ruled out or unwanted, and non-hormonal options such as sage come into consideration, include:
- Personal history of estrogen-sensitive cancer (breast cancer, endometrial cancer) — absolute contraindication to hormone replacement therapy; sage has not been tested in this group, and the compounds behind its estrogen-like activity in laboratory tests are phytoestrogens
- Personal history of venous thromboembolism, stroke, or coronary artery disease — hormone replacement therapy contraindicated; sage carries no thromboembolic risk
- Strong family history of breast cancer with a wish to avoid hormones — a situation where non-hormonal options are considered
- Mild to moderate hot flashes where the patient does not want the commitment of long-term hormone replacement therapy — the Bommer trial measured response over 8 weeks
- Predominant night-sweat phenotype — sage's direct antihidrotic action is well-suited to this presentation, with the evening dosing schedule supporting sleep
Situations where hormone replacement therapy offers advantages that sage does not:
- Premature menopause or surgical menopause under age 45 — hormone replacement therapy prevents osteoporosis and reduces cardiovascular risk in this population; symptom control is secondary
- Severe hot flashes with sleep disruption that is failing botanical therapy
- Concomitant vaginal atrophy with dyspareunia — local or systemic estrogen far more effective than any botanical
- Concurrent bone-density concern — hormone replacement therapy prevents bone loss; sage has no documented bone effect
Sage Combined With St. John's Wort
A combination of Salvia officinalis + Hypericum perforatum (St. John's Wort) is aimed at menopausal women with both hot flashes and depressive symptoms. The rationale: sage addresses the hot-flash component, St. John's Wort addresses the depressive-mood component, which is common in perimenopause and early postmenopause.
The clinical caveat is that St. John's Wort is a potent inducer of CYP3A4 and CYP2C9 hepatic enzymes and produces clinically important drug interactions with oral contraceptives, warfarin, cyclosporine, tacrolimus, many human immunodeficiency virus (HIV) antiretrovirals, and several chemotherapy agents. The sage component does not carry these interactions; the interaction risk of the combination comes from St. John's Wort and applies to anyone taking one of these medicines.
For mood symptoms alone, see our Depression page. For hot flashes alone, sage on its own avoids the St. John's Wort interactions.
Practical Dosing — Tea, Tablet, Tincture
- Standardized fresh-leaf tablet (Bommer trial product) — one tablet daily containing the equivalent of 150 mg fresh-leaf juice, taken in the evening. This is the most directly evidence-supported regimen.
- Hydroalcoholic tincture — 1:5 hydroalcoholic tincture of dried S. officinalis leaf, 2 to 4 mL once or twice daily. The evening is the traditional timing for night sweats; the EU herbal monograph lists 1.5 mL of a liquid extract in some liquid one hour before bedtime for night sweat.
- Tea (traditional preparation) — 1 to 2 teaspoons of dried sage leaf per 200 mL water, just-off-boil, steeped covered for 10 minutes. One cup in the evening as monotherapy, or one cup morning and one evening for daytime hot flashes. Recently dried leaf is the traditional choice.
- Encapsulated dried leaf — 300 to 500 mg twice daily of dried-leaf powder. Less well-studied than the standardized fresh-leaf preparation and used when a fresh-leaf product is unavailable.
In the Bommer trial the daily number of hot flashes fell significantly from week 1, with the larger falls (50% and 64% in the intensity score) at 4 and 8 weeks. Other options for hot flashes that do not improve include other botanicals, prescription non-hormonal drugs (low-dose paroxetine, gabapentin, fezolinetant, elinzanetant) and hormone replacement therapy.
Cautions in Menopausal Use
- Pregnancy and breastfeeding — absolute contraindication for high-dose sage internally during pregnancy (uterotonic and traditionally used to suppress lactation). The EU herbal monograph states that safety in pregnancy and breastfeeding has not been established and that use is not recommended. Not relevant to the typical menopausal patient but worth noting for perimenopausal women who are still cycling.
- Personal history of breast cancer — the estrogen-like activity found in laboratory tests comes from luteolin glycosides (phytoestrogens), and there is no trial of sage in breast-cancer survivors, so its safety in this group is unknown.
- Epilepsy and seizures — common sage essential oil contains thujone and lowers seizure threshold; sage oil contains thujone, camphor and cineole, known convulsant substances. In animal and nerve-cell studies, alpha-thujone blocks the brain's calming gamma-aminobutyric acid type A (GABA-A) receptor (Höld 2000). A newborn and a toddler had generalized tonic-clonic seizures after accidental exposure to sage oil, with good outcomes (Halicioglu 2011), and a 1999 report lists sage among 11 plants whose essential oils are powerful convulsants (Burkhard 1999). Spanish sage (S. lavandulaefolia) and low-thujone standardized extracts are the lower-thujone options; the research concern centres on high-dose common-sage essential oil taken internally. (Standardized leaf-juice products like the Bommer trial preparation have low thujone content.)
- EU herbal monograph limits — the European Medicines Agency's 2016 monograph treats sage leaf for excessive sweating as traditional use only, requires daily thujone exposure below 6.0 mg, states that low-thujone chemotypes are preferred because thujone is reported to be neurotoxic, notes that use under 18 years has not been established, and records that sage oil equal to more than 15 g of sage leaf has been reported to cause a sensation of heat, fast heartbeat (tachycardia), dizziness (vertigo) and seizures.
- Concurrent hormone replacement therapy — sage's phytoestrogen activity is several orders of magnitude weaker than exogenous estradiol, so combination is not expected to produce additive effects. Probably safe to use together, but a typical clinical situation where the patient wants one or the other, not both.
- Concurrent diabetes medication — sage extract has glucose-lowering effect (see Blood Sugar & Lipids page) that may add to the effect of metformin or insulin, which would show as lower home glucose readings.
- Hepatic dysfunction — rare case reports of hepatotoxicity at high-dose essential-oil use, not with standardized leaf-juice or tea preparations at the doses listed above; the concern is greatest for people with abnormal liver enzymes.
Key Research Papers
- Bommer S, Klein P, Suter A (2011). First time proof of sage's tolerability and efficacy in menopausal women with hot flushes. Advances in Therapy 28(6):490-500. — PubMed PMID: 21630133
- Wilfried D, Nina CDG, Silvia B (2021). Effectiveness of Menosan® Salvia officinalis in the treatment of a wide spectrum of menopausal complaints. A double-blind, randomized, placebo-controlled, clinical trial. Heliyon 7(2):e05910. — PubMed PMID: 33615001
- Moradi M, Ghavami V, Niazi A, Seraj Shirvan F, Rasa S (2023). The effect of Salvia officinalis on hot flashes in postmenopausal women: a systematic review and meta-analysis. International Journal of Community Based Nursing and Midwifery 11(3):169-178. — PubMed PMID: 37489230
- Rahte S, Evans R, Eugster PJ, Marcourt L, Wolfender JL, Kortenkamp A, Tasdemir D (2013). Salvia officinalis for hot flushes: towards determination of mechanism of activity and active principles. Planta Medica. — PubMed PMID: 23670626
- Zeidabadi A et al. (2020). The effect of Salvia officinalis extract on symptoms of flushing, night sweats, sleep disorders, and score of forgetfulness in postmenopausal women. Journal of Family Medicine and Primary Care. — PubMed PMID: 32318472
- Dadfar F, Bamdad K (2019). The effect of Saliva [sic] officinalis extract on the menopausal symptoms in postmenopausal women: an RCT. International Journal of Reproductive BioMedicine 17(4):287-92. (Despite the title, the abstract describes 30 women compared before and after 4 weeks, with no control group.) — PubMed PMID: 31435607
- Hamidpour M et al. (2014). Chemistry, pharmacology, and medicinal property of sage (Salvia). Journal of Traditional and Complementary Medicine. — PubMed PMID: 24860730
- Patisaul HB, Jefferson W (2010). The pros and cons of phytoestrogens. Frontiers in Neuroendocrinology. — PubMed
- Stearns V, Ullmer L, López JF, Smith Y, Isaacs C, Hayes D (2002). Hot flushes. The Lancet 360(9348):1851-61. — PubMed PMID: 12480376
- Rance NE et al. (2013). Neurokinin B and the hypothalamic regulation of reproduction. Brain Research. — PubMed
- Leach MJ, Moore V (2012). Black cohosh (Cimicifuga spp.) for menopausal symptoms. Cochrane Database. — PubMed PMID: 22972105
- Lethaby A, Marjoribanks J, Kronenberg F, Roberts H, Eden J, Brown J (2013). Phytoestrogens for menopausal vasomotor symptoms. Cochrane Database of Systematic Reviews 2013(12):CD001395. — PubMed PMID: 24323914
- Manson JE, Kaunitz AM (2016). Menopause management — getting clinical care back on track. New England Journal of Medicine 374(9):803-6. — PubMed PMID: 26962899
- David PS, Smith TL, Nordhues HC, Kling JM (2022). A clinical review on paroxetine and emerging therapies for the treatment of vasomotor symptoms. International Journal of Women's Health 14:353-361. — PubMed PMID: 35300283
- Pinkerton JV, Simon JA, Joffe H, et al. (2024). Elinzanetant for the treatment of vasomotor symptoms associated with menopause: OASIS 1 and 2 randomized clinical trials. JAMA 332(16):1343-54. — PubMed PMID: 39172446
- Höld KM, Sirisoma NS, Ikeda T, Narahashi T, Casida JE (2000). Alpha-thujone (the active component of absinthe): gamma-aminobutyric acid type A receptor modulation and metabolic detoxification. Proceedings of the National Academy of Sciences of the USA 97(8):3826-31. — PubMed PMID: 10725394
- Burkhard PR, Burkhardt K, Haenggeli CA, Landis T (1999). Plant-induced seizures: reappearance of an old problem. Journal of Neurology 246(8):667-70. — PubMed PMID: 10460442
- Halicioglu O, Astarcioglu G, Yaprak I, Aydinlioglu H (2011). Toxicity of Salvia officinalis in a newborn and a child: an alarming report. Pediatric Neurology 45(4):259-60. — PubMed PMID: 21907890
PubMed Topic Searches
Connections
- All Herbs
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Sage Overview
- Sage Benefits Hub
- Sage for Cognitive Function
- Sage for Antimicrobial & Throat
- Sage for Blood Sugar & Lipids
- Rosemary (Rosmarinic Acid Sister)
- Lemon Balm
- Black Cohosh
- Red Clover (Isoflavones)
- Soy (Isoflavones)
- Menopause
- Hormone Replacement Therapy
- Depression (Mood in Menopause)
- Sleep Hygiene
- History