⚠ Evidence warning: Clinical trials or other evidence do not support the claim that black seed clears or suppresses human immunodeficiency virus infection, raises immunoglobulin G and M antibody levels, works as a vaccine adjuvant, and reduces colds and antibiotic use in people. This page keeps it as a report of what people, websites or other media say.
Black Seed for Immune Function and Antiviral Activity
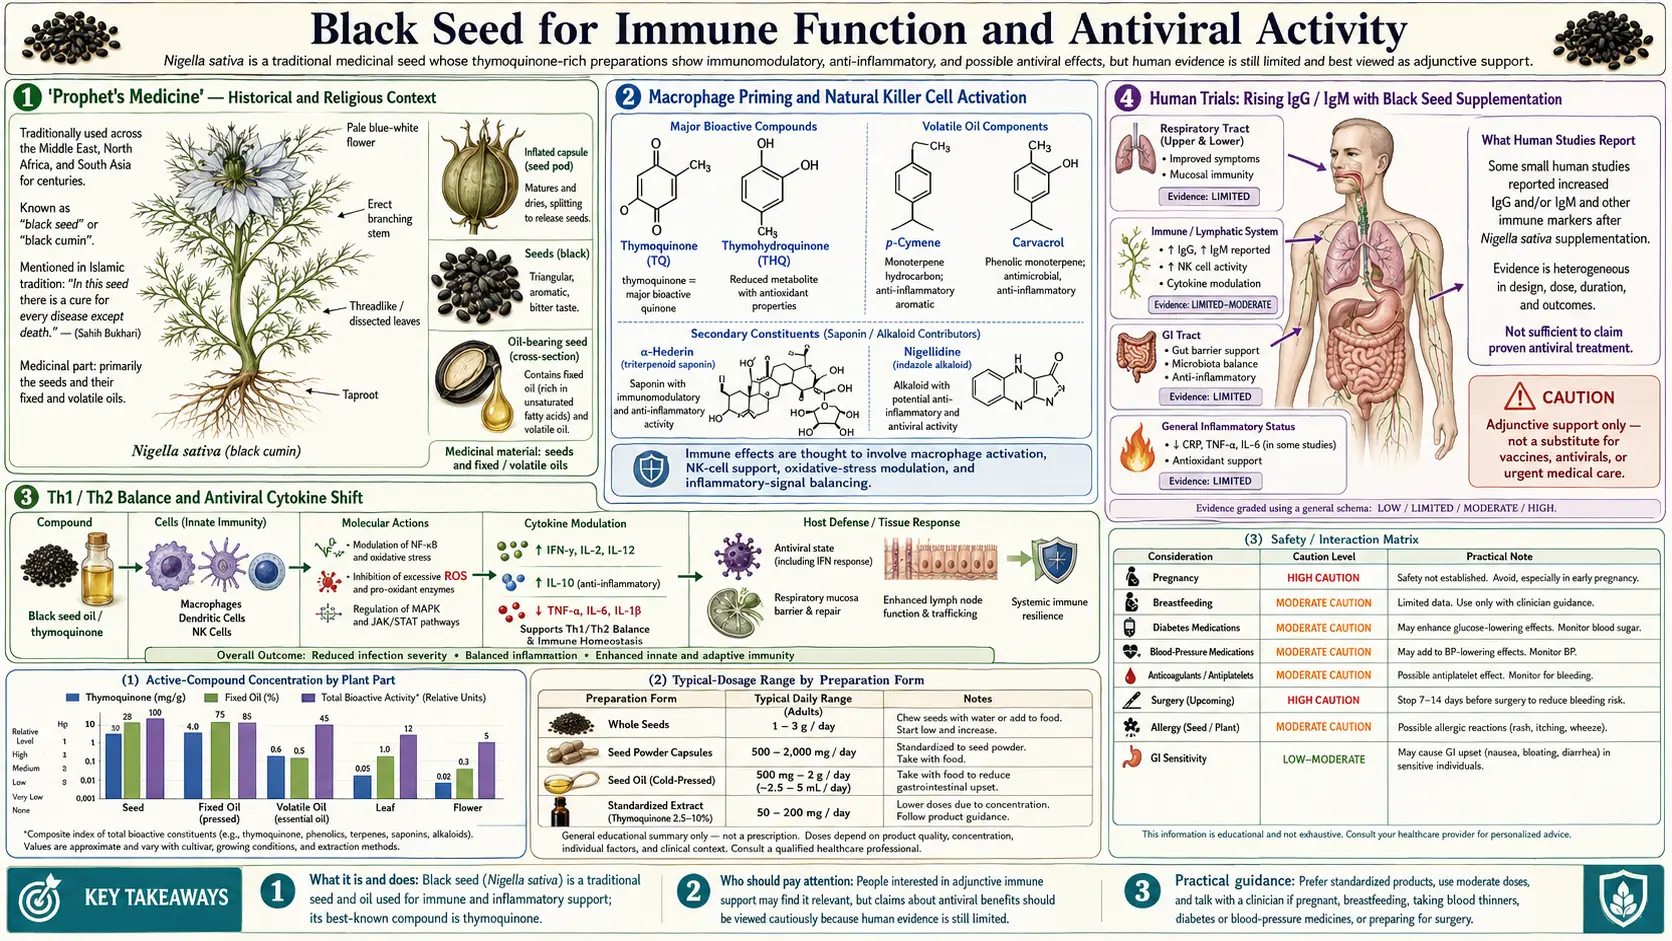
Black seed (Nigella sativa) occupies a unique position in herbal medicine: it is one of the very few plants explicitly named in a religious tradition as a universal remedy. The famous hadith attributed to the Prophet Muhammad — that the seed is "a cure for every disease except death" — has driven 1,400 years of clinical use across the Islamic world for fevers, respiratory infection, parasites, and convalescence. Modern pharmacology has gradually filled in the mechanism: thymoquinone primes macrophages, increases natural killer cell activity, shifts the balance between type 1 and type 2 helper T cells (Th1/Th2) toward antiviral Th1 responses, and drives measurable increases in immunoglobulin G (IgG) and immunoglobulin M (IgM) after several weeks of supplementation. Two single-patient case reports from Nigeria described undetectable human immunodeficiency virus viral load after treatment with black seed preparations. This deep-dive walks through the historical context, the immune mechanisms, the human trial evidence, and the realistic limits of the antiviral claims.
Table of Contents
- "Prophet's Medicine" — Historical and Religious Context
- Macrophage Priming and Natural Killer Cell Activation
- Th1 / Th2 Balance and Antiviral Cytokine Shift
- Reported Rises in Immunoglobulin G / Immunoglobulin M with Black Seed Supplementation
- The Nigerian Human Immunodeficiency Virus Case Reports (Onifade 2013/2015)
- Influenza, Rhinovirus, and Common-Cold Evidence
- Hepatitis C Viral-Load Reduction Trial
- Antibacterial and Antifungal Activity (Including Methicillin-Resistant Staphylococcus Aureus)
- Practical Use for Immune Support (Dose, Form, Timing)
- Realistic Limits, Cautions, and What Black Seed Does NOT Do
- Key Research Papers
- Connections
- Featured Videos
"Prophet's Medicine" — Historical and Religious Context
Black seed's status in Islamic medicine derives from a specific narration in the Sahih al-Bukhari and Sahih Muslim hadith collections, in which the Prophet Muhammad is reported to have said of habbat al-sawda ("the black seed") that it is "a remedy for every disease except death" (or, in some narrations, "a cure for every disease except al-sam," with al-sam generally interpreted to mean death). This single statement made black seed the most widely used medicinal herb in the Islamic world for the past 1,400 years and remains the reason it is sometimes called "the blessed seed" (habbat al-barakah).
The traditional preparation taught by the Persian physician Avicenna (Ibn Sina, 980–1037) in The Canon of Medicine includes black seed for fever, congestion, parasites, headache, toothache, and skin conditions. The Yemeni medical tradition pairs ground black seed with honey for daily morning use. Modern Turkish and Egyptian folk medicine continues to use black seed oil topically for psoriasis and eczema, and orally for asthma, allergies, and stomach upset.
This religious framing matters scientifically because it produced an unusually consistent dosing tradition across centuries and cultures. Most folk remedies vary widely in preparation. Black seed has been used relatively consistently as either whole-seed (1 teaspoon, roughly 3–5 grams, mixed with honey or warm water) or cold-pressed oil (1 teaspoon, roughly 5 mL, daily). This consistent tradition has made designing modern clinical trials straightforward — researchers can use doses similar to what generations of patients have already tolerated, which streamlines safety review and dose selection.
Macrophage Priming and Natural Killer Cell Activation
The innate immune effects of thymoquinone are the best-characterized part of the immune mechanism. Thymoquinone increases phagocytic activity of macrophages, enhances respiratory burst (the reactive oxygen burst that macrophages and neutrophils use to kill engulfed pathogens), and increases tumor necrosis factor-alpha and interleukin-12 (IL-12) production by activated macrophages. These cytokines in turn signal natural killer (NK) cells and Th1 lymphocytes to expand their antiviral and intracellular-pathogen response.
Natural killer cells are the front-line antiviral arm of the innate immune system. A 2005 review describes black seed oil and its active ingredients as augmenting natural killer cell-mediated immune responses (Salem 2005). Mechanistically this matters because natural killer cells are responsible for killing virus-infected cells and tumor cells via perforin/granzyme-mediated apoptosis, and reduced natural killer function is a known feature of chronic viral infection, autoimmune disease, and cancer.
The macrophage and natural killer effects are also relevant to recovery from acute infection.
Th1 / Th2 Balance and Antiviral Cytokine Shift
Beyond innate immunity, thymoquinone modulates the adaptive immune response by shifting the balance between Th1 (cellular immunity, antiviral, intracellular pathogens) and Th2 (humoral immunity, parasites, allergic responses). Most viral infections require an effective Th1 response — interferon-gamma, IL-2, and tumor necrosis factor-alpha — to clear the virus. Many chronic viral infections (human immunodeficiency virus (HIV), hepatitis C virus (HCV), herpes simplex virus (HSV)) are characterized by a defective Th1 response, sometimes called Th1-to-Th2 switching, that prevents viral clearance.
Thymoquinone shifts CD4+ T cell differentiation toward the Th1 phenotype in animal models and in some human studies. The mechanism appears to involve dendritic cell maturation: black seed extract enhances dendritic cell expression of IL-12 (the master Th1-inducing cytokine) while suppressing IL-4 and interleukin-10 (IL-10) (Th2-inducing cytokines). The net effect is a microenvironment more conducive to antiviral T cell responses.
This same Th1-promoting effect explains why black seed sometimes appears beneficial in conditions characterized by inappropriate Th2 dominance (allergic asthma, allergic rhinitis) — shifting the balance back toward Th1 reduces immunoglobulin E (IgE) production and mast cell degranulation. The asthma deep-dive covers this further.
For context on the broader Th1/Th2 framework and other immune-modulating herbs, see Immune Boosting and Astragalus — the latter is another classic Th1-promoting adaptogen widely used for chronic viral infection support.
Reported Rises in Immunoglobulin G / Immunoglobulin M with Black Seed Supplementation
Black seed supplementation is reported to raise serum immunoglobulin G and immunoglobulin M (the dominant systemic and acute-response antibody classes, respectively) after 4–8 weeks of black seed oil 1–3 mL daily. The increase described is modest (10–20%) and is said to be accompanied by an increased CD4+/CD8+ ratio — suggesting enhanced helper T cell function.
The clinical translation of "10–20% higher serum immunoglobulin" is genuinely useful in two scenarios:
- Selective immunoglobulin A (IgA) deficiency or common variable immunodeficiency (CVID) — patients with mild forms of these conditions may benefit from any intervention that nudges immunoglobulin synthesis upward. Black seed is not a replacement for intravenous immunoglobulin (IVIG) therapy in clinically significant CVID, but as an adjunct for mild deficiency it has plausible benefit.
- Elderly patients with immunosenescence — declining antibody responses are a feature of aging immune function. Black seed has been suggested as a vaccine adjuvant for older adults, taken in the weeks around an annual influenza vaccination.
These are mechanistically interesting reports rather than established findings — black seed is described as an adjunct, not a substitute for clinically appropriate immune-disease management.
The Nigerian Human Immunodeficiency Virus Case Reports (Onifade 2013/2015)
The most provocative human reports of black seed for viral infection are the papers by Onifade and colleagues from Nigeria. A 2013 case report described one adult man with HIV who presented to a herbal therapist and was given a Nigella sativa concoction, 10 mL twice daily for 6 months; the abstract does not mention antiretroviral therapy (ART). A 2015 report described one 27-year-old woman who could not receive free antiretroviral therapy because her CD4 count was above 200 cells/μL (350 cells/μL) and was given a black seed and honey mixture (60:40), 10 mL three times daily for a year. The same group also published a 2013 paper titled “Effectiveness of a herbal remedy in six HIV patients in Nigeria”. The reported findings:
- In the 2013 case, viral load fell from 27,000 copies/mL before treatment to ≤1,000 copies/mL on day 30 and was undetectable after therapy; in the 2015 case, viral load was undetectable and repeat HIV tests were negative from 2005 onward
- In the 2013 case, the CD4 count was 250 cells/mm³ before treatment, fell to 160 on day 30 and was 650 after therapy; in the 2015 case, no repeat CD4 count was below 750 cells/μL
- In the 2013 case, fever, diarrhoea and itchy skin lesions disappeared on days 5, 7 and 20 of treatment
- One case report described apparent viral clearance maintained 24 months after black seed therapy was discontinued
These findings are striking and have generated significant interest in the human immunodeficiency virus traditional-medicine literature. However, several important caveats apply:
- The two papers on black seed are single-patient case reports, not randomized double-blind trials.
- Neither report had a control arm to compare against.
- The reported "viral clearance maintained off therapy" finding is medically extraordinary and has not been reproduced in any subsequent controlled trial.
- Human immunodeficiency virus functional cure remains an active research area with billion-dollar trial programs; the Onifade case reports would warrant a major confirmatory study, which has not appeared in the decade since publication.
Practical interpretation: black seed may have legitimate immune-modulating adjunct utility in human immunodeficiency virus care, particularly for managing wasting, fatigue, and secondary infection risk. The case reports are not evidence that black seed can replace antiretroviral therapy, and the “viral cure” claim is a preliminary observation without controlled confirmation, not an established fact. Black seed also slowed drug breakdown by cytochrome P450 3A4 (CYP3A4), the enzyme that metabolizes many ART drugs, in a small study of healthy volunteers (see Realistic Limits below); it has not been studied in people taking HIV protease inhibitors.
Influenza, Rhinovirus, and Common-Cold Evidence
For the common viral respiratory infections that account for the vast majority of immune-related concerns — influenza, rhinovirus, respiratory syncytial virus (RSV), parainfluenza — the black seed evidence is mostly preclinical and traditional. In-vitro studies show direct antiviral activity of thymoquinone against influenza A H1N1 and H3N2 strains, with mechanism involving inhibition of viral attachment and reduction of viral RNA replication. Animal model studies (mice infected with influenza A) showed reduced lung viral titer and improved survival with prophylactic black seed oil.
For colds and other upper respiratory infections, black seed is reported to bring:
- Fewer upper respiratory infections when black seed oil is taken through the winter
- Shorter cold symptoms when black seed oil is started at the first sign of symptoms
- Less antibiotic use in children during respiratory-infection season
Two randomized trials have tested black seed in COVID-19. In a placebo-controlled randomized trial at four medical centers in Pakistan (313 adults with moderate or severe COVID-19, enrolled April–July 2020), honey plus Nigella sativa seeds for up to 13 days alongside standard care shortened the time to symptom relief (moderate cases 4 vs 7 days; severe cases 6 vs 13 days) and cleared the virus sooner (moderate 6 vs 10 days; severe 8.5 vs 12 days). In severe cases, deaths were 4% with honey and black seed vs 18.87% with placebo, and no adverse effects linked to the treatment were seen (Ashraf 2023). In an open-label randomized trial in Saudi Arabia (173 adults with mild COVID-19), black seed oil 500 mg twice daily for 10 days was followed by recovery within 14 days in 62% of patients vs 36% with usual care alone, with mean recovery in 10.7 vs 12.3 days; the authors write that these benefits need further study in placebo-controlled, double-blind trials (Koshak 2021).
The use people describe is similar to elderberry, vitamin C, zinc, and the other common-cold adjuncts: taken at early symptoms, alongside rather than in place of vaccination, with worsening symptoms still a reason for medical attention. For more on the broader common-cold supplement landscape, see Common Cold and Vitamin C.
Hepatitis C Viral-Load Reduction Trial
A 2013 study from Egypt (Barakat et al.) gave black seed (Nigella sativa) 450 mg three times daily for 3 months to 30 patients with chronic hepatitis C virus infection who were not eligible for interferon/ribavirin therapy (because of a medical reason, refusal, or cost). Every patient received black seed; there was no separate comparison group. After treatment:
- Significant reduction in hepatitis C virus viral load: the mean fell from 380,808.7 to 147,028.2 (P = 0.001)
- Improvement in liver enzymes (alanine aminotransferase (ALT), aspartate aminotransferase (AST))
- Improvement in albumin and platelet count
- Lower fasting and after-meal blood glucose, in patients with and without diabetes
- Side effects were limited to a few cases of stomach (epigastric) pain and low blood sugar (hypoglycemia) that did not affect whether patients kept taking it
The magnitude of viral-load reduction was modest compared to modern direct-acting antiviral (DAA) regimens like sofosbuvir/velpatasvir, which achieve sustained virologic response (essentially viral cure) in >95% of hepatitis C virus patients within 12 weeks. In the modern hepatitis C virus-care era, black seed has no role as primary hepatitis C virus therapy. However, in settings where DAA access is limited or unaffordable, or as an adjunct to support liver function during hepatitis C virus-related fibrosis, black seed may have some role — consistent with the broader pattern of hepatoprotective evidence for black seed in non-alcoholic fatty liver disease and drug-induced hepatotoxicity.
For more on liver-supportive herbs and on hepatitis C virus background, see Hepatitis C, Milk Thistle, and the general Hepatology hub.
Antibacterial and Antifungal Activity (Including Methicillin-Resistant Staphylococcus Aureus)
Black seed and isolated thymoquinone show direct in-vitro antimicrobial activity against a wide range of human pathogens:
- Gram-positive bacteria — Staphylococcus aureus (including methicillin-resistant Staphylococcus aureus (MRSA) strains), Streptococcus pneumoniae, Enterococcus faecalis, Bacillus cereus
- Gram-negative bacteria — Escherichia coli, Pseudomonas aeruginosa, Klebsiella pneumoniae, Helicobacter pylori
- Fungi — Candida albicans, Aspergillus species, Trichophyton (athlete's foot dermatophytes)
- Parasites — Schistosoma mansoni, Plasmodium species (malaria), Leishmania
The clinically interesting application is topical use for skin infections, where black seed oil applied directly to the affected area can deliver bactericidal concentrations of thymoquinone in vivo. Small clinical trials have shown benefit for tinea versicolor, mild superficial fungal infection, and as part of acne management. The methicillin-resistant Staphylococcus aureus in-vitro data is mechanistically interesting — thymoquinone appears to retain activity against multidrug-resistant strains that have lost susceptibility to multiple beta-lactam antibiotics — but the in-vivo translation for systemic methicillin-resistant Staphylococcus aureus infection has not been demonstrated. Invasive methicillin-resistant Staphylococcus aureus disease is treated in hospital with antibiotics such as vancomycin or daptomycin.
For Helicobacter pylori (H. pylori), a 2010 randomized trial in Saudi Arabia treated 88 adults with indigestion (non-ulcer dyspepsia) and H. pylori infection with either standard triple therapy (clarithromycin, amoxicillin and omeprazole) or ground black seed at 1, 2 or 3 g a day plus omeprazole. The infection was cleared in 82.6% with triple therapy, 66.7% with 2 g black seed (not statistically different from triple therapy), and 47.6% and 47.8% with 1 g and 3 g (significantly lower). Indigestion symptoms improved to a similar extent in all groups, and the authors suggest further studies combining black seed with antibiotics (Salem EM 2010). See Helicobacter pylori for more.
Practical Use for Immune Support (Dose, Form, Timing)
The doses used in traditional practice and in human studies fall in a fairly narrow range:
- Whole-seed powder: 1–3 grams per day, divided. Typically mixed with honey, yogurt, or warm water. Has the most traditional use.
- Cold-pressed black seed oil: 1–2 teaspoons (5–10 mL) per day, divided. Easier to dose consistently than whole seed; the oil is commonly kept refrigerated after opening and used within 6 months.
- Standardized capsule (thymoquinone-quantified): 500–1000 mg of standardized extract per day, divided. Some products state their thymoquinone (TQ) content, for example as 2–5% thymoquinone in the oil, or 50–100 mg TQ per dose in the capsule.
- Timing: the traditional Yemeni morning-dose-with-honey-and-warm-water is mechanistically reasonable — the fat content of the oil benefits from concurrent food fat absorption, and morning dosing aligns with the diurnal cortisol/immune rhythm. Some trials use twice-daily dosing for higher serum levels.
- Duration: 4–8 weeks is the period described for immunoglobulin and natural killer-activity changes. Most chronic-use traditions involve continuous dosing for months to years.
A regimen described in popular use for the onset of an acute infection is to double the daily dose for 7–10 days starting at the first sign of symptoms.
Realistic Limits, Cautions, and What Black Seed Does NOT Do
- Pregnancy — the pregnancy concern about high-dose black seed comes from animal studies. In rats, a hexane extract of the seeds prevented pregnancy when given by mouth at 2 g/kg a day on days 1–10 after mating (Keshri 1995). In isolated rat and guinea-pig uterine muscle, the seeds' volatile oil reduced spontaneous contractions and contractions triggered by oxytocin, rather than stimulating them (Aqel 1996). The concern is about therapeutic doses rather than the small amounts of black seed used in cooking.
- Surgery — thymoquinone has antiplatelet activity and may increase bleeding risk, particularly in combination with nonsteroidal anti-inflammatory drugs (NSAIDs), warfarin, clopidogrel, or other anticoagulants. Stopping black seed 2 weeks before planned surgery is a common precaution for herbs with antiplatelet activity, not a figure from a black seed study.
- Drug interactions — black seed inhibits cytochrome P450 3A4 (similar to grapefruit juice) and can elevate serum levels of drugs metabolized by this enzyme, including many statins, calcium channel blockers, immunosuppressants (cyclosporine, tacrolimus), and human immunodeficiency virus protease inhibitors. In a 2010 study of 4 healthy volunteers, black seed 2.5 g twice daily for 7 days slowed the breakdown of the test drug dextromethorphan by both CYP3A4 and cytochrome P450 2D6 (CYP2D6) (the urinary metabolic ratios rose 1.6-fold and 127-fold); the authors concluded that black seed “has the potential to interact with CYP2D6 and CYP3A4 substrates” (Al-Jenoobi 2010). The interaction has not been studied in people taking statins, tacrolimus or HIV protease inhibitors.
- Diabetes medication — because black seed lowers blood glucose, the effects add up for people on insulin or sulfonylureas, raising the risk of low blood sugar (hypoglycemia); a few cases of hypoglycemia occurred in the Barakat hepatitis C study. See the diabetes deep-dive for details.
- Not a substitute for vaccination — the antiviral signal in trials is modest and applies to mild upper respiratory infection. Black seed does not prevent measles, polio, hepatitis B, or any vaccine-preventable infection at the population level. It can plausibly support vaccine response as an adjuvant, but it is not vaccine equivalent.
- Not curative for human immunodeficiency virus, hepatitis C virus, or cancer — despite enthusiastic claims in some traditional-medicine literature, the controlled trial evidence does not support black seed as monotherapy for any major viral infection or malignancy. Its evidence-based role is adjunct support, not replacement of standard care.
- Quality variability — commercial black seed products vary enormously in thymoquinone content (0.1% to 2.5%). Some suppliers publish certificates of analysis stating the thymoquinone content.
- Allergic reaction — rare but documented. Contact dermatitis from topical use is more common than systemic allergy.
Key Research Papers
- Salem ML (2005). Immunomodulatory and therapeutic properties of the Nigella sativa L. seed. International Immunopharmacology. — PubMed PMID: 16275613
- Onifade AA et al. (2013). Nigella sativa concoction induced sustained seroreversion in HIV patient. African Journal of Traditional, Complementary and Alternative Medicines. — PubMed PMID: 24311845
- Onifade AA, Jewell AP, Ajadi TA, Rahamon SK, Ogunrin OO (2013). Effectiveness of a herbal remedy in six HIV patients in Nigeria. Journal of Herbal Medicine. 3(3):99–103. — doi:10.1016/j.hermed.2013.04.006
- Onifade AA, Jewell AP, Okesina AB (2015). Seronegative conversion of an HIV positive subject treated with Nigella sativa and honey. African Journal of Infectious Diseases. 9(2):47. — doi:10.4314/ajid.v9i2.6
- Barakat EM, El Wakeel LM, Hagag RS (2013). Effects of Nigella sativa on outcome of hepatitis C in Egypt. World Journal of Gastroenterology. 19(16):2529–2536. — PubMed PMID: 23674855
- Mouwakeh A et al. (2019). Nigella sativa essential oil and its bioactive compounds as resistance modifiers against Staphylococcus aureus. Phytotherapy Research. — PubMed PMID: 30672036
- Majdalawieh AF, Fayyad MW (2015). Immunomodulatory and anti-inflammatory action of Nigella sativa and thymoquinone. International Immunopharmacology. — PubMed PMID: 26117430
- Forouzanfar F et al. (2014). Black cumin (Nigella sativa) and its constituent (thymoquinone): a review on antimicrobial effects. Iranian Journal of Basic Medical Sciences. — PubMed PMID: 25859296
- Ulasli M et al. (2014). The effects of Nigella sativa (Ns), Anthemis hyalina (Ah) and Citrus sinensis (Cs) extracts on the replication of coronavirus and the expression of TRP genes family. Molecular Biology Reports. — PubMed PMID: 24413991
- Salem EM, Yar T, Bamosa AO, Al-Quorain A, Yasawy MI, Alsulaiman RM, Randhawa MA (2010). Comparative study of Nigella sativa and triple therapy in eradication of Helicobacter pylori in patients with non-ulcer dyspepsia. Saudi Journal of Gastroenterology. 16(3):207–214. — PubMed PMID: 20616418
- Al-Jenoobi FI, Al-Thukair AA, Abbas FA, Ansari MJ, Alkharfy KM, Al-Mohizea AM, Al-Suwayeh SA, Jamil S (2010). Effect of black seed on dextromethorphan O- and N-demethylation in human liver microsomes and healthy human subjects. Drug Metabolism Letters. 4(1):51–55. — PubMed PMID: 20201775
- Keshri G, Singh MM, Lakshmi V, Kamboj VP (1995). Post-coital contraceptive efficacy of the seeds of Nigella sativa in rats. Indian Journal of Physiology and Pharmacology. 39(1):59–62. — PubMed PMID: 7705872
- Aqel M, Shaheen R (1996). Effects of the volatile oil of Nigella sativa seeds on the uterine smooth muscle of rat and guinea pig. Journal of Ethnopharmacology. 52(1):23–26. — PubMed PMID: 8733115
- Ashraf S et al. (2023). Honey and Nigella sativa against COVID-19 in Pakistan (HNS-COVID-PK): A multicenter placebo-controlled randomized clinical trial. Phytotherapy Research. 37(2):627–644. — PubMed PMID: 36420866
- Koshak AE, Koshak EA, Mobeireek AF, Badawi MA, Wali SO, Malibary HM, Atwah AF, Alhamdan MM, Almalki RA, Madani TA (2021). Nigella sativa for the treatment of COVID-19: An open-label randomized controlled clinical trial. Complementary Therapies in Medicine. 61:102769. — PubMed PMID: 34407441
PubMed Topic Searches
Connections
- All Herbs
- Black Seed Overview
- Black Seed Benefits Hub
- Black Seed for Diabetes & Metabolic
- Black Seed for Asthma
- Black Seed for Inflammation
- Immune Boosting
- Astragalus
- Echinacea
- Elderberry
- Vitamin C
- Vitamin D3
- Zinc
- Common Cold
- Hepatitis C
- Milk Thistle
- Helicobacter pylori
- Honey (traditional pairing)
- History