⚠ Evidence warning: Clinical trials or other evidence do not support the claim that black seed protects pancreatic beta cells in people and treats the root inflammatory cause of type 2 diabetes; beta-cell protection has been shown only in rodent studies, and no human trial has measured it. This page keeps it as a report of what people, websites or other media say.
Black Seed for Diabetes and Metabolic Syndrome
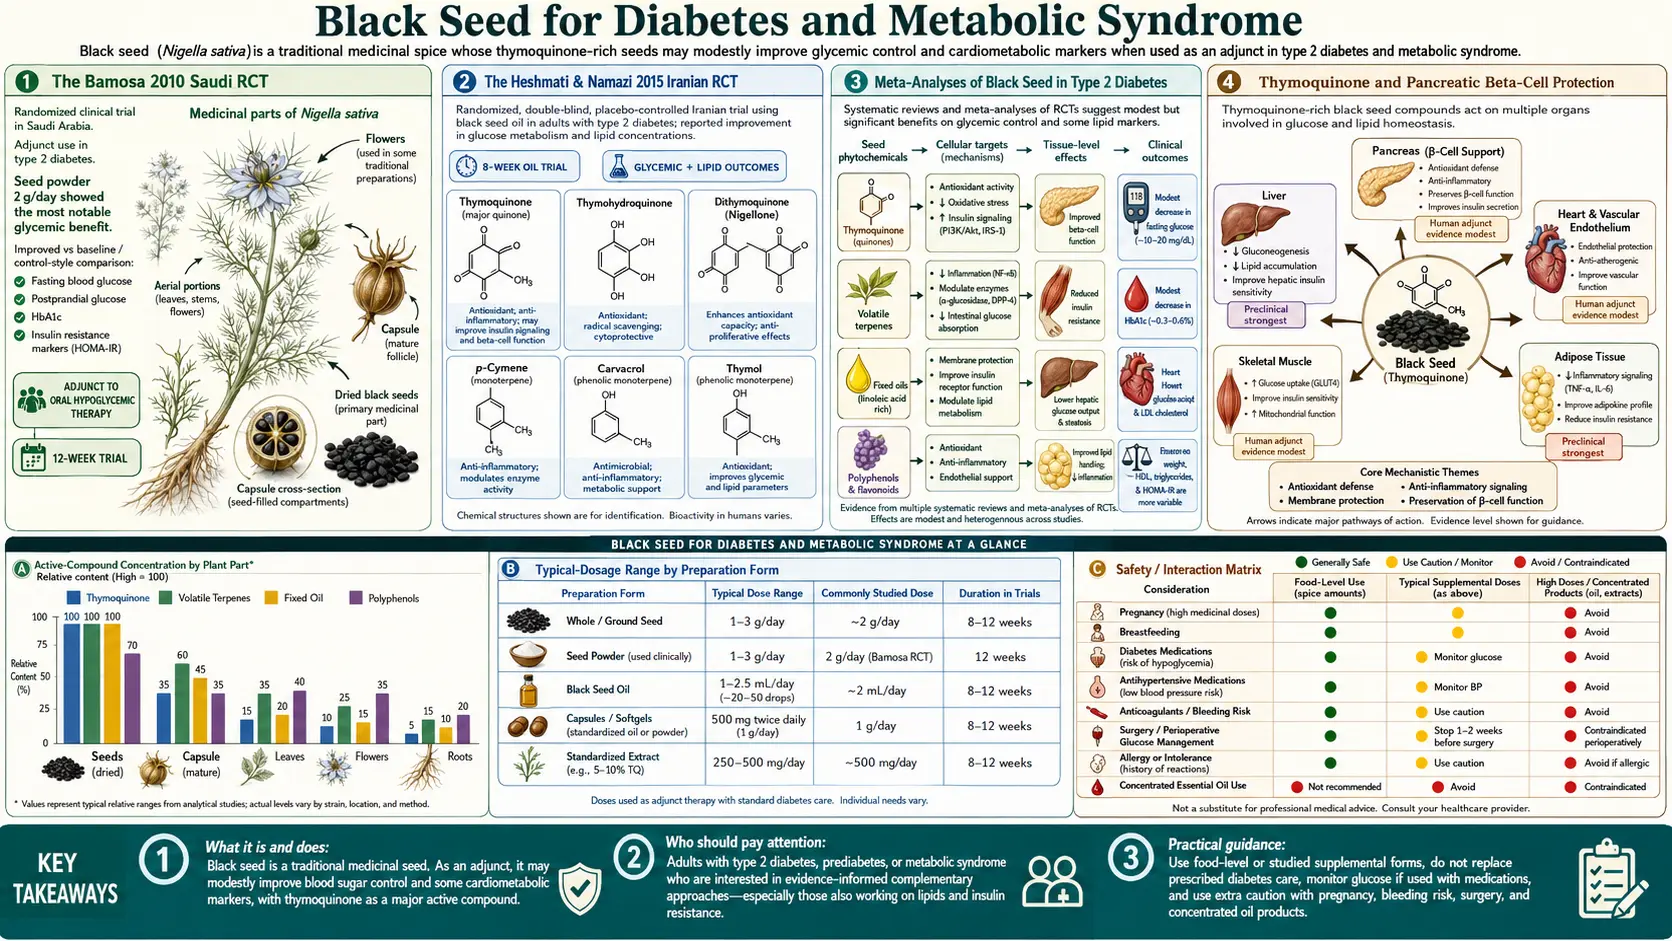
The strongest human evidence for any black seed indication is in type 2 diabetes. Two key randomized controlled trials ran for 12 weeks — Bamosa et al. 2010 (Saudi Arabia, 94 patients, black seed powder in capsules at 1, 2 or 3 grams per day) and Heshmati et al. 2015 (Iran, 72 patients, 3 grams per day of black seed oil versus placebo). In the Bamosa trial, hemoglobin A1c (HbA1c) fell by 1.52 percentage points from baseline at 2 grams per day, with no further gain at 3 grams; in the Heshmati trial, HbA1c fell significantly compared with placebo. Meta-analyses pooling many trials report smaller average falls in HbA1c, from 0.44 to 0.71 percentage points. The mechanism combines AMP-activated protein kinase (AMPK) activation (mimicking metformin), direct protection of pancreatic beta cells against oxidative damage, improved insulin sensitivity at the muscle and liver, and reductions in total cholesterol, low-density lipoprotein (LDL), and triglycerides. This deep-dive walks through both trials in clinical detail, the molecular mechanism, the doses used in the trials, and the safety considerations when combining black seed with conventional diabetes medication.
Table of Contents
- The Bamosa 2010 Saudi Randomized Controlled Trial
- The Heshmati et al. 2015 Iranian Randomized Controlled Trial
- Meta-Analyses of Black Seed in Type 2 Diabetes
- Thymoquinone and Pancreatic Beta-Cell Protection
- AMP-Activated Protein Kinase Activation — The Metformin-Like Mechanism
- Insulin Sensitivity at Muscle and Liver
- Lipid Improvements: Cholesterol, Low-Density Lipoprotein, Triglycerides
- Metabolic Syndrome and Weight Trial Evidence
- Doses Used in the Trials
- Drug Interactions and Hypoglycemia Risk
- Key Research Papers
- Connections
- Featured Videos
The Bamosa 2010 Saudi Randomized Controlled Trial
The Bamosa et al. 2010 trial published in the Indian Journal of Physiology and Pharmacology is the foundational human study for black seed in type 2 diabetes. The trial design:
- Population: 94 Saudi Arabian patients with type 2 diabetes, all on stable oral hypoglycemic therapy (sulfonylurea, biguanide, or both)
- Intervention: Three arms — black seed powder 1 g/day, black seed powder 2 g/day, or black seed powder 3 g/day, added to existing diabetes therapy
- Duration: 12 weeks
- Primary outcome: Fasting plasma glucose, hemoglobin A1c, and insulin levels
The 2 g/day dose gave the clearest result. The 1 g/day arm showed trends toward improvement that were not statistically significant from baseline, and the 3 g/day arm gave no further gain over 2 g/day. In the 2 g/day arm:
- Hemoglobin A1c reduction: 1.52 percentage points from baseline at the end of 12 weeks (P<0.0001)
- Fasting glucose reduction: an average of 45, 62 and 56 mg/dL at 4, 8 and 12 weeks
- Insulin resistance (homeostatic model assessment, HOMA2): significant reduction (P<0.01), while beta-cell function calculated by HOMA2 increased (P<0.02) at 12 weeks
- Adverse events: No clinically significant hypoglycemia, no gastrointestinal (GI) intolerance prompting discontinuation, no hepatic or renal abnormalities on lab monitoring
For context, the regulatory threshold for a new diabetes drug to be approved by the U.S. Food and Drug Administration (FDA) is typically a 0.5 percentage point hemoglobin A1c reduction versus placebo. The Bamosa effect size is three times that threshold.
The trial has limitations: single-blind rather than double-blind, single-center, and the patients were on background diabetes medication so the pure black-seed effect cannot be perfectly isolated. The trial also had no placebo group — it compared three doses. But the magnitude of effect at 2 g/day makes this one of the strongest human studies for any herbal hypoglycemic.
The Heshmati et al. 2015 Iranian Randomized Controlled Trial
The Heshmati et al. 2015 trial published in Food Research International tested black seed oil rather than seed powder:
- Population: 72 adults aged 30–60 with type 2 diabetes at endocrinology clinics in Kermanshah, Iran (36 per group; 67 finished the trial, and all 72 were included in the analysis)
- Intervention: Black seed oil 3 g/day as soft-gel capsules (one capsule three times a day) versus sunflower-oil soft-gel capsules as placebo
- Duration: 12 weeks
- Outcomes measured: body measurements, diet, and blood tests including fasting blood sugar, hemoglobin A1c, insulin and the lipid profile
Results:
- Significant changes versus placebo: fasting blood sugar, hemoglobin A1c, triglycerides and low-density lipoprotein (LDL) cholesterol (p<0.05, adjusted for confounding factors)
- Not significant after adjustment: insulin level and insulin resistance fell and high-density lipoprotein (HDL) cholesterol rose in the black seed group, but these changes were not significant once confounding factors were taken into account
- Body weight: weight and body mass index fell from baseline in the black seed group, but the difference between the two groups was not significant
- Size of the changes: the published summary of the trial does not give the change in each marker in mg/dL
The Heshmati design was stronger than Bamosa in two ways: it was double-blind, and it used a placebo arm rather than only dose comparisons. The finding of a significant hemoglobin A1c fall using a different form of black seed (oil vs powder), in a different population (Iranian vs Saudi), with a different design (placebo-controlled vs dose-ranging), strengthens the confidence that the effect is real and not a single-center artifact.
In this trial, blood sugar and two of the blood-fat markers (triglycerides and low-density lipoprotein) improved together compared with placebo; the high-density lipoprotein rise was not significant after adjustment, and the trial summary reports no blood-pressure result. Black seed's proposed multi-target activity at the nuclear factor kappa B (NF-kB) / AMP-activated protein kinase / lipid-metabolism node is the explanation usually offered for effects on both blood sugar and blood fats.
Meta-Analyses of Black Seed in Type 2 Diabetes
Several meta-analyses have pooled the available black seed diabetes trials. The 2017 meta-analysis by Daryabeygi-Khotbehsara et al. in Complementary Therapies in Medicine pooled seven trials in type 2 diabetes and found:
- Mean hemoglobin A1c reduction: 0.71 percentage points versus control
- Mean fasting glucose reduction: 17.84 mg/dL versus control
- Mean total cholesterol reduction: 22.99 mg/dL versus control
- Triglycerides: no significant overall change (−6.80 mg/dL, p=0.61); triglycerides fell with black seed oil (−14.8 mg/dL) but rose with seed powder (+29.4 mg/dL)
- Mean low-density lipoprotein reduction: 22.38 mg/dL versus control
- High-density lipoprotein: no significant change
The pooled effect is somewhat smaller than the individual Bamosa and Heshmati trials, partly because the meta-analysis includes lower-dose trials and trials with shorter duration. But the same direction for blood sugar, hemoglobin A1c and cholesterol across seven trials, conducted in different countries and using different black seed preparations, is the meaningful signal — this is not a single-trial finding that fails to replicate.
A 2019 meta-analysis by Askari et al. in Phytotherapy Research pooled 17 randomized controlled trials on blood-sugar control. Black seed lowered fasting glucose by 9.93 mg/dL, glucose after meals by 14.79 mg/dL and hemoglobin A1c by 0.57 percentage points; black seed oil lowered fasting glucose more than black seed powder.
A 2025 meta-analysis by Karimi et al. in Complementary Therapies in Medicine pooled 16 randomized controlled trials in people with type 2 diabetes. Black seed lowered fasting glucose by 21.43 mg/dL, hemoglobin A1c by 0.44 percentage points, total cholesterol by 18.80 mg/dL and low-density lipoprotein by 19.53 mg/dL. It found no significant effect on 2-hour after-meal glucose, fasting insulin, insulin resistance (HOMA), triglycerides, high-density lipoprotein, the liver enzymes aspartate aminotransferase (AST) and alanine aminotransferase (ALT), creatinine (a kidney marker), body weight or body mass index. In its subgroup analyses, the fasting-glucose fall was seen in trials longer than 8 weeks, and the falls in hemoglobin A1c, HOMA and low-density lipoprotein in trials using more than 1 g/day, trials of 8 weeks or less, and trials using the oil.
Thymoquinone and Pancreatic Beta-Cell Protection
Type 2 diabetes is characterized by both insulin resistance (peripheral tissues do not respond properly to insulin) and progressive pancreatic beta-cell failure (the cells that produce insulin gradually die off, partly from oxidative stress and partly from glucotoxicity). Most diabetes medications address insulin resistance (metformin, thiazolidinediones) or stimulate residual beta-cell function (sulfonylureas, glucagon-like peptide-1 (GLP-1) agonists). Few medications meaningfully protect the beta cells from ongoing damage.
Thymoquinone has shown striking beta-cell protective effects in animal models. In the classic streptozotocin (STZ) and alloxan diabetic-rat models — in which a single high dose of STZ or alloxan selectively destroys pancreatic beta cells via oxidative damage and produces diabetes within days — pretreatment with thymoquinone partially blocks beta-cell destruction. Histology of pancreatic islets in thymoquinone-pretreated rats shows preserved islet architecture and substantially higher beta-cell mass compared to untreated diabetic controls.
The mechanism involves several converging effects:
- Direct antioxidant activity — thymoquinone is a quinone with significant free-radical scavenging activity, particularly against the superoxide and hydroxyl radicals generated by STZ/alloxan metabolism in beta cells
- Mitochondrial protection — thymoquinone preserves mitochondrial membrane potential and prevents the mitochondrial permeability transition that triggers beta-cell apoptosis
- Anti-apoptotic signaling — thymoquinone upregulates Bcl-2 and downregulates Bax in beta cells, shifting the apoptosis/survival balance toward survival
- Suppression of NF-kB-driven inflammatory beta-cell damage — chronic low-grade pancreatic inflammation contributes to type 2 diabetes progression; thymoquinone's NF-kB inhibition addresses this
The human translation is necessarily indirect — we cannot biopsy human pancreatic islets to measure beta-cell mass in living patients — but in the Bamosa trial, beta-cell function calculated from blood tests (HOMA2) rose from baseline at 2 g/day (P<0.02) after 12 weeks; that trial had no placebo group, so it cannot show that black seed users keep beta-cell function better than people not taking it. This is a potentially distinctive benefit of black seed compared to most other diabetes interventions, which tend to either work the beta cells harder (sulfonylureas, accelerating burnout) or merely improve insulin response without addressing beta-cell preservation.
AMP-Activated Protein Kinase Activation — The Metformin-Like Mechanism
Metformin, the first-line oral medication for type 2 diabetes worldwide, works primarily by activating AMP-activated protein kinase (AMPK) in the liver. AMP-activated protein kinase is the cellular energy sensor — when cellular adenosine triphosphate (ATP) levels fall (signaling low energy), AMP-activated protein kinase activates a cascade of responses that increases adenosine triphosphate-generating processes (fatty acid oxidation, glucose uptake) and suppresses adenosine triphosphate-consuming processes (gluconeogenesis, fatty acid synthesis, cholesterol synthesis).
Thymoquinone activates AMP-activated protein kinase through a mechanism distinct from but parallel to metformin. The downstream effects on glucose metabolism are similar:
- Suppressed hepatic gluconeogenesis — the liver makes less glucose, lowering fasting glucose levels (this is the primary action of metformin and of black seed)
- Increased peripheral glucose uptake — skeletal muscle and adipose tissue take up more glucose, lowering postprandial glucose
- Suppressed lipogenesis — the liver makes less fatty acid and triglyceride, contributing to the lipid profile improvements
- Improved insulin sensitivity — AMP-activated protein kinase activation reduces hepatic insulin resistance over time
The clinical practical implication is that black seed and metformin appear to have additive rather than redundant glycemic effects in trial settings — patients on metformin who add black seed still see additional hemoglobin A1c reduction. The mechanisms overlap but the molecular targets are sufficiently distinct that the effects sum rather than max out. In the Bamosa trial, black seed was added to patients' existing diabetes medicines and hemoglobin A1c fell 1.52 percentage points from baseline at 2 g/day; with no placebo group, that trial cannot separate the black seed effect from other changes over the 12 weeks.
For people who cannot tolerate metformin (the gastrointestinal side effects are dose-limiting for 10–15% of users) or who have advanced renal disease that contraindicates metformin (estimated glomerular filtration rate (eGFR) < 30): none of the trials described on this page enrolled people with advanced kidney disease, and a 2013 case report described acute kidney failure in a diabetic patient taking black seed.
Insulin Sensitivity at Muscle and Liver
Beyond the AMP-activated protein kinase pathway, black seed appears to improve insulin signaling in skeletal muscle and liver through additional mechanisms. Animal studies have shown:
- Increased GLUT4 translocation to skeletal muscle cell membrane (the glucose transporter that responds to insulin)
- Increased IRS-1 phosphorylation (a key insulin signaling intermediate)
- Reduced hepatic insulin resistance markers
- Reduced inflammatory cytokines (tumor necrosis factor-alpha and interleukin-6) that drive insulin resistance
The tumor necrosis factor-alpha and interleukin-6 connection is particularly interesting because obesity-driven type 2 diabetes is increasingly understood as an inflammatory condition — chronic low-grade inflammation in adipose tissue and liver drives insulin resistance, which drives compensatory hyperinsulinemia, which over years drives beta-cell failure. By reducing the inflammatory signal at the source (NF-kB inhibition), black seed addresses the root inflammatory driver of type 2 diabetes, not just the downstream glucose elevation.
This is also why black seed's benefit is especially pronounced in patients with the obese, metabolic-syndrome phenotype of type 2 diabetes rather than in lean autoimmune-like type 2 diabetes or LADA (latent autoimmune diabetes in adults). For more on metabolic-syndrome-driven type 2 diabetes, see Insulin Resistance and Diabetes.
Lipid Improvements: Cholesterol, Low-Density Lipoprotein, Triglycerides
Black seed trials have measured blood fats alongside blood sugar. The Heshmati trial showed:
- Triglycerides and low-density lipoprotein: significant changes compared with placebo
- High-density lipoprotein: a rise in the black seed group that was not significant after adjustment for confounding factors
A 2016 meta-analysis by Sahebkar et al. pooled 17 randomized placebo-controlled trials of black seed and blood fats. Black seed lowered total cholesterol by 15.65 mg/dL, low-density lipoprotein by 14.10 mg/dL and triglycerides by 20.64 mg/dL, with no significant overall effect on high-density lipoprotein (0.28 mg/dL). Black seed oil lowered total cholesterol and low-density lipoprotein more than the seed powder, and a rise in high-density lipoprotein was found only with the seed powder.
The mechanism is multi-faceted:
- Reduced hepatic cholesterol synthesis — thymoquinone modestly inhibits HMG-CoA reductase (the enzyme target of statins) and reduces lipogenic gene expression
- Increased low-density lipoprotein receptor expression — more low-density lipoprotein receptors means more low-density lipoprotein clearance from circulation
- Improved triglyceride clearance — via AMP-activated protein kinase-mediated upregulation of fatty acid oxidation and lipoprotein lipase activity
- Improved high-density lipoprotein function and modest high-density lipoprotein elevation
For a person with combined metabolic syndrome (type 2 diabetes + dyslipidemia + hypertension), the pooled trials above report effects on two of the three components, blood sugar and blood fats. The size of each effect is smaller than with dedicated single-agent therapy (a full-dose statin reduces low-density lipoprotein by 40–60%).
Metabolic Syndrome and Weight Trial Evidence
Beyond strict type 2 diabetes, black seed has been studied in metabolic syndrome (the cluster of central obesity + dyslipidemia + hypertension + insulin resistance / hyperglycemia that precedes overt type 2 diabetes). The Mahdavi trial in obese women (90 enrolled, 84 completed; 8 weeks of black seed oil 3 g/day or placebo, with both groups on a low-calorie diet) showed, compared with placebo:
- Weight loss of 6.0% versus 3.6% in placebo
- Waist circumference reduction of 6.9% versus 3.4%
- Body mass index (BMI) reduction
- Triglyceride reduction (−14.0% versus +1.4%) and very-low-density lipoprotein reduction (−14.0% versus +7%)
The weight loss is modest in absolute terms, and it came on top of a low-calorie diet that both groups followed, so the trial tested black seed as an addition to diet rather than on its own.
For the broader metabolic-syndrome management framework, see Metabolic Syndrome and Blood Sugar Management.
Doses Used in the Trials
The doses and forms used in the trials described on this page:
- Whole black seed powder: the Bamosa trial gave 1, 2 or 3 grams per day in capsules; 2 g/day produced the significant changes and 3 g/day gave no further gain. 1 g = approximately 1/2 teaspoon ground.
- Black seed oil: the Heshmati trial used 3 g/day as soft-gel capsules (one three times a day); the Mahdavi trial used 3 g/day (1 g before each meal); the Najmi trial used 2.5 mL twice daily.
- Standardized capsule: extract products state a thymoquinone content on the label; none of the trials described on this page tested a standardized extract.
- Duration: the trials ran 6 to 12 weeks. In the Bamosa trial, fasting glucose was already 45 mg/dL lower at 4 weeks (62 at 8 weeks, 56 at 12 weeks); hemoglobin A1c was measured at 12 weeks.
- Monitoring: the trials measured hemoglobin A1c at the start and at the end. Low blood sugar (hypoglycemia) is the main risk when black seed is added to insulin or sulfonylureas, because the glucose-lowering effects add together.
- Lower hypoglycemia risk in combination with: Metformin, glucagon-like peptide-1 agonists, sodium-glucose cotransporter-2 (SGLT2) inhibitors — additive effects with low hypoglycemia risk.
- Higher hypoglycemia risk in combination with: Insulin, sulfonylureas (glipizide, glyburide), meglitinides (repaglinide) — these can produce hypoglycemia when combined with black seed, because the glucose-lowering effects add together.
Drug Interactions and Hypoglycemia Risk
- Insulin and sulfonylureas — the most important interaction. Black seed lowers blood glucose, and adding it to insulin or sulfonylurea therapy can produce hypoglycemia within days.
- Warfarin and antiplatelet drugs — black seed has mild antiplatelet activity. Combined with warfarin, aspirin, or clopidogrel, it may increase bleeding risk.
- Cytochrome P450 3A4 (CYP3A4) substrates — black seed inhibits cytochrome P450 3A4 (the cytochrome P450 enzyme responsible for metabolizing many drugs). This can elevate serum levels of:
- Statins (simvastatin and lovastatin particularly affected; atorvastatin less so)
- Calcium channel blockers (amlodipine, felodipine)
- Cyclosporine, tacrolimus (raised levels of these drugs are a particular concern for organ transplant patients)
- Some chemotherapy drugs
- Antihypertensive drugs — black seed lowers blood pressure modestly. Combined with angiotensin-converting enzyme inhibitors (ACE inhibitors), angiotensin receptor blockers (ARBs), or other antihypertensives, may produce additive blood pressure reduction.
- Pregnancy — animal studies report uterine-stimulant effects and dose-dependent abortifacient (miscarriage-causing) activity of high-dose black seed.
- Surgery — the antiplatelet effect described above is relevant to bleeding during and after surgery.
The good news: in the clinical trials, no serious adverse events have been reported at the doses used. The interactions above are manageable with awareness and appropriate monitoring. Black seed is one of the better-tolerated herbal interventions in diabetes care, with substantially fewer side effects than metformin (no gastrointestinal intolerance), sulfonylureas (hypoglycemia, weight gain), or thiazolidinediones (fluid retention, fracture risk).
Key Research Papers
- Bamosa AO et al. (2010). Effect of Nigella sativa seeds on the glycemic control of patients with type 2 diabetes mellitus. Indian Journal of Physiology and Pharmacology. — PubMed PMID: 21675032
- Heshmati J, Namazi N, Memarzadeh MR, Taghizadeh M, Kolahdooz F (2015). Nigella sativa oil affects glucose metabolism and lipid concentrations in patients with type 2 diabetes: A randomized, double-blind, placebo-controlled trial. Food Research International, 70, 87–93. — doi:10.1016/j.foodres.2015.01.030
- Daryabeygi-Khotbehsara R et al. (2017). Nigella sativa improves glucose homeostasis and serum lipids in type 2 diabetes: A systematic review and meta-analysis. Complementary Therapies in Medicine. — PubMed PMID: 29154069
- Askari G, Rouhani MH, Ghaedi E, Ghavami A, Nouri M, Mohammadi H (2019). Effect of Nigella sativa (black seed) supplementation on glycemic control: A systematic review and meta-analysis of clinical trials. Phytotherapy Research. — PubMed PMID: 30873688
- Karimi M, Pirzad S, Pourfaraji SMA, Sedgi FM, Darouei B, Amani-Beni R, Kazemi K, Rabiee R (2025). Effects of black seed (Nigella sativa L.) on cardiometabolic indices in type 2 diabetic patients: A systematic review and meta-analysis of RCTs. Complementary Therapies in Medicine. — PubMed PMID: 40210172
- Mahdavi R et al. (2015). Effects of Nigella sativa oil with a low-calorie diet on cardiometabolic risk factors in obese women: a randomized controlled clinical trial. Food & Function. — PubMed PMID: 26029855
- Kanter M, Coskun O, Korkmaz A, Oter S (2004). Effects of Nigella sativa on oxidative stress and beta-cell damage in streptozotocin-induced diabetic rats. Anatomical Record Part A. — PubMed PMID: 15224410
- El-Mahmoudy A et al. (2005). Successful abrogation by thymoquinone against induction of diabetes mellitus with streptozotocin via nitric oxide inhibitory mechanism. International Immunopharmacology. — PubMed PMID: 15589481
- Najmi A, Nasiruddin M, Khan RA, Haque SF (2008). Effect of Nigella sativa oil on various clinical and biochemical parameters of insulin resistance syndrome. International Journal of Diabetes in Developing Countries. — PubMed PMID: 19902033
- Sahebkar A et al. (2016). Nigella sativa (black seed) effects on plasma lipid concentrations in humans: A systematic review and meta-analysis of randomized placebo-controlled trials. Pharmacological Research. — PubMed PMID: 26875640
- Benhaddou-Andaloussi A et al. (2011). The in vivo antidiabetic activity of Nigella sativa is mediated through activation of the AMPK pathway and increased muscle Glut4 content. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 21584245
- Fararh KM, Atoji Y, Shimizu Y, Takewaki T (2002). Isulinotropic properties of Nigella sativa oil in Streptozotocin plus Nicotinamide diabetic hamster. Research in Veterinary Science. — PubMed PMID: 12443686
- Razavi BM, Hosseinzadeh H (2014). A review of the effects of Nigella sativa L. and its constituent, thymoquinone, in metabolic syndrome. Journal of Endocrinological Investigation. — PubMed PMID: 25125023
- Arslan E, Sayin S, Demirbas S, Cakar M, Somak NG, Yesilkaya S, Saglam K (2013). A case study report of acute renal failure associated with Nigella sativa in a diabetic patient. Journal of Integrative Medicine. — PubMed PMID: 23464648
PubMed Topic Searches
Connections
- All Herbs
- Black Seed Overview
- Black Seed Benefits Hub
- Black Seed for Immune & Antiviral
- Black Seed for Asthma
- Black Seed for Inflammation
- Type 2 Diabetes
- Insulin Resistance
- Metabolic Syndrome
- Blood Sugar Management
- Fenugreek (parallel blood-sugar herb)
- Cinnamon
- Berberine (parallel AMP-Activated Protein Kinase activator)
- Turmeric
- Magnesium (insulin sensitivity)
- Chromium
- Hemoglobin A1c Lab Test
- Continuous Glucose Monitor
- Metformin — the first-line AMP-activated protein kinase-activating diabetes drug black seed is benchmarked against and combined with.
- History