⚠ Evidence warning: Clinical trials or other evidence do not support the claims that black seed with honey shortens cough and bronchitis, and that steam or nasal use clears airways. This page keeps it as a report of what people, websites or other media say.
Black Seed for Asthma and Respiratory Function
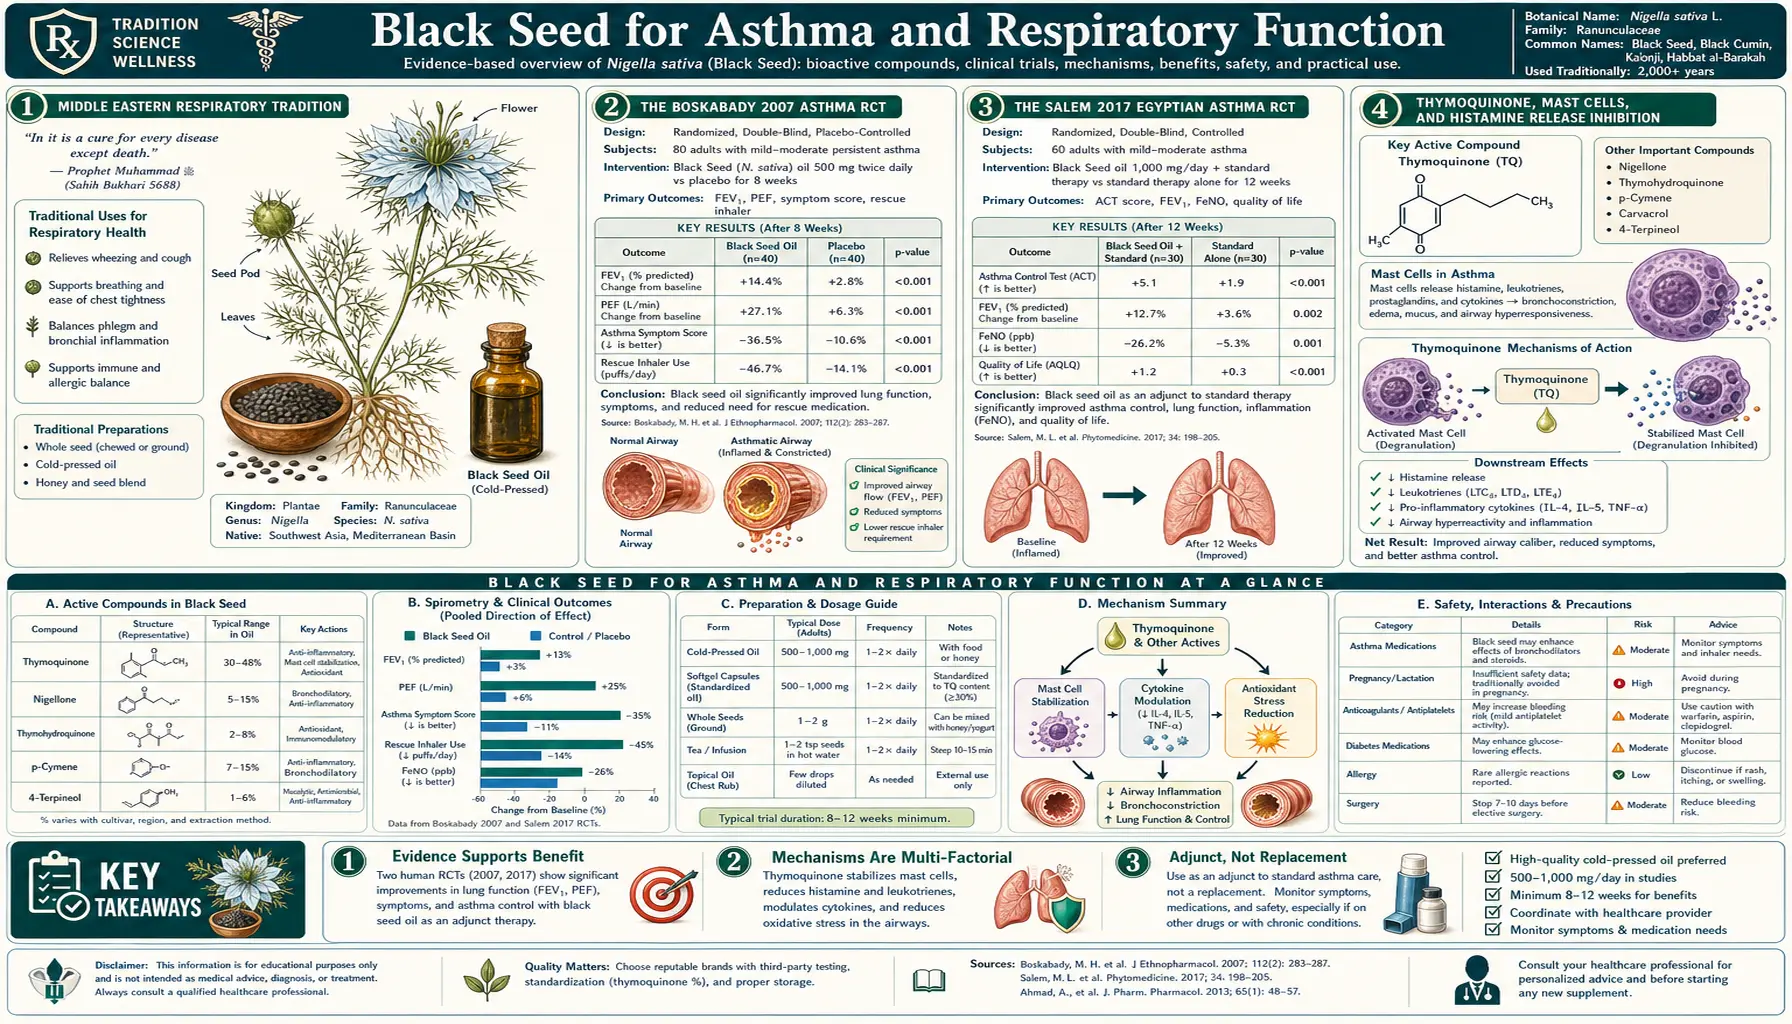
Asthma is the most clinically studied respiratory application of black seed. Three small randomized controlled trials — Boskabady et al. 2007 (Iran, a boiled seed extract), Salem et al. 2017 (Saudi Arabia, partly controlled adult asthma, ground whole seed) and Koshak et al. 2017 (Saudi Arabia, oil capsules) — gave black seed on top of usual asthma treatment and reported better asthma symptoms or control scores, with some lung function gains such as FEV1 (forced expiratory volume in one second) in the first two. A 2017 literature review called the evidence “scanty” and said it is often based on poorly characterised preparations. The proposed mechanism has three parts: nigellone and thymoquinone inhibit histamine release from mast cells (in laboratory rat cells), a seed extract relaxes the airway smooth muscle, and thymoquinone reduces airway inflammation via NF-kB inhibition. The Middle Eastern medical tradition of using black seed for cough, bronchitis, and chest congestion is a report of long use; no trial of those uses was found.
Table of Contents
- Middle Eastern Respiratory Tradition
- The Boskabady 2007 Asthma Randomized Controlled Trial
- The Salem 2017 Saudi Asthma Randomized Controlled Trial
- The Koshak 2017 Oil Capsule Trial
- Thymoquinone, Mast Cells, and Histamine Release Inhibition
- Direct Bronchodilation Mechanism
- Reduction of Airway Inflammation (NF-kB Pathway)
- Allergic Rhinitis Evidence
- Cough, Bronchitis, and Acute Respiratory Tract Use
- Chronic Obstructive Pulmonary Disease Evidence and Limitations
- Doses in the Trials and in Traditional Use
- Cautions and Limits
- Key Research Papers
- Connections
- Featured Videos
Middle Eastern Respiratory Tradition
The traditional Middle Eastern and South Asian use of black seed for respiratory complaints stretches back to at least the time of Avicenna (Ibn Sina, 980–1037 CE), whose Canon of Medicine recommends black seed for cough, breathing difficulty, fever, and chest tightness. The traditional preparations include:
- Steam inhalation — black seeds added to boiling water; the volatile thymoquinone-rich steam inhaled to clear nasal congestion and reduce bronchoconstriction
- Oral with honey — one teaspoon ground black seed mixed with one teaspoon honey, taken twice daily for cough and respiratory infection
- Chest poultice — warm black seed oil massaged into the chest for bronchitis and chest cold (still common in modern Yemeni and Egyptian folk practice)
- Smoking inhalation — in some older traditions, black seeds were burned and the smoke inhaled, similar to the use of stramonium and other anti-asthmatic plants in nineteenth-century Western pharmacopoeias before pharmaceutical bronchodilators
Modern pharmacology has explained why these preparations might genuinely have worked. Thymoquinone is volatile enough to be carried in steam, and inhalation delivers it directly to the bronchial mucosa where its anti-inflammatory and mast-cell-stabilizing effects are immediately relevant. Honey is itself mildly anti-inflammatory and has demonstrated benefit for acute cough in children (per multiple controlled trials). The traditional combination is mechanistically sound, not folk superstition.
The Boskabady 2007 Asthma Randomized Controlled Trial
The Boskabady 2007 trial published in Fundamental & Clinical Pharmacology is the earliest of the three trials on this page. The authors call it a phase I study. The design:
- Population: 29 Iranian adults with asthma, randomly divided into a control group (14) and a study group (15)
- Intervention: The abstract gives “15 mL/kg of 0.1 g% boiled extract” daily versus a placebo solution; an erratum to the paper exists and its content was not read
- Duration: 3 months
- Outcomes: Asthma symptom score, asthma severity, symptoms per week, wheezing, lung function tests and the drugs patients were using
Results favored the black seed arm:
- All asthma symptoms, symptom frequency and chest wheezing improved significantly in the black seed arm at 45 days and at 3 months against the start (P < 0.05 to P < 0.001); at 3 months every symptom differed significantly from the control group, which showed only small improvements at the second visit
- Lung function test values improved significantly in the black seed arm against the start; the abstract gives no percentages
- Drug use (inhaled and oral beta-agonists, oral corticosteroid, oral theophylline and inhaled corticosteroid) fell in the black seed arm by the end of the study, with no obvious change in controls; the abstract gives no doses or puff counts
The Boskabady 2007 limitations were primarily sample size (29 patients) and a single dose, so it cannot show a dose-response. The authors said the results generally suggest a preventive effect and warrant further research. A 2017 literature review later counted 14 animal or cell studies and 7 clinical studies of black seed in asthma, and said the evidence “remains scanty” and is often based on poorly characterised preparations.
The Salem 2017 Saudi Asthma Randomized Controlled Trial
The Salem et al. 2017 trial was published in the Annals of Saudi Medicine. Design:
- Population: Patients with partly controlled asthma at a university hospital clinic in eastern Saudi Arabia, in groups of 24 (placebo), 26 and 26, on inhaled maintenance therapy; the trial was single-blind
- Intervention: 1 g or 2 g a day of whole ground seed in capsules, versus a charcoal placebo capsule, added to existing therapy
- Duration: 3 months, with visits at 6 and 12 weeks
- Outcomes: Asthma Control Test (ACT) score, exhaled nitric oxide, peak expiratory flow (PEF) variability and other lung function tests, total serum immunoglobulin E (IgE), serum cytokines and frequency of attacks (exacerbations)
Results:
- ACT score improved significantly at 6 and 12 weeks against baseline at both doses
- FEV1 (% predicted) rose significantly at 6 and 12 weeks only at 2 g/day; PEF variability improved at both doses compared with controls
- Exhaled nitric oxide — a marker of airway inflammation — fell significantly after 12 weeks at both doses against baseline
- Serum immunoglobulin E fell significantly after 12 weeks at both doses against baseline
- Cytokines — interferon-gamma rose at 12 weeks against baseline at both doses; interleukin-4, interleukin-10, interleukin-17A and the eotaxins did not change significantly in any group
- Attacks — significantly fewer patients had exacerbations at 1 g/day
- Side effects — none reported by any participant
The trial was placebo-controlled and the patients remained on their standard controller therapy throughout — a design that studies adding black seed rather than replacing medicine. The authors concluded that it “improves some measures of pulmonary function and inflammation in partly controlled asthma”; many of the changes were measured against baseline, and no lavage or sputum samples were taken.
The Koshak 2017 Oil Capsule Trial
In this double-blind trial in Saudi Arabia, published in Phytotherapy Research, 80 adults with asthma took black seed oil capsules 500 mg or placebo twice daily for 4 weeks on top of their usual treatment. Ten people in each group withdrew.
- ACT score — 21.1 on oil against 19.6 on placebo after 4 weeks (p = 0.044). ACT >20 is the threshold for “well-controlled asthma.”
- Blood eosinophils — fell by 50 cells/µL on oil against a rise of 15 on placebo (p = 0.013)
- Lung function — FEV1 (% predicted) rose by 4 against 1, which was not significant (p = 0.170)
The authors said future studies need longer follow-up across several centres.
Thymoquinone, Mast Cells, and Histamine Release Inhibition
The cornerstone mechanism for black seed in asthma is mast cell stabilization — the inhibition of histamine and other inflammatory mediator release from mast cells in airway tissue. Mast cells are sentinel immune cells densely populated in airway mucosa, gastrointestinal mucosa, skin, and blood vessel walls. When activated by immunoglobulin E-allergen crosslinking on their surface, mast cells release granules containing histamine, tryptase, chymase, leukotrienes, prostaglandin D2, and platelet-activating factor — the cocktail responsible for the symptoms of allergic asthma, allergic rhinitis, urticaria, and anaphylaxis.
Cromolyn sodium was the first pharmaceutical mast cell stabilizer, developed in the 1960s based on khellin from Ammi visnaga (a Middle Eastern medicinal plant). Cromolyn works by stabilizing the mast cell membrane and preventing degranulation in response to allergen challenge.
Both thymoquinone and nigellone (the carbonyl polymer of thymoquinone formed during black seed oil aging) appear to function as natural mast cell stabilizers via a similar mechanism. A 1993 laboratory study on rat peritoneal mast cells found that nigellone in relatively low concentrations was very effective at inhibiting histamine release triggered by antigen in sensitized cells and by other agents; no work on human mast cells was read for this page. Animal reports describe reduced histamine and tryptase in lung washings from asthmatic-model animals after black seed treatment.
This is the proposed reason black seed could help asthma patients alongside their existing inhaler therapy: it would address the upstream mast cell degranulation that drives the entire allergic-asthma cascade, complementing but not duplicating the action of beta-2 agonists (which dilate already-constricted airways) or inhaled corticosteroids (which broadly suppress airway inflammation downstream of mast cell activation).
For more on mast cell stabilization broadly, including the related condition of mast cell activation syndrome (MCAS), see Mast Cell Activation Syndrome (MCAS) and Natural Mast Cell Stabilizers.
Direct Bronchodilation Mechanism
In addition to upstream mast cell stabilization, thymoquinone has demonstrated direct bronchodilator activity on airway smooth muscle in isolated tissue preparations. Tracheal rings from guinea pigs and rats, when pre-contracted with methacholine or histamine, show measurable relaxation upon thymoquinone application — an effect that is independent of beta-2 adrenergic receptors (because pretreatment with beta-2 blockers does not abolish the bronchodilation).
Reduced intracellular calcium release from the sarcoplasmic reticulum and possibly direct potassium channel opening have been proposed. Calcium channel blockade has been proposed too, but the same Iranian research group tested it on guinea pig trachea with seed extracts and concluded that it does not contribute to the relaxant effect.
There is one human measurement. In 15 asthma patients, boiled extract at 50 and 100 mg/kg raised lung function tests from 30 minutes to about 150 minutes after a dose. Most measures rose less than with theophylline, and the effect was significantly less than salbutamol at 30 minutes.
The weaker effect and 30-minute onset mean black seed extract does not match a rescue inhaler in an acute asthma attack. Practitioners propose that daily use adds a background bronchodilator tone to the controller medicine's anti-inflammatory effect.
The combined effect of (mast cell stabilization preventing future bronchoconstrictor mediator release) + (direct bronchodilation reducing baseline airway tone) + (anti-inflammatory effect reducing chronic airway inflammation) is the proposed case for black seed in asthma.
Reduction of Airway Inflammation (NF-kB Pathway)
Chronic eosinophilic airway inflammation is the underlying pathology of allergic asthma. Eosinophils accumulate in the airway mucosa, degranulate to release major basic protein and eosinophil cationic protein (which damage epithelium), and perpetuate a cycle of inflammation that drives remodeling of the airway wall over years — smooth muscle hypertrophy, basement membrane thickening, mucus gland hyperplasia — producing the fixed component of airflow obstruction in long-standing asthma.
Thymoquinone's NF-kB inhibition addresses this inflammation upstream. NF-kB drives the expression of cytokines (IL-4, IL-5, IL-13, IL-25, IL-33, TSLP) that recruit and activate eosinophils. By suppressing NF-kB activation, thymoquinone is proposed to reduce eosinophil recruitment to airway tissue and eosinophil degranulation. The Koshak 2017 trial measured the related blood marker: eosinophils fell by 50 cells/µL on oil against a rise of 15 on placebo (p = 0.013), alongside better control scores but no significant change in FEV1.
This is the same molecular mechanism that drives the benefit seen in rheumatoid arthritis (where NF-kB-driven synovial inflammation is the target) and in type 2 diabetes (where NF-kB-driven adipose tissue inflammation drives insulin resistance). One target, three clinical applications.
Allergic Rhinitis Evidence
Allergic rhinitis (hay fever) shares the same immunoglobulin E / mast cell / histamine mechanism as allergic asthma, but affects the upper rather than lower airway. Given the mast cell stabilization effect of thymoquinone, allergic rhinitis is a logical target for black seed therapy.
Several controlled trials have documented benefit:
- Nikakhlagh et al. 2011 — a double-blind trial of 66 patients with allergic rhinitis given black seed oil or placebo, followed to day 30. The black seed arm showed significant reductions in nasal congestion, runny nose, sneezing attacks, and itchy nose.
- Alsamarai et al. 2014 — tested topical black seed oil drops in the nostrils for allergic rhinitis. Significant symptom reduction.
- Several smaller case series consistently report benefit at the 1–2 g/day oral dose range over 4–8 weeks.
The clinical implication is that patients suffering both allergic asthma and allergic rhinitis (a common combination — the "unified airway" hypothesis) may get integrated benefit across both conditions from a single black seed regimen. This is parallel to what oral antihistamines and to a lesser extent inhaled corticosteroids accomplish, but with a different mechanism that may be useful for patients who do not tolerate or do not fully respond to conventional therapy.
For the broader allergy management framework, see Allergy & Immunology and Allergic Rhinitis.
Cough, Bronchitis, and Acute Respiratory Tract Use
For acute respiratory tract irritation — cough, bronchitis, post-viral airway hyperreactivity — black seed has a substantial folk-tradition base and limited but supportive modern data. A 2018 comparative review of cough-suppressing (antitussive) plants reported the most potent effect for black seed and flaxseed on coughs induced by sulfur dioxide, and said only a few clinical studies of medicinal plants for cough exist.
The mechanism proposed for the cough-suppressing effect is reduced airway sensory nerve hyper-excitability (the C-fiber and Adelta-fiber neurons that initiate the cough reflex). There may also be a TRPV1 receptor desensitization component — thymoquinone has been shown to interact with TRPV1, the sensory neuron channel responsible for the burning sensation of capsaicin and the cough response to irritant stimuli.
For acute bronchitis, people who use the traditional Yemeni black-seed-and-honey preparation report mild benefit for symptom severity and duration. No controlled trial of it was found. What people describe:
- A cough that clears a day or two sooner
- Less perceived need for antibiotics
- Less sleep disruption from night-time cough
The traditional home use is 1 teaspoon black seed oil with 1 teaspoon raw honey, taken twice daily, started at the first sign of respiratory illness and continued until symptoms clear, alongside fluids, rest and the standard supportive measures.
Chronic Obstructive Pulmonary Disease Evidence and Limitations
Chronic obstructive pulmonary disease (COPD) is mechanistically distinct from asthma — chronic obstructive pulmonary disease involves neutrophilic rather than eosinophilic inflammation, with parenchymal destruction (emphysema) and chronic mucus hypersecretion (chronic bronchitis) as the dominant pathologies. The mast cell stabilization and Th2-suppression mechanisms that work in asthma are less directly relevant to chronic obstructive pulmonary disease.
However, a randomized trial in chronic obstructive pulmonary disease has reported some benefit:
- In a 2020 randomized double-blind trial, 100 people with mild to moderate chronic obstructive pulmonary disease took standard medicine alone or with black seed oil for 3 months (44 and 47 assessed). The oil group had better lung function tests and lower interleukin-6 and tumor necrosis factor-alpha than controls
- This suggests some role for the bronchodilator and anti-inflammatory effects independent of the Th2/mast cell axis; it is one trial, and black seed was given as an add-on
Black seed has been tested only as an add-on in this disease — smoking cessation, inhaled bronchodilators, pulmonary rehabilitation, and (in advanced disease) supplemental oxygen remain the foundation of chronic obstructive pulmonary disease care. Black seed may have adjunct utility for the inflammatory component, particularly in patients with the asthma-COPD overlap syndrome (ACOS) where Th2 inflammation plays a larger role.
Doses in the Trials and in Traditional Use
- For persistent asthma (adjunct to controller therapy): The trials used black seed oil 500 mg capsule twice daily (Koshak 2017) or 1–2 g a day of ground whole seed (Salem 2017), with patients staying on their usual inhalers. Practitioners also describe 1–2 teaspoons cold-pressed black seed oil daily. No trial tested lowering controller medicine.
- For allergic rhinitis: Practitioners describe black seed oil 500–1000 mg twice daily orally, or 1–2 drops of black seed oil in each nostril twice daily. The Alsamarai nasal-drop trial ran for 6 weeks.
- For acute cough / bronchitis: Traditional use is 1 teaspoon black seed oil + 1 teaspoon raw honey, twice daily, starting at first symptom, continued until it clears, sometimes with steam inhalation of 1 teaspoon black seed in boiling water.
- Timing with inhalers: No absorption interaction with inhaled medicines has been documented; some practitioners describe spacing them 2 hours apart.
- Follow-up: The trials measured ACT scores at 4, 6 and 12 weeks.
Cautions and Limits
- Not a rescue medication — black seed extract acted more weakly than salbutamol at 30 minutes in the one human comparison, and no trial tested it in an acute attack. Asthma attacks are treated with a rapid-acting inhaler such as albuterol/salbutamol. Severe breathlessness that does not ease is a sign hospitals treat as urgent.
- Tested only as an add-on to controller medicine — the trials gave black seed as an adjunct to standard controller therapy. Stopping inhaled corticosteroids or long-acting beta-agonists in favor of black seed risks serious exacerbation and is not what the clinical trial data tested.
- Black seed has no role in anaphylaxis — for acute anaphylaxis (food allergy, insect sting), epinephrine is the treatment.
- Pregnancy — high-dose black seed is contraindicated in pregnancy (uterine-stimulant effects, dose-dependent abortifacient activity in animal studies). Inhaled controller therapy is considered safe in pregnancy, and replacing it with black seed has not been studied.
- Drug interactions — cytochrome P450 3A4 (CYP3A4) inhibition can elevate serum levels of some statins and various cardiac medications. Theophylline (still occasionally used in asthma) is cleared mainly through cytochrome P450 1A2, with 2E1 and 3A3, per its label; no study of black seed with theophylline was read for this page.
- Allergic reaction to black seed itself — rare but documented.
- Children — a 2025 review of 15 pediatric clinical trials reported no severe adverse effects, but said more high-quality studies are needed to establish dose, form and safety in children.
- Quality matters — thymoquinone content varies widely across commercial black seed products, one reason a 2017 literature review faulted poorly characterised preparations.
For the broader asthma management framework, see Asthma and Pulmonology.
Key Research Papers
- Boskabady MH, Javan H, Sajady M, Rakhshandeh H (2007). The possible prophylactic effect of Nigella sativa seed extract in asthmatic patients. Fundamental & Clinical Pharmacology 21(5):559-66. — PubMed PMID: 17868210
- Salem AM, Bamosa AO, Qutub HO, Gupta RK, Badar A, Elnour A, Afzal MN (2017). Effect of Nigella sativa supplementation on lung function and inflammatory mediators in partly controlled asthma: a randomized controlled trial. Annals of Saudi Medicine 37(1):64-71. — PubMed PMID: 28151459
- Koshak A, Wei L, Koshak E, Wali S, Alamoudi O, Demerdash A, Qutub M, Pushparaj PN, Heinrich M (2017). Nigella sativa Supplementation Improves Asthma Control and Biomarkers: A Randomized, Double-Blind, Placebo-Controlled Trial. Phytotherapy Research 31(3):403-409. — PubMed PMID: 28093815
- Koshak A, Koshak E, Heinrich M (2017). Medicinal benefits of Nigella sativa in bronchial asthma: A literature review. Saudi Pharmaceutical Journal 25(8):1130-1136. — PubMed PMID: 30166900
- Boskabady MH, Mohsenpoor N, Takaloo L (2010). Antiasthmatic effect of Nigella sativa in airways of asthmatic patients. Phytomedicine 17(10):707-13. — PubMed PMID: 20149611
- Saadat S, Shakeri F, Boskabady MH (2018). Comparative Antitussive Effects of Medicinal Plants and Their Constituents. Alternative Therapies in Health and Medicine 24(4):36-49. — PubMed PMID: 29332022
- Nikakhlagh S et al. (2011). Herbal treatment of allergic rhinitis: the use of Nigella sativa. American Journal of Otolaryngology. — PubMed PMID: 20947211
- Alsamarai AM et al. (2014). Evaluation of topical black seed oil in the treatment of allergic rhinitis. Anti-Inflammatory & Anti-Allergy Agents in Medicinal Chemistry. — PubMed PMID: 23855426
- Boskabady MH, Shirmohammadi B, Jandaghi P, Kiani S (2004). Possible mechanism(s) for relaxant effect of aqueous and macerated extracts from Nigella sativa on tracheal chains of guinea pig. BMC Pharmacology 4:3. — PubMed PMID: 15070429
- Chakravarty N (1993). Inhibition of histamine release from mast cells by nigellone. Annals of Allergy. — PubMed PMID: 7680846
- Kalus U et al. (2003). Effect of Nigella sativa (black seed) on subjective feeling in patients with allergic diseases. Phytotherapy Research. — PubMed PMID: 14669258
- Keyhanmanesh R et al. (2010). Effect of thymoquinone, the main constituent of Nigella sativa, on tracheal responsiveness and white blood cell count in lung lavage of sensitized guinea pigs. Planta Medica. — PubMed PMID: 19711253
- Al-Azzawi MA, AboZaid MMN, Ibrahem RAL, Sakr MA (2020). Therapeutic effects of black seed oil supplementation on chronic obstructive pulmonary disease patients: A randomized controlled double blind clinical trial. Heliyon 6(8):e04711. — PubMed PMID: 32904114
- Abumadini MM, Ahmad S, AlYahya W, Amalraj C, AlGindan Y (2025). Clinical Uses of Nigella Sativa in Pediatrics: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Journal of Pediatric Pharmacology and Therapeutics 30(5):580-592. — PubMed PMID: 41112345
- Gilani AH et al. (2004). A review of medicinal uses and pharmacological activities of Nigella sativa. Pakistan Journal of Biological Sciences 7:441-451. — doi:10.3923/pjbs.2004.441.451
PubMed Topic Searches
Connections
- All Herbs
- Black Seed Overview
- Black Seed Benefits Hub
- Black Seed for Immune & Antiviral
- Black Seed for Diabetes
- Black Seed for Inflammation
- Asthma
- Pulmonology
- Mast Cell Activation Syndrome (MCAS)
- Natural Mast Cell Stabilizers
- Ginger (parallel anti-inflammatory)
- Turmeric
- Quercetin (natural antihistamine)
- Vitamin C
- Vitamin D3
- Magnesium (bronchodilator)
- Honey (traditional pairing)
- Immune Boosting
- History