⚠ Evidence warning: Clinical trials or other evidence do not support the claim that St. John's wort oil speeds the healing of burns, bruises and chronic wounds (pressure, venous and diabetic foot ulcers), clears warts and cervical dysplasia, eases neuralgia and sciatica, and that modern research has substantially validated these traditional uses. This page keeps it as a report of what people, websites or other media say.
St. John's Wort for Antiviral and Wound-Healing Applications
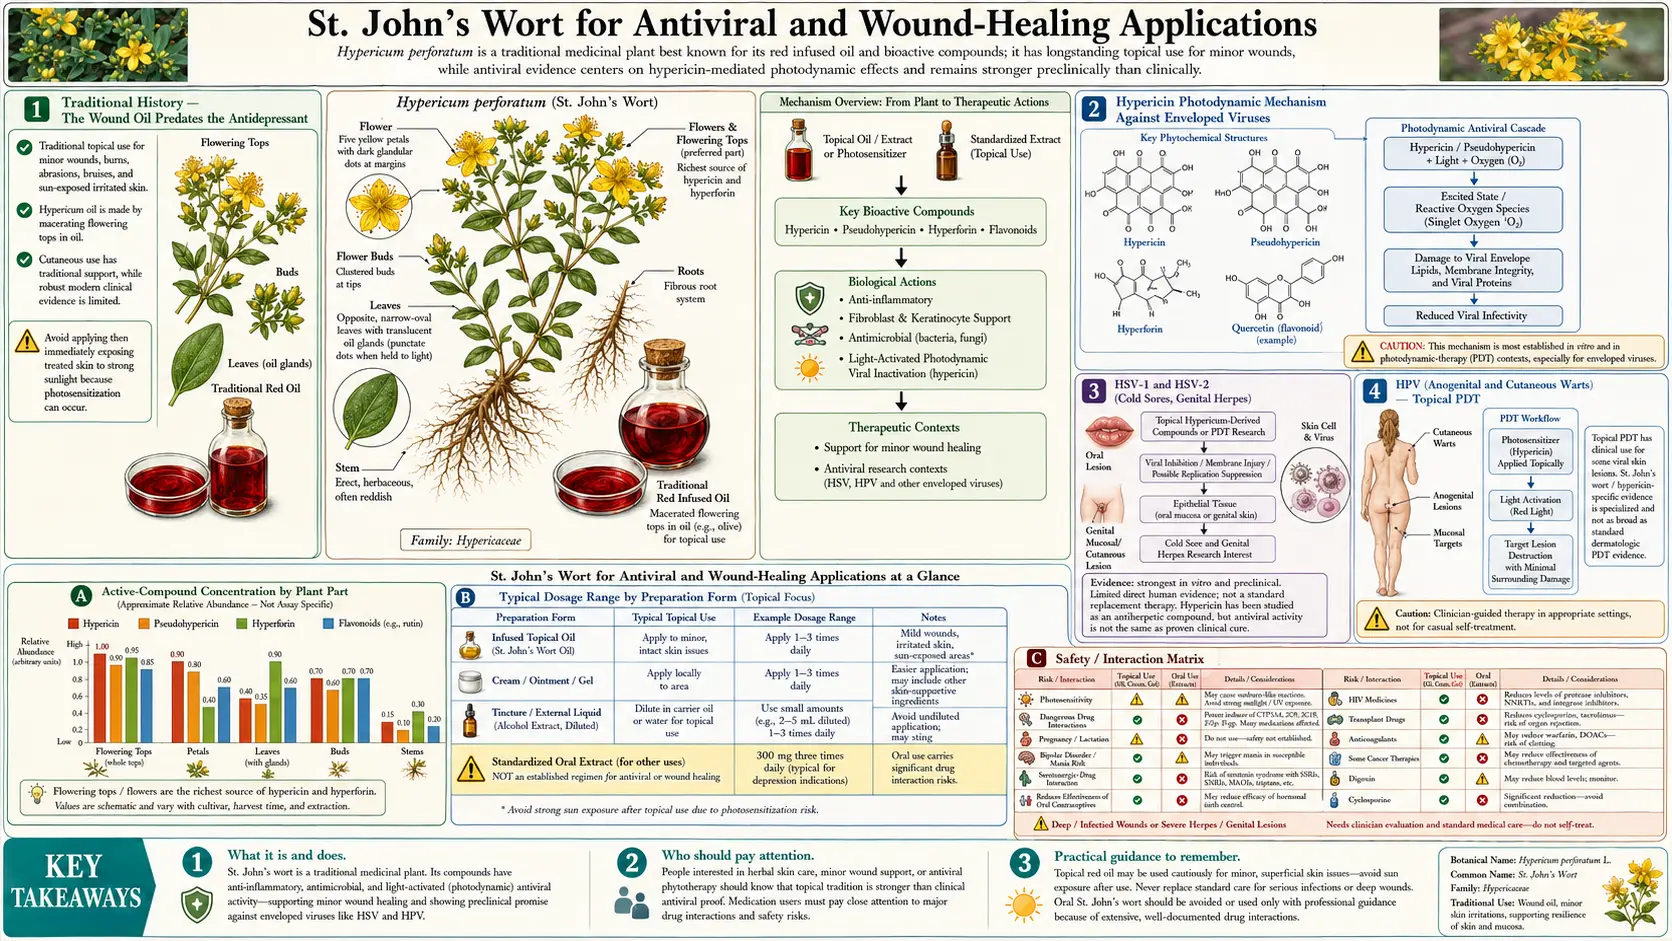
Long before St. John's Wort became famous as an antidepressant in the 1990s, the herb was renowned throughout European folk medicine as a wound-healing and nerve-soothing topical. The traditional preparation called Oleum Hyperici, "St. John's Oil," or "Red Oil" — fresh hypericum flowers infused in olive oil and sun-cured for several weeks until the oil turned deep crimson with extracted hypericin — was a staple of household medicine cabinets from medieval times through the 19th century. Modern research has substantially validated the traditional indications: hypericin is a potent photodynamic agent generating singlet oxygen under visible light that damages enveloped viral particles (HSV-1, HSV-2, influenza), hyperforin directly disrupts bacterial membranes including those of methicillin-resistant Staphylococcus aureus (MRSA), and the topical oil's combination of anti-inflammatory flavonoids, tannins, and tissue-regenerating activity produces measurably faster epithelialization in burns, bruises, abrasions, and surgical wounds. Hypericin photodynamic therapy (PDT) for HSV cold sores and for certain skin cancers is an area of research, and it has been proposed for anogenital human papillomavirus warts. This deep-dive explores the antiviral mechanisms, the traditional and modern topical applications, the nerve-pain indications (trigeminal neuralgia, post-herpetic neuralgia, sciatica), the bacterial-skin-infection applications including methicillin-resistant Staphylococcus aureus, and the home preparation of traditional infused oil.
Table of Contents
- Traditional History — The Wound Oil Predates the Antidepressant
- Hypericin Photodynamic Mechanism Against Enveloped Viruses
- HSV-1 and HSV-2 (Cold Sores, Genital Herpes)
- Human Papillomavirus (Anogenital and Cutaneous Warts) — Topical PDT
- Hypericum Light Therapy for Skin Pre-Cancers and Skin Cancer
- Influenza, Hepatitis, and Other Enveloped Viruses
- Hyperforin Antibacterial — Methicillin-Resistant Staphylococcus Aureus and Skin Pathogens
- Wound-Healing Mechanism (Flavonoids, Tannins, Tissue Regeneration)
- Burns, Bruises, and Minor Abrasions
- Surgical Wound Recovery
- Nerve-Pain Applications (Trigeminal Neuralgia, Post-Herpetic Neuralgia, Sciatica)
- Home Preparation of Traditional Infused Oil
- Topical Cautions and Photosensitivity
- Key Research Papers
- Connections
- Featured Videos
Traditional History — The Wound Oil Predates the Antidepressant
The modern association of Hypericum perforatum with mental health dates only to the late 20th century, but the herb's European medicinal history spans nearly two thousand years — and almost all of that history concerns its topical and wound-care use, not its psychological applications. The first-century Greek physician Dioscorides described hypericum in De Materia Medica as useful for "burns, sciatica, ulcers, and the bites of venomous beasts," recommending the freshly bruised herb applied directly to wounds. Pliny the Elder noted similar uses in his Natural History.
Through the medieval period, hypericum-infused oil (Oleum Hyperici) became a near-universal feature of European household medicine. The Benedictine and Franciscan monasteries cultivated the plant in apothecary gardens and prepared the red oil for treatment of:
- Burns from cooking fires, candles, and household accidents
- Bruises and contusions from manual labor and falls
- Open wounds, abrasions, and lacerations — often after suturing
- Nerve pain along defined anatomic distributions (what we now call neuralgia)
- Sciatica and back pain (massaged into affected areas)
- Skin ulcers and bedsores in immobilized patients
- Insect bites, stings, and the inflammatory reactions thereof
- Hemorrhoids (applied topically)
- Cracked nipples in nursing mothers
By the 17th-19th centuries, hypericum-infused oil was a routine entry in European pharmacopoeias and was carried in the medical kits of military surgeons. The British naval surgeon's manuals listed it for burns from gunpowder accidents and for shrapnel wound aftercare. The traditional knowledge encoded centuries of empirical observation: applied topically, this red oil predictably accelerated healing and reduced pain in a wide range of skin and soft-tissue injuries.
Modern mechanistic research has substantially validated the traditional use. The combination of hypericin (photodynamic antimicrobial and tissue-stimulating effects), hyperforin (anti-inflammatory, antibacterial including methicillin-resistant Staphylococcus aureus, and possibly tissue regenerative), flavonoids (antioxidant and anti-inflammatory), and tannins (astringent and antimicrobial) collectively produces the documented topical effects that European folk medicine had identified empirically over centuries.
Hypericin Photodynamic Mechanism Against Enveloped Viruses
Hypericin is the principal compound responsible for the antiviral activity of St. John's Wort. The mechanism is photodynamic: hypericin acts as a photosensitizer, absorbing visible light (peak absorption in the 540-610 nm green-yellow-orange range) and transferring that energy to molecular oxygen, generating singlet oxygen (a reactive electronically excited form of O2) and other reactive oxygen species (superoxide, hydroxyl radicals, peroxides).
These reactive oxygen species do not differentiate between host cells and pathogens, but the geometry of the photodynamic interaction strongly favors damage to enveloped viral particles because:
- Viral envelope lipids and proteins are particularly susceptible to singlet-oxygen-mediated peroxidation, disrupting the envelope and rendering the virus unable to bind target cells
- Viral genomic nucleic acids, once released from the damaged envelope, are degraded by reactive species
- The viral genome (a few thousand to a few hundred thousand bases) has many fewer redundant copies than a host cell genome, so any damage is much more functionally consequential
- Hypericin preferentially accumulates in the lipid envelope of viral particles due to its lipophilic nature
The result is selective destruction of enveloped viruses while topical host cells — with their robust DNA repair machinery, much larger genome, and antioxidant defenses — experience comparatively limited damage. The pattern is similar to other clinically used photodynamic photosensitizers (porphyrins, phthalocyanines) but with a substantially different photochemistry profile.
Hypericin photodynamic activity has been documented in vitro against a wide range of enveloped viruses including:
- Herpes simplex virus 1 (HSV-1) — oral cold sores
- Herpes simplex virus 2 (HSV-2) — genital herpes
- Varicella zoster virus (VZV) — chickenpox and shingles
- Cytomegalovirus (CMV)
- Epstein-Barr virus (EBV)
- Influenza A and B
- Hepatitis B and C viruses
- Human immunodeficiency virus (HIV)
- Vesicular stomatitis virus
- Murine cytomegalovirus
Non-enveloped viruses (adenovirus, rotavirus, poliovirus, papillomavirus) are generally less susceptible to hypericin photodynamic inactivation, Topical photodynamic therapy with hypericin has been proposed for human papillomavirus warts, through mechanisms beyond direct viral inactivation such as wart-cell killing, but a PubMed search finds no published clinical study of it.
HSV-1 and HSV-2 (Cold Sores, Genital Herpes)
Herpes simplex virus is the textbook example of an enveloped virus susceptible to hypericin photodynamic inactivation. Topical hypericum-infused oil and modern hypericin photodynamic preparations have been investigated for:
- HSV-1 oral cold sores (also called fever blisters or herpes labialis): traditional and modern application of hypericum oil directly to the lesion 3-4 times daily, ideally beginning at the prodromal tingle phase before the vesicle has formed. Anecdotal reports and small clinical observations suggest reduced lesion duration and severity compared to no treatment
- HSV-2 genital herpes lesions: similar topical application with the same caveats. Clinical evidence is more limited than for cold sores due to the practical difficulty of randomized trials in genital herpes
- Recurrent HSV prophylaxis: an interesting hypothesis (not yet well-tested clinically) is that oral hypericum's mood-stabilizing effects might reduce HSV recurrence frequency by reducing stress-mediated immunosuppression, which is a known HSV reactivation trigger. The hypothesis has biological plausibility but lacks rigorous trial evidence
How traditional hypericum oil is used on HSV lesions:
- Traditional sun-cured hypericum oil (deep red color, prepared as described in the home-preparation section below) is applied to the lesion or prodromal site 3-4 times daily
- A cotton swab avoids finger contact with the lesion (HSV is highly transmissible)
- Application continues until the lesion crusts over and resolves (typically 5-10 days for cold sores)
- Treated skin is sensitive to sunburn while the oil is being applied (the same photosensitization that gives the oil its antiviral effect)
- Use stops once the lesion has fully healed; the oil is not used continuously between outbreaks
Modern hypericin photodynamic therapy (PDT) protocols in dermatology research extend the traditional oil application to a more controlled clinical context: a standardized hypericin preparation is applied topically to the lesion, allowed to penetrate for 30-60 minutes, then activated by exposure to a controlled visible light source (typically broad-spectrum visible or specific 590-610 nm wavelength). This produces a more intense and controlled photodynamic effect than ambient-light activation of traditional oil application.
The most established conventional treatments for HSV remain oral antivirals (acyclovir, valacyclovir, famciclovir), which are highly effective and well-tolerated. Hypericum topical use is described as an adjunct, or as an option for people who cannot tolerate or cannot get conventional antiviral therapy; it is not first-line for severe or frequent HSV recurrences. For more on the relevant disease, see our Shingles page (varicella zoster, related to HSV but a distinct virus with its own treatment considerations).
Human Papillomavirus (Anogenital and Cutaneous Warts) — Topical PDT
Human papillomavirus (HPV) is a non-enveloped virus, and direct hypericin photodynamic inactivation of viral particles is less efficient than for enveloped viruses. Hypericin topical PDT has instead been proposed for human papillomavirus-related warts through a different mechanism — selective destruction of the wart cells themselves rather than direct viral inactivation — but no clinical study of it is published. The proposed mechanism: hypericin preferentially accumulates in proliferating wart-cell tissue, photodynamic activation destroys the wart cells, and the immune system clears the resulting cellular debris and any persistent viral particles.
Hypericin PDT and hypericum oil have been proposed or used for:
- Anogenital warts (condylomata acuminata): topical hypericin application followed by light activation has been proposed; no published clinical study reports its clearance rates
- Common cutaneous warts (verruca vulgaris): traditional hypericum oil application has been used in folk medicine for warts on hands, feet, and face. Clinical evidence is mostly anecdotal but the mechanism is biologically plausible
- Plantar warts: similar to common warts, with the practical limitation that the thick plantar skin reduces penetration of topical preparations
- Cervical intraepithelial neoplasia (CIN): hypericin PDT has been proposed for human papillomavirus-associated cervical dysplasia; no clinical study is published, and it is not clinical practice
For routine human papillomavirus wart management, conventional treatments (cryotherapy, imiquimod 5% cream, podophyllotoxin, salicylic acid for common warts, sinecatechins ointment for genital warts) remain the standard of care. Hypericum topical preparations sit outside that standard; their use on warts rests on folk tradition.
Hypericum Light Therapy for Skin Pre-Cancers and Skin Cancer
One small human study has tested St. John's wort light therapy on the skin. In a 2008 pilot study of 34 patients — 8 with actinic keratoses (pre-cancerous skin patches), 21 with basal cell carcinoma and 5 with Bowen's disease (a skin carcinoma in situ) — a St. John's wort extract was applied to the lesions under a covering dressing and lit with red light 2 hours later. The treatment was repeated weekly for 6 weeks on average.
- Complete clinical response was 50% for actinic keratoses, 28% for superficial basal cell carcinoma and 40% for Bowen's disease.
- Nodular basal cell carcinomas only partly responded.
- Under the microscope, tumour cells had completely disappeared in 11% of the superficial basal cell carcinomas and 80% of the Bowen's disease patients.
- All patients complained of burning and pain during the light exposure.
The authors wrote that the results “could be regarded as disappointing,” while listing ways the method might be improved (better lesion preparation, better hypericin delivery and other light procedures).
Influenza, Hepatitis, and Other Enveloped Viruses
The in vitro photodynamic activity of hypericin against influenza, hepatitis B, hepatitis C, and human immunodeficiency virus has been documented in laboratory research but has not translated into established clinical antiviral applications for these systemic infections. The fundamental problem is that effective in vivo systemic antiviral activity would require both adequate hypericin plasma concentrations and adequate light penetration to the tissues where viral replication occurs — and visible light does not penetrate deep tissues effectively. Hypericin photodynamic activity is therefore practically limited to topical and superficial applications where light can reach the infected tissue.
Hypericin has been tested as an antiviral drug in people, with negative results:
- HIV: in two phase I studies (AIDS Clinical Trials Group Protocols 150 and 258), 30 HIV-infected adults received hypericin into a vein (0.25 or 0.5 mg/kg twice weekly, or 0.25 mg/kg three times weekly) or by mouth (0.5 mg/kg daily). 16 of the 30 stopped treatment early because of toxic effects, severe skin phototoxicity occurred in 11 of 23 evaluable patients (48%), and virus markers and CD4 cell counts did not significantly change.
- Hepatitis C: in a phase I study, 12 patients took 0.05 mg/kg and 7 took 0.10 mg/kg of hypericin by mouth once a day for 8 weeks. No patient's hepatitis C virus RNA level changed by more than 1.0 log10, and phototoxic reactions developed in 5 of 12 and 6 of 7 patients at the two doses.
Two niches where hypericin antiviral activity may have practical application:
- Blood-product decontamination: hypericin can be added to blood products (plasma, platelet concentrates, packed red cells) and the product then exposed to light to inactivate any contaminating enveloped viruses (human immunodeficiency virus, hepatitis B and C, cytomegalovirus, Epstein-Barr virus) before transfusion. This is an extracorporeal application where light penetration is achievable and viral inactivation is selective. Hypericin and related compounds have been investigated for this application though current commercial blood-decontamination systems use other photosensitizers (riboflavin, amotosalen)
- Topical influenza/respiratory infections: speculative application of hypericin nasal spray or throat spray for prophylaxis or early treatment of upper respiratory enveloped viruses has been proposed but is not well-tested clinically
For systemic antiviral applications, conventional antivirals (oseltamivir for influenza, direct-acting antivirals for hepatitis C, combination antiretroviral therapy for human immunodeficiency virus) are highly effective and remain the standard of care. Hypericum oral supplementation does not provide meaningful systemic antiviral activity, and may in fact be contraindicated in human immunodeficiency virus due to its cytochrome P450 3A4 (CYP3A4) induction that reduces antiretroviral drug levels by 50% or more.
Hyperforin Antibacterial — Methicillin-Resistant Staphylococcus Aureus and Skin Pathogens
Beyond the hypericin photodynamic antiviral activity, hypericum extracts contain hyperforin, which has demonstrated direct antibacterial activity through a different mechanism: hyperforin disrupts bacterial cell membranes by inserting into the lipid bilayer and dissipating the membrane proton gradient that bacteria require for adenosine triphosphate (ATP) synthesis. The activity is most pronounced against Gram-positive bacteria.
The most clinically interesting finding: hyperforin shows potent activity against methicillin-resistant Staphylococcus aureus (MRSA) in vitro, with minimum inhibitory concentrations in the low-micromolar range and bactericidal (not just bacteriostatic) effect. Schempp et al. (1999) and subsequent investigators have characterized this activity in detail. The mechanism is membrane-disruptive rather than target-protein-binding, which is why methicillin-resistant Staphylococcus aureus resistance (mediated by altered penicillin-binding protein PBP2a that confers beta-lactam resistance) does not confer cross-resistance to hyperforin.
Documented hyperforin antibacterial spectrum includes:
- Staphylococcus aureus, including methicillin-resistant Staphylococcus aureus and vancomycin-intermediate isolates
- Staphylococcus epidermidis (common cause of catheter and prosthesis infections)
- Streptococcus species including group A streptococcus
- Enterococcus species including some vancomycin-resistant isolates
- Corynebacterium species
- Limited activity against Gram-negatives (E. coli, Klebsiella, Pseudomonas typically not inhibited at clinically achievable concentrations)
- Anti-mycobacterial activity against M. tuberculosis documented in vitro at high concentrations
Clinical translation of hyperforin antibacterial activity has focused primarily on topical applications:
- Atopic dermatitis: a cream of hypericum extract standardised to 1.5% hyperforin was tested in one randomized, double-blind half-side trial in 21 patients with mild to moderate atopic dermatitis (18 completed), applied twice daily for four weeks. Eczema severity (a modified SCORAD index) improved significantly more on the hypericum side than on the vehicle side (p < 0.05). S. aureus colonisation fell with both creams, with only a trend in favour of the hypericum cream (p = 0.064)
- Wound infection prevention: traditional hypericum oil application to clean wounds (as part of the broader wound-healing protocol) may contribute antibacterial activity that reduces infection rate, though this is difficult to separate from the oil's other wound-healing mechanisms in clinical studies
- Acne: topical hypericum preparations have been investigated for acne, where the antibacterial activity against Cutibacterium acnes (formerly Propionibacterium acnes) combined with the anti-inflammatory effect could be relevant. Clinical evidence is preliminary
For serious systemic bacterial infection, oral hypericum is not adequate antibacterial therapy and conventional antibiotic treatment is required. The topical hyperforin antibacterial activity is best understood as a complementary mechanism to the oil's broader wound-healing effects rather than a standalone antibacterial treatment.
Wound-Healing Mechanism (Flavonoids, Tannins, Tissue Regeneration)
The wound-healing properties of hypericum-infused oil arise from the combined action of multiple compound classes:
- Flavonoids (quercetin, rutin, hyperoside, isoquercitrin) — provide antioxidant activity that reduces oxidative damage in the wound environment, and anti-inflammatory effects through NF-kB inhibition that limits excessive inflammation that can delay healing
- Tannins — have astringent properties that promote tissue contraction at wound edges and antimicrobial activity that reduces bacterial colonization of the wound surface
- Hyperforin — provides direct antibacterial activity (especially against gram-positive skin flora including S. aureus and methicillin-resistant Staphylococcus aureus as noted above) and possibly direct tissue-regenerative effects through stimulation of keratinocyte and fibroblast proliferation
- Hypericin — provides photodynamic antibacterial and antiviral activity that reduces pathogen burden in the wound, and may directly stimulate angiogenesis and tissue regeneration
- Essential oils and other lipophilic compounds — provide additional anti-inflammatory and antimicrobial activity
- The olive oil carrier — provides occlusive moisturizing effect that maintains wound hydration, supports re-epithelialization, and reduces scarring
The net effect reported for hypericum preparations — with the human trials limited to small studies of ointments after caesarean section and episiotomy (see Surgical Wound Recovery) — is accelerated wound healing characterized by:
- Faster epithelialization (the migration of keratinocytes across the wound surface to form new epidermis)
- Reduced inflammation and edema at the wound margin
- Lower bacterial colonization and infection rates
- Reduced pain at the wound site
- Reduced scar formation, particularly in burns and surgical wounds
- Chronic wounds (pressure ulcers, venous stasis ulcers, diabetic foot ulcers) are a traditional use (skin ulcers and bedsores, listed above); the 2026 review below describes what has been tested
A 2026 structured review of St. John's wort for diabetes-related wounds found nine animal studies and three uncontrolled human reports involving St. John's wort–neem (Azadirachta indica) combination products. Most animal studies were at unclear or high risk of bias, and five of the nine lacked a carrier-matched control, so the plant's contribution could not be separated from the carrier oil's. No randomized human trial has established that St. John's wort alone heals diabetes-related wounds; outside diabetes, the human studies ranged from favourable acute surgical-wound trials to a negative randomized pressure-injury trial. The review concluded that clinical efficacy in diabetes-related wounds “remains unproven.”
Burns, Bruises, and Minor Abrasions
Burns: hypericum oil applied to first-degree (superficial epidermal) and minor second-degree (partial-thickness) burns is a traditional use; the controlled evidence comes from animals. The oil is traditionally applied directly to the burn surface 2-3 times daily after initial cooling and gentle cleansing. Effects reported include:
- Faster re-epithelialization (in a 2024 study of 60 rats, burn wounds treated with H. perforatum were smaller on day 7 and had the best re-epithelialization scores, compared with silver sulfadiazine, another ointment, a gel base and no treatment)
- Reduced pain during the healing process
- Lower infection rate (relevant for partial-thickness burns that have lost the epidermal barrier)
- Reduced scarring
For severe burns (deep partial-thickness, full-thickness, electrical burns, chemical burns, burns of greater than 10% body surface area, or burns of face/hands/genitalia/major joints), hospitals treat these as emergencies, and hypericum oil is not a first-line treatment for them. For minor home-care burns (small kitchen burns, sunburn, friction burns), hypericum oil is a traditional household remedy.
Bruises and contusions: traditional and modern use of hypericum oil for bruises involves topical massage of the oil into intact skin overlying the contusion. The anti-inflammatory and circulatory-stimulating effects help resolve the bruise more rapidly. The combination of hypericum oil with Arnica (another classic herbal bruise remedy) in topical preparations is common in European phytotherapy. Traditional use is 2-3 applications daily until the bruise resolves.
Minor abrasions and shallow lacerations: traditional use is to apply hypericum oil to the wound surface 2-3 times daily until epithelialized, after gentle cleansing with water rather than vigorous scrubbing or hydrogen peroxide (which damages healing tissue). A non-stick dressing keeps out contamination, particularly for wounds in high-friction or contaminated areas.
Sunburn: a notable paradox in topical use. While oral hypericum can cause photosensitivity reactions, topical hypericum oil applied to sunburned skin has soothing effects, reducing redness and pain and promoting healing. The mechanism likely involves the anti-inflammatory flavonoids dominating over any minor photodynamic effect at the local site. Traditional use is 2-3 applications daily after the initial burn has set; applied before further sun exposure, the oil itself, while soothing on already-sunburned skin, would theoretically increase photosensitivity on healthy skin.
Surgical Wound Recovery
Several clinical investigations have examined hypericum preparations for postoperative wound care, with the most rigorous evidence in:
- Cesarean section incisions: A 2010 randomized, double-blind trial (Samadi et al.) of 144 women after cesarean section compared three groups: hypericum ointment 3 times daily for 16 days, a placebo ointment, and no treatment. The hypericum group had significantly better wound healing on the REEDA scale (Redness, Edema, Ecchymosis, Discharge, Approximation) on day 10, less scarring on the Vancouver scar scale on day 40, and lower pain (visual analog scale) and itching on day 40 than both other groups
- Episiotomy wounds: in a triple-blind trial of 98 first-time mothers (84 analysed), hypericum ointment on the episiotomy site twice a day for ten days gave lower pain than a placebo ointment from eight hours onward (mean difference 2.17 at eight hours, 2.20 at five days and 2.21 at ten days; P < 0.001), with no difference before or four hours after use. A double-blind trial of 140 first-time mothers in four groups (hypericum ointment, yarrow (Achillea millefolium) ointment, placebo ointment, no treatment) found less pain, redness, oedema and bruising (ecchymosis) with the hypericum or yarrow ointment, but no difference in discharge or wound separation (dehiscence). Neither trial measured scarring
- Hemorrhoidectomy wounds: hypericum oil is used traditionally for hemorrhoids (listed above) and has been applied for postoperative hemorrhoidectomy pain and healing; a PubMed search finds no clinical study of it
- Mastectomy and breast reconstruction wounds: limited data but some clinical use exists in European surgical practice
Practical points described for surgical wound use:
- Application begins only after the initial wound has been sealed and any sutures are dry (typically 24-48 hours postoperatively for clean surgical wounds; longer if there is concern for wound dehiscence)
- A clean cotton-tipped applicator, rather than fingers, maintains sterility
- The oil is applied 2-3 times daily until the wound is fully healed
- Increased redness, warmth, drainage and fever are signs of wound infection, which is treated medically
- The topical use is for the skin surface only, not internal surgical sites
- Some surgical teams have preferences about topical applications during the early postoperative period
Nerve-Pain Applications (Trigeminal Neuralgia, Post-Herpetic Neuralgia, Sciatica)
Traditional herbalists classify St. John's Wort as a nervine — an herb that nourishes and restores the nervous system — and have used both topical and oral preparations for various nerve-pain conditions for centuries. Modern research suggests hypericin and hyperforin do have analgesic and neuroprotective effects, though the strength of clinical evidence varies by condition.
Trigeminal neuralgia: severe lancinating facial pain along the trigeminal nerve distribution. Conventional first-line treatment is carbamazepine (an anticonvulsant), with surgical decompression for refractory cases. Topical hypericum oil massaged along the affected facial nerve distribution has been used adjunctively in European phytotherapy, with anecdotal reports of pain reduction. Rigorous trial evidence is limited.
Post-herpetic neuralgia (PHN): persistent nerve pain after a shingles outbreak (varicella zoster reactivation). Topical hypericum oil application along the affected dermatome has been used both for acute shingles lesions and for the resulting post-herpetic neuralgia. The combination of antiviral activity (during the acute outbreak) and anti-inflammatory/analgesic activity (for both acute pain and PHN) is biologically appealing. Conventional first-line treatments for PHN include topical lidocaine, capsaicin, gabapentin/pregabalin, and tricyclic antidepressants. See our Shingles page for more on this condition.
Sciatica and back pain: massaging hypericum oil into the lumbar region and along the sciatic distribution down the affected leg has been a traditional European remedy for sciatic pain. The combination of anti-inflammatory effect (reducing nerve root inflammation), analgesic effect (modulating nociceptive signaling), and muscular relaxant effect from the massage itself may contribute to reported benefit. Not a substitute for evaluation of underlying causes (disc herniation, spinal stenosis, etc.).
Diabetic peripheral neuropathy: small studies and case reports of topical hypericum for the burning, tingling, and pain of diabetic peripheral neuropathy in feet and hands. Traditional use is 2-3 applications daily, with massage to enhance penetration, and it is also used alongside conventional treatments (alpha-lipoic acid, acetyl-L-carnitine, gabapentin/pregabalin or duloxetine).
Intercostal neuralgia: nerve pain along an intercostal nerve distribution, often from rib injury, surgical scar, or shingles reactivation in a thoracic dermatome. Topical hypericum oil application along the painful nerve distribution has been documented in European phytotherapy.
Oral hypericum for neuropathic pain: hyperforin's effects on serotonin and norepinephrine reuptake parallel the mechanism of duloxetine, a serotonin-norepinephrine reuptake inhibitor with established efficacy for diabetic peripheral neuropathy and fibromyalgia. Theoretically, oral hypericum could produce similar analgesic effects, though dedicated trials in neuropathic pain are limited. The drug-interaction profile of oral hypericum (see Critical Drug Interactions deep-dive) often precludes its use in patients on conventional pain medications, gabapentin, pregabalin, or tricyclics.
Home Preparation of Traditional Infused Oil
The traditional Oleum Hyperici can be prepared at home from fresh hypericum flowers if you have access to a clean source (cultivated in your garden or wildcrafted from an unpolluted area). The classic recipe:
- Harvest: collect fresh hypericum flower buds and just-opened flowers around the summer solstice (late June to mid-July in the northern hemisphere, when bloom is at peak). Pick flowers in mid-morning after dew has dried but before peak afternoon sun. Aim for approximately 1 cup of fresh flower material per pint of finished oil
- Prepare: gently rinse the flowers to remove any insects or debris, then spread on a clean cloth to dry for 1-2 hours (not completely — the flowers are meant to be wilted but still containing their volatile oils)
- Crush lightly: gently crush the flowers in a mortar or with the back of a spoon to release the oil glands. The flowers should release a small amount of red juice when crushed — this is the hypericin
- Infuse: place the crushed flowers in a clean glass jar (mason jar or similar) and cover with cold-pressed extra-virgin olive oil to about 1 inch above the plant material. Stir gently to release any trapped air bubbles. Cover with cheesecloth or a clean paper towel secured with a rubber band (not a tight lid — you need some air exchange for the photodynamic processes to occur)
- Sun-cure: place the jar in a warm, sunny location (a south-facing windowsill in the northern hemisphere works well) for 4 to 6 weeks. The oil will gradually develop the characteristic deep red color as hypericin is extracted into the oil and undergoes photoactivation. Stir or invert the jar every few days to redistribute the flowers
- Strain and bottle: after 4-6 weeks, strain the oil through fine cheesecloth or a coffee filter into clean amber glass bottles (the amber glass protects the finished oil from continued light exposure, which would otherwise degrade the active compounds). Squeeze the spent flowers thoroughly to extract all infused oil. Store in a cool, dark place
- Shelf life: properly prepared and stored, the oil keeps for 1-2 years. Discard if it develops a rancid smell, mold, or off color
The finished oil should be a deep, clear crimson-red color — a properly cured oil is dramatically darker than commercial preparations that have not been sun-cured. The intense color is the visible signature of high hypericin content.
Commercial hypericum oils are also sold. They differ in whether they are sun-cured or heat-extracted, in color, and in packaging (amber glass protects the finished oil from light, as noted above).
Topical Cautions and Photosensitivity
Topical hypericum is generally well-tolerated, but several cautions apply:
- Photosensitivity: skin to which hypericum oil has been applied may be more sensitive to sun-induced burning. Evening application, application to skin that will not be sun-exposed in the next 24 hours, and sunscreen on treated areas lower this risk, which matters most for fair-skinned individuals
- Allergic contact dermatitis: rare but reported reactions to topical hypericum. Redness, itching or rash at the application site are its signs
- Open wound concerns: while hypericum oil is appropriate for clean superficial wounds, it is not a treatment for deep puncture wounds (puncture wounds need to drain and remain open for infection clearance), severe burns (which hospitals treat as emergencies), bites from animals (which need antimicrobial coverage and possibly rabies prophylaxis), or any wound with signs of infection (increasing redness, drainage, fever)
- Eye contact: the oil can irritate the eyes, and hypericin may be a retinal photosensitizer at high concentrations
- Pregnancy and breastfeeding: topical application to localized small areas is unlikely to produce systemic exposure of concern, but large-area application or chronic use in pregnancy and breastfeeding falls under the general caution that applies to hypericum in those periods
- Drug interactions from topical use: topical hypericum application produces minimal systemic absorption and does not generally produce the cytochrome P450 3A4 induction associated with oral hypericum. However, large-area applications or chronic use over many weeks could theoretically produce some systemic effect. The drug-interaction concerns for oral hypericum do not typically apply to occasional topical use of small amounts of oil
Key Research Papers
- Schempp CM, Pelz K, Wittmer A, Schöpf E, Simon JC (1999). Antibacterial activity of hyperforin from St John's wort, against multiresistant Staphylococcus aureus and gram-positive bacteria. The Lancet, 353(9170):2129. The seminal hyperforin/MRSA paper. — PubMed PMID: 10382704
- Meruelo D, Lavie G, Lavie D (1988). Therapeutic agents with dramatic antiretroviral activity and little toxicity at effective doses: aromatic polycyclic diones hypericin and pseudohypericin. PNAS, 85(14):5230-4. The original hypericin antiviral discovery paper. — PubMed PMID: 2839837
- Lavie G et al. (1989). Studies of the mechanisms of action of the antiretroviral agents hypericin and pseudohypericin. PNAS, 86(15):5963-7. Hypericin antiviral mechanism elucidation. — PubMed PMID: 2548193
- Wood S, Huffman J, Weber N, Andersen D, North J, Murray B, Sidwell R, Hughes B (1990). Antiviral activity of naturally occurring anthraquinones and anthraquinone derivatives. Planta Medica, 56(6):651-2. Hypericin antiviral spectrum. — doi:10.1055/s-2006-961304
- Samadi S, Khadivzadeh T, Emami A, Moosavi NS, Tafaghodi M, Behnam HR (2010). The effect of Hypericum perforatum on the wound healing and scar of cesarean. Journal of Alternative and Complementary Medicine, 16(1):113-7. Postoperative cesarean wound trial: 144 women, three arms (hypericum ointment, placebo ointment, no treatment). — PubMed PMID: 20064022
- Reichling J, Weseler A, Saller R (2001). A current review of the antimicrobial activity of Hypericum perforatum L. Pharmacopsychiatry, 34 Suppl 1:S116-8. Antimicrobial activity review. — PubMed PMID: 11518059
- Schempp CM, Windeck T, Hezel S, Simon JC (2003). Topical treatment of atopic dermatitis with St. John's wort cream — a randomized, placebo controlled, double blind half-side comparison. Phytomedicine, 10 Suppl 4:31-7. Atopic dermatitis topical trial. — PubMed PMID: 12807340
- Süntar IP, Akkol EK, Yilmazer D, Baykal T, Kirmizibekmez H, Alper M, Yeşilada E (2010). Investigations on the in vivo wound healing potential of Hypericum perforatum L. Journal of Ethnopharmacology, 127(2):468-77. Animal wound models; hyperoside, isoquercitrin, rutin, (-)-epicatechin and hypericins identified as the active components. — PubMed PMID: 19833187
- Birt DF, Widrlechner MP, Hammer KD, Hillwig ML, Wei J, Kraus GA, Murphy PA, McCoy JA, Wurtele ES, Neighbors JD, Wiemer DF, Maury WJ, Price JP (2009). Hypericum in infection: identification of anti-viral and anti-inflammatory constituents. Pharmaceutical Biology, 47(8):774-782. Comprehensive antiviral/anti-inflammatory review. — PubMed PMID: 19907671
- Saddiqe Z, Naeem I, Maimoona A (2010). A review of the antibacterial activity of Hypericum perforatum L. Journal of Ethnopharmacology, 131(3):511-21. Antibacterial review. — PubMed PMID: 20659547
- Kacerovská D, Pizinger K, Majer F, Smíd F (2008). Photodynamic therapy of nonmelanoma skin cancer with topical hypericum perforatum extract — a pilot study. Photochemistry and Photobiology, 84(3):779-85. Hypericum PDT for skin cancer pilot: 34 patients. — PubMed PMID: 18179625
- Derbentseva NA, Mishenkova EL, Garagulia OD (1972). [Action of tannins from Hypericum perforatum L. on the influenza virus]. Mikrobiol Zh, 34(6):768-72. Early Soviet hypericum antiviral research. — PubMed PMID: 4667029
- Gulick RM, McAuliffe V, Holden-Wiltse J, Crumpacker C, Liebes L, Stein DS, Meehan P, Hussey S, Forcht J, Valentine FT (1999). Phase I studies of hypericin, the active compound in St. John's Wort, as an antiretroviral agent in HIV-infected adults. AIDS Clinical Trials Group Protocols 150 and 258. Annals of Internal Medicine, 130(6):510-4. 30 patients; 16 stopped early for toxic effects; no antiretroviral activity. — PubMed PMID: 10075619
- Jacobson JM, Feinman L, Liebes L, Ostrow N, Koslowski V, Tobia A, Cabana BE, Lee D, Spritzler J, Prince AM (2001). Pharmacokinetics, safety, and antiviral effects of hypericin, a derivative of St. John's wort plant, in patients with chronic hepatitis C virus infection. Antimicrobial Agents and Chemotherapy, 45(2):517-24. Phototoxicity and no detectable anti-HCV activity. — PubMed PMID: 11158749
- Vakili F, Mirmohammadaliei M, Montazeri A, Farokhi M, Minaee MB (2018). Impact of Hypericum Perforatum Ointment on Perineal Pain Intensity Following Episiotomy: a Randomized Placebo-Controlled Trial. Journal of Caring Sciences, 7(4):205-211. 98 women, ointment twice daily for ten days. — PubMed PMID: 30607361
- Hajhashemi M, Ghanbari Z, Movahedi M, Rafieian M, Keivani A, Haghollahi F (2018). The effect of Achillea millefolium and Hypericum perforatum ointments on episiotomy wound healing in primiparous women. Journal of Maternal-Fetal & Neonatal Medicine, 31(1):63-69. 140 women, four groups. — PubMed PMID: 28027682
- Hejazi Niyaki SA, Bayat Y (2026). Hypericum perforatum for diabetes-related wounds: A structured critical review of evidence and translational barriers. Journal of Tissue Viability, 36(1):101083. Nine animal studies and three uncontrolled human reports; clinical efficacy unproven. — PubMed PMID: 42994168
- Hamedi ZS, Manafi A, Hashemi SS, Mehrabani D, Seddighi A, Tanideh N, Mokhtari M (2024). Healing Effect of Hypericum perforatum in Burn Injuries. World Journal of Plastic Surgery, 13(3):57-65. Burn model in 60 rats. — PubMed PMID: 39665012
PubMed Topic Searches
Connections
- All Herbs
- St. John's Wort Benefits Hub
- St. John's Wort Overview
- St. John's Wort for Depression
- Mood & Seasonal Depression
- Critical Drug Interactions
- Shingles (HSV/VZV)
- Chronic Pain
- Arnica (Bruise Synergy)
- Calendula
- Comfrey
- Aloe Vera
- Topical Wound Care
- Methicillin-Resistant Staphylococcus Aureus
- Staphylococcus aureus
- History